This review examines associations between ultra-processed food (UPF) consumption and inflammatory bowel disease (IBD), highlighting proposed mechanisms involving gut microbiota alterations, epithelial barrier dysfunction, and immune activation. The role of dietary advanced glycation end products in autophagy remains uncertain. Current guidelines support limiting UPF intake and individualized nutritional care.
مقالة مراجعة
Epidemiological Evidence, Underlying Mechanisms, and Public Health Implications of Ultra-Processed Food Consumption in Inflammatory Bowel Disease
في هذه المقالة
ملخص
الملخص
The overall aim of this narrative review is to synthesize epidemiological evidence linking ultra-processed food (UPF) consumption to the onset and progression of inflammatory bowel disease (IBD), examine the proposed pathophysiological mechanisms, and evaluate contemporary clinical nutritional strategies. Epidemiological data demonstrates a robust, dose-response association between high UPF intake and an increased risk of incident IBD, predominantly Crohn’s disease (CD). Furthermore, in diagnosed patients, UPF consumption correlates with elevated clinical activity, inflammatory relapses, and adverse clinical outcomes. Experimental and observational findings suggest four potential pathways linking UPF-related exposures to altered gut immune homeostasis. First, UPF-rich dietary patterns may be associated with microbiota dysbiosis and reduced short-chain fatty acid (SCFA) availability. Second, experimental studies suggest that selected emulsifiers can alter intestinal mucus organization and epithelial tight-junction integrity. Third, increased intestinal permeability may facilitate exposure to luminal bacterial products and downstream inflammatory signaling through Toll-like receptor 4 (TLR4) and nuclear factor-kappa B (NF-κB). Fourth, advanced glycation end products (AGEs) may contribute to intestinal inflammatory signaling and epithelial stress, although their proposed effects on energy sensing and autophagy in IBD require further validation. Current clinical guidance supports healthy dietary patterns with limited UPF intake and individualized nutritional care, while evidence that UPF restriction alone reduces IBD flares remains insufficient. The review concludes that mitigating the clinical burden of IBD requires integrating personalized nutritional interventions managed by specialized dietitians, while highlighting the necessity for further research into specific food additives and precision nutrition strategies.
المقدمة
Inflammatory bowel disease (IBD), encompassing Crohn’s disease (CD) and ulcerative colitis (UC), represents a group of chronic, relapsing-remitting inflammatory conditions of the gastrointestinal tract that profoundly impact millions worldwide. The global incidence and prevalence of IBD have been escalating dramatically, particularly in newly industrialized countries, mirroring the epidemiological patterns described by Kaplan and Windsor1 in four stages: emergence, incidence acceleration, prevalence compounding, and prevalence equilibrium. While historically more prevalent in Western nations, the disease burden is increasingly observed in Asia, Africa, and South America, underscoring a shift that cannot be solely attributed to genetic factors and strongly implicates environmental influences, including dietary patterns2,3. A significant aspect of this Westernized dietary shift is the substantial and growing consumption of ultra-processed foods (UPFs), defined by the NOVA classification system as foods characterized by their industrial nature and the presence of cosmetic additives rather than nutritional content4,5,6. These foods are typically high in unhealthy fats, refined sugars, and sodium, while often being deficient in fiber and essential micronutrients, and containing numerous food additives not commonly used in home cooking4,5,6.
The concurrent rise in IBD incidence and UPF consumption has prompted investigations into whether UPF intake may represent one of several dietary factors associated with IBD onset and disease activity. This narrative review aims to synthesize current epidemiological evidence linking UPF consumption to IBD onset and disease activity, critically examine proposed molecular and pathophysiological mechanisms, and discuss the public health implications and evolving dietary management strategies for patients with IBD. By critically evaluating large-scale prospective cohort studies and empirical mechanistic investigations, this review seeks to provide a nuanced understanding of the multifaceted relationship between UPFs and IBD, informing both clinical practice and public health policy.
مراجعة ومنظور
Literature search and review approach
This article was prepared as a narrative review rather than a systematic review. Relevant literature was identified through targeted searches of PubMed/MEDLINE, supplemented by examination of reference lists from pertinent publications and professional society guidelines. Search terms included combinations of "ultra-processed foods", "NOVA classification", "inflammatory bowel disease", "Crohn’s disease", and "ulcerative colitis", with additional topic-specific terms such as "food additives", "emulsifiers", "gut microbiota", "intestinal barrier", "NLRP3", "advanced glycation end products", and "dietary therapy". Publications were considered if they addressed UPF-related epidemiology, experimental mechanisms relevant to intestinal inflammation, or dietary management in IBD. Original human studies, experimental investigations, evidence syntheses, and clinical guidelines were prioritized, while conference abstracts were selectively included to describe emerging findings. Duplicate reports and publications outside these thematic areas were excluded. Titles, abstracts, and available full texts were examined for relevance and interpretability, and findings were synthesized thematically. No exhaustive systematic search, quantitative meta-analysis, or formal study-level risk-of-bias assessment was undertaken.
Epidemiological evidence: association between UPF consumption and risk of IBD onset
The incidence of IBD, particularly CD, has significantly increased globally, coinciding with the widespread adoption of Western dietary patterns characterized by high UPF consumption1,2,3. Defined by the NOVA classification, UPFs are formulations of food substances often containing little or no whole foods and laden with additives7. Accumulating evidence from large perspective cohorts indicates an association between higher UPF intake and incident IBD, although a causal relationship has not been established.
A pivotal prospective study spanning 21 countries involving 116,087 adults revealed a dose-response relationship between UPF intake and incident IBD. Compared with those consuming less than one serving daily, individuals consuming five or more servings had a higher risk of incident IBD (Hazard ratio [HR] = 1.82, 95% CI: 1.22–2.72)7. Notably, higher consumption of specific categories, including soft drinks, salty snacks, and processed meats, was associated with increased IBD risk estimates, whereas no corresponding association was observed for unprocessed foods. Another massive cohort of 245,112 participants corroborated these findings, reporting a significantly higher CD risk (HR = 1.70, 95% CI: 1.23–2.35) associated with high UPF intake, particularly ultra-processed breads, ready-to-eat meals, and sauces8. Interestingly, this study, like others, found a less consistent link between UPFs and ulcerative colitis (UC), suggesting divergent etiological pathways.
A meta-analysis encompassing over one million individuals reported a similar association between higher UPF consumption and increased CD risk (HR = 1.71, 95% CI: 1.37–2.14), as well as an inverse association between unprocessed food intake and CD risk (HR = 0.71, 95% CI: 0.53–0.94)9. The inflammatory potential of UPFs extends beyond IBD, with large cohorts linking increased UPF intake to other systemic inflammatory conditions such as irritable bowel syndrome (IBS)10 and rheumatoid arthritis (RA)11.
While large adult cohorts dominate the evidence base, pediatric studies also point towards UPF involvement. A case-control study found higher UPF intake in children with UC than in healthy controls, although disease activity did not correlate with intake12. Furthermore, overall dietary inflammatory potential strongly correlates with CD risk13, and early-life high-quality diets appear protective against IBD14. Ongoing research, such as the D-ECCO Grant study using the Danish National Birth Cohort, is exploring how maternal and early-life UPF exposure influences offspring IBD risk15.
In summary, robust epidemiological evidence consistently demonstrates a significant association between high UPF consumption and an increased risk of developing IBD, predominantly CD. While causation remains difficult to definitively prove in observational studies, the strength, consistency, and dose-response nature of these associations underscore the critical need for further mechanistic investigations. The principal epidemiological studies and their findings are summarized in Table 1.
Table 1: Summary of Core Epidemiological Evidence Linking UPF Consumption to IBD Risk and Progression. Abbreviations: HR = hazard ratio; OR = odds ratio; CI = confidence interval; CD = Crohn’s disease; UC = ulcerative colitis; IBD = inflammatory bowel disease; UPF = ultra-processed food; FFQ = food frequency questionnaire; PFQ = processed food questionnaire; NOVA = food classification system based on extent and purpose of processing; PURE = Prospective Urban Rural Epidemiology; NHS = Nurses’ Health Study; NHS II = Nurses’ Health Study II; HPFS = Health Professionals Follow-up Study. Note: The fully adjusted analysis by Sarbagili-Shabat et al. included 231 patients. The findings of Lasfar et al. have been reported only as a conference abstract, limiting detailed methodological appraisal. The meta-analysis synthesizes previously published cohort evidence and should not be treated as an additional independent cohort. Cross-sectional findings cannot establish temporal direction; none of these observational estimates alone establish causality. Please click here to download this Table.
Disease activity and relapse: associations with UPF consumption in diagnosed patients
Among patients with established IBD, observational studies have examined associations between UPF consumption, disease activity, and relapse. Whether reducing UPF intake independently improves clinical outcomes remains uncertain.
Several studies have examined associations between UPF intake and IBD activity. An analysis of 135 participants from the Manitoba Living with IBD cohort investigated the association between UPF consumption and disease activity16. Among UC participants, higher UPF consumption strongly correlated with increased active disease and inflammation. Patients in the highest UPF tertile experienced significantly more active disease and inflammatory episodes than those with low intake. Interestingly, no significant differences were observed among CD participants in this study, suggesting that associations between UPF intake and disease activity may differ by IBD subtype16.
Supporting this link, a cross-sectional study found that higher UPF consumption was positively associated with active disease in IBD patients (OR = 3.82, 95% CI: 1.49 to 9.80)17. The strongest association was observed with ultra-processed meats (OR = 4.45, 95% CI: 2.07 to 9.79), while higher consumption of unprocessed foods was associated with lower odds of active disease17. A prospective observational study of 160 IBD patients assessed dietary intake using a validated food frequency questionnaire and calculated an anti-/pro-inflammatory dietary score18. Higher UPF consumption was associated with increased clinical disease activity (OR = 2.18, 95% CI: 1.22–3.89) and elevated fecal calprotectin levels. Among patients with colonic CD, higher refined sugar intake was associated with a greater proportion of patients having a Harvey–Bradshaw Index (HBI) score >5 (70% vs. 33%), whereas dietary patterns rich in fiber, fruits, vegetables, and omega-3 fatty acids were associated with fewer flares over 12 months (OR = 0.54, 95% CI: 0.31–0.93)18.
Nutritional adequacy is another important consideration when evaluating dietary patterns and clinical outcomes in IBD. Malnutrition is highly prevalent in IBD patients, increasing the risk of infections and poor prognosis19,20,21. A study examining 195 CD outpatients in remission found that UPFs contributed significantly to their macro- and micronutrient intake (mean NOVA 4 score of 39.8)22. While noting no direct association between UPF intake and nutrient inadequacy, the authors highlighted that blindly avoiding UPFs without targeted nutritional counseling could inadvertently lead to other dietary deficiencies22.
Beyond mucosal inflammation, two conference abstracts reported associations between UPF intake and body-composition outcomes in IBD. A cross-sectional analysis found that higher UPF intake was associated with pre-sarcopenia in patients in remission (OR = 3.40, 95% CI: 1.06–10.9; p = 0.039)23, while another report described an association with lower fat-free mass in CD24. These preliminary findings require confirmation in full-length studies.
Regarding specific formulation components, dietary emulsifiers found in UPFs have been investigated as potential contributors to intestinal inflammation. A conference abstract reported greater intake of selected emulsifiers, including carrageenan and guar gum, among patients with UC or CD than among healthy controls25. Another conference abstract described increased expression of TNF, IL8, and IL1B following κ-carrageenan exposure in colonic organoid-derived monolayers from patients with CD26. These findings suggest potential associations and experimental inflammatory effects but do not establish that emulsifier exposure causes disease exacerbation in patients.
In summary, observational studies suggest associations between higher UPF intake and disease activity in some IBD populations. However, potential reverse causation, residual confounding, and limited direct intervention evidence preclude conclusions that UPF consumption independently drives disease relapse or progression.
Proposed mechanisms linking UPF-related exposures to altered gut immune homeostasis
Gut microbiota dysbiosis and abnormal SCFA metabolism
Experimental and observational studies implicate changes in microbiota composition, intestinal barrier integrity, innate immune signaling, and cellular metabolism as potential pathways linking UPF-related exposures to intestinal inflammation. Evidence supporting these pathways comes from experimental models and observational studies, with varying degrees of mechanistic certainty.
UPF-rich dietary patterns are often relatively low in fiber and high in refined sugars and fats, characteristics that may influence gut microbial composition27,28. Observational and experimental studies have linked UPF-related exposures to changes in microbial diversity and the abundance of SCFA-producing taxa, including Faecalibacterium prausnitzii and Roseburia29,30,31. Concurrently, inflammatory microbial profiles emerge29,30. In a multicenter cohort of 313 IBD patients, elevated UPF consumption correlated with an inflammatory microbiota shift; active IBD patients in higher UPF quartiles exhibited increased Enterobacteriaceae, whereas remission patients in lower UPF quartiles maintained higher levels of Lachnospiraceae, Faecalibacterium, and Bifidobacterium30.
Such microbiota alterations may affect SCFA production and metabolism. SCFA fuels colonocytes, reinforces the intestinal barrier, and modulates mucosal immune responses32,33. UPF-associated fiber deficiency reduces SCFA production, compromising these protective functions29,34. In a short-term controlled feeding study involving healthy adults, carboxymethylcellulose (CMC) exposure altered the fecal metabolome, including reductions in SCFAs and free amino acids34. Parallel murine studies revealed UPF-rich diets induce dysbiosis and metabolic alterations35. These UPF-associated metabolic shifts correlate positively with inflammatory markers such as C-reactive protein (CRP) and coincide with the depletion of anti-inflammatory lipid mediators, including omega-3 fatty acids and docosahexaenoic acid36,37.
Alterations in microbial cross-feeding networks may represent another mechanism relevant to intestinal inflammation. Commensal taxa like Blautia sustain colonic mucus integrity during low-fiber intake by secreting SCFA that activate the Ffar2 receptor33. Depletion of such bacteria functionally compromises epithelial defense. Similarly, Bacteroides uniformis typically promotes Lactobacillus johnsonii, elevating indole-3-lactic acid to alleviate colitis38. IBD patients consistently exhibit disruptions in these synergistic microbial interactions alongside reduced SCFA-producing populations39,40.
Artificial sweeteners and emulsifiers have been associated with changes in gut microbial composition and metabolic output41,42. Analyses of commercial UPF products identified several additives of potential concern, including potassium sorbate, mono- and diglycerides, sucralose, CMC, and carrageenan43.
Effects of surfactant additives on intestinal mucus and epithelial tight-junction integrity
The mucus layer and epithelial tight junctions restrict luminal antigen exposure, and their disruption contributes to intestinal inflammation in IBD44, 45.
Experimental studies suggest that dietary emulsifiers, including polysorbate 80 (P80) and CMC, may alter mucus organization and intestinal barrier function. In a short-term controlled feeding study involving healthy adults, CMC exposure reduced microbial diversity, with increased mucus-layer microbiota encroachment observed in a subset of participants34. Murine models corroborate these findings, revealing CMC and P80 impair barrier function and promote chronic inflammation46. In colitis-susceptible IL-10-/- mice and wild-type hosts colonized with adherent-invasive Escherichia coli (AIEC), emulsifier exposure upregulated AIEC virulence genes and exacerbated mucosal inflammation46.
Experimental studies have also investigated the potential effects of carrageenan on intestinal barrier function. Animal studies indicate degraded carrageenan triggers intestinal ulceration and increases permeability47. In colonic organoid-derived monolayers from CD patients, κ-carrageenan upregulated pro-inflammatory cytokines, including TNF, IL8, and IL1B, thereby sensitizing epithelial cells and perpetuating inflammation26. Review and ingredient-composition studies raise concerns about possible effects of selected food additives on intestinal barrier function, although the strength and directness of evidence vary28, 29, 41, 48, 49. Conversely, galactooligosaccharides combined with Limosilactobacillus reuteri improved tight-junction integrity through microbiota-derived pentadecanoic acid in a murine colitis model50.
Transepithelial endotoxin translocation and activation of the mucosal immune cascade
With increased intestinal permeability, luminal lipopolysaccharide (LPS) may reach the lamina propria and engage the TLR4 receptor complex on immune cells28, 44, 45. Downstream NF-κB signaling promotes the expression of inflammatory mediators, including TNF-α, IL-1β, IL-6, and IL-827, 48, 51.
LPS-TLR4 signaling can prime NLRP3 inflammasome responses, whereas subsequent inflammasome activation promotes the maturation of IL-1β and IL-1848. Emulsifier-associated increases in intestinal permeability may enhance exposure to microbial products, although evidence linking this process to NLRP3 activation in human IBD remains indirect51, 52. Murine models further demonstrate that UPF exposure elevates systemic inflammatory markers, including IL-6 and TNF-α35.
Microbiota-innate immune interactions may further modulate mucosal inflammatory responses53. Observational studies associate higher UPF consumption with circulating inflammatory markers, including hs-CRP, IL-6, and TNF-α, although adiposity may partly mediate these associations54, 55.
Translocated lipopolysaccharide (LPS) acts as a bacterial pathogen-associated molecular pattern (PAMP), rather than a host-derived damage-associated molecular pattern (DAMP), and may amplify mucosal innate immune signaling through TLR456.
Dietary AGEs, intestinal inflammatory signaling, and proposed links to epithelial autophagy
Advanced glycation end products (AGEs) can form during high-temperature food processing, including the production of some ultra-processed foods (UPFs), and may also arise endogenously27, 57. AGE–RAGE signaling has been implicated in oxidative stress and inflammatory responses. However, direct evidence that dietary UPF-derived AGEs activate this pathway in the intestinal tissues of patients with inflammatory bowel disease (IBD) remains limited48, 58.
Autophagy is essential for intestinal epithelial homeostasis, including the removal of damaged cellular components and adaptation to cellular stress48. Although AGE-related oxidative stress has been proposed to interfere with autophagic processes, whether dietary UPF-derived AGEs directly impair epithelial autophagy in IBD has not been established.
The AMP-activated protein kinase (AMPK) and mammalian target of rapamycin (mTOR) pathways regulate cellular energy sensing and autophagy48, 57. Nutrient-related metabolic stress may influence these pathways, but evidence linking dietary UPF-derived AGEs specifically to AMPK/mTOR dysregulation in the inflamed intestinal epithelium remains indirect.
Endoplasmic reticulum (ER) stress and NLRP3 inflammasome signaling are involved in intestinal inflammatory responses48. Interactions among oxidative stress, ER stress, and autophagy provide a plausible mechanistic framework, although a direct causal pathway from dietary AGE exposure to inflammasome activation through impaired epithelial autophagy has not been demonstrated in patients with IBD.
IBD-specific clinical evidence concerning dietary AGEs remains primarily observational. A prospective cohort study involving 121,978 participants found that higher estimated intake of Nε-(1-carboxyethyl)-lysine (CEL), a specific dietary AGE, was associated with a modestly increased risk of incident IBD, particularly Crohn’s disease, whereas no significant association was observed for ulcerative colitis59. These findings support further investigation of dietary AGEs in IBD but do not establish AGE-induced impairment of epithelial autophagy or AMPK/mTOR signaling.
Overall, AGE-associated inflammatory signaling and epithelial stress responses represent plausible pathways contributing to intestinal inflammation. Nevertheless, direct mechanistic evidence linking UPF-derived dietary AGEs to impaired epithelial energy sensing and autophagy in human IBD remains insufficient. The proposed mechanisms linking UPF consumption to intestinal inflammation are illustrated in Figure 1. The potential effects of specific UPF components on intestinal immune homeostasis are summarized in Table 2.
Table 2: Proposed Molecular Mechanisms Linking Specific UPF Components to Altered Intestinal Immune Homeostasis. Abbreviations: UPF = Ultra-processed Food; CMC = Carboxymethylcellulose; P80 = Polysorbate 80; SCFA = Short-Chain Fatty Acids; AIEC = Adherent-Invasive Escherichia coli; TLR4 = Toll-like Receptor 4; NF-κB = Nuclear Factor-kappa B; CD = Crohn's Disease; RAGE = Receptor for Advanced Glycation End Products; AMPK = AMP-activated Protein Kinase; mTOR = Mammalian Target of Rapamycin; ER = Endoplasmic Reticulum. Please click here to download this Table.
Clinical nutritional intervention strategies and latest guideline recommendations
Given the growing epidemiological and mechanistic evidence linking UPF consumption with IBD, dietary guidance has become increasingly relevant to comprehensive disease management. Current recommendations distinguish general healthy eating advice from specific nutritional therapies, whose roles depend on disease phenotype, clinical status, and treatment goals.
The 2024 Clinical Practice Update from the American Gastroenterological Association (AGA) recommends a Mediterranean-style dietary pattern low in ultra-processed foods, added sugars, and salt for the overall health and well-being of patients with IBD, while acknowledging that no diet has consistently been shown to reduce flare rates in adults60. The 2025 European Crohn’s and Colitis Organisation (ECCO) consensus similarly recommends limiting UPF intake in accordance with healthy eating patterns, noting its association with incident Crohn’s disease but not ulcerative colitis61. However, the ECCO consensus does not recommend complete avoidance of UPFs and emphasizes maintaining nutritional adequacy. Both documents support individualized dietary guidance, with ECCO specifically recommending access to dietitians experienced in IBD care60, 61.
The 2023 European Society for Clinical Nutrition and Metabolism (ESPEN) guideline on clinical nutrition in IBD provides recommendations on nutritional assessment, dietary counseling, and nutritional support during active disease and remission62. Rather than specifically advocating UPF avoidance, these recommendations emphasize identifying and managing nutritional deficiencies and providing individualized nutritional care according to patients’ clinical needs.
Clinical studies have explored the potential benefits of dietary modification in IBD, although the certainty of evidence varies. In a 1-year prospective, non-randomized study involving 168 IBD patients in clinical remission, participants selected either an anti-inflammatory diet or a regular diet according to personal preference. Clinical remission was maintained in 95.2% of the anti-inflammatory diet group and 85.7% of the regular diet group (p = 0.036)63. Fecal calprotectin levels were lower in the anti-inflammatory diet group at follow-up, but the between-group difference was not statistically significant63. Given the preference-based allocation, these findings suggest a potential association between dietary modification and remission maintenance rather than establishing a causal treatment effect. Similarly, Mediterranean-style dietary patterns have been associated with potential improvements in dietary quality, gastrointestinal symptoms, and quality of life in IBD, although their effects on gut microbiota composition and objective inflammatory activity require further investigation64, 65. The Mediterranean diet, by definition, is rich in unprocessed and minimally processed foods, and therefore low in UPFs.
Specific dietary interventions have been explored for their efficacy in IBD management. Exclusive enteral nutrition (EEN) is a well-established therapy, particularly for inducing remission in CD, especially in children60, 66. While not directly about UPFs, EEN demonstrates the profound impact of controlled, nutritionally complete diets on disease activity. Other dietary regimes, such as the Crohn’s Disease Exclusion Diet (CDED), Immunoglobulin Exclusion Diet, Specific Carbohydrate Diet, LOFFLEX Diet, and Low FODMAPs Diet, have been examined for their effects on gut microbiota composition and balance, aiming to reduce inflammation during flare-ups and maintain remission66, 67. While not all of these explicitly target UPFs, they generally advocate for whole, unprocessed foods and restrict components commonly found in UPFs (e.g., certain carbohydrates and additives). For instance, the CDED focuses on excluding certain dietary components often associated with inflammation and promotes the consumption of specific whole foods.
Despite the growing consensus, challenges remain in the practical implementation of dietary advice. A narrative review on nutrition in IBD notes that patients often avoid gluten and dairy, and compliance with the Mediterranean Diet can be low68. This highlights the need for personalized approaches and robust patient education. Personalized dietary approaches are crucial for managing nutrient deficiencies, addressing the effects of Western diets, and handling food intolerances in IBD patients69. Nutrigenomic research, akin to pharmacogenetic research, aims to identify gene variants influencing food effects, which could enable individualized treatment strategies, prevent malnutrition, and establish protective dietary patterns against IBD.
The role of specific food components and their quality is also under scrutiny. For example, while fruit and vegetable intake is generally protective, the quality and preparation method matter. A study found no association between diet quality/patterns and disease activity in a Dutch IBD cohort, but a trend towards increased odds of increased disease activity with an animal protein-rich pattern was observed70. This emphasizes that not all dietary patterns are equally beneficial, and the specific composition matters. The concept of "food is medicine" is gaining traction, necessitating improved dietary assessment tools in adult IBD research to evaluate nutritional quality, dietary patterns, and inflammatory potential, integrating advanced methods such as biomarkers and multi-omics71.
In summary, current AGA and ECCO guidance supports healthy dietary patterns with limited UPF intake, while ESPEN emphasizes individualized nutritional assessment and support. These recommendations should not be interpreted as evidence that UPF restriction alone induces or maintains IBD remission. Dietitian-guided nutritional counseling remains important for ensuring nutritional adequacy and supporting dietary adherence. Further randomized controlled trials are needed to clarify the effects of specific dietary modifications on clinical outcomes in IBD. Current nutritional guidelines and clinical dietary strategies for IBD management are summarized in Table 3.
Table 3: Summary of International Guidelines and Contemporary Clinical Nutritional Strategies for IBD Management. Abbreviations: AGA = American Gastroenterological Association; ECCO = European Crohn’s and Colitis Organization; ESPEN = European Society for Clinical Nutrition and Metabolism; UPF = ultra-processed food; IBD = inflammatory bowel disease; CD = Crohn’s disease; UC = ulcerative colitis; EEN = exclusive enteral nutrition; CDED = Crohn’s disease exclusion diet; PEN = partial enteral nutrition; SCD = specific carbohydrate diet; FODMAPs = fermentable oligosaccharides, disaccharides, monosaccharides, and polyols; IBS = irritable bowel syndrome. Note: Guideline recommendations and observational study findings are presented separately. The non-randomized findings of Preda et al. do not establish treatment causality; low-FODMAP dietary therapy is intended for IBS-like symptoms in quiescent IBD, not for induction or maintenance of inflammatory remission. Please click here to download this Table.
Limitations of the evidence
As this review used a targeted, non-systematic approach to literature identification and narrative synthesis, relevant studies may have been missed, and source selection may have introduced selection bias. Several limitations should be considered when interpreting the evidence summarized in this review. First, mechanistic findings involving microbiota dysbiosis, epithelial barrier dysfunction, TLR4/NF-κB signaling, and NLRP3 inflammasome activation are derived largely from in vitro and animal studies. Experimental exposure doses, durations, and isolated additives may not reflect habitual human dietary patterns, while species-specific differences in microbial communities and immune responses further limit translation to human IBD. Although these findings provide biological plausibility, direct human evidence establishing these pathways as causal mechanisms of UPF-related intestinal inflammation remains limited72.
Second, the NOVA classification provides a widely used framework for categorizing foods according to processing, but its limitations warrant consideration. The UPF category includes nutritionally and technologically heterogeneous products, and classification criteria may not adequately distinguish differences in nutritional quality or specific processing methods5, 6. Moreover, dietary assessment instruments, particularly food frequency questionnaires not originally designed to assess processing, may lack sufficient detail on product formulations and preparation methods, increasing the possibility of exposure misclassification73. Such limitations may lead to UPF exposure misclassification and complicate comparisons across studies.
Third, associations between UPF consumption and IBD risk may be influenced by co-occurring lifestyle and socioeconomic factors, including smoking, physical activity, adiposity, educational attainment, and overall dietary quality. For example, Lo et al. reported higher BMI, lower physical activity, and poorer diet quality among participants with greater UPF intake8. Although large prospective cohorts have adjusted for several measured lifestyle and socioeconomic factors7, 8, residual confounding remains possible because these characteristics may be imperfectly measured or correlated with unmeasured exposures. Adiposity may also represent a potential mediator rather than solely a confounder, further complicating the interpretation of adjusted associations. Consequently, the observed relationships cannot be attributed exclusively to industrial food processing, and residual confounding could influence the magnitude or direction of the reported associations. Fourth, several included findings are available only as conference abstracts rather than full-length publications, including studies addressing dietary patterns, nutritional status, emulsifier exposure, and microbiota alterations18,22,23,24,25,26,30,37,40. Such reports often provide insufficient methodological detail to fully assess patient selection, exposure measurement, confounding adjustment, and risk of bias. Their findings should therefore be interpreted as preliminary and hypothesis-generating, rather than as independently conclusive evidence. Further well-characterized human studies and fully reported clinical investigations are needed to strengthen the evidence base.
These limitations are also reflected in larger epidemiological analyses and recent reviews. In a meta-analysis of 24 observational studies involving 4,035,694 participants, Babaei et al. reported a modest association between higher UPF consumption and overall IBD risk (RR = 1.13, 95% CI: 1.06–1.21), with substantial between-study heterogeneity (I2 = 73.2%); a dose-response association was observed for CD but not UC74. Similarly, a UK Biobank study by Chen et al. reported an association between higher UPF intake and incident CD (HR = 2.00, 95% CI: 1.32–3.03), but not UC75. Recent reviews by Choi and Moon76 and Spiller et al.77 also highlight potential microbiota- and barrier-related mechanisms while acknowledging the limitations of current human evidence. Collectively, these findings support further investigation of UPF exposure in IBD but do not eliminate concerns regarding exposure misclassification, study heterogeneity, and causal uncertainty.
To distinguish the strength of evidence supporting the major conclusions of this review, Table 4 presents a structured, claim-specific qualitative appraisal considering study design, temporal sequence, consistency, directness to human IBD, exposure assessment, potential confounding, and completeness of reporting. Because this narrative review did not include a systematic study-level risk-of-bias assessment or formal outcome-specific GRADE evidence profiles, the assigned categories represent descriptive judgments rather than formal GRADE certainty ratings.
Table 4: Structured Critical Appraisal of Evidence Supporting Major Claims About UPF Consumption and IBD. Abbreviations: AGE, advanced glycation end product; CD, Crohn’s disease; CMC, carboxymethylcellulose; EEN, exclusive enteral nutrition; IBD, inflammatory bowel disease; LPS, lipopolysaccharide; RAGE, receptor for advanced glycation end products; SCFA, short-chain fatty acid; UC, ulcerative colitis; UPF, ultra-processed food. Note: This is a domain-based narrative appraisal of the claims summarized in the review, not a formal GRADE assessment or a study-by-study risk-of-bias evaluation. Grades are descriptive and claim-specific: A = comparatively stronger human evidence for the stated association or established indication; B = limited or inconsistent human observational evidence; C = predominantly experimental, surrogate, or indirect evidence; D = insufficient direct evidence for the specified causal or therapeutic claim. Judgments considered study design, temporal sequence, consistency, directness to human IBD, exposure measurement, residual confounding, and completeness of reporting. Pooled estimates and their component cohorts are not independent evidence. Conference abstracts were treated as preliminary. Please click here to download this Table.
Future research priorities
Several research priorities emerge from the current evidence. First, studies should distinguish the effects of individual food additives, particularly emulsifiers and thickeners, from those of overall dietary composition and food processing. Controlled human studies using well-characterized additives and physiologically relevant exposure levels are needed to clarify their potential inflammatory effects. Second, prospective cohorts with repeated dietary assessments should investigate dose-response relationships and determine whether clinically meaningful exposure thresholds can be identified for different UPF categories. Third, adequately powered, long-term randomized controlled trials should evaluate whether reducing UPF intake improves clinical outcomes in IBD, using objective measures such as fecal calprotectin, endoscopic inflammation, and disease relapse, while monitoring dietary adherence and nutritional adequacy72, 76.
Further research should also explore microbiome-targeted nutritional strategies, including whether dietary modulation of microbial composition and short-chain fatty acid metabolism translates into measurable clinical benefits. Integrating microbiome, metabolomic, and host-related data may help identify patient subgroups with different responses to dietary interventions. Such precision nutrition approaches require prospective validation to establish their clinical utility, reproducibility, and feasibility before routine implementation61, 77.
الاستنتاجات
The rising global burden of IBD reflects complex interactions among genetic susceptibility, the intestinal microbiome, and environmental exposures, including smoking, antibiotic use, and dietary factors. Epidemiological evidence associates higher UPF consumption with increased risk of incident IBD, particularly Crohn’s disease, and with disease activity in some patient populations; however, these associations do not establish UPF consumption as an independent causal driver of the global IBD burden or disease progression. Experimental findings imply selected UPF additives in intestinal barrier disruption, whereas the contribution of dietary AGEs to epithelial dysfunction in IBD remains less certain. UPF-associated dietary patterns and selected additives may alter microbiota composition, reduce protective short-chain fatty acid-related functions, and weaken intestinal barrier integrity. Barrier dysfunction may facilitate endotoxin translocation and TLR4/NF-κB-related inflammation, whereas direct links between dietary UPF-derived AGEs, impaired epithelial energy sensing, and autophagy in IBD remain incompletely established.
Current AGA and ECCO guidance support healthy dietary patterns with limited UPF intake, while ESPEN emphasizes individualized nutritional assessment and support. Dietary modification should be integrated into comprehensive IBD care according to individual clinical needs rather than presented as a universally effective primary therapy.
Addressing these evidence gaps through rigorous human studies will be essential before UPF-specific dietary strategies can be more confidently recommended for IBD prevention or management. Ultimately, addressing the global burden of IBD requires multifaceted clinical and public health strategies, within which individualized nutritional counseling and further evaluation of UPF reduction may contribute to broader prevention and disease management efforts.
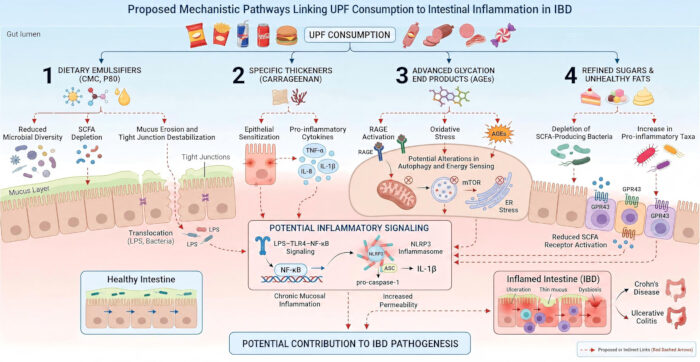
Figure 1: Proposed Mechanistic Pathways Linking Ultra-Processed Food (UPF) Consumption to Intestinal Inflammation in Inflammatory Bowel Disease (IBD). The schematic summarizes four potential pathways through which selected UPF components may affect intestinal immune homeostasis. (1) Dietary emulsifiers (e.g., carboxymethylcellulose [CMC] and polysorbate 80 [P80]) may alter gut microbiota composition, compromise mucus layer integrity and epithelial tight junctions, and facilitate exposure to luminal lipopolysaccharide (LPS) and bacteria. (2) Specific thickeners (e.g., carrageenan) may promote epithelial inflammatory responses, including increased expression of pro-inflammatory cytokines (TNF-α, IL-8, and IL-1β), as suggested by experimental studies. (3) Dietary advanced glycation end products (AGEs) may contribute to RAGE-associated oxidative and inflammatory signaling, while their proposed effects on epithelial energy sensing, autophagy, and endoplasmic reticulum (ER) stress remain insufficiently validated in IBD. (4) Diets rich in refined sugars and unhealthy fats may contribute to microbial dysbiosis and reduced short-chain fatty acid (SCFA) availability, potentially affecting G protein-coupled receptor 43 (GPR43)-mediated signaling. These pathways may interact with mucosal inflammatory processes, including LPS–TLR4–NF-κB signaling and context-dependent NLRP3 inflammasome activation. However, their convergence through a single unified causal pathway has not been established in human IBD. Red dashed arrows indicate proposed or indirect mechanistic links, while solid arrows schematically represent within-pathway relationships and do not establish clinical causality. Please click here to view a larger version of this figure.
الإفصاحات
The authors disclose no conflicts.
شكر وتقدير
The author declares that no funds, grants, or other support were received for this review. No specific acknowledgments are applicable.
المراجع
- Kaplan GG, Windsor JW. The four epidemiological stages in the global evolution of inflammatory bowel disease. Nat Rev Gastroenterol Hepatol. 2020;18:56-66.
- Ananthakrishnan AN, Kaplan GG, Ng SC. Changing global epidemiology of inflammatory bowel diseases: sustaining health care delivery into the 21st century. Clin Gastroenterol Hepatol. 2020;18:1252-60.
- Caron B, Honap S, Peyrin-Biroulet L. Epidemiology of inflammatory bowel disease across the ages in the era of advanced therapies. J Crohns Colitis. 2024;18:ii3-15.
- Rauber F, et al. Ultra-processed food consumption and chronic non-communicable diseases-related dietary nutrient profile in the UK (2008-2014). Nutrients. 2018;10:587.
- Brichacek AL, Florkowski M, Abiona E, Frank KM. Ultra-processed foods: a narrative review of the impact on the human gut microbiome and variations in classification methods. Nutrients. 2024;16:1738.
- Jones JM. Should grain-based staple foods be included in admonitions to 'avoid processed and ultra-processed food'? Nutrients. 2025;17:2188.
- Narula N, et al. Association of ultra-processed food intake with risk of inflammatory bowel disease: prospective cohort study. BMJ. 2021;372:n1554. doi:10.1136/bmj.n1554.
- Lo CH, et al. Ultra-processed foods and risk of Crohn's disease and ulcerative colitis: a prospective cohort study. Clin Gastroenterol Hepatol. 2022;20:e1323-37.
- Narula N, et al. Food processing and risk of inflammatory bowel disease: a systematic review and meta-analysis. Clin Gastroenterol Hepatol. 2023;21:2483-95.e1.
- Wu S, et al. Ultra-processed food consumption and long-term risk of irritable bowel syndrome: a large-scale prospective cohort study. Clin Gastroenterol Hepatol. 2024;22:1497-507.e5.
- Zhao H, et al. Association of ultraprocessed food consumption with risk of rheumatoid arthritis: a retrospective cohort study in the UK Biobank. Am J Clin Nutr. 2024;120:927-35.
- Kasznár E, et al. Ultra-processed food intake in children with inflammatory bowel disease: a pilot case-control study. Nutrients. 2025;17:3532.
- Lo CH, et al. Dietary inflammatory potential and risk of Crohn's disease and ulcerative colitis. Gastroenterology. 2020;159:873-83.e1.
- Guo A, et al. Early-life diet and risk of inflammatory bowel disease: a pooled study in two Scandinavian birth cohorts. Gut. 2024;73:590-600.
- Brusco De Freitas M, Anneberg OM, Jess T. D-ECCO grant dietary patterns during early life and risk of inflammatory bowel disease [conference abstract]. J Crohns Colitis. 2024;18:i2261. https://doi.org/10.1093/ecco-jcc/jjad212.1436
- Vagianos K, et al. Ultra-processed food, disease activity, and inflammation in ulcerative colitis: the Manitoba Living with IBD study. Am J Gastroenterol. 2024;119:1102-9.
- Sarbagili-Shabat C, et al. Ultra-processed foods consumption is positively associated with the clinical activity of inflammatory bowel diseases: a cross-sectional single-center study. Inflamm Intest Dis. 2024;9:241-51.
- Lasfar I, Gharbi K, Akka R. P0822 dietary patterns modulate disease activity in inflammatory bowel disease: a prospective cohort study [conference abstract]. J Crohns Colitis. 2026;20. https://doi.org/10.1093/ecco-jcc/jjaf231.1003
- Jabłońska B, Mrowiec S. Nutritional status and its detection in patients with inflammatory bowel diseases. Nutrients. 2023;15:1991.
- Balestrieri P, et al. Nutritional aspects in inflammatory bowel diseases. Nutrients. 2020;12:372.
- Schreiner P, et al. Nutrition in inflammatory bowel disease. Digestion. 2020;101:120-35.
- Katarachia V, et al. P0768 ultra processed food in inflammatory bowel disease - friend or foe? An examination into the contribution of UPFs to nutrient intake in an IBD remission cohort [conference abstract]. J Crohns Colitis. 2025;19:i1484-5. https://api.semanticscholar.org/CorpusID:275829334
- Compare D, et al. P1066 ultra-processed food intake independently predicts pre-sarcopenia in patients with inflammatory bowel disease in remission [conference abstract]. J Crohns Colitis. 2026;20. https://doi.org/10.1093/ecco-jcc/jjaf231.1247
- Ambrosio C, et al. P0300 ultra-processed food consumption affects body composition in a cohort of Italian patients with inflammatory bowel disease [conference abstract]. J Crohns Colitis. 2025;19:i751. https://doi.org/10.1093/ecco-jcc/jjae190.0474
- Wellens J, et al. P0622 total emulsifier intake, but not ultra-processed food consumption is higher in patients with inflammatory bowel disease compared to healthy controls [conference abstract]. J Crohns Colitis. 2025;19:i1228-30. https://doi.org/10.1093/ecco-jcc/jjae190.0796
- Vissers E, et al. P0098 effect of the dietary emulsifier κ-carrageenan on the inflammatory state and permeability of intestinal epithelial cells from patients with Crohn's disease [conference abstract]. J Crohns Colitis. 2025;19:i469-71. https://doi.org/10.1093/ecco-jcc/jjae190.0272
- Konjar Š, et al. Systems biology to unravel Western diet-associated triggers in inflammatory bowel disease. Front Immunol. 2025;16: 1621334.
- Manciulea (Profir) M, et al. Processed diets and food additives shape the gut microbiota and chronic disease risk across the life course-a three-layer ecosystem disruption model (TLED) model. Life. 2026;16:505.
- Rondinella D, et al. The detrimental impact of ultra-processed foods on the human gut microbiome and gut barrier. Nutrients. 2025;17:859.
- Kim KA, et al. P1316 increased ultra-processed food consumption is associated with inflammation-promoting shift of gut microbiota in inflammatory bowel disease [conference abstract]. J Crohns Colitis. 2025;19:i2371-3. https://doi.org/10.1093/ecco-jcc/jjae190.1490
- Cuevas-Sierra A, et al. Gut microbiota differences according to ultra-processed food consumption in a Spanish population. Nutrients. 2021;13:2710.
- Kopczyńska J, Kowalczyk M. The potential of short-chain fatty acid epigenetic regulation in chronic low-grade inflammation and obesity. Front Immunol. 2024;15: 1380476.
- Holmberg SM, et al. The gut commensal Blautia maintains colonic mucus function under low-fiber consumption through secretion of short-chain fatty acids. Nat Commun. 2024;15: 3502.
- Chassaing B, et al. Randomized controlled-feeding study of dietary emulsifier carboxymethylcellulose reveals detrimental impacts on the gut microbiota and metabolome. Gastroenterology. 2022;162:743-56.
- Menezes C de, et al. Effects of ultra-processed diets on adiposity, gut barrier integrity, inflammation, and microbiota in male and female mice. Nutrients. 2025;17:3116.
- Kityo A, et al. Association of ultra-processed food-related metabolites with selected biochemical markers in the UK Biobank. Nutr J. 2025;24:21
- Wang S, et al. DOP047 circulating metabolites unveil a link between ultra-processed food and the development of inflammatory bowel disease: a multi-cohort study among Western and Eastern populations [conference abstract]. J Crohns Colitis. 2026;20: jjaf231-084.
- Zhang S, et al. Bacteroides uniformis degrades β-glucan to promote Lactobacillus johnsonii improving indole-3-lactic acid levels in alleviating colitis. Microbiome. 2024;12:177.
- Park Y, et al. Integrated analysis of microbiome and metabolome reveals disease-specific profiles in inflammatory bowel diseases and intestinal Behçet's disease. Int J Mol Sci. 2024;25:6697.
- Park Y, et al. P1230 integrated analysis of microbiome and metabolome reveals disease-specific profiles in inflammatory bowel disease and intestinal Behçet's disease [conference abstract]. J Crohns Colitis. 2024;18:i2167. https://doi.org/10.1093/ecco-jcc/jjad212.1360
- Dale HF, Kolby M, Valeur J. Ultra-processed food consumption and irritable bowel syndrome: current evidence and clinical implications. Nutrients. 2025;17:3567.
- Besedin D, et al. Food additives and their implication in inflammatory bowel disease and metabolic syndrome. Clin Nutr ESPEN. 2024;64:483-95.
- Alcaire F, Giménez A, Ares G. Food additives associated with gut dysbiosis in processed and ultra-processed products commercialized in the Uruguayan market. Food Res Int. 2024;191:114721.
- Selvakumar B, Samsudin R. Intestinal barrier dysfunction in inflammatory bowel disease: pathophysiology to precision therapeutics. Inflamm Bowel Dis. 2025;31:3450-64.
- Dong T, et al. Recent advances in exploring casein peptide regulation of inflammatory bowel disease from an intestinal barrier perspective: correlations, mechanisms, challenges and solutions. Foods. 2026;15:997.
- Viennois E, et al. Dietary emulsifiers directly impact adherent-invasive E. coli gene expression to drive chronic intestinal inflammation. Cell Rep. 2020;33:108229.
- Kimilu N, et al. Carrageenan in the diet: friend or foe for inflammatory bowel disease? Nutrients. 2024;16:1780.
- Rutgrink JMI, te Velde AA. From diet to inflammasome: ultra-processed foods as upstream drivers of NLRP3-mediated intestinal inflammation in inflammatory bowel disease. Immuno. 2026;6:24.
- Shakhman S, et al. Industrial bread composition: potential implications for patients with inflammatory bowel disease. Nutrients. 2025;17:2120.
- Wu Y, et al. Galactooligosaccharides and Limosilactobacillus reuteri synergistically alleviate gut inflammation and barrier dysfunction by enriching Bacteroides acidifaciens for pentadecanoic acid biosynthesis. Nat Commun. 2024;15:9291.
- Maki KA, Sack MN, Hall KD. Ultra-processed foods: increasing the risk of inflammation and immune dysregulation? Nat Rev Immunol. 2024;24:453-4.
- Xiao W. The impact of emulsifiers in ultra processed foods on intestinal health, exacerbating non-alcoholic fatty liver disease, and intervention strategies. MedScien. 2025;1. https://doi.org/10.61173/cpgqwj87
- Jiao Y, Wu L, Huntington ND, Zhang X. Crosstalk between gut microbiota and innate immunity and its implication in autoimmune diseases. Front Immunol. 2020;11:282.
- Sajan K, et al. Ultra-processed foods and increased high sensitivity C-reactive protein. Am J Med. 2025;138:1742-5.
- Millar SR, Harrington JM, Perry IJ, Phillips CM. Associations between ultra-processed food and drink consumption and biomarkers of chronic low-grade inflammation: exploring the mediating role of adiposity. Eur J Nutr. 2025;64:150.
- Sandys O, Stokkers PCF, te Velde AA. DAMP-ing IBD: extinguish the fire and prevent smoldering. Dig Dis Sci. 2024;70:49-73.
- Clemente-Suárez VJ, et al. Global impacts of Western diet and its effects on metabolism and health: a narrative review. Nutrients. 2023;15:2749.
- Mostafavi Abdolmaleky H, Zhou JR. Gut microbiota dysbiosis, oxidative stress, inflammation, and epigenetic alterations in metabolic diseases. Antioxidants. 2024;13:985.
- Jiang F, et al. The contribution of dietary advanced glycation end-products and genetic risk in the development of inflammatory bowel disease: a prospective cohort study. Aliment Pharmacol Ther. 2024;60:1075-86.
- Hashash JG, Elkins J, Lewis JD, Binion DG. AGA clinical practice update on diet and nutritional therapies in patients with inflammatory bowel disease: expert review. Gastroenterology. 2024;166:521-32.
- Svolos V, et al. European Crohn's and Colitis Organisation consensus on dietary management of inflammatory bowel disease. J Crohns Colitis. 2025;19:jjaf122.
- Bischoff SC, et al. ESPEN guideline on clinical nutrition in inflammatory bowel disease. Clin Nutr. 2023;42:352-79.
- Preda CM, et al. Diet optimization in inflammatory bowel disease: impact on disease relapse and inflammatory markers. A 1-year prospective trial. J Gastrointestin Liver Dis. 2024;33:184-93.
- Naik RG, et al. From evidence to practice: a narrative framework for integrating the Mediterranean diet into inflammatory bowel disease management. Nutrients. 2025;17:470.
- Perrone P, D'Angelo S. Gut microbiota modulation through Mediterranean diet foods: implications for human health. Nutrients. 2025;17:948.
- Manski S, et al. Diet and nutrition in inflammatory bowel disease: a review of the literature. Crohns Colitis 360. 2023;6:otad077
- Fiorindi C, et al. Inflammatory bowel disease and customized nutritional intervention focusing on gut microbiome balance. Nutrients. 2022;14:4117.
- Roncoroni L, et al. Nutrition in patients with inflammatory bowel diseases: a narrative review. Nutrients. 2022;14:751.
- Laing BB, Lim AG, Ferguson LR. A personalised dietary approach-a way forward to manage nutrient deficiency, effects of the Western diet, and food intolerances in inflammatory bowel disease. Nutrients. 2019;11:1532.
- Koppelman LJM, et al. Can diet quality be associated with disease activity in a prospective Dutch inflammatory bowel disease cohort? Nutrients. 2025;17:1298.
- Andersen V, et al. Food is medicine: diet assessment tools in adult inflammatory bowel disease research. Nutrients. 2025;17:245.
- Whelan K, Bancil AS, Lindsay JO, Chassaing B. Ultra-processed foods and food additives in gut health and disease. Nat Rev Gastroenterol Hepatol. 2024;21:406-27.
- Cavero-Redondo I, et al. Validity and reliability of tools to measure ultraprocessed food intake under the NOVA system: a systematic review. Am J Clin Nutr. 2026;123:101263.
- Babaei A, et al. The association of ultra-processed food consumption with adult inflammatory bowel disease risk: a systematic review and dose-response meta-analysis of 4 035 694 participants. Nutr Rev. 2024;82:861-71.
- Chen J, et al. Intake of ultra-processed foods is associated with an increased risk of Crohn's disease: a cross-sectional and prospective analysis of 187 154 participants in the UK Biobank. J Crohns Colitis. 2023;17:535-52.
- Choi SY, Moon W. Ultra-processed foods and inflammatory bowel disease: a narrative review of epidemiology, mechanisms, and dietary implications. Nutrients. 2025;17:3852.
- Spiller AL, et al. Ultra-processed foods, gut microbiota, and inflammatory bowel disease: a critical review of emerging evidence. Nutrients. 2025;17:2677.