This protocol presents a standardized workflow for combining low-frequency repetitive transcranial magnetic stimulation with sensory arousal nursing for post-stroke dysphagia, while incorporating upper-limb activities to support self-feeding.
مقالة منهجية
Low-Frequency Repetitive Transcranial Magnetic Stimulation with Sensory Arousal Nursing for Post-Stroke Dysphagia
في هذه المقالة
ملخص
الملخص
Post-stroke dysphagia can compromise airway protection, nutrition, and functional recovery. This article describes a clinical protocol combining low-frequency repetitive transcranial magnetic stimulation (rTMS) with a structured sensory arousal nursing package for patients with acute ischemic stroke and dysphagia accompanied by feeding-related upper-limb dysfunction. Dysphagia is the primary treatment focus; upper-limb activities address associated limitations in self-feeding. The protocol integrates screening, stimulation safety review, motor-threshold determination, contralesional swallowing-motor targeting, 1 Hz rTMS, sequenced sensory input, feeding-related task practice, and outcome assessment. Representative results come from a single-center, randomized, assessor-blinded study of 160 patients (80 per group) comparing the combined intervention with routine nursing for swallowing rehabilitation over 2 weeks. The between-group difference in Standardized Swallowing Assessment change was −3.9 points (95% confidence interval [CI], −5.8 to −2.0; p < 0.001). The between-group change-score differences were 0.8 levels for the Functional Oral Intake Scale (95% CI, 0.4 to 1.2; p < 0.001) and −0.9 points for the Penetration-Aspiration Scale (95% CI, −1.5 to −0.3; p = 0.004), the latter restricted to participants with paired instrumental assessments (48 versus 46). Aspiration pneumonia occurred in 5/80 versus 11/80 participants (p = 0.118); no serious rTMS-related adverse events were reported. These findings indicate short-term differences in scale scores but do not establish a clinically important benefit in swallowing or a reduced risk of pneumonia. The protocol coordinates established rehabilitation components. Further studies are needed to determine their individual effects and identify patients who may benefit from contralesional inhibition.
المقدمة
Dysphagia occurs frequently after acute ischemic stroke and is associated with aspiration pneumonia, malnutrition, dehydration, poor functional outcomes, and increased care burden1,2,3. Stroke guidelines recommend formal dysphagia screening before oral intake and timely assessment by trained professionals1. In clinical nursing practice, however, swallowing rehabilitation is often constrained by fluctuating arousal, attention deficits, hemiparesis, fatigue, aphasia, and a reduced ability to participate actively in task-oriented training during the acute phase.
Swallowing depends on a distributed sensorimotor network with bilateral but asymmetric cortical representation4,5,6,7. Functional recovery after dysphagic stroke is related, in part, to cortical reorganization and recruitment of intact swallowing-related networks5. Repetitive transcranial magnetic stimulation (rTMS) can alter cortical excitability and has therefore been investigated as a noninvasive rehabilitation adjunct for post-stroke dysphagia8,9,10,11. Low-frequency protocols are commonly used to suppress excessive or maladaptive excitability at selected cortical sites, although the optimal target and stimulation strategy may vary according to lesion location, recovery phase, and patient phenotype11.
In this protocol, sensory arousal nursing refers to a structured combination of visual and auditory orientation, tactile and proprioceptive input to the paretic upper limb, oral thermal-tactile stimulation, and feeding-related task practice. Gustatory or olfactory input is conditional on clinical suitability and swallowing safety. The term is specific to this study; the combined approach has not been internationally standardized or independently validated. The activities aim to improve alertness and attention to the affected side, prepare patients for swallowing exercises, and support participation in rehabilitation. These proposed mechanisms were not measured.
This article presents a protocol suitable for video demonstration for post-stroke dysphagia in patients who also have feeding-related upper-limb dysfunction. Swallowing is the primary clinical focus, and arm and hand exercises address difficulties with self-feeding. A patient may improve swallowing yet remain unable to stabilize a cup, reach for a spoon, or bring an empty utensil to the mouth. The upper-limb component, therefore, provides task-specific practice in these feeding activities and postural support, without directly affecting pharyngeal physiology. Fugl-Meyer Assessment for Upper Extremity and Modified Barthel Index results are secondary functional outcomes, not direct measures of swallowing safety or validated measures of swallowing–arm coupling.
The method was applied in a single-center, two-arm, randomized, assessor-blinded study involving patients with acute ischemic stroke complicated by dysphagia and paretic upper-limb dysfunction. Participants were allocated in a 1:1 ratio to low-frequency rTMS combined with sensory arousal nursing or routine swallowing rehabilitation nursing. A computer-generated block randomization sequence with variable block sizes was prepared by an investigator who was not involved in enrollment or outcome assessment. Allocation was concealed using sequentially numbered, opaque, sealed envelopes that were opened only after completion of the baseline assessment.
Because the intervention required visible rTMS equipment and hands-on nursing procedures, blinding of participants and treating nurses was not feasible. Swallowing assessors, upper-limb assessors, and the statistician remained blinded to group assignment.
For the randomized controlled study, the primary outcome was the change in Standardized Swallowing Assessment score from baseline to day 1412. Secondary outcomes included the Functional Oral Intake Scale, Penetration-Aspiration Scale in the instrumental-assessment subgroup, Fugl-Meyer Assessment for Upper Extremity, Modified Barthel Index, nasogastric tube removal, diet texture upgrade, aspiration pneumonia, treatment completion, and adverse events13,14,15. The sample size calculation used an anticipated between-group difference of 3.5 points in the day-14 Standardized Swallowing Assessment change score and a common standard deviation of 7.0 points, based on ward pilot observations and prior dysphagia rehabilitation reports, with a two-sided α of 0.05 and 80% power. Thus, 7.0 points was the assumed standard deviation, not the target treatment difference. The normal-approximation calculation, n = 2 × (1.96 + 0.84)2 × 7.02 / 3.52, gives approximately 63 participants per group. Allowing for 10%–15% attrition would require approximately 70–75 participants per group; the target was increased further to 80 per group to preserve precision for secondary nursing outcomes. The 3.5-point design assumption should not be interpreted as an independently validated minimal clinically important difference.
The authors combined established rehabilitation techniques into a nursing sequence that progresses from arousal and attention to sensorimotor preparation and feeding practice. The sequence incorporates rTMS and repeated safety checks. Its contribution lies in the organization of treatment; the individual techniques are established, and the study did not test a new neurophysiological mechanism. The framework draws on evidence concerning oropharyngeal sensory input in cortical swallowing control7, thermal-tactile oral stimulation16, and multisensory rehabilitation after stroke17. Table 1 identifies the modules, their intended purposes, dose, and procedural boundaries.
First, visual and auditory cues were used to support wakefulness and command following. Second, tactile, proprioceptive, and oral thermal-tactile inputs provided sensorimotor preparation relevant to swallowing and affected-side awareness. Third, empty-cup and empty-spoon tasks linked this preparation to feeding-related hand-to-mouth practice, consistent with task-oriented and repeated-practice principles18,19,20. Actual oral intake remained conditional on swallowing clearance. Whether the components have additive or synergistic effects remains unknown.
The control group received routine nursing for swallowing rehabilitation in accordance with the stroke unit standard. Routine care included upright positioning during training and feeding; oral hygiene and secretion management; basic swallowing exercises; adjustment of diet texture and liquid viscosity to ensure safe swallowing; monitoring for aspiration warning signs; documentation of the feeding route and diet level; and caregiver education.
The control procedure did not include rTMS, structured multisensory arousal sequencing, oral thermal-tactile priming beyond routine care, or standardized feeding-related upper-limb task simulation. The incremental components were therefore contralesional low-frequency rTMS and the structured sensory arousal nursing package. Routine care can include individual sensory or feeding-related activities; the distinction in this study was the planned sequencing and integration of these activities within the combined package. Because both components were combined and the control group did not receive sham stimulation, the trial cannot disentangle the effects of rTMS, sensory input, additional therapist contact, or task practice.
The protocol targeted the contralesional swallowing-related motor cortex: the right hemisphere for a left-hemisphere infarct and the left hemisphere for a right-hemisphere infarct. The initial scalp location was 3 cm anterior and 5 cm lateral to Cz in the international 10–20 system. In 62 intervention participants, a small grid search at 1-cm intervals using surface electromyography identified the largest reproducible mylohyoid/suprahyoid motor response; 18 received stimulation at the fixed scalp coordinate. Neuronavigation was not used. The anatomical starting point and electrophysiological hotspot are distinct localization approaches, and the fixed-coordinate approach is less individualized.
The choice of contralesional 1 Hz stimulation was based on a proposed interhemispheric rebalancing mechanism and prior investigations of low-frequency rTMS in post-stroke dysphagia8,9,10,11. Using the same rule to select the stimulation side reduced procedural variation within the center. However, compensatory recruitment of the intact hemisphere is implicated in swallowing recovery5, and the bilateral, asymmetric swallowing network cannot be reduced to a universal interhemispheric competition model4,5,6. The present study did not demonstrate contralesional hyperexcitability or its normalization in individual participants. Patients with bilateral brainstem lesions, unstable cortical excitability mapping, or seizure risk were excluded. These exclusions do not establish adequate structural reserve in the remaining participants. The protocol remains investigational, and its suitability may vary among patients.
البروتوكول
The study protocol was approved by the Ethics Committee of The Traditional Chinese Medicine Hospital in Huangpi District, Wuhan City (Approval number: 202601013). Written informed consent was obtained from all participants or their legally authorized representatives.
1. Patient screening and enrollment
NOTE: Deliver the protocol through an interdisciplinary team comprising a physician, a TMS-trained therapist, a dysphagia-trained rehabilitation nurse, a speech-language therapist, and an occupational therapist, each according to their respective clinical roles. Adapt responsibilities to local professional scopes of practice; nursing delivery does not replace specialist dysphagia assessment21. Require treatment providers to complete 12 h of protocol-specific training and achieve at least 95% on the practical assessment before treatment delivery. Conduct weekly supervision and randomly audit approximately 10% of treatment records; the target adherence to key procedural steps was at least 90%, although the achieved adherence rate was not reported.
- Screen patients with imaging-confirmed acute ischemic stroke. Confirm medical stability and enrollment within the institutionally approved acute or early subacute treatment window, such as 3–14 days after stroke onset.
- Include adult patients with dysphagia confirmed by bedside swallowing screening. Confirm dysphagia using videofluoroscopic swallowing study (VFSS) or fiberoptic endoscopic evaluation of swallowing (FEES) when available.
- Confirm clinically observable upper-limb dysfunction on the paretic side. Verify that the patient can participate in the feeding-related arm-hand coordination component with appropriate assistance.
- Exclude patients with intracranial ferromagnetic implants, pacemakers, or other incompatible implanted devices, uncontrolled epilepsy, unstable cardiopulmonary disease, severe agitation, severe cognitive impairment preventing cooperation, active oral bleeding, or other contraindications to rTMS.
- Record age, sex, stroke type and location, time from stroke onset, National Institutes of Health Stroke Scale score, feeding route, comorbidities, medication use, and baseline rehabilitation status.
2. Baseline safety and functional assessment
- Perform formal dysphagia screening before permitting oral intake. Keep the patient nil per os and obtain further clinical evaluation when aspiration risk is suspected.
- Assess swallowing function using the Standardized Swallowing Assessment12, Functional Oral Intake Scale13, and, when available, instrumental parameters such as the Penetration-Aspiration Scale14.
- Assess upper-limb function using the Fugl-Meyer Assessment for Upper Extremity15. Observe and document feeding-related hand-to-mouth movement.
- Assess activities of daily living using the Modified Barthel Index or another validated functional scale. Use the same assessment instrument throughout the study.
- Inspect the oral cavity for secretion retention, ulcers, infection, loose teeth, mucosal injury, and denture-related risks. Complete appropriate oral care before stimulation or training.
3. Preparation for low-frequency rTMS
- Seat the patient in a supported upright or semi-recumbent position. Stabilize the head and trunk and confirm that blood pressure, heart rate, and oxygen saturation remain within locally approved safety ranges.
- Review the rTMS safety checklist before each treatment session. Check for seizure history, new neurological deterioration, fever, sleep deprivation, medication changes, and patient-reported discomfort22,23,24.
- Determine the stimulation side according to lesion laterality. Apply low-frequency stimulation to the contralesional swallowing-related motor cortex by selecting the right hemisphere for left-hemisphere stroke and the left hemisphere for right-hemisphere stroke.
- Identify the initial contralesional scalp location at 3 cm anterior and 5 cm lateral to Cz using the international 10–20 system.
- When surface electromyography is available, search a small grid around the initial location at 1 cm intervals. Select the site that produces the largest reproducible mylohyoid/suprahyoid motor-evoked potential.
- Place bipolar surface electrodes over the submental suprahyoid region. Position the recording electrode approximately 1–2 cm lateral to the mandibular midline, between the lower mandibular border and the hyoid.
- Position the reference electrode approximately 2 cm from the recording electrode. Place the ground electrode on the forehead.
- Position the stimulation coil tangentially over the identified target. Orient the coil handle posterolateral to the sagittal plane at approximately 45°.
- When hotspot mapping is unavailable, use the fixed contralesional scalp coordinate located 3 cm anterior and 5 cm lateral to Cz. Document the localization approach used for each participant.
NOTE: In the intervention group, 62 participants underwent anatomical localization followed by surface-EMG hotspot mapping, whereas 18 participants received stimulation using the fixed scalp coordinate. No participants underwent neuronavigation. The fixed-coordinate approach does not establish an individualized electrophysiological hotspot. - Keep the mylohyoid muscle at rest during motor-threshold determination. Determine the motor threshold (MT) as the lowest stimulation intensity that elicits a peak-to-peak motor-evoked potential greater than 100 µV in at least 3 of 5 consecutive stimuli.
- Determine the MT before the first treatment session, and repeat it before session 6, the first treatment session of week 2. At other visits, assess safety and tolerability without routinely redetermining the threshold.
- Reassess the MT if medication use, consciousness, or neurological function changes substantially. Adjust the prescribed stimulation intensity according to the reassessed MT.
NOTE: Base the treatment intensity on the mylohyoid MT rather than a hand-muscle threshold. - Set the stimulation intensity to 100% of the mylohyoid MT determined in step 3.10. Maintain the prescribed intensity within the approved safety and tolerance limits, and document any treatment interruptions or dose adjustments.
4. Delivery of low-frequency rTMS
- Place the stimulation coil tangentially over the identified target scalp region. Verify stable positioning and contact before initiating stimulation.
- Deliver stimulation at 1 Hz for 1,200 pulses per session over 20 min.
- Observe facial expression, speech, limb movement, level of consciousness, and vital signs throughout stimulation. Document clinically relevant changes.
- Stop stimulation immediately upon seizure-like activity, acute neurological deterioration, chest discomfort, severe headache, marked blood pressure elevation, oxygen desaturation, or participant refusal. Initiate the institutionally approved clinical response procedure.
- Deliver one treatment session daily for 5 days per week for 2 consecutive weeks. Interrupt treatment for medical instability, infection, clinically significant fatigue, withdrawal of consent, or another predefined safety criterion.
NOTE: Resume treatment only after clinical reassessment and confirmation that the participant meets the institutionally approved safety criteria.
5. Structured sensory arousal nursing package
NOTE: Begin the nursing package approximately 5 min after rTMS, aiming to initiate it within 30 min. Deliver the package once daily, 5 days per week for 2 weeks, for a total of 10 sessions. Provide visual and auditory orientation for 2–3 min, affected upper-limb sensory input for 5 min, oral cold stimulation for no more than 2 min, and feeding-related task practice for 5–10 min. Allow approximately 15–25 min for the complete package, including positioning and transitions. Follow the sequence described in sections 5–6. Permit oral exposure only after completing a swallowing safety assessment, and record the delivered dose and any interruption.
- Reduce environmental distractions before beginning the intervention. Address the patient by name and explain each activity using short, consistent verbal cues.
- Provide visual orientation by positioning a mirror, cup, spoon, or another high-contrast object within the patient's visual field. Instruct the patient to visually track the nurse or the selected object.
- Provide auditory stimulation using the patient's name, brief verbal commands, and rhythmic counting. Give immediate verbal feedback after successful responses.
- Apply gentle pressure and brushing to the paretic upper limb to provide tactile input. Monitor the patient for discomfort throughout the procedure.
- Provide proprioceptive input using assisted joint movement, hand opening and closing, and supported reaching. Stop the activity immediately if movement produces pain or compromises joint stability.
- Inspect the oral cavity before oral cold stimulation and confirm that the procedure is appropriate. Check for conditions that could make oral stimulation unsafe.
- Moisten a sterile cotton applicator with sterile water, seal it individually, and freeze it before use. Allow the frozen applicator to warm briefly before applying it to the oral cavity.
- Measure the applicator surface temperature immediately before use with a calibrated contact-probe thermometer. Confirm that the surface temperature is between −1 and 3 °C before beginning stimulation.
NOTE: Do not use freezer settings or freezing duration as substitutes for direct measurement of the applicator surface temperature. - Stroke one anterior faucial pillar three times with the cold applicator. Stroke the opposite anterior faucial pillar three times and then cue the patient to swallow.
- Repeat the bilateral stimulation sequence for five rounds to provide a total of 30 strokes. Alternate the starting side between participants and complete the entire oral cold-stimulation procedure within 2 min.
- Avoid contact with the tongue surface during cold stimulation. Do not apply heat or alternate cold and warm stimuli.
NOTE: The duration of each individual contact and the inter-stimulus interval were not recorded in the study. - Use a separate sterile applicator for each participant. Stop oral cold stimulation immediately if mucosal injury, bleeding, or marked pain occurs.
- Perform a dysphagia safety review before providing gustatory or olfactory stimulation. Confirm that the planned sensory exposure is appropriate for the patient's current swallowing status.
- Use minimal and controlled gustatory or olfactory stimuli when clinically appropriate. Do not perform unsupervised swallowing trials in patients at high risk of aspiration.
6. Feeding-related upper-limb practice integrated with swallowing rehabilitation
- Position the patient upright at 60°–90° with neutral head and trunk alignment. Support the affected shoulder and forearm to minimize traction.
- Direct the patient's attention toward the affected side. Instruct the patient to look at, touch, and move the paretic hand with appropriate assistance.
- Pair upper-limb activation with swallowing-related tasks. Cue lip closure, tongue movement, saliva swallowing, coughing, and throat clearing during coordinated training.
- Train feeding-related upper-limb movements using an empty cup and spoon. Practice hand-to-mouth movement, cup holding, spoon-to-mouth movement, and lip-touch cueing without introducing a bolus.
- Introduce oral intake only after appropriate swallowing clearance. Use the prescribed texture, viscosity, bolus size, posture, and compensatory swallowing strategy.
- Monitor for coughing, wet voice, delayed swallowing, oral residue, drooling, fatigue, oxygen desaturation, and reduced alertness during oral trials. Stop oral trials immediately when aspiration warning signs occur.
7. Routine nursing safety management
- Perform oral hygiene at least twice daily. Complete oral hygiene before swallowing training that involves taste or oral sensory stimulation.
- Maintain the patient in an upright position for at least 30 min after oral intake or oral sensory training.
- Document the feeding route, diet level, training content, aspiration warning signs, vital signs, adverse events, and patient tolerance after each session.
- Educate family caregivers about appropriate positioning, alertness monitoring, oral hygiene, and aspiration warning signs. Instruct caregivers not to provide unsupervised feeding until professional clearance is obtained.
8. Outcome assessment and data handling
- Repeat swallowing, upper-limb, and activities-of-daily-living assessments after completion of the intervention course. Repeat the assessments at the predetermined follow-up time point when applicable.
- Use blinded outcome assessors whenever feasible. Apply identical assessment definitions and scoring procedures at all time points.
- Use the prespecified primary outcome: change in Standardized Swallowing Assessment score from baseline to day 14. Calculate change as day 14 minus baseline; negative values indicate improvement. Maintain randomized group assignment in the intention-to-treat analysis.
- Record the secondary outcomes listed in the study design: Functional Oral Intake Scale, instrumental-subgroup Penetration-Aspiration Scale, Fugl-Meyer Assessment for Upper Extremity, Modified Barthel Index, nasogastric tube removal, diet texture upgrade, aspiration pneumonia, treatment completion, and adverse events.
- Perform Penetration-Aspiration Scale scoring only for patients who undergo VFSS or FEES at both baseline and day 14. Use blinded instrumental assessors and report the subgroup denominator separately from the full intention-to-treat population.
- Calculate the baseline-to-day-14 change scores for SSA, FOIS, PAS, FMA-UE, and the Modified Barthel Index. Compare the change scores between groups using independent-samples t tests.
- Compare baseline continuous variables between groups using independent-samples t tests. Analyze within-group baseline-to-day-14 changes using paired t tests.
- Examine continuous variables for clear departures from normality. Use the Mann–Whitney U test for independent comparisons and the Wilcoxon signed-rank test for paired comparisons when clear departures from normality are present.
- For t-based between-group estimates, calculate the 95% confidence interval as the difference in mean change scores ± the relevant t critical value multiplied by its standard error.
- Compare baseline and outcome categorical variables using Fisher’s exact test when any expected cell frequency is below 5. Otherwise, use Pearson’s chi-square test without Yates’ continuity correction.
- Describe outcomes with zero events in both groups without calculating a p value. Apply a two-sided α = 0.05 to the statistical analyses.
NOTE: Do not apply a multiplicity adjustment. Interpret p values for secondary outcomes as exploratory. - Retain all participants in their originally randomized groups regardless of treatment completion. Include all 160 participants in analyses of SSA, FOIS, FMA-UE, and the Modified Barthel Index because complete baseline and day-14 data were available for these outcomes.
NOTE: Do not perform imputation for SSA, FOIS, FMA-UE, or Modified Barthel Index data because no data were missing for these outcomes. - Analyze PAS only for participants with paired instrumental assessments. Include the 94 participants with paired assessments, comprising 48 participants in the combined-intervention group and 46 participants in the control group.
- Document the reasons for the absence of paired instrumental assessments among the remaining 66 participants. Classify the reasons as scheduling or resource limitations (n = 29), medical or transport constraints (n = 15), inability to cooperate or refusal (n = 12), or discharge before day 14 or failure to complete reassessment (n = 10).
NOTE: Report these reasons for both groups combined. The PAS subgroup was not randomly sampled and is susceptible to selection bias. - Report effect estimates, 95% confidence intervals, analysis denominators, and adverse events. Clearly identify analyses restricted to subsets of the randomized population.
النتائج
A total of 160 patients were included, with 80 assigned to the combined low-frequency repetitive transcranial magnetic stimulation (rTMS) plus sensory arousal nursing group and 80 to the routine swallowing rehabilitation nursing control group. All randomized participants had observed day-14 primary outcome data and were included in the intention-to-treat analysis, including those who did not complete all 10 treatment sessions. Participant flow is presented in Figure 1, and the analysis sets and treatment completion data are summarized in Table 2.
Baseline characteristics were comparable between groups (Table 3). The mean age was 66.3 ± 8.4 years in the combined-intervention group and 65.9 ± 8.7 years in the control group. Baseline National Institutes of Health Stroke Scale (NIHSS), Standardized Swallowing Assessment (SSA), Functional Oral Intake Scale (FOIS), Penetration-Aspiration Scale (PAS), Fugl-Meyer Assessment for Upper Extremity (FMA-UE), Modified Barthel Index, and nasogastric tube use did not differ significantly between groups. The intervention components and corresponding safety checkpoints are summarized in Table 4. Treatment completion was high, with 74 patients (92.5%) in the combined-intervention group and 71 patients (88.8%) in the control group completing all 10 planned sessions.
After 2 weeks, swallowing outcomes improved in both groups (Table 5). The SSA score decreased from 31.6 ± 4.8 to 21.0 ± 6.0 in the combined-intervention group and from 31.2 ± 5.1 to 24.5 ± 6.5 in the control group. The FOIS level increased from 2.1 ± 0.7 to 4.5 ± 1.4 in the combined-intervention group and from 2.2 ± 0.8 to 3.8 ± 1.5 in the control group. PAS was analyzed only in the instrumental-assessment subgroup with paired videofluoroscopic swallowing study or fiberoptic endoscopic evaluation of swallowing data (combined intervention, n = 48; control, n = 46). The PAS score decreased from 5.8 ± 1.1 to 3.7 ± 1.5 in the combined-intervention group and from 5.7 ± 1.2 to 4.5 ± 1.6 in the control group.
Upper-limb and functional outcomes also improved after the 2-week intervention (Table 5). The FMA-UE score increased from 22.4 ± 9.6 to 38.6 ± 13.0 in the combined-intervention group and from 23.1 ± 10.1 to 34.9 ± 13.4 in the control group. The Modified Barthel Index increased from 34.6 ± 11.5 to 58.1 ± 15.2 in the combined-intervention group and from 35.1 ± 10.9 to 51.8 ± 15.0 in the control group.
Between-group comparisons of changes from baseline favored the combined intervention for SSA, FOIS, the PAS subgroup, FMA-UE, and the Modified Barthel Index (Table 6). The mean change difference was −3.9 points (95% CI, −5.8 to −2.0; p < 0.001) for SSA, 0.8 (95% CI, 0.4 to 1.2; p < 0.001) for FOIS, −0.9 (95% CI, −1.5 to −0.3; p = 0.004) for PAS, 4.4 (95% CI, 1.0 to 7.8; p = 0.011) for FMA-UE, and 6.8 (95% CI, 2.5 to 11.1; p = 0.002) for Modified Barthel Index. Secondary p-values were not adjusted for multiple comparisons and should be interpreted as exploratory. Table 5 and Figure 2 show the descriptive within-group changes.
No serious rTMS-related adverse events occurred during the intervention period. Safety and nursing outcomes are summarized in Table 7 and illustrated in Figure 3. Aspiration pneumonia occurred in 5 patients (6.3%) in the combined-intervention group and 11 patients (13.8%) in the control group (p = 0.118). Nasogastric tubes were removed by day 14 in 48 patients (60.0%) and 36 patients (45.0%), respectively (p = 0.057), whereas diet texture was upgraded in 56 patients (70.0%) and 45 patients (56.3%), respectively (p = 0.071). These differences did not reach the prespecified threshold for statistical significance.
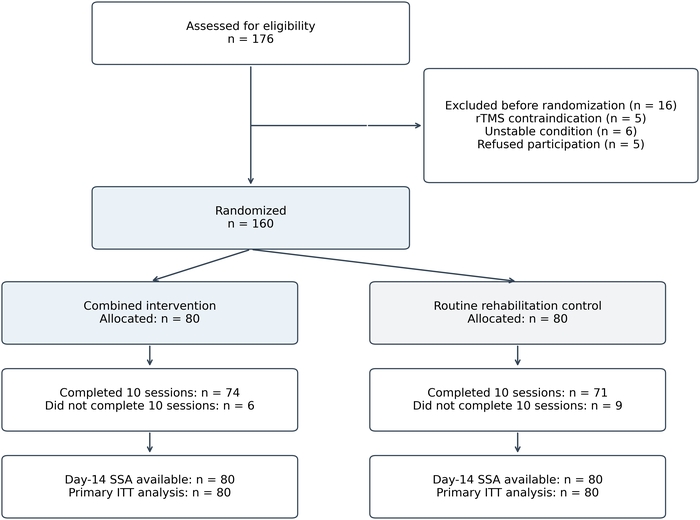
Figure 1: Participant flow through the randomized controlled study. Of 176 patients assessed for eligibility, 16 were excluded before randomization: rTMS contraindication (n = 5), unstable condition (n = 6), and refusal to participate (n = 5). The remaining 160 were randomized, with 80 allocated to each group, and all were included in the intention-to-treat primary analysis. All 10 sessions were completed by 74/80 participants in the combined-intervention group and 71/80 in the control group. All randomized participants provided day-14 SSA data, including those who did not complete treatment. Abbreviations: ITT = intention-to-treat; SSA = Standardized Swallowing Assessment. Please click here to view a larger version of this figure.
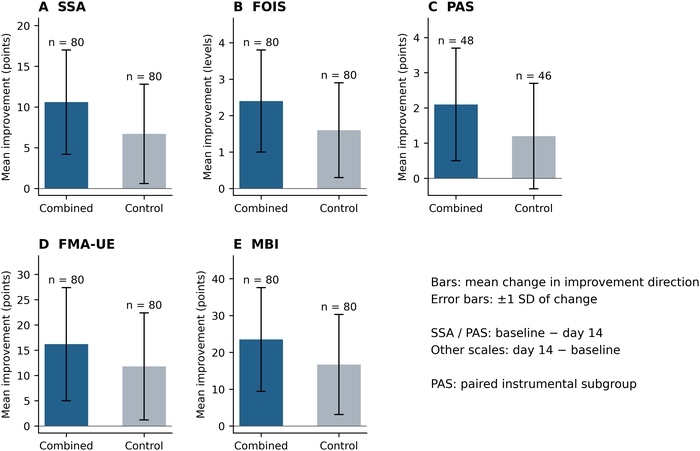
Figure 2: Mean improvement in swallowing, upper-limb, and functional scale scores after 2 weeks. Improvement is defined as baseline minus day 14 for SSA and PAS, and as day 14 minus baseline for FOIS, FMA-UE, and Modified Barthel Index; positive values indicate improvement. Bars show group mean improvements, and error bars represent ±1 SD of the within-group change scores reported in Table 5. Separate panels use scale-specific y-axes (“Mean improvement (points)” or “Mean improvement (levels)” for FOIS); bar heights across scales are not comparable standardized effect sizes. SSA, FOIS, FMA-UE, and MBI include 80 participants per group. PAS includes only paired instrumental assessments (combined intervention, n = 48; control, n = 46). Abbreviations: SSA = Standardized Swallowing Assessment; FOIS = Functional Oral Intake Scale; PAS = Penetration-Aspiration Scale; FMA-UE = Fugl-Meyer Assessment for Upper Extremity; MBI = Modified Barthel Index; SD = standard deviation. Please click here to view a larger version of this figure.
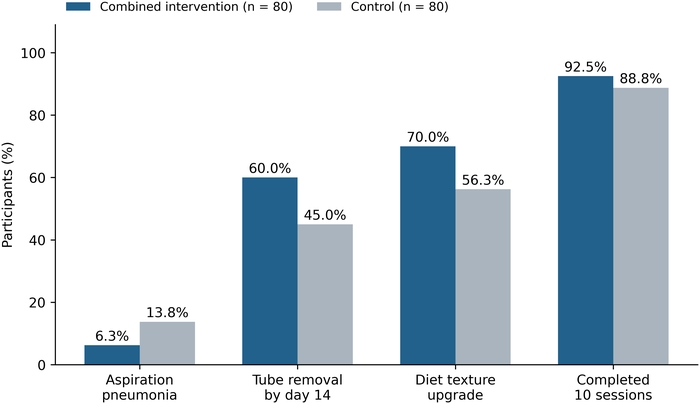
Figure 3: Safety and nursing outcomes after the 2-week intervention period. The y-axis is “Participants (%),” with a denominator of 80 in each randomized group. Combined-intervention versus control values are 6.3% versus 13.8% for aspiration pneumonia (5/80 versus 11/80), 60.0% versus 45.0% for nasogastric tube removal by day 14 (48/80 versus 36/80), 70.0% versus 56.3% for diet texture upgrade (56/80 versus 45/80), and 92.5% versus 88.8% for completion of all 10 sessions (74/80 versus 71/80). Tube-removal percentages are calculated using all randomized participants, rather than only baseline tube users. Please click here to view a larger version of this figure.
Table 1: Sensory arousal nursing modules, purposes, and intervention boundaries. Summary of orientation cues, affected upper-limb sensory input, cold tactile stimulation of the bilateral anterior faucial pillars, and feeding-related task practice. Oral cold stimulation comprises five rounds of three strokes per side, followed by one swallow, for 30 strokes within 2 min at an applicator surface temperature of −1 to 3 °C. The starting side alternates between participants; tongue-surface contact and heat stimulation are excluded. Abbreviation: ROM = range of motion. Please click here to download this Table.
Table 2: Analysis sets and treatment completion. The number of participants randomized, completing all 10 treatment sessions, included in the intention-to-treat analysis, providing day-14 Standardized Swallowing Assessment data, and included in the instrumental Penetration-Aspiration Scale subgroup. Abbreviations: SSA = Standardized Swallowing Assessment; PAS = Penetration-Aspiration Scale. Please click here to download this Table.
Table 3: Baseline characteristics of the combined-intervention and control groups. Demographic and clinical characteristics at baseline, including age, sex, time from stroke onset, lesion laterality, stroke severity, swallowing function, upper-limb function, activities of daily living, and nasogastric tube use. Values are presented as mean ± standard deviation or n (%), as appropriate. Abbreviations: NIHSS = National Institutes of Health Stroke Scale; SSA = Standardized Swallowing Assessment; FOIS = Functional Oral Intake Scale; PAS = Penetration-Aspiration Scale; FMA-UE = Fugl-Meyer Assessment for Upper Extremity. Please click here to download this Table.
Table 4: Intervention components and safety checkpoints for protocol reproducibility. Key parameters include contralesional 1 Hz rTMS at 100% mylohyoid MT, 1,200 pulses over 20 min per session, oral cold tactile stimulation of the anterior faucial pillars, upper-limb sensory input, and feeding-related task practice. Abbreviations: rTMS = repetitive transcranial magnetic stimulation; MT = motor threshold. Please click here to download this Table.
Table 5: Changes in swallowing, upper-limb, and activities-of-daily-living outcomes. Baseline, day-14, and change scores for SSA, FOIS, PAS, FMA-UE, and Modified Barthel Index in the combined-intervention and control groups. PAS results represent the subgroup with paired instrumental swallowing assessments. Values are presented as mean ± standard deviation. Abbreviations: SSA = Standardized Swallowing Assessment; FOIS = Functional Oral Intake Scale; PAS = Penetration-Aspiration Scale; FMA-UE = Fugl-Meyer Assessment for Upper Extremity. Please click here to download this Table.
Table 6: Between-group differences in change scores after 2 weeks. Estimates are the mean baseline-to-day-14 change in the combined-intervention group minus that in the control group, with 95% confidence intervals from the reported t-based comparison. PAS is restricted to the paired instrumental subgroup. Secondary-outcome p-values are unadjusted for multiplicity. Abbreviations: CI = confidence interval; SSA = Standardized Swallowing Assessment; FOIS = Functional Oral Intake Scale; PAS = Penetration-Aspiration Scale; FMA-UE = Fugl-Meyer Assessment for Upper Extremity. Please click here to download this Table.
Table 7: Safety and nursing outcomes during the 2-week intervention period. Values are n (%). Categorical comparisons used Fisher’s exact test if any expected cell frequency was below 5 and Pearson’s chi-square test otherwise, without Yates’ continuity correction. Outcomes with zero events in both arms are described without a p-value. Reported p-values for secondary outcomes are not multiplicity-adjusted. Abbreviation: rTMS = repetitive transcranial magnetic stimulation. Please click here to download this Table.
المناقشة
The protocol requires careful patient selection, repeated safety assessments, consistent control of repetitive transcranial magnetic stimulation (rTMS) parameters, standardized sensory input, and conservative nursing management for dysphagia. Patients with acute ischemic stroke may exhibit rapid changes in alertness, blood pressure, respiratory status, secretion management, fatigue, and neurological function. Clinical status and safety should therefore be reassessed before every session.
In this protocol, rTMS is combined with nursing care and rehabilitation exercises. Effective implementation depends on coordinated nursing components, including arousal priming, affected-side awareness, oral sensorimotor preparation, secretion monitoring, appropriate positioning, and safe feeding-related upper-limb movement. These components also support procedural reproducibility because coil placement, patient positioning, oral stimulation, upper-limb support, and aspiration monitoring can be demonstrated and standardized across treatment sessions.
The randomized study showed greater short-term improvements in the primary swallowing score and several secondary functional measures after the combined intervention. Statistical significance does not establish clinical importance. The SSA between-group change-score difference was −3.9 points (95% CI, −5.8 to −2.0); the absolute point estimate falls below a 4-point benchmark, although the interval includes both smaller and larger effects. If a 4–6-point threshold is used, the average additional benefit has not been shown to fall within that range. A context-specific minimal clinically important difference was not established in this study, and an individual-patient change threshold cannot automatically be applied to a between-group mean difference. For PAS, the −0.9-point difference (95% CI, −1.5 to −0.3) in participants with paired instrumental assessments does not establish a clinically important reduction in aspiration risk. PAS is ordinal, and a mean difference does not show how many individuals moved between clinically relevant airway-invasion categories. Aspiration pneumonia, nasogastric tube removal, and diet texture upgrade did not differ significantly. Accordingly, the study does not establish reduced complication rates, accelerated feeding-route conversion, or a clinically important benefit for every participant.
The sample-size design targeted a 3.5-point SSA difference with a standard deviation of 7.0, not a 7.0-point treatment effect. The reported absolute difference of 3.9 points was therefore not smaller than the design target. Nevertheless, the confidence interval is compatible with an additional benefit as small as 2.0 points. The confidence interval provides a more useful assessment of this uncertainty than a post hoc power calculation based on the observed effect. The trial was not designed to establish power for every secondary or safety outcome. No adjustment for multiple comparisons was used, so secondary findings are exploratory; nonsignificant results should not be read as evidence of equivalence.
Implementation at other centers may require adaptations. Neuronavigation can improve the consistency of target localization, whereas a predefined scalp-based localization method can serve as an alternative when applied and documented consistently. Instrumental swallowing assessment using videofluoroscopic swallowing study (VFSS) or fiberoptic endoscopic evaluation of swallowing (FEES) can provide an objective assessment of swallowing safety, whereas trained bedside screening remains necessary when instrumental assessment is unavailable. Stimulation intensity and pulse number must remain consistent with the ethics-approved protocol and established safety guidance.
The fixed contralesional 1 Hz strategy improves procedural consistency but has not been shown here to outperform bilateral or excitatory alternatives11. Xie et al reported PAS mean differences of −2.06 for bilateral and −1.37 for contralesional stimulation in separate trial subgroups; these are not a direct randomized comparison, and the overall PAS evidence was rated low quality25. These findings warrant further evaluation of alternative targets. The choice of target and frequency should be examined in comparative studies that account for patients’ clinical characteristics.
Structural reserve is a further limitation. The bimodal balance–recovery model proposes that contralesional activity can be maladaptive when ipsilesional reserve is relatively preserved but compensatory when damage is extensive26. This model was developed principally in motor recovery and is not a validated swallowing-specific selection rule. Alongside evidence linking intact-hemisphere reorganization to swallowing recovery5, it suggests that suppression of the contralesional swallowing network may not suit every patient. In patients dependent on that network, inhibition could theoretically impair compensation; the current average treatment effect cannot rule out this possibility. No reserve-stratified treatment effects or physiological evidence confirming the proposed mechanism are reported here. Prospective studies should assess lesion location and extent, corticobulbar pathway integrity, bilateral motor responses, and swallowing characteristics to inform individualized stimulation.
The acute enrollment window, approximately 3–14 days after stroke onset, includes patients with changing neurological status, spontaneous recovery, and varied lesion and swallowing characteristics. Randomization supports an average comparison but does not establish equal responses across these subgroups. The single-center design, 2-week observation period, lack of participant and treatment-provider blinding, additional intervention exposure, and restricted instrumental subgroup limit causal attribution and generalizability. The absence of a publicly accessible prospective registration record also limits independent verification of outcome and analysis prespecification. No serious rTMS-related event was reported, but this sample and follow-up period cannot rule out uncommon harms or adverse effects in patients with low structural reserve. The nonrandom PAS subset creates potential selection bias. In addition, 18 intervention participants were treated using fixed scalp coordinates rather than individualized EMG hotspots, thereby introducing localization heterogeneity. The absence of individual contact-duration and interval records for oral cold stimulation limits precise replication of the stimulation timing.
This protocol combines established dysphagia rehabilitation activities with upper-limb exercises to support self-feeding. Delivery requires coordination among qualified professionals within their local scopes of practice. Studies using the protocol should document stimulation parameters, sensory input, staff training, adherence checks, and any adaptations. Multicenter validation, patient-important outcomes, longer follow-up, sham-controlled comparisons, and a factorial design are needed to establish generalizability and distinguish the contributions of the individual components.
الإفصاحات
The authors declare no competing financial interests. Devices are identified to support reproducibility; their inclusion does not imply endorsement.
شكر وتقدير
This work was supported by the General Research Program of Traditional Chinese Medicine and Integrated Traditional Chinese and Western Medicine of the Wuhan Municipal Health Commission (Grant No. WZ21C38). The authors thank the patients, caregivers, stroke nursing team, rehabilitation therapists, speech-language pathologists, and physicians who contributed to the development and implementation of the protocol.
المواد
| الاسم | الشركة | رقم فهرسي | التعليقات |
|---|---|---|---|
| Adjustable chair or bed | Institutional standard | N/A | Supports upright 60–90° positioning |
| Butterfly coil | MagVenture, Denmark | MCF-B65 | Cortical stimulation |
| Contact-probe thermometer | Institutional standard | N/A | Calibrated; used to verify applicator surface temperature of −1 to 3 °C immediately before use |
| Empty cup and spoon | Institutional standard | N/A | Clean training tools for feeding-related movement practice |
| Oral-care and suction equipment | Institutional standard | N/A | Oral hygiene and secretion management |
| Pulse oximeter and blood pressure monitor | Institutional standard | N/A | Safety monitoring |
| rTMS stimulator | MagVenture, Denmark | MagPro X100 | 1 Hz repetitive transcranial magnetic stimulation |
| Single-use oral cold applicator | Institutional standard | N/A | Sterile cotton applicator moistened with sterile water, individually sealed and frozen; briefly rewarmed before use |
| Surface electrodes | Institutional standard | N/A | Bipolar submental electrodes with forehead ground for motor-response recording |
| Surface EMG system | Natus, USA | Nicolet EDX | Mylohyoid/suprahyoid motor-evoked potential recording; alternatively, use a stimulator-compatible two-channel surface EMG system |
المراجع
- Powers WJ et al. Guidelines for the early management of patients with acute ischemic stroke: 2019 update to the 2018 guidelines for the early management of acute ischemic stroke: a guideline for healthcare professionals from the American Heart Association/American Stroke Association. Stroke. 2019;50:e344-e418.
- Martino R et al. Dysphagia after stroke: incidence, diagnosis, and pulmonary complications. Stroke. 2005;36:2756-2763.
- Hinchey JA et al. Formal dysphagia screening protocols prevent pneumonia. Stroke. 2005;36:1972-1976.
- Hamdy S et al. The cortical topography of human swallowing musculature in health and disease. Nat Med. 1996;2:1217-1224.
- Hamdy S et al. Recovery of swallowing after dysphagic stroke relates to functional reorganization in the intact motor cortex. Gastroenterology. 1998;115:1104-1112.
- Mistry S et al. Unilateral suppression of pharyngeal motor cortex to repetitive transcranial magnetic stimulation reveals functional asymmetry in hemispheric projections to human swallowing. J Physiol. 2007;585:525-538.
- Gow D et al. Characterising the central mechanisms of sensory modulation in human swallowing motor cortex. Clin Neurophysiol. 2004;115:2382-2390.
- Yang W et al. The effect of repetitive transcranial magnetic stimulation on dysphagia after stroke: a systematic review and meta-analysis. Front Neurosci. 2021;15:769848.
- Wen X et al. The effectiveness of repetitive transcranial magnetic stimulation for post-stroke dysphagia: a systematic review and meta-analysis. Front Hum Neurosci. 2022;16:841781.
- Li H et al. Effectiveness of repetitive transcranial magnetic stimulation on poststroke dysphagia: a meta-analysis of randomized controlled trials. Int J Rehabil Res. 2022;45:109-117.
- Wu X et al. Repetitive transcranial magnetic stimulation strategies for poststroke dysphagia: a systematic review and network meta-analysis. Arch Phys Med Rehabil. 2025;106:1248-1257.
- Perry L. Screening swallowing function of patients with acute stroke. Part one: identification, implementation and initial evaluation of a screening tool for use by nurses. J Clin Nurs. 2001;10:463-473.
- Crary MA, Mann GDC, Groher ME. Initial psychometric assessment of a functional oral intake scale for dysphagia in stroke patients. Arch Phys Med Rehabil. 2005;86:1516-1520.
- Rosenbek JC et al. A penetration-aspiration scale. Dysphagia. 1996;11:93-98.
- Fugl-Meyer AR et al. The post-stroke hemiplegic patient. 1. A method for evaluation of physical performance. Scand J Rehabil Med. 1975;7:13-31.
- Teismann IK et al. Tactile thermal oral stimulation increases the cortical representation of swallowing. BMC Neurosci. 2009;10:71.
- Tinga AM et al. A systematic review of multisensory stimulation to improve functional recovery in stroke patients. Neuropsychol Rev. 2016;26:73-91.
- Logemann JA. The role of exercise programs for dysphagia patients. Dysphagia. 2005;20:139-140.
- Robbins J et al. The effects of lingual exercise in stroke patients with dysphagia. Arch Phys Med Rehabil. 2007;88:150-158.
- Lang CE et al. Observation of amounts of movement practice provided during stroke rehabilitation. Arch Phys Med Rehabil. 2009;90:1692-1698.
- Clark S, Ebersole B. Understanding the role of speech language pathologists in managing dysphagia. Nursing. 2018;48:42-46.
- Wassermann EM. Risk and safety of repetitive transcranial magnetic stimulation: report and suggested guidelines. Electroencephalogr Clin Neurophysiol. 1998;108:1-16.
- Rossi S et al. Safety and recommendations for TMS use in healthy subjects and patient populations. Clin Neurophysiol. 2009;120:2008-2039.
- Rossi S et al. Safety and recommendations for TMS use in healthy subjects and patient populations, with updates on training, ethical and regulatory issues: expert guidelines. Clin Neurophysiol. 2021;132:269-306.
- Xie YL et al. Transcranial magnetic stimulation for improving dysphagia after stroke: a meta-analysis of randomized controlled trials. Front Neurosci. 2022;16:854219.
- Di Pino G et al. Modulation of brain plasticity in stroke: a novel model for neurorehabilitation. Nat Rev Neurol. 2014;10:597-608.