يرسم هذا التحليل البيبليومتري والمرئي خريطة تطور أبحاث العلاج بالجروح بالضغط السلبي (NPWT) من عام 1991 إلى عام 2026. وهو يلخص أنماط النشر، وشبكات التعاون، والمصادر المؤثرة، والتحولات الموضوعية من الدراسات الميكانيكية إلى رعاية الجروح، وضمادات الجروح، والوقاية من العدوى، وتقييم النتائج السريرية.
مقالة بحثية
أبحاث العلاج بضغط السلب للجروح: تحليل بيبلومتري وتصويري لمجموعة Web of Science الأساسية
* These authors contributed equally
في هذه المقالة
ملخص
الملخص
يُستخدم العلاج بالضغط السلبي للجروح (NPWT) على نطاق واسع في الجراحة ورعاية الجروح، ولكن لا تزال بنيته الفكرية وأنماط التعاون طويلة المدى غير محددة بشكل كامل. قمنا بفحص 5,957 سجلاً تم استرجاعها من مجموعة Web of Science الأساسية، وأجرينا تحليلاً ببليومترياً وتصورياً لـ 4,063 مقالاً ومراجعة مدرجة. تم فحص السجلات بشكل مستقل من قبل باحثين اثنين، وحُسمت نقاط الاختلاف بالتوافق. استُخدمت برامج VOSviewer وCiteSpace وأدوات إحصائية تكميلية لتقييم اتجاهات النشر، وشبكات التعاون، والتكرار المشترك للكلمات المفتاحية، وطفرات الاستشهاد، والأنماط على مستوى الدول. وقد زاد نشاط النشر بشكل ملحوظ بعد عام 2004. وكانت الولايات المتحدة والصين الدول الأكثر إنتاجية، بينما احتلت المؤسسات الأوروبية والأمريكية مواقع مركزية في شبكات التعاون. وتطور التركيز الموضوعي من الضغط دون الجوي، والتروية، والأبحاث الآلية، نحو رعاية الجروح، وضمادات الجروح، وعدوى موقع الجراحة، وقرح القدم السكرية، والفعالية. وتحدد هذه النتائج تطور أبحاث NPWT وتحدد الأولويات للدراسات السريرية متعددة المراكز، والتحقيقات الآلية، وابتكار المواد، والتعاون الدولي.
المقدمة
يعد العلاج بالجروح بالضغط السلبي (NPWT) وسيلة سريرية مستخدمة على نطاق واسع لتعزيز التئام الجروح عن طريق تطبيق ضغط موضعي أقل من الضغط الجوي لتقليل وذمة الأنسجة، وإزالة الإفرازات، ودعم السيطرة على العدوى. وقد طُبق على قرح القدم السكرية1,2، وجروح البطن المفتوحة3,4، وعيوب الأنسجة الرخوة الرضحية، والجروح التقويمية5,6. وقد أرست تقارير تجريبية وسريرية بارزة نُشرت في عام 1997 الأساس البيولوجي والجدوى السريرية للإغلاق بمساعدة الفراغ7,8. وتشمل الآليات المقترحة تكاثر الخلايا الناجم عن التشوه الدقيق9، وتكوين الأوعية الدموية10، وتحسين التروية الموضعية. وعلى مدى العقود الثلاثة الماضية، توسع النطاق السريري لعلاج NPWT نحو العلاج الفردي والابتكار القائم على الأجهزة، بما في ذلك NPWT مع الغسيل11.
على الرغم من استخدامه على نطاق واسع، لا يزال هناك عدم يقين بشأن قوة الأدلة السريرية الخاصة بالعلاج بالضغط السلبي للجروح (NPWT)12. فقد وجدت مراجعة أجرتها مؤسسة كوكرين عام 2014 عدم كفاية الأدلة على وجود فوائد واضحة للجروح الجراحية التي تلتئم عن طريق النية الأولية، وأشارت إلى التأثير المحتمل للتمويل التجاري13. كما أفاد تحديث لاحق من كوكرين بوجود حالة من عدم اليقين تجاه العديد من النتائج ذات الأهمية السريرية، رغم أن NPWT قد يقلل من عدوى موقع الجراحة في حالات مختارة14. وبناءً على ذلك، هناك حاجة إلى تجارب ممولة بشكل مستقل وذات قوة إحصائية كافية، لا سيما لدى المجموعات الجراحية المعرضة لمخاطر عالية. كما لا تزال إعدادات الضغط المثالية، واختيار الضمادات، والبروتوكولات الخاصة بكل موقع، وعوامل التنبؤ طويلة المدى غير محددة بشكل كامل. وتتوزع الأنشطة البحثية بشكل غير متكافئ جغرافياً؛ حيث أجريت الدراسات التجريبية والسريرية التأسيسية لـ NPWT بواسطة مجموعات بحثية أمريكية، وتشير التحليلات العالمية اللاحقة إلى أن المؤسسات الأمريكية والأوروبية أصبحت مساهمة بارزة في شبكات البحث والتعاون في هذا المجال7,8,15. وقد ساهمت مجموعات بحثية صينية في تقديم مجموعة متزايدة من الأدلة السريرية المتعلقة بقرح القدم السكرية1، والحروق16، وجروح العظام والكسور المفتوحة17. ومع ذلك، في مجموعة البيانات الحالية، كانت المنشورات الصينية تُنتج بشكل متكرر ضمن شبكات بحثية داخل دولة واحدة، وكانت المشاركة في التعاونات متعددة الجنسيات أقل نطاقاً مما لوحظ بين العديد من المجموعات الأمريكية والأوروبية الراسخة. وتسلط هذه النتائج الضوء على فرص تعزيز التعاون متعدد الجنسيات والبحوث الموجهة آلياً حول NPWT.
يوفر التحليل البيبليومتري إطاراً كمياً لرسم خرائط اتجاهات النشر، وشبكات التعاون، والمساهمين المؤثرين، والمجلات الأساسية، والدراسات عالية الاستشهاد، والموضوعات الناشئة. وعلى الرغم منما تم الإبلاغ سابقاً عن تحليل بيبليومتري لـ NPWT15، إلا أن التقييم الشامل لاتجاهات النشر، وشبكات التعاون، والمصادر المؤثرة، والتطور الموضوعي لا يزال محدوداً. وبناءً على ذلك، قامت هذه الدراسة برسم خرائط اتجاهات النشر، وشبكات التعاون، والمصادر المؤثرة، والتطور الموضوعي في أبحاث NPWT.
البروتوكول
يتكون سير العمل البيبليومتري الكامل من استرجاع الأدبيات، وتقييم الأهلية، والتحقق من النسخ المكررة والإصدارات، وفحص الصلة بشكل مستقل، وتوحيد البيانات، والتحليل الوصفي، وتحليل الشبكات، والتصور البياني. وتتوفر السجلات الخام، وقرارات الفحص، وحزمة التحليل القابلة للتكرار في الملف التكميلي 1، والملف التكميلي 2، والملف التكميلي 3، على التوالي.
مصدر البيانات واستراتيجية البحث
أُجري التحليل البيبليومتري باستخدام مجموعة Web of Science Core Collection (WoSCC)، مع اختيار Science Citation Index Expanded (SCI-EXPANDED/SCIE) كمصدر للبيانات. وقد اقتصرت فترة النشر من 1 يناير 1991 حتى 30 يونيو 2026؛ وبناءً على ذلك، تمثل مجموعة منشورات عام 2026 جزءًا من السنة لأن نافذة البحث انتهت في 30 يونيو 2026.
تم تطبيق استراتيجية البحث التالية: TS=("negative pressure wound therapy" OR "vacuum assisted closure" OR "vacuum sealing drainage") AND DOP=(1991-01-01/2026-06-30). استُخدم حقل الموضوع (TS) للبحث في العناوين، والملخصات، والكلمات المفتاحية للمؤلفين، والكلمات المفتاحية الإضافية (Keywords Plus)، بينما استُخدم حقل تاريخ النشر (DOP) لتقييد فترة النشر.
لم يتم تطبيق أي قيود على اللغة أو نوع المستند أثناء استرجاع السجلات. وقد أجري تقييم الأهلية بعد تصدير البيانات للحفاظ على عملية اختيار سجلات كاملة وقابلة للتدقيق. أُجري البحث النهائي في WoSCC بتاريخ 23 يوليو 2026، وأسفر عن 5,957 سجلاً، تم تصديرها في 24 يوليو 2026. تظهر استراتيجية البحث الكاملة، ومعلومات قاعدة البيانات والفهرس، والنطاق الزمني، وتواريخ البحث والتصدير، ومسار عمل الأهلية ملخصة في الشكل 1، وموثقة بالتفصيل في ملف README Reproducible Workflow.md الوارد في الملف التكميلي 3.
تصدير السجلات والتحقق الأولي من البيانات
تَمَّ تصدير السجلات المسترجعة من مجموعة Web of Science Core Collection مع اختيار السجل الكامل والمراجع المستشهد بها (Full Record and Cited References) كمحتوى للسجل، وملف نصي بسيط (Plain Text File) كصيغة للتصدير. ونظراً لأن مجموعة البيانات الإجمالية تجاوزت الحد الأقصى لعدد السجلات المسموح بها في عملية التصدير الواحدة، فقد تم تنزيل السجلات البالغ عددها 5,957 على 12 دفعة متتالية تشمل السجلات من 1–500، و501–1,000، و1,001–1,500، و1,501–2,000، و2,001–2,500، و2,501–3,000، و3,001–3,500، و3,501–4,000، و4,001–4,500، و4,501–5,000، و5,001–5,500، و5,501–5,957.
بعد عملية التصدير، تم التحقق من السجلات لضمان وجود الحقول البيبليوغرافية الأساسية المطلوبة للتحليلات اللاحقة، بما في ذلك رقم الوصول (UT)، ومعرف الكائن الرقمي (DOI)، والعنوان، والمؤلفين، والانتسابات المؤسسية، والمجلة المصدر، وسنة النشر (PY)، وتاريخ النشر (PD)، ونوع المستند (DT)، واللغة، والملخص، والكلمات المفتاحية للمؤلف، وKeywords Plus، وإجمالي الاستشهادات (TC)، وعدد مرات الاستخدام (U1 و U2)، والمراجع المستشهد بها (CR). وقد تم الحفاظ على ملفات التصدير الأصلية بصيغة النص البسيط دون تعديل، وهي مرفقة كـ الملف التكميلي 1.
نظرًا لأن تصدير النص البسيط من WoSCC لا يحتفظ بصفحة سجل البحث أو حقل مخصص لتاريخ النشر (DOP)، فقد تم توثيق سلسلة البحث الأصلية وتاريخ البحث في الشكل 1، والمخطوطة، وملف README Reproducible Workflow.md المضمن في الملف التكميلي 3. وقد تم الإبقاء على قيد DOP الأصلي المطبق أثناء استرجاع قاعدة البيانات ولم يتم استبداله بتصفية ما بعد التصدير بناءً على سنة النشر (PY)، أو تاريخ النشر (PD)، أو تاريخ الوصول المبكر (EA).
فحص نوع المستند وتقييم السحب
تم استيراد السجلات المسترجعة البالغ عددها 5,957 إلى مجموعة بيانات الفرز لتقييم الأهلية. وقد تم الإبقاء على مقالات البحث الأصلي والمقالات المرجعية دون تطبيق أي قيود لغوية. وشملت تصنيفات أنواع المستندات المؤهلة في Web of Science ما يلي: مقالة, مقال؛ ورقة بحثية في أعمال مؤتمر, مقالة؛ وصول مبكر, مراجعة، و مراجعة؛ وصول مبكرتم التعامل مع "الوصول المبكر" (Early Access) كحالة فهرسة وليس كنوع نشر مستقل، وذلك لتجنب التكرار في عد المنشور الواحد.
خلال عملية الفرز، تم استبعاد 1,078 سجلاً بسبب عدم أهلية أنواع المستندات، تلا ذلك إزالة 59 سجلاً متعلقاً بسحب الأوراق العلمية. وبعد فرز أنواع المستندات وتقييم السحوبات، تم الاحتفاظ بـ 4,820 سجلاً من نوع "مقال" و"مراجعة" لتقييم التكرارات والإصدارات. تتوفر السجلات المستبعدة والأسباب المحددة لكل سجل في ورقتي العمل DT_Exclusions_1078 وRetraction_Exclusions_59 في الملف التكميلي 2.
تقييم النسخ المكررة ونسخة النشر
أُجري تقييم السجلات المكررة وإصدارات النشر باستخدام رقم الوصول في Web of Science (UT) كمعرف أساسي للسجل. وفي الحالات التي كانت فيها السجلات المكررة أو ذات الصلة تحمل أرقام وصول مختلفة، تمت مقارنتها باستخدام معرف الكائن الرقمي (DOI)، والعنوان الموحد، والمؤلفين، والمجلة المصدر، وسنة النشر، والمجلد، والعدد، وأرقام الصفحات، والملخص، ونوع المستند، ومعلومات إصدار النشر. وبالنسبة لكل مجموعة من السجلات ذات الصلة، تم الاحتفاظ بإصدار النشر النهائي أو الأكثر ملاءمة، كما تم توثيق العلاقة بين السجلات التي تم الاحتفاظ بها والسجلات التي تم استبعادها.
تمت إزالة ما مجموعه 23 سجلاً مكرراً أو من إصدارات تم استبدالها، بما في ذلك تسعة إصدارات مستبدلة من مراجعات Cochrane و14 سجلاً تم التحقق من كونها مكررة، أو إعادة طباعة، أو تكرار في الفهرسة، أو إصدارات لغوية، أو إصدارات أخرى ذات صلة. وبعد تقييم السجلات المكررة وإصدارات النشر، تم الاحتفاظ بـ 4,797 سجلاً فريداً لفحص الملاءمة الموضوعية. وتتوفر أرقام الوصول للسجلات التي تم الاحتفاظ بها والمستبعدة، ومعايير التحقق من التكرار، والمبررات الخاصة بكل سجل في ورقة العمل Duplicate_Exclusions_23 ضمن Supplemental File 2.
فحص مستقل لمدى الصلة الموضوعية
أجرى باحثان مدربان فحصاً مستقلاً للملاءمة الموضوعية لـ 4,797 سجلاً فريداً. وقام كل مراجع بتقييم العنوان، والملخص، والكلمات المفتاحية للمؤلف، وKeywords Plus لكل سجل، وسجل قراراً مستقلاً بالاشتمال أو الاستبعاد مع ذكر المبرر الخاص بكل سجل قبل عملية التوفيق بين النتائج.
اعتُبرت السجلات مؤهلة عندما كان العلاج بالضغط السلبي للجروح (NPWT)، أو الإغلاق بمساعدة الفراغ (VAC)، أو التصريف بالختم الفراغي (VSD) يمثل التدخل الرئيسي أو المقارن، أو التقنية الخاضعة للتقييم، أو نتيجة سريرية أولية، أو موضوعاً لبحث ميكانيكي، أو موضوعاً لإرشادات أو إجماع، أو مكوناً رئيسياً في مسار إدارة الجروح. واستُبعدت السجلات عندما ذُكر NPWT أو VAC أو VSD فقط كمعلومات خلفية، أو أُدرجت فقط ضمن قائمة خيارات العلاج، أو ذُكرت فقط كعلاج فشل سابقاً أو عدم استخدام، أو استُخدمت فقط كإجراء إنقاذ عرضي، أو وُصفت فقط كمضاعفة أو متغير مصاحب، أو وقعت خارج الموضوع الرئيسي للدراسة، أو ظهرت فقط كمصطلح Keywords Plus إيجابي خاطئ.
تمت مقارنة قرارات الفحص المستقلة، حيث تم تحقيق اتفاق أولي لـ 4,782 سجلاً، بينما تم تحديد خلاف في 15 سجلاً. تم حل جميع التباينات من خلال المناقشة، وعند الضرورة، عن طريق التحكيم من قبل باحث ثالث. تم توثيق القرار النهائي والمبررات الداعمة لكل سجل متنازع عليه. وفي مجموعة البيانات التي خضعت للتدقيق، استُبعدت في النهاية جميع السجلات المتنازع عليها البالغ عددها 15 سجلاً، ولم يتبقَّ أي خلافات دون حل.
بعد إجراء فحص الصلة الموضوعية، تم استبعاد 734 سجلاً والاحتفاظ بـ 4,063 سجلاً للتحليل البيبليومتري. يحتوي الملف التكميلي 2 على قرارات كلا المراجعين، والمبررات الخاصة بكل مراجع، ومؤشرات عدم الاتفاق، وقرارات الإدراج النهائية، وبيانات الأدلة الداعمة، ومجموعة البيانات النهائية المكونة من 4,063 سجلاً.
تم التحقق داخلياً من عملية اختيار السجلات النهائية، مما أكد أن السجلات المسترجعة البالغ عددها 5,957 سجلاً تضمنت 1,137 سجلاً تم استبعادها بسبب نوع المستند أو حالة السحب، و23 سجلاً مكرراً أو تم استبداله، و734 سجلاً تم استبعادها أثناء فحص الصلة الموضوعية، و4,063 سجلاً تم إدراجها في التحليل البيبليومتري النهائي (5,957 = 1,137 + 23 + 734 + 4,063). يوضح الشكل 1 مخطط تدفق بنمط PRISMA لتوضيح عملية اختيار السجلات البيبليوغرافية. وبما أن هذه الدراسة عبارة عن تحليل بيبليومتري وليست مراجعة منهجية، فلم يتم إجراء تقييم كامل للنص الخاص بمخاطر الانحياز.
بناء مجموعة البيانات النهائية وتكامل المراجع المستشهد بها
تم اعتماد وتجميد مجموعة البيانات النهائية المكونة من 4,063 سجلاً في 24 يوليو 2026، واستُخدمت في جميع التحليلات الوصفية والاستشهاد والشبكات والتصوير اللاحقة. وقد تم التحقق من أن جميع السجلات المدرجة تحتوي على أرقام وصول فريدة من Web of Science (UTs).
لتمكين تحليلات المراجع المُستشهد بها، استُرجعت حقول المراجع المُستشهد بها (CR) من السجل الكامل المكون من 5,957 سجلاً السجل الكامل والمراجع المستشهد بها تصديرها ودمجها في مجموعة البيانات النهائية عن طريق المطابقة الدقيقة لمعرفات UT. وقد أُجريت عملية الدمج هذه دون تغيير عضوية مجموعة البيانات أو لقطة عدد الاستشهادات والاستخدامات المرتبطة بالتصدير الأصلي.
بعد عملية التكامل، تم التأكد من أن 4,048 سجلاً مدرجاً تحتوي على حقل مرجع مستشهد به (CR) مصدّر واحد على الأقل، بينما لم تحتوي 15 سجلاً على قائمة مراجع مستشهد بها في ملفات التصدير الخاصة بمجموعة Web of Science Core Collection. يتوفر نص برمجي لتكامل المراجع المستشهد بها وتقرير التدقيق المقابل له في الملف التكميلي 3.
تنظيف البيانات والتحليل الوصفي
تم توحيد أسماء المؤلفين، وأسماء المؤسسات، وعناوين المجلات، والمراجع المستشهد بها، والبلدان/المناطق، والكلمات المفتاحية باستخدام مسارد مصطلحات خاصة بكل وحدة. وقد طُبقت مسارد منفصلة على كل وحدة تحليلية، ولم يتم دمج مسارد المؤلفين، والمؤسسات، والبلدان، والكلمات المفتاحية، والمجلات، والمراجع المستشهد بها خلال عملية التوحيد.
تم تجميع مخرجات النشر السنوية وفقاً لسنة النشر (PY) المسجلة في مجموعة Web of Science Core Collection. وقد تم الاحتفاظ بالسنوات التي لم تشهد أي منشورات بين عامي 1991 و2026 في التحليل وعرضها كقيمة صفر لضمان استمرارية السلسلة الزمنية. كما صُنفت أنواع المستندات إلى خمس فئات متنافية، مع اعتبار الوصول المبكر (Early Access) حالة فهرسة وليس نوع نشر مستقلاً لتجنب التكرار في العد.
تم تجميع إجمالي الاستشهادات (TC)، وأعداد الاستخدام خلال الـ 180 يوماً السابقة (U1)، وأعداد الاستخدام منذ عام 2013 (U2) حسب سنة النشر. ونظراً لأن TC وU1 وU2 مؤشرات ديناميكية في مجموعة Web of Science Core Collection، فإن هذه المقاييس تمثل لقطة من قاعدة البيانات تم تصديرها في 24 يوليو 2026.
تَمّ إجراء معالجة البيانات، وإدارة سجلات الفرز، والتحليلات الإحصائية الوصفية، وإنشاء الشكل 2A،B والشكل 3A–C باستخدام لغة Python 3.12.10 مع مكتبات pandas 3.0.3 و openpyxl 3.1.5 و matplotlib 3.11.0، بالإضافة إلى برنامج Microsoft Excel.
تحليلات شبكة VOSviewer
أُجريت تحليلات الشبكة الببليومترية باستخدام برنامج VOSviewer الإصدار 1.6.21. تم استيراد مجموعة البيانات النهائية للنصوص العادية من Web of Science Core Collection كملفات قاعدة بيانات ببليومترية. طُبق نظام العد الكامل في جميع التحليلات، واستُخدم تطبيع قوة الارتباط لبناء الشبكات الببليومترية وتصورها.
تم تطبيق قوائم المصطلحات الخاصة بكل وحدة وفقاً للوحدة التحليلية قيد البحث. وأُجري تحليل التكرار المشترك للكلمات المفتاحية باستخدام كافة الكلمات المفتاحية بحد أدنى للتكرار قدره 30، مما نتج عنه شبكة تضم 158 عقدة و 6,468 حافة (الشكل 4A). كما أُجري تحليل تعاون المؤلفين باستخدام وحدة المؤلفين بحد أدنى قدره ست وثائق لكل مؤلف، مما أنتج شبكة مكونة من 51 عقدة و 134 حافة (الشكل 5A). وأُجري تحليل التعاون المؤسسي باستخدام وحدة المؤسسات بحد أدنى قدره 10 وثائق لكل مؤسسة، مما أسفر عن 109 عقد و 351 حافة (الشكل 5B). أما تحليل التعاون بين الدول فقد استخدم وحدة الدول بحد أدنى قدره سبع وثائق لكل دولة، مما أنتج شبكة تكميلية تحتوي على 50 عقدة و 438 حافة. وأُجري تحليل الاقتران الببليوغرافي للمجلات المصدر باستخدام وحدة المصادر بحد أدنى قدره 20 وثيقة لكل مصدر، مما نتج عنه 39 عقدة و 741 حافة (الشكل 6A). كما أُجري تحليل الاستشهاد المشترك للمراجع المُستشهد بها باستخدام وحدة المراجع المُستشهد بها بحد أدنى قدره 68 استشهاداً لكل مرجع، مما أنتج شبكة من 91 عقدة و 3,626 حافة (الشكل 6C).
تم الاحتفاظ بملفات خرائط VOSviewer وملفات الشبكات المقابلة لها والناتجة عن كل تحليل لضمان إمكانية إعادة الإنتاج. تتوفر معلمات الخرائط الكاملة، وقيم العتبة، والقواميس، وعمليات مراجعة الخرائط، وملفات خرائط وشبكات VOSviewer المحفوظة في الملف التكميلي 3.
تحليلات انفجار الكلمات المفتاحية والخرائط المزدوجة للمجلات باستخدام CiteSpace
أُجري تحليل اكتشاف طفرات الكلمات المفتاحية وتحليلات الخريطة المزدوجة للمجلات باستخدام برنامج CiteSpace الإصدار 7.0.R0 (64-bit, Advanced) مع مجموعة البيانات النهائية والمجمدة من Web of Science Core Collection. وقد نُفذ تحليل طفرات الكلمات المفتاحية باستخدام نطاق زمني من 1991 إلى 2026 مع شرائح زمنية مدتها سنة واحدة. واستُخلصت المصطلحات من حقول العنوان، والمستخلص، والكلمات المفتاحية للمؤلف، وحقول Keywords Plus. الكلمات المفتاحية تم اختيار [node type] كنوع للعقدة، وتم تعيين معيار الاختيار إلى أفضل ن = 50 لكل شريحة زمنية، ولم يتم تطبيق أي عملية تشذيب.
أُجري تحليل تدفق الاستشهادات (Citation burst analysis) باستخدام دالة Burstness، وتم الاحتفاظ بـ 25 كلمة مفتاحية ذات أقوى تدفقات استشهادات لعرضها في الشكل 4B. ونظرًا لأن البحث المرجعي شمل المنشورات حتى 30 يونيو 2026 فقط، فقد تم تفسير تدفقات الاستشهادات التي انتهت في عام 2026 على أنها تمتد إلى نهاية نافذة البحث الجزئية، بدلاً من تمثيلها لنشاط على مدار سنة تقويمية كاملة.
تم إنشاء تراكب خريطة مزدوجة للمجلات من نفس مجموعة بيانات Web of Science المجمدة لتصوير مسارات الاستشهاد بين تخصصات المجلات المستشهد بها والمستشهدة (الشكل 7). تتوفر إعدادات معاملات CiteSpace الكاملة ونتائج تفجر الكلمات المفتاحية لأعلى 25 كلمة محفوظة في الملف التكميلي 3.
التصورات البيانية على مستوى المؤسسة والمجلة والدولة
تم إنشاء تصورات بيبلومترية على مستوى المؤسسات والمجلات والدول باستخدام bibliometrix وبرامج تصور تكميلية. وجرى توحيد أسماء المؤسسات باستخدام بيانات الانتساب الموحدة الموصوفة أعلاه. بعد ذلك، تم بناء شبكة التعاون بناءً على علاقات التأليف المشترك بين المؤسسات التي استوفت حد النشر المحدد مسبقاً. تمثل العقد المؤسسات، وتشير الروابط إلى علاقات التعاون، بينما تشير الروابط الأكثر سمكاً إلى كثافة تعاون أعلى.
لفحص علاقات الاستشهاد بين المجلات الأكثر إنتاجية، تم تحديد الـ 15 مجلة ذات أعلى مخرجات نشر. وأُنشئت روابط استشهاد موجهة من المجلات المستشهدة إلى المجلات المُستشهد بها بعد استبعاد الاستشهادات الذاتية للمجلات. تضمنت الشبكة الناتجة 15 عقدة و200 حافة استشهاد موجهة غير ذاتية. ولأغراض التصوير البياني، تم عرض 56 رابط استشهاد فقط بأوزان لا تقل عن 45 في الشكل 6B. وتمثل هذه الشبكة علاقات الاستشهاد المباشرة بين الـ 15 مجلة الأكثر إنتاجية، ولا تشكل تحليلاً لنواة برادفورد أو خريطة اقتران ببليوغرافي.
أُجريت تحليلات الدول والمناطق باستخدام طريقة العد الكامل لجميع انتماءات المؤلفين، مع احتساب كل دولة مرة واحدة فقط لكل منشور. صُنفت المنشورات كمنشورات أحادية الدولة (SCP) أو منشورات متعددة الدول (MCP) بناءً على دولة المؤلف المسؤول وما إذا كانت مجموعة انتماءات المؤلفين الكاملة تمثل دولة واحدة أو عدة دول. وبالنسبة للتحليلات على مستوى الدول فقط، تم دمج تايوان وهونغ كونغ وماكاو تحت مسمى الصين، بينما تم الحفاظ على الأسماء المؤسسية الأصلية ومعلومات العناوين.
تم إنشاء تحليلات الدول/المناطق وتصورات SCP/MCP المعروضة في الشكل 8A،B باستخدام إصدار R 4.6.1 مع حزمتي bibliometrix (v5.4.1) و ggplot2 (v4.0.3)، بالإضافة إلى برنامج SCImago Graphica الإصدار 1.0.55.
قابلية التكرار والتحقق من البيانات
تم دعم إمكانية التكرار والتحقق الفني من خلال ثلاثة ملفات تكميلية متممة. الملف التكميلي 1 يحتوي على ملف التصدير الخام غير المعدل من مجموعة الويب للعلوم الأساسية (WoSCC) المستخدم كمصدر أساسي للبيانات. الملف التكميلي 2 توثق جميع قرارات الفحص المتعلقة بنوع المستندات، والسحب، والنسخ المكررة/إصدارات النشر، والملاءمة الموضوعية، مما يتيح إعادة إنتاج عملية اختيار الدراسات بشكل كامل.
يوفر الملف التكميلي 3 المواد المطلوبة لإعادة تنفيذ إجراءات تنظيف البيانات، ودمج المراجع المستشهد بها، والتحليلات الوصفية، وتحليلات شبكة VOSviewer، وتحليلات تدفق الكلمات المفتاحية عبر CiteSpace، وشبكة التعاون المؤسسي، وشبكة الاستشهادات المباشرة للمجلات، وإجراءات التحقق الفني. وقد تمت مقارنة المخرجات التي أُعيد تنفيذها مع أعداد العقد المؤرشفة، وأعداد الحواف، وإجمالي عمليات الفرز، وتغطية المراجع المستشهد بها، وملفات تدقيق مصادر الأشكال للتحقق من الاتساق التحليلي.
تم التأكد من أن جميع التحليلات استخدمت نفس مجموعة البيانات المجمدة التي تضم 4,063 سجلاً، ونفس اللقطة الزمنية لعدد الاستشهادات والاستخدامات التي تم الحصول عليها في 24 يوليو 2026. تتوفر إصدارات البرامج الموحدة والمعايير التحليلية الرئيسية في جدول المواد.
النتائج
Basic publication output and annual trend analysis
A total of 4,063 NPWT-related publications were included: 3,563 Articles (87.7%) and 500 Reviews (12.3%). These totals classify Early Access as an indexing status rather than a separate document type. Annual publication output is shown in Figure 2A, and the plotting categories used to display document types and Early Access status are shown in Figure 2B.
Publication output was minimal from 1991 to 2003 and began to rise in 2004. Growth accelerated after 2019, and output remained high during 2021–2025. This trajectory indicates sustained international interest in NPWT.
Figure 2B uses five mutually exclusive display categories to show Early Access status: Article (n = 3,340; 82.2%), Article Proceedings Paper (n = 203; 5.0%), Article Early Access (n = 20; 0.5%), Review (n = 492; 12.1%), and Review Early Access (n = 8; 0.2%). Thus, 3,340 + 203 + 20 = 3,563 Articles and 492 + 8 = 500 Reviews; the five plotting categories sum to the same 4,063 records included in the PRISMA flow diagram.
Citation and usage trend analysis
Citation and usage patterns were evaluated by publication year. U1 was defined as the 180-day recent usage count, and U2 was defined as cumulative usage since 2013. Aggregate U1 and U2 values are influenced by the number and age of publications in each annual cohort. Results are shown in Figure 3.
As shown in Figure 3A, the annual total citation count reached its highest level of 5,265 in 2017, followed by 5,117 in 2013, 4,818 in 2008, 4,810 in 2011, and 4,714 in 2014. In contrast, the cumulative citation counts for articles published from 2024 to 2026 appeared comparatively lower; however, this observation should be interpreted with caution, as it may reflect a restricted citation window rather than an intrinsic decline in scholarly influence. Regarding citation performance per publication, the highest average was recorded for papers published in 1997 (1,681 citations per paper); however, this value was based on only two highly cited foundational publications and was therefore strongly influenced by the small cohort size. Mean and median citation counts should be considered when comparing citation performance across publication-year cohorts.
Figure 3B presents the recent usage count (U1) of publications by publication year over the past 180 days. The U1 metric reflects recent platform activity associated with published articles. It should be noted that the total U1 counts are inherently affected by the number of publications per year. Across all included records, the total U1 count was 1,507. Publications from 2025 recorded the highest U1 count (372), followed by those from 2023 and 2024 (167 each), 2021 (140), and the partial 2026 cohort (121). These findings indicate relatively high recent platform activity for newer NPWT publication cohorts. However, U1 should not be interpreted as a direct measure of full-text downloads, readership, or scholarly impact.
Cumulative usage since 2013 (U2) reflects longer-term platform activity. As shown in Figure 3C, publications from 2017 recorded the highest cumulative usage count (3,284), followed by those from 2021 (2,502), 2014 (2,166), 2020 (2,080), and 2015 (1,953). The total U2 count across all included records was 31,766. Notably, publications from 2021 demonstrated considerable cumulative usage despite their relatively shorter availability period. All U1 and U2 usage data were exported from the Web of Science Core Collection on 24 July 2026, and the temporal availability of these metrics should be taken into account when interpreting recent publication cohorts. For publications issued before 2013, U2 includes only usage recorded since 2013 and therefore does not represent lifetime usage.
Keyword co-occurrence and burst analysis
Following the identification of overall publication output and trend dynamics, this study further recognized research hotspots and frontier evolution in the field through keyword co-occurrence and burst analyses, with the results presented in Figure 4.
A minimum occurrence threshold of 30 was applied to improve network readability. A total of 158 connected keywords were retained to construct the co-occurrence network, which contained 6,468 links and was divided into 6 clusters (Figure 4A). Cluster 1 (red cluster) primarily focused on the core technologies, mechanisms, and reconstructive applications of NPWT. The most prominent keywords included “negative pressure wound therapy,” “reconstruction,” “trial,” “dressings,” and “device,” representing research focusing on equipment, mechanisms and reconstructive applications. Other highly associated terms included “skin,” “VAC,” “wounds,” “wound control,” “system,” “flap,” “defects,” “fractures,” and “repair,” reflecting research related to NPWT techniques, underlying mechanisms, and wound management.
Cluster 2 (green cluster) was mainly associated with wound healing and diabetic foot ulcers. The central keyword was “wound healing,” accompanied by terms such as “diabetic foot ulcers,” “multicenter,” “ulcers,” “wound,” “care,” “debridement,” and “instillation.” This cluster primarily represented clinical investigations evaluating the therapeutic efficacy of NPWT in chronic wounds, particularly diabetic foot ulcers.
Cluster 3 (blue cluster) focused on surgical complications, outcomes, and infection prevention. The core keyword was “complications,” “surgery,” “surgical site infection,” “prevention,” and “outcomes.” This cluster reflected the application of NPWT in perioperative complication management, surgical site infection prevention, and outcome evaluation.
The remaining clusters further complemented the knowledge structure of the NPWT field. Cluster 4 (yellow) was related to open-abdomen and trauma management, with “management,” “open abdomen,” “trauma,” “closure,” and “abdominal compartment syndrome.” as representative keywords. Cluster 5 (purple) focused on infection and cardiothoracic surgical applications, centered on “infection,” “mediastinitis,” “cardiac surgery,” “risk factors,” and “poststernotomy mediastinitis.” Cluster 6 (light blue) represented complex infections and their clinical outcomes, centered on “mortality,” “necrotizing fasciitis,” “Fournier’s gangrene,” “diagnosis,” and “case report.” Collectively, these six clusters provide a comprehensive overview of the major research directions and knowledge structure within the NPWT field.
Keyword burst analysis revealed the temporal characteristics of the top 25 keywords with the strongest citation bursts from 1991 to 2026 (Figure 4B). The three keywords with the highest burst strengths were “wound control” (strength = 41.68, 1999–2011), “subatmospheric pressure” (strength = 32.63, 2001–2014), and “wound care” (strength = 28.20, 2021–2026). During the early period (1999–2014), research primarily focused on the fundamental principles of negative pressure technology, represented by “wound control,” “subatmospheric pressure,” “topical negative pressure,” “wound closure,” “fascial closure,” and “VAC therapy.”
During the intermediate period (2007–2018), research directions gradually shifted toward specific clinical applications, including soft tissue injury, poststernotomy mediastinitis, abdominal compartment syndrome, and randomized controlled trials. In recent years, research hotspots have further evolved toward “surgical site infection” (2019–2026), “risk” (2019–2026), “diabetic foot ulcer” (2020–2026), and “wound care” (2021–2026), highlighting the growing emphasis on wound management, infection prevention and control, and diabetic foot ulcer treatment. Furthermore, the emergence of “case report” (2021–2026) and “efficacy” (2024–2026) as burst keywords indicates that clinical outcome evaluation and the accumulation of clinical evidence from case-based studies have become emerging frontiers in this field.
Interdisciplinary characteristics
To further illustrate the distribution patterns of source and cited journals, a dual-map overlay analysis was performed, as shown in Figure 7. The citing journals are displayed on the left side of the map, whereas the cited journals are presented on the right side. The labels represent the major disciplinary areas covered by the journals, and the colored curves indicate the major citation pathways from citing journals to cited journals.
Several prominent citation pathways were identified in the current map. The most significant pathway originated from “Medicine, Medical, Clinical” on the left and extended toward “Health, Nursing, Medicine” on the right, indicating that NPWT studies published in clinical medical journals primarily drew upon knowledge from health, nursing, and medicine journals. In addition, citation links were observed from “Medicine, Medical, Clinical” toward “Molecular Biology, Genetics” and “Dermatology, Dentistry, Surgery,” reflecting the interdisciplinary connections between NPWT research and molecular biology, surgical science, and related clinical specialties. Overall, these citation patterns demonstrate the interdisciplinary nature of NPWT research, with citation links spanning clinical medicine, nursing and health sciences, molecular biology, dermatology, dentistry, and surgery.
Author and institutional collaboration networks
As shown in Figure 5A, analysis of the author collaboration network based on 4,063 included publications revealed a multi-centric collaborative landscape comprising five major clusters, with 51 connected authors and 134 collaborative links. The green cluster, centered around Ingemansson R with Malmsjö M and Lindstedt S as co-core authors, represented the largest collaborative team in the field, predominantly from Lund University, Sweden. The red cluster was centered on Gabriel A, Kim PJ, and Attinger CE and also included Gupta S and Stannard JP, bringing together major clinical investigators from North America and Europe. The blue cluster, centered on Orgill DP and Horch RE, was primarily associated with plastic and reconstructive surgery. The yellow cluster, led by Lavery LA, Armstrong DG, and Kirsner RS, concentrated on diabetic foot and wound management. The purple cluster was centered on Sjögren J and included Hetzer R, Petzina R, and Gustafsson L, reflecting collaboration in cardiothoracic surgery and mediastinitis management.
According to Price’s Law, the core author threshold was calculated as M = 0.749 × √Nmax, where Nmax = 60 and M was approximately 5.80. Authors with at least 6 publications were classified as core authors. A total of 212 authors met this threshold, representing 1.3% of the 16,615 authors in the dataset. Figure 5A shows collaboration among these core authors; isolated nodes and some labels may not be displayed. The most prolific authors were Ingemansson R (60 publications), Malmsjö M (54), Orgill DP (39), Horch RE (34), Lindstedt S (29), Armstrong DG and Gabriel A (21 each), and Attinger CE, Liu Y, and Yu AX (20 each). These publication counts are summarized in Table 1.
Regarding institutional collaboration, as shown in Figure 5B, the network revealed a multi-centric landscape comprising nine major clusters, with prominent hubs in Europe and the United States and a distinct cluster of Chinese institutions. The red cluster included Harvard University, Harvard Medical School, Brigham and Women’s Hospital, Heidelberg University, Duke University, and the University of Utah. The green cluster was centered on Lund University, Lund University Hospital, and Skåne University Hospital and included Griffith University, Uppsala University, the University of Queensland, Ghent University, the University of Amsterdam, and the University of Helsinki. The blue cluster consisted primarily of Chinese institutions, including Shanghai Jiao Tong University, Zhejiang University, Soochow University, Shandong University, Sun Yat-sen University, and Sichuan University. The yellow cluster included the University of Oxford, the University of Manchester, Karolinska Institutet, University College London, and the University of Warwick. The purple cluster comprised the University Hospital Zurich, Mayo Clinic, Hannover Medical School, and the medical universities of Vienna and Graz. The light-blue cluster included Wake Forest University, the University of Miami, Georgetown University, the University of Arizona, MedStar Georgetown University Hospital, and the University of Toronto. The remaining orange, brown, and pink clusters represented additional collaborative groups centered on institutions such as Chang Gung University, the University of São Paulo, the University of Pisa, the University of Maryland, Johns Hopkins University, and the Cleveland Clinic.
In the institutional network visualization, node size was proportional to institutional publication output, edges denoted collaborative relationships with line thickness reflecting collaboration intensity, and node color represented cluster affiliation. Lund University exhibited a notably large node size within the network, while MedStar Georgetown University Hospital occupied a relatively central position within its respective cluster. It should be noted that due to potential differences in institutional name standardization between the network visualization and the publication count statistics, node sizes should not be directly equated with rankings in Table 2. Cross-regional edges among different clusters indicated the presence of inter-regional collaborations in NPWT research. Overall, the author and institutional collaboration networks consistently demonstrated prominent European and U.S. research hubs with substantial participation from Asian institutions, while highlighting the pivotal roles of Swedish and American scholars in driving the field’s collaborative framework.
Core journals and highly cited papers
After identifying the core research contributors, this study further analyzed the publication platforms and milestone achievements in the NPWT field, as shown in Figure 6A. Node size corresponded to the number of publications in the NPWT field, with larger nodes indicating higher publication output; colors represented different journal clusters; and edges denoted bibliographic coupling relationships among journals based on shared references. The network comprised five major clusters. The green cluster represented the core wound care and plastic surgery cluster, with the International Wound Journal as the largest node, and also included the Journal of Wound Care, Wounds-A Compendium of Clinical Research and Practice, Plastic and Reconstructive Surgery, and Ostomy Wound Management, among other wound care and plastic surgery specialty journals. The blue cluster focused on orthopedics, trauma, and general clinical medicine, with Medicine as its largest node. The red cluster centered on general surgery and surgical infection, anchored by the Journal of Clinical Medicine. The purple cluster specializes in plastic, thoracic, and cardiothoracic surgery, with the Annals of Plastic Surgery as its core. The yellow cluster covered wound care, burns, plastic surgery, and pediatric surgery, with Advances in Skin & Wound Care as its largest node. Overall, wound care journals exhibited the greatest concentration of large nodes and closely interconnected relationships within the network.
As shown in Table 3, among the top 15 most productive journals, the International Wound Journal ranked first with 265 publications, followed by Wounds-A Compendium of Clinical Research and Practice with 192, and the Journal of Wound Care with 153. These three journals together contributed 610 publications, accounting for 15.0% of all included literature. The top five also included Plastic and Reconstructive Surgery (88) and the Annals of Plastic Surgery (82). In terms of disciplinary distribution, the top 15 journals were predominantly wound care and plastic surgery journals, with wound care journals collectively contributing 872 publications (21.5%), representing the primary publication channels for NPWT research. Regarding journal publication-country distribution, among the top 15 journals, 2 were published in the United Kingdom, while the United States accounted for 10 journals, reflecting that U.S.-based journals constituted the largest share of these publication venues. Figure 6B illustrates the direct citation relationships among these core journals.
In addition to journal-level metrics, the most influential individual publications were further examined. As shown in Table 4, the most highly cited paper was the clinical study by Argenta LC et al. (1997) published in the Annals of Plastic Surgery (TC = 1,708), which introduced vacuum-assisted closure as a new method for wound control and treatment. The second most cited work was the foundational animal study by Morykwas MJ et al. (1997), also published in the Annals of Plastic Surgery (TC = 1,654), which investigated the basic mechanisms underlying vacuum-assisted closure. The third to fifth most cited papers were published in Advances in Therapy (2017, TC = 1,641), Intensive Care Medicine (2013, TC = 1,033), and The Lancet (2005, TC = 700), covering chronic wound management, clinical practice guidelines for intra-abdominal hypertension and abdominal compartment syndrome, and NPWT after partial diabetic foot amputation, respectively. The publication years of highly cited papers ranged from 1997 to 2021, with the most recent paper addressing moist wound healing using commonly available dressings. Collectively, these findings suggested that NPWT research was anchored in a core group of wound care journals, while the most influential works span both foundational experimental and clinical studies, reviews, randomized controlled trials, and clinical guidelines that have shaped the field’s knowledge base.
As shown in Figure 6C, the co-citation network of cited references was categorized into five clusters. The red cluster, positioned mainly on the left and in the center of the network, was anchored by the 1997 study by Morykwas MJ et al., which represented one of the foundational works in the field with a notably large node size; the cluster predominantly included foundational experimental and early clinical studies, with a focus on the mechanistic basis and clinical applications of NPWT. The green cluster, situated from the center to the upper-right, encompassed research on the mechanisms and wound-repair effects of NPWT, with the 2004 study by Wackenfors A et al. as a core node, along with a series of publications by Kim PJ. The yellow cluster, located in the lower-left region, was centered on cardiothoracic applications of NPWT, with a focus on the management of sternal wound infections. The purple cluster was distributed throughout the lower part of the network and included studies on temporary abdominal closure and open-abdomen management. The blue cluster, distributed mainly on the right and lower-right, was built around the body of work by Stannard JP et al., focusing on traumatic surgical scenarios, including open fractures and surgical site infections. Overall, the network exhibited a temporal evolution from fundamental mechanistic principles toward specialized clinical applications in wound repair, trauma, cardiothoracic surgery, and open-abdomen management.
Country/region output and collaboration landscape
Country and regional outputs are shown in Figure 8. Figure 8A uses countries identified from all contributing authors' affiliations, allowing a single publication to be attributed to multiple countries. The United States ranked first, followed by China, Germany, the United Kingdom, Italy and Japan. Figure 8B uses the corresponding author’s country and classifies records as Single-Country Publications (SCP) or Multi-Country Publications (MCP). The United States led both SCP and MCP output. China ranked second in total output but had a substantially lower MCP share, indicating a comparatively low proportion of internationally coauthored publications. European and selected Asian countries produced fewer publications but were also represented among the leading countries with corresponding authors.
Because Figure 8A uses all-author affiliations and Figure 8B uses the corresponding author’s country, country totals differ between panels. SCP denotes publications whose authors were affiliated with one country; MCP denotes publications involving authors from more than one country.
Data availability
The raw Web of Science Core Collection export (Supplemental File 1), record-level screening log (Supplemental File 2), and reproducible workflow, code, and analysis-output package (Supplemental File 3) are provided with the paper. Supplemental File 3 contains the software environment, analysis parameters, scripts, unit-specific thesauri, derived data tables, saved VOSviewer and CiteSpace outputs, and figure-source and audit files. Public redistribution and reuse of proprietary Web of Science records remain subject to Clarivate’s applicable licensing terms.
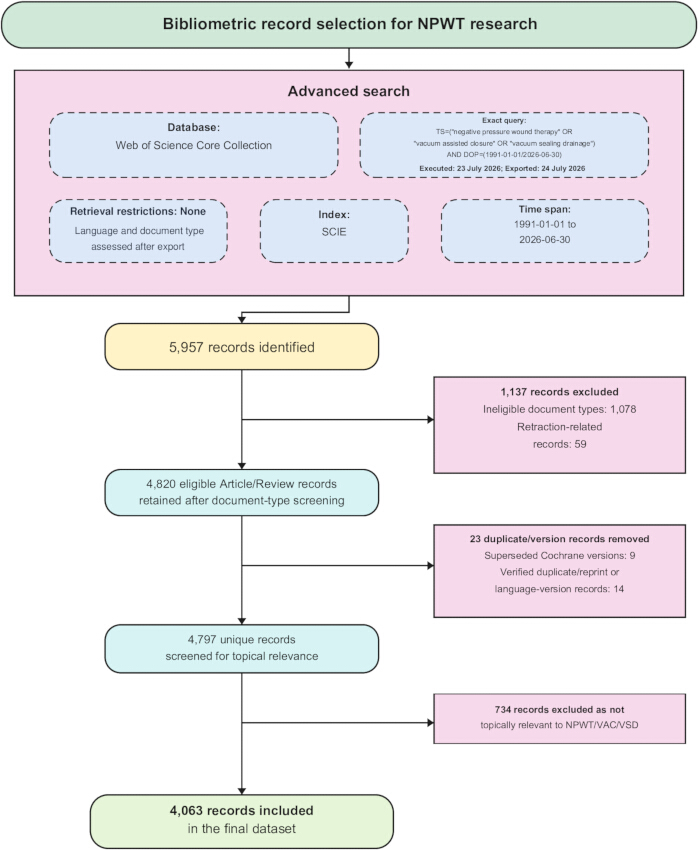
Figure 1. PRISMA-style flow diagram for the NPWT bibliometric analysis. PRISMA was used solely to display the record-selection process; this study was not conducted as a systematic review. The diagram summarizes record identification, document-type screening, topic-relevance screening, and final inclusion. The WoSCC search was conducted on 23 July 2026, and the records were exported on 24 July 2026; Early Access records were assigned to their underlying document type. Abbreviations: NPWT = negative pressure wound therapy; PRISMA = Preferred Reporting Items for Systematic Reviews and Meta-Analyses; WoSCC = Web of Science Core Collection; VAC = vacuum-assisted closure; VSD = vacuum sealing drainage. Please click here to view a larger version of this figure.
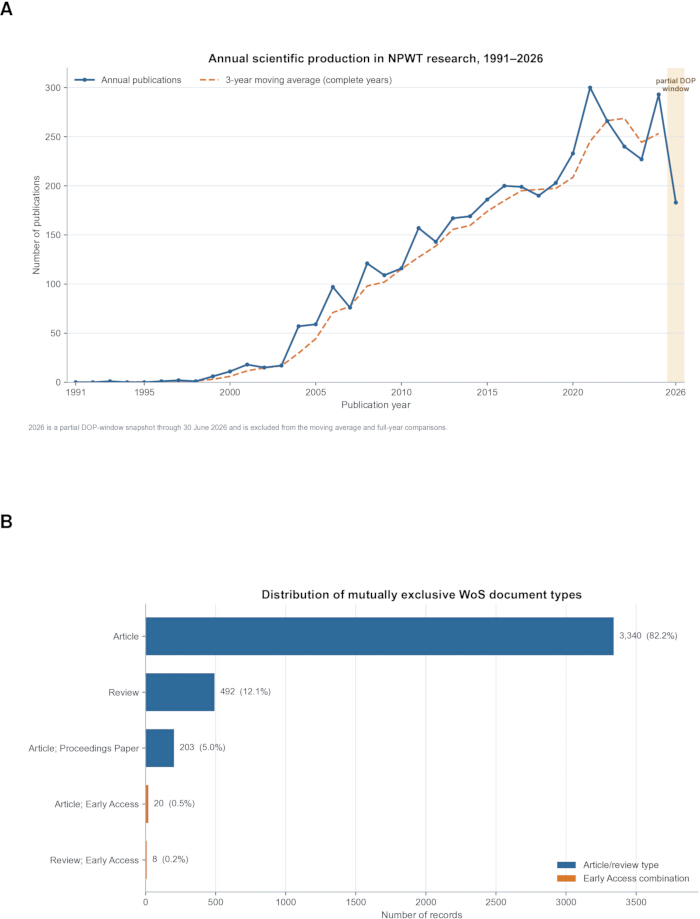
Figure 2. Annual publication output and document-type distribution of NPWT publications from 1991 to 2026. (A) Annual publication volume. (B) Article and Review categories, with Early Access status shown separately. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.
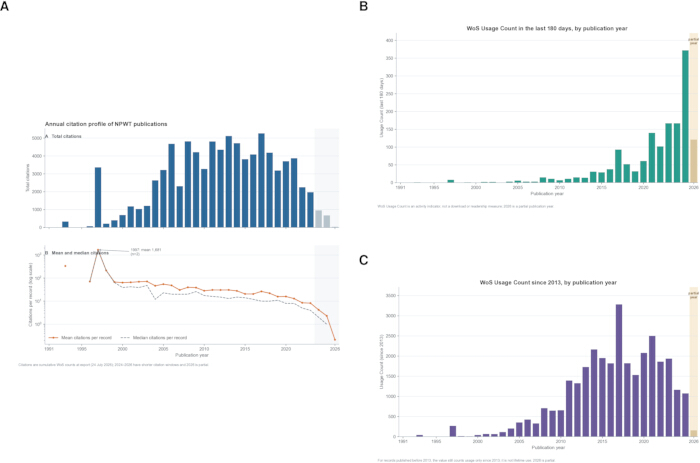
Figure 3. Citation and usage trends of NPWT publications. (A) Total, mean, and median citations by publication year. (B) Recent usage over 180 days. (C) Cumulative usage since 2013. Data were exported from WoSCC on 24 July 2026; recent cohorts have shorter citation and usage windows. Abbreviations: NPWT = negative pressure wound therapy; U1 = 180-day recent usage count; U2 = cumulative usage count since 2013; WoSCC = Web of Science Core Collection. Please click here to view a larger version of this figure.
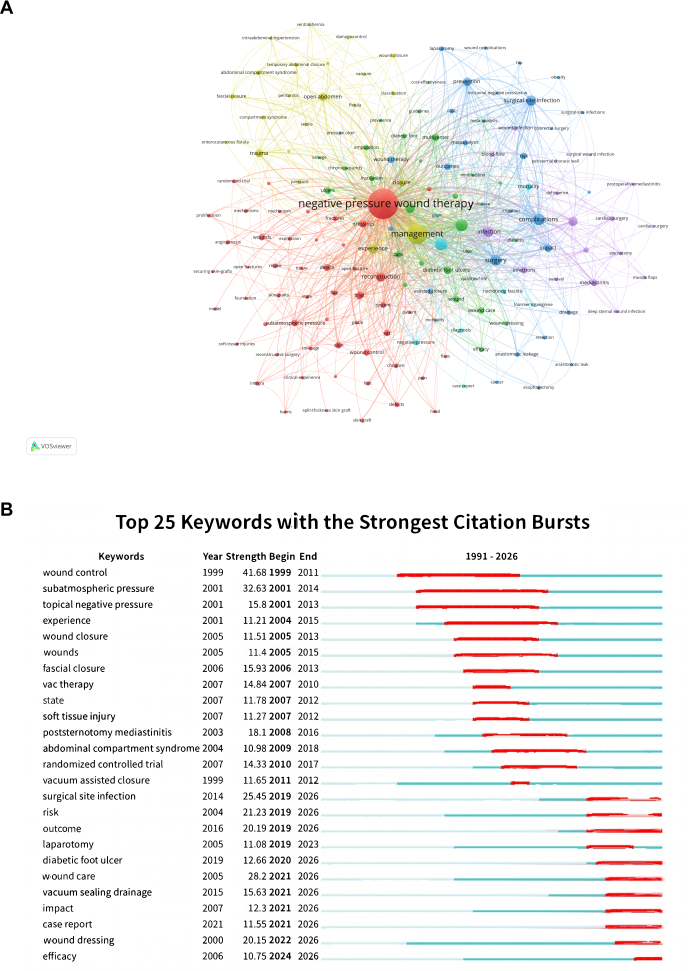
Figure 4. Keyword co-occurrence network and the top 25 burst keywords. (A) Keyword co-occurrence network using a frequency threshold of ≥30. (B) Temporal map of the 25 keywords with the strongest citation bursts. Please click here to view a larger version of this figure.
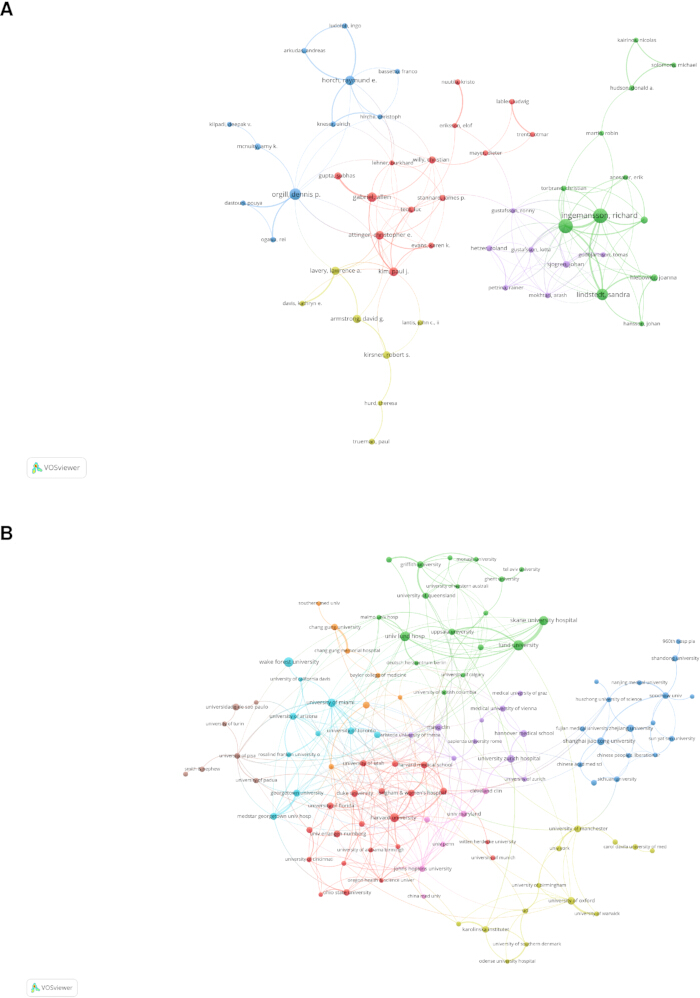
Figure 5. Author and institutional collaboration networks. (A) Core-author collaboration network, with node size proportional to publication count. (B) Institutional collaboration network. Please click here to view a larger version of this figure.
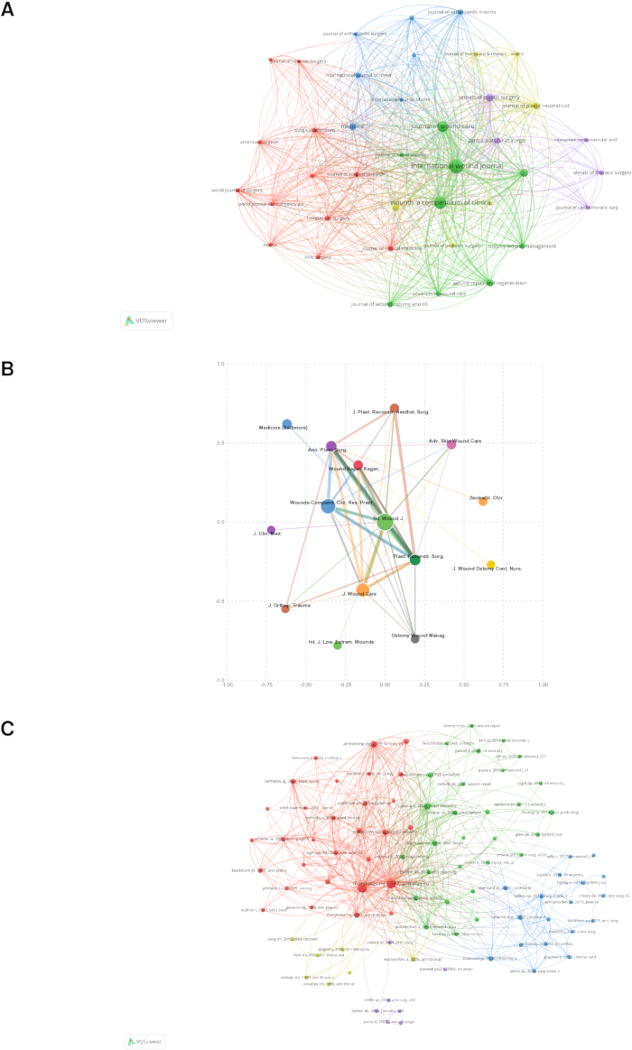
Figure 6. Publication journals and core-literature citation characteristics in NPWT research. (A) Journals with ≥20 NPWT publications. (B) Citation network of the 15 most productive journals. (C) Co-citation network of cited references. Network maps were generated using full counting. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.

Figure 7. Dual-map overlay analysis of journals in NPWT research. The left side represents citing journals, and the right side represents cited journals. Curves indicate major citation pathways; curve width reflects citation-flow strength. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.
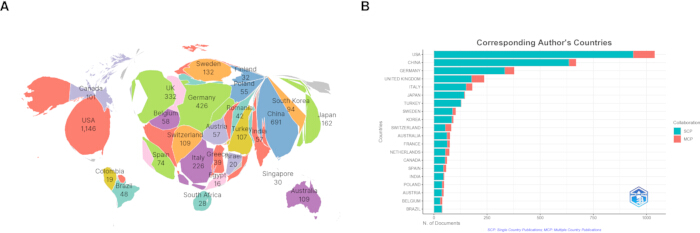
Figure 8. Global country/region output and international collaboration. (A) Publication distribution based on all author affiliations. (B) SCP and MCP distributions based on the corresponding author's country. Abbreviations: MCP = multi-country publications; SCP = single-country publications. Please click here to view a larger version of this figure.
| Rank | Author | Publications | Citations | Country |
| 1 | Ingemansson, Richard | 60 | 2747 | Sweden |
| 2 | Malmsjö, Malin | 54 | 2215 | Sweden |
| 3 | Orgill, Dennis P. | 39 | 3149 | United States |
| 4 | Horch, Raymund E. | 34 | 724 | Germany |
| 5 | Lindstedt, Sandra | 29 | 319 | Sweden |
| 6 | Gabriel, Allen | 21 | 962 | United States |
| 7 | Armstrong, David G. | 21 | 1494 | United States |
| 8 | Liu, Y | 20 | 285 | China |
| 9 | Yu, AX | 20 | 452 | China |
| 10 | Attinger, Christopher E. | 20 | 1662 | United States |
Table 1: Top 10 authors by publication output in NPWT research. The table presents publication and citation counts for the 10 most prolific authors. Abbreviations: NPWT = negative pressure wound therapy.
| Rank | Institution | Publications | Citations | Country |
| 1 | Lund University | 99 | 4291 | Sweden |
| 2 | Skane University Hospital | 94 | 4139 | Sweden |
| 3 | Harvard University | 83 | 5271 | United States |
| 4 | Harvard University Medical Affiliates | 77 | 5085 | United States |
| 5 | University of Texas System | 72 | 2540 | United States |
| 6 | University System of Ohio | 62 | 1339 | United States |
| 7 | Wake Forest University | 53 | 2975 | United States |
| 8 | Harvard Medical School | 52 | 3608 | United States |
| 9 | Brigham & Women's Hospital | 49 | 4127 | United States |
| 10 | University of California System | 46 | 1459 | United States |
Table 2: Top 10 institutions by publication output in NPWT research. The table presents publication and citation counts for the 10 most productive institutions. Abbreviation: NPWT = negative pressure wound therapy.
| Rank | Journal | Publications | Share |
| 1 | International Wound Journal | 265 | 6.52% |
| 2 | Wounds-A Compendium Of Clinical Research And Practice | 192 | 4.73% |
| 3 | Journal Of Wound Care | 153 | 3.77% |
| 4 | Plastic And Reconstructive Surgery | 88 | 2.17% |
| 5 | Annals Of Plastic Surgery | 82 | 2.02% |
| 6 | Medicine | 66 | 1.62% |
| 7 | Wound Repair And Regeneration | 64 | 1.58% |
| 8 | Advances In Skin&Wound Care | 61 | 1.50% |
| 9 | Journal Of Plastic Reconstructive And Aesthetic Surgery | 58 | 1.43% |
| 10 | Zentralblatt Fur Chirurgie | 51 | 1.26% |
| 11 | Journal Of Wound Ostomy And Continence Nursing | 48 | 1.18% |
| 12 | Ostomy Wound Management | 46 | 1.13% |
| 13 | International Journal Of Lower Extremity Wounds | 43 | 1.06% |
| 14 | Journal Of Clinical Medicine | 42 | 1.03% |
| 15 | Journal Of Orthopaedic Trauma | 41 | 1.01% |
Table 3: The 15 main journals publishing NPWT research. The table presents publication counts and shares of the complete dataset. Abbreviation: NPWT = negative pressure wound therapy.
| Rank | Title | Year | Journal | First author | Total citations | ||
| 1 | Vacuum-assisted closure:A new method for wound control and treatment:Clinical experience | 1997 | Annals Of Plastic Surgery | Argenta, LC | 1708 | ||
| 2 | Vacuum-assisted closure:A new method for wound control and treatment:Animal studies and basic foundation | 1997 | Annals Of Plastic Surgery | Morykwas, MJ | 1654 | ||
| 3 | Chronic Wound Healing:A Review of Current Management and Treatments | 2017 | Advances In Therapy | Han, G | 1641 | ||
| 4 | Intra-abdominal hypertension and the abdominal compartment syndrome:updated consensus definitions and clinical practice guidelines from the World Society of the Abdominal Compartment Syndrome | 2013 | Intensive Care Medicine | Kirkpatrick, AW | 1033 | ||
| 5 | Negative pressure wound therapy after partial diabetic foot amputation:a multicentre,randomised controlled trial | 2005 | Lancet | Armstrong, DG | 700 | ||
| 6 | Update on management of diabetic foot ulcers | 2018 | Annals Of The New York Academy Of Sciences | Everett, E | 671 | ||
| 7 | Pathogenesis and Treatment of Impaired Wound Healing in Diabetes Mellitus:New Insights | 2014 | Advances In Therapy | Baltzis, D | 587 | ||
| 8 | Vacuum-assisted closure:Micro deformations of wounds and cell proliferation | 2004 | Plastic And Reconstructive Surgery | Saxena, V | 545 | ||
| 9 | Moist Wound Healing with Commonly Available Dressings | 2021 | Advances In Wound Care | Nuutila, K | 516 | ||
| 10 | Comparison of negative pressure wound therapy using vacuum-assisted closure with advanced moist wound therapy in the treatment of diabetic foot ulcers:A multicenter randomized controlled trial | 2008 | Diabetes Care | Blume, PA | 451 | ||
Table 4: The 10 most-cited records included in the NPWT bibliometric dataset. Citation counts were exported from the Web of Science Core Collection on 24 July 2026. Abbreviation: NPWT = negative pressure wound therapy.
Supplemental File 1. Raw Web of Science Core Collection export. The records were retrieved using the reported search strategy on 23 July 2026 and exported as plain text on 24 July 2026.Please click here to download this file.
Supplemental File 2. Literature screening log for the NPWT bibliometric dataset. The spreadsheet provides record-level inclusion and exclusion decisions for the retrieved literature. Abbreviation: NPWT = negative pressure wound therapy.Please click here to download this file.
Supplemental File 3. Reproducible workflow, code, and analysis outputs for the NPWT bibliometric dataset. The ZIP archive contains the software environment, analysis parameters, data preparation and validation scripts, unit-specific thesauri, derived data tables, saved VOSviewer and CiteSpace outputs, and figure-source and audit files. Abbreviation: NPWT = negative pressure wound therapy.Please click here to download this file.
المناقشة
كشف التحليل عن توسع مستمر في أبحاث العلاج بالضغط السلبي للجروح (NPWT) وانتقال موضوعي واضح من الآليات التأسيسية إلى التحسين السريري18. وقد ركزت الدراسات المبكرة على الضغط دون الجوي، وتروية الأنسجة، والاستجابات البيولوجية. فعلى سبيل المثال، وجد Morykwas وآخرون (1999) أن تطبيق الضغط السلبي على الحروق ذات السماكة الجزئية في نماذج الخنازير منع تعمق الجرح، مما كشف عن نافذة علاجية مدتها 12 ساعة بعد الإصابة، حيث كانت فترة تطبيق قصيرة تصل إلى 6 ساعات كافية لوقف تطور الإصابة19. كما تناولت الأعمال اللاحقة مسارات رعاية الجروح، وعدوى موقع الجراحة، وقرح القدم السكرية، والضمادات المتقدمة20، والتروية السائلة (instillation)21,22. ويؤكد التوافق بين تجميع الكلمات المفتاحية وكشف الطفرات (burst detection) التقدم التسلسلي للأبحاث — من الاستقصاء الميكانيكي والترجمة السريرية إلى تحسين الضمادات، ومنع العدوى، وتقييم النتائج السريرية 15. ومن الناحية المنهجية، يكشف التجميع عن بنية المعرفة الثابتة في هذا المجال، بينما يرصد كشف الطفرات التحولات الموضوعية الديناميكية؛ ويعزز التوافق بين هذين البعدين صحة المسار المرصود. أما من حيث المحتوى، فإن هذا التقدم يرتكز على الأدبيات العلمية: حيث تركزت أبحاث NPWT المبكرة على الاستكشاف الميكانيكي، وهو ما يتجسد في العمل التأسيسي لـ Morykwas و Argenta (1997). وتناولت الدراسات اللاحقة بشكل متزايد كيف تؤثر خصائص الضمادة — مثل حجم مسام الرغوة (400–600 µm) — على التشوه الدقيق والاستجابات الخلوية، إلى جانب تقييمات مقارنة بين الأنظمة ذات الاستخدام الواحد والأنظمة التقليدية القائمة على العبوات23. وقد توسع الفهم الميكانيكي المعاصر من نموذج "زيادة التروية" المبسط نحو أطر أكثر دقة لتحويل الإشارات الميكانيكية (mechanotransduction) وتأثيرات منطقة التأثير (zone-of-influence)24. وبالمثل، أكد التصوير الببليومتري لـ NPWT الذي أجراه Deng وآخرون (2024) هذا التحول الموضوعي من الآليات الأساسية نحو التطبيقات السريرية وتحسين المواد، وهو ما يوازي النتائج في أبحاث رعاية الحروق حيث دخل NPWT تدريجياً في تصنيفات الكلمات المفتاحية عالية التكرار على مدى فترة 22 عاماً25,26. وبناءً على ذلك، تتقارب كل من الهياكل الموضوعية القائمة على التجميع والجبهات الناشئة المكتشفة عبر الطفرات حول مسار تطوري واضح — من فهم الآليات إلى تحسين التطبيقات وتطوير التدخلات المادية15.
بناءً على النتائج البيبليومترية، لوحظت اختلافات جغرافية واضحة. حيث ساهمت الصين بشكل كبير في حجم المنشورات واستفادت من المجموعات السريرية الضخمة وبيئات العناية بالجروح المتنوعة، وهو ما يتفق مع التحليلات البيبليومترية الحديثة التي أظهرت ريادة الصين في الإنتاجية البحثية المتعلقة بالتئام الجروح، كما أورد Xing et al. (2025) في تحليل بيبليومتري لهندسة الأنسجة المطبقة على التئام الجروح 27. ومع ذلك، هيمن على إنتاجها الدراسات السريرية أحادية الدولة (SCP)، بينما ظلت التعاونات متعددة الجنسيات، والأبحاث الميكانيكية الأساسية، وتطوير المواد الحيوية، والتجارب المنسقة دولياً محدودة نسبياً. في المقابل، شغلت المجموعات الأمريكية والأوروبية مواقع مركزية في الشبكات العابرة للمؤسسات طويلة الأمد، وساهمت بشكل أوسع في الأبحاث الميكانيكية وتطوير الأجهزة والأبحاث متعددة المراكز. ومن الجدير بالذكر أن البيانات البيبليومترية حول هندسة الأنسجة في التئام الجروح تظهر أن نسبة SCP/MCP في الصين (1,708/343) تشير إلى أن التعاونات متعددة الجنسيات لا تمثل سوى جزء بسيط من إجمالي إنتاجها، بينما يظهر الإنتاج الأمريكي نسبة أعلى من المنشورات التعاونية الدولية 27. وفي ظل هذا السياق، حققت الصين مع ذلك تقدماً في ابتكار أجهزة NPWT والوصول إلى الأسواق الدولية؛ حيث حصلت شركة Foryou Medical Electronics على تصريح 510(k) من إدارة الغذاء والدواء الأمريكية (FDA) لجهاز NPWT الخاص بها (K113236) في عام 201328. وفي عام 2024، أفادت الشركة المصنعة أن مضخات NPWT وأطقم الضمادات الخاصة بها قد حصلت على شهادة اعتماد بموجب لائحة الأجهزة الطبية للاتحاد الأوروبي من SGS29. ويمثل تحويل هذه الإنجازات التنظيمية إلى تحقيقات سريرية متعددة الجنسيات توجهاً مهماً للتطوير المستقبلي.
أشار التحليل المؤسسي إلى أن المساهمين الرئيسيين في أبحاث NPWT كانوا متركزين في السويد والولايات المتحدة. وحدد تحليل إنتاجية المؤلفين كلاً من Ingemansson R (60 منشوراً) و Malmsjö M (54 منشوراً) كأكثر المؤلفين غزارة في الإنتاج، يليهم Orgill DP (39 منشوراً). تسلط هذه النتائج الضوء على المساهمات البارزة للمجموعات البحثية السويدية والأمريكية في مجال NPWT.
أظهر تحليل المجلات أن الأبحاث المتعلقة بـ NPWT كانت مركزة في مجلات رعاية الجروح، والجراحة التجميلية، والمجلات السريرية ذات الصلة. وكانت المجلات الأكثر إنتاجية هي International Wound Journal وWounds-A Compendium of Clinical Research and Practice وJournal of Wound Care. كما كانت معظم المجلات ضمن قائمة أفضل 15 مجلة تتخذ من الولايات المتحدة أو المملكة المتحدة مقراً لها، مما يعكس الدور البارز لهذين البلدين في نشر أبحاث NPWT. وقد تساعد هذه النتائج الباحثين في تحديد المجلات التي تنشر أعمالاً بانتظام في هذا المجال، على الرغم من أن اختيار المجلة يجب أن يأخذ في الاعتبار أيضاً النطاق، وتصميم الدراسة، والقراء المستهدفين.
تناولت المنشورات الأكثر استشهاداً إدارة الجروح المزمنة، وضمادات الجروح المتقدمة، ومتلازمة الحيز البطني، وقرح القدم السكرية، والتطبيقات السريرية للعلاج بسحب الضغط السلبي للجروح (NPWT). ويظهر هذا النمط أن القاعدة المعرفية لهذا المجال تمتد إلى ما هو أبعد من الدراسات الخاصة بالأجهزة لتشمل بيولوجيا التئام الجروح على نطاق أوسع، والإرشادات السريرية، وإدارة الجروح متعددة التخصصات. وعلى الرغم من وضع البروتوكولات الأساسية لـ NPWT، لا يزال هناك عدم يقين فيما يتعلق باختيار الضمادة، ومعايير الضغط المثلى، والاستخدام الموحد في مواقع تشريحية محددة.
عززت نتائج الكلمات المفتاحية التسلسل التطوري ذاته. حيث تميزت المراحل المبكرة بالضغط دون الجوي، والتروية، والتجارب العشوائية؛ بينما برزت لاحقاً مجالات العناية بالجروح، وضمادات الجروح، وعدوى موقع الجراحة، وقرح القدم السكري، والفعالية. ويشير هذا التحول إلى أن المجال ينتقل من إثبات الآلية نحو تقديم سريري موحد، والابتكار في المواد، واستراتيجيات متكاملة لإدارة الجروح.
أصبح دمج العلاج بالضغط السلبي للجروح (NPWT) مع ضمادات محسنة وبروتوكولات معيارية للعناية بالجروح توجهاً سريرياً هاماً. وتتمتع كل من ضمادات الرغوة والضمادات الشاشية بمزايا وعيوب عملية، ولكن تظل الأدلة المقارنة عالية الموثوقية التي تدعم الاختيار الفردي محدودة. ومن المرجح أن يتضمن التطوير المستقبلي مواد حيوية محسنة، وأنظمة مدعومة بالمستشعرات، وبروتوكولات علاجية أكثر دقة مصممة وفقاً لخصائص الجرح ومخاطر المريض.
ركزت معظم المنشورات في مجموعة البيانات على التطبيقات السريرية، وفعالية العلاج، ومكافحة العدوى، وإدارة المضاعفات، وتحسين رعاية الجروح. ومقارنة بذلك، كان البحث الميكانيكي حول الاستجابات الخلوية والمسارات الجزيئية والتفاعلات بين المواد والأنسجة أقل بروزاً. يجب أن تجمع الدراسات المستقبلية بين التجارب السريرية الصارمة والبحث التجريبي لتوضيح كيفية تأثير NPWT على الالتئام ومكافحة العدوى. وتشمل الأولويات تحديد المؤشرات الحيوية للاستجابة المبكرة، وتطوير ضمادات جروح ذكية، ووضع استراتيجيات علاجية مخصصة من خلال التعاون متعدد التخصصات.
يجب الإقرار بوجود عدة قيود؛ حيث شملت الدراسة فقط المنشورات المفهرسة في Science Citation Index Expanded التابع لـ WoSCC، ولم يتم تطبيق أي قيود لغوية، لذا فمن المحتمل أن تكون بعض المنشورات ذات الصلة المفهرسة حصرياً في قواعد بيانات أخرى قد أغفلت. وعلى الرغم من قيام مراجعين مدربين بفحص السجلات واستخراجها بشكل مستقل، إلا أن احتمال حدوث أخطاء تصنيفية متبقية يظل قائماً. كما أن الاختلافات في أسماء المؤلفين والمؤسسات والمجلات قد تكون أثرت على بناء الشبكة رغم إجراء عملية التوحيد القياسي. وتعتبر مؤشرات الاقتباس والاستخدام معتمدة على الزمن، مما يضع المنشورات الحديثة في موقف غير مؤاتٍ. وأخيراً، تصف المؤشرات البيبليومترية أنماط النشر والتأثير، ولكنها لا تقيس الجودة المنهجية أو الفعالية السريرية بشكل مباشر.
لقد تطور البحث في مجال العلاج بالضغط السلبي للجروح (NPWT) من الدراسات التأسيسية حول الضغط والتروية وآليات التئام الجروح نحو الرعاية السريرية للجروح، والوقاية من العدوى، والضمادات المتقدمة، وتقييم النتائج. وقد تمركز التعاون الدولي في الأدبيات المفهرسة حول الشبكات الأمريكية والأوروبية. وساهمت الصين بحجم كبير من المطبوعات، بينما كانت نسبة المؤلفين المراسلين في منشوراتها الذين شاركوا في تأليف دولي أقل نسبياً. يصف هذا الاستنتاج هيكل التعاون في الأدبيات المفهرسة ولا ينبغي تفسيره على أنه تقييم لجودة البحث. وتشمل الفرص المستقبلية في هذا المجال إجراء تجارب سريرية صارمة، ودراسات الآليات الانتقالية، والمواد الحيوية الذكية، وبروتوكولات موحدة لمواقع محددة، وتعاون أوسع نطاقاً عابر للأقاليم.
الإفصاحات
يصرح المؤلفون بعدم وجود أي تضارب في المصالح.
شكر وتقدير
تم دعم هذه الدراسة من قبل المؤسسة الوطنية للعلوم الطبيعية في الصين (برنامج الشباب، رقم 82305237)، ومنحة باحث لونغيي (برنامج الشتلات، رقم YM2021025)، والتخصص الرئيسي رفيع المستوى - تعزيز بناء نظام أبحاث الطب الصيني التقليدي القائم على الأدلة (طب الشرج والمستقيم في الطب الصيني التقليدي)، ومركز شنغهاي لأبحاث أمراض الجيوب والناسور (رقم 2023ZZ02003).
المواد
| الاسم | الشركة | رقم فهرسي | التعليقات |
|---|---|---|---|
| `CiteSpace 7.0.R0 (64-bit) Advanced | Chaomei Chen, Drexel University, USA | https://citespace.podia.com/ | استُخدم لتحليل انفجار الكلمات المفتاحية (keyword burst analysis) والتراكب الخرائطي المزدوج. الإعدادات: 1991-2026، شرائح زمنية مدتها سنة واحدة، نوع العقدة كلمات مفتاحية، Top N = 50 لكل شريحة، بدون تشذيب، وأقوى 25 مصطلحاً منفجراً. |
| Python 3.12.10; pandas 3.0.3; openpyxl 3.1.5; matplotlib 3.11.0; NetworkX 3.6.1; Microsoft Excel 16.0.20131.20154 | Python Software Foundation; pandas, openpyxl, Matplotlib, and NetworkX development teams; Microsoft Corporation | https://www.python.org/; https://pandas.pydata.org/; https://openpyxl.readthedocs.io/; https://matplotlib.org/; https://networkx.org/; https://www.microsoft.com/microsoft-365/excel | استُخدمت لعمليات الفرز، وإزالة التكرار، وتدقيق البيانات، والتحليلات الوصفية، وإنشاء الأشكال. احتوت مجموعة البيانات النهائية على 4,063 سجلاً. استُخدم NetworkX لإنشاء شبكة الاستشهاد المباشر لأفضل 15 مجلة (15 عقدة؛ 56 حافة معروضة بأوزان >=45). |
| R 4.6.1; bibliometrix 5.4.1; ggplot2 4.0.3 | R Foundation for Statistical Computing; Massimo Aria and Corrado Cuccurullo; ggplot2 development team | https://www.r-project.org/; https://www.bibliometrix.org/; https://ggplot2.tidyverse.org/ | استُخدمت لتحليل الإنتاجية والتعاون حسب الدولة/المنطقة. طُبق العد الكامل على جميع العناوين؛ واستُخدم بلد المؤلف المسؤول لتحديد SCP/MCP. تم تجميع تايوان وهونج كونج وماكاو تحت الصين على مستوى الدولة فقط. |
| SCImago Graphica 1.0.55 | SCImago Lab | https://graphica.app/ | استُخدم للتنسيق النهائي والتصور المرئي لشبكة الاستشهاد المباشر للمجلات وخرائط الدول/المناطق. |
| VOSviewer 1.6.21 | Centre for Science and Technology Studies (CWTS), Leiden University, the Netherlands | https://www.vosviewer.com/ | عد كامل مع تطبيع قوة الارتباط. العتبات والشبكات النهائية: الكلمات المفتاحية >=30 (158 عقدة؛ 6,468 حافة)؛ المؤلفون >=6 وثائق (51؛ 134)؛ المؤسسات >=10 وثائق (109؛ 351)؛ المجلات المصدر >=20 وثيقة (39؛ 741)؛ المراجع المستشهد بها >=68 استشهاداً (91؛ 3,626). طُبقت قوائم مصطلحات خاصة بكل وحدة. |
المراجع
- Wu Y, Shen G, Hao C. Negative pressure wound therapy (NPWT) is superior to conventional moist dressings in wound bed preparation for diabetic foot ulcers: a randomized controlled trial. Saudi Med J. 2023;44(10):1020-9.
- Liu Z, Dumville JC, Hinchliffe RJ, Cullum N, Game F, Stubbs N, et al. Negative pressure wound therapy for treating foot wounds in people with diabetes mellitus. Cochrane Database Syst Rev. 2018;10(10):CD010318.
- Bruhin A, Ferreira F, Chariker M, Smith J, Runkel N. Systematic review and evidence-based recommendations for the use of negative pressure wound therapy in the open abdomen. Int J Surg. 2014;12(10):1105-14.
- Cirocchi R, et al. What is the effectiveness of negative pressure wound therapy (NPWT) in patients treated with open abdomen technique? A systematic review and meta-analysis. J Trauma Acute Care Surg. 2016;81(3):575-84.
- Orgill DP, Bayer LR. Negative pressure wound therapy: past, present and future. Int Wound J. 2013;10 Suppl 1:15-9.
- Robert N. Negative pressure wound therapy in orthopaedic surgery. Orthop Traumatol Surg Res. 2017;103(1 Suppl):S99-103.
- Morykwas MJ, Argenta LC, Shelton-Brown EI, McGuirt W. Vacuum-assisted closure: a new method for wound control and treatment: animal studies and basic foundation. Ann Plast Surg. 1997;38(6):553-62.
- Argenta LC, Morykwas MJ. Vacuum-assisted closure: a new method for wound control and treatment: clinical experience. Ann Plast Surg. 1997;38(6):563-76.
- Saxena V, et al. Vacuum-assisted closure: microdeformations of wounds and cell proliferation. Plast Reconstr Surg. 2004;114(5):1086-96.
- Normandin S, et al. Negative pressure wound therapy: mechanism of action and clinical applications. Semin Plast Surg. 2021;35(3):164-70.
- Kim PJ, et al. Negative pressure wound therapy with instillation: international consensus guidelines update. Int Wound J. 2020;17(1):174-86.
- Yamashiro T, et al. Negative-pressure wound therapy: what we know and what we need to know. In: Adv Exp Med Biol. 2023;1436:131-52.
- Webster J, Scuffham P, Stankiewicz M, Chaboyer WP. Negative pressure wound therapy for skin grafts and surgical wounds healing by primary intention. Cochrane Database Syst Rev. 2014;(10):CD009261.
- Norman G, et al. Negative pressure wound therapy for surgical wounds healing by primary closure. Cochrane Database Syst Rev. 2022;4(4):CD009261.
- Deng K, Yuan Z, Li D. Academic visualization and trend analysis of negative-pressure wound therapy from a global perspective. Asian J Surg. 2024;47(10):4449-51.
- Liu C, et al. Clinical study of early rehabilitation training combined with negative pressure wound therapy for the treatment of deep partial-thickness hand burns. Front Surg. 2023;10:1040407.
- Qian H, Lei T, Hu Y. Negative pressure wound therapy versus gauze dressings in managing open fracture wounds of the lower limbs: a meta-analysis of randomized controlled trials. Foot Ankle Surg. 2022;28(7):1120-8.
- Miller-Mikolajczyk C, Beach K, Silverman RP, Cooper ML. The evolution of commercial negative pressure wound therapy systems over the past three decades. Adv Wound Care (New Rochelle). 2024;13(8):375-90.
- Morykwas MJ, et al. Use of subatmospheric pressure to prevent progression of partial-thickness burns in a swine model. J Burn Care Rehabil. 1999;20(1 Pt 1):15-21.
- Tang L, et al. A biodegradable Janus sponge for negative pressure wound therapy. Biomacromolecules. 2024;25(4):2542-53.
- Agarwal P, Kukrele R, Sharma D. Vacuum-assisted closure (VAC)/negative pressure wound therapy (NPWT) for difficult wounds: a review. J Clin Orthop Trauma. 2019;10(5):845-8.
- Apelqvist J, et al. EWMA document: negative pressure wound therapy. J Wound Care. 2017;26 Suppl 3:S1-S154.
- Malmsjö M, Huddleston E, Martin R. Biological effects of a disposable, canisterless negative pressure wound therapy system. Eplasty. 2014;14:e15.
- Orgill DP, Bayer LR. Update on negative-pressure wound therapy. Plast Reconstr Surg. 2011;127 Suppl 1:105S-15S.
- Li Y, et al. Metabolic response to burn injury: a comprehensive bibliometric study. Front Med (Lausanne). 2024;11:1451371.
- Zhou Y, et al. Frontiers and hotspots in burn wound healing: a visualized bibliometric analysis. Regenesis Repair Rehabil. 2026;2(1):54-64.
- Xing Y, Huang Z, Cao L. Application of tissue engineering in wound healing: a 20-year bibliometric and visualized study. Medicine (Baltimore). 2025;104(35):e43008.
- U.S. Food and Drug Administration. 510(k) Premarket Notification K113236: Foryou NPWT Device. Updated February 12, 2013. Cited 2026 Jul 26. Available from: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfPMN/pmn.cfm?ID=K113236
- 4L Health Co. Ltd., Foryou Medical Electronics Co. Ltd. The first in China: Foryou NPWT entire product line for the EU market has obtained MDR certification. Updated July 2, 2024. Cited 2026 Jul 26. Available from: https://foryounpwt.com/NewsEvents/News_20240702.html