Filgotinib is an oral, preferential Janus kinase 1 inhibitor with demonstrated induction and maintenance efficacy in moderate-to-severe ulcerative colitis. Long-term extension and real-world findings support sustained benefit in selected patients, while rare-event safety uncertainty, confounding in observational comparisons, and geographic differences in availability require cautious, individualized positioning.
مقالة مراجعة
Filgotinib in Ulcerative Colitis: Long-term Outcomes and Treatment Positioning
* These authors contributed equally
في هذه المقالة
ملخص
الملخص
The therapeutic landscape of ulcerative colitis (UC) has expanded substantially with biologics and small-molecule agents, yet durable disease control, safety, and treatment sequencing remain important challenges. Filgotinib is an oral inhibitor with preferential activity for Janus kinase 1 (JAK1) relative to JAK2, JAK3, and tyrosine kinase 2. The pivotal SELECTION trial established induction and maintenance efficacy, and long-term extension and real-world studies have reported sustained clinical and patient-reported benefits in selected populations. Direct head-to-head trials remain scarce; most comparative evidence derives from network meta-analyses and nonrandomized cohorts that are vulnerable to heterogeneity and channeling bias. Rare adverse outcomes also remain imprecisely estimated. This narrative review integrates pivotal trials, long-term extension data, full peer-reviewed real-world studies, comparative analyses, guidelines, and regulatory information. It emphasizes cautious interpretation of JAK1 preference, clinically relevant risk assessment and monitoring, reproductive considerations, and geographic variation in therapeutic positioning. Filgotinib should be considered one option within individualized treatment sequencing rather than a uniformly preferred therapy.
المقدمة
The management of ulcerative colitis (UC) has undergone a profound transformation over the past two decades, driven by advances in disease pathophysiology and the development of targeted therapies. Conventional treatments such as corticosteroids and immunomodulators remain effective for inducing remission, but their long-term use is limited by toxicity, loss of response, and inability to achieve durable disease control. Biologic agents targeting tumor necrosis factor, integrins, and interleukins have improved outcomes for many patients; however, a substantial proportion experience primary non-response, secondary loss of response, or treatment intolerance1.
Against this background, small-molecule therapies, particularly Janus kinase (JAK) inhibitors, have gained attention because they offer oral administration, rapid onset of action, and broad suppression of inflammatory signaling. Filgotinib is a preferential JAK1 inhibitor—that is, it inhibits JAK1 more strongly than JAK2, JAK3, and tyrosine kinase 2 at clinically relevant exposures, although selectivity is neither absolute nor equivalent to absence of class-related risk2,3.
The pivotal SELECTION trial established filgotinib as an effective induction and maintenance therapy for adults with moderate-to-severe UC, including patients with prior biologic exposure4. Long-term extension studies and peer-reviewed real-world cohorts have subsequently informed treatment durability, corticosteroid-free remission, and safety beyond the controlled trial setting5,6,7,8,9,10. These data are relevant to contemporary treatment algorithms, meaning the selection and sequencing of biologics and small-molecule therapies together with pretreatment risk assessment and longitudinal monitoring.
Important uncertainties remain. Comparative evidence between filgotinib and other advanced therapies relies mainly on indirect comparisons, network meta-analyses, and nonrandomized cohorts. The clinical implications of preferential JAK1 inhibition for long-term effectiveness and safety also remain incompletely resolved. This review, therefore, integrates trial, real-world, guideline, regulatory, and comparative evidence to clarify what is known, what remains uncertain, and how filgotinib may be positioned within individualized contemporary UC care. Figure 1 presents this framework without implying a prescriptive treatment algorithm.
مراجعة ومنظور
Literature search approach
For this narrative review, PubMed/MEDLINE was searched from database inception through 15 September 2026. The search was supplemented by backward and forward citation checking, targeted searches of publisher websites, regulatory and guideline sources, and major gastroenterology conference proceedings when no full article was identified. Search concepts combined (ulcerative colitis OR UC) AND filgotinib AND (efficacy OR remission OR safety OR persistence OR real-world OR comparative OR positioning), with additional terms for JAK selectivity, monitoring, and reproductive safety. English-language human studies relevant to adults with moderate-to-severe UC were eligible. Evidence was prioritized in the following order: pivotal randomized trials, long-term extensions, systematic reviews or network meta-analyses, full peer-reviewed observational cohorts, and conference abstracts only when no full publication was available. Study relevance, design, follow-up, population, and reporting completeness informed selection; conference-only evidence is identified as preliminary.
Mechanistic rationale for selective JAK1 inhibition
The Janus kinase–Signal Transducer and Activator of Transcription (JAK–STAT) signaling pathway is central to cytokine-driven inflammation in UC. Earlier JAK inhibitors inhibit multiple JAK isoforms, whereas filgotinib preferentially inhibits JAK1, with relatively less inhibition of JAK2/3-related pathways at clinically relevant exposures3,11. This preference is not absolute, varies with exposure and cellular context, and does not establish clinical superiority or freedom from class-associated risk.
Preclinical and translational observations suggest that JAK1-focused inhibition can attenuate cytokine pathways involved in epithelial barrier dysfunction and mucosal immune activation3,11. This provides a pharmacologic rationale for anti-inflammatory activity, but proposed reductions in off-target effects cannot be treated as evidence of a clinical safety advantage. Benefit–risk judgments must remain anchored to observed outcomes, comparative study design, patient risk factors, and appropriate monitoring.
Long-term efficacy in clinical trials
The phase 2b/3, double-blind, randomized, placebo-controlled SELECTION trial established the induction and maintenance efficacy of once-daily filgotinib in adults with moderate-to-severe UC4. The open-label SELECTIONLTE study subsequently reported persistence of symptomatic, clinical, biochemical, and health-related quality-of-life benefits for up to approximately four years among participants who entered and remained in the extension7. These long-term estimates are clinically informative but should be interpreted in light of responder enrichment, treatment discontinuation, attrition, and the selected trial population.
Sustained efficacy has been observed in biologic-naive and biologic-experienced populations, although outcomes may be lower with greater baseline disease burden or extensive prior treatment exposure4,8,9,10. A conference abstract reported an association between lower baseline disease severity and selected outcomes; because this evidence remains available only in abstract form, it is preliminary and hypothesis-generating12. Neither lower baseline severity nor subgroup response establishes that filgotinib is more effective when positioned earlier in the treatment sequence. Sequencing should instead consider disease activity, prior mechanisms, comorbidity, patient preference, and local access.
Indirect comparisons and network meta-analyses generally place filgotinib among effective induction and maintenance options, while upadacitinib—an oral, preferential JAK1 inhibitor—often ranks higher for short-term induction endpoints1,13. Rankings depend on included trials, endpoint definitions, treatment periods, and assumptions used to connect heterogeneous populations. They should inform, rather than replace, individualized clinical judgment.
Real-world effectiveness and treatment persistence
Real-world cohorts complement randomized trials by including patients with broader comorbidity profiles, varied prior advanced therapies, and routine-care follow-up. Peer-reviewed cohorts from Europe and Japan have reported clinically meaningful symptomatic and corticosteroid-free remission across heterogeneous populations6,8,9,10,14. Estimates vary by activity index, assessment window, missing-data rule, and prior exposure; they support effectiveness in practice but do not remove the need for cautious cross-study comparison.
Treatment persistence integrates effectiveness, tolerability, access, and patient preference. Peer-reviewed cohorts have reported continued filgotinib use during follow-up, with discontinuation commonly attributed to nonresponse or loss of response rather than adverse events8,9,10. Comparative observational studies have sometimes reported higher short-term effectiveness or more adverse events with upadacitinib, but nonrandomized treatment allocation, baseline imbalance, and residual confounding limit causal interpretation14,15.
Prior biologic or other advanced-therapy failure does not eliminate the possibility of benefit, as responses and treatment continuation have been documented in treatment-experienced cohorts6,8,9. Average outcomes may nevertheless differ from those in less-exposed populations. These findings support filgotinib as an option after advanced-therapy failure but do not establish superiority of earlier use. Prospective comparative registries with standardized endpoints and transparent missing-data handling are needed for stronger sequencing inferences.
Long-term safety and tolerability
Integrated analyses of SELECTION and SELECTIONLTE reported low exposure-adjusted rates of serious infection, venous thromboembolism, and major adverse cardiovascular events, without an unexpected safety signal during the reported follow-up5,7. Peer-reviewed real-world cohorts have likewise reported relatively few serious events6,8,9,10. These observations should not be interpreted as proof of a favorable comparative safety profile: event counts are limited for uncommon outcomes, extension cohorts are selected, and uncertainty is greatest for older patients and those with cardiovascular, thromboembolic, malignancy, or serious-infection risk factors.
Comparative observational data have reported differences in adverse-event frequency among JAK inhibitors, but sparse nonrandomized evidence does not establish that filgotinib has a clinically superior safety profile14,15. Preferential JAK1 inhibition should therefore be considered only one component of the benefit–risk assessment. Continuation is reasonable when treatment is effective and tolerated, provided that class-related warnings, patient-specific risks, and local product information are respected16,17.
Before treatment, clinicians should assess serious or recurrent infection, tuberculosis, and viral hepatitis risk, vaccination status, complete blood count, liver function and lipids, and individual cardiovascular, venous thromboembolic, malignancy, and reproductive risk. Older adults, current or former long-term smokers, and patients with established cardiovascular, thromboembolic, malignancy, or infection risk require particularly careful consideration. During treatment, clinical review and laboratory monitoring should follow the local product label and guideline recommendations, with prompt evaluation of infection, thrombosis, cardiovascular symptoms, cytopenia, liver-test abnormalities, or lipid change. Pregnancy and breastfeeding considerations should be addressed before and during therapy16,17.
Comparative effectiveness and treatment positioning
In the absence of head-to-head randomized trials, matching-adjusted comparisons and network meta-analyses suggest context-dependent efficacy differences among filgotinib, vedolizumab, an anti-α4β7 integrin monoclonal antibody; ustekinumab, an interleukin-12/23 p40 monoclonal antibody; tofacitinib, a less isoform-selective JAK inhibitor; and upadacitinib, a preferential JAK1 inhibitor1,13,18. These analyses do not establish a universally optimal sequence and are sensitive to cross-trial heterogeneity and modeling assumptions.
Filgotinib combines once-daily oral administration, rapid onset of action, absence of immunogenicity, and evidence for sustained symptom control. These features may matter to patients who prefer an oral option or require a steroid-sparing strategy, but convenience does not guarantee adherence. Health-technology and multicriteria assessments emphasize effectiveness, safety, convenience, and economic value, while also showing that cost-effectiveness and access are health-system dependent19,20,21.
Treatment algorithms also differ across regions. Filgotinib availability, approved indication, reimbursement, prior-therapy requirements, and preferred comparators vary by jurisdiction and health system. For example, European product information and United Kingdom health-technology guidance provide a regulatory and reimbursement framework that is not directly transferable to every country, while the AGA guideline reflects a United States practice context in which treatment availability differs16,21,22. Positioning statements should therefore be interpreted locally rather than as a universal sequence.
Table 11,2,3,4,5,6,7,8,9,10,11,12,13,14,15,16,17,18,20,21,22 provides a cautious, citation-linked synthesis of efficacy, safety, durability, and treatment-positioning considerations. Table 24,6,7,8,9,10,14,15 summarizes the designs, populations, exposure histories, doses, follow-up, outcomes, safety findings, and limitations of pivotal and representative long-term or real-world studies. Neither table is intended as a prescriptive algorithm.
Patient-centered outcomes and future perspectives
Long-term disease control is meaningful only if it improves daily functioning and reduces treatment burden. SELECTIONLTE reported sustained health-related quality-of-life improvement among extension participants7. Shared decision-making should cover expected benefits, uncertainty, monitoring, prior treatment experience, comorbidity, reproductive plans, and patient preferences. Product information advises against use during pregnancy and calls for effective contraception during treatment and for at least one week after the last dose; reproductive counseling should also address breastfeeding and any jurisdiction-specific labeling16.
The principal evidence gaps are the scarcity of direct head-to-head trials, limited comparative safety follow-up, heterogeneity in real-world outcome definitions, and uncertainty about the optimal sequence of JAK inhibitors and biologics. Biomarkers that predict response to a specific mechanism are not yet available for routine treatment selection. Future studies should use standardized clinical, endoscopic, biochemical, and patient-reported endpoints; prespecified analyses by disease severity and prior exposure; and sufficiently long follow-up to capture uncommon adverse outcomes. Pragmatic comparative trials and coordinated registries would be especially valuable for distinguishing treatment effects from differences in patient selection.
Until stronger comparative evidence is available, filgotinib is best viewed as one component of individualized treatment sequencing. Its value rests on demonstrated induction and maintenance efficacy, oral delivery, and reported durability in selected trial-extension and real-world populations, balanced against indirect comparative evidence, incomplete rare-event precision, and jurisdiction-specific availability. Pharmacologic selectivity alone should neither justify preferential use nor exclude appropriate use.
الاستنتاجات
Filgotinib is a clinically relevant option for adults with moderate-to-severe ulcerative colitis, supported by randomized evidence for induction and maintenance efficacy and by longer-term and real-world reports of benefit in selected populations. Preferential JAK1 inhibition provides a mechanistic rationale but does not establish superior safety or efficacy. Comparative conclusions remain uncertain because head-to-head randomized trials are lacking, observational studies are confounded, and rare adverse-event counts are limited. Treatment decisions should integrate disease activity, prior therapy, comorbidity, infection, and cardiovascular or thromboembolic risk, reproductive considerations, patient goals, monitoring requirements, and local regulatory and reimbursement conditions. Direct comparative studies, harmonized registries, longer surveillance, and validated predictive biomarkers are needed.
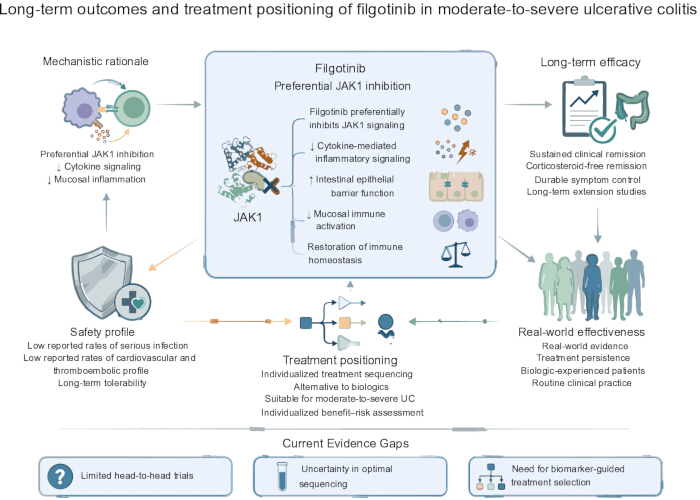
Figure 1: Conceptual framework for the long-term outcomes and treatment positioning of filgotinib in moderate-to-severe ulcerative colitis. The figure integrates the mechanistic rationale for preferential JAK1 inhibition with long-term efficacy, safety, real-world effectiveness, practical treatment positioning, and current evidence gaps. This is an original conceptual diagram created specifically for this manuscript using the Figurelabs platform; it is not adapted from a published source and contains no third-party copyrighted material. Please click here to view a larger version of this figure.
| Domain | Integrated findings | Clinical interpretation |
| Mechanism of action | Filgotinib preferentially inhibits JAK1, with relatively less inhibition of JAK2/3-related pathways; this preference is not absolute [3,11]. | The mechanism supports a pharmacologic rationale but does not prove clinical superiority or absence of class-related risk [3,5]. |
| Induction efficacy | The pivotal SELECTION trial demonstrated induction efficacy in biologic-naïve and biologic-experienced adults; indirect rankings vary by endpoint and model [1,4,13]. | Filgotinib is an effective induction option, but indirect rankings should not replace individualized treatment selection [1,4,13]. |
| Maintenance of remission | SELECTION and SELECTIONLTE reported maintenance and persistence of symptomatic, clinical, biochemical, and quality-of-life benefits among selected participants [4,7]. | The findings support maintenance use while requiring consideration of responder enrichment, attrition, and discontinuation [4,7]. |
| Corticosteroid-sparing effect | Corticosteroid-free remission has been reported in trial-extension and peer-reviewed real-world cohorts [7-10]. | Steroid-free disease control is a relevant treatment goal, but definitions and assessment windows differ across studies [7-10]. |
| Effectiveness after prior advanced therapy | Benefit has been observed in biologic- or advanced-therapy-experienced populations, although outcomes vary with baseline burden and prior exposure [4,6,8-10]. | Prior treatment failure does not preclude benefit; it also does not establish a preferred treatment sequence [4,6,8-10]. |
| Disease severity | A conference abstract reported associations between lower baseline severity and selected outcomes; the evidence is preliminary and hypothesis-generating [12]. | Lower baseline severity does not demonstrate a benefit from earlier positioning and requires confirmation in appropriately designed comparative studies [12]. |
| Real-world treatment persistence | Peer-reviewed cohorts report continued treatment during follow-up, with discontinuation commonly related to nonresponse or loss of response [8-10]. | Persistence integrates effectiveness, tolerability, access, and preference and should not be interpreted as efficacy alone [8-10]. |
| Long-term safety | Trial and real-world studies report low observed rates of selected serious events, but rare-event counts and representation of higher-risk patients remain limited [5-10]. | The evidence does not exclude clinically important rare risks; risk stratification and monitoring remain necessary [5,7,16-17]. |
| Comparative safety within JAK inhibitors | Some observational comparisons report differences in adverse-event frequency, but nonrandomized allocation and sparse events preclude a causal safety advantage [14-15]. | Agent selection should rely on individualized benefit–risk assessment and monitoring, not presumed class safety superiority [14-17]. |
| Quality-of-life outcomes | SELECTIONLTE reported sustained health-related quality-of-life improvement among extension-study participants [7]. | Patient-reported benefit is clinically relevant but should be interpreted with the selected extension population in mind [7]. |
| Comparative effectiveness vs biologics | Indirect analyses compare filgotinib with vedolizumab, ustekinumab, and other advanced therapies; results depend on cross-trial assumptions [1,13,18]. | Filgotinib is one advanced-therapy option; indirect comparisons do not establish universal superiority or sequencing [1,13,18]. |
| Comparative effectiveness vs other JAK inhibitors | Upadacitinib often ranks higher for short-term induction, while real-world JAK comparisons remain nonrandomized and heterogeneous [13-15]. | Within-class selection should consider treatment goals, risk factors, uncertainty, and patient preferences [13-15,17]. |
| Practical features | Once-daily oral administration, rapid onset, and absence of immunogenicity may reduce administration burden [2-3]. | Convenience may matter to patients but does not guarantee adherence or establish a favorable benefit–risk profile [2-3]. |
| Treatment positioning | Guidelines, regulatory status, reimbursement, prior-therapy requirements, and available comparators differ across jurisdictions and health systems [16,20-22]. | Filgotinib should be positioned through shared, locally contextualized decision-making rather than as a uniform first- or last-line therapy [16,20-22]. |
| Key evidence gaps | Direct head-to-head trials, long-term comparative safety data, harmonized real-world endpoints, and validated predictive biomarkers remain limited [1,13-15]. | Pragmatic comparative trials, coordinated registries, and longer rare-event surveillance are priorities [1,13-15]. |
Table 1: Integrated summary of long-term outcomes, safety, and treatment positioning of filgotinib in moderate-to-severe ulcerative colitis. Each statement is linked to the numbered manuscript references, and comparative or safety interpretations are deliberately framed as cautious, noncausal conclusions.
| Study [ref] | Design | Sample size | Population | Prior advanced-therapy exposure | Filgotinib dose | Follow-up | Main efficacy endpoints/findings | Major safety findings | Key limitations |
| SELECTION — Feagan et al. [4] | Phase 2b/3 double-blind randomized placebo-controlled induction and maintenance trial | 1,348 in two induction cohorts; responders re-randomized for maintenance | Adults with moderate-to-severe active UC; separate biologic-naïve and biologic-experienced induction cohorts | Induction A: biologic-naïve; Induction B: prior TNF antagonist or vedolizumab failure/intolerance | 100 or 200 mg once daily | 10-week induction; maintenance through week 58 | Clinical remission and response at induction and maintenance; efficacy established for 200 mg | Safety assessed across placebo and dose groups; uncommon serious events | Responder-enriched maintenance; selected trial population; limited precision for rare events |
| SELECTIONLTE — Feagan et al. [7] | Open-label long-term extension | 622 entered reported analysis (250 completers; 372 nonresponders from parent study) | SELECTION participants entering extension | Mixed; reflects parent-trial biologic-naïve and experienced cohorts | 100 or 200 mg once daily according to parent-study pathway | Up to approximately 4 years | Symptoms, partial Mayo measures, biomarkers, and health-related quality of life remained improved in continuing participants | No unexpected signal reported; low observed rates of selected serious events | Open-label; attrition; responder/survivor enrichment; no concurrent randomized comparator |
| Gros et al. [10] | Retrospective real-world cohort | 91 | Routine-care UC cohort in Scotland | Approximately two-thirds were advanced-therapy-naïve | Predominantly 200 mg once daily | Median 39 weeks | Clinical, biochemical, and corticosteroid-free outcomes; treatment persistence | Serious adverse events were uncommon | Single regional cohort; retrospective ascertainment; incomplete standardized follow-up |
| Young et al. [9] | Retrospective multicentre real-world cohort | 286 across 9 UK centres | Adults receiving filgotinib in routine care | 56% had previous advanced therapy exposure | 200 mg once daily in routine practice | Median 229 days | Clinical effectiveness, corticosteroid-free outcomes, and persistence | Adverse events and treatment discontinuations reported; no randomized comparator | Retrospective; heterogeneous assessment timing; missing data; treatment selection changed over calendar time |
| Naber et al. [8] | Prospective multicentre registry cohort | 96 | Dutch ICC registry; 71% met difficult-to-treat criteria | Predominantly treatment-experienced | 200 mg once daily | 52 weeks | Corticosteroid-free clinical remission, biochemical outcomes, and persistence | No severe infections reported in the cohort | No control group; modest sample; missing routine-care observations; limited rare-event precision |
| Nogami et al. [14] | Retrospective multicentre comparative cohort | 168 total: 98 filgotinib; 70 upadacitinib | Japanese routine-care UC cohort | Mixed prior biologic and tofacitinib exposure | Filgotinib 200 mg once daily | Median 181 days | Week-8 response/remission and treatment persistence | Adverse events: 24.5% with filgotinib vs 45.7% with upadacitinib | Nonrandomized treatment selection; short follow-up; residual confounding despite adjustment |
| Akiyama et al. [15] | Retrospective multicentre comparative cohort | 602 total: 215 filgotinib, 228 upadacitinib, 159 tofacitinib | Treatment-experienced Japanese UC cohort | Mixed and frequently prior advanced therapy | Filgotinib 200 mg once daily | Median filgotinib follow-up approximately 56 weeks | Clinical/biochemical response, remission, and persistence across three JAK inhibitors | Agent-specific adverse events reported; comparisons remained observational | Confounding by indication; heterogeneous follow-up; no randomized assignment; rare-event uncertainty |
| Tursi et al. [6] | Prospective observational real-world study | 102 | Italian adults receiving filgotinib as second- or third-line therapy | Prior biologic or other advanced therapy common by design | 200 mg once daily | Median 24 weeks | Clinical response/remission and biomarker improvement | Adverse events in 5.8%; severe events leading to discontinuation in 2.0% | Short follow-up; no comparator; modest sample; selected line-of-therapy population |
Table 2: Characteristics of pivotal and representative long-term or real-world filgotinib studies in ulcerative colitis. The table summarizes study design, sample size, population, previous advanced-therapy exposure, dose, follow-up, efficacy outcomes, major safety findings, and key limitations. Numbers in square brackets correspond to the manuscript reference list. Observational comparisons should not be interpreted as causal. Abbreviations: UC = ulcerative colitis; TNF = tumor necrosis factor; JAK = Janus kinase.
الإفصاحات
The authors declare that they have no conflicts of interest.
شكر وتقدير
The authors received no specific funding for this work.
المراجع
- Panaccione R, et al. Efficacy and safety of advanced therapies for moderately to severely active ulcerative colitis at induction and maintenance: an indirect treatment comparison using Bayesian network meta-analysis. Crohns Colitis 360. 2023;5(2):otad009.
- Fanizza J, et al. The role of filgotinib in ulcerative colitis and Crohn's disease. Immunotherapy. 2024;16(2):59–74.
- Dal Buono A, et al. Critical appraisal of filgotinib in the treatment of ulcerative colitis: current evidence and place in therapy. Clin Exp Gastroenterol. 2022;15:121–128.
- Feagan BG, et al. Filgotinib as induction and maintenance therapy for ulcerative colitis (SELECTION): a phase 2b/3 double-blind, randomised, placebo-controlled trial. Lancet. 2021;397(10292):2372–2384.
- Schreiber S, et al. Integrated safety analysis of filgotinib for ulcerative colitis: results from SELECTION and SELECTIONLTE. Aliment Pharmacol Ther. 2023;58(9):874–887.
- Tursi A, et al. Filgotinib effectiveness and safety as second- or third-line therapy in patients with ulcerative colitis: data from a real-world study. Intest Res. 2026;24(2):341–351.
- Feagan BG, et al. Long-term safety and efficacy of filgotinib for the treatment of moderately to severely active ulcerative colitis: interim analysis from up to 4 years of follow-up in the SELECTION open-label long-term extension study. Aliment Pharmacol Ther. 2024;60(5):563–584.
- Naber MR, et al. Filgotinib is an effective and safe treatment option for difficult-to-treat ulcerative colitis: real-world evidence of the Dutch Initiative on Crohn and Colitis (ICC) Registry. United European Gastroenterol J. 2026;14(1):e70141.
- Young D, et al. Real-world assessment of effectiveness and safety of filgotinib in 286 patients with ulcerative colitis in 9 UK centres. Drugs Context. 2025;14:2024-11-1.
- Gros B, et al. Real-world cohort study on the effectiveness and safety of filgotinib use in ulcerative colitis. J Crohns Colitis. 2025;19(1):jjad187.
- Neri B, et al. Efficacy and safety of Janus kinase inhibitors in ulcerative colitis. J Clin Med. 2024;13(23):7186.
- Allez M, et al. P1144 Effect of baseline disease severity on achieving efficacy endpoints in patients with ulcerative colitis treated with filgotinib [conference abstract; preliminary evidence]. J Crohns Colitis. 2025;19(Suppl 1):i2090–i2092.
- Shehab M, et al. Comparative efficacy of biologics and small molecules in ulcerative colitis: a systematic review and network meta-analysis. Clin Gastroenterol Hepatol. 2025;23(2):250–262.
- Nogami A, et al. Real-world comparative effectiveness and safety of filgotinib and upadacitinib for ulcerative colitis: a multicentre cohort study. United European Gastroenterol J. 2024;12(10):1357–1366.
- Akiyama S, et al. Comparative efficacy and safety of three Janus kinase inhibitors in ulcerative colitis: a real-world multicentre study in Japan. Aliment Pharmacol Ther. 2025;61(3):524–537.
- European Medicines Agency. Jyseleca: EPAR—product information [Internet]. [cited 2026 Sep 15]. Available from: EMA product information.
- Jairath V, et al. Practical guidance for managing patients with moderate-to-severe ulcerative colitis using small molecule therapies. J Can Assoc Gastroenterol. 2024;7(4):282–289.
- Lu X, et al. Matching-adjusted indirect comparisons of filgotinib vs vedolizumab, tofacitinib, and ustekinumab for moderately to severely active ulcerative colitis. Inflamm Bowel Dis. 2024;30(1):64–77.
- Taxonera C, et al. Determinación de la contribución de valor de filgotinib para el tratamiento de la colitis ulcerosa de moderada a grave mediante el análisis de decisión multicriterio (MCDA). Economía de la Salud. 2023;18:18.
- van Asselt ADI, et al. Filgotinib for treating moderately to severely active ulcerative colitis: an Evidence Review Group perspective of a NICE single technology appraisal. Pharmacoeconomics. 2023;41(3):239–251.
- National Institute for Health and Care Excellence. Filgotinib for treating moderately to severely active ulcerative colitis (Technology appraisal guidance TA792) [Internet]. 2022 [cited 2026 Sep 15]. Available from: NICE guidance TA792.
- Singh S, et al. AGA living clinical practice guideline on pharmacological management of moderate-to-severe ulcerative colitis. Gastroenterology. 2024;167(7):1307–1343.