This case report describes a 72-year-old man with mixed pneumonia and pulmonary embolism. Computed tomography pulmonary angiography identified a pulmonary arterial filling defect, while bronchoalveolar lavage fluid targeted sequencing provided additional pathogen-specific information after antimicrobial therapy. The report emphasizes case-specific interpretation and limitations of single-case diagnostic and mechanistic inference.
Rapport de cas
Mixed Pneumonia with Pulmonary Embolism and Multiple Pathogens Detected in Bronchoalveolar Lavage Fluid: A Case Report
Dans cet article
Résumé
Résumé
Severe community-acquired pneumonia may involve mixed pathogens and concurrent vascular complications. A 72-year-old man presented with fever, nonproductive cough, vomiting, hypoxemia, markedly elevated inflammatory markers, and an elevated D-dimer concentration. Chest computed tomography showed left lower-lobe consolidation and pleural effusion. Computed tomography pulmonary angiography, obtained because of hypoxemia and suspected pulmonary embolism, showed a filling defect in a right upper-lobe pulmonary artery. The patient received antimicrobial therapy prior to bronchoalveolar lavage (BAL). Bronchoscopy was performed in the bronchopulmonary segment corresponding to the radiographic lesion, and approximately 10 mL of bronchoalveolar lavage fluid (BALF) was recovered aseptically for microbiological and cytological testing. An aliquot of at least 3 mL was allocated to a multiplex pathogen-targeted sequencing assay, which detected Chlamydia psittaci, influenza A H3N2, Streptococcus pneumoniae, and additional conditionally pathogenic or commensal organisms. The three principal detections were interpreted in conjunction with the clinical presentation, imaging, inflammatory markers, BALF cytology, conventional testing, and treatment response. The patient improved during antimicrobial and anticoagulant treatment and was discharged on December 3, 2025. At the documented outpatient follow-up on December 17, rivaroxaban was continued for approximately one further month. This case highlights the adjunctive value and interpretive limitations of targeted sequencing in a treated patient. The serial imaging and invasive sampling reflected case-specific decisions and should not be interpreted as a routine protocol for pneumonia.
Introduction
Influenza A virus can cause severe lower respiratory tract infection and may coexist with bacterial or atypical pathogens1,2,3,4. Chlamydia psittaci is an uncommon cause of community-acquired pneumonia that can be difficult to identify by conventional culture or serology5,6,7,8,9. Targeted next-generation sequencing (tNGS) enriches for predefined microbial targets and may provide additional information when conventional testing is inconclusive, although detected nucleic acid does not, by itself, establish active infection10,11,12,13. Severe infection can also disturb the balance between inflammation and coagulation14,15,16,17,18. In patients with pneumonia, hypoxemia, and pulmonary embolism (PE), the clinical findings may overlap. Computed tomography pulmonary angiography (CTPA) is therefore considered when the clinical presentation raises specific concern for PE, rather than as routine imaging for all patients with pneumonia. We report a patient with influenza A H3N2, C. psittaci, and S. pneumoniae detected in bronchoalveolar lavage fluid (BALF), together with a pulmonary arterial filling defect. The report focuses on the clinical course and interpretation of the microbiological findings. It does not propose a new or validated diagnostic workflow.
CASE PRESENTATION:
A 72-year-old man, born on September 9, 1953, was admitted at 08:59 on November 22, 2025, after three days of nonproductive cough, vomiting, and subsequent fever. He was a farmer and had previously been healthy. He had smoked approximately 10 cigarettes daily for more than 20 years but had stopped more than 20 years earlier. He reported no long-term medication use, recent travel to an epidemic area, or contact with birds, poultry, or other animals. Vaccination history and a formal patient-perspective narrative were not documented. On presentation, the arterial oxygen partial pressure was 59.8 mmHg on room air. Early-hospitalization laboratory testing showed C-reactive protein values of 237.6 and 306.85 mg/L; procalcitonin was 6.119 ng/mL, and D-dimer was 6.81 µg/mL (Table 1). Chest computed tomography showed left lower-lobe consolidation with pleural effusion. Because of hypoxemia and an elevated D-dimer concentration, contrast-enhanced computed tomography performed on November 25, 2025 confirmed a filling defect in the right upper-lobe pulmonary artery (Figure 1). Oxygen was administered by nasal cannula at 2 L/min from November 24 through December 3. Pulmonary tuberculosis and Mycoplasma pneumoniae pneumonia were considered. Tuberculosis was considered less likely because the imaging did not show the typical cavitary or calcified pattern described in the differential assessment, and BALF Mycobacterium tuberculosis DNA testing was negative. M. pneumoniae pneumonia was considered less likely because nucleic acid testing was negative, and the clinical and radiographic findings were not typical. These findings were interpreted in light of the limitations of a single case. The PE was classified clinically as low risk. On November 22, brain natriuretic peptide was 92 pg/mL, and troponin was below 0.025 ng/mL. Echocardiography on November 23 showed partial aortic valve degeneration with mild regurgitation and impaired left ventricular diastolic function. Lower-extremity duplex ultrasonography showed patent bilateral deep veins with normal compressibility and no sonographic evidence of deep-vein thrombosis (DVT). The clinical record did not provide quantitative right-heart strain measurements or a numerical bleeding-risk score.
DIAGNOSIS, ASSESSMENT, AND PLAN:
The working diagnosis was severe mixed pneumonia with a pulmonary arterial filling defect consistent with PE. Piperacillin/tazobactam 4.5 g intravenously every 8 h and levofloxacin 0.5 g intravenously once daily were administered from November 22 through December 3. Levofloxacin was selected as a respiratory fluoroquinolone with activity against both common and atypical community-acquired pneumonia pathogens, consistent with community-acquired pneumonia guidance19. No isolate-specific susceptibility result was available; therefore, the regimen was not described as a pathogen-specific targeted therapy. Baloxavir 40 mg was given orally as a single dose on November 22. Dalteparin 5,000 U (0.2 mL) subcutaneously twice daily was administered from November 25 through November 28, followed by rivaroxaban 20 mg orally once daily from November 28. The documented plan was to continue oral anticoagulation for 3–6 months, subject to clinical reassessment and bleeding risk, consistent with current PE guidance20. Because BAL was obtained after broad-spectrum antimicrobial treatment had begun, negative conventional culture results could have been influenced by prior exposure. The culture-negative and tNGS-positive findings were therefore not interpreted as proof of diagnostic superiority. The sequencing results were treated as adjunctive evidence and assessed against the complete clinical picture.
Protocole
Written informed consent for publication was obtained. The report was approved by the Ethics Committee of Yueqing Third People’s Hospital (approval no. 2026005). The reagents and equipment are listed in the Table of Materials. The procedural details below describe the care provided to this patient and are not intended as a standardized diagnostic protocol for all patients with pneumonia. Flexible bronchoscopy in older adults requires individualized assessment and appropriate cardiorespiratory monitoring21.
1. Patient preparation and anesthesia
- The patient was placed supine, and intravenous access was established. Electrocardiography, noninvasive blood pressure, and pulse oximetry were monitored throughout the procedure.
- Intravenous anesthesia was administered using propofol 250 mg and alfentanil 0.5 mg, as documented for this procedure. Cardiorespiratory monitoring was continued until recovery from anesthesia.
2. Bronchoscopic inspection and lesion-directed lavage
- A flexible video bronchoscope was introduced, and the tracheobronchial tree was inspected. In this patient, the vocal cords were mobile, the main airways were patent, and mucosal hyperemia with abundant secretions was present in the left lower-lobe bronchus (Figure 2).
- The bronchoscope was advanced into the bronchopulmonary segment corresponding to the radiographic lesion. The initial return was discarded if contaminated, a total of 100 mL of sterile normal saline was instilled in five aliquots of 20 mL each, and approximately 10 mL of BALF was recovered using sterile technique.
3. Specimen allocation, handling, and conventional testing
- BALF was transferred immediately into sterile screw-cap containers. Approximately 10 mL of BALF was recovered in this case, and an aliquot of at least 3 mL was allocated to tNGS in accordance with the service requirement.
- Non-blood specimens were transported promptly under refrigerated cold-chain conditions. When immediate processing was not possible, specimens were stored at 4 °C for no more than 24 h. Specimens were frozen if the delay exceeded 24 h, and repeated freeze-thaw cycles were avoided.
- BALF and brushing specimens were submitted for the clinically indicated conventional studies, including bacterial and fungal culture, acid-fast staining, M. tuberculosis DNA testing, cryptococcal capsular antigen testing, and cytological evaluation.
4. Multiplex pathogen-targeted sequencing
- The Dian Diagnostics multiplex pathogen-targeted sequencing assay (200+ panel), which covers 231 pathogens and selected resistance genes or variants for lower respiratory tract infection specimens, was used.
- Viscous BALF was liquefied with the validated digestive solution, DNA/RNA preservative was added, and mechanical disruption was performed. The supernatant was recovered after gentle centrifugation (1,500 x g for 5 min), and DNA and RNA were extracted using the automated co-extraction platform according to the service procedure. The automated extraction platform, pathogen-analysis software, and curated pathogen reference database were proprietary components of the Dian Diagnostics service; separate model or version identifiers were not available to the authors.
- The library was prepared by multiplex polymerase chain reaction, purified, and quantified. Sequencing was performed on the MGISEQ-200 platform using single-end 50-base-pair reads. The run was accepted when clean reads were at least 100,000, internal-control reads were at least 100, and Q30 was at least 80%.
- The reads were processed using the validated pathogen-analysis software for quality control, read filtering, and alignment against the curated reference database.
- A detected pathogen was considered positive when reads per million (RPM) were at least 20, at least one target amplicon was present, relative RPM was at least 10, and the within-batch proportion was at least 0.05% of the highest RPM for that pathogen among samples in the same batch. Relative RPM was calculated as the pathogen RPM divided by the RPM for the same pathogen in the negative control.
- The result was interpreted according to the specimen source, inherent pathogenicity, sequence count, patient immune status, clinical presentation, imaging findings, inflammatory markers, cytology, conventional microbiology, prior antimicrobial exposure, and treatment response. A positive sequencing result alone was not considered sufficient to establish infection.
Résultats
BALF tNGS detected C. psittaci (27,926 sequences; estimated concentration 103 copies/mL) and influenza A H3N2 (14,671 sequences; 103 copies/mL), both classified as pathogenic organisms in the laboratory report. S. pneumoniae was detected at 6,485 sequences and 103 copies/mL and was classified as conditionally pathogenic (Figure 3A and Table 2). The clinical interpretation considered it potentially relevant because of the lower respiratory specimen, severe inflammatory response, neutrophil-predominant BALF cytology, radiographic consolidation, and clinical response. However, sequence count alone could not distinguish infection from upper-airway carriage.
The report also detected Tropheryma whipplei (71,003 sequences; 103 copies/mL) and Aspergillus flavus complex (217 sequences; below 103 copies/mL), both classified as conditionally pathogenic, and Staphylococcus epidermidis (160 sequences; below 103 copies/mL), classified as microbiota or a colonizing organism. The clinical, radiographic, host, and treatment information did not support these organisms as the principal causes of pneumonia. Confirmed C-reactive protein measurements decreased during treatment and follow-up (Figure 3B), and follow-up imaging showed improvement of the left lower-lobe consolidation. Piperacillin/tazobactam and levofloxacin were stopped at discharge on December 3. Rivaroxaban was continued. At outpatient follow-up on December 17, rivaroxaban was prescribed for approximately one further month. No later follow-up record was available (Figure 4).
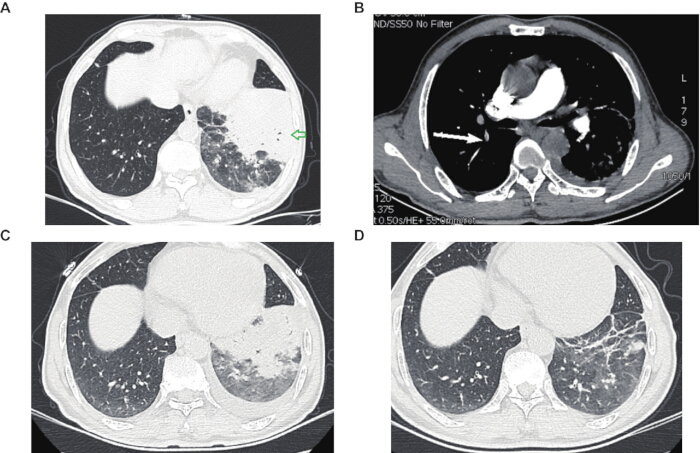
Figure 1: Radiological findings and follow-up. (A) Initial chest computed tomography shows left lower-lobe consolidation and pleural effusion. (B) Axial CTPA shows a filling defect in a right upper-lobe pulmonary artery (arrow). (C,D) Follow-up computed tomography images show interval improvement and residual linear opacity. The serial examinations reflected case-specific clinical decisions and should not be interpreted as routine imaging for pneumonia. Please click here to view a larger version of this figure.
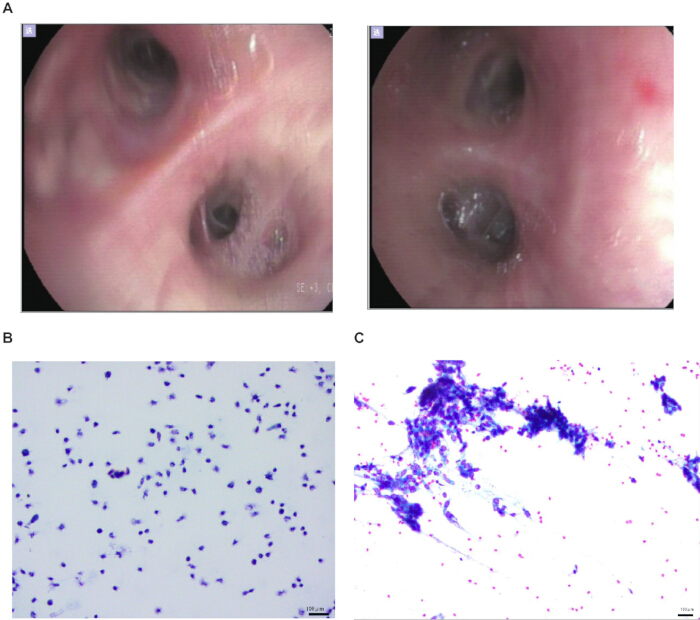
Figure 2: Bronchoscopy and lower respiratory tract cytology. (A) Bronchoscopic images show mucosal hyperemia and secretions in the affected left lower-lobe bronchus. (B) BALF cytology shows neutrophil predominance. (C) Gram staining did not show a predominant bacterial morphology. Scale bars = 100 µm. Please click here to view a larger version of this figure.
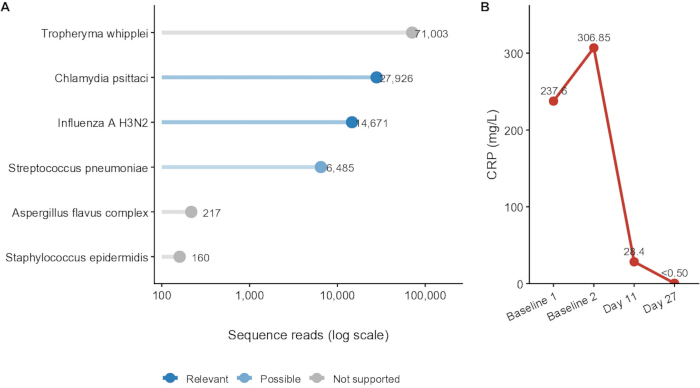
Figure 3: BALF tNGS findings and confirmed C-reactive protein measurements. (A) Sequence reads for all detected organisms, colored by the case-specific clinical interpretation (relevant, possible, or not supported/commensal). Interpretation was based on the complete clinical and microbiological context rather than the read count alone. (B) Confirmed C-reactive protein values at Baseline 1, Baseline 2, Day 11, and Day 27. CRP, C-reactive protein. Please click here to view a larger version of this figure.
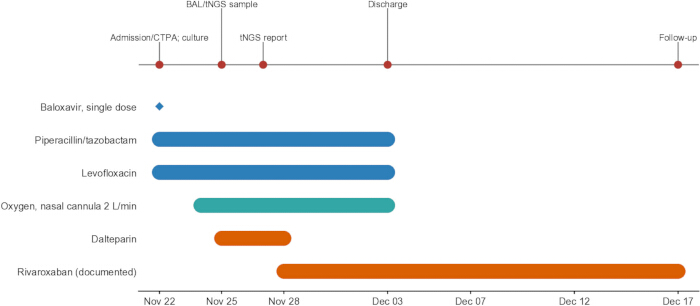
Figure 4: Clinical timeline and treatment course. Calendar dates show admission, blood culture, bronchoscopy, and BALF sampling, tNGS reporting, oxygen support, antimicrobial treatment, anticoagulant transition, discharge, and outpatient follow-up. The rivaroxaban bar shows the available record through December 17; the documented treatment plan was 3–6 months, subject to reassessment and bleeding risk. Please click here to view a larger version of this figure.
| Parameter | Unit | Reference range | Baseline value 1 | Baseline value 2 | Mid-treatment (Day 11) | Follow-up (Day 27) |
| White blood cell count | x 109/L | 3.50–9.50 | 8.53 | 6.05 | 4.79 | 3.96 |
| Neutrophil percentage | % | 40.0–75.0 | 82.3 | 81.9 | 58.1 | 39.8 |
| C-reactive protein | mg/L | 0.00–10.00 | 237.6 | 306.85 | 28.4 | <0.50 |
| Serum amyloid A | mg/L | <10.00 | Not tested | Not tested | 50.08 | Not tested |
| D-dimer | μg/mL | 0.00–0.50 | 6.81 | Not available | 1.3 | 0.29 |
| Platelet count | x 109/L | 125–350 | 159 | 186 | 543 | 146 |
| Alanine aminotransferase | U/L | 0–50 | 36 | 35 | 76 | 12 |
| Aspartate aminotransferase | U/L | 0–40 | 66 | 86 | 231 | 27 |
| Serum creatinine | μmol/L | 57–111 | 106 | 73 | 55 | 45 |
Table 1: Sequential laboratory parameters. Baseline 1 and Baseline 2 denote two early-hospitalization measurements; exact collection times were not available in the clinical record.
| Method category | Diagnostic modality | Specimen | Target or organism | Result | Clinical interpretation |
| Conventional | Multiplex PCR | Throat swab | Influenza A virus | Positive | Detected before BALF tNGS |
| Conventional | Multiplex PCR | Throat swab | Influenza B, adenovirus, RSV, Mycoplasma pneumoniae, rhinovirus | Negative | No target detected |
| Conventional | Standard culture | Blood | Aerobic and anaerobic bacteria; fungi | Negative | Blood culture was obtained on admission |
| Conventional | Standard culture | BALF | Pathogenic bacteria and fungi | Lower respiratory tract normal flora | BAL was obtained after antimicrobial exposure |
| Conventional | Antigen detection | Serum/BALF | Cryptococcal capsular antigen | Negative | No antigen detected |
| Conventional | Serology | Serum | Chlamydia pneumoniae IgM | Negative | No serological support |
| Conventional | Specific DNA assay | BALF | Mycobacterium tuberculosis | Negative | No target detected |
| Conventional | Microscopic staining | BALF/brushing | Acid-fast bacilli | Negative | No acid-fast bacilli observed |
| tNGS 200+ panel | Targeted sequencing | BALF | Chlamydia psittaci | 27,926 reads; 10^3 copies/mL | Pathogenic in report; considered clinically relevant |
| tNGS 200+ panel | Targeted sequencing | BALF | Influenza A H3N2 | 14,671 reads; 10^3 copies/mL | Pathogenic in report; considered clinically relevant |
| tNGS 200+ panel | Targeted sequencing | BALF | Streptococcus pneumoniae | 6,485 reads; 10^3 copies/mL | Conditionally pathogenic; potentially clinically relevant |
| tNGS 200+ panel | Targeted sequencing | BALF | Tropheryma whipplei | 71,003 reads; 10^3 copies/mL | Conditionally pathogenic; not supported as a principal pathogen |
| tNGS 200+ panel | Targeted sequencing | BALF | Aspergillus flavus complex | 217 reads; <10^3 copies/mL | Conditionally pathogenic; not supported as a principal pathogen |
| tNGS 200+ panel | Targeted sequencing | BALF | Staphylococcus epidermidis | 160 reads; <10^3 copies/mL | Microbiota/commensal interpretation |
| Note: Conventional testing identified influenza A but did not identify the additional bacterial pathogens later detected by tNGS.Prior antimicrobial exposure may have reduced BALF culture yield. A sequencing detection was not treated as proof of active infection without clinical correlation. Abbreviations: BALF = bronchoalveolar lavage fluid; tNGS = targeted next-generation sequencing; PCR = polymerase chain reaction; RSV = respiratory syncytial virus; IgM = immunoglobulin M. | |||||
Table 2: Conventional microbiological tests and BALF tNGS findings. Conventional testing detected influenza A but did not identify the additional bacterial pathogens later detected by tNGS. Prior antimicrobial exposure may have reduced culture yield.
Discussion
This case documents mixed respiratory pathogen detections and PE in a single patient. Its educational value lies in the coexistence of these findings and the clinical reasoning used to evaluate them. CTPA for suspected PE, lesion-directed BAL, and molecular testing after inconclusive conventional studies are established clinical practices. Their use here does not establish a new workflow or support routine for CTPA and BAL in all patients with pneumonia. Interpretation of the tNGS findings required separation of detection from causation. C. psittaci and influenza A H3N2 were classified as pathogenic in the laboratory report and were compatible with the clinical presentation. S. pneumoniae was conditionally pathogenic and could also represent airway carriage. Its possible clinical relevance was supported by the lower respiratory specimen, consolidation, severe inflammatory response, neutrophil-predominant BALF cytology, and improvement during antibacterial treatment, but true infection could not be proven independently. The absence of documented bird or poultry contact does not exclude C. psittaci infection, but it limits epidemiological support.
Broad-spectrum antimicrobial therapy had begun before BAL sampling. Prior exposure may have reduced the yield of conventional culture. We therefore do not interpret culture-negative and tNGS-positive results as direct evidence of diagnostic superiority. tNGS provided additional pathogen-specific information in a treated patient, while its predefined target range, contamination risk, and inability to distinguish viable organisms from nucleic acid remain important limitations10,11,12,13. Influenza-associated systemic inflammation and immunothrombotic mechanisms may have contributed to pulmonary thrombosis, but a direct causal relationship was not established in this patient14,15,16,17,18. In the absence of demonstrable lower-extremity DVT, the pulmonary arterial filling defect could represent embolic PE from an undetected venous source or infection-associated in situ pulmonary immunothrombosis. This single case cannot distinguish these mechanisms. Likewise, the temporal improvement during anticoagulation does not show that anticoagulation attenuated systemic inflammation.
Successful use of BALF tNGS depends on lesion-directed sampling, prompt specimen transport, controlled pre-analytical handling, validated quality thresholds, and interpretation alongside conventional testing. The patient had already received antimicrobials; therefore, the findings reflect a treated clinical context. The study also has the limitations of a single-case study, incomplete long-term follow-up, no formal patient-perspective narrative, no independent confirmation of every detected organism, and no direct measurement of the proposed inflammatory or immunothrombotic mechanisms. The initial CTPA was obtained because hypoxemia and an elevated D-dimer raised concern for PE. Subsequent CT examinations were case-specific assessments of persistent or residual structural lung abnormalities and possible underlying malignancy. They do not constitute a routine imaging schedule, and the balance between diagnostic value and radiation exposure should be individualized.
CONCLUSION:
In this patient, CTPA identified a pulmonary arterial filling defect, and BALF tNGS provided additional pathogen-specific information after antimicrobial treatment had begun. The sequencing results required clinical interpretation, particularly for S. pneumoniae and other conditionally pathogenic detections. The findings support cautious, case-specific use of molecular diagnostics and vascular imaging rather than a standardized diagnostic protocol.
Déclarations de divulgation
The author reports no conflicts of interest.
Remerciements
This study was supported by the Wenzhou Municipal Health Commission, Wenzhou City 2025 Medical and Health Research Project (No. 2025025). A large language model tool was used during manuscript revision to polish the language.
Matériaux
| Nom | Entreprise | Numéro de catalogue | Commentaires |
|---|---|---|---|
| 0.9% sodium chloride solution | Baxter | 2B1324 | Sterile lavage fluid |
| Acid-fast stain kit | Sigma-Aldrich | HT80-1KT | Conventional staining |
| Alfentanil | Any Standard Manufacturer | N/A | Intravenous opioid anesthetic; 0.5 mg used |
| Cryptococcal capsular antigen lateral flow assay kit | IMMY | CR2003 | Antigen detection |
| Cytology brush | Olympus | BC-202D-2010 | Bronchial brushing |
| Electronic video bronchoscope | PENTAX Medical | EB-1575K | Flexible bronchoscopy |
| Gram stain kit | Sigma-Aldrich | 77730-1KT | Conventional staining |
| MGISEQ-200 sequencing platform | MGI Tech Co., Ltd. | National Medical Products Administration registration no. 20183400258 | Single-end 50-base-pair sequencing |
| Multiplex pathogen-targeted sequencing assay (200+ panel) | Dian Diagnostics | Service identification: 200+ panel | 231 pathogens and selected resistance genes/variants |
| Propofol | Any Standard Manufacturer | N/A | Intravenous anesthetic; 250 mg used |
| Sequencing reaction universal kit | Dian Diagnostics | Zhejiang Hangzhou medical-device filing no. 20240005 | Sequencing consumable |
Références
- Iuliano AD et al. Estimates of global seasonal influenza-associated respiratory mortality: a modelling study. Lancet. 2018;391(10127):1285-1300.
- Paget J et al. Global mortality associated with seasonal influenza epidemics: new burden estimates and predictors from the GLaMOR Project. J Glob Health. 2019;9(2):020421.
- Lee WC et al. The impacts of bacterial co-infections and secondary bacterial infections on patients with severe influenza pneumonitis admitted to intensive care units. J Crit Care. 2022;72:154164.
- Yang J et al. Co-existence and co-infection of influenza A viruses and coronaviruses: public health challenges. Innovation (Camb). 2022;3(5):100306.
- Fang C et al. Clinical features of 186 cases of Chlamydia psittaci pneumonia: a multicenter study. Infect Drug Resist. 2026;19:563892.
- Ghosh H, Reza S, Mazid MAR, Dewan SMR. Psittacosis in focus: a review addressing the risks and management challenges in outbreak scenarios. Health Sci Rep. 2025;8(5):e70834.
- Zhang W et al. Global research trends on the zoonotic pathogen Chlamydia psittaci from 2006 to 2024: a bibliometric analysis. The Microbe. 2026;11:100710.
- Smith KA, Bradley KK, Stobierski MG, Tengelsen LA. Compendium of measures to control Chlamydophila psittaci (formerly Chlamydia psittaci) infection among humans (psittacosis) and pet birds, 2005. J Am Vet Med Assoc. 2005;226(4):532-539.
- Huang Y, Zheng W, Gan W, Zhang T. Chlamydia psittaci pneumonia: a clinical analysis of 12 patients. Ann Transl Med. 2023;11(3):144.
- Chen Y et al. Application of metagenomic next-generation sequencing in the diagnosis of pulmonary infectious pathogens from bronchoalveolar lavage samples. Front Cell Infect Microbiol. 2021;11:541092.
- Zheng YR, Chen XH, Chen Q, Cao H. Comparison of targeted next-generation sequencing and metagenomic next-generation sequencing in the identification of pathogens in pneumonia after congenital heart surgery: a comparative diagnostic accuracy study. Ital J Pediatr. 2024;50(1):174.
- Society of Clinical Microbiology of China International Exchange and Promotion Association for Medical and Healthcare. Expert consensus on the application and practice of targeted next-generation sequencing in infectious diseases. Zhonghua Yi Xue Za Zhi. 2024;104(48):4375-4383.
- Liang A et al. Targeted next-generation sequencing: an upcoming application for pathogen identification in clinical diagnosis. J Infect Public Health. 2025;18(10):102936.
- Levi M, van der Poll T. Coagulation and sepsis. Thromb Res. 2017;149:38-44.
- Iba T, Levy JH, Raj A, Warkentin TE. Advance in the management of sepsis-induced coagulopathy and disseminated intravascular coagulation. J Clin Med. 2019;8(5):728.
- Qiu X et al. Thrombosis in critically ill influenza patients: incidence and risk factors. Clin Appl Thromb Hemost. 2024;30:10760296241278615.
- Tang N, Li D, Wang X, Sun Z. Abnormal coagulation parameters are associated with poor prognosis in patients with novel coronavirus pneumonia. J Thromb Haemost. 2020;18(4):844-847.
- Lee GD et al. Risk factor and mortality in patients with pulmonary embolism combined with infectious disease. Tuberc Respir Dis (Seoul). 2020;83(2):157-166.
- Metlay JP et al. Diagnosis and treatment of adults with community-acquired pneumonia. An official clinical practice guideline of the American Thoracic Society and Infectious Diseases Society of America. Am J Respir Crit Care Med. 2019;200(7):e45-e67. doi:10.1164/rccm.201908-1581ST.
- Creager MA et al. 2026 AHA/ACC/ACCP/ACEP/CHEST/SCAI/SHM/SIR/SVM/SVN guideline for the evaluation and management of acute pulmonary embolism in adults. Circulation. 2026;153:e977-e1051. doi:10.1161/CIR.0000000000001415.
- Saito Z et al. Safety and efficacy of flexible bronchoscopy in elderly patients: a retrospective comparative study. Open Respir Arch. 2023;5(4):100276.