This analysis assesses the associations of emergency surgery and preoperative frailty with postoperative pulmonary complications (PPCs); both serve as independent factors associated with increased 35 PPC risk, and their coexistence is associated with the highest observed PPC risk, consistent with a joint association and effect modification rather than a causal synergistic effect.
Article de recherche
Emergency Surgery and Preoperative Frailty with Postoperative Pulmonary Complications in Elderly Patients Undergoing Major Abdominal Surgery
Dans cet article
Résumé
Résumé
This single-center retrospective study investigated associations of emergency surgery and preoperative frailty with postoperative pulmonary complications (PPCs) in elderly major abdominal surgery patients. Of 350 initially recruited patients at The First Hospital of Jiaxing (Mar 2024–Mar 2025), 294 were eligible after screening and stratified into PPCs (n = 53) and non-PPCs (n = 241) groups. Multivariate logistic regression identified PPC predictors; interaction analysis evaluated their joint effect. Receiver operating characteristic curves evaluated the predictive performance of individual indicators and the combined model. Between-group disparities were identified in age, American Society of Anesthesiologists class, smoking, diabetes, emergency surgery, preoperative frailty, assess respiratory risk in surgical patients in Catalonia (ARISCAT) score, infusion volume, and postoperative day 1 visual analogue scale (VAS) pain score (all P < 0.05). The PPCs group had higher rates of emergency surgery (P = 0.002) and preoperative frailty (P < 0.001). Patients with both emergency surgery and preoperative frailty had a 35.7% PPCs rate (P < 0.001). Multivariate logistic regression identified age, ARISCAT score, postoperative day 1 VAS pain score, emergency surgery, and preoperative frailty as independent factors associated with PPCs (all P < 0.05). Emergency surgery and preoperative frailty were both independent risk factors for PPCs, and their combination showed a significant multiplicative interaction [interaction odds ratio (OR) = 1.363, 95% confidence interval (CI): 1.010–1.832, P = 0.044], yielding a joint OR notably higher than either factor alone. A combined model including age, emergency surgery, preoperative frailty, ARISCAT score, and postoperative day 1 VAS score achieved an area under the curve of 0.894 (95% CI: 0.833-0.956), which was higher than any single indicator (all P < 0.05). Preoperative frailty was associated with PPCs more strongly than emergency surgery in this cohort, and the two factors showed a joint association; assessment and intensified care are recommended.
Introduction
Driven by the accelerating global trend of population aging, the proportion of elderly patients undergoing major abdominal surgery has been rising steadily year by year. Major abdominal procedures encompass a wide spectrum of interventions, including gastrointestinal, hepatobiliary-pancreatic, splenic, and retroperitoneal surgery. Characterized by extensive surgical trauma, complex operative maneuvers, and marked perioperative physiological disturbances, they place extremely high demands on patients’ physiological reserve capacity1,2. Due to the natural decline in physiological function among elderly individuals—including reduced pulmonary elasticity, diminished chest wall compliance, and weakened diaphragmatic strength—lung function progressively deteriorates. Moreover, elderly patients commonly present with multiple comorbidities. As a result, their risk of developing various postoperative complications is significantly higher compared with younger patients following major abdominal surgery3. Among these complications, postoperative pulmonary complications (PPCs) represent one of the most prevalent perioperative adverse events in elderly patients undergoing major abdominal surgery. PPCs not only prolong hospital stays and inflate medical costs but also substantially elevate perioperative mortality, emerging as a critical risk factor affecting patient prognosis and a key concern for both clinical surgery and anesthesiology departments4.
Clinical research data indicate that the incidence of PPCs after abdominal surgery ranges from 1.3% to 17.5%5. Among elderly patients undergoing major abdominal procedures, however, this rate can exceed 18.0% and even surpass 40% in some high-risk subgroups6. The pathogenesis of PPCs is complex and not fully elucidated. It is thought to involve multiple interconnected factors, such as immunosuppression triggered by surgical stress, atelectasis secondary to restricted diaphragmatic movement, and aspiration or bacterial colonization associated with general anesthesia and nasogastric tube placement. In essence, PPCs arise from the combined effects of patient-related, surgery-related, and postoperative management-related factors7. Of these, the unique physiological and preoperative baseline status of elderly patients, along with the urgency of surgical intervention, is regarded as a key variable influencing PPC development.
Preoperative frailty, a multidimensional physiological syndrome unique to the elderly population and closely linked to advancing age, is defined by diminished physiological reserve and multisystem functional decline. This condition results in markedly reduced tolerance to external stressors such as surgery and infection, representing an independent pathological entity distinct from comorbidities and disability8,9. The development of frailty is associated with sarcopenia, malnutrition, chronic inflammation, oxidative stress, and hormonal metabolic disturbances. Its core feature is the loss of homeostatic regulatory capacity; when challenged by stressors such as surgery, the body struggles to return to its preoperative health status, making patients susceptible to a range of postoperative complications and even mortality10,11,12.
As an important category of major abdominal surgery, emergency procedures differ distinctly from elective operations. They are marked by acute clinical conditions, limited preoperative preparation time, and complex patient baseline status, and are mainly indicated for acute abdominal emergencies, including abdominal trauma, perforated acute appendicitis, and gastroduodenal ulcer perforation13. Patients undergoing emergency surgery frequently present with acute pathological states such as infection, shock, and fluid-electrolyte imbalance. Inadequate preoperative evaluation and preparation further intensify the surgical stress response, leading to a significantly higher risk of postoperative complications relative to elective surgery patients. Existing research has demonstrated that the incidence of PPCs in emergency surgery patients (2.28%) is considerably higher than that in elective surgery patients (0.53%)14. Additionally, the detection rate of multidrug-resistant organisms is elevated in emergency surgical cohorts, further complicating PPC treatment and worsening prognostic outcomes. In elderly patients, who already possess insufficient physiological reserve, the dual impact of acute stress from emergency surgery and insufficient preoperative preparation may exacerbate pulmonary injury and heighten the risk of PPCs15.
To date, researchers worldwide have conducted several investigations into the risk factors for PPCs among elderly patients undergoing major abdominal surgery16. However, most existing studies focus on the impact of isolated factors, with relatively limited attention paid to emergency surgery and preoperative frailty as key determinants. Although preliminary evidence suggests a potential joint association and effect modification between emergency surgery and preoperative frailty, robust supporting data remain scarce17. Furthermore, few studies have compared the predictive value of preoperative frailty and emergency surgery for PPCs, nor have they developed predictive models that combine these two factors with other clinical indicators. Consequently, reliable theoretical support is lacking for identifying and targeting interventions for high-risk patients in clinical settings.
Against this research background, the present study focuses on elderly patients undergoing major abdominal surgery as a high-risk population and employs a single-center retrospective cohort design. It aims to explore the independent associations of emergency surgery and preoperative frailty with the occurrence of PPCs, clarify their respective predictive values, and develop a multi-indicator combined prediction model. The findings are expected to provide a scientific basis for identifying patients at high risk of PPCs and optimizing perioperative management strategies. This study will not only address the current gap in research on the interaction between emergency surgery and preoperative frailty, enriching the literature on risk factors for PPCs in elderly patients undergoing major abdominal surgery, but also deliver actionable clinical interventions to reduce the medical burden. As such, it carries substantial clinical significance and practical application value.
Protocole
This study was performed in strict accordance with the principles outlined in the Declaration of Helsinki. All research procedures were reviewed and approved by the Ethics Committee of The First Hospital of Jiaxing (approval No.: 2023-LY-123; approval date: March 29, 2023; see Supplementary File 1 for the official ethics approval document). A waiver of informed consent was granted due to the retrospective nature of the study, use of de-identified data, and minimal risk to participants. Details of the materials, equipment, and software used in this study are provided in the Table of Materials.
Study design
This work presents a single-center retrospective cohort study conducted at The First Hospital of Jiaxing between March 2024 and March 2025. A total of 350 elderly patients who underwent major abdominal surgery were screened for eligibility. Of the included patients, thirty-two individuals were omitted due to incomplete clinical data, including 10 cases lacking preoperative frailty assessment results, 10 with missing documentation regarding PPC occurrence, 7 missing visual analogue scale (VAS) pain scores on the first postoperative day, and 5 without assess respiratory risk in surgical patients in Catalonia (ARISCAT) scores. Additional exclusions comprised 5 cases of acute myocardial infarction, 2 cases of severe pneumonia, 5 cases of advanced heart failure, 5 patients who received intraoperative tracheotomy, 2 cases of malignant tumor, 2 cases of end-stage uremia, and 3 cases of severe pulmonary fibrosis. Subsequent to exclusion of ineligible patients, a total of 294 patients were finally enrolled in the analysis. Based on whether PPCs occurred during hospitalization, enrolled patients were categorized into the PPCs group (n = 53) and the non-PPCs group (n = 241) (Figure 1).
Inclusion criteria
Patients aged 65 years or older who received major abdominal operations, including radical gastrectomy, radical colorectal cancer resection, cholecystectomy, pancreatic surgery, and intestinal obstruction lysis, with body mass index between 17.5 and 29.0 kg/m2 and an American Society of Anesthesiologists physical status of Grade I to III18. Both laparoscopic and open major abdominal procedures were included.
Emergency surgery was explicitly defined as surgery performed within 24 h after admission or after the acute onset of the condition requiring operative intervention, as documented in the electronic medical record. This definition was intended to capture procedures that could not be postponed for further preoperative optimization and corresponds to the "emergency" category rather than the "urgent" or "semi-urgent" categories. Urgent or semi-urgent procedures, defined as surgery performed more than 24 h but within 72 h after admission, and elective procedures, defined as surgery scheduled in advance after adequate preoperative preparation, were not classified as emergency surgery. In the present cohort, all patients classified as undergoing emergency surgery met the 24 h criterion, and no patients with urgent or semi-urgent procedures were included in the emergency surgery group. The interval between admission and surgery was extracted from the electronic medical record and anesthesia information system for each patient. Because emergency surgery is a major variable in both the primary multivariable analysis and the interaction analysis, this operational definition was pre-specified prior to data analysis and applied uniformly to all patients.
Exclusion criteria
Patients complicated with severe comorbidities including preoperatively active and severe respiratory diseases such as severe pneumonia, hepatic, renal, cardiovascular or cerebrovascular diseases; patients with severe preoperative pneumonia were excluded because an active, uncontrolled pulmonary infection at baseline would substantially confound preoperative frailty assessment and the attribution of postoperative pulmonary complications to emergency surgery and frailty; individuals with stage IV malignant tumors accompanied by extensive distant metastases confirmed by imaging or pathology19; subjects missing core clinical and follow-up data involving frailty evaluation, ARISCAT score, postoperative day 1 VAS pain score or PPC records; patients receiving preoperative or intraoperative pulmonary interventions, or requiring postoperative ICU admission with respiratory support within 24 h for non-pulmonary issues; people suffering from severe mental illnesses or significant cognitive dysfunction; those treated with immunosuppressants two months before surgery; and patients with perioperative blood loss over 2000 mL or an operation time longer than 10 h20. Major abdominal operations were defined as open or laparoscopic abdominal procedures performed under general anesthesia, involving gastrointestinal, hepatobiliary-pancreatic, splenic, or retroperitoneal surgery, with expected moderate-to-high surgical trauma, substantial perioperative physiological disturbance, and a typical operative duration of at least 60 min. Minor procedures such as simple appendectomy, diagnostic laparoscopy, and superficial abdominal wall surgery were not included.
These exclusion criteria were applied to improve internal homogeneity and to reduce confounding by severe baseline cardiopulmonary, renal, hepatic, or neurological disease, stage IV malignancy, major intraoperative blood loss, prolonged operative time, and postoperative ICU respiratory support. However, it should be acknowledged that these criteria also produce a relatively selected elderly population. In particular, elderly patients requiring emergency abdominal surgery who also have severe systemic illness may be precisely the group in whom frailty and emergency surgery are most clinically relevant, and such patients were largely excluded from the present cohort. Therefore, the findings of this study should be generalized with caution to the broader population of elderly patients undergoing major abdominal surgery, especially those with severe comorbidities or extreme perioperative risk profiles.
Diagnostic criteria for PPCs
Diagnosis of PPCs was established in accordance with the official guideline released by the European Joint Task Force in 202121. Patients were diagnosed with PPCs if they met any one of the listed criteria (Table 1). For the primary association analysis, only PPCs occurring after the postoperative day-1 VAS assessment were considered as outcomes, so that the temporal sequence between the postoperative predictor and the outcome was unambiguous. PPCs that occurred before or at the time of the VAS assessment were not counted as events in the primary analysis. The exact timing of PPC onset relative to surgery and to the VAS assessment was extracted from the electronic medical record, and the interval between the VAS assessment and PPC onset was calculated for each case.
Frailty assessment criteria
Preoperative frailty was evaluated using the Fried Frailty Phenotype scale22. This instrument defines frailty based on assessments across five domains. Patients were classified as frail if they met three or more criteria, as pre‑frail if one or two criteria were present, and as robust if none of the criteria were fulfilled (Table 2).
Data extraction
Data were retrospectively collected by two uniformly trained investigators from the hospital’s electronic medical record system, anesthesia information system, and laboratory and imaging databases for a total of 294 elderly patients who underwent major abdominal surgery between March 2024 and March 2025. Baseline characteristics, including sex, age, BMI, ASA physical status, educational level, smoking history, alcohol consumption history, hypertension, diabetes mellitus, coronary heart disease, symptomatic stroke, surgical site, metabolic equivalents (METs), preoperative peripheral capillary oxygen saturation (SpO₂), preoperative hemoglobin (Hb), preoperative white blood cell count (WBC), and preoperative albumin (ALB), were extracted from medical records obtained within 72 h before surgery. Frailty status and ARISCAT score were obtained from anesthesia preoperative evaluation documents completed within 24 h prior to the operation. Information regarding emergency versus elective surgery, intraoperative blood loss, fluid infusion volume, anesthesia duration, and operative time was gathered from intraoperative and anesthesia records on the day of surgery. The VAS pain score on the first postoperative day was derived from pain assessments performed within 24 h after surgery and before any confirmed PPC events. The occurrence of PPCs was defined as the first confirmed event during hospitalization occurring after the postoperative day-1 VAS assessment, based on which patients were categorized into the PPCs group (n = 53) and non-PPCs group (n = 241). Information regarding emergency versus elective surgery, including the exact time of admission, the time of surgery, and the interval between admission and surgery, was gathered from intraoperative and anesthesia records on the day of surgery. Patients were classified as undergoing emergency surgery only if the interval between admission and surgery was within 24 h; patients whose surgery was performed more than 24 h after admission were classified as undergoing elective or non-emergency surgery. After data collection, all entries were independently cross‑checked and organized by the two researchers to ensure accuracy and completeness.
Outcome measures
Height and body weight were measured using a mechanical height-weight scale, and BMI was calculated accordingly. SpO₂ was measured with a finger-clip pulse oximeter. For hematological testing, fasting peripheral venous blood (5 mL) was sampled from each patient and collected in anticoagulant tubes. Hb and WBC were determined in whole blood using an automated hematology analyzer. Another 5 mL sample of fasting venous blood was placed in serum-separating tubes without anticoagulant and centrifuged at 1500 × g for 10 min using a centrifuge to obtain serum. Serum ALB was then measured from the separated serum sample with an automated biochemical analyzer. Postoperative pain intensity was evaluated using VAS. Scores ranged from 0 to 10, with higher scores indicating more severe pain23. The VAS assessment was performed within the first 24 postoperative hours. To avoid reverse causation, the VAS score was treated as a postoperative variable rather than as a preoperative etiological risk factor. Only PPCs occurring after the VAS assessment were included in the primary analysis, and the time from surgery and from the VAS assessment to PPC onset was documented. The ASA physical status classification was assigned by attending anesthesiologists or senior physicians based on overall health and severity of comorbidities. Grade I was defined as a completely healthy individual with no systemic disease. Grade II indicated mild systemic disease without functional impairment. Grade III represented severe systemic disease with definite functional limitation. Grade IV referred to severe systemic disease that posed a constant threat to life. Grade V denoted a moribund patient unlikely to survive 24 h with or without surgery24. The ARISCAT score was completed by anesthesiologists. This scoring system included seven domains: age, preoperative SpO₂, recent respiratory infection within one month, preoperative anemia, surgical site, operative duration, and emergency surgery. The total possible score spanned 0 to 53, and a higher score indicated an increased risk of PPCs16. Data on operative time, anesthesia duration, intraoperative blood loss, fluid infusion volume, and METs were all retrieved from anesthesia records and perioperative nursing documents.
Sample size calculation
PPCs were set as the primary endpoint. The primary analysis of this study was multivariable logistic regression, on which a combined prediction model was further constructed. Therefore, the sample size justification should be aligned with prediction model development rather than with precision-based estimation of a single proportion. According to previous literature, the incidence of PPCs in elderly patients undergoing major abdominal surgery was reported to be approximately 11.3%25. In this study, the EPV (events per variable) rule, which is commonly used in clinical prediction model development, was adopted for sample size estimation. This rule requires at least 10 outcome events per predictor variable included in logistic regression. The final primary multivariable logistic regression model contained exactly eight fitted covariates, as reported in Table 3: age, ASA physical status ≥ Grade III, smoking history, diabetes mellitus, intraoperative fluid infusion volume, postoperative day 1 VAS pain score, emergency surgery, and preoperative frailty. No additional covariates, including the ARISCAT composite score or its non-overlapping components (preoperative SpO₂, recent respiratory infection, preoperative anemia, surgical site, and operative duration), were entered into the final fitted primary model. Therefore, the minimum required number of events was 8 × 10 = 80 PPC events. Based on the expected PPC incidence of 11.3%, the total sample size required to achieve 80 events was 80 ÷ 0.113 ≈ 708 cases. A total of 294 patients were actually enrolled in this study, among whom 53 developed PPCs, yielding an overall incidence of 18%. With 53 actual events corresponding to the eight fitted predictors in the primary model, the EPV was 6.6, which is below the conventional threshold of EPV ≥ 10. In addition, the interaction model included a further product term (emergency surgery × preoperative frailty) on top of age, emergency surgery, preoperative frailty, and postoperative day 1 VAS pain score, so the EPV for the interaction model was even lower than that for the primary model. This raises concerns regarding potential model instability and overfitting. Therefore, the apparent AUC of the combined prediction model should be regarded as a preliminary estimate in the derivation dataset rather than as a validated measure of predictive performance. The conclusions of this study are primarily based on effect estimates and their 95% confidence intervals; model stability and predictive performance still require further confirmation through internal and external validation. Future studies with larger sample sizes, sufficient event numbers, and formal internal and external validation are needed to confirm the robustness and generalizability of the combined prediction model.
Statistical analysis
Normality (Kolmogorov‑Smirnov test) and homogeneity of variance (Levene test) were first examined for all continuous variables. Data with normal distribution and homogeneous variance were presented as mean ± standard deviation (mean ± SD), and between‑group comparisons were performed using an independent samples t‑test. Non‑normally distributed data were expressed as median (interquartile range) [M (Q1, Q3)] and compared using the Mann‑Whitney U test. Categorical variables were reported as number (percentage) [n (%)] and analyzed using the chi‑square test; if the expected frequency was less than 5, Fisher’s exact test was applied instead.
Logistic regression analysis was conducted to identify independent factors associated with PPCs. The occurrence of PPCs (yes = 1, no = 0) was taken to be the dependent variable. The variables included in the multivariable logistic regression model were pre-specified based on clinical reasoning and prior literature, rather than selected solely based on univariable P values. Specifically, the predictors were chosen a priori because they are established or plausible factors associated with PPCs in elderly patients undergoing major abdominal surgery, including age, ASA physical status, smoking history, diabetes mellitus, intraoperative fluid infusion volume, postoperative day 1 VAS pain score, emergency surgery, and preoperative frailty. These variables were retained in the model irrespective of their univariable P values, so that the model would not be driven by data-dependent selection and to reduce the risk of unstable estimates and biased inference in a relatively small dataset. Accordingly, the final primary multivariable logistic regression model contained exactly eight covariates: age (continuous, years), ASA physical status ≥ Grade III (yes/no), smoking history (yes/no), diabetes mellitus (yes/no), intraoperative fluid infusion volume (continuous), postoperative day 1 VAS pain score (continuous), emergency surgery (yes/no), and preoperative frailty (yes/no). These eight variables are exactly the covariates reported in Table 3, and no additional covariates were entered into the primary model. Although the non-overlapping components of the ARISCAT score available in the dataset (preoperative SpO₂, recent respiratory infection, preoperative anemia, surgical site, and operative duration) were initially considered, they were not included in the final fitted primary model because of the limited number of PPC events (53 events) and the resulting concern regarding model instability and overfitting; the ARISCAT composite score was likewise not included because age and emergency surgery are constituent components of ARISCAT, and including the composite score together with its own constituents would create conceptual overlap and complicate the interpretation of the regression coefficients. The interaction model was specified separately from the primary model and included age, emergency surgery, preoperative frailty, postoperative day 1 VAS pain score, and the product term emergency surgery × preoperative frailty; the ARISCAT composite score was not included because emergency surgery is one of its constituent items. The main-effect estimates for emergency surgery and preoperative frailty reported in Table 4 were derived from this interaction model.
Univariable analyses were performed for descriptive purposes and to characterize between-group differences, but the univariable P value was not used as the sole criterion for entry into the multivariable model. Because age and emergency surgery are both components of the ARISCAT score, including the composite ARISCAT score, along with its individual components, in the same model would create conceptual overlap and complicate the interpretation of the regression coefficients. Therefore, the ARISCAT composite score was not included in the primary multivariable model. Instead, the non-overlapping components of ARISCAT available in the dataset, including age, preoperative SpO₂, recent respiratory infection, preoperative anemia, surgical site, and operative duration, were considered alongside emergency surgery, preoperative frailty, and postoperative day 1 VAS pain score. This specification avoids modeling a composite score simultaneously with its own constituents and allows the coefficient for emergency surgery to be interpreted as its independent association with PPCs rather than as an effect conditional on a score that already contains emergency surgery. A sensitivity analysis using the ARISCAT composite score instead of its individual components was not performed because the two specifications condition on different sets of covariates, and their coefficients are not directly comparable; the primary model was pre-specified to address the conceptual overlap issue. An interaction term “emergency surgery × preoperative frailty” was incorporated (both were binary variables: emergency surgery, yes = 1, no = 0; preoperative frailty, yes = 1, no = 0). To examine whether emergency surgery modifies the association between preoperative frailty and PPCs, the interaction model was specified without the ARISCAT composite score, because ARISCAT already contains emergency surgery as a constituent item, and its inclusion would make the interaction term difficult to interpret. The interaction model, therefore, included age, emergency surgery, preoperative frailty, postoperative day 1 VAS pain score, and the other non-overlapping components of ARISCAT available in the dataset.
Because the number of PPC events was relatively small (53 events) relative to the number of parameters in the multivariable and interaction models, the events-per-variable ratio was relatively low. This raises concerns regarding model instability and overfitting, and the regression coefficients and apparent predictive performance should therefore be interpreted with caution. The combined prediction model should be regarded as hypothesis-generating rather than as a validated risk-prediction tool, and future studies with larger samples and formal internal and external validation are needed to confirm the robustness of the estimates.
The statistical significance of the multiplicative interaction was evaluated using odds ratio (OR), 95% confidence interval (95% CI), and corresponding P values. Because the outcome was not rare (PPCs incidence approximately 18%), OR-based interaction measures were interpreted as measures of association rather than direct causal risk interaction. Additive interaction indices such as RERI, AP, and S were not reported because they could not be reproducibly derived from the fitted model with internal consistency. Receiver operating characteristic (ROC) curve analysis was performed to assess the predictive value of each indicator for PPCs. The area under the curve (AUC), sensitivity, and specificity were calculated to evaluate predictive performance. All statistical tests were two-sided, and P < 0.05 was considered statistically significant. The number of outcome events was relatively small (53 PPC events) relative to the complexity of the multivariable and interaction models. With several predictors, including age, ASA physical status, smoking history, diabetes mellitus, intraoperative fluid infusion volume, postoperative day 1 VAS pain score, emergency surgery, and preoperative frailty, the number of events per model parameter was relatively low. Although the traditional “10 events per variable” rule should not be treated as an absolute threshold, this sample size nonetheless raises a substantial concern regarding model instability and overfitting. The reported predictive performance of the combined model should therefore be regarded as apparent performance in the derivation dataset only; no internal validation, bootstrap correction, or optimism adjustment was performed, and the model's predictive performance may be overestimated.
Résultats
Baseline Data
Baseline clinical characteristics of 53 patients who developed PPCs (the PPCs group) and 241 patients without such complications (the non‑PPCs group) are outlined in Table 5. Relative to the non‑PPCs group, patients experiencing PPCs group were significantly older, had a higher proportion of ASA physical status ≥ Grade III, a higher prevalence of smoking history, a higher rate of diabetes mellitus, higher ARISCAT risk scores, greater intraoperative fluid infusion volume, and higher VAS pain scores on postoperative day 1 (all P < 0.05). All these factors were associated with an elevated risk of PPCs (OR > 1). Conversely, METs value ≥ 4 was less frequently observed in the PPCs group (P = 0.070), showing a propensity for reduced PPC risk (OR = 0.44). No statistically significant intergroup differences were detected in terms of sex, BMI, educational level, alcohol consumption history, other comorbidities including hypertension, coronary heart disease, and symptomatic stroke, surgical site, preoperative SpO₂, Hb level, WBC, ALB concentration, intraoperative blood loss, anesthesia duration, surgical approach, or operative duration (all P > 0.05).
Distribution of preoperative frailty and emergency surgery between the PPCs and non‑PPCs Groups
Compared with the non‑PPCs group, the PPCs group presented a markedly higher proportion of emergency operations (32.1% vs 14.5%, P = 0.002, Phi = 0.177) and a significantly greater prevalence of preoperative frailty (49.1% vs 24.9%, P < 0.001, Phi = 0.204). In stratified analyses, the PPCs group also showed significantly higher rates of frailty combined with elective surgery (30.2% vs 17.4%, P = 0.035, Phi = 0.123) and frailty combined with emergency surgery (18.9% vs 7.5%, P = 0.010, Phi = 0.149). By contrast, no significant intergroup difference was observed in the proportion of emergency surgery among non‑frail patients (13.2% vs 7.1%, P = 0.139). These findings suggest that both preoperative frailty and emergency surgery are more prevalent among patients who develop PPCs, and their coexistence may be associated with an even stronger link to the occurrence of PPCs (Table 6).
Comparison of PPCs incidence across different subgroups
The incidence of PPCs was 10.9% in the subgroup of elective surgery with non‑frail patients (n = 184), 27.6% in the elective surgery plus frail subgroup (n = 58), 29.2% in the emergency surgery plus non‑frail subgroup (n = 24) and reached as high as 35.7% in the emergency surgery plus frail subgroup (n = 28). Intergroup differences were statistically significant overall (P < 0.001), with a Cramer’s V effect size of 0.247. These results indicate that patients with both emergency surgery and preoperative frailty had the highest observed PPC incidence (Table 7).
Multivariable logistic regression analysis for independent factors associated with PPCs
Table 3 summarizes the results of multivariable logistic regression analysis aimed at identifying independent factors associated with PPCs. Because age and emergency surgery are constituent components of the ARISCAT score, the ARISCAT composite score was not included in the primary model; instead, its non-overlapping components available in the dataset were considered. After adjusting for potential confounders including ASA physical status, smoking history, diabetes mellitus, and intraoperative fluid infusion volume, the analysis demonstrated that age (β = 0.093, P = 0.001, OR = 1.098, 95% CI: 1.038–1.161), VAS pain score on the first postoperative day (β = 0.345, P = 0.003, OR = 1.412, 95% CI: 1.128–1.768), emergency surgery (β = 1.049, P = 0.003, OR = 2.856, 95% CI: 1.423–5.734), and preoperative frailty (β = 0.988, P = 0.005, OR = 2.685, 95% CI: 1.356–5.316) were all independent factors associated with PPCs. Variance inflation factors (VIF) for all variables were relatively low, suggesting that multicollinearity was within an acceptable range. By contrast, ASA physical status ≥ Grade III, smoking history, diabetes mellitus, and intraoperative fluid volume showed no statistically significant associations in the multivariable model (all P > 0.05).
Interaction analysis for the combined effect of emergency surgery and preoperative frailty
Table 4 presents the results of multiplicative interaction analysis assessing the joint effect of emergency surgery and preoperative frailty on the risk of PPCs. The interaction model did not include the ARISCAT composite score because emergency surgery is one of its constituent items. Both emergency surgery (OR = 2.856, 95% CI: 1.423–5.734, P = 0.003) and preoperative frailty (OR = 2.685, 95% CI: 1.356–5.316, P = 0.005) were independently associated with PPCs. The observed joint OR for patients with both emergency surgery and preoperative frailty was 10.452 (95% CI: 4.823–22.658, P < 0.001), which was higher than the OR associated with either factor alone. The multiplicative interaction OR was 1.363 (95% CI: 1.010–1.832, P = 0.044), suggesting that emergency surgery modifies the association between preoperative frailty and PPCs on the multiplicative scale. However, the four-group analysis showed that the difference between frail and non-frail patients within the emergency surgery group was relatively modest compared with the overall difference between elective and emergency surgery, and the interaction estimate was based on a limited number of events. Therefore, this finding should be described as effect modification or a joint association rather than as evidence of a causal biological synergy, and it should be interpreted as an association rather than direct causal risk interaction because PPCs were not rare.
Predictive value of individual indicators and combined model for PPCs by ROC curve analysis
As observed in Figure 2 and Table 8, among single indicators, preoperative frailty yielded an AUC of 0.819 (95% CI: 0.744–0.894), whose predictive capacity was significantly superior to that of emergency surgery (AUC = 0.762, 95% CI: 0.679–0.846; P = 0.010). The AUC values for the ARISCAT score and VAS pain score on the first postoperative day were 0.717 (95% CI: 0.653–0.782) and 0.734 (95% CI: 0.653–0.816), respectively. A combined predictive model was constructed incorporating age, emergency surgery, preoperative frailty, ARISCAT score, and VAS pain score on postoperative day 1. This integrated model achieved an AUC of 0.894 (95% CI: 0.833–0.956). At the optimal cutoff value of 0.42, the model demonstrated a sensitivity of 88.7% and a specificity of 82.3%. The Hosmer‑Lemeshow goodness‑of‑fit test yielded a P value of 0.811, supporting satisfactory model calibration. DeLong test further confirmed that the combined model exhibited significantly better predictive performance than any single indicator (all P < 0.05). These results indicate that the proposed combined model showed favorable apparent predictive performance for PPCs in elderly patients undergoing major abdominal surgery. However, because only 53 PPC events were available and no internal validation or optimism correction was performed, this AUC should be interpreted as an apparent estimate in the derivation dataset rather than as a validated measure of predictive performance, and it may be optimistically biased.
DATA AVAILABILITY:
The de-identified data supporting the findings of this study are provided in Supplementary File 2.
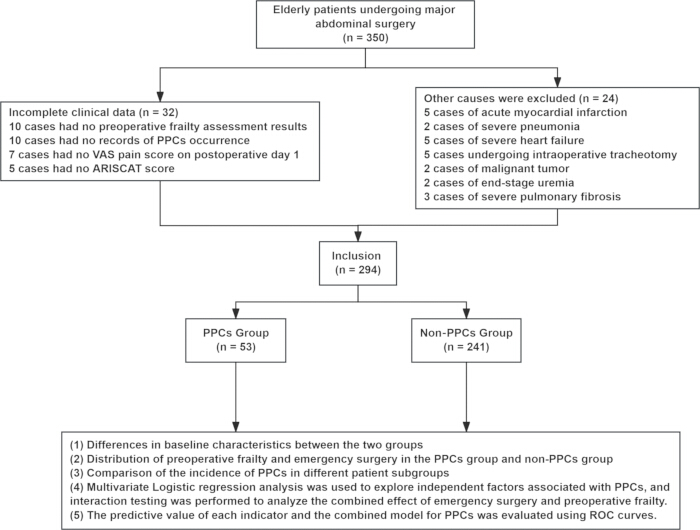
Figure 1: Flowchart of patient enrollment and study inclusion. A total of 350 patients were initially screened in this study. After exclusion, 294 cases were finally enrolled, including 53 cases in the PPCs group and 241 cases in the non-PPCs group. Abbreviations: VAS, Visual Analogue Scale; ARISCAT, Assess Respiratory Risk in Surgical Patients in Catalonia; PPCs, Postoperative Pulmonary Complications; ROC, Receiver Operating Characteristic. Please click here to view a larger version of this figure.
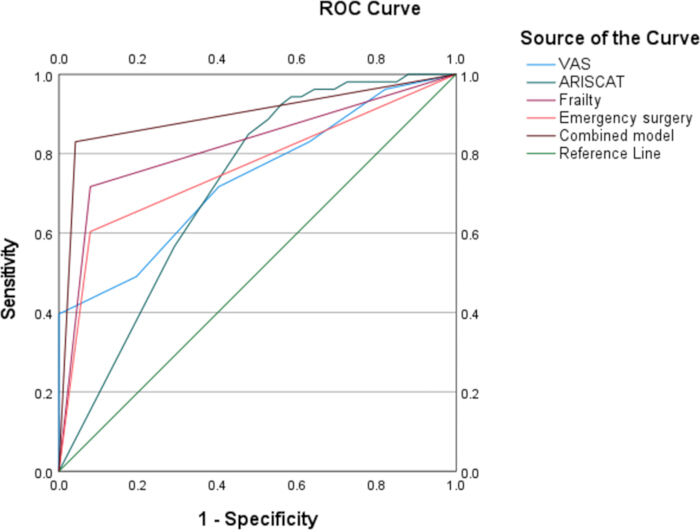
Figure 2: ROC curve for evaluating the predictive value of each indicator and the combined model for PPCs. This figure shows the ROC curve, illustrating the predictive value of preoperative frailty, emergency surgery, ARISCAT score, and VAS pain score on postoperative day 1, as well as the predictive performance of a combined prediction model constructed based on age, emergency surgery, preoperative frailty, ARISCAT score, and VAS pain score on postoperative day 1. Please click here to view a larger version of this figure.
| Feature | Assessment Criteria |
| Pulmonary infection | Suspected respiratory infection treated with antibiotics and meeting at least one of the following: new or changed sputum production; new or progressive pulmonary infiltration; fever; WBC > 12 × 109/L |
| Respiratory failure | PaO₂ < 60 mmHg (1 mmHg = 0.133 kPa) while breathing room air, PaO₂/FiO₂ < 300 mmHg, or SpO₂ < 90%, requiring oxygen therapy |
| Pleural effusion confirmed by imaging | ‐ |
| Atelectasis confirmed by imaging | ‐ |
| Pneumothorax confirmed by imaging | ‐ |
| Bronchospasm | New-onset wheezing auscultated requiring bronchodilator therapy |
| Aspiration pneumonia | Acute lung injury following aspiration of gastric contents |
Table 1: Diagnostic criteria for PPCs. Definitions of each type of PPC, including pulmonary infection, respiratory failure, imaging-verified pleural effusion, atelectasis, pneumothorax, bronchospasm, and aspiration pneumonia are listed. Abbreviations: WBC, White Blood Cell; PaO2, Partial pressure of oxygen in arterial blood; FiO2,Fraction of inspired oxygen; SpO2, Peripheral capillary oxygen saturation.
| Feature | Assessment Criteria |
| Unintentional weight loss | Unintentional weight loss (without deliberate weight loss) ≥ 5% or ≥ 4.5 kg in the past year |
| Reduced grip strength | Grip strength of the dominant hand (or non-dominant hand, if specified) measured by a hand-held dynamometer, below the cutoff values stratified by sex and BMI (e.g., males: 24 kg/m2 < BMI ≤ 26 kg/m2: grip strength ≤ 30 kg; females: 23 kg/m2 < BMI ≤ 26 kg/m2: grip strength ≤ 17.3 kg) |
| Self-reported exhaustion/low energy | Frequent feelings (≥ 3 days/week) of “everything requires effort” or “cannot keep going” in the past 4 weeks |
| Slow walking speed | Time taken to walk 4.57 meters at usual pace, converted to speed (m/s), below the cutoff values stratified by sex and height (e.g., males: height ≤ 173 cm: speed ≤ 0.65 m/s; females: height ≤ 159 cm: speed ≤ 0.65 m/s) |
| Low physical activity level | Using a simplified assessment: “In the past week, how many times did you engage in moderate or vigorous activities that made you sweat or breathe faster (e.g., brisk walking, cycling, swimming, dancing, gardening, heavy lifting, etc.)?” Low physical activity is defined as ≤ 1 time/week for males and ≤ 1 time/week for females |
Table 2: Diagnostic criteria for preoperative frailty. Diagnostic criteria for preoperative frailty based on five core indicators, including weight loss, grip strength, fatigue, walking speed, and physical activity. Cutoff thresholds stratified by sex, BMI, or height are provided. Abbreviations: BMI, Body Mass Index.
| Indicators | β | P | OR | 95% CI for OR | VIF |
| Age | 0.093 | 0.001 | 1.098 | 1.038‐1.161 | 1.216 |
| ASA ≥ 3 | 0.756 | 0.067 | 2.13 | 0.950‐4.776 | - |
| Smoking history | 0.542 | 0.174 | 1.719 | 0.788‐3.751 | - |
| Diabetes mellitus | 0.485 | 0.21 | 1.624 | 0.761‐3.466 | - |
| Infusion volume | 0.612 | 0.086 | 1.844 | 0.917‐3.709 | - |
| VAS score on postoperative day 1 | 0.345 | 0.003 | 1.412 | 1.128‐1.768 | 1.502 |
| Emergency surgery | 1.049 | 0.003 | 2.856 | 1.423‐5.734 | 2.265 |
| Frailty | 0.988 | 0.005 | 2.685 | 1.356‐5.316 | 1.112 |
Table 3: Multivariate logistic regression analysis of independent factors associated with PPCs. Multivariate logistic regression identifying independent factors associated with PPCs. Regression coefficient (β), P values, odds ratios (OR), 95% confidence intervals and variance inflation factor (VIF) are listed. The ARISCAT composite score was not included because age and emergency surgery are constituent components of ARISCAT; instead, the non-overlapping components of ARISCAT available in the dataset were considered. Abbreviations: VIF, Variance Inflation Factor
| Indicators | OR | 95% CI for OR | P |
| Emergency surgery | 2.856 | 1.423‐5.734 | 0.003 |
| Frailty | 2.685 | 1.356‐5.316 | 0.005 |
| Observed joint effect of emergency surgery plus frailty | 10.452 | 4.823‐22.658 | < 0.001 |
| Multiplicative interaction OR | 1.363 | 1.010‐1.832 | 0.044 |
Table 4: Multiplicative interaction analysis for the combined effect of emergency surgery and preoperative frailty. Multiplicative interaction analysis evaluating the joint effect of emergency surgery and preoperative frailty on PPCs. Odds ratios, 95% CIs, and P values are presented. The multiplicative interaction OR was calculated from the same multivariable logistic regression model. The interaction model did not include the ARISCAT composite score because emergency surgery is a constituent item of ARISCAT; this specification allows the interaction term to be interpreted as the modification of the frailty–PPCs association by emergency surgery. Because PPCs were not rare (approximately 18%), the multiplicative interaction OR should be interpreted as a measure of association rather than a direct causal risk interaction. Additive interaction indices (RERI, AP, S) were not reported because they could not be reproducibly derived with internal consistency from the fitted model.
| Indicators | PPCs Group | NonPPCs Group | P | OR | 95% CI for OR |
| (n = 53) | (n = 241) | ||||
| Age [years, M (Q1, Q3)] | 74.0 (71.5, 78.5) | 71.0 (68.0, 73.0) | < 0.001 | 1.08 | 1.04–1.13 |
| Gender (n %) | 0.994 | 0.99 | 0.56–1.77 | ||
| Male | 29 (54.7) | 132 (54.8) | |||
| Female | 24 (45.3) | 109 (45.2) | |||
| BMI [kg/m2, M (Q1, Q3)] | 24.9 (23.1, 25.7) | 24.3 (22.9, 25.6) | 0.227 | 1.06 | 0.96–1.17 |
| ASA classification (n %) | 0.004 | 2.97 | 1.39–6.33 | ||
| < 3 | 8 (15.1) | 86 (35.7) | |||
| ≥ 3 | 45 (84.9) | 155 (64.3) | |||
| Education level (n %) | 0.232 | 0.67 | 0.34–1.31 | ||
| Primary school or below | 27 (50.9) | 113 (46.9) | |||
| Junior high school | 14 (26.4) | 88 (36.5) | |||
| Senior high school / technical secondary school | 6 (11.3) | 28 (11.6) | |||
| College or above | 6 (11.3) | 12 (5.0) | |||
| Smoking history (n %) | 33 (62.3) | 90 (37.3) | 0.001 | 2.79 | 1.54–5.04 |
| Alcohol drinking history (n %) | 31 (58.5) | 109 (45.2) | 0.08 | 1.69 | 0.94–3.02 |
| Comorbidities (n %) | |||||
| Hypertension | 27 (50.9) | 113 (46.9) | 0.592 | 1.17 | 0.66–2.08 |
| Diabetes mellitus | 20 (37.7) | 45 (18.7) | 0.002 | 2.62 | 1.42–4.82 |
| Coronary heart disease | 21 (39.6) | 69 (28.6) | 0.116 | 1.62 | 0.89–2.97 |
| Symptomatic stroke | 10 (18.9) | 31 (12.9) | 0.253 | 1.57 | 0.72–3.42 |
| Surgical site (n %) | 0.743 | 1.34 | 0.63–2.85 | ||
| Gastrointestinal | 35 (66.0) | 164 (68.0) | |||
| Liver | 10 (18.9) | 35 (14.5) | |||
| Spleen | 5 (9.4) | 20 (8.3) | |||
| Pancreas | 3 (5.7) | 22 (9.1) | |||
| METs (n %) | 0.07 | 0.44 | 0.18–1.07 | ||
| < 4 | 47 (88.7) | 187 (77.6) | |||
| ≥ 4 | 6 (11.3) | 54 (22.4) | |||
| Preoperative SpO₂ [%, M (Q1, Q3)] | 94.7 (92.2, 98.4) | 95.5 (92.7, 98.0) | 0.67 | 0.95 | 0.76–1.19 |
| ARISCAT risk category [scores, M (Q1, Q3)] | 32.0 (27.0, 36.0) | 25.0 (16.5, 32.0) | < 0.001 | 1.12 | 1.06–1.18 |
| Hb [g / L, M (Q1, Q3)] | 140.1 (138.2, 142.0) | 139.3 (137.5, 141.4) | 0.076 | 1.07 | 0.99–1.15 |
| WBC [× 10⁹/L, M (Q1, Q3)] | 6.6 (5.9, 7.5) | 6.6 (5.4, 7.6) | 0.239 | 1.03 | 0.98–1.08 |
| ALB [g/L, M (Q1, Q3)] | 47.9 (44.7, 51.0) | 47.9 (44.4, 51.2) | 0.56 | 0.95 | 0.52–1.31 |
| Blood loss [mL, M (Q1, Q3)] | 176.3 (152.3, 212.5) | 180.8 (145.7, 212.5) | 0.924 | 0.92 | 0.85–1.05 |
| Infusion volume [mL, M (Q1, Q3)] | 1386.4 (1125.6, 1738.5) | 1280.2 (1168.3, 1380.8) | 0.015 | 1.15 | 1.12–1.18 |
| Anesthesia time [min, M (Q1, Q3)] | 216.0 (179.5, 256.0) | 213.0 (174.0, 245.0) | 0.175 | 0.77 | 0.42–1.12 |
| Operation time [min, M (Q1, Q3)] | 183.0 (164.0, 212.0) | 173.0 (152.0, 201.0) | 0.11 | 1.01 | 0.95–1.07 |
| VAS score on postoperative day 1 [scores, M (Q1, Q3)] | 7.0 (5.0, 7.0) | 4.0 (3.0, 5.0) | < 0.001 | 2.17 | 1.75–2.70 |
| Surgical approach (n %) | 0.93 | 0.974 | 0.534, 1.774 | ||
| Laparoscopic | 30 (56.6) | 138 (57.3) | |||
| Open | 23 (43.4) | 103 (42.7) |
Table 5: Baseline clinical data. Baseline clinical characteristics of older adults stratified by presence or absence of PPCs. Univariate comparisons report P values, OR, and corresponding 95% CI. Abbreviations: OR, Odds Ratio; 95%CI, 95% Confidence Interval; BMI, Body Mass Index; Hb, Hemoglobin; WBC, White Blood Cell Count; VAS, Visual Analogue Scale; PPCs, Postoperative Pulmonary Complications; ASA, American Society of Anesthesiologists; METs, Metabolic Equivalents; SpO2, Peripheral capillary oxygen saturation; ARISCAT, Assess Respiratory Risk in Surgical Patients in Catalonia; ALB, Albumin.
| Indicators | PPCs Group | Non‑PPCs Group | P | Effect size (Phi) |
| (n = 53) | (n = 241) | |||
| Elective surgery | 36 (67.9) | 206 (85.5) | 0.002 | 0.177 |
| Emergency surgery | 17 (32.1) | 35 (14.5) | 0.002 | 0.177 |
| Frailty | 26 (49.1) | 60 (24.9) | < 0.001 | 0.204 |
| Elective surgery + frailty | 16 (30.2) | 42 (17.4) | 0.035 | 0.123 |
| Emergency surgery + non-frailty | 7 (13.2) | 17 (7.1) | 0.139 | 0.086 |
| Emergency surgery + frailty | 10 (18.9) | 18 (7.5) | 0.01 | 0.149 |
Table 6: Distribution of preoperative frailty and emergency surgery between the PPCs group and non‑PPCs group (n %). Distribution of preoperative frailty and emergency surgery status in PPCs and non-PPCs groups, presented as case numbers and percentages. P values and Phi effect sizes for intergroup comparisons are displayed.
| Indicators | PPCs |
| Elective surgery + non-frailty (n = 184) | 20 (10.9) |
| Elective surgery + frailty (n = 58) | 16 (27.6) |
| Emergency surgery + non-frailty (n = 24) | 7 (29.2) |
| Emergency surgery + frailty (n = 28) | 10 (35.7) |
| P | < 0.001 |
| Effect size (Cramer’s V) | 0.247 |
Table 7: Comparison of the incidence of PPCs in different patient subgroups. Incidence rates of postoperative pulmonary complications (PPCs) across four subgroups stratified by emergency surgery and preoperative frailty status. Overall P value and Cramer’s V effect size are shown.
| Indicators | Cut-off | Sensitivity (%) | Specificity (%) | AUC | 95% CI for AUC | Hosmer-Lemeshow (P) | Delong (P) |
| Combined Model | 0.42 | 88.7 | 82.3 | 0.894 | 0.833‐0.956 | 0.811 | - |
| Frailty | 0.18 | 86.2 | 75.8 | 0.819 | 0.744‐0.894 | 0.085 | 0.001 |
| Emergency surgery | 1 | 79.4 | 68.9 | 0.762 | 0.679‐0.846 | 0.102 | < 0.001 |
| ARISCAT score | 27 | 75.6 | 65.2 | 0.717 | 0.653‐0.782 | 0.144 | < 0.001 |
| VAS pain score on postoperative day 1 | 4 | 77.3 | 67.5 | 0.734 | 0.653‐0.816 | 0.095 | 0.002 |
Table 8: Diagnostic efficacy indicators of ROC curve. Predictive performance of single predictors and the combined model for PPCs assessed via ROC analysis, including cutoff values, sensitivity, specificity, AUC, 95% CIs, Hosmer-Lemeshow and DeLong test P values. Abbreviations: ROC, Receiver Operating Characteristic; AUC, Area Under the Curve.
Supplementary File 1: Ethical approval document. This file contains the ethical approval (Opinion No. 2023-LY-123, Acceptance No. 2023-KY-133) from the Medical Ethics Committee of the First Hospital of Jiaxing through an expedited review on March 28, 2023. Follow-up review is required every 12 months. Please click here to download this file.
Supplementary File 2: De-identified raw clinical data. This file contains the de-identified raw clinical data of the 294 enrolled elderly patients who underwent major abdominal surgery. Patients are stratified into the PPCs group (n = 53) and non-PPCs group (n = 241). This dataset contains demographic characteristics, preoperative laboratory and evaluation indicators, comorbidities, surgical-anesthesia-related parameters, and postoperative pain scores. Please click here to download this file.
Discussion
In this retrospective study involving 294 elderly patients undergoing major abdominal surgery, the overall incidence of PPCs was18.0%, which is generally consistent with the 11%–45% range reported in previous literature25,26. Multivariate logistic regression analysis identified age, ARISCAT risk score, VAS pain score on the first postoperative day, emergency surgery, and preoperative frailty as independent factors associated with PPCs. Of particular note, the coexistence of emergency surgery and preoperative frailty was associated with a significantly higher joint OR for PPCs, with a multiplicative interaction OR of 1.363 (95% CI: 1.010-1.832), indicating that emergency surgery modifies the association between preoperative frailty and PPCs on the multiplicative scale. This finding is more appropriately interpreted as effect modification or a joint association than as a causal synergistic effect, particularly because the four-group analysis showed that the difference between frail and non-frail patients within the emergency surgery group was relatively modest compared with the overall difference between elective and emergency surgery. A combined predictive model constructed based on the above factors achieved an apparent AUC of 0.894. However, given the relatively small number of PPC events (n = 53) compared with the number of parameters in the multivariable and interaction models, the events-per-variable ratio was low, raising concerns about model instability and overfitting. In addition, no internal validation or optimism correction was performed; therefore, the reported AUC reflects apparent performance on the derivation dataset and may overestimate the model's true predictive performance. The decision not to include the ARISCAT composite score in the primary model deserves emphasis. Because emergency surgery and age are embedded in the ARISCAT score, a model that includes both the composite score and these individual items would estimate the effect of emergency surgery conditional on a score that already incorporates it, thereby obscuring the interpretation of the emergency surgery coefficient. The primary model, therefore, excluded the ARISCAT composite score and instead considered its non-overlapping components. This approach allows the associations between age and emergency surgery and PPCs to be interpreted independently while still accounting for other ARISCAT domains, such as preoperative SpO₂, recent respiratory infection, preoperative anemia, surgical site, and operative duration. A sensitivity analysis using the ARISCAT composite score instead of its individual components was not performed because the two specifications condition on different sets of covariates, and their coefficients are not directly comparable; the primary model was pre-specified to address the conceptual overlap issue.
In the current investigation, patients exhibiting preoperative frailty showed a markedly elevated risk of PPCs, and the predictive value of frailty was even superior to that of emergency surgery. Frailty, a multisystem syndrome characterized by reduced physiological reserve and impaired stress tolerance, may contribute to an increased risk of PPCs through multiple biological pathways27. For one thing, frail individuals frequently present with weakened respiratory muscle strength and blunted cough reflexes, which raise the likelihood of postoperative secretion retention and atelectasis. For another, frailty is closely linked to compromised immune function, potentially predisposing patients to postoperative pulmonary infections. Furthermore, patients with frailty may mount an exaggerated inflammatory response to surgical stress, thereby exacerbating lung injury. Prospective cohort studies28,29 have demonstrated that the severity of frailty exhibited a positive relationship with both the number and severity of postoperative complications, with rates being significantly higher in the high-frailty group relative to the low-frailty group. These findings are consistent with the present findings and support the integration of frailty assessment into routine preoperative screening. In this study, the prevalence of PPCs was considerably elevated in patients undergoing emergency surgery relative to those receiving elective surgery, and multivariate analysis confirmed emergency surgery as an independent factor associated with PPCs. The increased risk of PPCs associated with emergency surgery may be attributed to several factors. First, insufficient preoperative preparation time fails to effectively control potential pulmonary infections30. Second, patients in emergency settings often experience a more intense response to stress, which can adversely affect pulmonary function. Third, the timing of emergency surgery is often forced, leaving no room to optimize the patient’s baseline physical condition. Additionally, emergency surgeries are frequently associated with more severe primary diseases, further increasing the vulnerability to PPCs31. Notably, the incidence of PPCs in the subgroup of patients with both emergency surgery and preoperative frailty reached as high as 35.7%, which was significantly higher than that in other subgroups. This finding suggests that close attention should be paid to this vulnerable population in routine clinical care. A single-center study32 reported that implementing a clinical pathway incorporating frailty assessment for elderly patients undergoing emergency abdominal surgery reduced the incidence of PPCs from 69% to 44%, indicating that early identification and targeted intervention may improve patient prognosis.
The present study identified a significant multiplicative interaction between emergency surgery and preoperative frailty, suggesting that emergency surgery modifies the association between preoperative frailty and PPCs on the multiplicative scale, and that their coexistence is associated with a higher joint risk of PPCs. This finding carries important clinical implications: when frail patients undergo emergency surgery, their association with PPCs may not be a simple superposition of individual risks but may reflect a joint association through shared pathophysiological pathways. However, this should be regarded as effect modification or a joint association rather than as a causal biological synergy, especially given the relatively modest difference between frail and non-frail patients within the emergency surgery group and the limited number of PPC events. For instance, the stress response elicited by emergency surgery may further deplete the already limited physiological reserve in frail individuals, while frailty-related immune deficiency may in turn exacerbate the inflammatory response under emergency conditions33.
A retrospective cohort study of 3,298 elderly patients undergoing major abdominal surgery reported that frailty quantified via the 5-item modified frailty index (mFI-5) was independently and positively associated with PPC risk34. Moreover, incorporating the mFI-5 into conventional risk models significantly improved predictive performance, with statistically significant increases in AUC and net reclassification improvement. The incidence of PPCs in that study was 10.6%, slightly lower than the 18.0% observed in the present investigation, which may be attributed to differences in study populations, surgical procedures, and diagnostic criteria for PPCs. Another prospective study focused on patients undergoing emergency abdominal surgery also confirmed that a higher degree of frailty correlated with a greater cumulative risk of postoperative complications35. The clinical frailty scale (CFS) score was positively related to both the Clavien–Dindo classification of complication severity and the comprehensive complication index (CCI). Regarding emergency surgery, a study of 1,467 elderly patients undergoing upper abdominal operations demonstrated that emergency surgery was an independent factor associated with PPCs31, which is consistent with the findings of the present study. That research also suggested that patient-controlled analgesia (PCA) might reduce the risk of PPCs, highlighting the value of optimized perioperative management strategies. Although most studies support a link between frailty and PPCs, comparisons across investigations are limited by the variety of frailty assessment tools used. For example, some studies adopted phenotype-based measures such as grip strength and gait speed34, which objectively reflect physical function but can be difficult to administer in emergency settings or when preoperative time is constrained. The frailty assessment used in the current study emphasizes clinical feasibility, which may have somewhat underestimated the true impact of frailty on PPCs. Furthermore, one study indicated that the relative effect of frailty on mortality may be greater for low-risk procedures such as hernia repair and appendectomy than for high-risk surgeries36. However, the present study included only patients undergoing major abdominal surgery and did not explore whether surgical risk stratification modulates the relationship between frailty and PPCs. Future research could further compare the association between frailty and PPCs across different levels of surgical risk. This study has several notable strengths. To date, this is the first study in China to systematically explore the independent associations of emergency surgery and preoperative frailty with PPCs, as well as their potential interaction, in elderly patients undergoing major abdominal surgery. This fills a notable gap in the current domestic literature regarding this specific clinical population. Second, the study employed the ARISCAT score, a validated and specialized predictive tool for PPCs, thereby enhancing the reliability and robustness of our risk assessment. Third, by constructing a combined predictive model, it is confirmed that the integration of multiple factors associated with PPCs significantly improves the accuracy of PPCs prediction. This provides a practical instrument for clinical risk stratification, enabling more targeted and effective perioperative management strategies.
This study has several limitations. First, the single-center retrospective design may introduce selection bias and information bias, limiting the generalizability of the findings. In addition, the exclusion criteria substantially restricted the study population by excluding patients with severe cardiopulmonary, renal, hepatic, or neurological disease; stage IV malignancy; major intraoperative blood loss; prolonged operative time; and postoperative ICU respiratory support. Although these exclusions improved internal homogeneity, they also produced a relatively selected elderly population. This is particularly relevant because elderly patients requiring emergency abdominal surgery with severe systemic illness may be precisely the patients in whom frailty and emergency surgery are most clinically important. Consequently, the present findings may not be directly generalizable to this high-risk subgroup, and the clinical relevance of frailty and emergency surgery in such patients remains to be specifically examined. Second, only patients undergoing major abdominal surgery were included, so the potential moderating effect of surgical risk stratification on the relationship between frailty and PPCs was not examined. Third, objective indicators, such as preoperative pulmonary function tests, were unavailable, preventing further analysis of the association between frailty and pulmonary functional reserve. Fourth, although both laparoscopic and open procedures were included, the potential influence of surgical approach on PPCs was not fully explored. Future studies should examine whether laparoscopic versus open surgery modifies the synergistic effect of emergency surgery and preoperative frailty on PPCs. Fifth, because age and emergency surgery are constituent components of the ARISCAT score, the ARISCAT composite score was not included in the primary model; instead, its non-overlapping components were considered. This approach avoids the conceptual overlap between the composite score and its constituents, but it means that the ARISCAT score and its individual components cannot be mutually adjusted, and the present findings should be interpreted within this constraint. Future studies with larger samples and external validation are needed to determine the optimal model specification when both composite and component variables are of interest. Sixth, the postoperative day-1 VAS pain score was measured after surgery and may be influenced by early postoperative pulmonary events, analgesic administration, and mobilization. Although VAS was treated as a postoperative variable rather than an etiological risk factor, residual reverse causation cannot be entirely ruled out, and the regression coefficient for VAS should be interpreted with caution. Future studies with serial pain assessments and clearly defined temporal windows are warranted to further clarify the association between postoperative pain and PPCs. Seventh, only 53 PPC events were observed, which is relatively small for the complexity of the multivariable and interaction models. This low events-per-variable ratio raises concerns about model instability and overfitting, and the reported combined AUC of 0.894 is an apparent performance estimate without internal validation or optimism correction. The model's predictive performance should therefore be interpreted with caution, and the claim of high predictive performance should be substantially tempered. Future studies with larger sample sizes, internal validation (e.g., bootstrapping or cross-validation), and external validation are needed to confirm the robustness and generalizability of the model. Eighth, although the predictors in the multivariable model were pre-specified based on clinical reasoning and prior literature rather than selected solely on the basis of univariable P values, the relatively small number of PPC events (53 events) still limits the stability of the regression estimates. Future studies with larger samples and formal validation are needed to confirm the robustness of these findings. Objective indicators such as preoperative pulmonary function tests and preoperative oxygen requirement were not systematically recorded in the electronic medical record and were therefore not available, which prevented further analysis of the association between frailty and pulmonary functional reserve and left residual confounding by baseline pulmonary function and chronic respiratory conditions possible. Future prospective studies with systematic preoperative pulmonary function assessment, including spirometry and arterial blood gas analysis, are needed to clarify whether baseline pulmonary status modifies the association between frailty and PPCs. Ninth, the interaction between emergency surgery and preoperative frailty was assessed only on the multiplicative scale, and additive interaction indices were not reported. In addition, the four-group analysis showed that the difference between frail and non-frail patients within the emergency surgery group was relatively modest compared with the overall difference between elective and emergency surgery. Therefore, the interaction finding should be interpreted as effect modification or a joint association rather than as evidence of causal biological synergy, and future studies with larger samples and correctly specified interaction models are needed to confirm this finding.
Several directions can be pursued in future research. Multicenter prospective cohort studies are warranted to validate the present findings and improve the level of clinical evidence. Such studies should also deliberately include elderly patients with severe systemic illnesses who require emergency abdominal surgery, since this subgroup was largely excluded from the present analysis and may derive the greatest clinical benefit from frailty assessment and targeted perioperative intervention. Such studies should also include internal and external validation of the combined prediction model to determine whether its apparent predictive advantage persists after correcting for optimism. Second, optimized perioperative strategies for frail patients undergoing emergency surgery should be explored, including feasible modifications of preoperative rehabilitation in emergency settings, enhanced early mobilization, and intensive respiratory exercise after surgery. Third, simplified predictive models combining frailty assessment and the ARISCAT score could be developed to enable rapid identification of high‑risk individuals in emergency environments37. However, before such models are adopted clinically, their performance must be confirmed in adequately powered studies with formal validation. Further studies may also evaluate the efficacy of various frailty‑targeted interventions in reducing the incidence of PPCs.
In elderly patients undergoing major abdominal surgery, both preoperative frailty and emergency surgery were independently associated with PPCs, and their combination shows a significant multiplicative interaction and a higher joint association with PPCs. This phenomenon is more appropriately described as effect modification or a joint association than as a causal synergistic effect, because the four-group analysis showed that the difference between frail and non-frail patients within the emergency surgery group was relatively modest compared with the overall difference between elective and emergency surgery. For high-risk patients with both emergency surgery and preoperative frailty, enhanced perioperative monitoring and management should be implemented to reduce the incidence of PPCs and improve patient prognosis. However, because the exclusion criteria of this study largely excluded patients with severe systemic illness, the present findings should be generalized with caution to the broader elderly population requiring emergency abdominal surgery, particularly those with severe comorbidities in whom frailty and emergency surgery may be most clinically important. Owing to the limited number of outcome events and the lack of internal validation, the combined prediction model should currently be regarded as hypothesis-generating rather than as a validated risk-prediction tool, and its apparent predictive performance requires confirmation in larger studies with formal validation.
Déclarations de divulgation
The manuscript has neither been previously published nor is under consideration by any other journal. The authors have all approved the content of the paper. The authors declare that they have no financial conflicts of interest. No artificial intelligence (AI) tools, including but not limited to large language models, image-generation software, or automated writing assistants, were used in the preparation of this manuscript or in the creation of any figures or tables. All content, data analysis, and graphical presentations were generated and verified entirely by the authors.
Remerciements
This study was supported by Zhejiang Provincial Clinical Key Specialties-Anesthesiology (Project No.: 2023-ZJZK-001); Jiaxing Municipal Science and Technology Program Project (Project No.: 2024AD30084); Recipient of Outstanding Young Medical Talents Training Program, Jiaxing Municipality (Project No.: 2024-yxqnrc-61).
Matériaux
| Nom | Entreprise | Numéro de catalogue | Commentaires |
|---|---|---|---|
| automated biochemical analyzer | Hitachi High-Tech Corporation | Hitachi 7600 | Serum ALB was measured |
| automated hematology analyzer | Sysmex Corporation | Sysmex XN-1000 | Hb and WBC were determined |
| centrifuge | Cence Centrifuge Instruments Co., Ltd. | TDL-4 | Separate serum by centrifugation |
| finger-clip pulse oximeter | Medtronic | Nellcor PM10N | SpO2 was measured |
| G*Power software | Heinrich - Heine - Universität Düsseldorf | Version 3.1.9.7 | Sample size calculation |
| mechanical height-weight scale | Suhong Medical Devices Co., Ltd. | RGZ-120 | Height and body weight were measured |
| SPSS software | IBM | SPSS 27.0 | Statistical analysis |
Références
- Trocheris-Fumery O et al. Early use of norepinephrine in high-risk patients undergoing major abdominal surgery: a randomized controlled trial. Anesthesiology. 2025;143(5):1160–1170.
- Saugel B et al. Individualized perioperative blood pressure management in patients undergoing major abdominal surgery: the IMPROVE-multi randomized clinical trial. JAMA. 2025;334(21):1893–1904.
- Liang Z et al. Postoperative quality of recovery comparison between ciprofol and propofol in total intravenous anesthesia for elderly patients undergoing laparoscopic major abdominal surgery: a randomized, controlled, double-blind, non-inferiority trial. J Clin Anesth. 2024;99:111660.
- Skorepa P et al. The impact of prehabilitation on outcomes in frail and high-risk patients undergoing major abdominal surgery: a systematic review and meta-analysis. Clin Nutr. 2024;43(3):629–648.
- Zhang Y et al. The relationship between preoperative SPPB scores and 30-day postoperative pulmonary complications in elderly patients undergoing elective major abdominal surgery. BMC Surg. 2025;25(1):507.
- Boden I et al. Preoperative physiotherapy prevents postoperative pulmonary complications after major abdominal surgery: a meta-analysis of individual patient data. J Physiother. 2024;70(3):216–223.
- Kochupurackal JC et al. Postoperative pulmonary complications with high versus standard FiO2 in adult patients undergoing major abdominal surgery: a noninferiority trial. Surgery. 2024;175(2):536–542.
- Feng A et al. Effect of goal-directed fluid therapy based on plasma colloid osmotic pressure on the postoperative pulmonary complications of older patients undergoing major abdominal surgery. World J Surg Oncol. 2023;21(1):67.
- Kim DH, Rockwood K. Frailty in older adults. N Engl J Med. 2024;391(6):538–548.
- Ji S et al. Intraoperative oxygen concentration and postoperative delirium in elderly patients undergoing major abdominal surgery: a prospective randomized controlled clinical trial. Int J Colorectal Dis. 2025;40(1):137.
- Fernandez-Bustamante A et al. Perioperative lung expansion and pulmonary outcomes after open abdominal surgery versus usual care in the USA (PRIME-AIR): a multicentre, randomised, controlled, phase 3 trial. Lancet Respir Med. 2025;13(5):447–459.
- Silversides JA et al. Sugammadex or neostigmine for prevention of post-operative pulmonary complications after major abdominal or thoracic surgery: study protocol for the SINFONIA (Sugammadex for prevention of post-operative pulmonary complications) randomised controlled superiority trial. Trials. 2025;26(1):319.
- Zhang YT et al. Effect of inspiratory oxygen fraction during driving pressure-guided ventilation strategy on pulmonary complications following open abdominal surgery: a randomized controlled trial. J Clin Anesth. 2024;99:111676.
- Zhang NR et al. Intraoperative protective ventilation with or without periodic lung recruitment manoeuvres on pulmonary complications after major abdominal surgery (REMAIN-1): protocol for a randomised controlled trial. BMJ Open. 2025;15(3):e093360.
- Elefterion B et al. Intraoperative mechanical power and postoperative pulmonary complications in noncardiothoracic elective surgery patients: a 10-year retrospective cohort study. Anesthesiology. 2024;140(3):399–408.
- Kokotovic D, Degett TH, Ekeloef S, Burcharth J. The ARISCAT score is a promising model to predict postoperative pulmonary complications after major emergency abdominal surgery: an external validation in a Danish cohort. Eur J Trauma Emerg Surg. 2022;48(5):3863–3867.
- Canan A et al. Preoperative thoracic CT findings associated with postoperative mechanical ventilation in patients undergoing major abdominal or pelvic surgery: a matched case-control study. AJR Am J Roentgenol. 2022;218(2):279–288.
- Liu W et al. Effects of electrical impedance tomography-guided positive end-expiratory pressure on postoperative cardiopulmonary exercise capacity in elderly patients: study protocol for a randomized controlled trial. Med Sci Monit. 2023;29:e938333.
- Palermo J, Tingey S, Khanna AK, Segal S. Evaluation and prevention of perioperative respiratory failure. J Clin Med. 2024;13(17):5083.
- Kashyap RM et al. Effects of different extubation strategies on atelectasis in older adults after major abdominal surgery: a prospective randomized controlled trial. Ann Geriatr Med Res. 2024;28(2):201–208.
- Boney O et al. Core outcome measures for perioperative and anaesthetic care (COMPAC): a modified Delphi process to develop a core outcome set for trials in perioperative care and anaesthesia. Br J Anaesth. 2022;128(1):174–185.
- Han J, Wang J, Xie B, Wang Y. Comparison of consistency and validity of Fried frailty phenotype, FRAIL scale and Edmonton frailty scale for frailty screening among community-dwelling older adults. Chin Gen Pract. 2021;24(21):2669–2675.
- Bijur PE, Silver W, Gallagher EJ. Reliability of the visual analog scale for measurement of acute pain. Acad Emerg Med. 2001;8(12):1153–1157.
- Shivali S, Thiagarajan P. A practical guide to the American Society of Anesthesiologists Physical Status Classification (ASA-PS). Indian J Anaesth. 2022;66(4):299–300.
- Aceto P et al. Predictive power of modified frailty index score for pulmonary complications after major abdominal surgery in the elderly: a single centre prospective cohort study. Eur Rev Med Pharmacol Sci. 2021;25(10):3798–3802.
- Prado CM et al. Nascent to novel methods to evaluate malnutrition and frailty in the surgical patient. JPEN J Parenter Enteral Nutr. 2023;47 Suppl 1:S54–S68.
- Bain CR et al. Postoperative systemic inflammation after major abdominal surgery: patient-centred outcomes. Anaesthesia. 2023;78(11):1365–1375.
- Snitkjaer C, Jensen TK, Kokotovic D, Burcharth J. The cumulative risk and severity of postoperative complications in patients with frailty undergoing major emergency abdominal surgery—a prospective cohort study. World J Surg. 2025;49(1):55–65.
- Duman TT. Evaluation of the relationship between vitamin D and inflammation in type 2 diabetes and diabetic complications. Adv Mod Biomed. 2025;1(3):23–32.
- Sun M, Xu M, Sun J. Risk factor analysis of postoperative complications in patients undergoing emergency abdominal surgery. Heliyon. 2023;9(3):e13971.
- He Q et al. Postoperative pulmonary complications after major abdominal surgery in elderly patients and its association with patient-controlled analgesia. BMC Geriatr. 2024;24(1):751.
- Aakre EK et al. Impact of a care pathway for older patients undergoing emergency abdominal surgery: a before-and-after study. Acta Anaesthesiol Scand. 2026;70(2):e70182.
- Piccioni F et al. Postoperative pulmonary complications and mortality after major abdominal surgery: an observational multicenter prospective study. Minerva Anestesiol. 2023;89(11):964–976.
- Li CQ, Ma JH, Liu ZZ, Li J. Role of frailty in predicting postoperative pulmonary complications in older patients undergoing major abdominal surgery: a retrospective cohort study. Korean J Anesthesiol. 2025;78(6):547–559.
- Yamada S et al. Frailty as a predictor of postoperative aspiration pneumonia after abdominal surgery for digestive cancers. Medicine (Baltimore). 2025;104(46):e45697.
- Lin T, Zhai TF, Fan Y, Xie KL. Research progress on the assessment of frailty and postoperative complications in elderly patients. Int J Anesth Resus. 2023;44(6):653–656.
- Fan G et al. Association of preoperative frailty with pulmonary complications after cardiac surgery in elderly individuals: a prospective cohort study. Aging Clin Exp Res. 2023;35(11):2453–2462.