This hypothesis-generating narrative review examines gut–brain axis dysfunction in children with non-organic poor appetite and evaluates proposed mechanisms of Traditional Chinese Medicine interventions involving central appetite-regulatory networks, brain–gut peptides, intestinal barrier function, and gut microbiota. Current evidence is predominantly correlational, heterogeneous, and indirect.
Article de revue
Gut–Brain Axis and Appetite: A Hypothesis-Generating Narrative Review of Traditional Chinese Medicine for Non-Organic Poor Appetite in Children
Dans cet article
Résumé
Résumé
Non-organic poor appetite/feeding difficulty in children is characterized by persistent poor appetite or reduced food intake without the body-image disturbance or fear of weight gain characteristic of anorexia nervosa. This hypothesis-generating narrative review examines gut–brain axis dysfunction in this condition and evaluates proposed mechanisms of Traditional Chinese Medicine (TCM) interventions. Peer-reviewed literature published from January 2000 to August 2026 was reviewed using PubMed, Web of Science, and China National Knowledge Infrastructure (CNKI). Human, animal, and review studies relevant to appetite regulation, pathogenesis, or TCM were considered, while studies exclusively concerning anorexia nervosa were excluded unless used as clearly identified indirect mechanistic evidence. Risk of bias was assessed using the Cochrane Risk of Bias 2 (RoB 2) tool, Risk Of Bias In Non-randomized Studies of Interventions (ROBINS-I), and A Measurement Tool to Assess Systematic Reviews 2 (AMSTAR 2), where applicable. The evidence was organized across four dimensions: central appetite-regulatory networks, including neurotransmitters; brain–gut peptides; intestinal barrier function; and gut microbiota. Available studies suggest alterations across these dimensions and propose that specific TCM interventions, including herbal formulas, acupuncture, and tuina, may influence related pathways. Evidence concerning microbiota composition and short-chain fatty acids (SCFAs) is primarily preclinical or indirect, and functional restoration of gut–brain communication has not been demonstrated in affected children. Overall, the evidence is heterogeneous, predominantly correlational, and frequently derived from animal models, in-vitro studies, other disease populations, or specific interventions. Direct pediatric mechanistic evidence remains limited, causal pathways have not been established, and no efficacy conclusion can currently be drawn.
Introduction
Non-organic poor appetite/feeding difficulty in children is a pediatric feeding condition characterized by persistent poor appetite and reduced food intake. It is clinically distinct from anorexia nervosa, a psychiatric eating disorder defined by deliberate food restriction, low body weight, and body-image disturbance. Clinical reports have described the use of pediatric tuina and Chinese herbal interventions in children diagnosed with infantile anorexia1,2; however, these treatment studies do not establish population prevalence or comparative efficacy. Prolonged inadequate food intake can lead to malnutrition, growth retardation, and impaired immune function and may adversely affect long-term development3,4,5. Data from the Global Burden of Disease Study indicate that eating problems, including anorexia-related disorders, have shown a sustained upward trend among adolescents in Asia and China6,7,8. In contemporary medical practice, symptomatic supportive measures such as prokinetic agents, digestive enzymes, or zinc supplementation are commonly employed. Although these approaches may improve selected digestive or nutritional outcomes, their effects on central appetite regulation and long-term outcomes in children with non-organic poor appetite/feeding difficulty remain uncertain9,10,11. The fundamental challenge lies in the fact that appetite is precisely modulated by a complex neural network within the hypothalamic arcuate nucleus, involving neuropeptide Y/agouti-related protein (NPY/AgRP) neurons and pro-opiomelanocortin/cocaine- and amphetamine-regulated transcript (POMC/CART) neurons. To date, there is a lack of safe and targeted therapeutic strategies capable of precisely intervening in this “appetite balance”12,13,14.
In traditional Chinese medicine (TCM), poor appetite in children has historically been discussed within theoretical frameworks such as liver–spleen disharmony; however, this construct is theoretical and requires mechanistic and clinical validation. The coexistence of digestive and neurological symptoms suggests that the biological basis may extend beyond a single organ, likely pointing to a regulatory network that connects emotional states and visceral functions. Recent research has provided a critical neurobiological framework for this network: bidirectional dysregulation of the brain–gut axis has been associated with the development of poor appetite/feeding difficulty in children15. This process has been associated with gut microbiota imbalance and enteric nervous system dysfunction, leading to network-level disturbances in brain–gut peptides such as ghrelin and cholecystokinin (CCK), as well as neurotransmitters including serotonin and dopamine16,17. Aberrant signals are transmitted via the vagus nerve to the central nervous system, where they may be misinterpreted by the hypothalamus as satiety or visceral discomfort signals. This, in turn, may suppress orexigenic pathways and attenuate the rewarding effects of feeding, while simultaneously exacerbating gastrointestinal motility disorders through descending autonomic pathways. Ultimately, a self-reinforcing vicious cycle may be formed, characterized by “signal distortion, central misreading, effect amplification, and feeding refusal”18,19,20,21.
It is noteworthy that the symptomatology of brain–gut axis dysfunction—including decreased appetite, abdominal discomfort, and emotional fluctuations—closely overlaps with clinical presentations historically described in TCM. This suggests that the scientific connotation of TCM therapeutic principles, grounded in a holistic perspective, may lie in comprehensive modulation of the multidimensional brain–gut regulatory network. In recent years, numerous studies have explored the effects of TCM interventions on non-organic poor appetite/feeding difficulty in children through regulation of the brain–gut axis; however, these findings have not yet been systematically reviewed or integrated. The present article aims to review and critically appraise the available evidence, with the goal of deepening our understanding of the scientific basis of TCM interventions and providing references for clinical optimization.
Revue et perspective
TCM Theoretical Background: Liver–Spleen as TCM Theoretical Constructs
The TCM concepts of Spleen and Liver are presented as frameworks for hypothesis generation rather than established biological mechanisms or equivalents of modern physiological entities
In TCM theory, the Spleen is described as the “foundation of acquired constitution” and as governing the transportation and transformation of food essences22. This construct has been conceptually compared with gastrointestinal digestive and absorptive processes23 but is not equivalent to a modern organ or physiological mechanism. “Spleen governing transportation and transformation” is described as encompassing gastric reception and ripening, small intestinal separation of clear from turbid, and large intestinal conduction of waste. These descriptions have been proposed to be conceptually analogous to gastrointestinal motility, digestive enzyme secretion, and nutrient absorption24,25, but remain theoretical rather than established biological mechanisms. “Spleen governing ascending the clear” is described as reflecting the distribution of absorbed nutrients to the heart, lungs, and central nervous system and has been conceptually compared with nutrient entry into the portal circulation and traversal of the blood–brain barrier; however, this comparison does not establish a biological mechanism. Some clinical studies have reported gastrointestinal motility disturbances and diminished digestive enzyme activity in children classified as having Spleen deficiency pattern26,27,28. These preliminary associations are exploratory and do not establish the Spleen as a biological mechanism.
In TCM theory, the Liver is described as governing the free flow and dispersion of qi and regulating systemic qi dynamics. This theoretical function has been conceptually compared with the neuroendocrine–immune network in modern medicine, particularly the emotional regulatory functions of the central nervous system29,30. “Liver governing free flow and dispersion” has also been conceptually mapped to the integration of emotional processing and autonomic nervous system function by the limbic system. Irritability, anger, and nocturnal restlessness historically attributed to Liver qi stagnation may therefore be conceptually mapped to emotional disturbances associated with limbic system dysfunction31. Similarly, “Liver regulating qi dynamics” is theorized to reflect modulation of gastrointestinal smooth muscle by the autonomic nervous system: unimpeded Liver function is described as ensuring orderly gastrointestinal peristalsis, whereas dysregulation is theorized to contribute to gastrointestinal motility disturbances through sympathetic–vagal imbalance32,33. These conceptual mappings do not establish biological mechanisms. Some research has reported alterations in monoamine neurotransmitter levels, including serotonin and dopamine, in children classified as having Liver depression pattern34. However, this represents an indirect association based on TCM pattern classification and does not establish Liver function as a biological mechanism. Thus, Spleen and Liver provide TCM frameworks for hypothesis generation that require mechanistic and clinical validation and should not be interpreted as established physiological entities or causal pathways.
Clinical Practice and Evidence for TCM Therapy in Children with Non-Organic Poor Appetite/Feeding Difficulty
The following clinical practices are described within the TCM theoretical framework and should not be interpreted as mechanistic proof of Liver–Spleen function.
In TCM theory, the core therapeutic aim for poor appetite/feeding difficulty in children is often described as regulating Liver qi to restore neurological–emotional homeostasis and fortifying the Spleen to restore gastrointestinal transport and transformation functions. These are TCM theoretical descriptions, not established effects on neurological or gastrointestinal function. Commonly prescribed formulas include Xiaoyao San35, Chaihu Shugan San, Sijunzi Tang36, and self-devised formulas derived from classical prescriptions. Within TCM formulary theory, “Liver-soothing” is often described as achieved through the combination of Bupleurum (Chaihu) and White Peony Root (Baishao), whereas “Spleen-fortifying” is described as accomplished through Atractylodes (Baizhu) and Poria (Fuling). These are TCM therapeutic terms, not modern pharmacological mechanisms. Digestant and stagnation-transforming agents such as Hawthorn Fruit (Shanzha), Medicated Leaven (Shenqu), and Barley Sprout (Maiya) are also frequently incorporated37. This compatibility pattern provides a rationale for hypothesizing multi-target modulation; however, the cited evidence concerns a spleen-strengthening and liver-draining formula in non-alcoholic fatty liver disease, not children with non-organic poor appetite, and does not establish gut–brain axis modulation in this population38.
Some small clinical studies have reported that TCM formulas may improve appetite and increase food intake in affected children, with overall response rates in some studies superior to symptomatic treatment alone or blank controls39,40,41,42. These formulas have also been reported to alleviate poor appetite and abdominal distension and may favorably affect irritability and nocturnal restlessness. However, these studies are small and heterogeneous, and TCM pattern-based outcomes should not be interpreted as mechanistic evidence for Liver–Spleen function. Larger randomized controlled trials are required for confirmation.
Acupuncture and tuina have been used in affected children and have been reported to regulate visceral function through stimulation of specific acupoints and body regions43,44. Tuina, owing to its non-invasive nature and ease of administration, is more readily accepted by children and their caregivers45. Among tuina techniques, spinal pinching manipulation may regulate visceral function and autonomic nervous system tone through stimulation of the Governing Vessel and bilateral Bladder Meridian Back-Shu points46; abdominal circular massage may promote intestinal peristalsis and alleviate abdominal distension; and kneading of Zusanli is described in TCM theory as potentially enhancing Spleen–Stomach transport and transformation capacity. Some clinical observations indicate that specific acupuncture or tuina protocols may improve appetite, food intake, body weight, abdominal distension, and irregular bowel movements through regulation of gastrointestinal rhythm. These therapies have been hypothesized to act through superficial body stimulation, with signal transmission to the central nervous system and viscera via neuroendocrine pathways47. This mechanism remains hypothetical and has not been established in children with non-organic poor appetite/feeding difficulty.
In some clinical settings, integrated Chinese–Western management has been used48. This approach typically combines pattern-based TCM therapies with conventional Western symptomatic treatments such as prokinetic agents or trace element supplementation. Acupuncture treatment may include acupoints such as Zusanli (ST36), Taichong (LV3), Zhongwan (CV12), and Sifeng (EX-UE10)49,50,51. Small studies and reviews have proposed complementary effects of combined TCM and Western protocols. Within TCM theory, these therapies are described as regulating Liver–Spleen function, and it has been proposed that they may modulate gut–brain axis function11; however, this remains a theoretical construct rather than an established biological mechanism. Western symptomatic treatments may provide more rapid relief of selected symptoms, but whether their combination with TCM produces synergistic effects has not been established. Reference 50 concerns adolescents with anorexia nervosa, not children with non-organic poor appetite/feeding difficulty, and is cited only as indirect background50.
Some small clinical studies have suggested that integrated management may be associated with better overall symptom response or lower recurrence than Western symptomatic treatment alone48,51. However, these studies were small, heterogeneous, often single-center, and commonly involved combined interventions; they were not designed or powered to demonstrate superiority. Therefore, no comparative efficacy conclusion can be drawn.
Whether integrated treatment reduces adverse effects of Western medications remains uncertain. Some clinical experience suggests that TCM, particularly non-invasive tuina, may improve comfort and adherence11, but no adequately powered safety comparison is available. Long-term use of prokinetic agents may carry risks of neurological side effects or drug resistance; however, whether TCM permits reductions in the dosage or duration of Western medications and thereby lowers adverse-event probability has not been established. External modalities such as tuina may support comfort and adherence, but these observations remain largely clinical impressions.
Mechanistic Advances in TCM Therapy for Non-Organic Poor Appetite/Feeding Difficulty
The four dimensions are presented in the same order throughout this review: (1) central appetite-regulatory networks, including neurotransmitters; (2) brain–gut peptides; (3) intestinal barrier; and (4) gut microbiota. The direct pediatric and indirect/preclinical evidence supporting these dimensions, together with key biological endpoints and major limitations, is summarized in Table 1.
Table 1: Evidence summary for the proposed four-dimensional gut–brain axis framework in children with non-organic poor appetite/feeding difficulty. Evidence is organized across central appetite-regulatory networks, including neurotransmitters; brain–gut peptides; intestinal barrier; and gut microbiota. Direct pediatric evidence is distinguished from indirect or preclinical evidence, with key biological endpoints and major limitations summarized for each dimension. Abbreviations: 5-HT, 5-hydroxytryptamine; CCK, cholecystokinin; LPS, lipopolysaccharide; NPY, neuropeptide Y; SCFAs, short-chain fatty acids; TCM, Traditional Chinese Medicine; VIP, vasoactive intestinal peptide; ZO-1, zonula occludens-1. Please click here to download this file.
Central Appetite-Regulatory Networks and Neurotransmitters: Proposed TCM Modulation:
Certain TCM interventions have been proposed to influence neurotransmitter systems52,53,54,55; however, evidence derives largely from reviews, adults, or animal models, with little direct evidence in affected children. Preclinical and indirect evidence has led to the hypothesis that certain TCM interventions may influence serotonergic signaling through peripheral and central mechanisms. In mechanistic studies not involving TCM, gut microbial metabolites such as short-chain fatty acids (SCFAs) have been associated with enterochromaffin cell 5-hydroxytryptamine (5-HT) synthesis and secretion56. Reviews in chronic constipation and depression have proposed that TCM may modulate 5-HT signaling57,58, but these populations differ from children with non-organic poor appetite. A preclinical study of electroacupuncture in rats with cisplatin-induced anorexia suggested possible effects on monoamine neurotransmitters59. Whether TCM modulates 5-HT receptor expression or reuptake in children with non-organic poor appetite/feeding difficulty is unknown. A non-TCM review of eating disorders is cited only as conceptual background60. Thus, this proposed peripheral–central modulation remains hypothetical. At the reward-system level, TCM has been proposed to influence dopaminergic and noradrenergic function in neuropsychiatric or neurotransmitter-related conditions61. This evidence is indirect and not specific to children with non-organic poor appetite. Dopamine is thought to influence the hedonic experience and motivational drive for eating through mesolimbic pathways, particularly the nucleus accumbens62,63,64. However, the available evidence is indirect: one study was conducted in overweight adults62, while other mechanistic studies did not evaluate TCM interventions63,64. Preclinical evidence, largely from animal models, suggests that some specific TCM interventions may alter dopamine synthesis or release, but whether this translates into restored reward responses to food in affected children is unknown. The noradrenergic system is involved in arousal, stress responses, and initiation of feeding behavior; whether TCM modulation of noradrenergic activity contributes to appetite motivation in these children is likewise speculative. Thus, proposed multi-neurotransmitter regulation remains hypothetical and does not establish a mechanism or treatment effect in children with non-organic poor appetite/feeding difficulty.
Brain–Gut Peptides: Proposed Network Balance:
Brain–gut peptides serve as critical signaling molecules connecting the central nervous system and gastrointestinal function65. Secretory imbalance of brain–gut peptides has been reported in children with anorexia nervosa66, but anorexia nervosa is clinically distinct from non-organic poor appetite/feeding difficulty, for which direct evidence remains limited. Preclinical and preliminary clinical evidence suggests that some TCM interventions may modulate brain–gut peptides, but whether this restores orexigenic/anorexigenic equilibrium in affected children remains unknown. The evidence can be distinguished at three levels.
Altered peptides in children with poor appetite: Clinical observational studies have reported altered serum levels of ghrelin, cholecystokinin (CCK), vasoactive intestinal peptide (VIP), and leptin in children with poor appetite. These findings are associational and do not establish that peptide changes cause appetite impairment.
TCM changes peptides: Some small clinical studies in children with TCM pattern-defined anorexia have reported clinical improvement after specific interventions such as tuina plus chiropractic plus Western medicine28. However, whether TCM changes serum ghrelin or related peptides in children with non-organic poor appetite remains uncertain. In rodent models of cisplatin-induced anorexia, electroacupuncture has been suggested to modulate ghrelin and monoamine neurotransmitters59. In rats with functional dyspepsia, Pingwei capsules have been reported to improve gastrointestinal motility67. These findings are indirect and not specific to children with non-organic poor appetite. Preclinical rodent studies also suggest that some TCM interventions, including electroacupuncture, may modulate appetite-related neuropeptides59. However, available pediatric evidence did not evaluate hypothalamic neuropeptide Y (NPY)28, while evidence concerning gastrointestinal motility was derived from an animal model of functional dyspepsia67. Ghrelin is thought to activate NPY/agouti-related protein (AgRP) neurons in the hypothalamic arcuate nucleus and may contribute to hunger and feeding behavior68,69; however, this represents mechanistic background rather than evidence of a TCM effect in children. Small clinical studies have also reported changes in serum vasoactive intestinal peptide (VIP) following specific TCM interventions in children with TCM pattern-defined anorexia40. Whether TCM reduces CCK, VIP, or leptin levels, or whether such changes relieve early satiety or abdominal distension in children with non-organic poor appetite, remains uncertain. These findings should not be generalized to all TCM interventions or to children with non-organic poor appetite.
Peptide changes and clinical improvement: Importantly, no study has demonstrated that TCM-induced changes in these peptides are directly responsible for clinical improvement in children with non-organic poor appetite. A preclinical dissertation study in rats with functional bowel disease proposed that electroacupuncture at different acupoints may exert bidirectional regulation70. This is indirect evidence and does not establish bidirectional peptide regulation in affected children. In a rat model of functional diarrhea, Shenling Baizhu San has been reported to regulate brain–gut peptides71. It has also been hypothesized that some TCM formulas may act on multiple peptide targets in a state-dependent manner72. These findings support a hypothesis of multi-target regulation, but whether physiological equilibrium is restored in affected children remains unknown.
Intestinal Barrier: Proposed Repair:
Intestinal barrier impairment, including the proposed ‘leaky gut’ phenomenon, may contribute to poor appetite/feeding difficulty. Preclinical studies in non-appetite disease models have suggested that some specific TCM formulas may affect intestinal barrier markers73,74. Direct human evidence for a TCM-mediated barrier–inflammation–brain pathway in children with non-organic poor appetite is lacking. In a loperamide-induced constipation mouse model, Wenyang Yiqi Decoction was reported to affect laxation and intestinal barrier-related markers73. Whether similar effects occur in children with non-organic poor appetite or with other TCM formulas is unknown. Tight junction proteins are important determinants of intestinal barrier permeability. In a sepsis rat model, Tong-fu-li-fei decoction was proposed to upregulate zonula occludens-1 (ZO-1), occludin, and claudin-1 and thereby reduce mucosal permeability74. This is preclinical, disease-specific evidence and has not been validated in affected children. Animal models have led to the hypothesis that barrier-protective effects of certain TCM formulas may reduce endotoxin translocation and inflammatory cytokine levels, potentially lowering systemic low-grade inflammation. Mechanistic studies, including reviews and animal experiments without TCM, have further proposed that reduced peripheral inflammation may attenuate blood–brain barrier damage and limit inflammatory cytokine access to hypothalamic pro-opiomelanocortin (POMC) neurons75,76. These studies provide mechanistic background only and do not test TCM in children with non-organic poor appetite. It has consequently been hypothesized that this cascade may contribute to “pathological anorexia.” However, direct human brain-imaging or clinical-trial evidence in children with non-organic poor appetite is lacking. Thus, a putative TCM-mediated “gut–barrier–inflammation–brain” cascade remains a hypothesis-generating framework rather than a validated causal pathway in affected children.
Gut Microbiota: Proposed Remodeling:
Evidence in this section is categorized as (i) direct pediatric evidence in children with non-organic poor appetite/feeding difficulty; (ii) indirect or preclinical TCM evidence from other conditions; and (iii) non-TCM mechanistic background. Evidence in categories (ii) and (iii) is not considered direct evidence of TCM effects in affected children.
The gut microecosystem occupies an important position in connecting the peripheral environment with central nervous system function within proposed gut–brain axis regulation77. In children with poor appetite, pediatric tuina has been reported to affect intestinal flora44. More broadly, reviews have proposed that TCM interventions may be associated with changes in gut microbial community structure78. However, most evidence is correlational, and whether TCM restores microecological homeostasis or improves gut–brain communication remains unproven.
In some preclinical and small clinical studies, specific TCM interventions, including pediatric tuina and certain herbal formulas, have been reported to increase the relative abundance of Lactobacillus and Bifidobacterium. However, these studies are heterogeneous, and increased abundance alone does not demonstrate functional restoration of gut–brain communication. Evidence for suppression of Escherichia coli and Bacteroides is inconsistent. This “fortifying the healthy qi and eliminating pathogenic factors” pattern has been proposed within TCM theory as a population-level basis for restoring intestinal microecological equilibrium; however, direct functional evidence in children with non-organic poor appetite/feeding difficulty is lacking.
Separately from TCM evidence, mechanistic studies not involving TCM suggest that SCFAs may serve as an energy source for intestinal epithelial cells and participate in gut–brain communication. In an in-vitro study without TCM intervention, bacterial supernatants were reported to alter hypothalamic gene expression79. This study did not test TCM and was not conducted in children; it is cited only as background evidence that microbial metabolites can, in principle, influence hypothalamic gene expression. Similarly, a non-TCM review proposed that SCFAs may stimulate enterochromaffin cells to release 5-HT, with vagal signaling to the nucleus tractus solitarius and hypothalamus80. This is likewise indirect mechanistic background rather than evidence of a TCM effect.
Preclinical and indirect evidence has further led to the hypothesis that some TCM interventions may be associated with altered gut microbial SCFA production, including acetate, propionate, and butyrate, in animal models or non-pediatric disease contexts81. However, no direct evidence in children with non-organic poor appetite/feeding difficulty demonstrates that TCM promotes SCFA production, and causality remains unestablished. Thus, TCM has been hypothesized to modulate gut–brain communication through microbiota-related metabolic pathways, but whether it modulates SCFA production or serotonin secretion in children with poor appetite requires direct investigation. Overall, evidence for microbiota–brain signaling is largely indirect or preclinical, remains predominantly correlational, and lacks causal validation in affected children
Integrative Mechanisms of Multi-Target Network Regulation
In summary, some TCM interventions have been proposed to affect non-organic poor appetite/feeding difficulty through multi-target, multi-level regulation of gut–brain axis homeostasis (Figure 1).
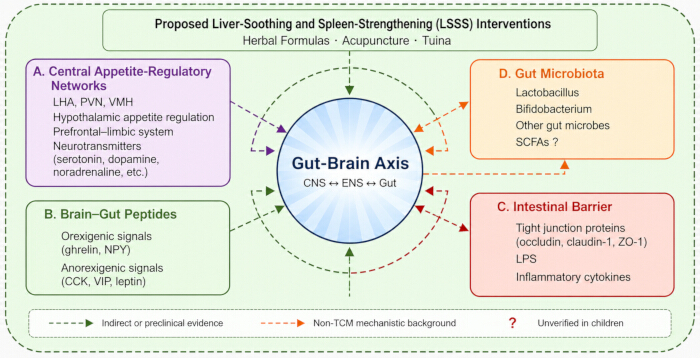
Figure 1. Hypothesis-generating framework for proposed liver-soothing and spleen-strengthening interventions and the gut–brain axis in children with non-organic poor appetite/feeding difficulty. Liver-soothing and spleen-strengthening (LSSS) is a Traditional Chinese Medicine (TCM) theoretical construct proposed to relate to four dimensions of gut–brain axis regulation: (A) central appetite-regulatory networks, including appetite- and emotion-related pathways; (B) brain–gut peptides; (C) intestinal barrier function; and (D) gut microbiota. The depicted relationships are hypothetical and should not be interpreted as established causal effects. Dashed arrows indicate indirect or preclinical evidence, orange dashed arrows indicate non-TCM mechanistic background, and question marks indicate relationships unverified in affected children. No direct pediatric mechanistic pathway has been established. Changes in short-chain fatty acid production remain unproven in affected children. Abbreviations: CCK, cholecystokinin; CNS, central nervous system; ENS, enteric nervous system; LHA, lateral hypothalamic area; LPS, lipopolysaccharide; LSSS, liver-soothing and spleen-strengthening; NPY, neuropeptide Y; PVN, paraventricular nucleus; SCFAs, short-chain fatty acids; TCM, Traditional Chinese Medicine; VIP, vasoactive intestinal peptide; VMH, ventromedial hypothalamus; ZO-1, zonula occludens-1. Please click here to view a larger version of this figure.
First, some TCM interventions have been proposed to modulate central appetite-regulatory networks, including serotonergic, dopaminergic, and noradrenergic signaling, potentially influencing emotional state and feeding behavior. Proposed peripheral effects include modulation of intestinal motility, whereas proposed central effects include alleviation of anxiety and restoration of reward responses to feeding. However, these effects remain hypothetical and have not been directly demonstrated in children with non-organic poor appetite/feeding difficulty. Second, some TCM interventions have been proposed to influence brain–gut peptide network balance and hypothalamic appetite regulation. Proposed modulation of orexigenic signals such as ghrelin and neuropeptide Y (NPY), together with anorexigenic signals including cholecystokinin (CCK), vasoactive intestinal peptide (VIP), and leptin, might influence appetite-regulatory signaling. However, direct causal evidence in children is lacking. Third, some TCM interventions have been proposed to support intestinal barrier function and thereby reduce inflammation-related signaling to the central nervous system. Proposed upregulation of tight junction proteins, reduction of intestinal permeability, and decreased endotoxin translocation might lower systemic inflammatory burden and protect the blood–brain barrier and hypothalamic microenvironment. This proposed cascade remains hypothetical. Fourth, remodeling of gut microbial community structure and metabolic function has been hypothesized to optimize the microecological environment for gut–brain communication. Some preclinical and indirect studies have reported increased relative abundance of beneficial bacteria such as Lactobacillus and Bifidobacterium and, in some models, altered SCFA production. These metabolic signals have been hypothesized to reach the central nervous system through circulatory and vagal pathways. However, whether TCM alters SCFA production or serotonin secretion in children with poor appetite remains unproven.
These four dimensions may be interconnected within a proposed self-reinforcing network (Figure 2). Gut microbial dysbiosis may compromise intestinal barrier integrity, promoting lipopolysaccharide (LPS) translocation and systemic low-grade inflammation. Inflammatory signals may subsequently affect the blood–brain barrier and hypothalamic pro-opiomelanocortin (POMC) neurons, potentially disrupting neurotransmitter metabolism and reinforcing abnormal satiety signaling and emotional dysregulation. Central dysfunction may further exacerbate restrictive feeding behaviors, potentially perpetuating gut microbial dysbiosis and forming a pathological feedback loop. Some TCM interventions have therefore been hypothesized to act at multiple nodes within this network. However, these four dimensions constitute a conceptual framework rather than established causal pathways, and the precise neural targets of TCM therapy remain unknown.
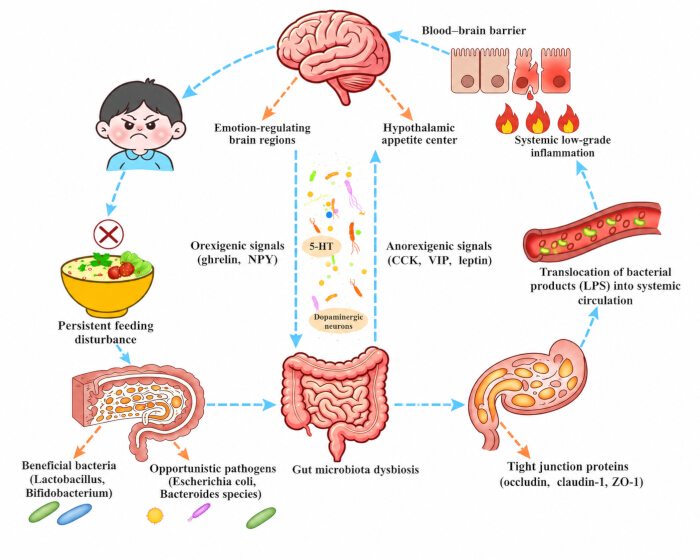
Figure 2. Hypothesis-generating model of a proposed gut microbiota–barrier–inflammation–brain feedback loop in children with non-organic poor appetite/feeding difficulty. The diagram illustrates proposed relationships among persistent feeding disturbance, gut microbiota dysbiosis, intestinal barrier impairment, translocation of bacterial products, systemic low-grade inflammation, and central appetite- and emotion-regulatory processes. The depicted pathway is based predominantly on indirect, preclinical, or non-TCM mechanistic evidence and has not been causally validated in affected children. Arrows indicate proposed relationships and do not establish causality or TCM efficacy. Dashed arrows indicate proposed relationships supported predominantly by indirect, preclinical, or non-TCM mechanistic evidence. Abbreviations: 5-HT, 5-hydroxytryptamine; CCK, cholecystokinin; LPS, lipopolysaccharide; NPY, neuropeptide Y; VIP, vasoactive intestinal peptide; ZO-1, zonula occludens-1. Please click here to view a larger version of this figure.
Limitations and Future Perspectives
Despite increasing research, important evidence-based and mechanistic limitations remain.
Challenges in Mechanistic Dissection:
Existing mechanistic studies remain predominantly correlational, inferring potential TCM mechanisms from changes in peripheral blood brain–gut peptides, inflammatory cytokines, or microbial abundance82. Although these studies provide important mechanistic clues, they lack causal validation83. Advanced approaches such as gene knockout, neural tracing, chemogenetics, and optogenetics have yet to be widely introduced84, limiting the ability to determine which neural pathways and neuronal subpopulations are affected by specific TCM components85. For example, whether acupuncture or specific TCM formulas activate vagal afferent fibers to influence the nucleus tractus solitarius–hypothalamus circuit remains unclear. Electroacupuncture studies involving the hypothalamic paraventricular nucleus provide only indirect mechanistic background86. The multi-component, multi-target characteristics of TCM formulas also make identification of the pharmacologically active substances responsible for observed effects challenging87. Current evidence cannot clearly determine which compounds bind specific receptors or activate particular pathways88. Furthermore, existing studies rely largely on peripheral measurements and provide limited direct assessment of central nervous system function. Cerebrospinal fluid neuropeptide analysis, functional magnetic resonance imaging (fMRI), or positron emission tomography (PET) could facilitate evaluation of TCM-related effects at the brain level; however, existing studies in functional gastrointestinal disorders provide only indirect background89,90.
Challenges in Clinical Evidence Quality:
Most current clinical studies involve small samples and single centers, while rigorously designed large-sample, multicenter, double-blind, placebo-controlled randomized controlled trials (RCTs) remain limited. Consequently, potential placebo effects cannot be adequately excluded, and the generalizability and certainty of current conclusions remain limited. Therapeutic evaluation also relies predominantly on subjective symptom scores, with insufficient incorporation of objective biological measures such as brain–gut peptide levels, microbial diversity indices, or functional brain-imaging changes.
Future Perspectives:
These limitations indicate that future research should move beyond predominantly correlational observations toward causal mechanistic validation and higher-quality clinical evidence. Establishing direct links among TCM interventions, gut–brain axis changes, and clinical outcomes will be important. Future studies should also distinguish evidence obtained directly in children with non-organic poor appetite/feeding difficulty from findings derived from animal models, other disease populations, and non-TCM mechanistic studies. Detailed priorities for future investigation are summarized in the Conclusion.
Conclusions
TCM has a long history of use in children with poor appetite. From a gut–brain axis perspective, current evidence provides a hypothesis-generating framework in which some TCM interventions may influence four interconnected dimensions: central appetite-regulatory networks, including neurotransmitters; brain–gut peptides; intestinal barrier function; and gut microbiota. However, these proposed mechanisms should not be interpreted as established causal pathways. The available evidence is heterogeneous and predominantly correlational, with substantial reliance on animal models, in-vitro studies, other disease populations, and small or indirect clinical studies. Direct causal evidence in children with non-organic poor appetite/feeding difficulty remains limited, and no efficacy conclusion can currently be drawn. Similarly, the Liver–Spleen concepts discussed in this review represent TCM theoretical constructs rather than established biological mechanisms and are included as historical and clinical frameworks for hypothesis generation. Future research should prioritize causal validation of the proposed mechanisms. Neural tracing, optogenetic, and chemogenetic approaches could help determine whether specific interventions influence defined gut–vagus–nucleus tractus solitarius–hypothalamus circuits. Integration of metagenomics, metabolomics, and transcriptomics could characterize microbiota–metabolite–host interactions and identify candidate pathways underlying proposed multi-target effects. Serum pharmacochemistry combined with network pharmacology may further assist in identifying blood-absorbed active components, potential molecular targets, and relationships among formula, pattern, and target. At the clinical level, adequately powered, multicenter, appropriately controlled RCTs incorporating objective measures such as brain–gut peptides, microbial diversity, and functional brain imaging are needed alongside validated clinical outcomes. Overall, the relationship among TCM patterns, gut–brain axis alterations, and non-organic poor appetite/feeding difficulty in children remains speculative. Progress will therefore depend on integrating rigorous mechanistic experiments with well-designed pediatric clinical studies capable of distinguishing association from causation and determining whether the proposed biological changes are directly related to clinical improvement.
Déclarations de divulgation
Conflicts of Interest:
The authors declare no financial or non-financial conflicts of interest.
AI Use Disclosure:
During preparation of this manuscript, the authors used DeepSeek solely for translation. All translated content was subsequently reviewed, revised, and verified by the authors, who take full responsibility for the final manuscript.
Remerciements
No additional acknowledgments are applicable. This research received no external funding.
Références
- Chen ML, Wang FJ. Clinical observation on pediatric tuina for invigorating the spleen and promoting transportation in the treatment of infantile anorexia with spleen-stomach qi deficiency. Zhejiang J Integr Tradit Chin West Med. 2014;24(4):334-336.
- Ma H, Wang J. Clinical observation of Kaiwei Zengshi Ling in the treatment of infantile anorexia. Chin J Inf Tradit Chin Med. 2005;12(12):63-64.
- Song CF, Pan YJ, Xia YL. Research progress on infantile anorexia in traditional Chinese and Western medicine. Hebei J Tradit Chin Med. 2014;36(10):1580-1582.
- Wang XH, Sun LP. Clinical experience of Professor Sun Liping in treating infantile anorexia by constitution differentiation. Chin J Integr Tradit West Med Pediatr. 2024;16(4):363-366.
- Downey AE, Richards A, Tanner AB. Linear growth in young people with restrictive eating disorders: “Inching” toward consensus. Front Psychiatry. 2023;14:1094222.
- Chen Q, et al. Trends and prevalence of eating disorders in children and adolescents. World J Psychiatry. 2024;14(12):1815-1826.
- Tam FI, et al. The impact of the COVID-19 pandemic on administrative eating disorder prevalence in the outpatient sector and on severity of anorexia nervosa. Eur Child Adolesc Psychiatry. 2025;34(3):983-995.
- Van Eeden AE, Van Hoeken D, Hoek HW. Incidence, prevalence and mortality of anorexia nervosa and bulimia nervosa. Curr Opin Psychiatry. 2021;34(6):515-524.
- Standardization Project Group of the “Clinical Application Guidelines for Chinese Patent Medicines in the Treatment of Advantageous Diseases.” Clinical application guidelines for Chinese patent medicines in the treatment of infantile anorexia. Chin J Integr Tradit West Med. 2025;45(12):1413-1419.
- Lask B, et al. Zinc deficiency and childhood-onset anorexia nervosa. J Clin Psychiatry. 1993;54(2):63-66.
- Han ZC, et al. Mechanism and treatment of infantile anorexia based on the brain-gut interaction theory. Chin Med Mod Distance Educ China. 2025;23(18):164-166.
- Chen J, Cai M, Zhan C. Neuronal regulation of feeding and energy metabolism: a focus on the hypothalamus and brainstem. Neurosci Bull. 2025;41(4):665-675.
- Parker JA, Bloom SR. Hypothalamic neuropeptides and the regulation of appetite. Neuropharmacology. 2012;63(1):18-30.
- Hong SH, Choi KM. Gut hormones and appetite regulation. Curr Opin Endocrinol Diabetes Obes. 2024;31(3):115-121.
- Sun WJ, Yu LJ, Guo K. Exploration of the pathogenesis and treatment progress of infantile anorexia based on the “microbiota-brain-gut axis” theory. Sichuan J Tradit Chin Med. 2025;43(7):213-218.
- Zhu YJ, et al. Research progress on the correlation between serum brain-gut peptides and infantile anorexia. Zhejiang J Integr Tradit Chin West Med. 2023;33(12):1173-1176.
- Muhammed M, et al. Gut-derived appetite regulating hormones across the anorexia nervosa spectrum. Psychoneuroendocrinology. 2025;172:107257.
- Schwartz GJ. Neural-immune gut-brain communication in the anorexia of disease. Nutrition. 2002;18(6):528-533.
- Dockray GJ. Cholecystokinin and gut-brain signalling. Regul Pept. 2009;155(1-3):6-10.
- Anton-Păduraru DT, et al. The role of the gut microbiota in anorexia nervosa in children and adults-systematic review. Int J Mol Sci. 2023;25(1):41.
- Roubalová R, et al. Influence of the gut microbiome on appetite-regulating neuropeptides in the hypothalamus: insight from conventional, antibiotic-treated, and germ-free mouse models of anorexia nervosa. Neurobiol Dis. 2024;193:106460.
- He YZ, et al. Study on the correlation between the theory of “spleen governing transportation and transformation” and intestinal microecology. J Pediatr Tradit Chin Med. 2023;19(6):100-103.
- Zhang H, et al. Analysis of “spleen governing transportation and transformation” in traditional Chinese medicine from the perspective of modern medicine. Beijing J Tradit Chin Med. 2022;41(2):179-181.
- Li Q, Shen H. Shengjing Runchang Decoction ameliorates spleen deficiency-induced constipation in children: an observational study. Medicine (Baltimore). 2022;101(51):e32341.
- Liang X, et al. Study on the effects of Massa Medicata Fermentata with different formulations on the intestinal microbiota and enzyme activities in mice with spleen deficiency constipation. Front Cell Infect Microbiol. 2024;14:1524327.
- Wang N, et al. Exploration of the pathogenesis of functional dyspepsia in children based on “spleen deficiency as the root.” Chin J Integr Tradit West Med Pediatr. 2024;16(6):477-481.
- Lin D, Jin JJ. Clinical study on Jianpi Xiaoji Formula combined with Tuina in the treatment of infantile food stagnation with syndrome of spleen deficiency complicated by food accumulation. J New Chin Med. 2024;56(17):83-87.
- Li HZ, Zeng MY. Efficacy of Tuina and spinal pinching combined with Western medicine in the treatment of infantile anorexia with spleen-stomach qi deficiency syndrome. Acta Med Sin. 2020;33(4):85-89.
- Wang RYQ, et al. Modern biological mechanisms of the liver governing free flow of qi. Chin J Tradit Chin Med Pharm. 2023;38(10):5018-5022.
- Xiao KH, et al. Modern biological interpretation of “the liver governing free flow of qi.” World Chin Med. 2022;17(24):3519-3523.
- Chen GF, et al. Near-infrared brain imaging study of depressive disorder with liver qi stagnation syndrome before and after treatment. Front Psychiatry. 2025;16:1529575.
- Zhang Y, Fang XM. The pan-liver network theory: from traditional Chinese medicine to western medicine. Chin J Physiol. 2023;66(6):401-436.
- Chen ZQ, et al. Plasma L-ENK, AVP, ANP and serum gastrin in patients with syndrome of Liver-Qi-stagnation. World J Gastroenterol. 1999;5(1):61-63.
- He YZ, et al. Exploration of the pathogenesis of infantile anorexia based on appetite regulation through the gut-brain axis. Chin J Microecol. 2025;37(3):345-349.
- Liu X, et al. Brain metabonomics study of the antidepressant-like effect of Xiaoyaosan on the CUMS-depression rats by (1)H NMR analysis. J Ethnopharmacol. 2019;235:141-154.
- Qiao XJ, et al. Treatment of functional gastrointestinal disorders from the perspective of “liver failing to govern free flow of qi and spleen failing to govern transportation and transformation.” Chin J Integr Tradit West Med Dig. 2025;33(4):464-468.
- Gao QY, Yang LX, Xu L. Professor Xu Ling's experience in syndrome differentiation and treatment of infantile anorexia based on the theory of “supporting earth and inhibiting wood.” J Pediatr Tradit Chin Med. 2026;22(2):40-43.
- Hui D, et al. The spleen-strengthening and liver-draining herbal formula treatment of non-alcoholic fatty liver disease by regulation of intestinal flora in clinical trial. Front Endocrinol (Lausanne). 2022;13:1107071.
- Huang YY, Yao ZY. Clinical study on Shugan Jianpi Decoction combined with Western medicine in the treatment of childhood anorexia. J New Chin Med. 2021;53(17):123-125.
- Lian JL, et al. Effects of Tiaozhong Yin on clinical efficacy, electrogastrogram, serum zinc and vasoactive intestinal peptide in children with anorexia of the spleen deficiency and liver hyperactivity syndrome. J Pediatr Tradit Chin Med. 2020;16(1):42-46.
- Yang YF, et al. Exploration on the application of Chaizhu Tiaogan Lipi Decoction in pediatric diseases. J Chengdu Univ Tradit Chin Med. 2021;44(2):76-79.
- Guo DY, Chu CD. Comparative trial of modified Shenling Baizhu San combined with Xiaoyao San in the treatment of infantile anorexia. Anhui Med Pharm J. 2018;22(1):131-134.
- Jang JH, et al. Changes in small intestinal motility and related hormones by acupuncture stimulation at Zusanli (ST 36) in mice. Chin J Integr Med. 2017;23(3):215-220.
- Gao H, et al. Effects of pediatric Tuina on intestinal flora in children with anorexia. J Acupunct Tuina Sci. 2025;23(4):313-320.
- Zhou BW, Chen MM. Nie-pinching the spine, puncturing Sifeng (EX-UE 10) plus Chinese herbs for pediatric anorexia due to dysfunction of spleen in transportation: a randomized controlled trial. J Acupunct Tuina Sci. 2021;19(2):104-109.
- Zhang C, et al. Study on the mechanism of acupuncture underlying improvement of functional dyspepsia with depression-like behavior in rats. Zhen Ci Yan Jiu. 2025;50(1):76-83.
- Chen Y, et al. Acupuncture at Sifeng (EX-UE 10) for pediatric anorexia: a systematic review and meta-analysis. Complement Ther Med. 2023;78:102988.
- Cai RQ, et al. Clinical observation of Xiaoji Lipi San and Yanshi Patch combined with conventional treatment in children with anorexia (syndrome of spleen failing to govern transportation and transformation). Chin J Integr Tradit West Med Pediatr. 2025;17(6):461-465.
- Bao SR, Sun ZQ, Zheng SS. Effects of Xiaoer Liuwei Zengshi Paste on intestinal mucosal absorption function and gastrointestinal hormones in children with anorexia of the syndrome of spleen failing to govern transportation and transformation. J Clin Med Pract. 2021;25(15):110-113.
- Cao HL, et al. Research progress on traditional Chinese medicine in treating adolescent anorexia nervosa based on the “gut-brain co-regulation” theory. Sichuan J Tradit Chin Med. 2025;43(7):195-200.
- Tang QM, Tu YS. Efficacy observation of Jianpi Yiqi Paste in the treatment of infantile anorexia (spleen-stomach qi deficiency syndrome). Chin J Integr Tradit West Med Pediatr. 2025;17(6):472-476.
- Hu XL, Wu X. Review of traditional Chinese medicines in ameliorating neuropsychiatric diseases by improving the levels of monoamine neurotransmitters via gut microbiota regulation. Zhongguo Zhong Yao Za Zhi. 2023;48(4):853-860.
- Jia ZJ, et al. Effects of Xiaoyao Cong'er Formula on inflammatory factors and neurotransmitters in tinnitus rats with liver depression and spleen deficiency syndrome. China Med Herald. 2024;21(32):40-45.
- Li Y, Li HF. Efficacy of Tiaoren Tongdu acupuncture combined with Shugan Anshen Decoction in the treatment of insomnia and its effects on serotonin and dopamine levels. Mod J Integr Tradit Chin West Med. 2017;26(32):3561-3563,3594.
- Chen WK, Linghu T, Ren Y. Research progress on the mechanism of traditional Chinese medicine in the treatment of depression. Chin Tradit Herb Drugs. 2025;56(11):4090-4102.
- Reigstad CS, et al. Gut microbes promote colonic serotonin production through an effect of short-chain fatty acids on enterochromaffin cells. FASEB J. 2015;29(4):1395-1403.
- Zhang S, et al. Chronic constipation and the brain-gut-microbiome axis: the role of 5-HT signaling and traditional Chinese medicine in pathophysiology and treatment. Front Med (Lausanne). 2025;12:1706411.
- Bi C, et al. The microbiota-gut-brain axis and its modulation in the therapy of depression: comparison of efficacy of conventional drugs and traditional Chinese medicine approaches. Pharmacol Res. 2022;183:106372.
- Baek JY, et al. Electro-acupuncture alleviates cisplatin-induced anorexia in rats by modulating ghrelin and monoamine neurotransmitters. Biomolecules. 2019;9(10):624.
- Rantala MJ, et al. Eating disorders: an evolutionary psychoneuroimmunological approach. Front Psychol. 2019;10:2200.
- Zhang X, et al. Research progress in the effect of traditional Chinese medicine for invigoration on neurotransmitter related diseases. Evid Based Complement Alternat Med. 2018;2018:4642018.
- Von Deneen KM, et al. Connectivity study of the neuromechanism of acute acupuncture needling during fMRI in “overweight” subjects. Evid Based Complement Alternat Med. 2015;2015:384389.
- Smith GP. Accumbens dopamine mediates the rewarding effect of orosensory stimulation by sucrose. Appetite. 2004;43(1):11-13.
- Hernández L, Paredes D, Rada P. Feeding behavior as seen through the prism of brain microdialysis. Physiol Behav. 2011;104(1):47-56.
- Holliday A, et al. Appetite-related gut hormone responses to feeding across the life course. J Endocr Soc. 2025;9(2):bvae223.
- Lu X, et al. Effects of probiotic supplementation on intestinal flora, brain-gut peptides and clinical outcomes in children with anorexia nervosa. Br J Nutr. 2025;133(4):491-496.
- Liang Q, et al. Pingwei capsules improve gastrointestinal motility in rats with functional dyspepsia. J Tradit Chin Med. 2018;38(1):43-53.
- Brittain HR, Gorvin CM. Recent developments in GPCR signalling in appetite regulation. Biosci Rep. 2026;46(6):BSR20250120.
- Botushanov N, Botushanov A, Botushanova A. Neuroendocrine regulation of appetite. Folia Med (Plovdiv). 2026;68(1):e156353.
- Wang Y. A preliminary study on the bidirectional regulatory mechanism of electroacupuncture at different acupoints in rats with functional bowel disease [dissertation]. Nanjing University of Chinese Medicine; Nanjing; 2013.
- Li Y, et al. Study on the regulation of brain–gut peptide by Shenling Baizhu San in functional diarrhea rats. J Tradit Chin Med Sci. 2018;5(3):283-290.
- Xiong X, Xu TS. Exploration of the mechanism of traditional Chinese medicine in improving functional dyspepsia based on brain-gut interaction. Shaanxi J Tradit Chin Med. 2023;44(2):224-228.
- Su Y, et al. Laxative effect of Wenyang Yiqi Decoction on loperamide-induced astriction model mice. Ann Transl Med. 2023;11(4):170.
- Chen L, et al. Tong-fu-li-fei decoction exerts a protective effect on intestinal barrier of sepsis in rats through upregulating ZO-1/occludin/claudin-1 expression. J Pharmacol Sci. 2020;143(2):89-96.
- Banks WA. The blood-brain barrier: connecting the gut and the brain. Regul Pept. 2008;149(1-3):11-14.
- Gayle D, Ilyin SE, Plata-Salamán CR. Feeding status and bacterial LPS-induced cytokine and neuropeptide gene expression in hypothalamus. Am J Physiol. 1999;277(4):R1188-R1195.
- Montiel-Castro AJ, et al. The microbiota-gut-brain axis: neurobehavioral correlates, health and sociality. Front Integr Neurosci. 2013;7:70.
- Su W, et al. Potential efficacy and mechanism of eight mild-natured and bitter-flavored TCMs based on gut microbiota: a review. Chin Herb Med. 2024;16(1):42-55.
- Cuesta-Marti C, et al. In vitro assessment of bacterial supernatants on hypothalamic gene expression: implications for appetite regulation. NPJ Biofilms Microbiomes. 2025;11(1):192.
- Hwang YK, Oh JS. Interaction of the vagus nerve and serotonin in the gut–brain axis. Int J Mol Sci. 2025;26(3):1160.
- Zhou Y, et al. Repairing gut barrier by traditional Chinese medicine: roles of gut microbiota. Front Cell Infect Microbiol. 2024;14:1389925.
- Guo S, Chi X, Yin D. The role of brain-gut peptides in the symptoms of functional dyspepsia and their predictive value for disease. J Clin Med Res. 2024;5(4):611.
- Fu H, et al. Dynamic knowledge graphs for bidirectional causal reasoning in traditional Chinese medicine diagnosis. Expert Syst Appl. 2026;331:133434.
- Wang T, et al. Application of optogenetics and chemogenetics in brain science research of traditional Chinese medicine. World Chin Med. 2020;15(11):1535-1539,1545.
- Zhang ZX, et al. Application of brain science technologies in acupuncture research. World Sci Technol Mod Tradit Chin Med. 2022;24(3):911-917.
- Tjen ALSC, et al. Neurogenic hypotension and bradycardia modulated by electroacupuncture in hypothalamic paraventricular nucleus. Front Neurosci. 2022;16:934752.
- Zheng S, et al. Chinese medicine in the treatment of non-alcoholic fatty liver disease based on network pharmacology: a review. Front Pharmacol. 2024;15:1381712.
- Yuan Y, et al. Research progress on analytical techniques for the pharmacodynamic material basis of traditional Chinese medicine compound formulas. China Pharm. 2025;36(21):2738-2741.
- Liu X, Wen X. The latest research progress on traditional Chinese medicine treatment of functional gastrointestinal diseases with emotional disorders based on the “brain-gut axis” and “neuroendocrine-immune network.” Journal of Contemporary Medical Practice. 2025;7(8):172-178.
- Zeng F, et al. Influence of acupuncture treatment on cerebral activity in functional dyspepsia patients and its relationship with efficacy. Am J Gastroenterol. 2012;107(8):1236-1247.