This review summarizes positron emission tomography– and single-photon emission computed tomography–based radionuclide imaging strategies for tracking mesenchymal stem cells during knee osteoarthritis therapy and their translational applications.
מאמר סקירה
Radionuclide Imaging for Tracking Mesenchymal Stem Cell Therapy in Knee Osteoarthritis: Current Status and Pathways to Clinical Translation
במאמר זה
סיכום
תקציר
Knee osteoarthritis (KOA) is a common degenerative joint disease, and mesenchymal stem cell (MSC) therapy has emerged as a promising regenerative treatment option. However, the clinical translation of MSC therapy faces significant challenges, particularly in effectively monitoring the in vivo behavior of MSCs, including their survival, biodistribution, and functional integration. This review provides a comprehensive examination of the current landscape of radionuclide imaging techniques, particularly positron emission tomography (PET) and single-photon emission computed tomography (SPECT), for tracking MSCs in the treatment of KOA. It outlines the primary challenges associated with these imaging methods, including limitations related to radiotoxicity, tracer efflux, and the precision of quantitative cell tracking. Furthermore, the review discusses the potential of multimodal imaging and artificial intelligence (AI)-driven automated analysis to address these challenges, facilitating more accurate and functional monitoring of MSCs and their therapeutic effects. The review concludes by outlining future research directions, with an emphasis on the development of improved labeling methods, optimized imaging technologies, and enhanced integration of AI into clinical applications. These advancements are crucial for bridging the gap between preclinical findings and clinical practice, ultimately establishing radionuclide imaging as a potentially valuable tool for the clinical management of KOA.
מבוא
Knee osteoarthritis (KOA) is a chronic degenerative disease involving the entire joint and represents one of the most common forms of osteoarthritis. It is associated with substantial disability and a considerable socioeconomic burden, making it a global public health concern1,2. Current mainstream treatment strategies have significant limitations. Non-steroidal anti-inflammatory drugs (NSAIDs) offer only short-term pain relief and anti-inflammatory effects without preventing cartilage degradation3, and physical therapy provides limited benefits for advanced disease. Joint arthroplasty can improve function in end-stage disease; however, it involves substantial surgical trauma, risks of perioperative complications, and limited prosthesis longevity. Overall, most currently available treatments primarily focus on symptom relief and provide limited modification of the underlying disease process, underscoring an urgent need for new therapies. Regenerative approaches based on mesenchymal stem cells (MSCs) have therefore attracted increasing attention.
MSCs are adult stem cells with multilineage differentiation potential and have demonstrated considerable therapeutic potential in KOA. Their therapeutic effects may involve paracrine signaling, immunomodulation, and, to a lesser extent, direct differentiation toward chondrogenic or osteogenic lineages4. The clinical evidence supporting MSC therapy for KOA has been systematically evaluated in multiple recent meta-analyses. A systematic review of 43 clinical trials found that 97.7% of trials reported clinical improvement following MSC therapy, and 76.7% reported better clinical outcomes in MSC-treated groups than in control groups5. Furthermore, a meta-analysis of 25 randomized controlled trials enrolling 1,048 participants demonstrated that MSC therapy resulted in significantly lower pain scores than viscosupplementation at 12 months of follow-up (visual analog scale [VAS] mean difference [MD], −1.91; 95% confidence interval [CI], −3.23 to −0.59), with no difference in adverse events6. These findings underscore the therapeutic promise of MSCs while also highlighting the need for standardized protocols and more rigorous evaluation tools.
However, a major bottleneck in clinical translation is the poorly understood in vivo fate of MSCs. Crucial questions persist regarding where the cells go after injection, how long they survive, and how they exert therapeutic effects. Conventional methods cannot reliably determine whether intra-articular leakage occurs, whether intravenous infusion leads to pulmonary first-pass effects, whether cells effectively home to damaged knee joint sites, or how long they survive and function in the inflammatory microenvironment. This uncertainty directly limits the standardization of clinical parameters such as dosage, administration route, and treatment timing. To address this gap, molecular imaging techniques such as positron emission tomography (PET) and single-photon emission computed tomography (SPECT) provide unique advantages by enabling noninvasive, dynamic, and quantitative monitoring of transplanted cell distribution and fate, thereby offering a solid foundation for optimizing MSC therapy.
PET and SPECT, as representative functional molecular imaging modalities in nuclear medicine, provide critical technical frameworks for elucidating these complex biological processes. Unlike conventional imaging, which visualizes only macroscopic knee joint anatomy, PET and SPECT can address three core questions about MSCs in real time through noninvasive dynamic monitoring, high-sensitivity detection, and quantitative analysis: “Where do they go? How long do they survive? How do they exert their effects?”7 This capability is grounded in the fundamental principles of molecular imaging: PET offers superior sensitivity (10−11–10−12 mol/L) and quantitative accuracy, enabling the longitudinal and noninvasive evaluation of post-transplant cellular behavior8. As highlighted in a recent editorial, PET molecular imaging integrates individual features, cellular properties, and dynamic biomarkers, enabling personalized strategies for stem cell therapy with maximized efficacy and minimized risks9. Furthermore, by tracking the temporal dynamics of stem cells in vivo, molecular imaging directly facilitates the evaluation of therapeutic efficacy in clinical practice10. Specifically, PET can enable systemic, dynamic, and long-term tracking of stem cells after transplantation, revealing their biodistribution throughout the body and across target and non-target organs11.
Using ex vivo radionuclide labeling, PET and SPECT enable real-time dynamic tracking of cell migration and homing, precise assessment of cell survival and proliferation, and simultaneous quantitative analysis of local metabolic changes in the knee joint, thereby supporting the precise optimization of MSC-based therapeutic protocols. The impact of PET imaging on therapy optimization extends beyond mere visualization. By providing real-time pharmacokinetic data on cell biodistribution, PET enables the optimization of critical therapeutic parameters, including delivery route, dosage, and timing12. For instance, dynamic PET tracking of [89Zr]Zr-radiolabeled MSCs revealed that cell size serves as the primary biophysical determinant governing MSC localization within host tissues, a finding with direct implications for cell selection in clinical practice. Similarly, PET monitoring has demonstrated that the initial distribution of transplanted MSCs is consistent across species but differs according to the administration route, informing decisions on optimal delivery strategies. As such, PET molecular imaging can provide valuable support for optimizing stem cell therapy and bridging the gap to clinical practice. It serves not merely as an imaging tool but also as an active decision-support system that facilitates clinical translation. However, both techniques face practical challenges, such as radiation dose, labeling efficiency, and the balance between signal detection and cell viability. A consensus on clinical application scenarios and detection thresholds has not yet been reached.
This review examines the technical principles and current applications of PET and SPECT in MSC therapy for KOA, focusing on their roles in cell tracking, viability assessment, and therapeutic efficacy monitoring. Current technical bottlenecks and barriers to clinical translation are discussed, and the potential of emerging technologies, such as artificial intelligence (AI) and multimodal imaging, is explored, with the aim of providing a reference for in-depth research and clinical translation in this interdisciplinary field.
From a practical standpoint, the selection of an appropriate radionuclide imaging strategy for KOA-MSC therapy should be guided by several key clinical decision points. First, the route of administration dictates the required imaging window and radionuclide half-life: for intra-articular (IA) injection, where the primary concern is local retention versus leakage within 24–48 h, short-half-life tracers such as 99mTc (t1/2 = 6.02 h) or 18F (t1/2 = 110 min) are more appropriate13; for intravenous (IV) administration, where systemic tracking across multiple organs over several days is required, longer-half-life isotopes such as 89Zr (t1/2 = 78.4 h) or 111In (t1/2 = 67.3 h) are necessary. Second, labeling efficiency and cell viability must be balanced: while higher radionuclide activity improves imaging sensitivity, activities exceeding 0.5 Bq per cell for 89Zr may induce DNA damage and apoptosis. Third, the choice between direct labeling and reporter gene approaches involves a trade-off between simplicity and specificity—direct labeling is clinically straightforward but suffers from tracer efflux and signal attenuation from dead cells, whereas reporter gene methods ensure that only viable cells are detected but require genetic modification, raising additional regulatory hurdles. Fourth, the interpretive framework must account for the fact that persistent radionuclide signals may originate from apoptotic debris or tracer redistribution rather than viable cells, necessitating validation with complementary functional assays14.
Beyond these primary decision points, the clinical translation of PET/SPECT for KOA-MSC tracking is further governed by several technical and biological constraints. A major limitation is the translational resolution gap between preclinical micro-PET systems (~1 mm) and clinical scanners (~4–5 mm). This resolution gap means that signals readily detectable in rodent joints may fall below the detection threshold in human knees, particularly given the small number of MSCs that survive and engraft after transplantation15. Furthermore, the unique pharmacokinetics of the knee joint compartment, including impaired synovial lymphatic clearance in KOA (t1/2 prolonged from 0.5 h to 2.8 h) and elevated background signals from synovitis (present in 74%–95% of patients with KOA), further complicate quantitative signal interpretation16. Addressing these constraints will require not only standardized imaging protocols but also the integration of higher-resolution hardware and advanced quantitative algorithms.
סקירה ופרספקטיבה
Pathophysiology of Knee Osteoarthritis and Mesenchymal Stem Cell Therapy
Core Molecular Pathological Features of Knee Osteoarthritis:
The hallmark of KOA is progressive degeneration of articular cartilage, driven by matrix metalloproteinases (MMPs) and aggrecanases that degrade the extracellular matrix, leading to cartilage thinning and erosion (Figure 1). Vascular channels form at these sites, allowing abnormal ingrowth of blood vessels and nerves, while pro-inflammatory cytokines (IL-1β, TNF-α) further sensitize pain receptors. The infrapatellar fat pad, together with the adjacent cartilage and synovium, constitutes a functionally integrated pathological unit that drives disease progression17,18,19.
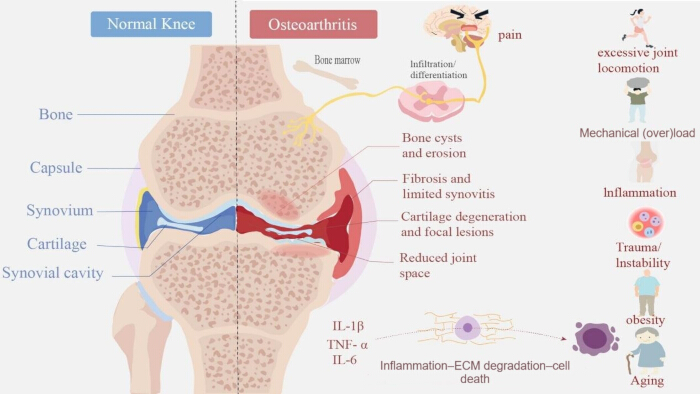
Figure 1: Comparison of the normal knee joint and pathological changes in knee osteoarthritis. The left panel illustrates the normal knee joint and identifies the bone, joint capsule, synovium, articular cartilage, and synovial cavity. The middle panel illustrates characteristic pathological changes associated with knee osteoarthritis (KOA), including bone cysts and erosion, synovial fibrosis and inflammation, cartilage degeneration and focal lesions, and reduced joint space. The inflammatory joint microenvironment is characterized by increased levels of pro-inflammatory cytokines, including interleukin-1 beta (IL-1β), tumor necrosis factor alpha (TNF-α), and interleukin-6 (IL-6), which contribute to extracellular matrix (ECM) degradation and cell death. The right panel summarizes major factors associated with KOA development and progression, including excessive joint locomotion, mechanical overload, inflammation, trauma or instability, obesity, and aging, which contribute to inflammatory responses and pain. Please click here to view a larger version of this figure.
The Normal Knee Joint Microenvironment: Anatomical and Physiological Considerations for Radionuclide Imaging: The knee joint is a pharmacokinetically distinct, closed synovial compartment that must be considered when interpreting radionuclide signals20. In the healthy joint, 0.5–4 mL of synovial fluid—enriched with hyaluronic acid (HA) and lubricin—is regulated by a thin synovial intima and cleared mainly through a synovial lymphatic plexus. Articular cartilage is avascular and aneural and is composed of 60%–80% water, 15%–20% type II collagen, and 3%–10% proteoglycans (Table 1)21,22,23,24.
| Component | Key Features | Functional Significance for Tracer Behavior | |||
| Joint cavity | Closed synovial space; ~0.5–4 mL of synovial fluid | Defines a pharmacokinetically confined compartment; tracer clearance depends on synovial lymphatics and microvascular reabsorption | |||
| Articular cartilage | Avascular and aneural; 60–80% water, 15–20% type II collagen, and 3–10% proteoglycans; 2–4 mm thick | No direct blood supply; tracer access occurs via diffusion from synovial fluid; the thin structure is susceptible to partial volume effects | |||
| Synovial intima | 1–2 cell layers; type A (macrophage-like) and type B (fibroblast-like) cells; loose intercellular junctions | Regulates synovial fluid composition; intercellular gaps (0.1–5.0 μm) allow the passage of large molecules and tracers | |||
| Synovial fluid | Plasma ultrafiltrate containing hyaluronic acid (HA; 2–4 mg/mL) and lubricin; viscosity of 10–100 Pa·s; <200 cells/μL | High viscosity slows tracer diffusion; HA provides viscosity-dependent retention; low cellularity results in a low baseline metabolic signal | |||
| Synovial vasculature | Genicular arterial network; dense subintimal capillary plexus; regulated permeability | Primary route for tracer influx from the blood into the joint cavity; permeability is tightly regulated under normal conditions | |||
| Synovial lymphatics | Lymphatic plexus in the subintima draining to the popliteal lymph nodes | Primary route for macromolecular and particulate tracer clearance; clearance t₁/₂ is ~0.5 h in young, healthy joints | |||
| Ligaments (ACL, PCL, MCL, LCL) | Hypovascular except at insertion sites (entheses); poor healing capacity, particularly for the ACL | Limited vascular access for tracers; enthesis vascularization may create focal uptake hotspots | |||
| Subchondral bone | Trabecular bone with a vascular supply; cartilage–bone interface | Active bone-turnover sites may accumulate bone-seeking tracers (e.g., [99mTc]Tc-MDP); vascular exchange occurs at the subchondral plate | |||
| Infrapatellar fat pad (IFP) | Adipose tissue that secretes adipokines and lipid mediators | Metabolically active; may contribute to background FDG signal and serves as a source of inflammatory mediators in KOA | |||
Table 1: Structural and functional characteristics of the normal knee joint microenvironment. Summary of the principal anatomical and physiological components of the normal knee joint and their functional significance for radionuclide tracer distribution, retention, and clearance. ACL, anterior cruciate ligament; PCL, posterior cruciate ligament; MCL, medial collateral ligament; LCL, lateral collateral ligament; HA, hyaluronic acid; IFP, infrapatellar fat pad; FDG, fluorodeoxyglucose; KOA, knee osteoarthritis; t1/2, half-life.
Pathological Remodeling of the Joint Microenvironment in KOA: KOA remodels this environment through three coupled changes that directly alter tracer kinetics. First, synovitis is present in 74% of patients with KOA across all Kellgren–Lawrence grades and in up to 95% of those with moderate-to-severe disease; inflammatory mediators (IL-6 at ~120-fold the serum concentration) degrade HA, reducing fluid viscosity and creating heterogeneous tracer “pooling”25. Second, permeability increases via VEGF and TGF-β signaling, accelerating tracer influx but also elevating background signals through plasma protein extravasation26. Third, synovial lymphatic clearance is impaired—the clearance half-time is prolonged from 0.5 to 2.8 h in aged/OA joints—causing prolonged tracer retention that may be mistaken for cell survival. Concurrently, progressive cartilage thinning (<1 mm in advanced KOA) further exacerbates partial volume effects, as the cartilage thickness falls below the resolution of clinical PET/SPECT27,28,29. Beyond altering tracer kinetics, these microenvironmental changes also actively modify MSC behavior, with inflammatory conditions promoting a destructive MSC phenotype via MMP-13 upregulation30,31. The key changes are summarized in Table 2, with tracer-specific considerations presented in Table 3.
| Component | Normal State | KOA-Induced Changes | Impact on Radionuclide Imaging | |||||
| Synovial fluid volume | 0.5–4 mL | Increased effusion, often >10 mL | Larger distribution volume → signal dilution; altered tracer diffusion kinetics | |||||
| Synovial fluid composition | High HA (2–4 mg/mL); low cytokine levels; viscosity of 10–100 Pa·s | HA degradation → reduced viscosity; elevated IL-1β, TNF-α, IL-6 (~120× serum), IL-18 (~5× serum), and MMP-3 (~18× serum) | Tracer “pooling” in areas of effusion; nonspecific probe binding to inflammatory proteins; reduced TBR | |||||
| Synovial intima | 1–2 cell layers; low metabolic activity | Hyperplasia; >2-fold increase in M1/M2 ratio; NF-κB activation; aggressive FLS phenotype | Increased metabolic background signal due to increased FDG uptake by activated synoviocytes and macrophages; focal inflammatory hotspots | |||||
| Vascular permeability | Tightly regulated | VEGF-driven angiogenesis; ~2-fold elevation in TGF-β; increased permeability | Increased tracer influx from blood → enhanced sensitivity but increased background signal; plasma protein extravasation → increased nonspecific signal | |||||
| Lymphatic clearance | t1/2 ~0.5 h in young joints; inflow 4.1% | t1/2 ~2.8 h in aged/OA joints; inflow 1.7%; decreased VEGF-C in late OA | Prolonged tracer retention → apparent signal persistence; delayed clearance may mimic cell survival | |||||
| Articular cartilage | 2–4 mm; intact type II collagen and aggrecan | ~40% collagen loss from grade 1 to grade 4; ~80% reduction in elastic modulus; MMP-13/ADAMTS-5-mediated degradation | Thinner target → greater PVE; signal spillover into adjacent bone or fluid; reduced quantitative accuracy | |||||
| Subchondral bone | Normal trabecular architecture | Sclerosis, BMLs, and SBCs (74.2% prevalence); abnormal remodeling | Focal [99mTc]Tc-MDP uptake unrelated to MSC engraftment; altered pharmacokinetics at the cartilage–bone interface | |||||
| Infrapatellar fat pad | Quiescent adipose tissue | Pro-inflammatory adipokine secretion; fibrosis | Additional source of FDG-avid inflammatory signal; altered local tracer distribution | |||||
| Inflammatory microenvironment | Low cytokine milieu | Five interacting dimensions: inflammation, senescence, hypoxia, hyperglycemia, and hyperlipidemia | May induce a destructive MSC phenotype with increased MMP-13 expression; tracer signal may reflect inflammation rather than MSC viability | |||||
| Immune cell composition | <200 cells/μL in synovial fluid | Macrophages constitute 12–40% of synovial cells; M1 dominance; T-cell infiltration | FDG uptake by macrophages is ~3.5-fold higher than that by parenchymal cells; MSC-derived signals cannot be readily distinguished from inflammatory cell signals | |||||
Table 2: KOA-induced alterations of the joint microenvironment and their implications for radionuclide imaging. Comparison of the normal knee joint microenvironment with KOA-associated changes and their potential effects on radionuclide tracer distribution, retention, background signal, and quantitative interpretation. KOA, knee osteoarthritis; HA, hyaluronic acid; IL, interleukin; TNF-α, tumor necrosis factor alpha; MMP, matrix metalloproteinase; TBR, target-to-background ratio; NF-κB, nuclear factor kappa B; FLS, fibroblast-like synoviocyte; FDG, fluorodeoxyglucose; VEGF, vascular endothelial growth factor; TGF-β, transforming growth factor beta; OA, osteoarthritis; VEGF-C, vascular endothelial growth factor C; PVE, partial volume effect; ADAMTS-5, a disintegrin and metalloproteinase with thrombospondin motifs 5; BML, bone marrow lesion; SBC, subchondral bone cyst; MSC, mesenchymal stem cell; t1/2, half-life.
| Probe | Isotope/Half-life | Target/Mechanism | Advantages in KOA | Limitations in the KOA Microenvironment | |||
| [18F]FDG | 18F / 110 min | Glucose metabolism via GLUT transport | High sensitivity; SUV correlates with WOMAC (r = 0.309) and K-L grade (r = 0.410); SUV is an independent predictor of OA progression (HR = 5.653) | Nonspecific; macrophage FDG uptake is 3.5-fold higher than that of parenchymal cells; cannot distinguish MSCs from activated synoviocytes or macrophages; interference from insulin and metformin; variability in physiological joint uptake | |||
| [68Ga]Ga-FAPI | 68Ga / 68 min | Fibroblast activation protein (FAP) | Detects stromal activation before structural damage; identifies 6.1% more affected joints than FDG in RA; lower physiological uptake than FDG | EPR effect in inflamed synovium may cause nonspecific uptake; limited KOA-specific validation; short half-life constrains the imaging window | |||
| [68Ga]Ga-Pentixafor | 68Ga / 68 min | CXCR4 receptor | Targets an MSC homing receptor; potential for specific MSC tracking when cells are CXCR4-engineered | CXCR4 is also expressed on infiltrating inflammatory cells; limited data in KOA; cannot distinguish endogenous from transplanted CXCR4-positive cells | |||
| [89Zr]Zr-oxine (cell labeling) | 89Zr / 78.4 h | Passive intracellular diffusion; binding to intracellular proteins | Long half-life enables IV tracking over days to weeks; labeling efficiency ~47–87%; prolonged intracellular retention | Signal may persist after cell death because of apoptotic debris or tracer release (see Section 1.2); radiation burden to labeled cells; lymphatic impairment prolongs apparent retention | |||
| [89Zr]Zr-DFO-NCS (cell labeling) | 89Zr / 78.4 h | Surface protein conjugation via DFO chelator | Labeling efficiency up to 87.3%; maintains MSC viability; applicable to HSCs | Higher lung uptake than the oxine formulation; higher effective radiation dose; same viability ambiguity as other direct-labeling approaches | |||
| [99mTc]Tc-HMPAO (cell labeling) | 99mTc / 6 h | Lipophilic diffusion followed by intracellular glutathione trapping | Short half-life is suitable for IA injection and 24–48 h assessment; high labeling efficiency; lower radiation dose | Significant tracer efflux from cells at 24 h; limited to short-term tracking; unsuitable for long-term IV homing assessment | |||
| [99mTc]Tc-MDP | 99mTc / 6 h | Hydroxyapatite in bone mineral | Assesses subchondral bone metabolism; reflects bone remodeling; complements cellular tracers | Nonspecific bone uptake; cannot assess soft-tissue or cellular dynamics; SBCs and BMLs may produce confounding focal uptake | |||
| [111In]In-oxine (cell labeling) | 111In / 2.8 days | Passive intracellular diffusion | Intermediate half-life for SPECT tracking; suitable for monitoring over 3–7 days | Lower spatial resolution than PET; higher radiation dose per cell; γ-emission requires longer acquisition times | |||
| NIS reporter gene | 99mTcO₄⁻ / 125I / [18F]TFB | Sodium iodide symporter (SLC5A5) | Only viable cells produce a signal because reporter expression requires transcription; enables repeated imaging; distinguishes viable from dead cells | Requires genetic modification, creating ethical barriers for non-life-threatening KOA (see Section 3.2); potential immune response to NIS protein; limited clinical translation | |||
| HSV1-tk reporter gene | [18F]FEAU / [124I]FIAU | Herpes simplex virus type 1 thymidine kinase | PET-based; high sensitivity; well characterized in preclinical models | Requires viral-vector-mediated genetic modification; risk of insertional mutagenesis and immunogenicity; particularly challenging for clinical translation in non-life-threatening KOA | |||
Table 3: Principal radionuclide probes used in KOA-MSC imaging: advantages, limitations, and KOA microenvironment-specific considerations. Summary of radionuclide probes and reporter-gene approaches relevant to MSC tracking and complementary imaging in KOA, including radionuclide half-life, principal targeting or labeling mechanism, potential advantages, and limitations associated with the KOA microenvironment. FDG, fluorodeoxyglucose; GLUT, glucose transporter; SUV, standardized uptake value; WOMAC, Western Ontario and McMaster Universities Osteoarthritis Index; K-L, Kellgren–Lawrence; OA, osteoarthritis; HR, hazard ratio; FAPI, fibroblast activation protein inhibitor; FAP, fibroblast activation protein; RA, rheumatoid arthritis; EPR, enhanced permeability and retention; CXCR4, C-X-C chemokine receptor type 4; MSC, mesenchymal stem cell; DFO, desferrioxamine; NCS, isothiocyanate; HSC, hematopoietic stem cell; IV, intravenous; IA, intra-articular; HMPAO, hexamethylpropyleneamine oxime; MDP, methylene diphosphonate; SBC, subchondral bone cyst; BML, bone marrow lesion; SPECT, single-photon emission computed tomography; PET, positron emission tomography; NIS, sodium iodide symporter; SLC5A5, solute carrier family 5 member 5; TFB, tetrafluoroborate; HSV1-tk, herpes simplex virus type 1 thymidine kinase; FEAU, 2′-fluoro-2′-deoxy-1β-D-arabinofuranosyl-5-ethyluracil; FIAU, 2′-fluoro-2′-deoxy-1β-D-arabinofuranosyl-5-iodouracil.
Collectively, the osteoarthritic joint is an active pharmacokinetic environment rather than a neutral imaging substrate. Failure to account for these factors may lead to misattribution—interpreting prolonged tracer retention as MSC survival when it reflects lymphatic impairment, or increased FDG uptake as MSC metabolism when it originates from activated macrophages (which exhibit ~3.5-fold higher glucose metabolism than parenchymal cells). Future protocols should therefore incorporate synovitis grading and lymphatic function assessment as covariates for accurate interpretation and should prioritize dynamic acquisition protocols over static time-point measurements to distinguish cell-associated signals from free-tracer kinetics.
Mechanisms of Mesenchymal Stem Cell Therapy in Knee Osteoarthritis:
MSCs exert therapeutic effects in KOA mainly through paracrine signaling and immunomodulation, with direct differentiation contributing to a lesser extent. Injury-derived cytokines can induce MSC differentiation toward chondrocytes and osteoblasts, providing a cellular basis for in situ regeneration, and MSCs from even end-stage diseased tissue retain repair potential32,33,34. The dominant mechanism, however, is the secretion of bioactive factors—notably MSC-derived extracellular vesicles (MSC-EVs) and cytokines—that inhibit chondrocyte apoptosis, delay extracellular matrix (ECM) degradation, and stimulate endogenous progenitors35.
Regarding EV terminology, two complementary classification systems should be distinguished: biogenesis-based classification divides EVs into exosomes, microvesicles, and apoptotic bodies, whereas size-based classification categorizes them as small EVs (<200 nm), medium EVs (200–500 nm), and large EVs (>500 nm)36. MSC-EVs transfer bioactive cargo (lipids, proteins, messenger RNA [mRNA], microRNA [miRNA], and long non-coding RNA) to recipient cells, recapitulating the immunomodulatory functions of parent MSCs while offering reduced immunogenicity and fewer ethical constraints as a cell-free strategy37. Current evidence indicates that MSCs act mainly by modulating immune cell activity and inflammatory factor secretion rather than through permanent engraftment38,39,40 (Figure 2).
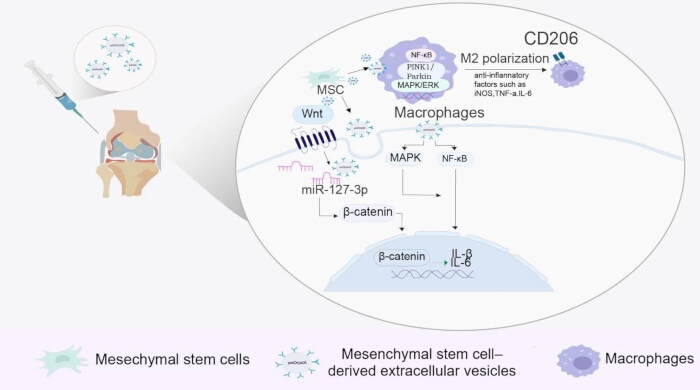
Figure 2: Anti-inflammatory and immunomodulatory mechanisms of mesenchymal stem cell-derived extracellular vesicles in knee osteoarthritis. Mesenchymal stem cells (MSCs) and MSC-derived extracellular vesicles (MSC-EVs) modulate inflammatory signaling within the osteoarthritic joint. MSC-EVs regulate Wnt/β-catenin signaling through miR-127-3p and modulate mitogen-activated protein kinase (MAPK) and nuclear factor kappa B (NF-κB) signaling. MSCs and MSC-EVs also regulate macrophage activity and promote anti-inflammatory M2 macrophage polarization, characterized by CD206 expression and the production of anti-inflammatory mediators, including interleukin-10 (IL-10), transforming growth factor beta (TGF-β), and interleukin-6 (IL-6). Collectively, these mechanisms contribute to modulation of the inflammatory joint microenvironment in knee osteoarthritis. Please click here to view a larger version of this figure.
Importantly, MSC apoptosis itself—rather than being a therapeutic failure—is an indispensable component of the immunomodulatory cascade, termed the “dying stem cell hypothesis”41. Clinical and preclinical evidence confirms rapid MSC apoptosis after transplantation: MSC-derived cell-free DNA peaks at 4 h post-infusion and becomes undetectable within 1 week, and transplanted MSCs are nearly cleared within 7 days in mice42,43,44. This apoptotic clearance is biologically active: apoptotic MSCs are engulfed by macrophages via efferocytosis, driving M2 polarization characterized by IL-10 and kynurenine secretion and T-cell suppression45,46. These findings reframe the interpretation of radionuclide tracking—a persistent 89Zr or 111In signal days to weeks after injection may originate from apoptotic debris or tracer taken up by macrophages rather than from viable cells.
Limitations of Conventional Imaging for Monitoring:
Conventional imaging modalities cannot monitor the dynamic behavior of MSCs at the cellular level. X-ray imaging offers high spatial resolution but very low soft-tissue contrast—owing to minimal differences in electron density between soft tissues and surrounding fluid—so it can only assess late-stage structural changes through indirect signs such as joint-space narrowing and osteophytes47. Although magnetic resonance imaging (MRI) is the clinical gold standard for morphological assessment of cartilage, it cannot distinguish viable MSCs from apoptotic debris or provide real-time, quantitative tracking for therapeutic optimization48. Consequently, conventional imaging is insufficient for predicting long-term outcomes, whereas molecular imaging bridges this gap through noninvasive, dynamic, and quantitative monitoring of MSC behavior.
Comparison of Radionuclide Imaging with Other Cell Tracking Modalities:
Optical imaging—including bioluminescence and fluorescence—offers high sensitivity and multiplexed tracking, but poor tissue penetration and signal attenuation restrict its use to small animals, making it unsuitable for deep joints49,50. Magnetic particle imaging (MPI) detects superparamagnetic iron oxide tracers with zero background and depth-independent detection but remains preclinical, with uncertain long-term tracer safety51,52. Ultrasound molecular imaging uses targeted microbubbles and offers real-time temporal resolution, but penetration and quantification are limited in deep joints53,54.
In contrast, PET and SPECT offer decisive advantages for KOA-MSC tracking: (1) unlimited tissue penetration; (2) whole-body imaging for systemic biodistribution; (3) absolute quantification using standardized uptake value (SUV) and percentage injected dose per gram (%ID/g); (4) established clinical infrastructure; and (5) compatibility with molecularly specific tracers. Although PET/SPECT involve ionizing radiation and have lower spatial resolution than MRI, their depth-independent, quantitative, whole-body imaging capabilities make them well suited for longitudinal monitoring of MSC biodistribution in KOA55,56,57,58,59.
Comparison of Molecular Imaging Techniques: PET vs SPECT
Positron Emission Tomography (PET):
PET detects annihilation photons from positron-emitting radionuclides to generate three-dimensional tomographic images60,61. Its main advantages are very high sensitivity (10−11–10−12 mol/L), good spatial resolution (4–5 mm clinically and 1–2 mm with micro-PET), and quantitative capability. Positron emitters typically have short half-lives, limiting long-term tracking; however, the longer-lived 89Zr (t1/2 = 78.4 h) partially overcomes this constraint. Despite these advantages, PET has inherent limitations: the equipment is expensive, and some tracers lack cell specificity62.
In MSC tracking, PET enables dynamic monitoring of cell distribution, homing efficiency, and metabolic activity. However, signal interpretation requires caution: high uptake may originate from transplanted cells, host inflammatory cells, or metabolic activation during tissue repair. Distinguishing these sources therefore requires control experiments or multimodal imaging (e.g., PET/MRI) to differentiate cell retention from nonspecific uptake63,64.
[18F]Fluorodeoxyglucose ([18F]FDG) is the most widely used PET tracer. It enters cells via glucose transporters (GLUTs) and is phosphorylated by hexokinase to [18F]FDG-6-phosphate, which cannot undergo further glycolysis and is metabolically trapped intracellularly65,66. However, [18F]FDG lacks cell specificity and cannot distinguish MSCs from activated inflammatory cells; it is therefore mainly used to assess the overall metabolic status of the transplantation microenvironment rather than for specific cell tracking67,68. This nonspecificity is particularly problematic in KOA, where synovitis—present in up to 95% of patients—creates a persistently elevated background signal.
89Zr, with a 78.4-h half-life, is well suited for long-term MSC tracking, achieving 70%–90% labeling efficiency with Df-Bz-NCS or [89Zr]Zr-oxine complexes69. However, activities >0.5 Bq/cell may induce DNA damage and apoptosis, and free 89Zr released from dead cells can be reaccumulated by surrounding tissues, generating false-positive signals that must be interpreted using complementary viability assays70. As alternatives to direct labeling, reporter-gene and targeted probes—such as the CXCR4-targeted [68Ga]Ga-Pentixafor, which binds a receptor involved in MSC homing—offer greater cell specificity than [18F]FDG and are under active investigation71,72,73,74.
Single-Photon Emission Computed Tomography (SPECT):
SPECT detects gamma rays from single-photon-emitting radionuclides using a rotating gamma camera to reconstruct three-dimensional images75,76. Its core advantages are wide radionuclide availability, low cost, and multi-tracer imaging. However, its sensitivity (10−10–10−11 mol/L) and spatial resolution (8–10 mm) are lower than those of PET, and its quantitative accuracy is affected by attenuation and scatter correction.
In MSC tracking, SPECT is often combined with computed tomography (CT; SPECT/CT) for anatomical localization77. 99mTc (t1/2 = 6.02 h) is one of the most widely used SPECT radionuclides. [99mTc]Tc-HMPAO directly labels viable cells (50%–70% efficiency) for short-term (≤24 h) distribution studies; however, it is prone to cellular leakage and decreased post-labeling viability, and its short half-life makes it unsuitable for long-term tracking78,79. [99mTc]Tc-MDP is widely used for bone metabolic imaging but reflects bone metabolism rather than MSCs and must therefore be combined with cell-labeling strategies80,81.
Bifunctional chelators such as DTPA and CHX-A″-DTPA form thermodynamically stable complexes with 111In, reducing radioactive dissociation and leakage82,83. In theranostics, 177Lu (t1/2 ≈ 6.7 days) combines β-emission with therapeutic potential and is being explored for combined imaging and local radiotherapy84,85.
Nuclear Medicine Approaches to MSC Labeling and Tracking
Direct Labeling Method:
Direct labeling remains a preferred method for radionuclide labeling of MSCs and is the mainstream approach in current preclinical studies. Lipophilic carriers (e.g., oxine and HMPAO) transport radiotracers into the cytoplasm via passive diffusion or endocytosis without genetic modification, offering simplicity, considerable labeling efficiency, and suitability for short-term distribution studies (Figure 3)86. However, several inherent limitations remain: tracers do not participate in genetic replication, so the signal is progressively diluted with cell division; some tracers are actively expelled by cells; and free tracers released from apoptotic MSCs can be phagocytosed by macrophages, causing background signals and imaging distortion87. Additionally, high tracer concentrations may impair MSC proliferation and differentiation, and no standardized protocol exists for determining the optimal labeling concentration.
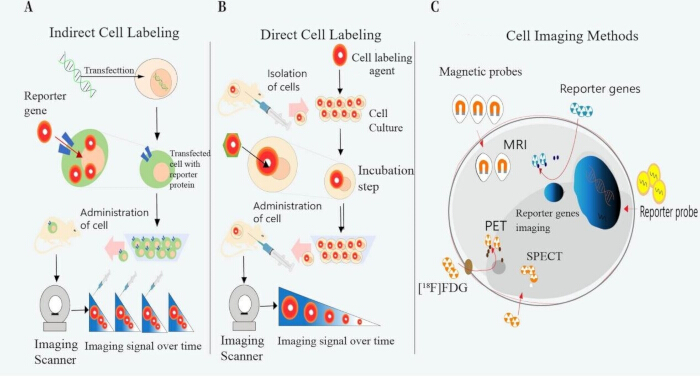
Figure 3: Principles of direct and indirect cell labeling and imaging approaches for stem cell tracking. (A) Indirect cell labeling using a reporter-gene strategy. Cells are genetically modified to express a reporter protein and are subsequently administered to the subject. Following administration of a corresponding imaging probe, reporter-expressing cells can be monitored longitudinally using molecular imaging. Reporter-gene expression is maintained in viable cells and can be transmitted to daughter cells. (B) Direct cell labeling. Cells are isolated and labeled in vitro with an imaging agent before administration to the subject, allowing their distribution to be monitored over time. In contrast to reporter-gene labeling, the detected signal may persist independently of cell viability and can decrease because of radioactive decay, tracer efflux, or cell division. (C) Schematic representation of imaging approaches used for cell tracking, including magnetic resonance imaging (MRI), positron emission tomography (PET), single-photon emission computed tomography (SPECT), and reporter-gene imaging. [18F]Fluorodeoxyglucose ([18F]FDG) is shown as an example of a PET radiotracer.Please click here to view a larger version of this figure.
Indirect Labeling Method/Reporter Gene Method:
Indirect (reporter-gene) labeling addresses the signal attenuation and false-positive signals associated with direct labeling: MSCs are transduced with reporter genes such as HSV1-tk or NIS so that only viable cells capture and retain the specific radiotracer, enabling precise monitoring of viable cells. As a proof of concept, Kitzberger et al. used an interleukin-6 (IL-6) promoter to drive NIS expression in MSCs and, combined with [18F]TFB PET imaging and subsequent 131I radiotherapy, inhibited glioblastoma growth and increased median mouse survival by 60%, demonstrating the feasibility of viable-cell imaging-guided radiotherapy88. Although this approach resolves signal dilution and avoids false-positive interference, clinical translation faces several obstacles—genetic modification carries risks of insertional mutagenesis and immunogenicity, reporter expression may be inhibited by the inflammatory microenvironment, and genetic modification can alter intrinsic MSC biology89.
A more fundamental barrier is the risk–benefit calculus: in life-threatening diseases such as glioblastoma, the mortality benefit may justify genetic modification, but because KOA is chronic and non-life-threatening, even a small risk of insertional mutagenesis is difficult to justify90,91,92. Additional concerns include the immunogenicity of exogenous reporter proteins, such as NIS and HSV1-tk93,94,95. Alternative non-genetic strategies—improved chelator-based labeling with reduced efflux, nanoparticle-enhanced labeling, and metabolic labeling—offer more clinically accessible pathways, although they cannot match the viability specificity of reporter genes. Table 4 summarizes the key differences. In addition to the classical methods discussed above, a range of novel labeling strategies have emerged in recent years—including advanced chelators, targeted probes, and nanoparticle-enhanced approaches—each offering distinct improvements in labeling efficiency, targeting specificity, and translational potential (Table 5).
| Feature | Direct Labeling | Reporter Gene Imaging |
| Mechanism | Ex vivo incubation with a radiotracer; passive diffusion or endocytosis | Genetic modification to express a reporter enzyme or receptor |
| Viability specificity | No—signals may persist after cell death | Yes—only transcriptionally active cells produce a signal |
| Signal dilution | Yes—signal is diluted with cell division | No—reporter genes are passed to daughter cells |
| Tracking duration | Limited by tracer half-life (hours to days) | Potentially indefinite |
| Genetic modification | Not required | Required; associated with safety concerns |
| Immunogenicity risk | Low | Moderate to high because of viral vectors or foreign proteins |
| Regulatory pathway | Cell therapy product | Gene therapy product; more stringent regulatory requirements |
| Clinical translation | Feasible in the near term | Significant hurdles for non-life-threatening diseases |
| KOA applicability | Suitable for short-term IA retention studies | Limited by the risk–benefit calculus |
| Cost and complexity | Lower | Higher |
Table 4: Comparison of direct labeling and reporter gene imaging for mesenchymal stem cell tracking. Comparison of direct radionuclide labeling and reporter gene imaging with respect to labeling mechanism, viability specificity, signal dilution, tracking duration, genetic modification, immunogenicity, regulatory considerations, clinical translation, applicability to knee osteoarthritis, and cost and complexity. MSC, mesenchymal stem cell; KOA, knee osteoarthritis; IA, intra-articular.
| Approach | Key Advance | Application in KOA-MSC | Key Findings | Limitations |
| [89Zr]Zr-DFO-NCS labeling | Labeling efficiency up to 87.3% while maintaining MSC viability | Applicable to MSCs and HSCs for PET tracking | High labeling efficiency with preserved cell function | Higher lung uptake than the oxine formulation; higher effective radiation dose |
| [89Zr]Zr-oxine labeling | Continuous PET monitoring for up to 7 days | Tracking homing dynamics in inflamed joints | Clear visualization of spleen, bone marrow, and joint homing | High radioactivity (>0.5 Bq/cell) may induce DNA damage |
| NIS reporter gene + [18F]TFB | Viable cell-specific imaging; signal correlates with cell count | Monitoring MSC survival and proliferation | Only viable cells produce a signal; distinguishes living from dead cells | Requires genetic modification; potential immunogenicity; ethical barriers for non-life-threatening KOA |
| [68Ga]Ga-Pentixafor (CXCR4-targeted) | Targets an MSC homing receptor | Tracking CXCR4-expressing MSCs | Greater cell specificity than FDG in OA models | CXCR4 is also expressed on inflammatory cells; limited validation in KOA |
| [68Ga]Ga-FAPI | Detects fibroblast activation protein | Imaging synovial stromal activation | Identifies 6.1% more affected joints than FDG in RA; lower physiological uptake | EPR effect in inflamed synovium may cause nonspecific uptake |
| [99mTc]Tc-HMPAO labeling | Short half-life suited to IA injection | Assessing local retention versus leakage within 24–48 h | Simple and feasible for evaluating early homing dynamics | Significant tracer efflux at 24 h; unsuitable for long-term tracking |
| Nanoparticle-enhanced labeling | Improved cytocompatibility and labeling stability | Potential to reduce radiation damage to MSCs | Improved performance compared with conventional direct-labeling approaches | Remains in preclinical development |
Table 5: Novel advances in nuclear medicine approaches for mesenchymal stem cell labeling and tracking. Summary of emerging radionuclide labeling, reporter-gene, targeted-probe, and nanoparticle-enhanced strategies relevant to MSC tracking, including their principal technical advances, potential applications in knee osteoarthritis, key findings, and current limitations. DFO, desferrioxamine; NCS, isothiocyanate; MSC, mesenchymal stem cell; HSC, hematopoietic stem cell; PET, positron emission tomography; NIS, sodium iodide symporter; TFB, tetrafluoroborate; KOA, knee osteoarthritis; CXCR4, C-X-C chemokine receptor type 4; FDG, fluorodeoxyglucose; OA, osteoarthritis; FAPI, fibroblast activation protein inhibitor; RA, rheumatoid arthritis; EPR, enhanced permeability and retention; HMPAO, hexamethylpropyleneamine oxime; IA, intra-articular.
A critical synthesis of the labeling strategies reviewed above reveals three fundamental tensions that remain unresolved: (1) the stability–viability trade-off—89Zr-DFO labeling achieves high efficiency (>80%) but induces DNA damage at >0.5 Bq/cell, presenting an inherent paradox; (2) the preclinical–clinical accessibility gap for reporter genes; and (3) the standardization deficit across institutions, which requires coordinated multicenter efforts.
Specific Applications of PET and SPECT in KOA-MSC Therapy
Most evidence on PET/SPECT tracking of MSCs in KOA derives from preclinical small-animal studies, with few human trials. Preclinical scintigraphy/SPECT studies using [99mTc]Tc-HMPAO-labeled MSCs demonstrated the feasibility of assessing intra-articular retention, whereas PET-based human trials remain scarce owing to 89Zr logistics and regulatory hurdles96.
Monitoring Cell Distribution and Homing Efficiency:
Tracer selection must be guided by the administration route and clinical question. Wang et al. labeled human bone marrow-derived MSCs with [89Zr]Zr-oxine and conducted micro-PET/CT imaging to track their biodistribution97,98. For IA injection, local retention versus systemic leakage can be assessed within 24–48 h, favoring short-half-life tracers such as 99mTc (6.02 h) or 18F (110 min). In contrast, IV administration requires long-half-life tracers such as 89Zr (78.4 h) to track homing over days to weeks. IV-infused MSCs show temporal redistribution—predominantly pulmonary at 1 h, followed by hepatic and splenic redistribution by day 1099. Kath et al. showed that [89Zr]Zr-DFO-Bz-NCS labeling achieves an efficiency as high as 87.30%, indicating that an adequate cell dose is needed for high-efficiency IA labeling100. However, a unified standard for quantifying homing efficiency has not been established.
Assessment of Cell Survival and Proliferation:
The local inflammatory microenvironment in KOA exerts cytotoxic effects that can reduce MSC survival, contributing to variability in clinical efficacy. Reporter-gene imaging enables dynamic monitoring of MSC survival through serial imaging. In a glioblastoma model, Kitzberger et al. demonstrated that [18F]TFB PET/MRI distinguished viable from dead MSCs—but only when stimulated by high IL-6 expression did engineered MSCs specifically take up the tracer (SUV ≈ 1.9% ID/mL), with minimal background in non-target organs101. Compared with invasive biopsy, this approach allows repeated measurements and longitudinal observation; however, these findings derive from a glioblastoma model dependent on high IL-6 stimulation and remain preclinical, with human safety awaiting validation in large-scale trials.
Pharmacodynamics and Quantitative Evaluation of Therapeutic Efficacy:
[18F]FDG PET quantifies synovial glucose metabolism, with changes in SUV reflecting local inflammation; however, interpretation requires caution because activated macrophages exhibit ~3.5-fold higher glucose metabolism than parenchymal cells, and synovitis creates a persistent background signal that can overwhelm the MSC signal102,103. Supporting this, FDG SUV correlates with C-reactive protein (CRP) and patient global assessment, reflecting inflammation rather than MSC activity104. Consequently, [18F]FDG is best suited for assessing overall joint inflammatory status rather than specific MSC tracking. [99mTc]Tc-MDP SPECT, by contrast, assesses subchondral bone metabolism, providing a complementary dimension of bone turnover that FDG cannot capture105,106,107.
Next-generation cell-specific tracers offer greater molecular specificity. CXCR4-targeted [68Ga]Ga-Pentixafor targets a key receptor involved in MSC homing and outperforms [18F]FDG in detecting CXCR4-expressing MSCs in osteoarthritis models108.109. Separately, fibroblast activation protein inhibitor (FAPI) tracers (e.g., [68Ga]Ga-FAPI) detect stromal activation in inflammatory joint disease, with lower physiological uptake than FDG and the ability to identify affected joints before structural damage appears on conventional imaging110.
Standardized quantitative metrics are essential for cross-study comparisons: SUV (SUVmean/SUVmax), %ID/g, and cell-retention ratio. We propose: (a) reporting SUV with full normalization details and acquisition time; (b) using %ID/g for preclinical cross-species comparisons; (c) calculating the cell-retention ratio at consistent time points (1, 24, 48, and 7 days post-injection); (d) applying partial volume correction for thin cartilage/synovium; and (e) applying background correction using a reference region111. In summary, Table 6 presents the key application strategies of PET/SPECT in MSC therapy, with non-KOA studies retained as supporting evidence.
Distinct Considerations for MSC-Derived Extracellular Vesicle Tracing:
MSC-EVs present distinct tracing considerations: their smaller size (30–200 nm) requires different labeling strategies—direct surface labeling with chelators such as DFO has been applied to EVs with 50%–70% efficiency—and, because fewer radionuclide atoms can be incorporated per vesicle, the signal-to-noise ratio is reduced. Their biodistribution and clearance also differ from those of intact MSCs, factors that should be considered when designing EV-based imaging protocols112.
Current Challenges and Future Perspectives
Core Technical Bottlenecks and Challenges:
Several technical limitations remain. Ionizing radiation damages MSC DNA while increasing patient exposure, and the field lacks consensus on safe labeling parameters. For [99mTc]Tc-HMPAO, 10–30 MBq per 106 cells achieves an adequate signal without compromising proliferation or differentiation113,114,115,116,117. For [111In]In-oxine, labeling at ~5 µCi per 108 cells achieves 85%–95% efficiency with >95% post-labeling viability, whereas higher activities induce Auger-electron radiotoxicity118,119. Substantial efflux (retention ~46% by 20 h) and redistribution of free 111In to the liver, spleen, and bone further cause false-positive signals120. To minimize false-positive signals from free radionuclides released by dead cells, complementary approaches include tracers with rapid renal clearance, viability stains, dynamic imaging protocols, and ex vivo validation; however, standardized protocols across institutions remain lacking121.
A central limitation of direct labeling is the imperfect correlation between imaging signal and viable cell number, arising through three principal mechanisms: (1) tracer leakage via efflux pumps, with significant signal loss within 24 h; (2) signal dilution with cell division, as radionuclides do not participate in genetic replication; and (3) false-positive signals from free radionuclides released by dead or dying cells and taken up by surrounding tissues or macrophages122. In addition, the correspondence between imaging signals and anatomical structures requires multimodal imaging for improved spatial resolution. Collectively, radionuclide imaging should be interpreted as a measure of biodistribution and tracer pharmacokinetics rather than as a direct cell-viability assay.
Beyond these technical mechanisms, a further interpretive challenge arises from the biological reality that transplanted MSCs undergo rapid apoptosis followed by efferocytosis (macrophage-mediated clearance of apoptotic cells). Persistent signal detection should not be interpreted as evidence of prolonged cell survival, just as signal loss should not necessarily be interpreted as therapeutic failure—because MSC apoptosis and subsequent efferocytosis constitute a core component of the therapeutic mechanism described by the “dying stem cell hypothesis.” This “signal–viability dissociation” is exacerbated in the KOA joint, where impaired lymphatic clearance prolongs the retention of released tracers, and should be resolved through complementary viability-specific strategies such as reporter-gene imaging, dual-tracer approaches, or serial imaging calibrated to apoptosis kinetics123.
In addition to these general technical challenges, KOA presents several specific obstacles. First, the knee joint is a closed synovial compartment in which tracer clearance depends on synovial lymphatic function, which is impaired in KOA (t1/2, 0.5 h → 2.8 h), causing prolonged retention that may mimic cell survival124,125,126. Second, thin articular cartilage (<1 mm in advanced disease) falls far below the spatial resolution of PET (4–5 mm) and SPECT (7–12 mm), causing severe partial volume effects through bidirectional signal spillover127,128,129,130; emerging deep-learning partial volume correction is promising, but validation in musculoskeletal applications remains limited131,132,133. Third, increased synovial vascular permeability driven by VEGF and TGF-β accelerates tracer influx but elevates background signals through plasma protein extravasation, while degradation of synovial fluid HA reduces viscosity, creating heterogeneous tracer “pooling.” Collectively, SUV and tumor-to-background ratio (TBR) measured in the KOA joint cannot be interpreted using the same pharmacokinetic assumptions applied to other tissues.
Indirect labeling (reporter-gene) approaches are likewise constrained: the safety of genetic modification and transfection efficiency have not yet reached clinical standards. Internationally accepted standards and evaluation criteria, standardized detection protocols, and defined efficacy metrics are urgently needed to accelerate translation into clinical practice.
Practical Barriers to Clinical Translation:
Translation is hindered by regulatory, safety, and practical barriers. Radiopharmaceuticals and cell-therapy products fall under different regulatory categories (Food and Drug Administration [FDA] combination product/investigational new drug [IND] framework in the United States; advanced therapy medicinal product [ATMP] framework in the European Union), and reporter-gene imaging falls under gene therapy, with stricter requirements134,135. Radiation safety is a concern for a non-life-threatening condition: a single [99mTc]Tc-HMPAO SPECT/CT scan (~3–5 mSv) is acceptable, but cumulative exposure from repeated scans raises concerns. Good manufacturing practice (GMP)-compliant cell labeling adds substantial cost and complexity.
A further barrier is the preclinical-to-clinical resolution gap: clinical PET (4–5 mm) and SPECT (7–12 mm) have 3- to 5-fold lower spatial resolution than preclinical micro-PET (1–2 mm), so signals detectable in rodent joints may fall below the detection threshold in human knees136. Consequently, negative imaging findings in human studies should not be automatically interpreted as failed MSC homing—they may instead reflect technical limitations. Total-body PET may partially bridge this gap, but the fundamental resolution mismatch remains unresolved.
As illustrated in the clinical translation roadmap (Figure 4), overcoming these barriers requires a stage-by-stage strategy, from robust cell labeling and preclinical validation to standardized trials and regulatory approval. Critically, the roadmap highlights that the resolution gap and standardization deficits can be addressed through multimodal fusion (PET/MRI), AI-assisted analysis, and multidisciplinary collaboration, offering a pragmatic framework for navigating the regulatory, safety, and technical hurdles discussed above.
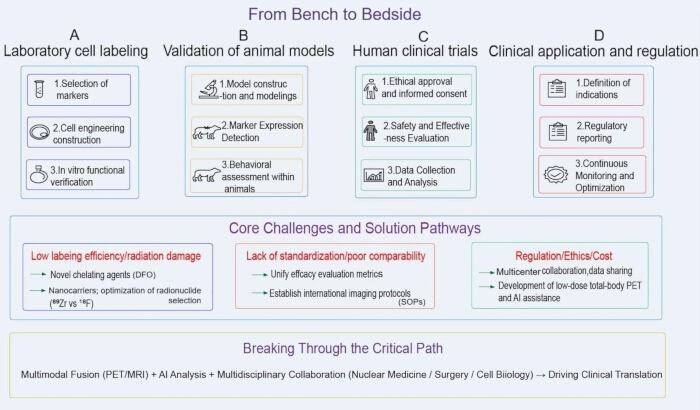
Figure 4: Clinical translation roadmap for mesenchymal stem cell tracking from bench to bedside. The roadmap illustrates four sequential stages in the clinical translation of MSC tracking technologies: (A) laboratory cell labeling, including marker selection, cell engineering, and in vitro functional verification; (B) validation in animal models, including model construction and modeling, marker-expression detection, and behavioral assessment; (C) human clinical trials, including ethical approval and informed consent, safety and effectiveness evaluation, and data collection and analysis; and (D) clinical application and regulation, including definition of indications, regulatory reporting, and continuous monitoring and optimization. Major challenges include low labeling efficiency and radiation damage, lack of standardization and poor comparability, and regulatory, ethical, and cost barriers. Potential solution pathways include novel chelating agents, nanocarrier-based approaches, optimization of radionuclide selection, unified efficacy metrics, standardized imaging protocols, multicenter collaboration and data sharing, low-dose total-body PET, and AI-assisted analysis. Multimodal imaging, including PET/MRI, together with AI-assisted analysis and multidisciplinary collaboration among nuclear medicine, surgery, and cell biology, provides a potential pathway for advancing clinical translation.Please click here to view a larger version of this figure.
Future Directions:
Progress should focus on technical optimization, standardization, and cross-disciplinary integration. Multimodal imaging (PET/MRI, SPECT/CT) combines molecular and anatomical information, compensating for single-modality resolution limits137,138. AI-based deep learning can optimize segmentation, quantification, and personalized prediction; however, challenges remain, including the need for large annotated datasets, the risk of overfitting, “black box” interpretability, and the lack of standardized evaluation metrics6,139,140. Total-body PET—extending the axial field of view to ~194 cm with ~40-fold higher sensitivity—enables whole-body dynamic monitoring and may help bridge the resolution gap, albeit with limited availability and high cost141.
| Cell Source | Tracer/Labeling Method | Imaging Modality | Study Type | Model Type | Key Findings | Limitations | ||||
| hBM-MSCs | [89Zr]Zr-oxine | micro-PET/CT | Preclinical (SD rats) | Healthy rat model | Labeling efficiency, 52.6 ± 0.01%; retention, 66.7 ± 0.9% at 7 days; IV administration showed predominant accumulation in the liver (7.35% ± 1.41% ID/g) and spleen (8.48 ± 1.20% ID/g) at day 10 | Signal does not distinguish viable from dead cells; the 78.4-h half-life of 89Zr enables a tracking window of approximately 7–10 days | ||||
| Human MSCs | [89Zr]Zr-oxine | PET | Preclinical | SLE mouse model | Systemic distribution of MSCs was successfully tracked in an SLE mouse model. After clearance from the lungs, the cells homed to and accumulated in the damaged kidneys and spleen, providing direct in vivo evidence of MSC distribution in SLE | The potential effects of 89Zr labeling on the long-term function and therapeutic efficacy of MSCs were not evaluated; the study was limited to an animal model; clinical translation requires consideration of radiation dose; PET resolution is insufficient for cell-level observation | ||||
| UC-MSCs | NIS reporter gene + [18F]TFB | PET/MRI | Preclinical | Glioblastoma model | Only viable cells produced a signal; SUVmax was ~1.9% ID/mL; signal intensity correlated linearly with viable cell count (R2 > 0.95) | Genetic modification is required; potential immunogenicity; ethical barriers for non-life-threatening KOA; preclinical evidence only | ||||
| hMSCs | [99mTc]Tc-HMPAO | Scintigraphy/SPECT | Preclinical | Healthy (non-KOA) rabbit model | IA administration showed activity predominantly within the injected cavity, with complete absence of pulmonary uptake; IV administration showed that the bulk of radioactivity was trapped in the lung parenchyma | Significant tracer efflux at 24 h; limited to short-term tracking; unsuitable for long-term homing assessment | ||||
| hUC-MSCs | [89Zr]Zr-oxine ([89Zr]Zr-MSCs) / luciferase gene transduction (Luc-MSCs) | PET/CT | Preclinical | Healthy (non-KOA) NCG mouse model | Biodistribution and persistence followed the general pattern lung > liver > kidney > spleen, with discrepancies noted for the liver and kidney. Real-time tracking of [89Zr]Zr-MSCs lasted 14 days, whereas tracking of Luc-MSCs lasted 7 days | 89Zr-PET/CT was affected by 89Zr shedding and signals associated with dead cells | ||||
| hUC-MSC-EVs | [89Zr]Zr-DFO | PET | Preclinical | Tumor-bearing mouse model | Labeling efficiency was 85.89%; EV tumor-targeting ability was preserved, enabling noninvasive tumor visualization | EV size (30–200 nm) limits the radionuclide payload per vesicle; biodistribution differs from that of parent MSCs | ||||
Table 6: Summary of PET/SPECT applications in KOA-MSC therapy and supporting evidence from non-KOA models. Summary of representative preclinical studies using radionuclide imaging and reporter-gene approaches to track MSCs or MSC-derived extracellular vesicles. Because direct KOA-specific evidence remains limited, studies conducted in healthy animals and non-KOA disease models are included as supporting evidence and are identified in the Model Type column. PET, positron emission tomography; SPECT, single-photon emission computed tomography; KOA, knee osteoarthritis; MSC, mesenchymal stem cell; hBM-MSC, human bone marrow-derived mesenchymal stem cell; SD, Sprague-Dawley; CT, computed tomography; IV, intravenous; ID/g, injected dose per gram; SLE, systemic lupus erythematosus; UC-MSC, umbilical cord-derived mesenchymal stem cell; NIS, sodium iodide symporter; TFB, tetrafluoroborate; MRI, magnetic resonance imaging; SUVmax, maximum standardized uptake value; IA, intra-articular; HMPAO, hexamethylpropyleneamine oxime; hMSC, human mesenchymal stem cell; hUC-MSC, human umbilical cord-derived mesenchymal stem cell; NCG, NOD-Prkdcem26Cd52 Il2rgem26Cd22/NjuCrl; Luc-MSC, luciferase-expressing mesenchymal stem cell; EV, extracellular vesicle; DFO, desferrioxamine.
| Feature | Conventional PET | Total-Body PET |
| Average total-body scan time | 10–30 min | 30 s–3 min |
| Sensitivity | Moderate | Ultra-high, with up to 40-fold higher sensitivity for whole-body imaging |
| Large axial field of view (LAFOV) | 15–20 cm | >100 cm |
| Dynamic imaging potential (continuous capture of data over time) | Tracers can be followed for ~3 half-lives, limiting dynamic imaging | Tracers can be followed for 5–6 additional half-lives, enabling whole-body, real-time imaging |
| Average administered radioactivity for a full-body scan | ~370 MBq | ~9.25 MBq |
| Patient throughput | Lower | Potential for approximately twice as many clinical scans per day |
Table 7: Key performance distinctions between conventional and total-body PET imaging systems. Comparison of conventional and total-body PET systems with respect to scan duration, sensitivity, axial field of view, dynamic imaging capability, administered radioactivity, and potential patient throughput. PET, positron emission tomography; LAFOV, large axial field of view; MBq, megabecquerel.
מסקנות
PET and SPECT, as noninvasive, quantitative, and highly sensitive molecular imaging techniques, provide important support for understanding the in vivo fate of cells in KOA-MSC therapy and for improving therapeutic efficacy monitoring. They play important roles in assessing cell distribution and homing, providing indirect information on cell persistence, and evaluating treatment-associated changes. PET and SPECT provide complementary capabilities for MSC tracking and treatment evaluation, with PET offering higher sensitivity and SPECT offering greater accessibility and broader radionuclide availability. They can be flexibly applied to quantitative cell tracking, biodistribution studies, and early clinical exploration, depending on the available equipment. The two technologies complement each other across different applications. They not only help elucidate the molecular mechanisms of MSC therapy for KOA but also support the transition toward precision medicine. However, challenges such as radiation exposure, a lack of clinical standardization, and ethical and regulatory concerns remain. Additionally, most studies are still in the preclinical phase, and clinical efficacy and safety require validation through large-scale studies. With advances in multimodal imaging, artificial intelligence, novel tracer technologies, and the standardization of clinical protocols, PET and SPECT have the potential to become valuable tools for the clinical translation of KOA-MSC therapy and to further support the development of precision diagnosis and treatment in knee joint regeneration.
גילויים
The authors declare no competing financial interests.
תודות
This work was supported by the National Natural Science Foundation of China (22077061 and 81701738) and the Construction Project of Shanghai Key Laboratory of Molecular Imaging (18DZ2260400).
מקורות
- Cui A, et al. Global, regional prevalence, incidence and risk factors of knee osteoarthritis in population-based studies. EClinicalMedicine. 2020;29-30:100587.
- Ding Y, Liu X, Chen C, Yin C, Sun X. Global, regional, and national trends in osteoarthritis disability-adjusted life years (DALYs) from 1990 to 2019: A comprehensive analysis of the Global Burden of Disease Study. Public Health. 2024;226:261-72.
- Foster NE, Eriksson L, Deveza L, Hall M. Osteoarthritis year in review 2022: Epidemiology & therapy. Osteoarthritis Cartilage. 2023;31(7):876-83.
- Wang J, Xue H, Shi M, Chen R. Mesenchymal stem cell-based therapy for osteoarthritis: A systematic review and meta-analysis of clinical outcomes and functional recovery. Front Cell Dev Biol. 2025;13:1746471.
- Fares MY, et al. Mesenchymal stem cell injections for the treatment of osteoarthritis: A systematic review of clinical trials. Acta Orthop Belg. 2024;90(2):319-33.
- Tabet CG, et al. Advanced therapy with mesenchymal stromal cells for knee osteoarthritis: Systematic review and meta-analysis of randomized controlled trials. J Orthop Transl. 2024;48:176-89.
- Saito Y, et al. In vivo tracking transplanted cardiomyocytes derived from human induced pluripotent stem cells using nuclear medicine imaging. Front Cardiovasc Med. 2023;10:1261330.
- Xu L, Shi J, Wu S. Positron emission tomography probes for stem cell monitoring: A review. Am J Transl Res. 2024;16(8):3534-44.
- Cen P, et al. Bridging the gap to clinical translation: The advanced role of PET molecular imaging in stem cell therapy. Eur J Nucl Med Mol Imaging. 2026;53(8):4803-6.
- Wang J, et al. Future direction: Molecular imaging-based stem cell research. Eur J Nucl Med Mol Imaging. 2025;52(5):1614-7.
- Ji X, et al. Impact of mesenchymal stem cell size and adhesion modulation on in vivo distribution: Insights from quantitative PET imaging. Stem Cell Res Ther. 2024;15(1):456.
- Guzmán-Sastoque P, et al. Nanotheranostics revolutionizing gene therapy: Emerging applications in gene delivery enhancement. J Nanotheranostics. 2025;6(2).
- Kahts M, et al. A proof-of-concept study to investigate the radiolabelling of human mesenchymal and hematopoietic stem cells with [89Zr]Zr-DFO-Bz-NCS. EJNMMI Radiopharm Chem. 2024;9(1):82.
- Gao T, et al. Reporter genes for brain imaging using MRI, SPECT and PET. Int J Mol Sci. 2022;23(15).
- Meng X, et al. The role of total-body PET in drug development and evaluation: Status and outlook. J Nucl Med. 2024;65(Suppl 1):46S-53S.
- Zoghi S, et al. Role of total-body PET/CT in inflammatory disorders. Semin Nucl Med. 2025;55(1):41-51.
- Xue HY, et al. Research progress on mesenchymal stem cell-derived exosomes in the treatment of osteoporosis induced by knee osteoarthritis (review). Int J Mol Med. 2025;56(4):1-32.
- He C, et al. Pain phenotype in knee osteoarthritis: Implications for mechanism-based therapy. Orthop Surg. 2025;17(11):3007-21.
- Mallia I, Fioravanti A, Guiducci S. Infrapatellar fat pad in knee osteoarthritis: A comprehensive review of pathophysiology and targeted therapeutic strategies. Int J Mol Sci. 2025;26(21):10408.
- Mathiessen A, Conaghan PG. Synovitis in osteoarthritis: Current understanding with therapeutic implications. Arthritis Res Ther. 2017;19(1).
- Zou Z, et al. The potential role of synovial cells in the progression and treatment of osteoarthritis. Exploration. 2023;3(5).
- Han D, et al. The emerging role of fibroblast-like synoviocyte-mediated synovitis in osteoarthritis: An update. J Cell Mol Med. 2020;24(17):9518-32.
- Raikov B, et al. Methods for determining the molecular composition of knee joint structures in osteoarthritis: Collagen, proteoglycans and water content: A systematic review. Collagen Leather. 2024;6(1).
- Lin X, et al. Targeting synovial lymphatic function as a novel therapeutic intervention for age-related osteoarthritis in mice. Arthritis Rheumatol. 2023;75(6):923-36.
- Waszczykowski M, Fabiś-Strobin A, Bednarski I, Narbutt J, Fabiś J. Serum and synovial fluid concentrations of interleukin-18 and interleukin-20 in patients with osteoarthritis of the knee and their correlation with other markers of inflammation and turnover of joint cartilage. Arch Med Sci. 2020. doi:10.5114/aoms.2020.96717.
- Lee K, Niku S, Koo SJ, Belezzuoli E, Guma M. Molecular imaging for evaluation of synovitis associated with osteoarthritis: A narrative review. Arthritis Res Ther. 2024;26(1):25.
- Mukherjee A, Das B. The role of inflammatory mediators and matrix metalloproteinases (MMPs) in the progression of osteoarthritis. Biomater Biosyst. 2024;13.
- Azimi MS, et al. Critical review of partial volume correction methods in PET and SPECT imaging: Benefits, pitfalls, challenges, and future outlook. Eur J Nucl Med Mol Imaging. 2026;53(4):2830-61.
- Kaspiris A, et al. Subchondral bone cyst development in osteoarthritis: From pathophysiology to bone microarchitecture changes and clinical implementations. J Clin Med. 2023;12(3).
- Zhang H, et al. Roles of microenvironment on mesenchymal stem cell therapy for osteoarthritis. J Inflamm Res. 2024;17:7069-79.
- Fan M, et al. Detrimental alteration of mesenchymal stem cells by an articular inflammatory microenvironment results in deterioration of osteoarthritis. BMC Med. 2023;21(1):215.
- Wu KC, Chang YH, Ding DC, Lin SZ. Mesenchymal stromal cells for aging cartilage regeneration: A review. Int J Mol Sci. 2024;25(23):12911.
- Li Y, et al. Mesenchymal stem cells and extracellular vesicles for knee osteoarthritis: Clinical application, mechanism exploration and prospect. Stem Cell Res Ther. 2025;16(1):688.
- Rahmadian R, Adly M, Dilogo IH, Revilla G, Ariliusra Z. Single intra-articular injection of human synovial membrane MSC from grade IV knee osteoarthritis patient improves cartilage repair in an OA rat model. J Orthop Surg Res. 2024;19(1):710.
- Yang XH, Chen SY, Zhou QF, Cai YZ. Exosomes in osteoarthritis: Breakthrough innovations and advanced tissue engineering for cartilage regeneration since 2020. Biomedicines. 2025;13(10):2486.
- Welsh JA, et al. Minimal information for studies of extracellular vesicles (MISEV2023): From basic to advanced approaches. J Extracell Vesicles. 2024;13(2).
- Meng Z, et al. Mapping the knowledge landscape of and emerging future trends in stem cell therapy for osteoarthritis: A bibliometric analysis of the literature from 1998 to 2024. J Multidiscip Healthc. 2025;18:1281-95.
- Kitzberger C, et al. The sodium iodide symporter (NIS) as theranostic gene: Its emerging role in new imaging modalities and non-viral gene therapy. EJNMMI Res. 2022;12(1):25.
- Svajger U, Kolar M, Kobold A, Drobnic M. Mechanisms of treatment effects using allogeneic, umbilical cord-derived mesenchymal stromal stem cells (MSCs) in knee osteoarthritis: A pharmacological clinical study protocol. Trials. 2024;25(1):533.
- Yuan S, et al. Mesenchymal stromal cell-derived extracellular vesicles as potential treatments for osteoarthritis. Pharmaceutics. 2023;15(7).
- Najar M, Martel-Pelletier J, Pelletier JP, Fahmi H. Mesenchymal stromal cell immunology for efficient and safe treatment of osteoarthritis. Front Cell Dev Biol. 2020;8.
- Dreyer GJ, et al. Cell-free DNA measurement of three genomes after allogeneic MSC therapy in kidney transplant recipients indicates early cell death of infused MSCs. Front Immunol. 2023;14.
- Preda MB, et al. Short lifespan of syngeneic transplanted MSCs is a consequence of in vivo apoptosis and immune cell recruitment in mice. Cell Death Dis. 2021;12(6).
- Payne NL, et al. Proinflammatory cytokines sensitise mesenchymal stromal cells to apoptosis. Cell Death Discov. 2025;11(1).
- Blinova GA, Yarygin KN, Kholodenko IV. Efferocytosis as one of the mechanisms for realizing the therapeutic effects of mesenchymal stem cells. Biomed Chem Res Methods. 2024;7(3).
- Schrodt MV, et al. Efferocytosis of viable versus heat-inactivated MSCs induces human monocytes to distinct immunosuppressive phenotypes. Stem Cell Res Ther. 2023;14(1).
- Dortaj H, Azarpira N, Tayebi L. Non-invasive imaging modalities for stem cell tracking in osteoarthritis. Regen Eng Transl Med. 2024;10:9-18.
- Hayashi D, Roemer FW, Guermazi A. Osteoarthritis year in review 2024: Imaging. Osteoarthritis Cartilage. 2025;33(1):88-93.
- Li Q, et al. Optical imaging of in vivo adoptive T-cell therapy: State of the art and challenges. iRADIOLOGY. 2023;1(3):225-35.
- Muhammad S, et al. Advances in the engineering of living probiotics for cancer immunotherapy. Theranostics. 2026;16(3):1164-226.
- Harvell-Smith S, Tung LD, Thanh NTK. Magnetic particle imaging: Tracer development and the biomedical applications of a radiation-free, sensitive, and quantitative imaging modality. Nanoscale. 2022;14(10):3658-97.
- Ngwu-Hyacinth O, et al. Ultrasmall superparamagnetic iron oxide nanoparticles as positive contrast agents in low-field magnetic resonance imaging. iRADIOLOGY. 2025;3(5):372-87.
- Exner AA, Kolios MC. Bursting microbubbles: How nanobubble contrast agents can enable the future of medical ultrasound molecular imaging and image-guided therapy. Curr Opin Colloid Interface Sci. 2021;54.
- Vo Chieu VD, et al. Juvenile idiopathic arthritis of the knee: Is contrast needed to score disease activity when using an augmented MRI protocol comprising PD-weighted sequences? Eur Radiol. 2022;33(5):3775-84.
- Boekestijn I, et al. The current status and future prospects for molecular imaging-guided precision surgery. Cancer Imaging. 2022;22(1).
- Morath V, et al. PET-based tracking of CAR T cells and viral gene transfer using a cell surface reporter that binds to lanthanide complexes. Nat Biomed Eng. 2025;9(11):1886-906.
- Aide N, et al. EANM/EARL harmonization strategies in PET quantification: From daily practice to multicentre oncological studies. Eur J Nucl Med Mol Imaging. 2017;44(Suppl 1):17-31.
- Capilla-González V, Herranz-Pérez V, Sarabia-Estrada R, Kadri N, Moll G. Editorial: Mesenchymal stromal cell therapy for regenerative medicine. Front Cell Neurosci. 2022;16.
- Li H, Bai L. Advances in mesenchymal stem cell- and exosome-based therapies for aging and age-related diseases. Stem Cell Res Ther. 2025;16(1).
- Gonzalez-Montoro A, Ullah MN, Levin CS. Advances in detector instrumentation for PET. J Nucl Med. 2022;63(8):1138-44.
- Bruzgo-Grzybko M, et al. Preclinical PET and SPECT imaging in small animals: Technologies, challenges and translational impact. Cells. 2025;15(1):73.
- Hicks RJ, Ware RE, Callahan J. Total-body PET/CT: Pros and cons. Semin Nucl Med. 2025;55(1):11-20.
- Shalaby N. In vivo multi-modal imaging approaches for cancer, stem and immune cells. 2023.
- Marquardt N, Wirth B, Schäfers K. Motion simulation of radiolabeled cells in whole-body positron emission tomography. IEEE Trans Med Imaging. 2026;45(3):919-30.
- Menendez Montes MI, Pham CTN, Liu Y, Guilak F. Advances in molecular imaging for osteoarthritis. Connect Tissue Res. 2025;66(5):407-13.
- Garg P, et al. Molecular PET imaging: Unlocking the secrets of cancer metabolism. Biochem Pharmacol. 2025;242(Pt 3):117202.
- Nguyen BJ, et al. The prognostic and diagnostic value of 18F-FDG PET/CT for assessment of symptomatic osteoarthritis. Nucl Med Commun. 2018;39(7):699-706.
- Tavakoli S. Promises and challenges of metabolic imaging: Where does 18F-FDG stand in the immunometabolism era? J Nucl Med. 2020;61(Suppl 2):130S-1S.
- Ding L, et al. Construction of [89Zr]Zr-labeled human umbilical cord mesenchymal stem cell-derived extracellular vesicles for noninvasive detection of tumors. ACS Appl Mater Interfaces. 2025;17(21):30589-99.
- Wuensche TE, Lyashchenko S, Van Dongen G, Vugts D. Good practices for 89Zr radiopharmaceutical production and quality control. EJNMMI Radiopharm Chem. 2024;9(1):40.
- Shalaby N, et al. Complementary early-phase magnetic particle imaging and late-phase positron emission tomography reporter imaging of mesenchymal stem cells in vivo. Nanoscale. 2023;15(7):3408-18.
- Huang W, et al. Advances in immunoPET/SPECT imaging: The role of Fab and F(ab′)2 fragments in theranostics. Acta Pharm Sin B. 2025;15(8):3888-924.
- Astrelina TA, et al. Biodistribution of mesenchymal stromal cells labeled with [89Zr]Zr-oxine in local radiation injuries in laboratory animals. Molecules. 2023;28(20):7169.
- Breun M, et al. [68Ga]Ga-Pentixafor PET/CT for CXCR4-mediated imaging of vestibular schwannomas. Front Oncol. 2019;9:503.
- Xu S, et al. Recent advances in radionuclide medical imaging techniques. Front Med (Lausanne). 2025;12:1662020.
- Sharma S, Pandey MK. Radiometals in imaging and therapy: Highlighting two decades of research. Pharmaceuticals (Basel). 2023;16(10).
- Kamiyama Y, et al. Biodistribution studies for cell therapy products: Current status and issues. Regen Ther. 2021;18:202-16.
- Chung YH, et al. In vivo SPECT imaging of 99mTc-radiolabeled exosomes from human umbilical cord-derived mesenchymal stem cells in small animals. Biomed J. 2024;47(5):100721.
- Fatima H, et al. Advances in extracellular vesicle research: Tools and techniques. Nanoscale Horiz. 2026. doi:10.1039/D5NH00734H.
- He J, Zhong YP, Zhang S. Technetium-99m-methylene diphosphonate single-photon emission computed tomography/computed tomography combined with prostate-specific antigen/free prostate-specific antigen ratio for bone metastasis of prostate cancer. World J Clin Cases. 2024;12(20):4082-90.
- Cai Z, Lin X, Zhuang Y, Miao W, Xie Y. Augmentation of bone formation by sympathectomy in rats as evaluated by [99mTc]Tc-MDP. Front Endocrinol (Lausanne). 2025;16:1580230.
- Fuchigami T, et al. Development of 111In-labeled monoclonal antibodies targeting SFTSV structural proteins for molecular imaging of SFTS infectious diseases by SPECT. Molecules. 2024;30(1).
- Miederer M, et al. Alpha-emitting radionuclides: Current status and future perspectives. Pharmaceuticals (Basel). 2024;17(1).
- Salgueiro MJ, Moretton MA, Medina V, Chiappetta D, Zubillaga M. Pharmacoscintigraphy: Advancing nanotheranostic development through radionuclide imaging. J Nanotheranostics. 2025;6(2).
- Machulkin AE, et al. Synthesis and preclinical evaluation of urea-based prostate-specific membrane antigen-targeted conjugates labeled with 177Lu. ACS Pharmacol Transl Sci. 2024;7(5):1457-73.
- Gawne PJ, Man F, Blower PJ, de Rosales RTM. Direct cell radiolabeling for in vivo cell tracking with PET and SPECT imaging. Chem Rev. 2022;122(11):10266-318.
- Andrzejewska A, Dabrowska S, Lukomska B, Janowski M. Mesenchymal stem cells for neurological disorders. Adv Sci (Weinh). 2021;8(7):2002944.
- Shah S, Lucke-Wold B. Image-guided mesenchymal stem cell sodium iodide symporter (NIS) radionuclide therapy for glioblastoma. Cancers (Basel). 2024;16(16).
- Kitzberger C, et al. Interleukin-6-controlled, mesenchymal stem cell-based sodium/iodide symporter gene therapy improves survival of glioblastoma-bearing mice. Mol Ther Oncolytics. 2023;30:238-53.
- Golikova EA, Alshevskaya AA, Alrhmoun S, Sivitskaya NA, Sennikov SV. TCR-T cell therapy: Current development approaches, preclinical evaluation, and perspectives on regulatory challenges. J Transl Med. 2024;22(1).
- Elsallab M, Gillner S, Bourgeois FT. Comparison of clinical evidence submitted to the FDA and EMA for cell and gene therapies. JAMA Intern Med. 2025;185(4):468-71.
- Salazar-Fontana LI. A regulatory risk-based approach to ATMP/CGT development: Integrating scientific challenges with current regulatory expectations. Front Med (Lausanne). 2022;9.
- Shalaby N, Dubois VP, Ronald J. Molecular imaging of cellular immunotherapies in experimental and therapeutic settings. Cancer Immunol Immunother. 2021;71(6):1281-94.
- Kiraga Ł, et al. Nuclear imaging for immune cell tracking in vivo: Comparison of various cell labeling methods and their application. Coord Chem Rev. 2021;445.
- Kim J, Park J, Song SY, Kim E. Advanced therapy medicinal products for autologous chondrocytes and comparison of regulatory systems in target countries. Regen Ther. 2022;20:126-37.
- Yubo M, et al. Clinical efficacy and safety of mesenchymal stem cell transplantation for osteoarthritis treatment: A meta-analysis. PLoS One. 2017;12(4):e0175449.
- Tian X, Qu Z, Cao Y, Zhang B. Relative efficacy and safety of mesenchymal stem cells for osteoarthritis: A systematic review and meta-analysis of randomized controlled trials. Front Endocrinol (Lausanne). 2024;15:1366297.
- Deng L, et al. Efficacy and safety of single versus repeated injections of mesenchymal stem cells for the treatment of knee osteoarthritis: A systematic review and network meta-analysis of randomized controlled trials. Stem Cell Res Ther. 2025;16(1):505.
- Wang S, et al. Biodistribution of 89Zr-oxine-labeled human bone marrow-derived mesenchymal stem cells by micro-PET/computed tomography imaging in Sprague-Dawley rats. Nucl Med Commun. 2022;43(7):834-46.
- Kim KI, Lee WS, Kim JH, Bae JK, Jin W. Safety and efficacy of the intra-articular injection of mesenchymal stem cells for the treatment of osteoarthritic knee: A 5-year follow-up study. Stem Cells Transl Med. 2022;11(6):586-96.
- Kim YS, Suh DS, Tak DH, Chung PK, Koh YG. Mesenchymal stem cell implantation in knee osteoarthritis: Midterm outcomes and survival analysis in 467 patients. Orthop J Sports Med. 2020;8(12):2325967120969189.
- Friberger I, et al. Comparative in vivo biodistribution of cells labelled with [89Zr]Zr-(oxinate)4 or [89Zr]Zr-DFO-NCS using PET. EJNMMI Res. 2023;13(1):73.
- Thoenen J, Mackay JW, Sandford HJC, Gold GE, Kogan F. Imaging of synovial inflammation in osteoarthritis, from the AJR special series on inflammation. AJR Am J Roentgenol. 2022;218(3):405-17.
- Reddy N, et al. 18F-FDG and 18F-NaF PET/CT global assessment of large joint inflammation and bone turnover in rheumatoid arthritis. Diagnostics (Basel). 2023;13(13).
- Abdelhafez Y, et al. Total-body 18F-FDG PET/CT in autoimmune inflammatory arthritis at ultra-low dose: Initial observations. J Nucl Med. 2022;63(10):1579-85.
- Yang M, Tan Q, Tang Z. Bones on fire: Illuminating osteomyelitis through the radiant lens of 18F-FDG PET/CT. Front Immunol. 2024;15:1378409.
- Duan Y, et al. The feasibility of quantitative assessment of dynamic 18F-fluorodeoxyglucose PET in Takayasu's arteritis: A pilot study. Eur J Nucl Med Mol Imaging. 2023;51(1):81-92.
- Kraus S, et al. 68Ga-Pentixafor PET/CT for detection of chemokine receptor CXCR4 expression in myeloproliferative neoplasms. J Nucl Med. 2022;63(1):96-9.
- Moul JW, et al. Application of next-generation imaging in biochemically recurrent prostate cancer. Prostate Cancer Prostatic Dis. 2023;27(2):202-11.
- Schmidkonz C, Kuwert T, Götz TI, Ramming A, Atzinger A. Recent advances in nuclear medicine and their role in inflammatory arthritis: Focus on the emerging role of FAPI PET/CT. Skeletal Radiol. 2024;54(11):2243-52.
- Swiha M, et al. Development of a visually calculated SUVmean (HIT score) on screening PSMA PET/CT to predict treatment response to 177Lu-PSMA therapy: Comparison with quantitative SUVmean and patient outcomes. J Nucl Med. 2024;65(6):904-8.
- Kattner AA. Communicating across distances: Biological functions of extracellular vesicles. Biomed J. 2024;47(5).
- Kim KI, et al. Clinical efficacy and safety of the intra-articular injection of autologous adipose-derived mesenchymal stem cells for knee osteoarthritis: A phase III, randomized, double-blind, placebo-controlled trial. Am J Sports Med. 2023;51(9):2243-53.
- Park SB, et al. The usefulness of quantitative 99mTc-HMPAO WBC SPECT/CT for predicting lower extremity amputation in diabetic foot infection. Sci Rep. 2024;14(1).
- Woods JJ, et al. Synthesis and evaluation of a bifunctional chelator for thorium-227-targeted radiotherapy. J Med Chem. 2025;68(2):1682-92.
- Cassells I, et al. Radiolabeling of human serum albumin with terbium-161 using mild conditions and evaluation of in vivo stability. Front Med (Lausanne). 2021;8.
- Kurebayashi Y, Choyke PL, Sato N. Imaging of cell-based therapy using 89Zr-oxine ex vivo cell labeling for positron emission tomography. Nanotheranostics. 2021;5(1):27-35.
- Gustavsson T, Herth MM, Sehlin D, Syvänen S. Indium-111 radiolabelling of a brain-penetrant Aβ antibody for SPECT imaging. Ups J Med Sci. 2024;129.
- Nyong E, Kurebayashi Y, Asiedu KO, Choyke PL, Sato N. Intracellular protein binding of Zr-89 oxine cell labeling for PET cell tracking studies. Pharmaceutics. 2025;17(4):518.
- Pruller J, et al. An indium-111-labelled membrane-targeted peptide for cell tracking with radionuclide imaging. RSC Chem Biol. 2023;4(1):65-73.
- Roger LM, et al. Evaluation of fluorescence-based viability stains in cells dissociated from scleractinian coral Pocillopora damicornis. Sci Rep. 2022;12(1).
- Yu G, et al. Recent advancements in biomaterials for chimeric antigen receptor T-cell immunotherapy. Biomater Res. 2024;28:0045.
- Cheung TS, Galleu A, Von Bonin M, Bornhäuser M, Dazzi F. Apoptotic mesenchymal stromal cells induce prostaglandin E2 in monocytes: Implications for the monitoring of mesenchymal stromal cell activity. Haematologica. 2019;104(10):e438-41.
- Marquis H, Willowson KP, Bailey DL. Partial volume effect in SPECT and PET imaging and impact on radionuclide dosimetry estimates. Asia Ocean J Nucl Med Biol. 2023;11(1):44-54.
- Petersen ET, et al. Patients with knee osteoarthritis can be divided into subgroups based on tibiofemoral joint kinematics of gait: An exploratory and dynamic radiostereometric study. Osteoarthritis Cartilage. 2022;30(2):249-59.
- Binvignat M, et al. Use of machine learning in osteoarthritis research: A systematic literature review. RMD Open. 2022;8(1):e001998.
- Lammi MJ, Qu C. Regulation of oxygen tension as a strategy to control chondrocytic phenotype for cartilage tissue engineering and regeneration. Bioengineering (Basel). 2024;11(3).
- Otani T, et al. Performance evaluation of a clinical SPECT system with multifocal collimator for brain studies. Med Phys. 2026;53(5):e70451.
- Jebur AS. Applications of nuclear physics in medical diagnostics: A comparative study between SPECT and PET. Academia Open. 2025;11(1):10.21070/acopen.21011.22026.13138.
- Hayashi E, Hibino S, Mase M. Validity of a simple spillover correction for positron emission tomography measurements in the cerebrospinal fluid region. Radiol Phys Technol. 2025;18(4):1321-9.
- Sanaat A, et al. A cycle-consistent adversarial network for brain PET partial volume correction without prior anatomical information. Eur J Nucl Med Mol Imaging. 2023;50(7):1881-96.
- Chen W, et al. Artificial intelligence-powered advancements in upper extremity joint MRI: A review. Heliyon. 2024;10(7).
- Kafkaletos A, et al. The significance of partial volume effect on the estimation of hypoxic tumour volume with [18F]FMISO PET/CT. EJNMMI Phys. 2024;11(1):43.
- Lechermann LM, Lau D, Attili B, Aloj L, Gallagher FA. In vivo cell tracking using PET: Opportunities and challenges for clinical translation in oncology. Cancers (Basel). 2021;13(16).
- Viswanathan S, et al. An International Society for Cell and Gene Therapy mesenchymal stromal cells (MSC) committee perspective on International Standards Organization/Technical Committee 276 biobanking standards for bone marrow MSCs and umbilical cord tissue-derived MSCs for research purposes. Cytotherapy. 2023;25(8):803-7.
- Yu S, Yu S, Liu H, Liao N, Liu X. Enhancing mesenchymal stem cell survival and homing capability to improve cell engraftment efficacy for liver diseases. Stem Cell Res Ther. 2023;14(1):235.
- Trozzo S, Neupane B, Foster PJ. A comparison of the sensitivity and cellular detection capabilities of magnetic particle imaging and bioluminescence imaging. Tomography. 2024;10(11):1846-66.
- Bezuglov E, et al. Mesenchymal stem cell injections in traumatology and orthopaedics: Common practice or still a promising area with many uncertainties? BMC Musculoskelet Disord. 2025;26(1):840.
- Rovera G, et al. Machine learning CT-based automatic nodal segmentation and PET semi-quantification of intraoperative 68Ga-PSMA-11 PET/CT images in high-risk prostate cancer: A pilot study. Diagnostics (Basel). 2023;13(18).
- Guzman Gomez R, et al. Deep learning approaches for automated prediction of treatment response in non-small-cell lung cancer patients based on CT and PET imaging. Tomography. 2025;11(7).
- Ferrara D, et al. Total-body [18F]FDG PET/CT imaging of healthy volunteers with minimal effective dose. Eur J Nucl Med Mol Imaging. 2025;53(4):2622-35.