This review synthesizes evidence on premenstrual syndrome and probable premenstrual dysphoric disorder among female health sciences students, highlighting their prevalence and associations with impaired academic performance, absenteeism, and reduced well-being, and identifying the need for supportive university health policies and further prospective research.
מאמר סקירה
Premenstrual Syndrome and Premenstrual Dysphoric Disorder: A Systematic Review of Academic Performance and Well-Being in University Students
במאמר זה
סיכום
תקציר
Premenstrual syndrome (PMS) and premenstrual dysphoric disorder (PMDD) are common among women of reproductive age and are associated with academic performance and general well-being at the university level. This review aimed to synthesize evidence on the prevalence of PMS and PMDD and their associations with academic, psychological, and well-being outcomes among female medical and health sciences students. Searches were conducted using PubMed, MEDLINE via Ovid, Web of Science, Wiley Online Library, and EBSCOhost, through which Academic Search Complete, MEDLINE, and PsycINFO were searched for studies published between January 2014 and December 2024. Of 317 identified records, 11 studies met the inclusion criteria; all were observational and cross-sectional. Prevalence estimates varied widely, with PMS ranging from 37.0% to 86.2% and probable PMDD from 13.8% to 66.9%. All PMDD estimates were based on questionnaire screening rather than prospective diagnostic confirmation and therefore represent screening-positive cases rather than confirmed diagnoses. Premenstrual symptoms were associated with impaired concentration, absenteeism, reduced class participation, lower perceived academic performance, and poorer psychological well-being. Associated factors included severe dysmenorrhea, family history, academic stress, irregular or shorter menstrual cycles, and low physical activity. The cross-sectional designs, heterogeneous diagnostic criteria, and varying outcome measures limit causal inference and generalizability. PMS and probable PMDD are associated with poorer academic performance and well-being among female medical and health sciences students. Universities should consider proportionate supportive responses, including menstrual health education, access to health services and counseling, and appropriate academic or social support. Future research should employ standardized diagnostic and outcome measures and prospective study designs.
מבוא
Premenstrual syndrome (PMS) is a common cyclical condition in women of reproductive age. It is characterized by physical, psychological, social, and behavioral symptoms1,2. A key methodological issue within PMS and premenstrual dysphoric disorder (PMDD) research is the distinction between questionnaire-based symptom screening and formal diagnosis. PMS is usually evaluated retrospectively using symptom scales. In contrast, PMDD requires prospective confirmation across at least two symptomatic cycles, together with careful exclusion of symptom exacerbation attributable to underlying psychiatric disorders. Researchers and clinicians should therefore interpret prevalence estimates cautiously, particularly when studies report probable PMDD without prospective diagnostic validation, as this may lead to inappropriate interpretation and application of the findings3,4,5.
PMS is estimated to affect 20%–40% of women globally, with some populations experiencing an even greater burden6,7. Over the last 30 years, the absolute number of women with PMS has increased significantly as a result of population growth and greater awareness and diagnosis of menstrual cycle-related health disorders8. Despite this increase in absolute numbers, the age-standardized prevalence of PMS has remained approximately stable, underscoring PMS as an enduring and widespread public health issue8. Similarly, the absolute number of years lived with disability associated with PMS has increased substantially, while the age-standardized years-lived-with-disability rate has remained stable8.
Female university students may experience particular difficulties in coping with PMS because the cognitive, emotional, and social demands of higher education settings place additional challenges on them6,9,10,11. In addition to academic disruption, university students with PMS have been reported to experience mental health concerns, including anxiety and depression, which may intensify existing difficulties9,10.
Despite its substantial impact, PMS remains underrecognized and undertreated in academic settings and within the health care system6,12. Societal stigma and normalization of symptoms make it important to study the prevalence of PMS among university students to better understand its association with academic performance. Such information is also important for designing tailored interventions, health-promotion initiatives, and clearly articulated support mechanisms that may enhance the academic achievement and well-being of female students12.
The rationale for this review is the reported burden of PMS and PMDD among female university students and their associations with aspects of academic performance, including concentration, attendance, and participation in both curricular and extracurricular activities2,7. In these studies, many enrolled students reported adverse effects on schoolwork, including decreased time spent in the classroom and reduced productivity. Such correlates are important for informing interventions and institutional policies intended to support these students and, in turn, promote academic achievement and mental health2,7.
From an educational perspective, menstrual symptoms should not be treated solely as a private health concern; they may affect participation, assessment, performance, and concentration in classroom and clinical settings. In demanding training environments such as medicine and allied health, repeated short-term functional impairment may accumulate over time and contribute to stress, disengagement, and reduced well-being, even when students do not seek formal care13,14,15.
Despite growing interest in menstrual health in higher education, the current literature remains fragmented. Some studies report on PMS, others on PMDD, and others on dysmenorrhea or more general menstrual disturbances, making it difficult to link observed academic effects to precisely defined premenstrual conditions. The absence of clear constructs also limits comparability across studies, highlighting the need for a review based on clearer conceptual boundaries16.
The Saudi context is particularly relevant, as regional literature suggests that the burden of menstrual and premenstrual symptoms among female university students is considerable and is accompanied by underreporting, self-management practices, and academic disruption. This does not imply that Saudi students differ fundamentally from their international peers; rather, it provides an opportunity to interpret international evidence in the context of local university health realities, patterns of stigma, and the availability of student support services. The academic environment may further amplify these challenges through cognitive and emotional demands that are associated with absenteeism, reduced participation, and poorer academic achievement. Understanding the prevalence and significance of PMS and probable PMDD among female students is therefore important for informing appropriate interventions and support. The specific focus of this systematic review is the relationship between PMS and PMDD and academic performance and psychological well-being among medical and health sciences students, who study in particularly demanding academic environments. Addressing these gaps is important for promoting health and educational equity for women. Accordingly, this review aims to synthesize the current literature on PMS and PMDD among medical and health sciences students, focusing on prevalence, associated factors, academic performance, and well-being. A schematic overview of the systematic review is presented in Figure 1.
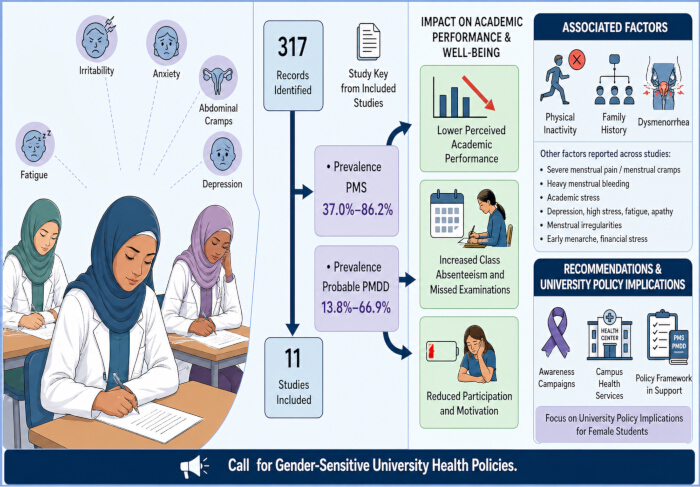
Figure 1. Schematic overview of the systematic review. Premenstrual syndrome (PMS) and probable premenstrual dysphoric disorder (PMDD) are summarized in relation to reported prevalence, academic and well-being outcomes, associated factors, and potential university policy implications among female university students. The schematic shows 317 identified records, 11 included studies, PMS prevalence of 37.0%–86.2%, and probable PMDD prevalence of 13.8%–66.9%. Academic outcomes included lower perceived academic performance, absenteeism, missed examinations, and reduced participation and motivation. Associated factors included physical inactivity, family history, dysmenorrhea, menstrual pain, heavy menstrual bleeding, academic stress, menstrual irregularities, early menarche, and other study-specific correlates. Please click here to view a larger version of this figure.
סקירה ופרספקטיבה
Review approach, protocol, and registration
This systematic review summarizes the evidence on the association of PMS and PMDD with academic performance and well-being among female medical and health sciences students. The review was conducted in accordance with the PRISMA statement17. Before formal screening commenced, the review protocol was prospectively registered with PROSPERO (CRD420251156246) to support transparency and methodological accountability. During the review, several deviations from the PROSPERO record occurred. These included changes to the eligibility time window for publications, modifications to the search information sources, and the non-implementation of some planned procedures concerning unpublished literature and quantitative synthesis. The specific deviations and their implications are addressed later in this section.
Eligibility criteria
Studies were included if: (1) participants were female university or college students enrolled in degree programs in medicine, nursing, allied health, or other health sciences; (2) PMS and/or PMDD or premenstrual symptoms relevant to the review were assessed using validated symptom-based criteria, standardized questionnaires, American College of Obstetricians and Gynecologists (ACOG) criteria, Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) criteria, or clearly reported premenstrual symptom measures; (3) at least one academic outcome, including but not limited to grades, marks, academic performance, absenteeism, presenteeism, or concentration, or a psychological or well-being outcome, including quality of life, mental well-being, or health consequences of menstrual disturbance, was reported; and (4) an observational study design, including cross-sectional, case-control, or cohort studies, was used.
Eligible studies were English-language articles published from January 2014 to December 2024. Reviews, editorials, opinion pieces, case reports, and conference abstracts without sufficient extractable data were excluded. Grey literature, dissertations, and unpublished studies were also excluded. Studies reporting dysmenorrhea or other menstrual complaints were excluded unless they also provided extractable data on PMS/PMDD symptoms or their academic or well-being correlates relevant to the review question. For PMDD, questionnaire-based studies were included and classified as reporting probable or screening-positive PMDD unless prospective cycle-based diagnostic confirmation was documented.
Operational definitions
For this review, PMS was defined as recurrent, cyclical physical, emotional, or behavioral symptoms occurring during the premenstrual phase of the menstrual cycle and identified using symptom-based criteria or validated questionnaires. PMDD was defined more narrowly as a severe premenstrual disorder characterized by marked affective and functional impairment. Given that most studies included in this review used cross-sectional questionnaires rather than prospective daily ratings over two symptomatic cycles, PMDD prevalence estimates should be interpreted as probable or screening-positive PMDD rather than diagnostically confirmed prevalence rates.
Information sources and search strategy
A systematic search was performed using PubMed, MEDLINE via Ovid, Web of Science, Wiley Online Library, and EBSCOhost, through which Academic Search Complete, MEDLINE, and PsycINFO were searched. The search covered studies published from January 2014 to December 2024. The search strategy was constructed using Boolean operators (AND/OR) and three groups of core concept terms: (1) PMS/PMDD-related terms, including database-specific controlled vocabulary where applicable and free-text keywords (Premenstrual Syndrome, Premenstrual Dysphoric Disorder, PMS, and PMDD); (2) population terms (medical students, nursing students, health science students, university students, and college students); and (3) outcome terms (academic performance, absenteeism, concentration, well-being, quality of life, mental health, and psychological outcomes). Searches were restricted to English-language articles. Complete database-specific search strategies are provided in Supplementary Table 1.
Study selection process
All retrieved records were imported into Rayyan for duplicate management and screening. Two reviewers independently screened titles and abstracts, followed by full-text assessment of potentially eligible studies. Disagreements were discussed and resolved through consultation with a third reviewer when consensus could not be reached.
Data extraction
Data extraction was performed using a standardized, piloted form completed independently by two reviewers. The extracted data comprised study characteristics, identifying information, country, setting, study design, sample size, participant characteristics, PMS/PMDD definitions and assessment tools, outcome domains, statistical measures used to analyze outcomes, and key findings relevant to academic performance and well-being. To further ensure transparency, the process included calibration exercises and documentation of discrepancies and their resolution.
Risk-of-bias assessment
The Newcastle–Ottawa Scale (NOS), adapted for cross-sectional studies, was used to assess risk of bias because all included studies were cross-sectional. Disagreements were resolved through discussion and referral to a third reviewer. Studies were classified as having low, moderate, or high risk of bias using prespecified score thresholds of 7–9, 4–6, and 0–3, respectively. The assessment considered sample representativeness, ascertainment of exposure, comparability, and outcome assessment.
Data synthesis and analysis
The findings were synthesized and summarized based on the extracted data. A narrative synthesis was conducted to describe the study characteristics, methodological quality, and principal findings of the included studies in relation to the review question.
Software
Study selection and screening were managed using Rayyan (version 2024), a web-based collaborative platform for systematic review screening. Data extraction was performed using a standardized, piloted form in Microsoft Excel (Microsoft 365). Risk-of-bias assessment was conducted using the NOS adapted for cross-sectional studies. The review was reported in accordance with the PRISMA 2020 guidelines. The databases, software, methodological tools, reporting guidelines, and artificial intelligence-assisted tools used in this review are summarized in Supplementary Table 2. The completed PRISMA 2020 checklist is provided in Supplementary File 1.
Study selection
The initial and updated database searches, covering January 2014 to December 2024, identified 317 records. After duplicate removal and other initial exclusions, 245 records underwent title and abstract screening, of which 201 were excluded for not meeting the eligibility criteria. Forty-four reports were sought for retrieval; however, 13 could not be retrieved. Ultimately, 31 full-text articles were assessed for eligibility based on the inclusion and exclusion criteria. Of these, 20 were excluded due to an ineligible study design, an incorrect setting, or insufficient extractable data, resulting in 11 studies being included in the final synthesis (Figure 2).
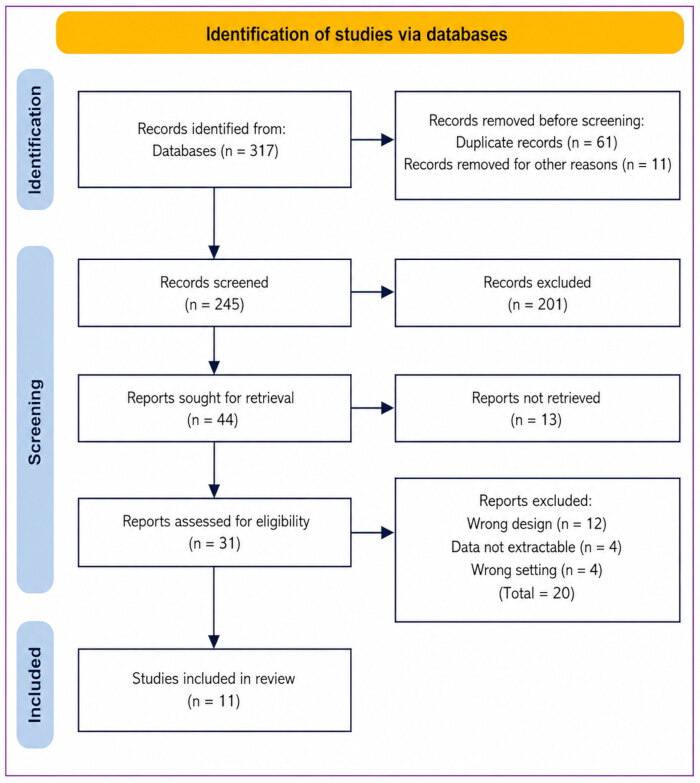
Figure 2. PRISMA 2020 flow diagram of study selection. Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 flow diagram showing study identification, screening, eligibility assessment, and inclusion. A total of 317 records were identified from databases; after removal of 61 duplicates and 11 records for other reasons, 245 records were screened. Forty-four reports were sought for retrieval, 31 were assessed for eligibility, 20 were excluded, and 11 studies were included in the final review. Please click here to view a larger version of this figure.
Study characteristics
The final review comprised 11 observational studies18,19,20,21,22,23,24,25,26,27,28, all of which were cross-sectional and conducted in university settings in Ethiopia, Saudi Arabia, Turkey, and the United Arab Emirates. Sample sizes ranged from 251 to 620 participants, and most studies involved female students in medicine or health sciences or the general university population. Because the included studies varied by country, sampling approach, symptom definitions, and outcome measures, the findings were synthesized narratively rather than quantitatively. The characteristics of the included studies are summarized in Table 1.
| Authors | Country | PMS Prevalence | Probable PMDD Prevalence | Academic Outcomes | Associated Factors |
| Tolossa et al.¹⁸ | Ethiopia | 37.00% | Not assessed | Academic impairment in 48%; class absenteeism; missed examinations; lower grades | Short menstrual cycles; academic problems |
| Alemu et al.¹⁹ | Ethiopia | 86.20% | 13.80% | No significant difference in GPA; self-reported decreased performance | Shorter menstrual cycles; severe pain; heavy bleeding |
| Tsegaye et al.²⁰ | Ethiopia | Not assessed | 66.90% | Negative academic effects in 85.4%; absenteeism (61.8%); poor grades (25.3%) | Severe dysmenorrhea |
| Bayomy et al.²¹ | Saudi Arabia | 68.80% | 29.00% | Reduced concentration; absenteeism; poor motivation | Family history; physical inactivity; academic stress |
| Bilir et al.²² | Turkey | 71.30% | Not assessed | Academic and social withdrawal; reduced performance | Dysmenorrhea; depression |
| Minichil et al.²³ | Ethiopia | Not assessed | 34.70% | Impaired academic performance | Severe menstrual pain; high stress; fatigue; apathy |
| Al-Shahrani et al.²⁴ | Saudi Arabia | ~66.0% | Not assessed | Increased stress during periods; disrupted concentration; difficulty completing homework | Family history of PMS; menstrual irregularities |
| Eshetu et al.²⁵ | Ethiopia | 37.20% | Not assessed | Reduced academic performance; absenteeism; poor concentration | Severe dysmenorrhea; family history; irregular cycles |
| Mesele et al.²⁶ | Ethiopia | Not assessed | Not assessed | Difficulty concentrating in class (76%); difficulty completing homework | Early menarche; financial stress; severe pain |
| Katib et al.²⁷ | Saudi Arabia | Not assessed | Not assessed | Reduced productivity; impaired academic performance | Pain severity; family history |
| Omara et al.²⁸ | United Arab Emirates | 78.90% | 16.30% | Impaired concentration; class absenteeism; academic performance affected in >90% | Premenstrual symptom severity |
Table 1: Summary of findings across the included studies. Premenstrual syndrome (PMS) and probable premenstrual dysphoric disorder (PMDD) prevalence estimates, academic outcomes, and associated factors are summarized for the 11 included studies. Grade point average (GPA) is reported where applicable. “Not assessed” indicates that the corresponding outcome was not evaluated or reported in the study. Associated factors are presented as reported in the individual studies and should not be interpreted as causal risk factors.
Prevalence
Reported prevalence estimates varied substantially across studies. PMS prevalence ranged from 37.0% to 86.2%, whereas probable PMDD prevalence ranged from 13.8% to 66.9%. This wide variation should be interpreted with caution because the studies used different symptom criteria and screening instruments. All PMDD estimates were based on questionnaire screening rather than prospective diagnostic assessment across two symptomatic cycles and should therefore be interpreted as probable or screening-positive PMDD rather than confirmed diagnostic prevalence.
Among Ethiopian health sciences students, Tolossa et al. reported a PMS prevalence of 37%, with 48% experiencing academic impairment associated with symptoms such as abdominal cramps, mood swings, and depression. Frequent class absenteeism, missed examinations, and lower grades were reported consequences, yet only about half sought treatment18.
Alemu et al. reported a PMS prevalence of 86.2% and a probable or screening-positive PMDD prevalence of 13.8%. Shorter menstrual cycles and severe pain were significantly associated with PMDD, which was also associated with decreased academic performance, although differences in grades were not statistically significant19.
Tsegaye et al. reported a probable or screening-positive PMDD prevalence of 66.9% among students at Wollo University, with 85.4% reporting that their symptoms negatively affected academic achievement through absenteeism (61.8%) and low grades (25.3%). Severe dysmenorrhea was strongly associated with PMDD20.
In Saudi Arabia, Bayomy et al. reported a PMS prevalence of 68.8% and academic effects including reduced concentration, absenteeism, and poor motivation, particularly among medical students; family history and physical inactivity were also associated factors21. Bilir et al. reported high prevalences of dysmenorrhea (90.1%) and PMS (71.3%) among Turkish students, with depression and academic and social withdrawal reported as major consequences. Fewer than 20% sought care, while most relied on self-management strategies such as analgesics and heat packs22.
Other studies consistently described fatigue, depression, anxiety, and severe menstrual pain as prominent symptoms. Across studies, PMS or PMDD symptoms were associated with impaired concentration, reduced participation, absenteeism, and lower perceived academic performance23,24,25,26,27,28; however, findings for objective academic indicators such as grades were less consistent. Lifestyle and participant characteristics associated with PMS or PMDD included physical inactivity, stress, early menarche, family history of PMS, and irregular menstrual cycles. Despite the substantial symptom burden, medical help-seeking was low, and most students used self-care practices and informal coping strategies25,26.
Academic outcomes
Across the included studies, students with PMS or PMDD reported academic difficulties, including reduced concentration, absenteeism, reduced class participation, difficulties with homework completion, and lower perceived academic performance. However, findings on objective academic indicators such as grades were less consistent; while most studies reported perceived academic decline, Alemu et al. found no significant difference in grade point average between students with and without significant premenstrual symptoms.
Psychological and symptom burden
The most frequently reported symptoms included fatigue, irritability, anxiety, depression, abdominal cramps, apathy, and severe menstrual pain. These symptoms were commonly associated with impaired daily performance and poorer well-being, in addition to academic disruption. The symptom profile was not uniform across studies, likely reflecting variation in assessment tools, case definitions, and study populations.
Associated factors
Several studies identified factors associated with greater symptom severity or a higher likelihood of PMS or PMDD, although the pattern was not uniform across the evidence base. The most frequently reported correlates included severe dysmenorrhea, shorter or irregular menstrual cycles, heavy menstrual bleeding, family history of PMS, academic stress, high perceived stress, and low physical activity19,20,21,23,24,25. Because these associations were based mainly on cross-sectional studies with limited adjustment for potential confounding factors, they should be considered potential correlates rather than established risk factors.
Help-seeking and coping
Despite the substantial symptom burden reported across studies, formal help-seeking was generally low. Many students relied on self-management strategies such as analgesics, rest, sleep, and hot packs rather than seeking professional medical or psychological support18,22,25. This pattern suggests an important gap in treatment and support, although the reasons for low help-seeking were not consistently examined across the included studies. Figure 3 presents the outcome areas evaluated across the included studies. The most frequently assessed outcome was academic performance (n = 7), followed by physical symptoms/pain (n = 6), mental health (n = 5), and absenteeism/presenteeism (n = 5). Fewer studies assessed sleep/fatigue (n = 3) and help-seeking/management (n = 2). Individual studies could contribute to more than one outcome domain.
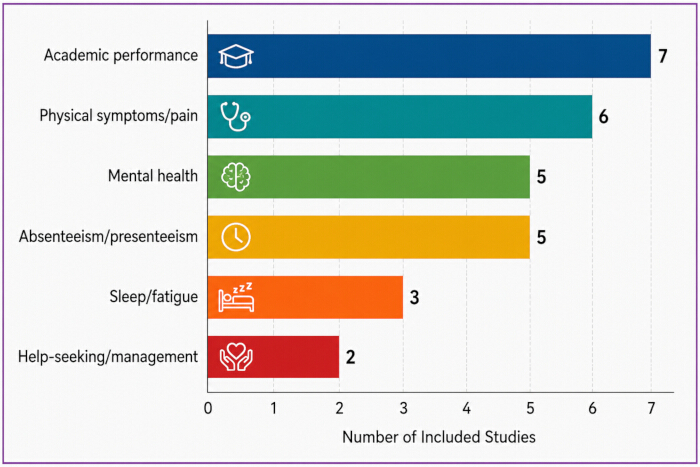
Figure 3. Evidence map of outcome domains assessed across the included studies. The figure summarizes the number of included studies reporting each outcome domain: academic performance (n = 7), physical symptoms/pain (n = 6), mental health (n = 5), absenteeism/presenteeism (n = 5), sleep/fatigue (n = 3), and help-seeking/management (n = 2). Individual studies could contribute to more than one outcome domain. Please click here to view a larger version of this figure.
Risk-of-bias findings
Based on the risk-of-bias assessment using the Newcastle–Ottawa Scale, the included studies received total scores ranging from 4 to 7 out of 9. Two studies were rated as having a low risk of bias, each scoring 7/918,19, while the remaining nine studies were rated as having a moderate risk of bias, with scores ranging from 4/9 to 6/9 (Table 2)20,21,22,23,24,25,26,27,28. No study was classified as having a high risk of bias. The main methodological limitations across studies were limited representativeness of study samples, reliance on self-reported symptom and academic outcome measures, and insufficient control for potential confounders. These limitations should be considered when interpreting the findings of this review and do not support strong causal conclusions.
| Authors | Q1 | Q2 | Q3 | Q4 | Q5 | Q6 | Q7 | Q8 | Total score | Risk of bias |
| Tolossa et al.¹⁸ | * | * | – | * | ** | * | – | * | 7/9 | Low risk |
| Alemu et al.¹⁹ | * | * | – | * | ** | * | – | * | 7/9 | Low risk |
| Tsegaye et al.²⁰ | * | – | * | * | * | * | – | * | 6/9 | Moderate risk |
| Bayomy et al.²¹ | * | – | * | * | * | * | * | N/A | 6/9 | Moderate risk |
| Bilir et al.²² | * | – | * | * | ** | * | – | N/A | 6/9 | Moderate risk |
| Minichil et al.²³ | * | – | * | * | ** | * | – | N/A | 6/9 | Moderate risk |
| Al-Shahrani et al.²⁴ | * | – | * | * | ** | * | – | N/A | 6/9 | Moderate risk |
| Eshetu et al.²⁵ | * | – | * | * | ** | * | – | N/A | 6/9 | Moderate risk |
| Mesele et al.²⁶ | * | – | * | * | ** | * | – | N/A | 6/9 | Moderate risk |
| Katib et al.²⁷ | * | – | * | * | ** | * | – | N/A | 6/9 | Moderate risk |
| Omara et al.²⁸ | * | – | * | * | – | * | – | N/A | 4/9 | Moderate risk |
| Selection: Q1, representativeness of the exposed cohort; Q2, selection of the non-exposed group; Q3, ascertainment of exposure; Q4, demonstration that the outcome of interest was not present at the start of the study. Comparability: Q5, comparability of groups on the basis of study design or analysis. Outcome: Q6, assessment of outcome; Q7, adequacy of follow-up duration for outcomes to occur; Q8, adequacy of follow-up. * = 1 point; ** = 2 points; – = 0 points; N/A = not applicable. Total scores of 7–9 were classified as low risk of bias, 4–6 as moderate risk, and 0–3 as high risk. | ||||||||||
Table 2: Risk-of-bias assessment of the included studies using the Newcastle–Ottawa Scale adapted for cross-sectional observational studies. The Newcastle–Ottawa Scale (NOS) assessment presents item-level ratings (Q1–Q8), total scores out of 9, and overall risk-of-bias classifications for the 11 included studies. An asterisk (*) indicates 1 point, two asterisks (**) indicate 2 points, an en dash (–) indicates 0 points, and N/A indicates not applicable. Total scores of 7–9 were classified as low risk of bias, 4–6 as moderate risk, and 0–3 as high risk.
Interpretation of prevalence and diagnostic heterogeneity
Overall, prevalence estimates varied widely across studies. PMS prevalence ranged from 37.0% to 86.2%, while probable PMDD prevalence ranged from 13.8% to 66.9%. This variability should be interpreted with caution, as differences in diagnostic criteria and the self-report questionnaires used across studies may explain part of the heterogeneity.
Academic implications
Another important finding across the included studies was the association between premenstrual symptoms and poorer academic performance. However, some studies reported inconsistent effects on objective indicators of academic outcomes, underscoring the importance of accounting for differences in symptom severity, coping strategies, institutional context, and measurement methods. Much of the literature indicates that these conditions are associated with educational difficulties, including impaired concentration, absenteeism, disengagement from class activities, and lower perceived academic performance19,20,22,23,24,25. However, Alemu et al. reported no significant difference in grades, representing an important exception19.
Psychological and cognitive implications
The most frequently reported symptoms included irritability, fatigue, depression, and anxiety18,22,23,24. These symptoms may be particularly relevant in an academic environment because they may contribute to difficulties with concentration and academic performance.
Associated factors and interpretation
Although these associations are clinically plausible, the cross-sectional design of the included studies precludes conclusions about directionality or causality. These variables should therefore be interpreted as correlates or markers of greater burden rather than proven causative risk factors19,20,25. In addition, a family history of premenstrual complaints was repeatedly identified as an associated factor 21,24,25, suggesting possible familial susceptibility. Other potentially modifiable lifestyle factors, such as low physical activity21, were also explored, highlighting it as a potentially modifiable correlate. At the same time, academic stress may exacerbate symptom perception or make coping more difficult, suggesting a potentially bidirectional relationship that cannot be established from cross-sectional studies alone19,23. While social support was assessed in some studies, it was not consistently identified as a significant factor.
Help-seeking and the Saudi context
Such patterns may reflect normalization of symptoms, stigma, limited menstrual health literacy, restricted access to services, or uncertainty about whether symptoms require evaluation by a healthcare professional. However, these explanations remain inferential because they were not consistently examined across the included studies.
The Saudi context is particularly relevant because several of the included studies were conducted at Saudi universities. Cultural norms, help-seeking behavior, access to campus-based services, and differences in academic expectations may affect menstrual symptom experiences, reporting, and management. However, the current literature is too sparse and heterogeneous to support strong Saudi Arabia-specific conclusions beyond indicating that menstrual health may be an under-researched issue related to student well-being in this context. A stronger Saudi-focused evidence base would require more methodologically consistent local studies using clearer PMS/PMDD definitions and standardized academic outcomes.
Institutional implications and perspectives
The current literature suggests that universities should consider PMS/PMDD within broader student health and well-being frameworks rather than treating these symptoms solely as private or incidental concerns. Because the evidence base is observational and heterogeneous, these recommendations should be framed as pragmatic and supportive rather than as interventions proven by high-certainty evidence to improve academic outcomes.
Looking forward, integrated approaches combining medical, psychological, and educational resources may help address the physical and mental health consequences associated with PMS and PMDD. Recent literature has proposed educational and supportive approaches, including awareness initiatives and access to counseling or treatment, as potential strategies for affected students29,31.
Institutional framework and future directions
In light of the consistent association between PMS/PMDD symptoms and reduced academic performance, a multilevel university support framework may represent a reasonable, evidence-informed response (Figure 4). Such a framework should be regarded as a pragmatic institutional approach rather than as an intervention model supported by high-certainty evidence. The first component is awareness and destigmatization, with the aim of improving menstrual health literacy and reducing stigma through institution-wide educational initiatives, embedded teaching, and faculty development. The second component is access and support, including access to student health services and counseling, referral pathways to additional resources, and peer-support options for students experiencing substantial cyclical symptom burden. The third component is academic accommodation, focusing on equitable and proportionate flexibility, such as reasonable adjustments to attendance and other supports for students with documented functional impairment. This framework may help address the gap between unmet symptom-related needs and the low level of formal help-seeking reported across the reviewed studies.
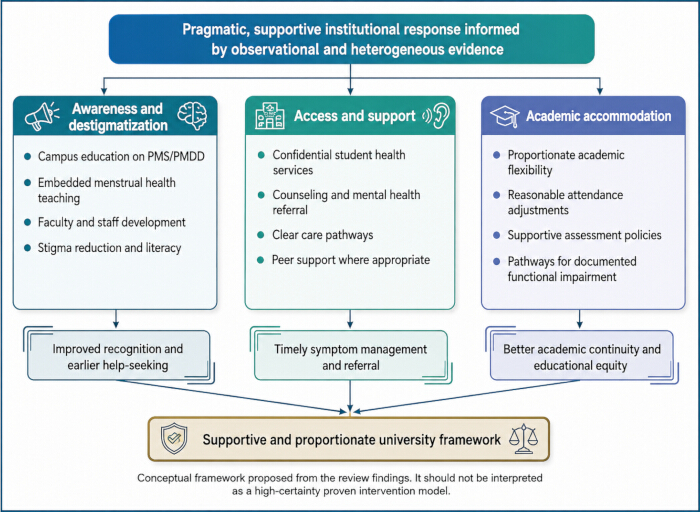
Figure 4. Multilevel university support framework for premenstrual syndrome and premenstrual dysphoric disorder. Premenstrual syndrome (PMS) and premenstrual dysphoric disorder (PMDD) are addressed through a proposed framework comprising awareness and destigmatization, access and support, and academic accommodation. The framework includes menstrual health education, confidential student health and counseling services, referral and peer-support pathways, and proportionate academic flexibility for documented functional impairment. It represents a pragmatic institutional response informed by observational and heterogeneous evidence and should not be interpreted as a high-certainty, proven intervention model. Please click here to view a larger version of this figure.
Limitations
This review has several limitations. All included studies were cross-sectional, which precludes causal inference and leaves open the possibility of bidirectional relationships. Reliance on self-reported measures may introduce recall and response bias. PMDD prevalence estimates based on screening questionnaires may overestimate true diagnostically confirmed rates. Heterogeneity in diagnostic criteria, assessment tools, and outcome measures limits comparability and generalizability. Restriction to English-language studies and the geographic concentration of included studies in Ethiopia, Saudi Arabia, Turkey, and the United Arab Emirates may further limit applicability. The inability to conduct a meta-analysis also limits the strength of the conclusions.
Protocol deviations and their implications
There were several deviations from the registered PROSPERO protocol. The eligibility period was changed to January 2014–December 2024 to better reflect the most recent decade of evidence. An updated search was conducted later to ensure comprehensive capture of all eligible studies through December 2024. For feasibility reasons, the search sources were limited to PubMed, MEDLINE via Ovid, Web of Science, Wiley Online Library, and EBSCOhost, and unpublished literature was not searched. A quantitative meta-analysis was not performed because of substantial methodological heterogeneity across studies, which would have made pooled estimates unreliable. These deviations were intended to support feasibility while maintaining the core eligibility criteria and systematic search process. Any changes to the registered protocol were transparently reported in PROSPERO to support accountability and reproducibility
מסקנות
This systematic review found a substantial burden of PMS and probable PMDD among female medical and health sciences students, with associations with academic difficulties, including reduced concentration, absenteeism, lower perceived academic achievement, and poorer psychological well-being. Severe dysmenorrhea, family history of PMS, academic stress, irregular menstrual patterns, and low physical activity were among the most frequently reported associated factors. Formal help-seeking was generally low despite the reported symptom burden. The evidence base is limited by the cross-sectional design of all included studies, reliance on self-reported measures, heterogeneous diagnostic criteria and outcome measures, and questionnaire-based estimates of PMDD. Accordingly, the findings should be interpreted as associations rather than evidence of causation, and probable or screening-positive PMDD should not be considered equivalent to diagnostically confirmed PMDD. Universities may consider pragmatic and proportionate supportive approaches, including menstrual health education, access to student health and counseling services, mental health referral pathways, peer support, and reasonable academic accommodations for students experiencing substantial cyclical impairment. These approaches should be regarded as supportive institutional responses rather than interventions proven by high-certainty evidence. Future research should prioritize multicenter longitudinal studies to clarify temporal relationships, intervention studies to evaluate support strategies, and the use of standardized diagnostic criteria and outcome measures. Further research is also needed on barriers to help-seeking and the feasibility, acceptability, and cost-effectiveness of university-based support programs. Multidisciplinary approaches integrating medical, psychological, and educational support may be valuable, but their effectiveness in university settings remains to be established.
Supplementary Table 1. Database-specific search strategies used for the systematic review. Search strategies and limits applied across PubMed, MEDLINE via Ovid, Web of Science, Wiley Online Library, and EBSCOhost (Academic Search Complete, MEDLINE, and PsycINFO) for studies published from January 2014 to December 2024. Database-specific controlled vocabulary and free-text terms were used as applicable. Abbreviations: MeSH, Medical Subject Headings; PMS, premenstrual syndrome; PMDD, premenstrual dysphoric disorder; tiab, title/abstract; TS, topic; TX, all text. Please click here to download this file.
Supplementary Table 2. Databases, software, methodological tools, reporting guidelines, and artificial intelligence-assisted tools used in the systematic review. Resources used for literature searching, study selection and screening, data extraction, narrative synthesis, risk-of-bias assessment, systematic review reporting, language editing and proofreading, and preparation of Figure 1 are summarized. Abbreviations: NOS, Newcastle–Ottawa Scale; PRISMA, Preferred Reporting Items for Systematic Reviews and Meta-Analyses; AI, artificial intelligence; N/A, not applicable. Please click here to download this file.
Supplementary File 1. Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 checklist. The completed PRISMA 2020 checklist reports the location within the manuscript where each applicable reporting item is addressed. Items not applicable to the present systematic review are indicated as “NA.” Please click here to download this file.
גילויים
Conflict of Interest:
Elhadi Miskeen is a Guest Editor for the journal but was not involved in the review of this manuscript or in any editorial decision regarding its publication. The remaining authors declare no conflicts of interest.
AI Declaration:
Artificial intelligence (AI)-assisted tools were used in the preparation of this manuscript. Grammarly (2025; Grammarly Inc., San Francisco, California, USA) was used to support language editing, reference formatting, and refinement of the manuscript structure. GPT-5.4 was used to assist in the design of Figure 1. The authors independently verified all data, interpretations, and references and take full responsibility for the content and conclusions presented.
תודות
The authors thank the Deanship of Graduate Studies and Scientific Research at the University of Bisha for supporting this work through the Fast-Track Research Support Program.
מקורות
- Granda D, Szmidt MK, Surała O, Malczewska-Lenczowska J. Prevalence of premenstrual syndrome and premenstrual dysphoric disorder among highly trained and elite female athletes: a systematic review and meta-analysis. Biol Sport. 2025;42(3):211-25.
- Sultana J, et al. Updated insight into the pathophysiology of premenstrual dysphoric disorder and therapeutic approaches. J Affect Disord. 2026;121593.
- Al-Harbi NN, et al. Premenstrual syndrome among female university students in Jeddah, Saudi Arabia. J Family Med Prim Care. 2020;9(5):2498-503.
- Maity S, et al. Prevalence of premenstrual syndrome, premenstrual dysphoric disorder, and dysmenorrhea in nursing students: a systematic review, meta-analysis, and evidence-based recommendations. Front Glob Womens Health. 2026;6:1701704.
- Ceylan Ş, Arslan İ. Approach to premenstrual syndrome and premenstrual dysphoric disorder from the perspective of family medicine. Konuralp Med J. 2026;18(1):98-103.
- Shah RS, Christian DS. Association of socio-demographic, dietary and lifestyle factors with premenstrual syndrome (PMS) among undergraduate medical students of a tertiary care institute in Ahmedabad, Gujarat. J Family Med Prim Care. 2020;9(11):5719-24.
- Gao M et al. Global and regional prevalence and burden for premenstrual syndrome and premenstrual dysphoric disorder: a study protocol for systematic review and meta-analysis. Medicine (Baltimore). 2022;101(1):e28528.
- Liu X, Li R, Wang S, Zhang J. Global, regional, and national burden of premenstrual syndrome, 1990-2019: an analysis based on the Global Burden of Disease Study 2019. Hum Reprod. 2024;39(6):1303-15.
- Rafique N, Al-Sheikh MH. Prevalence of menstrual problems and their association with psychological stress in young female students studying health sciences. Saudi Med J. 2018;39(1):67-73.
- Maity S et al. Academic and social impact of menstrual disturbances in female medical students: a systematic review and meta-analysis. Front Med (Lausanne). 2022;9:821908.
- Chekol AT et al. Determinants of premenstrual dysphoric disorder and associated factors among regular undergraduate students at Hawassa University Southern, Ethiopia, 2023: institution-based cross-sectional study. BMC Public Health. 2024;24:1390.
- Edis EK, Keten M. Premenstrual syndrome experiences and coping levels of university students: a mixed method study. Bezmialem Sci. 2023;11(3):308-14.
- Mahwish N, et al. Prevalence and impact of dysmenorrhea on the academic performance of students at medical and health sciences university. New Emirates Med J. 2024;5(1):e02506882288695.
- Belayneh W, et al. Prevalence of dysmenorrhea and associated factors and its effect on daily academic activities among female undergraduate students of Hawassa University College of Medicine and Health Sciences, Hawassa, Ethiopia. Front Reprod Health. 2023;5:1244540.
- Islas-Preciado D, Ramos-Lira L, Estrada-Camarena E. Unveiling the burden of premenstrual dysphoric disorder: a narrative review to call for gender perspective and intersectional approaches. Front Psychiatry. 2025;15:1458114.
- Almslamani R, et al. Period pain among female university students in Jeddah City, Saudi Arabia: cross-sectional study. Clin Exp Obstet Gynecol. 2023;50(2):28.
- Haddaway NR, Page MJ, Pritchard CC, McGuinness LA. PRISMA2020: an R package and Shiny app for producing PRISMA 2020-compliant flow diagrams, with interactivity for optimised digital transparency and open synthesis. Campbell Syst Rev. 2022;18:e1230.
- Tolossa FW, Bekele ML. Prevalence, impacts and medical managements of premenstrual syndrome among female students: cross-sectional study in college of health sciences, Mekelle University, Mekelle, Northern Ethiopia. BMC Womens Health. 2014;14:52.
- Alemu SM, Habtewold TD, Haile YG. Mental and reproductive health correlates of academic performance among Debre Berhan University female students, Ethiopia: the case of premenstrual dysphoric disorder. Biomed Res Int. 2017;2017:9348159.
- Tsegaye D, Getachew Y. Premenstrual dysphoric disorder and associated factors among female health science students in Wollo University, Ethiopia, 2017/18. Matern Health Neonatol Perinatol. 2019;5(8):1-8.
- Bayomy HE, et al. Premenstrual syndrome and premenstrual dysphoric disorder among female students in Northern Border University, Arar City, Saudi Arabia. Biosci Res. 2020;17(4):4100-11.
- Bilir E, Yıldız Ş, Yakın K, Ata B. The impact of dysmenorrhea and premenstrual syndrome on academic performance of college students, and their willingness to seek help. Turk J Obstet Gynecol. 2020;17(3):196-201.
- Minichil W, Eskindir E, Demilew D, Mirkena Y. Magnitude of premenstrual dysphoric disorder and its correlation with academic performance among female medical and health science students at University of Gondar, Ethiopia, 2019: a cross-sectional study. BMJ Open. 2020;10:e034166.
- Al-Shahrani AM, et al. Premenstrual syndrome and its impact on the quality of life of female medical students at Bisha University, Saudi Arabia. J Multidiscip Healthc. 2021;14:2373-9.
- Eshetu N, et al. Premenstrual syndrome, coping mechanisms and associated factors among Wolkite University female regular students, Ethiopia, 2021. BMC Womens Health. 2022;22:88.
- Mesele TT, Ayalew HG, Syoum AT, Antehneh TA. Impact of dysmenorrhea on academic performance among Haramaya University undergraduate regular students, Eastern Ethiopia. Front Reprod Health. 2022;4:939035.
- Katib Y, et al. Prevalence of primary dysmenorrhea and its effect on the quality of life among female students at Umm Al-Qura University. Cureus. 2024;16(10):e72136.
- Omara EIM, et al. Impact of premenstrual tension syndrome on academic performance among female university students from the United Arab Emirates: a cross-sectional study. Health Sci Rep. 2024;7:e70124.
- Omara EIM, et al. Impact of premenstrual tension syndrome on academic performance and physical activity among female university students. Health Sci Rep. 2024;7(10):e1905.
- Khodakarami B et al. The effect of cognitive-behavioral counseling on resilience in adolescent girls with premenstrual syndrome: a randomized clinical trial. Iran J Nurs Midwifery Res. 2023;28(1):57-62.
- Jeihooni AK et al. Behavioral management intervention to modify premenstrual syndrome and improve knowledge, attitude, and preventive behaviors: an educational interventional study based on the health belief model. Open Public Health J. 2023;16(1):e187494452212345.
הדפסות חוזרות והרשאות
מאמר זה פורסם
הסרטון יגיע בקרוב