The Interleukin-33 (IL-33)/Growth stimulation expressed gene 2 (ST2) axis exerts context-dependent effects in transplantation: membrane-bound ST2 (ST2L) promotes immune tolerance, whereas soluble ST2 (sST2) blocks protective signaling and drives inflammation and fibrosis. Elevated sST2 is associated with rejection and graft-versus-host disease, though causal evidence remains limited.
Articolo di revisione
The Interleukin-33/Growth Stimulation Expressed Gene 2 Signaling Axis in Transplantation: Context-Dependent Roles and Clinical Implications
* These authors contributed equally
In questo articolo
Sommario
Abstract
This article comprehensively summarizes the expression, mechanisms of action, and clinical significance of the IL-33/ST2 axis in solid organ transplantation and hematopoietic stem cell transplantation. Rather than being uniformly protective or pathogenic, the IL-33/ST2 axis exerts context-dependent effects: ST2L, expressed on regulatory T cells, group 2 innate lymphoid cells, and Th2 cells, promotes immune tolerance, whereas sST2 acts as a decoy receptor that blocks this pathway and promotes inflammation and fibrosis. The net effect depends on tissue-specific innate immune cell composition, differential ST2 isoform expression, donor versus recipient compartment, intervention timing and dosage, and the degree of ischemia-reperfusion injury. Clinically, elevated sST2 is associated with antibody-mediated rejection in kidney transplantation, graft dysfunction in heart transplantation, and treatment-refractory graft-versus-host disease in allogeneic hematopoietic stem cell transplantation. However, these are primarily observational associations; direct causal evidence from genetic or pharmacological intervention studies remains limited and is often derived from animal models. Comparative analysis across transplant types reveals that sST2 may complement established biomarkers such as donor-derived cell-free DNA and donor-specific antibodies, particularly for chronic graft fibrosis and DSA-negative rejection. Future research should use single-cell and spatial transcriptomics to characterize the dynamic expression of ST2 isoforms across immune cells and transplant stages, and explore strategies to induce immune tolerance targeting the IL-33/ST2 axis to improve long-term outcomes for transplant patients.
Introduzione
Organ transplantation is one of the most significant achievements in modern medicine and remains the most effective treatment for patients with end-stage organ failure. Over the past decades, global transplant volumes have continued to rise, with hundreds of thousands of procedures performed annually. China's organ transplantation has undergone leapfrog development, and in 2024, a total of 24,684 solid organ transplants were performed nationwide, ranking first in Asia and second globally1. Despite these achievements, long-term graft survival remains limited by several unresolved clinical challenges.
The most critical unmet needs include: (1) limited early-warning tools for chronic allograft dysfunction, which often progresses silently before a decline in graft function becomes clinically apparent; (2) severe graft-versus-host disease (GVHD) after allogeneic hematopoietic stem cell transplantation (allo-HCT), which remains a major cause of non-relapse mortality; and (3) toxic side effects of long-term immunosuppression, which contribute to infection, malignancy, and cardiovascular disease. Current monitoring strategies—such as serum creatinine, donor-derived cell-free DNA (dd-cfDNA), and donor-specific antibodies (DSA)—have improved risk stratification but still lack sufficient sensitivity and specificity for predicting chronic graft failure or treatment-refractory GVHD2. Therefore, identifying robust biomarkers and therapeutic targets that reflect the graft's dynamic immune status is an urgent clinical need.
ST2, a member of the interleukin-1 receptor family, has emerged as a promising candidate. ST2 exists in two main isoforms: ST2L and sST2, both of which bind IL-33 as their common ligand3. The IL-33/ST2 axis plays a context-dependent and bidirectional role in transplantation. On one hand, ST2L expressed on regulatory T cells (Tregs), group 2 innate lymphoid cells (ILC2s), and Th2 cells can promote immune tolerance and attenuate rejection. On the other hand, sST2 acts as a decoy receptor that sequesters IL-33, thereby blocking ST2L-mediated protective signaling and promoting inflammation and fibrosis4. Importantly, whether ST2 exerts protective or pathogenic effects depends on cell type, donor versus recipient expression, intervention timing, and the specific transplant setting—a complexity that has not been systematically addressed in previous reviews.
Emerging clinical evidence supports sST2 as a prognostic biomarker in both solid organ and hematopoietic stem cell transplantation5. Elevated circulating sST2 levels have been associated with acute and chronic antibody-mediated rejection in kidney transplantation, graft dysfunction in heart transplantation, and treatment-refractory GVHD in allo-HCT6,7,8,9. However, most of these findings are observational associations; direct causal evidence from genetic or pharmacological intervention studies remains limited and is often derived from animal models. A critical appraisal that distinguishes clinical correlations from mechanistic evidence is therefore needed.
This review aims to: (1) summarize the expression patterns and downstream signaling pathways of the IL-33/ST2 axis; (2) comparatively analyze its protective and pathogenic roles across different transplant types, with particular emphasis on tissue-specific microenvironments; (3) critically evaluate the clinical evidence supporting sST2 as a biomarker, including reported cutoff values, sampling windows, and assay methods; and (4) examine therapeutic strategies targeting the IL-33/ST2 axis, distinguishing interventions directed at soluble and membrane-bound ST2. By integrating preclinical and clinical evidence, this review seeks to clarify the context-dependent functions of ST2, identify key knowledge gaps, and highlight future research directions. Particular emphasis is placed on the potential of ST2-related biomarkers for early detection, accurate diagnosis, and individualized management of post-transplant complications to improve transplant outcomes.
Revisione e prospettiva
Literature search strategy
A systematic literature search was conducted in PubMed from database inception through March 31, 2026. The search strategy combined Medical Subject Headings (MeSH) and free-text keywords related to the IL-33/ST2 axis and transplantation. The following search terms were used: ("IL-33" OR "interleukin-33" OR "ST2" OR "sST2" OR "ST2L" OR "suppression of tumorigenicity 2" OR "growth stimulation expressed gene 2") AND ("transplantation" OR "transplant" OR "graft" OR "allograft" OR "graft-versus-host disease" OR "GVHD" OR "rejection").
Two independent reviewers screened titles and abstracts, followed by full-text assessment of potentially eligible articles. Disagreements were resolved through discussion or consultation with a third reviewer. The inclusion criteria were: (1) original research articles, reviews, or meta-analyses investigating the role of the IL-33/ST2 axis in solid organ transplantation or allogeneic hematopoietic stem cell transplantation; (2) studies reporting clinical, experimental, or mechanistic outcomes related to ST2/sST2; and (3) articles published in English. The exclusion criteria were: (1) conference abstracts without full text; (2) studies not directly related to transplantation; and (3) duplicate publications.
A total of 91 records were identified, of which 90 were screened after duplicate removal. Following title and abstract screening, 60 full-text articles were assessed, and 57 studies were included in the review. Given the narrative nature of the review, no quantitative meta-analysis was performed.
1. ST2 and its ligand IL-33
Expression and distribution of ST2
The ST2 gene (IL1RL1) is located on human chromosome 2q12 and produces three main isoforms through alternative splicing: ST2L, sST2, and ST2V. ST2L is a membrane-bound receptor belonging to the Toll/IL-1R superfamily. Its intracellular domain is highly homologous to IL-1R1. The soluble isoform, sST2, lacks the transmembrane domain and retains the three extracellular immunoglobulin-like domains of ST2L but contains an additional nine amino acids at the C-terminus. This structure enables sST2 to be secreted into the extracellular space, where it functions as a decoy receptor. ST2V is another membrane-bound isoform containing only two immunoglobulin domains and a hydrophobic tail and is primarily expressed in intestinal tissues10.
ST2 expression in the immune system exhibits marked cell lineage specificity. Among T-cell subsets, ST2L was initially considered a specific marker of Th2 cells and was thought to be absent from Th1 cells11. Subsequent findings have demonstrated that ST2L is expressed not only on regulatory T cells (Tregs) but also on Th1 cells, CD8+ T cells, natural killer (NK) cells, and NKT cells12. In Tregs, ST2L expression contributes to the maintenance of immune tolerance13.
Among innate immune cells, mast cells exhibit particularly high ST2 expression. Studies of lung tissue from patients with chronic obstructive pulmonary disease (COPD) have identified mast cells as the predominant ST2 mRNA-expressing cells14. Basophils, eosinophils, dendritic cells, and macrophages also express ST2, although at relatively lower levels13.
Beyond immune cells, ST2 is widely expressed in nonimmune cell populations. In the cardiovascular system, cardiomyocytes and cardiac fibroblasts express ST2L, whereas sST2 has been extensively investigated as a clinical biomarker of heart failure15,16. In the respiratory system, bronchial epithelial cells, pulmonary vascular endothelial cells, and airway smooth muscle cells express ST2L and sST2 mRNA14. In the digestive system, gastric, small-intestinal, and colonic epithelial cells express ST2V, which may contribute to the maintenance of mucosal barrier function17.
The IL-33/ST2 signaling axis
Interleukin-33 (IL-33), a member of the IL-1 cytokine family, was initially identified as a nuclear protein in 1999 and subsequently confirmed as a functional ligand for ST2 in 200518. In barrier tissues, including the skin, lungs, and intestine, IL-33 is predominantly localized to the nuclei of epithelial and endothelial cells. Following tissue damage, cell necrosis, or cellular stress, IL-33 is released as an alarmin that signals tissue injury to the immune system18,19.
IL-33 binds to ST2 in association with the IL-1 receptor accessory protein (IL-1RAcP). Ligand binding induces a conformational change in ST2 and activates myeloid differentiation primary response protein 88 (MyD88). MyD88 recruits tumor necrosis factor receptor-associated factor 6 (TRAF6), which subsequently activates IL-1 receptor-associated kinase 1 (IRAK1) and IRAK4, thereby activating the mitogen-activated protein kinase (MAPK) pathway. Downstream effectors include extracellular signal-regulated kinases (ERKs), p38 MAPK, and c-Jun N-terminal kinase (JNK). In parallel, TRAF6 activates IκB kinase (IKK), resulting in phosphorylation and degradation of the NF-κB inhibitor, leading to the subsequent release of NF-κB. Additionally, the IL-33/ST2 axis modulates signal transducer and activator of transcription 3 (STAT3), STAT5, mammalian target of rapamycin (mTOR), and peptidyl-prolyl cis/trans isomerase NIMA-interacting protein 1–interleukin-1 receptor-associated kinase M, thereby promoting cytokine and chemokine production20.
The biological effects of the IL-33/ST2L signaling axis are pleiotropic and depend on the target cell type and immune microenvironment. In type 2 immunity, IL-33 activates ST2L-positive Th2 cells, group 2 innate lymphoid cells (ILC2s), eosinophils, and mast cells, promoting the production of IL-4, IL-5, and IL-13, which contribute to antiparasitic immunity, allergic responses, and tissue repair4,18,21. During regulatory immune responses, IL-33 promotes the expansion of ST2L-expressing Tregs, helping preserve immune tolerance and limit inflammatory damage22,23,24. In type 1 immunity, IL-33 enhances the expansion and effector functions of cytotoxic T lymphocytes (CTLs) and Th1 cells through inducible ST2L expression, thereby strengthening antiviral immunity25.
2. ST2 in transplantation
ST2 and lung transplantation
Foxp3+ cells residing within transplanted grafts are critical regulators of lung transplant tolerance. In lung allografts, IL-33-induced expansion of Foxp3+ cells is at least partially dependent on cell-surface ST2 expression. Airway administration of IL-33 attenuates antibody-mediated rejection and acute cellular rejection within the first seven days after transplantation26. In rat transplantation models, IL-33-dependent signaling facilitates lung allograft acceptance during ischemia-reperfusion injury by promoting eosinophil-mediated immune tolerance27. In tissues affected by chronic lung allograft dysfunction (CLAD), IL-33 expression is significantly upregulated and may activate type 2 inflammatory signaling pathways involved in disease progression through binding to its receptor, ST228.
ST2 and heart transplantation
During cardiac allograft rejection, serum soluble ST2 (sST2) concentrations increase and may predict acute cellular or antibody-mediated rejection29,30. Elevated donor sST2 concentrations are associated with graft dysfunction requiring extracorporeal membrane oxygenation (ECMO) support, whereas elevated postoperative sST2 concentrations in recipients correlate with in-hospital mortality31. Furthermore, sST2 may predict long-term mortality following orthotopic heart transplantation32.
Investigations into the mechanisms linking ST2 to transplant rejection have primarily focused on immune cells, particularly macrophages and T cells. In mice, recipient ST2 deficiency results in more severe graft vascular disease and fibrosis, accompanied by increased infiltration of F4/80+ macrophages and CD3+ T cells into the allograft. Conversely, ST2 deficiency within the graft reduces infiltration by F4/80+ macrophages, CD3+ T cells, and CD20+ B cells, thereby attenuating graft injury33.
IL-33 promotes Th2-type immune responses and improves cardiac allograft survival34. In a mouse model of cardiac xenotransplantation, IL-33 administration substantially improved graft survival, accompanied by enhanced Th2-type responses, reduced CD8+IFN-γ+ cell populations, and ST2-dependent expansion of CD4+Foxp3+ Tregs, including the ST2L+ subset. The therapeutic effects of IL-33 in heart transplantation depend on recipient ST2 expression, although ST2 expression is also upregulated in cardiomyocytes and endothelial cells during rejection35. Under chronic rejection conditions, IL-33 administration promotes Th2-type immune deviation, enhances myeloid-derived suppressor cell (MDSC) and Treg expansion, reduces antibody-mediated rejection (AMR), and improves allograft survival36.
Additionally, IL-33 can directly suppress the proinflammatory activity of graft-infiltrating macrophages during the early post-transplantation period. This effect involves metabolic reprogramming toward reparative and regulatory functions, thereby limiting the development of chronic rejection37.
ST2 and kidney transplantation
In kidney transplant recipients, soluble ST2 concentrations and IL-33/ST2 expression are higher in cases of acute antibody-mediated rejection (AAMR), acute cellular-mediated rejection (ACMR), and chronic antibody-mediated rejection (CAMR) than in controls38. Additionally, each twofold increase in ST2 concentration is associated with a 36% increase in the risk of all-cause mortality39.
Findings in kidney transplantation differ from those reported for several other transplant types, suggesting predominantly pathogenic effects of ST2 signaling. Expression of the proinflammatory cytokine IL-8 correlates with IL-33 and ST2 concentrations. In vivo findings indicate that anti-ST2 antibody treatment decreases IL-8 production in a dose-dependent manner and specifically inhibits the upregulation of mixed lymphocyte reactions38. Furthermore, IL-33 immunostaining is positive in renal tubules from patients with chronic allograft dysfunction, and IL-33 induces epithelial–mesenchymal transition (EMT) in HK-2 cells through time- and dose-dependent activation of p38 MAPK40.
Based on the available evidence, the proposed sequence linking IL-33 to chronic graft fibrosis in kidney transplantation involves tissue damage, IL-33 release from tubular epithelial cells, circulating sST2 accumulation, macrophage polarization toward a profibrotic phenotype, myofibroblast activation, and subsequent graft interstitial fibrosis38,40. However, this proposed mechanistic sequence remains incompletely validated and requires further investigation using cell-specific ST2 knockout and lineage-tracing approaches. Furthermore, invariant natural killer T (iNKT) cells, an innate-like T-cell subset regulated by IL-33, become activated within one hour after transplantation and contribute to ischemia-reperfusion injury (IRI)41.
ST2 and liver transplantation
In liver transplant recipients, elevated serum sST2 concentrations may reflect deterioration in renal and hepatic function42. Hepatic ischemia-reperfusion injury triggers IL-33 release, whereas eosinophils express ST2. This IL-33/ST2 signaling pathway contributes to eosinophil-dependent hepatoprotection and represents a potential therapeutic target for improving liver transplantation outcomes43.
ST2 and hematopoietic stem cell transplantation
The study by Vander Lugt et al. (2013), published in the New England Journal of Medicine, provided the first multicenter prospective validation of sST2 as a prognostic biomarker in allogeneic hematopoietic cell transplantation (allo-HCT)44. Plasma sST2 concentrations were measured at the initiation of graft-versus-host disease (GVHD) treatment in 403 patients. Patients with elevated sST2 concentrations at treatment initiation had a 2.3-fold higher risk of developing treatment-refractory GVHD and a 3.7-fold higher risk of death within six months, independent of established clinical risk factors. The study also demonstrated that sST2 concentrations on day 14 after transplantation correlated with six-month non-relapse mortality. These findings established a rationale for incorporating sST2 into risk-adapted GVHD treatment algorithms and were subsequently validated in pediatric and cord blood transplantation cohorts6,7,45. However, whether sST2-guided treatment decisions improve patient outcomes remains to be determined through prospective interventional trials.
Importantly, sST2 concentrations are also elevated in patients with infections, thrombotic microangiopathy, veno-occlusive disease, and other life-threatening post-transplantation complications46. Consequently, the specificity of sST2 for rejection or GVHD is limited, and elevated concentrations should not be interpreted as definitive evidence of immune-mediated rejection without clinical correlation. Moreover, prognostic value must be distinguished from clinical utility, as prospective interventional trials have not yet established whether sST2-guided treatment improves patient outcomes.
Studies investigating ST2 in hematopoietic cell transplantation have produced conflicting findings, suggesting both protective and pathogenic roles. In peripheral blood stem cell transplantation, IL-33 administration expands ST2-expressing Tregs through a MAPK-dependent mechanism, thereby preventing acute GVHD (aGVHD)47. ST2+ Tregs expand from donor-derived thymic Tregs (tTregs) following allo-HCT and are predominantly distributed within aGVHD target organs, including the intestine and liver. Activation of the ST2/IL-33 pathway in Tregs prevents severe aGVHD48.
Conversely, several studies have reported opposing effects. In vitro findings indicate that the ST2 inhibitor XY52 suppresses proinflammatory T-cell proliferation while expanding Treg populations. In a clinically relevant GVHD model, a 21-day prophylactic course of XY52 reduced plasma sST2 and interferon-gamma (IFN-γ) concentrations, improved GVHD scores, and prolonged survival49. Disruption of ST2/MyD88 signaling protects mice against lethal aGVHD by reducing sST2 production from conventional T cells while preserving Treg function50. Additionally, IL-33 can induce T-bet expression independently of IL-12 and facilitate the differentiation of Th1 cells that infiltrate GVHD target organs51.
In IL-33 knockout (Il33−/−) recipient mice, GVHD-associated mortality and tumor necrosis factor-alpha (TNF-α) production are markedly reduced. ST2 expression increases in both murine and human alloreactive T cells, whereas sST2 concentrations rise during experimental GVHD progression. Accordingly, ST2 knockout (Il1rl1−/−) donor T cells induce substantially lower GVHD-associated mortality and less gastrointestinal histopathological injury than wild-type donor T cells. Administration of an exogenous ST2-Fc fusion protein to block IL-33/ST2 interactions during allogeneic hematopoietic cell transplantation markedly reduces GVHD-associated mortality52.
Administration of a neutralizing anti-ST2 monoclonal antibody (anti-ST2 mAb) before transplantation also attenuates GVHD severity and mortality. ST2 blockade decreases systemic concentrations of IFN-γ, IL-17, and IL-23, while increasing plasma concentrations of IL-10 and IL-33. Furthermore, ST2 blockade reduces sST2 production by IL-17-producing T cells while preserving protective ST2L-expressing T cells, increases the proportion of intestinal MDSCs, and decreases the proportion of intestinal CD103+ dendritic cells5.
ST2 and skin transplantation
In skin transplantation models, IL-33 stimulates CD4+ T-cell expansion and promotes the conversion of peripheral CD4+Foxp3− T cells into CD4+Foxp3+ Tregs, thereby establishing an anti-inflammatory microenvironment53. Exogenous IL-33 treatment generally reduces the expression of genes associated with T-cell biology while increasing Treg-associated gene expression. These Tregs exhibit potent suppressive activity in vivo and support long-term skin allograft survival in stringent experimental models54. Conversely, recipient ST2 expression exacerbates graft injury by facilitating the infiltration of multiple immune cell populations into skin allografts, thereby promoting the onset and progression of chronic rejection.
3. Comparative analysis of the IL-33/ST2 axis across transplant types
The role of the IL-33/ST2 axis varies substantially across transplant types, reflecting tissue-specific differences in innate immune cell composition, ST2 isoform expression, and the severity of IRI. Table 1 summarizes the principal findings across transplant types.
Protective versus pathogenic effects across organs
In heart and lung transplantation, the IL-33/ST2 axis predominantly exerts protective effects. IL-33 administration expands ST2L-positive Tregs and ILC2s, promotes Th2-type immune deviation, and prolongs allograft survival in murine models34,35. In lung transplantation, IL-33 released during IRI promotes eosinophil-mediated tolerance and improves graft acceptance27.
In kidney transplantation, however, the axis appears predominantly pathogenic. Soluble ST2 concentrations and IL-33/ST2 expression are elevated during acute and chronic antibody-mediated rejection, whereas IL-33 promotes EMT in renal tubular cells through p38 MAPK signaling38,40.
In liver transplantation, the IL-33/ST2 axis exerts protective effects during hepatic IRI through eosinophil-dependent IL-13 production43. In allo-HCT, findings are more complex and sometimes contradictory, depending on the experimental model, intervention timing, and IL-33 dosage.
Factors underlying the opposing effects of IL-33/ST2 signaling
Several factors may explain the context-dependent outcomes of IL-33/ST2 signaling.
Tissue-specific innate immune cell composition: The relative abundance of ILC2s, eosinophils, mast cells, and macrophages varies across organs. In the heart and lungs, ILC2s and eosinophils are abundant and responsive to IL-33, favoring type 2 immunity and immune tolerance. In the kidneys, tubular epithelial cells and infiltrating macrophages predominate, and IL-33 promotes EMT and fibrosis rather than tolerance.
Differential expression of ST2 isoforms: ST2L is expressed on cardiomyocytes, cardiac fibroblasts, and bronchial epithelial cells, where it mediates protective signaling. In renal tubular cells, sST2 is preferentially upregulated during injury and functions as a decoy receptor that blocks IL-33/ST2L signaling and amplifies inflammation.
Donor versus recipient expression: In cardiac transplantation, recipient ST2 deficiency exacerbates graft vascular disease, whereas graft ST2 deficiency attenuates injury33. These compartment-specific effects indicate that the cellular source of ST2, whether donor- or recipient-derived, critically influences transplantation outcomes.
Timing and dosage of intervention: In allo-HCT, IL-33 administration before transplantation expands ST2+ Tregs and prevents aGVHD, whereas administration during ongoing GVHD may promote Th1 differentiation and exacerbate disease48,52. Similarly, ST2 blockade before transplantation reduces GVHD severity, whereas intervention at other time points may impair protective Treg function5,50.
Degree of ischemia-reperfusion injury: IRI is a potent stimulus for IL-33 release. In lung and liver transplantation, IRI-induced IL-33 predominantly activates eosinophils and ILC2s, promoting immune tolerance. In kidney transplantation, IRI-induced IL-33 activates NKT cells and contributes to tubular injury within the first hour after transplantation41.
Evidence stratification and clinical predictive metrics
Evidence supporting the role of the IL-33/ST2 axis in transplantation can be categorized into three levels.
Level 1: Preclinical animal models. Most mechanistic evidence derives from murine heart, lung, kidney, and skin transplantation models, as well as experimental GVHD models27,33,34,35,36,37,43,47,48,49,50,51,52,53,54. These studies establish causal relationships between IL-33/ST2 signaling and graft outcomes through genetic deletion, neutralizing antibodies, or recombinant protein administration. However, species-specific differences in ST2 isoform expression and immune cell composition limit direct translation to humans.
Level 2: Single-center observational cohorts. Several single-center studies have reported associations between circulating sST2 concentrations and clinical outcomes in kidney, heart, and liver transplantation31,32,38,39,42. These studies provide hypothesis-generating evidence but are limited by relatively small sample sizes, heterogeneous assay methods, and insufficient external validation.
Level 3: Multicenter studies or phase III clinical trials. The strongest clinical evidence derives from multicenter studies in allo-HCT, including the study by Vander Lugt et al., published in the New England Journal of Medicine, which validated sST2 as a biomarker of treatment-refractory GVHD and six-month nonrelapse mortality44. A multicenter phase III trial involving patients with uniform transplantation characteristics further confirmed the prognostic value of plasma biomarkers, including sST28.
Table 2 summarizes reported sST2 cutoff values, sampling windows, assay methods, and adjusted effect sizes, including hazard ratios (HRs), odds ratios (ORs), and areas under the receiver operating characteristic curve (AUCs), across transplant types. Cutoff values vary considerably among studies, reflecting differences in assay platforms and patient populations. External validation in independent cohorts remains limited for most solid organ transplantation settings.
Comparison of sST2 with dd-cfDNA and DSA and the potential for multimarker panels
The clinical utility of sST2 should be evaluated alongside two established biomarkers: donor-derived cell-free DNA (dd-cfDNA) and donor-specific antibodies (DSA). Each biomarker reflects a distinct aspect of graft injury. Table 3 compares the characteristics of these three biomarkers.
In kidney transplantation, combining DSA and dd-cfDNA to identify AMR achieved 80.0% sensitivity and 90.7% specificity, outperforming either biomarker alone55. dd-cfDNA-guided biopsy reduced the time to AMR diagnosis from 14.5 to 2.8 months56. In heart transplantation, dd-cfDNA provided additional information beyond DSA status. Among DSA-positive patients, AMR incidence was 1.4% when dd-cfDNA concentrations were below 0.20%, compared with 15.5% when concentrations were at least 0.50%57.
However, chronic graft fibrosis may progress without elevated dd-cfDNA concentrations or detectable DSA. DSA testing cannot identify DSA-negative antibody-mediated rejection (ABMR), and dd-cfDNA has limited utility in GVHD. Because sST2 reflects dysregulation of the IL-33/ST2 axis and is associated with fibrosis, it may complement these established biomarkers. Nevertheless, no prospective study has evaluated the combined diagnostic or prognostic performance of sST2, dd-cfDNA, and DSA. Future investigations should determine whether multimarker panels improve risk stratification for chronic rejection and DSA-negative ABMR.
Future directions
Therapeutic interventions targeting the ST2 pathway have not yet entered clinical practice in transplantation. Strategies targeting the IL-33/ST2 axis should be distinguished according to the specific pathway components affected, as different interventions have distinct mechanistic consequences.
Recombinant IL-33: Recombinant IL-33 provides an exogenous ligand that activates ST2L on Tregs, ILC2s, and Th2 cells, thereby promoting immune tolerance. However, in allo-HCT, IL-33 administration during ongoing GVHD may promote Th1 differentiation and exacerbate disease. These findings demonstrate that the same intervention may exert protective or pathogenic effects depending on timing and biological context.
ST2-Fc fusion proteins: ST2-Fc fusion proteins function as decoy receptors that neutralize circulating IL-33, thereby inhibiting IL-33 availability for ST2L-mediated signaling and altering the effects associated with soluble ST2.
Anti-ST2 monoclonal antibodies: These may be designed to target either sST2 or ST2L. Selective sST2 blockade may preserve ST2L-mediated Treg function while reducing pathogenic effects associated with sST2.
Genetic ST2 deletion: Genetic deletion of ST2 eliminates both soluble and membrane-bound isoforms, complicating the attribution of observed biological effects to individual isoforms.
A major unresolved question is whether interventions intended to enhance regulatory immune responses may simultaneously affect pathogenic effector responses in different cellular or temporal contexts. Future therapeutic development should therefore specify the targeted isoform (sST2 or ST2L), the targeted compartment (donor or recipient), and the timing of intervention (before transplantation or during rejection). Both soluble and membrane-bound ST2 expression should also be monitored.
Given the immunomodulatory properties of the IL-33/ST2 axis, future investigations should evaluate recombinant IL-33 and ST2 agonists as potential adjunctive therapies for inducing transplant immune tolerance. These approaches may promote Treg and ILC2 expansion and potentially reduce dependence on long-term immunosuppressive treatment.
Conclusioni
Current evidence supports ST2, particularly sST2, as a prognostic biomarker following heart transplantation and indicates its potential predictive value in kidney, lung, and liver transplantation. As a receptor for IL-33, ST2 functions as an important immunomodulatory component in solid organ and hematopoietic stem cell transplantation, as illustrated in Figure 1.
Available evidence indicates that IL-33/ST2 signaling exerts context-dependent regulatory effects rather than uniformly protective or pathogenic actions. ST2L-mediated signaling in ILC2s, Tregs, and Th2 cells promotes immune tolerance and attenuates rejection. Conversely, sST2 functions as a decoy receptor, and persistently elevated circulating concentrations reflect the severity of tissue injury and are associated with acute rejection, post-transplantation complications, and graft failure.
The overall effects of the IL-33/ST2 axis depend on tissue-specific innate immune cell composition, differential ST2 isoform expression, donor versus recipient compartment, intervention timing and dosage, and the severity of IRI. Important knowledge gaps remain, including the absence of prospective studies evaluating the combined diagnostic or prognostic performance of sST2 with established biomarkers such as dd-cfDNA and DSA, and the lack of interventional trials investigating whether sST2-guided treatment improves patient outcomes. Addressing these gaps may facilitate the clinical translation of IL-33/ST2-targeted strategies and improve long-term transplantation outcomes.
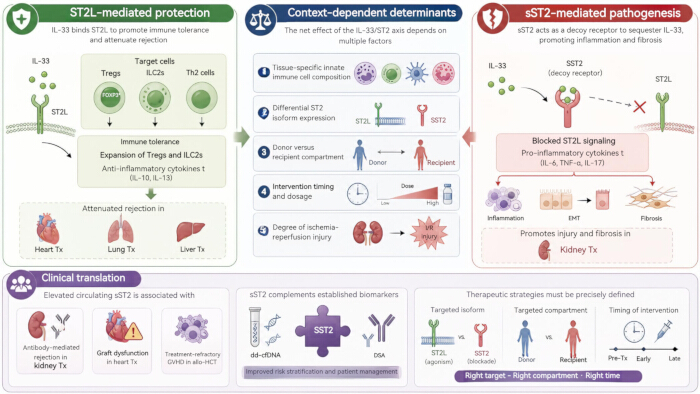
Figure 1: Context-dependent roles of the IL-33/ST2 axis in transplantation. The IL-33/ST2 axis exerts bidirectional and transplant-specific effects. Left panel (ST2L-mediated protection): IL-33 binds to membrane-bound ST2L on Tregs, ILC2s, and Th2 cells, promoting immune tolerance, expanding Tregs and ILC2s, and attenuating rejection in heart, lung, and liver transplantation. Right panel (sST2-mediated pathogenesis): Soluble sST2 acts as a decoy receptor that sequesters IL-33, blocking ST2L-mediated protective signaling and promoting inflammation, epithelial-mesenchymal transition (EMT), and fibrosis in kidney transplantation. Central panel (context-dependent determinants): The net effect of the IL-33/ST2 axis depends on five factors: (1) tissue-specific innate immune cell composition; (2) differential ST2 isoform expression; (3) donor versus recipient compartment; (4) intervention timing and dosage; and (5) degree of ischemia-reperfusion injury. Bottom panel (clinical translation): Elevated circulating sST2 is associated with antibody-mediated rejection in kidney transplantation, graft dysfunction in heart transplantation, and treatment-refractory GVHD in allo-HCT. sST2 may complement established biomarkers such as dd-cfDNA and DSA. Therapeutic strategies targeting the IL-33/ST2 axis must specify the targeted isoform (sST2 vs. ST2L), the targeted compartment (donor vs. recipient), and the timing of intervention. Please click here to view a larger version of this figure.
Table 1: Comparative roles of the IL-33/ST2 axis across transplant types. Summary of experimental models, target cells, intervention timing, and outcomes associated with IL-33/ST2 signaling in different transplantation settings. Please click here to download this Table.
Table 2: Clinical predictive performance of soluble ST2 across transplant types. Summary of study designs, sampling windows, assay methods, reported cutoff values, adjusted effect sizes, and clinical outcomes. Please click here to download this Table.
Table 3: Comparison of sST2, DSA, and dd-cfDNA as transplantation biomarkers. Overview of the biological processes reflected by each biomarker, along with their respective strengths and limitations. Please click here to download this Table.
Dichiarazioni
The authors declare no conflicts of interest. This research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors. All authors have reviewed and approved the final manuscript.
Riferimenti
- Peng ZH, et al. The development history of organ transplantation in China: from clinical exploration to construction and innovation of a standardized system. Chin J Exp Surg. 2025;42(6):989–992.
- Kang H, Cho SI, Oh EJ. Donor-derived cell-free DNA in solid organ transplantation: analytical considerations, diagnostic performance, and clinical interpretation. Clin Transplant Res. 2025;39(3):200–213.
- Dwyer GK, D'Cruz LM, Turnquist HR. Emerging functions of IL-33 in homeostasis and immunity. Annu Rev Immunol. 2022;40(1):15–43.
- Zhang J, et al. ST2 blockade reduces sST2-producing T cells while maintaining protective mST2-expressing T cells during graft-versus-host disease. Sci Transl Med. 2015;7(308):308ra160.
- Paczesny S. Post-haematopoietic cell transplantation outcomes: why ST2 became a 'golden nugget' biomarker. Br J Haematol. 2021;192(6):951–967.
- Rowan CM, et al. Assessment of ST2 for risk of death following graft-versus-host disease in pediatric and adult age groups. Blood. 2020;135(17):1428–1437.
- Ponce DM, et al. High day 28 ST2 levels predict for acute graft-versus-host disease and transplant-related mortality after cord blood transplantation. Blood. 2015;125(1):199–205.
- Abu Zaid M, et al. Plasma biomarkers of risk for death in a multicenter phase 3 trial with uniform transplant characteristics post-allogeneic HCT. Blood. 2017;129(2):162–170.
- Rowan CM, et al. Early high plasma ST2, the decoy IL-33 receptor, in children undergoing hematopoietic cell transplantation is associated with the development of post-transplant diabetes mellitus. Haematologica. 2020;105(5):e249–e252.
- Kakkar R, Lee RT. The IL-33/ST2 pathway: therapeutic target and novel biomarker. Nat Rev Drug Discov. 2008;7(10):827–840.
- Trajkovic V, Sweet MJ, Xu D. T1/ST2—an IL-1 receptor-like modulator of immune responses. Cytokine Growth Factor Rev. 2004;15(2):87–95.
- Liew FY, Girard JP, Turnquist HR. Interleukin-33 in health and disease. Nat Rev Immunol. 2016;16(11):676–689.
- Zhou Y, Xu Z, Liu Z. Role of IL-33-ST2 pathway in regulating inflammation: current evidence and future perspectives. J Transl Med. 2023;21:902.
- Sanden C, et al. Altered site-specific expression patterns of interleukin-33 and its receptor ST2 in COPD lungs. Eur Respir J. 2022;60(Suppl 66):2119. https://doi.org/10.1183/13993003.congress-2022.2119
- Weinberg EO, et al. Expression and regulation of ST2, an interleukin-1 receptor family member, in cardiomyocytes and myocardial infarction. Circulation. 2002;106(23):2961–2966.
- Bartunek J, et al. Non-myocardial production of ST2 protein in human hypertrophy and failure is related to diastolic load. J Am Coll Cardiol. 2008;52(25):2166–2174.
- Tago K, et al. Tissue distribution and subcellular localization of a variant form of the human ST2 gene product, ST2V. Biochem Biophys Res Commun. 2001;285(5):1377–1383.
- Sheng F, et al. IL-33/ST2 axis in diverse diseases: regulatory mechanisms and therapeutic potential. Front Immunol. 2025;16:1533335.
- He PY, et al. Interleukin-33/serum stimulation-2 pathway: regulatory mechanisms and emerging implications in immune and inflammatory diseases. Cytokine Growth Factor Rev. 2024;76:112–126.
- Yang YE, et al. IL-33/NF-κB/ST2L/Rab37 positive-feedback loop promotes M2 macrophage to limit chemotherapeutic efficacy in lung cancer. Cell Death Dis. 2024;15(5):356.
- Okano M, et al. Interleukin-33-activated neuropeptide CGRP-producing memory Th2 cells cooperate with somatosensory neurons to induce conjunctival itch. Immunity. 2022;55(12):2352–2368.e7.
- Nascimento DC, et al. IL-33 contributes to sepsis-induced long-term immunosuppression by expanding the regulatory T cell population. Nat Commun. 2017;8:14919.
- Griffith JW, et al. Regulatory T cell-derived IL-1Ra suppresses the innate response to respiratory viral infection. Nat Immunol. 2023;24(12):2091–2107.
- Sabapathy V, et al. ST2+ T-regulatory cells in renal inflammation and fibrosis after ischemic kidney injury. J Am Soc Nephrol. 2025;36(1):73.
- Brunner TM, et al. A type 1 immunity-restricted promoter of the IL-33 receptor gene directs antiviral T-cell responses. Nat Immunol. 2024;25(2):256–267.
- Li W, et al. Maintenance of graft tissue-resident Foxp3+ cells is necessary for lung transplant tolerance in mice. J Clin Invest. 2025;135(10):e178975.
- Guo Y, et al. Ischemia reperfusion injury facilitates lung allograft acceptance through IL-33 mediated activation of donor-derived IL-5 producing group 2 innate lymphoid cells. Am J Transplant. 2022;22(8):1963–1975.
- Todd JL, et al. BAL fluid eosinophilia associates with chronic lung allograft dysfunction risk: a multicenter study. Chest. 2023;164(3):670–681.
- Mathews LR, et al. Elevated ST2 distinguishes incidences of pediatric heart and small bowel transplant rejection. Am J Transplant. 2016;16(3):938–950.
- Pascual-Figal DA, et al. Soluble ST2 is a marker for acute cardiac allograft rejection. Ann Thorac Surg. 2011;92(6):2118–2124.
- Galeone A, et al. Suppression of tumorigenicity-2 (ST2) is a promising biomarker in heart transplantation. Clin Transplant. 2022;36(5):e14616.
- Januzzi JL, et al. Interleukin receptor family member ST2 concentrations in patients following heart transplantation. Biomarkers. 2013;18(3):250–256.
- Zhang Z, et al. Allograft or recipient ST2 deficiency oppositely affected cardiac allograft vasculopathy via differentially altering immune cells infiltration. Front Immunol. 2021;12:657803.
- Yin H, et al. IL-33 prolongs murine cardiac allograft survival through induction of TH2-type immune deviation. Transplantation. 2010;89(10):1189–1197.
- Turnquist HR, et al. IL-33 expands suppressive CD11b+ Gr-1int and regulatory T cells (Treg), including ST2L+ Foxp3+ cells, and mediates Treg-dependent promotion of cardiac allograft survival. J Immunol. 2011;187(9):4598–4610.
- Brunner SM, et al. Interleukin-33 prolongs allograft survival during chronic cardiac rejection. Transpl Int. 2011;24(10):1027–1039.
- Li T, et al. Graft IL-33 regulates infiltrating macrophages to protect against chronic rejection. J Clin Invest. 2020;130(10):5397–5412.
- Yu MY, et al. Role of the IL-33/ST2 pathway in renal allograft rejection. Exp Cell Res. 2021;405(2):112705.
- Devine PA, Cardwell C, Maxwell AP. Association of soluble ST2 with all-cause and cardiovascular mortality in renal transplant recipients: a single-centre cohort study. BMC Nephrol. 2020;21:22.
- Xu Z, et al. Interleukin-33 levels are elevated in chronic allograft dysfunction of kidney transplant recipients and promotes epithelial to mesenchymal transition of human kidney (HK-2) cells. Gene. 2018;644:113–121.
- Thierry A, et al. The alarmin concept applied to human renal transplantation: evidence for a differential implication of HMGB1 and IL-33. PLoS One. 2014;9(2):e88742.
- Moon JJ, et al. Soluble suppression of tumorigenicity 2 is a potential predictor of post-liver transplant renal outcomes. PLoS One. 2023;18(11):e0293844.
- Wang Y, et al. Eosinophils attenuate hepatic ischemia-reperfusion injury in mice through ST2-dependent IL-13 production. Sci Transl Med. 2021;13(579):eabb6576.
- Vander Lugt MT, et al. ST2 as a marker for risk of therapy-resistant graft-versus-host disease and death. N Engl J Med. 2013;369(6):529–539.
- Cuvelier GDE, et al. Age related differences in the biology of chronic graft-versus-host disease after hematopoietic stem cell transplantation. Front Immunol. 2020;11:571884.
- Matsumura A, et al. Predictive values of early suppression of tumorigenicity 2 for acute GVHD and transplant-related complications after allogeneic stem cell transplantation: prospective observational study. Turk J Haematol. 2020;37(1):20–29.
- Matta BM, et al. Peri-alloHCT IL-33 administration expands recipient T-regulatory cells that protect mice against acute GVHD. Blood. 2016;128(3):427–439.
- Yang J, et al. Rorc restrains the potency of ST2+ regulatory T cells in ameliorating intestinal graft-versus-host disease. JCI Insight. 2019;4(5):e122014.
- Yuan X, et al. Prophylactic mitigation of acute graft versus host disease by novel 2-(pyrrolidin-1-ylmethyl)pyrrole-based stimulation-2 (ST2) inhibitors. ACS Pharmacol Transl Sci. 2023;6(9):1275–1287.
- Griesenauer B, et al. ST2/MyD88 deficiency protects mice against aGVHD and spares T-regulatory cells. J Immunol. 2019;202(10):3053–3064.
- Dwyer GK, et al. IL-33 acts as a costimulatory signal to generate alloreactive Th1 cells in graft-versus-host disease. J Clin Invest. 2022;132(12):e150927.
- Reichenbach DK, et al. The IL-33/ST2 axis augments effector T-cell responses during acute GVHD. Blood. 2015;125(20):3183–3192.
- Gajardo T, et al. Exogenous interleukin-33 targets myeloid-derived suppressor cells and generates periphery-induced Foxp3+ regulatory T cells in skin-transplanted mice. Immunology. 2015;146(1):81–88.
- Kawai K, et al. IL-33 drives the production of mouse regulatory T cells with enhanced in vivo suppressive activity in skin transplantation. Am J Transplant. 2021;21(3):978–992.
- Kim HD, et al. Donor-derived cell-free DNA predicted allograft rejection and severe microvascular inflammation in kidney transplant recipients. Front Immunol. 2024;15:1433918.
- Akifova A, et al. Donor-derived cell-free DNA monitoring for early diagnosis of antibody-mediated rejection after kidney transplantation: a randomized trial. Nephrol Dial Transplant. 2025;40(7):1384–1395.
- Kim PJ, et al. Donor-derived cell-free DNA in antibody-mediated rejection: an analysis of the Surveillance HeartCare Outcomes Registry. JACC Heart Fail. 2026;14(1):102716.