This review synthesizes current knowledge on radiation-induced esophagitis across epidemiology, pathophysiology, diagnosis, risk stratification, predictive modeling, and management and proposes a precision-management research agenda for this dose-limiting toxicity.
Articolo di revisione
Radiation-Induced Esophagitis: From Clinical Observation to Precision Management
* These authors contributed equally
In questo articolo
Sommario
Abstract
For the past seven decades, radiation-induced esophagitis (RE) has been a major dose-limiting acute toxicity of thoracic radiotherapy, substantially impairing patients' quality of life and their ability to complete planned treatment courses. Research on RE has progressed from phenomenological reporting to multidimensional quantification and, more recently, toward precision-driven intervention. This review provides a comprehensive overview of current research on the epidemiology, pathophysiology, diagnosis, risk stratification, predictive modeling, prevention, and treatment of radiation-induced esophagitis. Dose–volume parameters established an important quantitative framework for risk assessment, while more recent advances in genomic profiling, functional imaging, and artificial intelligence have supported the development of integrative multi-omics predictive models. Pharmacological prophylaxis has shown limited success in randomized trials, whereas technical refinements in radiation delivery and emerging regenerative approaches offer promising alternatives. Persistent knowledge gaps remain, including the need for prospective multicenter validation of omics-derived models, re-evaluation of RE risk in the immunotherapy era, investigation of chronomodulated treatment scheduling, and translation of tissue-engineering strategies into clinical practice. The review is intended to provide clinicians and investigators with a comprehensive reference and to support future research in thoracic radiation oncology.
Introduzione
Among the spectrum of normal-tissue complications arising from thoracic irradiation for malignancies such as lung cancer, esophageal carcinoma, breast cancer, and mediastinal lymphomas, radiation-induced esophagitis (RE) remains one of the most frequently encountered and clinically consequential acute toxicities, particularly in patients receiving concurrent chemoradiotherapy1,2,3. It is important to distinguish clinical toxicity assessment from risk prediction. Clinical toxicity assessment grades the severity of esophagitis that has already occurred using standardized systems such as the Common Terminology Criteria for Adverse Events (CTCAE) or the Radiation Therapy Oncology Group (RTOG) criteria. In contrast, risk prediction estimates the probability of RE before or during treatment using dosimetric, biological, and imaging data4,5. The former guides acute symptom management and treatment modification, whereas the latter informs pretreatment planning and patient selection. In patients with locally advanced non-small cell lung cancer (NSCLC) receiving concurrent chemoradiotherapy, acute RE remains a frequent toxicity affecting a substantial proportion of patients4. However, its clinical impact extends well beyond the cardinal symptoms of odynophagia, dysphagia, and retrosternal discomfort6. Patients may experience debilitating weight loss, a marked deterioration in quality of life, and unplanned treatment interruptions or dose attenuations that may ultimately erode locoregional tumor control and compromise overall survival7,8.
The history of RE research reflects the broader evolution of radiation oncology. The field has progressed through phases of empirical observation, mechanistic inquiry, and quantitative dosimetric-biological integration. Early scoring systems were limited in granularity, whereas contemporary practice has been complemented by predictive algorithms incorporating dosimetric, biological, and imaging data. The clinical adoption of three-dimensional conformal radiotherapy and intensity-modulated techniques enabled the systematic exploration of dose–volume relationships4,5. In parallel, advances in genomics9,10,11,12, functional imaging13,14,15,16, and artificial intelligence17,18,19 have collectively supported the development of multi-omic prognostic frameworks. Meanwhile, the failure of multiple pharmacological interventions in well-conducted randomized trials20,21,22,23 has redirected interest toward technical optimization and biologically restorative strategies24,25,26.
This review synthesizes current knowledge on radiation-induced esophagitis across epidemiology, pathophysiology, diagnosis, risk factors, predictive modeling, and management to provide a comprehensive resource for clinicians and researchers. It also highlights key knowledge gaps and outlines future research priorities aimed at advancing precision management of this treatment-limiting toxicity.
Revisione e prospettiva
1. Epidemiology
The incidence and severity of radiation-induced esophagitis (RE) are determined by a multifactorial interplay of tumor site, treatment intent, systemic therapy, radiation dose, and fractionation schedule, with additional variability introduced by the grading system used for toxicity assessment1,2,3,4. This multifactorial dependence explains the wide range of reported RE rates and underscores the importance of interpreting epidemiological data within their clinical context. In a large prospective consortium study of 1,760 patients with stage II–III non-small cell lung cancer (NSCLC) treated with definitive radiotherapy with or without chemotherapy, the overall rate of acute grade 2 or higher esophagitis was 48.4%, with grade 3 esophagitis occurring in 2.2%4. Among patients receiving concurrent chemotherapy, a mean esophageal dose (MED) of 22 Gy corresponded to a 50% risk of grade 2 or higher RE, whereas a MED of 29 Gy and a minimum dose to the hottest 2 cm3 of the esophagus (D2cc) of 61 Gy corresponded to a 3% risk of grade 3 or higher RE4.
For esophageal squamous cell carcinoma receiving concurrent chemoradiotherapy, the incidence of grade 2 or higher acute RE ranges from 59.6% to 63.9%27,28. High-dose radiotherapy to 60 Gy was associated with a trend toward increased grade 2–3 acute esophagitis compared with standard-dose regimens, with rates of 37.4% and 27.9%, respectively28. In patients with breast cancer undergoing regional nodal irradiation (RNI), grade 2 or higher RE occurs in 16.2%–23.7% of cases29,30,31. Intensity-modulated radiotherapy (IMRT) was associated with higher rates than three-dimensional conformal radiotherapy (3DCRT; 23.6% vs. 10.9%)29. Among patients receiving supraclavicular field irradiation, grade 2 or higher RE reached 48% when the mean cervical esophageal dose exceeded 13 Gy32.
The higher esophagitis rate observed with IMRT in breast RNI likely reflects its specific dosimetric characteristics. Unlike 3DCRT, which typically uses anterior-posterior supraclavicular and tangential chest wall fields, IMRT employs multiple beam angles to improve target coverage and dose homogeneity, thereby expanding the low-to-intermediate dose bath (e.g., V10–V20) to the cervical esophagus adjacent to the supraclavicular and level III–IV axillary nodal regions29. A systematic review of esophageal doses across breast radiotherapy regimens found that MEDs exceeded 10 Gy for IMRT-based nodal irradiation and were lower with other nodal techniques33. This trade-off provides a plausible explanation for the observed association.
In contrast, IMRT can have a more favorable toxicity profile in other thoracic malignancies. In the PROACTIVE phase 3 trial, esophageal-sparing IMRT (ES-IMRT) reduced symptomatic esophagitis from 24% to 2% in patients receiving palliative thoracic radiotherapy34. The differing effects in breast RNI and NSCLC likely reflect the anatomical relationship between the target and esophagus. In breast RNI, the cervical esophagus is adjacent to the supraclavicular target, whereas inverse planning in NSCLC can more readily reduce esophageal dose while maintaining target coverage.
In limited-stage small-cell lung cancer, twice-daily radiotherapy to 45 Gy does not appear to exacerbate severe esophagitis compared with once-daily regimens; reported rates of grade 3 or higher RE range from 5.8% to 13.2%35,36. An analysis of the US National Inpatient Sample from 2005–2016, encompassing 443 million weighted hospitalizations, identified 482,525 cases attributed to radiotherapy complications, of which RE accounted for 3.5%. These episodes had a median length of stay of 4.1 days and a median charge of $10,097 per patient, with cumulative national costs reaching $4.9 billion37. However, these data may not fully reflect the contemporary economic burden of RE because thoracic radiotherapy and supportive care have subsequently evolved. The widespread adoption of IMRT and proton therapy, the emergence of immune checkpoint inhibitors, and increasing use of hypofractionated and stereotactic regimens have altered the treatment landscape. The 2005–2016 data should therefore be interpreted as a historical benchmark rather than a direct estimate of current RE-related costs.
For centrally and ultracentrally located thoracic lesions, stereotactic body radiotherapy (SBRT) and hypofractionated regimens have distinct toxicity profiles. The HILUS trial, a prospective evaluation of SBRT for ultracentral tumors, reported grade 3 or higher toxicity in 34% of patients and grade 5 events in 15%, predominantly bronchopulmonary hemorrhage, with esophageal Dmax constrained to <41.6 Gy38. In contrast, the SUNSET trial, using a more protracted schedule, reported grade 3 or higher toxicity of approximately 10%, with proposed esophageal constraints of Dmax <50 Gy and V40 <1 cc39. A systematic review by the International Association for the Study of Lung Cancer Advanced Radiation Technology Subcommittee identified grade 3 or higher esophagitis rates of 0%–8% in prospective studies of definitive accelerated hypofractionation without concurrent chemotherapy and 0%–23.5% in studies incorporating concurrent chemotherapy40. These findings indicate that toxicity is highly schedule-dependent and support caution when accelerated hypofractionation is combined with chemotherapy or targeted agents40.
2. Pathophysiology
Ionizing radiation induces double- and single-strand DNA breaks in esophageal epithelial cells, triggering programmed cell death. Radiolysis of water simultaneously generates reactive oxygen species and oxidative stress41. Damaged epithelium releases pro-inflammatory cytokines, including tumor necrosis factor-alpha, interleukin-1 beta, interleukin-6, and interleukin-8, recruiting neutrophils, macrophages, and T cells and establishing an inflammatory cascade11. Animal models and human histopathology demonstrate a characteristic temporal sequence41. During the necrotic phase, which spans the radiotherapy period and first post-treatment week, basal cell proliferation ceases, epithelial thinning and denudation develop, and submucosal edema and inflammatory infiltration occur. The ulcerative phase, one to four weeks after irradiation, is characterized by epithelial necrosis, erosion or overt ulceration, and occasional pseudomembrane formation. The subsequent reparative and fibrotic phase, developing over months to years, involves basal-cell regeneration, fibroblast activation, collagen deposition, and potential stricture formation.
Transforming growth factor-beta 1 (TGF-β1) is a central mediator of radiation-induced fibrosis, promoting fibroblast proliferation and extracellular matrix accumulation. TGFB1 polymorphisms, particularly rs1800469 C-509T, have been associated with RE risk12,42. Carriers of CT or TT genotypes have an increased likelihood of grade 3 or higher RE. The HSPB1 rs7459185 CC genotype has likewise been associated with severe RE, with a reported hazard ratio of 17.739. The CXCR4 pathway is a potential therapeutic and diagnostic target in preclinical models, although its clinical efficacy and diagnostic utility have not been validated prospectively in humans. CXCR4 upregulation has been demonstrated in experimental RE models and clinical specimens, with CXCR4-positive neutrophils and monocytes identified as principal sources of radiotracer uptake. Pharmacological blockade with AMD3100 attenuated RE severity in vivo14. However, no CXCR4-targeted therapeutic or imaging agent has entered prospective clinical trials for RE, and these strategies should currently be regarded as hypothesis-generating rather than practice-changing.
Radiation also induces miR-132-3p and its uridylated isoform in esophageal epithelial cells. miR-132-3p mimics suppress proliferation and migration and exacerbate radiation injury, whereas the triuridylated isoform exerts a protective effect by reducing binding to MEF2A and modulating cell-cycle progression43. Epidermal growth factor (EGF) expression declines in irradiated esophagus, while exogenous EGF partially protects epithelial cells against radiation-induced apoptosis through phosphorylation of EGFR, AKT, and ERK signaling intermediates41. Single-cell transcriptomic analysis has identified dynamic changes in myeloid cells and fibroblast subsets across inflammatory and reparative phases, with Atf4 implicated in regulation of inflammatory responses44. TUT4-mediated uridylation of miR-132/212 has also been shown to modulate esophageal epithelial radiosensitivity45. A schematic overview of the necrotic, ulcerative, and reparative/fibrotic phases, together with their cellular events, molecular mediators, and therapeutic targets, is presented in Figure 1.
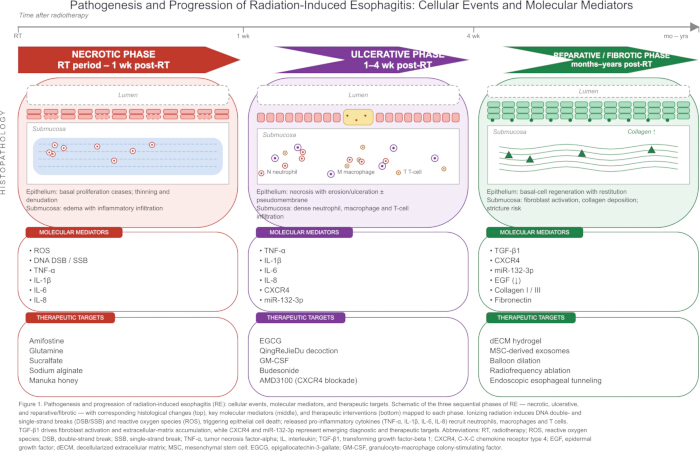
Figure 1: Pathogenesis and Progression of Radiation-Induced Esophagitis. Schematic representation of the necrotic, ulcerative, and reparative/fibrotic phases of RE, showing the corresponding histological changes, cellular events, key molecular mediators, and therapeutic interventions. Please click here to view a larger version of this figure.
3. Diagnosis
RE typically presents with odynophagia, dysphagia, and retrosternal pain6. Symptoms generally emerge two to three weeks after initiation of radiotherapy, peak during the final treatment week or one to two weeks thereafter, and gradually subside over subsequent weeks6. Patient-reported outcome measures may detect symptoms earlier and more sensitively than physician-assessed Common Terminology Criteria for Adverse Events (CTCAE) grading. In a cohort of 200 patients, the 30-day cumulative incidence of patient-reported moderate-to-severe swallowing difficulty was 26%, compared with 6% for provider-reported grade 2 or higher dysphagia34.
Endoscopy is not routinely required for uncomplicated RE but has defined indications. It should be considered when symptoms are disproportionate to expected radiation toxicity, when infectious esophagitis or tumor progression must be differentiated from radiation injury, or when suspected grade 3 or higher mucosal injury requires objective assessment to guide nutritional support, analgesic escalation, or treatment modification. Although Radiation Therapy Oncology Group symptom scores correlate with endoscopic findings, clinically important discordance can occur, including significant ulceration in asymptomatic patients46.
The Fukui Acute Radiation Esophagitis (FARE) endoscopic grading system provides a standardized framework for quantifying mucosal injury. FARE grade correlates with CTCAE grade but may identify severe esophagitis, including deep ulcers and impending stricture formation, in patients with few or no symptoms47. Such findings may prompt nutritional support, closer monitoring, or consideration of treatment interruption, whereas low FARE grades in symptomatic patients may encourage investigation of non-radiation causes of dysphagia. Barium esophagography can demonstrate segmental narrowing and discrete ulcers, although its diagnostic yield is lower than that of endoscopy48.
Functional imaging provides additional diagnostic and predictive information. Increased esophageal fluorodeoxyglucose (FDG) uptake during radiotherapy correlates with RE severity, and changes in SUVmax at week 2 may predict grade 3 or higher RE with an area under the curve (AUC) of 0.69, comparable with V50 and V6015,16. FDG uptake must, however, be distinguished from tumor progression and Candida esophagitis49,50. Changes in target-to-background ratio on 18F-FAPI-04 PET/CT have also been reported to identify RE, particularly grade 3 RE13, while CXCR4-targeted probes remain preclinical14.
A case report described a continuous “tube-like” pattern of FDG uptake in acute RE that resolved in parallel with symptomatic improvement49. Diffuse uptake can also occur in reflux, medication-induced or infectious esophagitis, and infiltrating carcinoma. The reported RE pattern was confined to the irradiated field and lacked the characteristic endoscopic findings of Candida infection49.
Accordingly, first-line assessment relies on clinical evaluation using CTCAE grading complemented by patient-reported outcomes. FDG-PET/CT may be considered when the diagnosis is uncertain or alternative etiologies require exclusion. Endoscopy is reserved for disproportionate symptoms, suspected infectious or neoplastic disease requiring biopsy, or suspected high-grade mucosal injury requiring objective assessment for management decisions.
4. Risk factors
Dose–volume parameters are among the most robust predictors of RE. A MED of 22 Gy corresponded to a 50% probability of grade 2 or higher RE in chemotherapy-treated patients, whereas a MED of 29 Gy predicted a 3% probability of grade 3 or higher RE4. A V55 of 5% predicted a 5% risk of grade 3 or higher RE5, while a V60 threshold of 17% was identified as the optimal single predictor in an individual-patient-data meta-analysis51. D2cc thresholds of 50 Gy and 61 Gy corresponded to a 50% risk of grade 2 or higher RE with chemotherapy and a 3% risk of grade 3 or higher RE, respectively4. Generalized equivalent uniform dose and V40 have also demonstrated predictive value5,52, and external validation has supported the upper-middle esophageal mean dose as a robust predictor53. Key dosimetric predictors are summarized in Table 1.
Concurrent chemotherapy is an important exacerbating factor, with risk varying by agent and schedule. Docetaxel/cisplatin was associated with higher rates of esophagitis than cisplatin/etoposide and carboplatin/paclitaxel in stage III NSCLC54. Vinorelbine/cisplatin was associated with a lower risk of grade 3 acute esophagitis than docetaxel/cisplatin55. In esophageal squamous cell carcinoma, nedaplatin was associated with lower rates of grade 3–4 acute radiation-associated esophagitis than other platinum agents56, while etoposide/lobaplatin produced lower acute RE rates than etoposide/cisplatin in limited-stage small-cell lung cancer57.
Weekly paclitaxel/carboplatin with concurrent radiotherapy produced grade 3–4 esophagitis rates of 35%–45% in phase II NSCLC studies58,59. In esophageal cancer, erlotinib combined with 5-FU/cisplatin and radiotherapy was associated with esophagitis in all treated patients, including grade 3 and 4 events60. In contrast, a phase I study of pemetrexed/cisplatin with 66 Gy thoracic radiotherapy reported grade 3 acute esophagitis in 1 patient (6.7%) and no grade 4 toxicity61, while another phase I study supported the tolerability of the regimen62. Dose-escalation studies of 5-FU/cisplatin in esophageal cancer identified grade 3 esophagitis as a dose-limiting toxicity63,64.
Radiotherapy technique and fractionation also influence risk. IMRT was associated with higher grade 2 or higher RE than 3DCRT in breast RNI29, while proton therapy did not demonstrate a significant esophageal-sparing advantage over photon therapy based on imaging biomarkers65. Twice-daily fractionation does not appear to increase severe RE35,36, although accelerated hyperfractionation has been associated with earlier and more pronounced toxicity66,67. In a 2025 prospective multicenter breast cancer cohort receiving 43.5 Gy in 15 fractions, RV25 <20% and AV35 <0.27 mL were validated as protective constraints68.
Patient-specific factors further modify risk. Increasing age has been inversely associated with RE incidence69. Reported germline associations include TGFB1 rs1800469 C-509T12, TGFB1 rs114663539, HSPB1 rs74591859, SDC2 rs1778808470, and inflammation-related gene polymorphisms11. Alterations in homologous recombination repair pathways have also been associated with high-grade RE in esophageal squamous cell carcinoma10. These genetic associations are summarized in Table 2. Baseline IL-8 combined with age and esophageal generalized equivalent uniform dose (EUD) improves predictive model performance71, while early-treatment serum miR-155 and miR-221 have been identified as predictors of severe RE72. Among these factors, dose–volume parameters have the clearest immediate clinical utility. MED, V60, and D2cc can inform treatment planning and esophageal sparing4,5,51. Chemotherapy selection may also influence management when esophageal dose constraints cannot be achieved57. Genetic markers such as TGFB1 rs1800469 and HSPB1 rs7459185 remain research tools9,12, while IL-8 and miR-155/miR-221 remain investigational and have not been incorporated into routine clinical decision algorithms71,72.
Table 1: Key Dosimetric Predictors of Radiation Esophagitis. Summary of the principal dosimetric parameters associated with radiation-induced esophagitis (RE), including reported thresholds and corresponding clinical endpoints. Please click here to download this file.
Table 2: Genetic Polymorphisms Associated with Radiation Esophagitis. Summary of germline single nucleotide polymorphisms associated with radiation-induced esophagitis risk, including the reported risk allele, direction of association, and effect size where available. Please click here to download this file.
5. Predictive modeling
The Lyman-Kutcher-Burman (LKB) framework remains a standard normal tissue complication probability (NTCP) model for RE. In proton-treated NSCLC, optimized LKB parameters for grade 2 or higher RE were TD50 = 44.83 Gy, n = 0.24, and m = 0.51, with an optimism-corrected AUC of 0.78373. A comparison of five modeling techniques found that LASSO multivariable logistic regression achieved an AUC of 0.799 and generalized LKB an AUC of 0.79674. The simpler LKB model performed similarly to more complex support vector machine approaches and was less prone to overfitting.
LKB parameters have established radiobiological interpretations, whereas machine learning (ML) models may capture nonlinear relationships at the expense of interpretability18. This trade-off is particularly relevant in RE studies, where datasets are often relatively small. Nevertheless, incorporation of radiomic and dosiomic features has improved predictive performance. Planning CT-derived radiomic models achieved a test AUC of 0.744 compared with 0.509 for clinical-only models17, while deep learning-derived dosiomic features achieved an AUC of 0.812 compared with 0.730 for handcrafted features75. Decision-tree models have also reported high classification accuracy, with V40, V60, and MED among key predictors76, and multiomic random forest approaches have demonstrated the feasibility of integrating clinical, dosimetric, dosiomic, and radiomic information77. In 273 patients with esophageal squamous cell carcinoma, a combined deep-learning, dosiomic, and clinical model achieved internal and external validation AUCs of 0.821 and 0.805, respectively78. Multi-objective Bayesian network models have also demonstrated simultaneous prediction of radiation pneumonitis and RE19. Early FDG-PET changes predicted grade 3 or higher RE with an AUC of 0.6916, while esophageal expansion on CT achieved an AUC of 0.93 for grade 2 or higher RE79.
Clinical translation remains limited by overfitting, small single-center datasets, interinstitutional heterogeneity, and limited external validation80. Differences in esophageal contouring, treatment-planning systems, dose-calculation algorithms, and fractionation schemes further affect generalizability81. Although externally validated dosiomics-guided models have been reported18, most published models remain retrospective and single-center. Across studies, dose–volume histogram parameters, particularly V50, V55, V60, and MED, remain among the most reproducible predictors80. Dosiomic features may add predictive value beyond conventional dose–volume metrics18, although dependence on manual region-of-interest delineation introduces interobserver variability. FDG-PET/CT offers functional information not available from planning CT. Early changes in FDG uptake predict RE severity15, and PET-based planning has been associated with reductions in V45 and MED while permitting dose escalation15. CT-based radiomics remains useful when PET/CT is unavailable, although its reported performance is more variable18.
6. Prevention and treatment
Technical optimization can reduce RE. In the PROACTIVE phase III trial, esophageal-sparing IMRT did not significantly improve esophageal quality of life but reduced symptomatic esophagitis from 24% to 2%, with the greatest benefit in patients receiving 30 Gy34. Contralateral esophagus-sparing IMRT reduced pain events and severe pain in patients with stage III NSCLC without compromising oncological outcomes82. Involved-field irradiation has also been associated with reduced acute RE compared with elective nodal irradiation83, while PET-CT-guided omission of clinical target volume reduced grade 3 or higher esophagitis and pneumonitis84.
Pharmacological prophylaxis has generally shown limited benefit in randomized trials. Although retrospective studies suggested benefit from glutamine85,86, a double-blind randomized trial was terminated for futility, with RE rates of 74% with glutamine and 68% with placebo20. Manuka honey22, sodium alginate21, sucralfate23, and amifostine87 also failed to demonstrate clear preventive efficacy in randomized trials. In contrast, prophylactic epigallocatechin-3-gallate reduced maximum esophagitis grade in a phase III trial88, and a meta-analysis of 11 randomized controlled trials reported reductions in acute RE with QingReJieDu therapy89. In the immunotherapy era, expert consensus has emphasized upfront risk assessment, incorporation of prophylactic measures into treatment planning, escalation of management according to adverse-event grade, and multidisciplinary communication for patients receiving concurrent chemoradiotherapy with or without durvalumab consolidation90.
Treatment of established RE includes medical and endoscopic approaches. Oro-dispersible budesonide produced complete remission in a case report91, while oral granulocyte-macrophage colony-stimulating factor enabled most patients with grade 3 esophagitis in reported studies to complete radiotherapy92,93. Radiofrequency ablation has been used for hemorrhagic RE94,95, balloon dilation for radiation-induced strictures96, and endoscopic tunneling for complete esophageal obstruction97. Regenerative strategies remain preclinical. Decellularized extracellular matrix hydrogel delivered using a 3D-printed stent promoted resolution of inflammation and tissue repair in a rat model25. Drug-loaded nanofibrous membranes improved mucosal healing26, while mesenchymal stem cell-derived exosomes reduced fibrosis and inflammation and improved muscular restoration in a murine model24.
7. Future directions
Several priorities remain. First, multi-omics models require prospective and external validation before routine clinical implementation17,18,78. Future studies should emphasize multicenter cohorts, clinically usable decision-support tools, and dynamic risk assessment incorporating early treatment-related imaging changes. Second, although durvalumab is established as consolidation therapy in stage III NSCLC90, the interaction between immunotherapy and radiation-associated esophageal injury remains incompletely characterized. Refractory esophagitis during durvalumab therapy has been described98. Future work should evaluate esophageal dose constraints in this setting, biomarkers that distinguish radiation-induced from immune-mediated esophagitis, and management approaches for combined toxicity. Third, chronomodulated radiotherapy warrants further evaluation. Evening radiotherapy after 19:00 was associated with increased RE risk in one study99. Prospective validation is required before treatment timing can be considered a preventive strategy. Fourth, regenerative approaches, including decellularized extracellular matrix hydrogels, nanofibrous membranes, and mesenchymal stem cell-derived exosomes, have demonstrated benefit in preclinical models24,25,26. Translation will require early-phase clinical trials to establish safety, preliminary efficacy, delivery methods, and appropriate patient selection. Finally, natural language processing models capable of automatically extracting esophagitis severity from clinical notes may facilitate large-scale real-world toxicity research, retrospective electronic health record analysis, automated toxicity surveillance, and detection of uncommon toxicity patterns100.
Conclusioni
Radiation-induced esophagitis (RE) exemplifies the evolution of toxicity management in radiation oncology, progressing from descriptive observation to mechanistic understanding, from empirical symptom management to data-driven risk prediction, and from passive acceptance of toxicity to active prevention and repair. The identification of dose–volume parameters established a quantitative framework for risk assessment, while the integration of genomics, functional imaging, and artificial intelligence is advancing personalized risk prediction. Although pharmacological prophylaxis has shown limited success, technical optimization and regenerative strategies offer promising alternatives. Key challenges include prospective validation of multi-omics models, clarification of RE risk in the immunotherapy era, and clinical translation of regenerative approaches. Addressing these challenges may further advance RE toward becoming a more predictable, preventable, and manageable toxicity of thoracic radiotherapy.
Abbreviations: AUC, area under the receiver operating characteristic curve; CXCR4, C-X-C chemokine receptor type 4; D2cc, minimum dose to the 2 cm3 receiving the highest dose; dECM, decellularized extracellular matrix; EGF, epidermal growth factor; EGCG, epigallocatechin-3-gallate; GM-CSF, granulocyte-macrophage colony-stimulating factor; HR, hazard ratio; IL, interleukin; MED, mean esophageal dose; MSC, mesenchymal stem cell; OR, odds ratio; RE, radiation-induced esophagitis; ROS, reactive oxygen species; SNP, single nucleotide polymorphism; TGF-β1, transforming growth factor-beta 1; TNF-α, tumor necrosis factor-alpha; Vx, percentage of esophageal volume receiving ≥x Gy.
Dichiarazioni
The authors declare no conflicts of interest. No author received financial support, honoraria, consulting fees, or other benefits from any commercial entity related to the subject matter of this review. All authors have read and approved the final.
Ringraziamenti
This research received no specific grant or funding from any public, commercial, or not-for-profit funding agency. No individuals other than the listed authors contributed to the conception, writing, or revision of this manuscript.
Riferimenti
- Simone CB. Thoracic Radiation Normal Tissue Injury. Seminars in Radiation Oncology. 2017;27(4):370–377.
- Wu Q et al. Research progress of radiation esophagitis: A narrative review. Medicine. 2025;104(19):e42273. doi: 10.1097/MD.0000000000042273.
- Adebahr S, Schimek-Jasch T, Nestle U, Brunner TB. Oesophagus side effects related to the treatment of oesophageal cancer or radiotherapy of other thoracic malignancies. Best Practice & Research. Clinical Gastroenterology. 2016;30(4):565–580.
- Herr DJ et al. Factors associated with acute esophagitis during radiation therapy for lung cancer. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2024;197:110349. doi: 10.1016/j.radonc.2024.110349.
- Paximadis P et al. Dosimetric predictors for acute esophagitis during radiation therapy for lung cancer: Results of a large statewide observational study. Practical Radiation Oncology. 2018;8(3):167–173.
- Murro D, Jakate S. Radiation esophagitis. Archives of Pathology & Laboratory Medicine. 2015;139(6):827–830.
- Werner-Wasik M. Treatment-related esophagitis. Seminars in Oncology. 2005;32(2 Suppl 3):S60–66.
- Sanders KJC et al. Early Weight Loss during Chemoradiotherapy Has a Detrimental Impact on Outcome in NSCLC. Journal of Thoracic Oncology: Official Publication of the International Association for the Study of Lung Cancer. 2016;11(6):873–879.
- Delgado BD et al. Association of single nucleotide polymorphisms at HSPB1 rs7459185 and TGFB1 rs11466353 with radiation esophagitis in lung cancer. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2019;135:161–169.
- Li L et al. Clinical Outcome-Related Cancer Pathways and Mutational Signatures in Patients With Unresectable Esophageal Squamous Cell Carcinoma Treated With Chemoradiotherapy. International Journal of Radiation Oncology, Biology, Physics. 2023;115(2):382–394.
- Hildebrandt MAT et al. Genetic variants in inflammation-related genes are associated with radiation-induced toxicity following treatment for non-small cell lung cancer. PloS One. 2010;5(8):e12402. doi: 10.1371/journal.pone.0012402.
- Guerra JLL et al. Association between single nucleotide polymorphisms of the transforming growth factor β1 gene and the risk of severe radiation esophagitis in patients with lung cancer. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2012;105(3):299–304.
- Hu X et al. Detecting radiation esophagitis using 18F-FAPI-04 PET/CT in patients with LA-ESCC treated with concurrent chemoradiotherapy. BMC Cancer. 2025;25(1):854. doi: 10.1186/s12885-025-14236-3.
- Pei J et al. C-X-C-chemokine-receptor-type-4 as a potential target for diagnosis and treatment of acute radiation-induced esophagitis. International Immunopharmacology. 2025;150:114289. doi: 10.1016/j.intimp.2025.114289.
- Niedzielski JS et al. (18)F-Fluorodeoxyglucose Positron Emission Tomography Can Quantify and Predict Esophageal Injury During Radiation Therapy. International Journal of Radiation Oncology, Biology, Physics. 2016;96(3):670–678.
- Mehmood Q et al. Predicting Radiation Esophagitis Using 18F-FDG PET During Chemoradiotherapy for Locally Advanced Non-Small Cell Lung Cancer. Journal of Thoracic Oncology: Official Publication of the International Association for the Study of Lung Cancer. 2016;11(2):213–221.
- Zheng X et al. Multi-omics to predict acute radiation esophagitis in patients with lung cancer treated with intensity-modulated radiation therapy. European Journal of Medical Research. 2023;28(1):126. doi: 10.1186/s40001-023-01041-6.
- Yu X et al. Dosiomics-guided deep learning for radiation esophagitis prediction in lung cancer: optimal region of interest definition via multi-branch fusion auxiliary learning. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2025;212:111121. doi: 10.1016/j.radonc.2025.111121.
- Nair SS et al. Multiomic based Bayesian network toxicity modeling for simultaneous prediction of multiple toxicity outcomes in NSCLC. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2025;210:111011. doi: 10.1016/j.radonc.2025.111011.
- Alshawa A et al. Effects of glutamine for prevention of radiation-induced esophagitis: a double-blind placebo-controlled trial. Investigational New Drugs. 2021;39(4):1113–1122.
- Ninomiya K et al. A randomized trial of sodium alginate prevention of esophagitis in LA-NSCLC receiving chemoradiotherapy: OLCSG1401. Supportive Care in Cancer: Official Journal of the Multinational Association of Supportive Care in Cancer. 2021;29(9):5237–5244.
- Fogh SE et al. A Randomized Phase 2 Trial of Prophylactic Manuka Honey for the Reduction of Chemoradiation Therapy-Induced Esophagitis During the Treatment of Lung Cancer: Results of NRG Oncology RTOG 1012. International Journal of Radiation Oncology, Biology, Physics. 2017;97(4):786–796.
- McGinnis WL et al. Placebo-controlled trial of sucralfate for inhibiting radiation-induced esophagitis. Journal of Clinical Oncology: Official Journal of the American Society of Clinical Oncology. 1997;15(3):1239–1243.
- Kim M-K et al. Regenerative effects of myogenic gene transfected MSC derived exosomes on radiation esophagitis. Tissue Engineering and Regenerative Medicine. 2026;23(4):597–612.
- Ha D-H et al. Therapeutic effect of decellularized extracellular matrix-based hydrogel for radiation esophagitis by 3D printed esophageal stent. Biomaterials. 2021;266:120477. doi: 10.1016/j.biomaterials.2020.120477.
- Ma S et al. Preparation of nanofibrous membrane-covered saccule gastric tubes and their treatment of radiation esophagitis. Acta Biomaterialia. 2026;214:74–88.
- Ren XJ, Wang L, Han C, Liu LL. The efficacy and safety of high dose versus standard dose radiotherapy in concurrent chemoradiotherapy for patients with esophageal squamous cell carcinoma. Zhonghua zhong liu za zhi [Chinese journal of oncology]. 2019;41(2):135–139.
- Ren X, Wang L, Han C, Ren L. Retrospective analysis of safety profile of high-dose concurrent chemoradiotherapy for patients with oesophageal squamous cell carcinoma. Radiotherapy and oncology: journal of the European Society for Therapeutic Radiology and Oncology. 2018;129(2):293–299.
- Yaney A et al. Dosimetric parameters associated with radiation-induced esophagitis in breast cancer patients undergoing regional nodal irradiation. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2021;155:167–173.
- Wang D-Q et al. Dose-Volume Predictors for Radiation Esophagitis in Patients With Breast Cancer Undergoing Hypofractionated Regional Nodal Radiation Therapy. International Journal of Radiation Oncology, Biology, Physics. 2023;117(1):186–197.
- Wang D-Q et al. Dosimetric and clinical predictors for radiation esophagitis in patients with breast cancer undergoing conventional fractionated regional nodal irradiation: A prospective study. International Journal of Cancer. 2026;158(4):1055–1066.
- Ahmed ZM et al. Radiation-induced Esophagitis in Breast Cancer Patients Treated With Supraclavicular Field Irradiation. Anticancer Research. 2024;44(10):4543–4549.
- Duane FK et al. Exposure of the oesophagus in breast cancer radiotherapy: A systematic review of oesophagus doses published 2010–2020. Radiotherapy and Oncology. 2021;164:261–267.
- Louie AV et al. Palliative Radiation for Advanced Central Lung Tumors With Intentional Avoidance of the Esophagus (PROACTIVE): A Phase 3 Randomized Clinical Trial. JAMA Oncology. 2022;8(4):1–7.
- Faivre-Finn C et al. Concurrent once-daily versus twice-daily chemoradiotherapy in patients with limited-stage small-cell lung cancer (CONVERT): an open-label, phase 3, randomised, superiority trial. The Lancet. Oncology. 2017;18(8):1116–1125.
- Suzuki R et al. Twice-daily Thoracic Radiotherapy for Limited-stage Small-cell Lung Cancer Does Not Increase the Incidence of Acute Severe Esophagitis. Clinical Lung Cancer. 2018;19(6):e885–e891.
- Tonse R et al. Hospitalization rates from radiotherapy complications in the United States. Scientific Reports. 2022;12(1):4371. doi: 10.1038/s41598-022-08491-8.
- Lindberg K et al. The HILUS-Trial-a Prospective Nordic Multicenter Phase 2 Study of Ultracentral Lung Tumors Treated With Stereotactic Body Radiotherapy. Journal of Thoracic Oncology: Official Publication of the International Association for the Study of Lung Cancer. 2021;16(7):1200–1210.
- Rock C et al. Ten fraction hypofractionated stereotactic body radiotherapy for the management of ultracentral lung tumors: a retrospective analysis of dosimetry, outcomes, and toxicity. Radiation Oncology. 2023;18(1):128. doi: 10.1186/s13014-023-02298-1.
- Said BI et al. Accelerated Hypofractionated Radiotherapy for Locally Advanced NSCLC: A Systematic Review From the International Association for the Study of Lung Cancer Advanced Radiation Technology Subcommittee. Journal of Thoracic Oncology. 2025;20(1):39–51.
- Kim KS et al. Radiation-Induced Esophagitis In Vivo and In Vitro Reveals That Epidermal Growth Factor Is a Potential Candidate for Therapeutic Intervention Strategy. International Journal of Radiation Oncology, Biology, Physics. 2016;95(3):1032–1041.
- Yuan ST et al. Genetic variations in TGFβ1, tPA, and ACE and radiation-induced thoracic toxicities in patients with non-small-cell lung cancer. Journal of Thoracic Oncology: Official Publication of the International Association for the Study of Lung Cancer. 2013;8(2):208–213.
- Liu M, Sun Z, Tang Y, Zhang S, Luo J. The Regulation of Exosome-Mediated miR-132-3p/miR-132-3p-UUU on Radiation-Induced Esophageal Injury. Radiation Research. 2023;200(2):151–161.
- Huang X, Ma Y, Tian B, Yu J, Chen D. Single-Cell Transcriptomic Analysis Deciphers Key Signatures Associated with Dynamic Evolution in Radiation-Induced Esophageal Injury. International Journal of Radiation OncologyBiologyPhysics. 2024;120(2):e368–e369.
- Ren H et al. Potential protective regulatory effects on radiation-induced esophageal injury in TUT4-/- mice. Frontiers in Oncology. 2025;15:1600597. doi: 10.3389/fonc.2025.1600597.
- Hirota S et al. Endoscopic findings of radiation esophagitis in concurrent chemoradiotherapy for intrathoracic malignancies. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2001;58(3):273–278.
- Hasatani K et al. Efficacy of Endoscopic Evaluation of Acute Radiation Esophagitis during Chemoradiotherapy with Proton Beam Therapy Boost for Esophageal Cancer. Digestion. 2020;101(4):366–374.
- Collazzo LA, Levine MS, Rubesin SE, Laufer I. Acute radiation esophagitis: radiographic findings. AJR. American journal of roentgenology. 1997;169(4):1067–1070.
- Kawahara T et al. Acute Radiation Esophagitis After Chemoradiotherapy Demonstrating “Tube-Like” FDG Uptake on PET-CT: Case Report and Literature Review. Cancer Reports. 2025;8(10):e70365. doi: 10.1002/cnr2.70365.
- Mukherjee A, Chakraborty PS, Behera A, Bal C, Kumar R. Radiation-Induced Esophagitis Masquerading as Disease Progression in Case of Esophageal Carcinoma: A Diagnostic Dilemma Solved on Follow-up FDG PET/CT. Clinical Nuclear Medicine. 2015;40(7):e380–e381.
- Palma DA et al. Predicting esophagitis after chemoradiation therapy for non-small cell lung cancer: an individual patient data meta-analysis. International Journal of Radiation Oncology, Biology, Physics. 2013;87(4):690–696.
- Pan Y et al. Acute esophagitis for patients with local-regional advanced non small cell lung cancer treated with concurrent chemoradiotherapy. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2016;118(3):465–470.
- Monti S, Palma G, Caroprese M, Cella L. External Validation of Dose Patterns and Dosimetric Predictors for Radiation-Induced Esophagitis In Non-Small Cell Lung Cancer. International Journal of Radiation Oncology, Biology, Physics. 2026;124(1):206–214.
- Ozcelik M et al. Comparison of efficacy and safety of three different chemotherapy regimens delivered with concomitant radiotherapy in inoperable stage III non-small cell lung cancer patients. Tumor Biology. 2016;37(7):8901–8907.
- Zhang Z et al. Risk factors of radiation-induced acute esophagitis in non-small cell lung cancer patients treated with concomitant chemoradiotherapy. Radiation Oncology. 2014;9(1):54. doi: 10.1186/1748-717X-9-54.
- Zhuang Q et al. Safety and efficacy analysis of neoadjuvant radiotherapy combined with concurrent paclitaxel plus nedaplatin versus other platinum-based chemotherapy for thoracic segmental esophageal squamous cell carcinoma. Frontiers in Oncology. 2025;15:1582481. doi: 10.3389/fonc.2025.1582481.
- Wang M et al. Preliminary results of randomized phase II study of etoposide plus lobaplatin or etoposide plus cisplatin with concurrent thoracic radiotherapy in the treatment of limited-stage small cell lung cancer. Anti-Cancer Drugs. 2023;34(10):1183–1189.
- Choy H et al. Preliminary analysis of a phase II study of paclitaxel, carboplatin, and hyperfractionated radiation therapy for locally advanced inoperable non-small cell lung cancer. Seminars in Oncology. 1997;24(4 Suppl 12):S12-21–S12-26.
- Choy H, Akerley W, Safran H, Graziano S, Chung C. Paclitaxel plus carboplatin and concurrent radiation therapy for patients with locally advanced non-small cell lung cancer. Seminars in Oncology. 1996;23(6 Suppl 16):117–119.
- Dobelbower MC et al. Epidermal growth factor receptor tyrosine kinase inhibitor, erlotinib, and concurrent 5-fluorouracil, cisplatin and radiotherapy for patients with esophageal cancer: a phase I study. Anti-Cancer Drugs. 2006;17(1):95–102.
- Brade A et al. Phase I trial of radiation with concurrent and consolidation pemetrexed and cisplatin in patients with unresectable stage IIIA/B non-small-cell lung cancer. International Journal of Radiation Oncology, Biology, Physics. 2011;79(5):1395–1401.
- Surmont V et al. Pemetrexed and cisplatin with concurrent radiotherapy for locally advanced non-small cell and limited disease small cell lung cancer: results from 2 phase I studies. Lung Cancer. 2010;69(3):302–306.
- Lin Q et al. Phase I trial of escalating-dose cisplatin with 5-fluorouracil and concurrent radiotherapy in Chinese patients with esophageal cancer. Acta Medica Okayama. 2008;62(1):37–44.
- Nakajima TE et al. A phase I trial of 5-fluorouracil with cisplatin and concurrent standard-dose radiotherapy in Japanese patients with stage II/III esophageal cancer. Japanese Journal of Clinical Oncology. 2009;39(1):37–42.
- Niedzielski JS et al. Differences in Normal Tissue Response in the Esophagus Between Proton and Photon Radiation Therapy for Non-Small Cell Lung Cancer Using In Vivo Imaging Biomarkers. International Journal of Radiation Oncology, Biology, Physics. 2017;99(4):1013–1020.
- Byhardt RW et al. Response, toxicity, failure patterns, and survival in five Radiation Therapy Oncology Group (RTOG) trials of sequential and/or concurrent chemotherapy and radiotherapy for locally advanced non-small-cell carcinoma of the lung. International Journal of Radiation Oncology, Biology, Physics. 1998;42(3):469–478.
- Bütof R et al. Dose-volume predictors of early esophageal toxicity in non-small cell lung cancer patients treated with accelerated-hyperfractionated radiotherapy. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2020;143:44–50.
- Wang D-Q et al. Prospective cohort study to validate esophageal dose constraints and predictive models for esophagitis in patients with breast cancer undergoing hypofractionated regional nodal radiotherapy. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2025;212:111120. doi: 10.1016/j.radonc.2025.111120.
- Soni PD et al. Lower Incidence of Esophagitis in the Elderly Undergoing Definitive Radiation Therapy for Lung Cancer. Journal of Thoracic Oncology: Official Publication of the International Association for the Study of Lung Cancer. 2017;12(3):539–546.
- Zhang M et al. Genetic variation in SDC2 is associated with the risk of radiation esophagitis in patients with esophageal squamous cell carcinoma receiving radiotherapy. Zhonghua Zhong Liu Za Zhi [Chinese Journal of Oncology]. 2015;37(6):422–426.
- Wang S et al. A model combining age, equivalent uniform dose and IL-8 may predict radiation esophagitis in patients with non-small cell lung cancer. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2018;126(3):506–510.
- Xu T et al. Serum inflammatory miRNAs predict radiation esophagitis in patients receiving definitive radiochemotherapy for non-small cell lung cancer. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2014;113(3):379–384.
- Wang Z et al. Lyman-Kutcher-Burman normal tissue complication probability modeling for radiation-induced esophagitis in non-small cell lung cancer patients receiving proton radiotherapy. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2020;146:200–204.
- Chen M et al. Predictive performance of different NTCP techniques for radiation-induced esophagitis in NSCLC patients receiving proton radiotherapy. Scientific Reports. 2022;12(1):9178. doi: 10.1038/s41598-022-12898-8.
- Ma Z et al. Enhanced prediction of postoperative radiotherapy-induced esophagitis in non-small cell lung cancer: Dosiomic model development in a real-world cohort and validation in the PORT-C randomized controlled trial. Thoracic Cancer. 2023;14(28):2839–2845.
- Alizade-Harakiyan M, Khodaei A, Yousefi A, Zamani H, Mesbahi A. Decision tree-based machine learning algorithm for prediction of acute radiation esophagitis. Biochemistry and Biophysics Reports. 2025;42:101991. doi: 10.1016/j.bbrep.2025.101991.
- Nair SS et al. Multiomic random forest toxicity modeling of radiation esophagitis. Physics and Imaging in Radiation Oncology. 2025;36:100838. doi: 10.1016/j.phro.2025.100838.
- Xie C et al. Combined deep learning and radiomics in pretreatment radiation esophagitis prediction for patients with esophageal cancer underwent volumetric modulated arc therapy. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2024;199:110438. doi: 10.1016/j.radonc.2024.110438.
- Niedzielski JS et al. Objectively Quantifying Radiation Esophagitis With Novel Computed Tomography-Based Metrics. International Journal of Radiation Oncology, Biology, Physics. 2016;94(2):385–393.
- Tong D et al. A systematic review and meta-analysis of the utility of quantitative, imaging-based approaches to predict radiation-induced toxicity in lung cancer patients. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2025;208:110935. doi: 10.1016/j.radonc.2025.110935.
- Khanam N, Kumar R. Recent Applications of Artificial Intelligence in Early Cancer Detection. Curr Med Chem. 2022;29(25):4410–4435.
- Lim HS et al. Reduced frequency and severity of radiation esophagitis without marginal failure risk by contralateral esophagus sparing IMRT in stage III non-small cell lung cancer patients undergoing definitive concurrent chemoradiotherapy. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2024;199:110436. doi: 10.1016/j.radonc.2024.110436.
- Zhu H et al. What Is the Optimal Radiotherapy Target Size for Non-Operable Esophageal Cancer? A Meta-Analysis. Oncology research and treatment. 2019;42(9):470–479.
- Cui T et al. Feasibility of omitting the clinical target volume under PET-CT guidance in unresectable stage III non-small-cell lung cancer: A phase II clinical trial. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2023;181:109505. doi: 10.1016/j.radonc.2023.109505.
- Gul K, Mehmet K, Meryem A. The effects of oral glutamine on clinical and survival outcomes of non-small cell lung cancer patients treated with chemoradiotherapy. Clinical Nutrition. 2017;36(4):1022–1028.
- Chang S-C, Lai Y-C, Hung J-C, Chang C-Y. Oral glutamine supplements reduce concurrent chemoradiotherapy-induced esophagitis in patients with advanced non-small cell lung cancer. Medicine. 2019;98(8):e14463. doi: 10.1097/MD.0000000000014463.
- Movsas B et al. Randomized trial of amifostine in locally advanced non-small-cell lung cancer patients receiving chemotherapy and hyperfractionated radiation: radiation therapy oncology group trial 98-01. Journal of Clinical Oncology: Official Journal of the American Society of Clinical Oncology. 2005;23(10):2145–2154.
- Zhao H et al. A prospective, three-arm, randomized trial of EGCG for preventing radiation-induced esophagitis in lung cancer patients receiving radiotherapy. Radiotherapy and Oncology: Journal of the European Society for Therapeutic Radiology and Oncology. 2019;137:186–191.
- Wang J, Qiu D, Dong X, Liu Y, Chen J. Efficacy and safety of QingReJieDu therapy in preventing acute radiation esophagitis: A systematic review and meta-analysis. Medicine. 2024;103(49):e40779. doi: 10.1097/MD.0000000000040779.
- Brade AM et al. Esophagitis and Pneumonitis Related to Concurrent Chemoradiation ± Durvalumab Consolidation in Unresectable Stage III Non-Small-Cell Lung Cancer: Risk Assessment and Management Recommendations Based on a Modified Delphi Process. Current Oncology. 2024;31(11):6512–6535.
- Reinshagen M, Hoffmann W. Therapy of radiation-induced esophagits by oro-dispersible budesonide. Zeitschrift Fur Gastroenterologie. 2020;58(11):1091–1093.
- Koc M, Onuk MD, Koruk M, Memik F. Therapeutic effect of oral recombinant human granulocyte macrophage-colony stimulating factor in radiotherapy-induced esophagitis. Hepato-Gastroenterology. 2003;50(53):1297–1300.
- Koukourakis MI et al. Oral administration of recombinant human granulocyte macrophage colony-stimulating factor in the management of radiotherapy-induced esophagitis. Clinical Cancer Research: An Official Journal of the American Association for Cancer Research. 1999;5(12):3970–3976.
- Marin F-S et al. Successful treatment of hemorrhagic radiation esophagitis with radiofrequency ablation. Endoscopy. 2022;54(S 02):E830–E831.
- Monino L, Garces-Duran R, Deprez PH, Moreels TG. Upper gastrointestinal bleeding due to mixed adenoneuroendocrine carcinoma and radiation esophagitis treated with cap-mucosectomy combined with radiofrequency ablation. Endoscopy. 2022;54(6):E308–E309.
- Rodrigues-Pinto E et al. Risk factors associated with refractoriness to esophageal dilatation for benign dysphagia. European Journal of Gastroenterology & Hepatology. 2016;28(6):684–688.
- Wagh MS, Draganov PV. Per-oral endoscopic tunneling for restoration of the esophagus: a novel endoscopic submucosal dissection technique for therapy of complete esophageal obstruction. Gastrointestinal Endoscopy. 2017;85(4):722–727.
- Utsumi T, Tsubouchi K, Harada T. Refractory Severe Esophagitis During Durvalumab Therapy in a Patient With Locally Advanced NSCLC. Journal of Thoracic Oncology: Official Publication of the International Association for the Study of Lung Cancer. 2019;14(2):e40–e42.
- Xing Y et al. Comparison of radiation esophagitis associated with daytime versus evening radiotherapy in patients with esophageal carcinoma. Radiation Oncology. 2025;20(1):3. doi: 10.1186/s13014-024-02575-7.
- Chen S et al. Natural Language Processing to Automatically Extract the Presence and Severity of Esophagitis in Notes of Patients Undergoing Radiotherapy. JCO Clinical Cancer Informatics. 2023;7:e2300048. doi: 10.1200/CCI.23.00048.