電気鍼治療と漢方アイロン療法を組み合わせることで、患者の便秘症状と生活の質を効果的に改善することができます。ここでは、機能性便秘に対する電気鍼治療と漢方アイロン療法を組み合わせた治療プロセスを説明するためのプロトコルを紹介します。
この記事について
サマリー
要約
機能性便秘(FC)は、複雑な排便、不完全な排便、排便の頻度の低下、乾燥して硬い便などの主な臨床症状を伴う機能不全の胃腸疾患であり、患者の生活の質と心理に深刻な影響を及ぼします。電気鍼治療は、腸の蠕動運動を促進するために体内の特定のポイントに鍼治療を行うことにより、便秘を改善します。漢方アイロン療法(CMIT)は、経絡を温め、局所的な血液循環を促進し、胃腸のダイナミクスを促進し、胃内容排出を促進することができます。この研究では、機能性便秘に対するCMITと組み合わせた電気鍼治療の方法と手順について、患者の選択、材料の準備、手術手順、術後ケア、予防措置などについて詳しく説明しました。また、この方法の治療効果も評価しました。この研究の結果、4週間の治療後、西洋医学単独と比較して、CMITと組み合わせた電気鍼治療は、FC患者の随意排便の頻度、便秘、および生活の質を改善できることが示されました。明らかな副作用はありませんでした。
概要
機能性便秘(FC)1は、患者さんの生活の質に深刻な影響を与える慢性消化器疾患で、主に複雑な排便、低便、硬便やしこり便、排便のこわばり2を伴います。FCは、患者3の生活や心理に大きな影響を与え、腹痛4、睡眠障害5、結腸がん6、循環器疾患7などの重篤な疾患を誘発する必須因子である。研究によると、世界人口の約10%〜15%がFC8の影響を受けています。FCは慢性で治療が不十分であり、患者の50%近くが従来の治療に完全に満足しておらず9、患者10,11に重大な財政負担を課す重大な公衆衛生問題として。FCの治療手段には、一般的な治療(水分摂取量の増加、食物繊維の補給12,13、および運動14)および薬理学的治療(容積性下剤15、浸透圧性下剤16、覚醒剤下剤17、5-ヒドロキシトリプタミン4受容体作動薬18、およびプロバイオティクス19,20,21)が含まれます。).しかし、ほとんどの薬には、薬物依存、下痢、膨満感、鼓腸、腸のけいれん、食道閉塞などの副作用があります。そのため、副作用の少ないFCの効果的な治療法の探求は、臨床医の注目を集めています。
鍼灸は古代中国で生まれた治療法で、様々な消化器疾患の治療によく用いられています。鍼治療に基づいて、電気鍼治療は軽度で継続的な電気刺激を適用して、針の感覚を強化し、臨床効果を向上させます。電気鍼治療は、毎週の完全自発排便(CSBM)22を改善し、ブリストル便フォームスケール(BSFS)スコア23を上げました。このメカニズムは、腸の運動性24を促進し、結腸25における5-ヒドロキシトリプタミンおよびトリプトファンヒドロキシラーゼを増加させることに関連している可能性があります。一般に、電気鍼治療は、FC患者の臨床症状を効果的に改善し26、患者の生活の質と治療満足度を高めることができます23,27。
漢方アイロン療法(CMIT)とは、漢方薬の袋(レイヤン袋と呼ばれる)を加熱し、特定のポイントで戻したり回転させたりすることを意味します。CMITは、侵害受容神経の興奮性を低下させ、血液循環を改善し、腸の運動性を促進し、薬と体温の物理的効果を通じて便秘を改善します28。一般にフェンネルと呼ばれるFoeniculum vulgareミルは、主にCMITで、 気を促進し、 経絡を温め、脾臓と胃の隆起を調整して停滞を排除し、便29を渡す能力を発揮するために使用されています。
この研究では、鍼治療とCMITを組み合わせ、FC患者の胃腸の経穴に作用して便秘症状を改善し、FC患者を治療するための新しく効果的な方法を提供しました。
プロトコル
自貢第一人民病院の治験審査委員会は、臨床プログラムを審査し、承認しました。この研究では、治療プロセス、治療原理、および副作用が患者に詳細に説明され、患者はインフォームドコンセントフォームに署名した後に実施されました。
1. 患者の評価
- 包含基準:
- 機能性便秘のローマIV診断基準を満たす患者を含めます30。
- 性別に関係なく、21歳から69歳までの患者を含めます。
- 治療前(>14日)に、便秘の治療に薬が使用されていないことを確認してください(緊急時を除く)。
- 他の進行中の臨床研究に関与していない患者を含めます。
- 電子結腸内視鏡検査によって確認された器質性腸疾患のない患者を含めます。
- 研究への参加を志願し、インフォームドコンセントに署名した患者を含めます。
- 除外基準
- 他の内分泌疾患、代謝性疾患、神経疾患、術後疾患、または薬物誘発性便秘の患者を除外します。.
- 過敏性腸症候群、炎症性腸疾患、またはその他の構造性腸疾患の患者は除外します。.
- 精神疾患、認知機能障害、または失語症の患者を除外します。
- 過去 4 週間以内に鍼治療と CMIT を受けた患者は除外します。
- 心臓ペースメーカーを装着している患者を除外します。.
- 介入手段
- ランダム比較表法を使用して、患者を4つのグループに分けます。
注: この研究に関与するグループは、対照群、実験群 A (電気鍼治療群)、実験グループ B (CMIT グループ)、およびグループ C (電気鍼治療 + CMIT グループ) です。対照群には、Management of Functional Constipation in Children and Adults31 と Consensus Opinion on Integrated Chinese and Western Medicine Treatment of Functional Constipation (2017)32 に導かれた標準化された治療が受けられました。 - すべての患者が水分(毎日2000mLの水)と食物繊維の摂取量(30g)を増やし、良好な排便習慣(1日1回)を身に付け、自転車やウォーキングなどの定期的な運動(週3回、30分)を行ったことを確認します。
- 対照群の患者に、ラクツロース経口溶液を1日3回、毎回15mLを食事の前に4週間与えます33。
- 実験群Aの患者を電気鍼治療で30分間、1週間に5回、対照群に基づいて4週間治療します。
- 実験グループ B の患者を CMIT で CMIT で毎日 20 分間、対照群に基づいて 4 週間治療します。
- 実験群Cの患者を電気鍼治療(30分、週5回)およびCMIT(毎日20分)で、対照群に基づいて4週間治療します。
- 4週間後、週1回の完全自発排便(CSBM)34、クリーブランド便秘スコアリングシステム(CSS)35、および便秘の患者評価による生活の質(PAC-QOL)36により、2つのグループの治療効果を評価します。
- ランダム比較表法を使用して、患者を4つのグループに分けます。
2. 材料の準備
- 電気鍼治療器具を準備します(図1)。
- 漢方薬のアイロン療法に必要な使い捨て滅菌布バッグ、フェンネルシード、使い捨て滅菌手袋を準備します(図2)。
3. 治療プロセス
- 電気鍼治療
- 体の姿勢:患者を治療ベッドに横たえ、リラックスして快適に過ごします。
- ツボを見つけて選択します。
- 肘縞の外側端と上腕骨の外部上顆37との間の線の中央にQuchi(LI11)を配置します(図3)。
- Shangjuxu(ST37)ポイントを下腿の前外側、Dubiの6寸(12 cm38)下に、脛骨37 の前端から1本の交差指(中指)で位置します(図4)。
注:子午線とツボ39の研究に従ってポイントを選択します。CunはTCMの特別な測定単位です。これは、遠位指節間関節と人差し指の近位指節間関節との間の距離です。文献に基づくと、1 cunは約2.0〜2.2 cm38,40です。
- 75%アルコールを使用して、オペレーターの手と患部の皮膚を消毒し、感染を防ぎます。
注:電気鍼治療は、皮膚の損傷、結節、および瘢痕化を避ける必要があります。暖かく保ち、感情的にリラックスしたままでください。 - 患者の両側のQuchi(LI11)およびShangjuxu(ST37)ポイントに針を垂直に挿入します 1寸(2 cm38)持ち上げる、挿入する、ねじる、回転する、およびその他の操作により、患者は痛みやしびれを感じます。
- 電気鍼治療器具の波形を連続波41、周波数を1.5Hz、電流強度を0.5mAに設定します。(図 5)。
- 鍼治療を週5回、30分ずつ4週間行います。
- 漢方アイロン療法
- 患者の腹部のアイロン領域を調べて、破損のない皮膚の完全性を確認します。
- フェンネル(300g)を使い捨ての滅菌布袋(20cm×30cm)に入れ、電子レンジで3分(温度50〜70°C)加熱し、レイヤン袋をしっかりと結びます。
- 滅菌手袋を着用し、患者の腹部の皮膚を露出させ、中湾(CV12)、神楽(CV8)、天州(ST25)、および関元(CV4)にレイヤンバッグを塗布します(図6)。
- 患者のへそを中心にしてレイヤンバッグを時計回りに押します。
- 最初は、より軽い圧力を使用し、少し速く動かします。レイアンバッグの温度が下がったら、より強い圧力をゆっくりと、約5分間使用します。
- 患者の皮膚が灼熱感を伴わずに暖かく感じたら、レイヤンバッグをZhongwan(CV12)に適用して、温湿布を続けます(図7)。各ツボにレイヤンバッグを5分間適用します。これを1日1回、20分間、4週間の治療を行います。
4. 統計解析
- 連続変数を平均±標準偏差として表します。マルチグループ比較には一元配置分散分析を使用し、グループ間のペアワイズ比較にはLSD-t検定を使用します。
- カテゴリ変数をケース (パーセンテージ) として表し、カイ 2 乗検定を使用してグループを比較します。テスト水準 α = 0.05 (両側)。
結果
この研究では、2022年8月から2022年12月までに自貢第一人民病院に通った60人のFC患者をスクリーニングし、対象としました。乱数表法を用いて、患者を対照群、実験群A(電気鍼治療群)、実験群B(CMIT群)、C群(電気鍼治療+CMIT群)に分け、それぞれ15例ずつとした。4つのグループ間で性別、年齢、および疾患の期間に統計的な差はなかった( 表1を参照のこと)。
治療前と治療後にCSBM、CSS、PAC-QOLの質問票を実施した。治療前は、すべての群のCSBM、CSS、およびPAC-QOLスコアに統計的な差はなく、同等であった。4週間の治療後、すべてのグループでCSBMが増加し、CSSスコアが減少しました。グループCのCSBM、CCS、およびPAC-QOLスコアは、対照グループ、グループAおよびBよりも良好でした(p < 0.05)。BグループのPAC-QOLスコアはAグループよりも良好でした(p < 0.05)( 表2参照)。この結果は、CMITと組み合わせた電気鍼治療が、患者の自発的な排便、便秘、および生活の質の頻度を改善できることを示唆しています。重篤な副作用は全群で発生しませんでした。
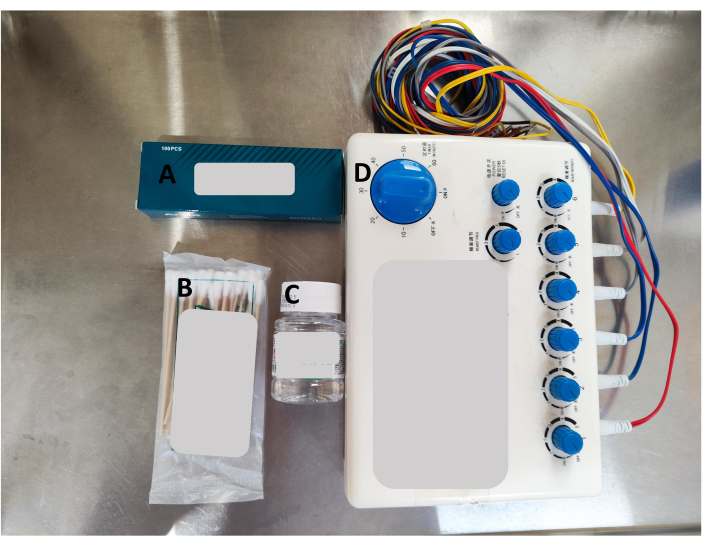
図1:電気鍼治療用材料 (A)鍼治療用鍼。(B)75%エタノール消毒剤。(C)医療用綿棒。(D)電子針治療器具。 この図の拡大版を表示するには、ここをクリックしてください。

図2:漢方アイロン療法用材料( A)フェンネル。(B)使い捨て滅菌布袋。(C)使い捨て滅菌手袋。 この図の拡大版を表示するには、ここをクリックしてください。

図3:Quchi(LI11)のツボの位置。 肘の縞の外側の端と上腕骨の外部上顆との間の線の中央にツボを配置します。 この図の拡大版を表示するには、ここをクリックしてください。

図4:Shangjuxu(ST37)のツボの位置。 脛骨の前端から1本の交差指(中指)で、下肢の前外側、Dubiの下6寸(12 cm38)にツボを配置します。 この図の拡大版を表示するには、ここをクリックしてください。

図5:Quchi(LI11)とShangjuxu(ST37)の電気鍼治療。この図の拡大版を表示するには、ここをクリックしてください。

図6:腹部アイロン治療のためのツボ。 Zhongwan(CV12)は上腹部、前正中線、臍の4F-cun上にありました。シェンケ(CV8)は臍の真ん中にいました。Tianshu(ST25)は腹部、水平臍帯にあり、前正中線から2F-cunでした。Guanyuan(CV4)は下腹部、正中線前方、および臍の3F-cun下にありました。 この図の拡大版を表示するには、ここをクリックしてください。

図7:中湾(CV12)にレイヤンバッグを置いて、アイロンがけを続けます。この図の拡大版を表示するには、ここをクリックしてください。
| 群 | 男性 | 女性 | 年齢 | 病気の期間 |
| 対照群(n=15) | 7 | 8 | 61.93±5.77 | 3.77 ± 1.84 |
| 実験グループA (n = 15) | 8 | 7 | 60.53±5.39 | 3.37 ± 1.68 |
| 実験グループB(n = 15) | 8 | 7 | 61.33 ± 4.40 | 3.53 ± 1.48 |
| 実験グループC(n = 15) | 7 | 8 | 62.13 ± 4.38 | 3.74±1.55 |
| x2&F | 0.57 | 0.305 | 2.093 | |
| p | 0.61 | 0.822 | 0.112 | |
表1:ベースライン時の患者の特性。
| 群 | CSBMの | CCSスコア | PAC-QOLスコア | |||
| 治療前 | 治療後 | 治療前 | 治療後 | 治療前 | 治療後 | |
| 対照群 (n = 15) | 1.57 ± 0.75 | 3.21 ± 0.80 | 24.57±5.08 | 19.64±5.07 | 63.64±3.61 | 55.21±3.66 |
| 実験グループA (n = 15) | 1.4 ± 0.63 | 3.73 ± 0.70A | 23.4 ± 4.94 | 15.2 ± 5.19a | 63.2 ± 6.45 | 52.33±4.56 |
| 実験グループB(n = 15) | 2±0.53 | 3.87 ± 0.99a | 25.13 ± 4.82 | 15.53±4.48A | 63.6 ± 3.85 | 47.87 ± 4.53AB |
| 実験グループC(n = 15) | 1.6 ± 0.91 | 4.13 ± 0.91ABC | 24.53±5.16 | 13.87 ± 5.55ABCの | 63.73±4.66 | 41.47 ± 5.78ABCの |
| F値 | 1.855 | 2.892 | 0.316 | 3.429 | 1.572 | 20.844 |
| p値 | 0.148 | 0.043 | 0.814 | 0.023 | 0.207 | <0.001 |
表2:CSBM、CSS、PAC-QOLスコアの比較。 (a、対照群と比較して、p< 0.05。 b、グループAと比較して、p<0.05。 グループ Bと比較したc、p < 0.05)。
ディスカッション
FCの主要な病態生理学的基礎は、交感神経の緊張と副交感神経の興奮性によって引き起こされる腸の運動性の低下である42。FCの病因は、腸の神経伝達物質機能障害、酸化ストレス指数バランスの乱れ、アクアポリン発現異常、血清イオンの異常な変化、腸内細菌叢障害、結腸直腸感覚および運動機能の異常、および心理的影響に関連している可能性があります43。FCの西洋医学治療は、主にさまざまな種類の下剤と胃腸の分裂促進薬に基づいています。これらの薬剤を長期間使用すると、吐き気、嘔吐、腹痛44、電解質障害45、結腸網膜症46,47を生じさせ、個人や社会の経済的負担を増大させる可能性がある。
漢方薬では、便秘は脾臓と胃と密接に関連していると考えられています48。FCのTCM治療には、鍼治療49,50、推術51、指圧52、ハーブアイロン53、ハーブ浣腸54など、さまざまな方法があり、効果的です。
FCは、世界保健機関(WHO)が電気鍼治療に推奨する43の一般的な疾患の1つです55。便秘や下痢の治療における鍼治療の有効性は、上位2位にランクされ、56であり、独特の利点があります。研究によると、鍼治療は腸の運動性を高め22、胃腸機能を調節し、便秘症状を軽減することができる57。
Shenque (CV8) ツボでの電気鍼治療は、機能性便秘に苦しむラットの糞便水分量と腸内輸送速度を改善することが証明されています。これは、おそらくアクアポリン-3 (AQP3) 発現と核因子-κB (NF-κB) シグナル伝達経路の調節によるものです58。
フェンネルは、消化器系、内分泌系、生殖器系、呼吸器系59に関連するさまざまな病気に伝統医学で使用されてきました。フェンネルには、抗酸化作用、抗炎症作用、抗菌作用、抗血栓作用、降圧作用、胃保護作用、肝保護作用、記憶力増強作用、抗変異原性作用など、多くの薬理学的効果があります60。加熱されたレイヤンバッグは、腹部のZhongwan(CV12)、Shenque(CV8)などのツボを刺激し、気を促進し、うっ血を取り除き、側副血を取り除きます。重大な腸排泄の方向に沿った腹部マッサージは、小腸と大腸のリズミカルな収縮を増加させ、輸送をスピードアップし、便を柔らかくして排出しやすくします61,62。
鍼治療は侵襲的な手術であり、鍼の失神、針の刺し込み、出血、創傷感染のリスクを伴う可能性があるため、機能を実行し、無菌性認識を促進するには経験豊富な医師が必要です。この研究では、電気鍼治療を使用して、鍼治療の感覚を高め、治療効果を改善し、一方では鍼治療の一貫性を確保し、さまざまなオペレーターが鍼治療を行うことによる試験への影響を回避しました。
本研究で選ばれたツボはQuchi(LI11)とShangjuxu(ST37)で、これらはそれぞれ大腸の動員点であり、下部治癒の終了点である。これらのポイントは両方とも、内臓の病気を治療するためのTCMの主要なツボと考えられており、FC34の患者に一般的に使用されています。Quchi(LI11)とShangjuxu(ST37)の組み合わせは、内側のfu-organsを治療するために使用されるHe-seaポイントの適合性に属しています。内京は、合算点と低い合算点の効果は同じだと考えている63。以前の研究64 では、He-seaポイントの適合性がCSBMを大幅に増加させ、患者の排便困難と生活の質を改善し、ポイントとポイントの組み合わせにより、治療中止後4週間有効性を維持できることが示されています。
過熱したレイヤンバッグは患者の不快感を高め、さらには皮膚の火傷を引き起こすため、治療の開始時にレイヤンバッグを優しく素早く動かし、患者がレイヤンバッグの温度に慣れた後、継続的なアイロン治療のために中湾(CV12)に置く必要があります。
本研究にはいくつかの制限があります。まず、FCは低速伝送、出口閉塞、混合タイプに分けられ、動作が異なります1。この研究では、FCはタイプ化されておらず、さまざまなタイプのFCに関連する有効性指標の比較が不足していたため、CMITと組み合わせた電気鍼治療に敏感なFCのタイプを明確にすることができませんでした。第二に、この研究はサンプルサイズが小さい単一施設研究であり、併存疾患が治療効果に及ぼす不均一な影響は分析されていません。したがって、FC に対する CMIT と組み合わせた電気鍼治療の臨床的利点と欠点を調査し、既存の治療法を補完し、CMIT と組み合わせた電気鍼治療が FC の最良の治療法であるかどうかを調査するには、さらなる試験が必要です。
西洋医学単独と比較して、CMITと組み合わせた電気鍼治療は、患者の自発的な排便、便秘、および生活の質の頻度を改善することができます。
開示事項
著者には開示すべき利益相反はありません。
謝辞
本研究は、四川省科学技術局の重点研究開発計画(主要科学技術特別プロジェクト)(番号:2022YFS0392)および四川省伝統中国医学行政局の重点分野構築プロジェクト(番号:202072)の支援を受けて行われました。
材料
| 名前 | 会社 | カタログ番号 | コメント |
|---|---|---|---|
| 75%アルコール消毒剤 | 山東安塁高済消毒技術有限公司 | Q / 371402AAJ008 | |
| 吸収綿棒 | Zigong Jisheng医療機器有限公司 | チュアン機械登録20162140199 | |
| 鍼治療針(0.25 mm x 50 mm) | 蘇州医療用品工場有限公司 | 蘇機械登録20162270970 | |
| 使い捨て滅菌布袋 | 自貢第一人民病院材料部門 | N / A | |
| 使い捨て滅菌手袋 | Kefu Medical Technology Co. Ltd | Xiang機械登録20202140410 | |
| フェンネル | 州Huayi漢方薬スライス Co.LTD | 岳20160614 | |
| G91-Aタイプ電子針治療器具と支持電極線 | 蘇州医療用品工場有限公司 | Suマシン登録20172270675 | |
| ラクツロース経口溶液 | Abbott Trading (Shanghai) Co., Ltd | H11022318 |
参考文献
- Savarino, E., et al. Functional bowel disorders with diarrhea: Clinical guidelines of the United European Gastroenterology and European Society for Neurogastroenterology and Motility. United European Gastroenterol J. 10 (6), 556-584 (2022).
- Bassotti, G., Villanacci, V. A practical approach to diagnosis and management of functional constipation in adults. Intern Emerg Med. 8 (4), 275-282 (2013).
- Prichard, D. O., Bharucha, A. E. Recent advances in understanding and managing chronic constipation. F1000Res. 7, F1000 Faculty Rev-1640 (2018).
- Wong, M. Y. W., Hebbard, G., Gibson, P. R., Burgell, R. E. Chronic constipation and abdominal pain: Independent or closely interrelated symptoms. J Gastroenterol Hepatol. 35 (8), 1294-1301 (2020).
- Moezi, P., et al. Prevalence of chronic constipation and its associated factors in Pars cohort study: A study of 9000 adults in Southern Iran. Middle East J Dig Dis. 10 (2), 75-83 (2018).
- Song, E. M., et al. Long-term risks of Parkinson's disease, surgery, and colorectal cancer in patients with slow-transit constipation. Clin Gastroenterol Hepatol. 19 (12), 2577-2586 (2021).
- Sumida, K., et al. Constipation and risk of death and cardiovascular events. Atherosclerosis. 281, 114-120 (2019).
- Barberio, B., Judge, C., Savarino, E. V., Ford, A. C. Global prevalence of functional constipation according to the Rome criteria: a systematic review and meta-analysis. Lancet Gastroenterol Hepatol. 6 (8), 638-648 (2021).
- Nelson, A. D., et al. Comparison of efficacy of pharmacological treatments for chronic idiopathic constipation: a systematic review and network meta-analysis. Gut. 66 (9), 1611-1622 (2017).
- Han, D., Iragorri, N., Clement, F., Lorenzetti, D., Spackman, E. Cost effectiveness of treatments for chronic constipation: A systematic review. Pharmacoeconomics. 36 (4), 435-449 (2018).
- van Mill, M. J., Koppen, I. J. N., Benninga, M. A. Controversies in the management of functional constipation in children. Curr Gastroenterol Rep. 21 (6), 23(2019).
- Suares, N. C., Ford, A. C. Systematic review: the effects of fiber in the management of chronic idiopathic constipation. Aliment Pharmacol Ther. 33 (8), 895-901 (2011).
- Lai, H., et al. Effects of dietary fibers or probiotics on functional constipation symptoms and roles of gut microbiota: a double-blinded randomized placebo trial. Gut Microbes. 15 (1), 2197837(2023).
- Gao, R., et al. Exercise therapy in patients with constipation: a systematic review and meta-analysis of randomized controlled trials. Scand J Gastroenterol. 54 (2), 169-177 (2019).
- Jalanka, J., et al. The effect of Psyllium husk on intestinal microbiota in constipated patients and healthy controls. Int J Mol Sci. 20 (2), 433(2019).
- Piche, T., Dapoigny, M. Comparative efficacy and safety of lactulose plus paraffin vs polyethylene glycol in functional constipation: a randomized clinical study. United European Gastroenterol J. 8 (8), 923-932 (2020).
- Wei, L., et al. Topical therapy with rhubarb navel plasters in patients with chronic constipation: Results from a prospective randomized multicenter study. J Ethnopharmacol. 264, 113096(2021).
- Camilleri, M., et al. Efficacy and safety of Prucalopride in chronic constipation: An integrated analysis of six randomized, controlled clinical trials. Dig Dis Sci. 61 (8), 2357-2372 (2016).
- Zhang, C., et al. Meta-analysis of randomized controlled trials of the effects of probiotics on functional constipation in adults. Clin Nutr. 39 (10), 2960-2969 (2020).
- Dimidi, E., Mark Scott, S., Whelan, K. Probiotics and constipation: mechanisms of action, evidence for effectiveness and utilization by patients and healthcare professionals. Proc Nutr Soc. 79 (1), 147-157 (2020).
- Martoni, C. J., Evans, M., Chow, C. T., Chan, L. S., Leyer, G. Impact of a probiotic product on bowel habits and microbial profile in participants with functional constipation: A randomized controlled trial. J Dig Dis. 20 (9), 435-446 (2019).
- Liu, Z., et al. Acupuncture for chronic severe functional constipation: A randomized trial. Ann Intern Med. 165 (11), 761-769 (2016).
- Yao, J. P., et al. Effectiveness and safety of acupuncture for treating functional constipation: An overview of systematic reviews. J Integr Med. 20 (1), 13-25 (2022).
- Zhang, X., et al. Effect of manual acupuncture, electroacupuncture and moxibustion on intestinal motility and expression of enteric nervous activity related proteins in functional constipation rats. Zhen Ci Yan Jiu. 42 (5), 407-412 (2017).
- Zhu, X., et al. The effect and mechanism of electroacupuncture at LI11 and ST37 on constipation in a rat model. Acupunct Med. 34 (3), 194-200 (2016).
- Li, P., et al. Efficacy and safety of acupuncture at Tianshu (ST25) for functional constipation: Evidence from 10 randomized controlled trials. Evid Based Complement Alternat Med. 2020, 2171587(2020).
- Wu, X., et al. Electroacupuncture for functional constipation: A multicenter, randomized, control trial. Evid Based Complement Alternat Med. 2017, 1428943(2017).
- Liu, J., et al. Comparative observation on the curative effect of Chinese medicine ironing and ear point pressing after anal fistula operation. Sichuan Chinese Medicine. 39 (10), 205-208 (2021).
- Qin, C., et al. Effect of hot cumin compresses on gastrointestinal function recovery after laparoscopic radical colorectal cancer surgery. Chinese Journal of Modern Medicine. 29 (20), 92-95 (2019).
- Mearin, F., et al. Bowel disorders. Gastroenterology. 150 (6), 1393-1407 (2016).
- Vriesman, M. H., Koppen, I. J. N., Camilleri, M., Di Lorenzo, C., Benninga, M. A. Management of functional constipation in children and adults. Nat Rev Gastroenterol Hepatol. 17 (1), 21-39 (2020).
- Li, J., et al. Consensus opinion on the combined diagnosis and treatment of functional constipation in Chinese and Western medicine (2017). Chinese Journal of Integrative Medicine and Digestion. 26 (01), 18-26 (2018).
- Lv, Y., et al. Combining Chinese and Western medicine therapy in treating functional constipation in 52 cases is effective. Chinese Journal of Anorectal Diseases. 42 (09), 37-39 (2022).
- Zhu, J., et al. Efficacy and safety of vibrating capsule for functional constipation (VICONS): A randomized, double-blind, placebo-controlled, multicenter trial. EClinicalMedicine. 47, 101407(2022).
- Tsai, Y. J., Yang, Y. W., Lan, Y. T. Translation and validation of the traditional Chinese version of the constipation severity instrument. J Chin Med Assoc. 84 (3), 299-302 (2021).
- Ibarra, A., Latreille-Barbier, M., Donazzolo, Y., Pelletier, X., Ouwehand, A. C. Effects of 28-day Bifidobacterium animalis subsp. lactis HN019 supplementation on colonic transit time and gastrointestinal symptoms in adults with functional constipation: A double-blind, randomized, placebo-controlled, and dose-ranging trial. Gut Microbes. 9 (3), 236-251 (2018).
- Zhong, F., et al. A randomized controlled study on treating functional constipation by electroacupuncture of the large intestine with acupuncture points under the acupuncture points with matching ends. Sichuan TCM. 36 (04), 185-188 (2018).
- Park, H. J., et al. A comparison between directional and proportional methods in locating acupuncture points using dual-energy X-ray absorptiometry in Korean women. American Journal of Chinese Medicine. 34 (5), 749-757 (2006).
- Shen, X. Y. Meridians and Acupoints. , People's Military Medical Press. Singing Dragon, London and Philadelphia. (2010).
- Godson, D. R., Wardle, J. L. Accuracy and precision in acupuncture point location: A critical systematic review. Journal of Acupuncture and Meridian Studies. 12 (2), 52-66 (2019).
- Zhang, H. Cupping treatment the clinical effect of the treatment of functional constipation and experimental research. Liaoning University of Chinese Medicine. , (2019).
- Black, C. J., Drossman, D. A., Talley, N. J., Ruddy, J., Ford, A. C. Functional gastrointestinal disorders: advances in understanding and management. Lancet. 396 (10263), 1664-1674 (2020).
- An, D. W., et al. Progress in the study of the mechanism of functional constipation. Chinese Modern Physicians. 61 (04), 121-128 (2023).
- Hao, Z., et al. Effectiveness of concomitant use of green tea and polyethylene glycol in bowel preparation for colonoscopy: a randomized controlled study. BMC Gastroenterol. 20 (1), 150(2020).
- Wu, S., et al. Assessment of the effectiveness, compliance, and effect on blood electrolytes of polyethylene glycol, mannitol, and magnesium sulfate in bowel preparation before colonoscopy. China Practical Medicine. 14 (30), 88-89 (2019).
- Xiao, J. Discovery of a case of pharmacogenetic colonic melanosis and thoughts on pharmacy services. Practical Drugs and Clinics. 26 (03), 237-240 (2023).
- Zhang, Z., et al. Progress of research on the effects and mechanisms of anthraquinone-containing herbal medicines on colonic melanosis. Journal of Tianjin University of Traditional Chinese Medicine. 41 (04), 539-544 (2022).
- Li, G., et al. Overview of research on the treatment of functional constipation with Chinese medicine specialties. Henan TCM. 43 (01), 146-151 (2023).
- Ma, Q., et al. Clinical study on treating Yang deficiency type chronic functional constipation with warm acupuncture and moxibustion at the Eight Shao points. Journal of Guangzhou University of Traditional Chinese Medicine. 40 (02), 363-367 (2023).
- Liu, S., et al. Clinical exploration of acupuncture and moxibustion for treating functional constipation in the elderly based on the five viscera Yuanzhen flux theory. Chinese Journal of Basic Chinese Medicine. 28 (11), 1841-1844 (2022).
- Wang, Y., et al. Current clinical research on treating functional constipation in the elderly with acupressure points. Massage and Rehabilitation Medicine. 13 (24), 44-46 (2022).
- Xia, J., et al. Clinical observation on treating functional constipation by acupuncture point application of Yi Qi intestine moving cream. Chinese Traditional Chinese Medicine Science and Technology. 29 (05), 834-836 (2022).
- Hu, Y., et al. The efficacy of using Ziwu Liujiao herbal hot ironing, abdominal massage, and laxative formula to prevent functional constipation. Clinical Research in Chinese Medicine. 12 (22), 18-21 (2020).
- Zhang, S., et al. Effect of Chinese herbal enema combined with acupressure in treating elderly patients with functional constipation. Chinese Journal of Drug Abuse Prevention and Control. 28 (12), 1870-1873 (2022).
- Ebrary, I. Acupuncture: Review and analysis reports on controlled clinical trials. , Available from: https://iama.edu/wp-content/uploads/2019/10/acupuncture_WHO_full_report.pdf (2019).
- Du, Y., et al. Study on the spectrum of acupuncture diseases in the digestive system. Clinical Journal of Acupuncture and Moxibustion. 3, 1-2 (2006).
- Liu, L., et al. Evaluation of the safety and efficacy of acupuncture in treating chronic functional constipation. Liaoning Journal of Traditional Chinese Medicine. 48 (03), 159-162 (2021).
- Xie, L., et al. Exploring the improvement mechanism of gastrointestinal dynamics of functional constipation by electroacupuncture at Shenqui point based on water channel protein 3 and nuclear transcription factor-κB signaling pathway. Journal of Anhui University of Traditional Chinese Medicine. 40 (05), 64-69 (2021).
- Badgujar, S. B., Patel, V. V., Bandivdekar, A. H. Foeniculum vulgare Mill: a review of its botany, phytochemistry, pharmacology, contemporary application, and toxicology. Biomed Res Int. 2014, 842674(2014).
- Rahimi, R., Ardekani, M. R. Medicinal properties of Foeniculum vulgare Mill. in traditional Iranian medicine and modern phytotherapy. Chin J Integr Med. 19 (1), 73-79 (2013).
- Li, Y. R. Effect evaluation of Chinese medicine Remai Bao combined with acupoint hot compress nursing intervention in elderly patients with chronic functional constipation. Chronic Epidemiology Magazine. 23 (4), 638-640 (2022).
- Wang, Y. Q. Observation on nursing effect of Wuren reyan bag pushing and ironing external application on senile constipation. Hunan Journal of Traditional Chinese Medicine. 36 (11), 111-113 (2020).
- Ma, P. H., et al. Theoretical basis and clinical application of "Hezhi inner government". Jilin Province Traditional Chinese medicine. 5 (01), 81-84 (2017).
- Wu, J., et al. Comparison of efficacy of different acupuncture points in treating functional constipation: randomized controlled trial. Chinese Journal of Acupuncture and Moxibustion. 34 (06), 521-528 (2014).
再版と許可
この記事は公開されました
動画は近日公開