本研究では、大腿骨近位部骨折後の看護師主導による胃腸耐性適応型骨粗鬆症ケアパスを評価します。このケアパスでは、リスク層別化、レジメン選択、構造化されたフォローアップ、およびトリガーに基づく最適化を用いることで、24か月にわたる治療の継続性、アドヒアランス、およびアウトカムの把握を改善します。
このコンテンツを表示するには、JoVEへの購読が必要です。 または、無料トライアルをお申し込みください。
この記事について
サマリー
要約
高齢者は大腿骨近位部骨折後、その後の脆弱性骨折を起こすリスクが高いままですが、退院後の抗骨粗鬆症療法は遅延、中断、あるいは中止されることが頻繁にあります。この単施設非ランダム化縦断的実装研究では、大腿骨近位部骨折の手術治療を受けた高齢者を対象に、看護師主導の胃腸(GI)耐性適応型骨粗鬆症ケアパスを評価しました。合計147名の参加者が登録され、そのうち73名が看護師主導パス群に、74名が通常ケア群に割り当てられました。介入内容には、退院時のGI耐性リスク層別化、安全性確認、耐性適応型のレジメン選択、標準化された患者教育、1週間後および1、3、6、12、18、24カ月後の構造化フォローアップ、および治療再評価のための事前定義された基準が含まれていました。アウトカムには、実装の忠実度、適時な治療開始、処方日数充足率(PDC)で測定した服薬アドヒアランス、治療継続性、骨密度(BMD)の変化、GI副作用、および最初に確認されたその後の脆弱性骨折が含まれました。通常ケアと比較して、看護師主導パスでは、GIリスク層別化、教育チェックリストの完了、安全性ラボレビュー、適時な治療開始、フォローアップの完了、および二重エネルギーX線吸収法(DXA)評価の実施率が高くなりました。平均PDCおよびPDC ≥0.80を達成した参加者の割合は、24カ月間のフォローアップ期間を通じて、介入群で一貫して高い値を示しました。腰椎および全股関節のBMDはパス群でより大きな改善を示しましたが、大腿骨頸部のBMD変化はわずかでした。その後の脆弱性骨折までの期間に関するイベントタイム分析では介入群が有利な結果となりましたが、イベント数が限定的であることと非ランダム化研究デザインであることを考慮し、慎重に解釈する必要があります。これらの知見は、看護師主導のGI耐性適応型骨粗鬆症ケアパスが実現可能であり、大腿骨近位部骨折後の治療継続性を向上させる可能性があることを示しています。BMDおよび再骨折アウトカムへの効果を確認するためには、より大規模な多施設共同ランダム化比較試験が必要です。
概要
高齢者の大腿骨近位部骨折は、機能低下、障害、施設入所、および死亡率の上昇に関連しているため、重大な公衆衛生上の課題となっている1。初回の大腿骨近位部骨折後、特に骨折後早期における二次的な脆弱性骨折のリスクは非常に高く、二次骨折の予防は長期的な回復において不可欠な要素である2。現在の臨床ガイドラインでは、骨折後の管理に抗骨粗鬆症薬物療法を組み込むことが推奨されているが、退院後の治療開始および長期的な継続は一貫していない3。この実装上のギャップが、急性期の外科的治療から持続的な骨折予防管理への移行を妨げている。
骨粗鬆症治療の有効性は、時間の経過とともに適切な薬剤曝露を維持できるかどうかにかかっています。骨密度(BMD)の改善および骨折リスクの低減には、一般的に単なる治療の開始よりも、持続的なアドヒアランス(服薬遵守)と治療継続が必要です4。骨粗鬆症の管理においてアドヒアランスの低下は一般的であり、治療効果の減弱に関連しています5。実臨床研究において、一般的に認められているアドヒアランスの閾値を下回る薬剤カバー率は、その後の骨折リスクの増加に関連していることが示されています6。したがって、アドヒアランスは重要なケアプロセスの指標であるだけでなく、骨格系のアウトカムを決定する中間要因としても機能します7。特に大腿骨近位部骨折後において長期的なアドヒアランスを維持することは困難です。なぜなら、回復過程において、フレイル、ポリファーマシー(多剤併用)、介護者への依存、可動性の制限、および退院後の断片的なフォローアップなどが複雑に絡み合うことが多いためです8。
胃腸(GI)不耐症は、持続的な骨粗鬆症治療における重要な障壁となります。経口ビスホスホネート製剤は特定の投与条件を必要とし、胃食道逆流症状、嚥下困難、体位制限、便秘、または上部GI疾患の既往がある高齢者では耐容性が低い場合があります9。GI症状により、服用忘れや、医師の指示のない治療中断、あるいは永続的な治療中止につながる可能性があります10。フォローアップが不十分な場合や、処方箋の更新情報が病院と地域の薬局システムに分散している場合、これらの問題は見過ごされる可能性があります。退院前にGIリスクを特定し、不耐症の兆候を治療の適時な再評価に結びつける構造化されたケアパスウェイは、回避可能な治療中断を減少させるのに役立つと考えられます。
看護師主導の骨折連携サービスおよび骨折後ケアモデルは、脆弱性骨折後の骨粗鬆症アセスメント、患者教育、治療開始、およびケア調整を改善することが示されています11。看護師は、体系的な教育の提供、症状のモニタリング、介護者とのコミュニケーション、薬剤の補充管理、および治療に関する障壁が生じた際の医師や薬剤師による再評価の調整を行うのに適した立場にあります12。しかし、多くの骨折後ケアモデルでは診断と治療開始が重視されているものの、レジメン選択や長期的なフォローアップの体系的な構成要素として、胃腸(GI)への耐容性を組み込んでいるものは比較的少数です13。GIリスク層別化と継続的なアドヒアランスモニタリングの統合は、長期的な抗骨粗鬆症治療を必要とする一方で、複雑な経口治療レジメンの耐容に困難を伴う可能性がある大腿骨近位部骨折から回復中の高齢者にとって、特に価値があると考えられます。
したがって、本研究では、大腿骨近位部骨折の手術治療後の高齢者を対象とした、看護師主導でGI耐性に適応させた抗骨粗鬆症ケアパスを評価しました。このケアパスには、退院時のGIリスク評価、安全性確認、耐性に適応した治療法の選択、標準化された患者教育、構造化された長期フォローアップ、および治療最適化のための事前定義された基準が組み込まれています。本研究では、実施忠実度、服薬アドヒアランスおよび継続性、骨密度の変化、GI副作用、および24か月間にわたる初回後続脆弱性骨折の発生を評価しました。治療の割り付けはランダム化ではなくケアパスの実施に基づいているため、後続骨折アウトカムの分析は、確定的ではなく、探索的かつ仮説生成的なものであると考えられました。
アクセスが制限されています。このコンテンツを表示するにはログインするか、トライアルを開始してください。
プロトコル
The study was approved by the Ethics Committee of Ziyang Central Hospital, West China Hospital Ziyang Branch, Sichuan University (Approval ID: 2026(115)). Written informed consent was obtained from all participants or their legally authorized representatives before enrollment. All procedures were conducted in accordance with the Declaration of Helsinki and institutional guidelines for clinical research involving human participants.
Study design and setting
This single-center, non-randomized, parallel-group controlled implementation study evaluated a nurse-led gastrointestinal (GI) tolerability–adapted anti-osteoporosis care pathway for older adults following surgical treatment of hip fracture. The study was conducted at Ziyang Central Hospital, West China Hospital Ziyang Branch, Sichuan University, between January 2021 and December 2024. Participants were followed for 24 months after hospital discharge. The study was reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines14. Participant screening, group allocation, follow-up schedule, and analysis-set construction are summarized in Figure 1. The prespecified outcome definitions and 24-month assessment schedule are summarized in Supplementary Table 1.
Participants were allocated based on the implementation of the nurse-led pathway rather than by randomization. Patients admitted before pathway implementation (January 2021–December 2022) received usual care, whereas those admitted after implementation (January 2023–December 2024) were managed using the nurse-led pathway. To minimize temporal bias, identical eligibility criteria, follow-up schedules, outcome definitions, DXA assessment windows, adherence calculations, and refracture adjudication procedures were applied to both groups. The calendar period was included in the adjusted and sensitivity analyses.
Participants
Consecutive inpatients aged ≥65 years admitted with a low-energy femoral neck or intertrochanteric hip fracture were screened for eligibility. Low-energy fractures were defined as fractures resulting from a fall from standing height or lower.
Participants were eligible if they were ≥65 years of age, underwent surgical treatment for a low-energy femoral neck or intertrochanteric fracture, survived to hospital discharge, were considered eligible for anti-osteoporosis therapy after assessment of renal function, corrected calcium, and vitamin D status, had complete baseline clinical and medication data, were able to participate in follow-up directly or through a caregiver, and provided written informed consent.
Participants were excluded if they sustained high-energy trauma, had pathological fractures secondary to malignancy or metabolic bone disease other than osteoporosis, had an expected survival of <6 months, had severe renal impairment (estimated glomerular filtration rate <30 mL/min/1.73 m2), uncorrected hypocalcemia, active upper GI bleeding, severe esophageal stricture, unstable gastrointestinal disease requiring urgent treatment, prior anti-osteoporosis therapy for >3 months during the preceding year, lacked reliable follow-up or caregiver support, or declined participation.
Baseline assessment
Baseline assessments were completed during the index hospitalization, preferably within 48 h before discharge. Demographic and clinical variables included age, sex, body mass index, fracture type, surgical procedure, time from admission to surgery, length of hospital stay, smoking status, alcohol consumption, previous fragility fracture, comorbidities, medication history, caregiver availability, and baseline GI risk factors. Comorbidity burden was assessed using the Charlson Comorbidity Index, and frailty was evaluated using the Clinical Frailty Scale.
Baseline laboratory investigations included serum calcium, albumin, corrected calcium, phosphate, creatinine, estimated glomerular filtration rate, alkaline phosphatase, 25-hydroxyvitamin D, and parathyroid hormone, where available. Medication review focused on nonsteroidal anti-inflammatory drugs, antiplatelet agents, anticoagulants, proton pump inhibitors, glucocorticoids, sedatives, and previous anti-osteoporosis medications.
Bone mineral density (BMD) was assessed using dual-energy X-ray absorptiometry (DXA) before discharge whenever feasible. If pre-discharge DXA could not be performed, scanning was completed within 4–6 weeks after discharge and considered the baseline assessment. Measurements were obtained at the lumbar spine, femoral neck, and total hip, with the contralateral non-fractured hip preferentially selected for hip measurements.
Usual care
Participants assigned to the usual-care group received routine perioperative management, standard discharge counseling, physician-directed anti-osteoporosis therapy, and routine outpatient follow-up in accordance with institutional practice. Structured GI risk stratification, nurse-led treatment selection, proactive refill monitoring, and predefined treatment-modification algorithms were not incorporated into usual care.
Nurse-led GI tolerability–adapted pathway
The nurse-led pathway was initiated before discharge and continued throughout the 24-month follow-up period. A specialist osteoporosis nurse coordinated care among orthopedic surgeons, geriatricians or endocrinologists, pharmacists, rehabilitation staff, DXA and laboratory services, and community healthcare providers. The workflow for GI risk assessment, treatment selection, follow-up, and regimen modification is illustrated in Figure 2.
Before discharge, GI tolerability was categorized as low, moderate, or high risk according to predefined clinical criteria (Supplementary Table 2). Risk classification incorporated gastrointestinal history, swallowing ability, ability to remain upright after medication administration, concomitant medications, and current GI symptoms.
Treatment selection was individualized according to GI risk, renal function, corrected calcium concentration, 25-hydroxyvitamin D status, fracture risk, patient preference, and anticipated follow-up compliance. Patients at low GI risk were preferentially prescribed oral bisphosphonates with standardized administration instructions. Patients at moderate risk received oral therapy only when administration requirements could be reliably followed; otherwise, non-oral antiresorptive therapy was recommended. Patients classified as high GI risk preferentially received intravenous zoledronic acid or subcutaneous denosumab after confirmation of treatment safety and physician approval. Calcium and vitamin D supplementation were recommended unless contraindicated.
Before discharge, the specialist nurse completed a standardized education checklist covering medication administration, dosing schedule, calcium and vitamin D supplementation, recognition of warning symptoms, refill procedures, follow-up appointments, and contact information. Patients receiving oral bisphosphonates received additional education on fasting administration with water, maintaining an upright posture for at least 30 min after dosing, separating from food and calcium supplements, and promptly reporting GI symptoms.
Trigger-based regimen optimization
Treatment optimization followed the decision algorithm shown in Figure 2. Gastrointestinal triggers included new or worsening reflux, nausea, vomiting, epigastric pain, abdominal pain, dysphagia, constipation, suspected GI bleeding, or any GI symptom interfering with medication adherence. Adherence triggers included missed prescription refills; treatment interruptions exceeding 30 days for oral therapy; delayed injections or infusions exceeding 30 days; early PDC <0.80; patient-reported discontinuation; or caregiver-reported treatment difficulties.
Mild symptoms prompted reinforcement of medication administration techniques, pharmacist review of concomitant medications, dietary and constipation management, and repeat assessment within 7–14 days. Persistent symptoms or recurrent non-adherence prompted multidisciplinary reassessment involving the treating physician, pharmacist, and specialist nurse. Management included temporary treatment interruption, gastroprotective therapy when appropriate, transition from oral to injectable therapy, simplification of the treatment regimen, or referral for community nursing support. Severe symptoms, suspected GI bleeding, progressive dysphagia, dehydration, or hospitalization required urgent physician assessment and discontinuation or modification of therapy.
Outcomes and follow-up
The primary outcome was medication continuity, assessed using the proportion of days covered (PDC), adherence target attainment, and treatment persistence. Secondary outcomes included changes in bone mineral density (BMD) at prespecified skeletal sites and the time to first confirmed subsequent fragility fracture. Safety outcomes included gastrointestinal (GI) adverse events, other treatment-related adverse events, regimen switching, temporary treatment interruption, permanent treatment discontinuation, adverse event-related hospitalization, and death. Outcome definitions and the 24-month assessment schedule are provided in Supplementary Table 1.
Follow-up assessments were performed at 1 week and at 1, 3, 6, 12, 18, and 24 months after discharge in both study groups. At each follow-up, medication exposure, refill status, adherence barriers, GI symptoms, other adverse events, falls, suspected refractures, hospitalizations, deaths, and treatment modifications were recorded. DXA examinations were repeated at 12 and 24 months whenever feasible.
Medication adherence and persistence
Medication adherence was assessed using the proportion of days covered (PDC), which estimates medication availability over a defined observation period15. The observation period began on the date of discharge following the index hip-fracture admission and ended at 24 months, death, withdrawal, or the last confirmed follow-up, whichever occurred first. Time-specific PDC values were calculated at 1, 3, 6, 12, 18, and 24 months. PDC was calculated as the number of covered medication days divided by the total eligible follow-up days, capped at 1.00. A PDC ≥0.80 was considered to indicate adequate adherence, consistent with commonly accepted thresholds in osteoporosis research16. PDC was interpreted as a measure of medication availability rather than confirmed medication ingestion.
Medication dispensing and refill data were obtained from hospital outpatient pharmacy records, discharge prescriptions, electronic medical records, external prescription documentation, community pharmacy receipts, medication packages presented or photographed during follow-up, and structured nursing records. External pharmacy use without documentary verification was documented but excluded from the primary PDC analysis and included only in the expanded-source sensitivity analysis. For oral therapies, covered days were calculated based on the dispensed quantity and the prescribed dosing interval. Each confirmed denosumab injection contributed 180 covered days, whereas each confirmed zoledronic acid infusion contributed 365 covered days. Overlapping medication supplies were carried forward without double-counting.
Treatment persistence was defined as continuous anti-osteoporosis therapy without a clinically meaningful treatment gap. Non-persistence was defined as an interruption exceeding 60 days for oral therapy or more than 90 days beyond the scheduled administration date for injectable or infusion therapies. The date, duration, cause, and corrective action associated with each interruption were recorded. Permanent discontinuation was defined as the absence of anti-osteoporosis medication coverage for the remainder of the follow-up period after treatment interruption.
BMD assessment
Bone mineral density was measured at the lumbar spine, femoral neck, and total hip using dual-energy X-ray absorptiometry (DXA). Absolute BMD change was expressed in g/cm2, and relative BMD change was calculated as:
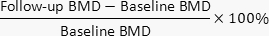
Site-specific BMD changes were classified using the least significant change approach for serial DXA interpretation17. An increase in BMD was defined as a relative gain >3.0% from baseline, whereas a decrease was defined as a relative loss >3.0%. Changes between −3.0% and +3.0% were classified as stable BMD. Participants without valid baseline and follow-up DXA measurements at the same anatomical site were excluded from site-specific BMD analyses but remained eligible for adherence and refracture analyses.
Refracture ascertainment
A subsequent fragility fracture was defined as a new low-energy fracture occurring after discharge from the index hip-fracture admission. At each follow-up visit, participants were screened for suspected refractures by recording new falls, focal pain, emergency department visits, hospitalizations, imaging examinations, or fracture diagnoses made at other institutions. Refractures were confirmed using imaging reports, hospital records, discharge summaries, or external medical documentation. Events reported only during interviews, without radiographic or medical-record confirmation, were classified as suspected refractures and excluded from the primary analysis.
The event date was defined as the injury date when available, or, if unavailable, as the date of the first medical encounter. Only the first confirmed refracture was included in the primary time-to-event analysis. Fracture location, confirmation source, and the interval between symptom onset and confirmation were recorded. All refracture events were independently reviewed by two clinicians, and disagreements were resolved by a senior orthopedic specialist.
GI adverse-event grading
Gastrointestinal adverse events were graded using a predefined four-level clinical severity scale. Grade 1 events consisted of mild symptoms that did not require treatment interruption or additional medication. Grade 2 events comprised moderate symptoms requiring additional medical management, pharmacist or physician review, intensified follow-up, or treatment interruption of ≤14 days. Grade 3 events included symptoms resulting in discontinuation of the current regimen, treatment interruption exceeding 14 days, outpatient or emergency evaluation, or a change in the route of administration. Grade 4 events represented serious GI complications, including suspected or confirmed GI bleeding, gastrointestinal perforation, severe dehydration, or hospitalization. The relationship between each event and anti-osteoporosis therapy was classified by the treating physician as unrelated, possibly related, probably related, or definitely related.
Implementation fidelity and KPI thresholds
Implementation fidelity was evaluated using predefined indicators, including completion of GI risk stratification, discharge education checklist completion, baseline safety laboratory review, treatment initiation within 1 month and within 90 days, calcium and vitamin D supplementation when indicated, completion of scheduled follow-up, DXA completion, documentation of GI adverse-event assessments, completion of trigger-based interventions, and completeness of refracture adjudication. Prespecified key performance indicator (KPI) thresholds and corrective-action criteria are summarized in Figure 3 and Supplementary Table 3.
The predefined KPI targets were as follows: GI risk stratification completion ≥90% by discharge or within 1 week; discharge education checklist completion ≥85%; baseline safety laboratory review ≥85% before treatment selection; treatment initiation ≥70% within 1 month and ≥85% within 90 days; follow-up completion ≥80% through 6 months and ≥75% at 24 months; DXA completion ≥70% at 24 months; documented GI adverse-event assessment ≥85%; and confirmed refracture adjudication ≥95%. Failure to achieve predefined KPI targets triggered additional patient contact, caregiver engagement, staff retraining, pharmacist collaboration, community nursing support, or reassessment of the treatment regimen.
Sample size
The sample size calculation was based on the primary adherence outcome. Pilot data from the study center and published osteoporosis adherence studies suggested a mean 24-month PDC of 0.55 in the usual-care group and 0.68 in the pathway group, corresponding to an anticipated between-group difference of 0.13. Assuming a pooled standard deviation of 0.25, a two-sided α of 0.05, and 80% statistical power, a minimum of 59 participants per group was required. Allowing for a 20% attrition rate over the 24-month follow-up period, the target enrollment was approximately 74 participants per group. The final study cohort comprised 147 participants, including 73 in the pathway group and 74 in the usual-care group. The study was not powered to detect differences in refracture outcomes; therefore, refracture analyses were considered secondary and exploratory.
Statistical analysis
Statistical analyses were performed using R version 4.3.2 and SPSS version 27.0. All statistical tests were two-sided, and a P < 0.05 was considered statistically significant. Continuous variables are presented as the mean ± standard deviation or median (interquartile range), as appropriate, whereas categorical variables are presented as frequencies and percentages. Between-group comparisons were performed using Student's t-test or the Mann–Whitney U test for continuous variables and the chi-square or Fisher's exact test for categorical variables. Baseline comparability was assessed using P values and standardized mean differences.
The primary analysis followed the intention-to-treat principle, with all participants analyzed according to their original group allocation. A per-protocol analysis was also performed after excluding participants with major protocol deviations, withdrawal of consent, or no post-discharge adherence data available.
PDC was analyzed both as a continuous outcome and as a binary variable, using the predefined adherence threshold of PDC ≥ 0.80. Continuous PDC values were evaluated using linear regression, whereas binary adherence outcomes were analyzed using log-binomial regression or modified Poisson regression with robust standard errors. Multivariable models were adjusted for age, sex, fracture type, surgical procedure, Charlson Comorbidity Index, previous fragility fracture, baseline GI risk category, estimated glomerular filtration rate, baseline 25-hydroxyvitamin D concentration, baseline BMD, and calendar period.
Longitudinal BMD changes were analyzed using linear mixed-effects models with fixed effects for treatment group, time, and the group-by-time interaction, together with participant-specific random intercepts. Separate analyses were performed for the lumbar spine, total hip, and femoral neck. Time to first confirmed refracture was evaluated using Kaplan–Meier survival curves, the log-rank test, and Cox proportional hazards regression. The proportional hazards assumption was assessed using Schoenfeld residuals. Because the number of refracture events was limited, hazard ratio estimates were interpreted as exploratory. Death before refracture was evaluated using Fine–Gray competing-risk regression18.
Missing data were summarized by study group, variable, follow-up time point, and reason for missingness. Multiple imputation by chained equations was used for missing covariates and repeated non-event outcomes when the missing-at-random assumption was considered plausible19. Because follow-up completion varied across study groups, prespecified sensitivity analyses for missing-not-at-random were performed. For adherence analyses, a conservative worst-case scenario classified participants lost to follow-up in the pathway group as non-adherent and those lost to follow-up in the usual-care group as adherent at 24 months. For BMD analyses, missing pathway-group DXA values were imputed to the 10th percentile of observed changes, whereas missing usual-care values were imputed to the 90th percentile. For refracture analyses, a conservative event-assignment scenario assumed that participants lost to follow-up in the pathway group experienced a refracture at the midpoint between their last contact and 24 months, whereas participants lost to follow-up in the usual-care group were censored at their last confirmed follow-up. A tipping-point analysis was performed by varying the assumed outcomes among participants lost to follow-up until the principal between-group conclusions were no longer statistically or clinically meaningful.
Prespecified subgroup analyses evaluated the effects of age, sex, GI risk category, renal function, baseline BMD category, and previous fragility fracture. Interaction terms were assessed within the regression models, and all subgroup analyses were considered exploratory.
アクセスが制限されています。このコンテンツを表示するにはログインするか、トライアルを開始してください。
結果
コホートの登録、割り当て、および追跡調査の把握
外科的に治療された大腿骨近位端骨折を持つ高齢者計198名を対象に適格性のスクリーニングを行いました。51名の参加者は、選択基準を満たさなかった(n = 29)、参加を拒否したかインフォームドコンセントが得られなかった(n = 12)、重篤な併存疾患があるか予想生存期間が6か月未満であった(n = 6)、または介護者がいないか有効な連絡先がなくフォローアップを完了できなかった(n = 4)ため、除外されました。最終的な研究コホートは147名の参加者で構成され、そのうち73名が看護師主導の胃腸(GI)耐性適応パスウェイ群に、74名が通常ケア群に割り当てられました。参加者のスクリーニング、群への割り付け、フォローアップ、および解析セットの構築を図1に示します。通常ケア群の参加者は看護師主導パスウェイの導入前に登録され、パスウェイ群の参加者は導入後に登録されました。
ベースラインの二重エネルギー...
アクセスが制限されています。このコンテンツを表示するにはログインするか、トライアルを開始してください。
ディスカッション
この単一施設、非ランダム化実装研究では、大腿骨近位部骨折の手術治療後における高齢者を対象とした、看護師主導の胃腸(GI)耐性適応型抗骨粗鬆症ケアパスウェイを評価した。最も一貫した結果が得られたのは、ケアプロセスの実行と調剤ベースの服薬アドヒアランスであった。通常ケアと比較して、パスウェイ群では、GIリスク層別化、退院教育、安全性に関する検査値レビュー、治療開始、フォローアップの捕捉、および24か月間のPDC(処方日数充足率)ベースのアドヒアランスがより完全に実施されていた。これらの結果は、二次性骨折予防プロセスの改善における、構造化された骨折後ケアモデルの役割と一致している20。BMDの変化および再骨折に関連するイベント発生までの期間の推定値は方向性としては良好であったが、DXA完了率が群間で異なり、サンプルサイズが限定的であり、再骨折イベント数も少なかったため、解釈には注意が必要である。
このパスウェイは主に、急性期の外科的エピソード後、つまり骨粗鬆症治療の開始、モニタリング、および継続を院外で行わなければならない退院後に発生するケ...
アクセスが制限されています。このコンテンツを表示するにはログインするか、トライアルを開始してください。
開示事項
著者らは、本研究に関連して競合する金銭的利益および利益相反がないことを宣言します。
謝辞
著者らは、患者のスクリーニング、パスウェイの実施、および長期的なフォローアップにおいて支援をいただいた研究センターの看護スタッフ、整形外科チーム、およびフォローアップ担当者に感謝いたします。また、本研究にご協力いただいたすべての患者様とそのご家族に感謝申し上げます。本研究は、[以下、組織名が続く]の健康福祉局による支援を受けて行われました。 成都市龍泉驿区(助成金番号 WJKY2025020)
アクセスが制限されています。このコンテンツを表示するにはログインするか、トライアルを開始してください。
材料
| 名前 | 会社 | カタログ番号 | コメント |
|---|---|---|---|
| 25-ヒドロキシビタミンDアッセイ | Beckman Coulter | Access 25(OH) Vitamin D Total Kit, B24838 | 骨吸収抑制療法前のベースラインビタミンD評価および安全性確認。 |
| 症例報告書 | Study site | Local document set | 適格性、ベースライン特性、骨折の詳細、投薬歴、フォローアップ状況、有害事象、およびアウトカムの標準化された収集。 |
| 化学分析装置 | Roche Diagnostics | cobas 8000 modular analyzer series, cobas c 702 module | 血清カルシウム、アルブミン、リン酸塩、クレアチニン、アルカリホスファターゼ、およびその他のルーチン化学指標の測定。 |
| 退院指導チェックリスト | Study site | Local document set | 薬剤指導、投与方法、警告症状、補充計画、およびフォローアップスケジュールの標準化された記録。 |
| DXA解析ソフトウェア | GE HealthCare | enCORE software platform | 関心領域(ROI)の定義、BMD算出、および連続DXA比較。 |
| DXA骨密度測定装置 | GE HealthCare | Lunar iDXA | ベースライン、12ヶ月、および24ヶ月時点での腰椎、大腿骨頸部、および全股関節の骨密度の測定。 |
| 外部処方補充記録 | External hospitals / community pharmacies | Not applicable | 外部処方箋、院外薬局の領収書、薬剤パッケージ、または介護者が提供した補充記録の確認。 |
| GI耐容性リスクチェックリスト | Study site | Local document set | GI症状、GI疾患歴、嚥下能力、直立保持の可否、GIリスク薬剤、便秘、および多剤併用の記録。 |
| 病院電子カルテシステム | Study hospital | Local institutional EMR/HIS | 入院データ、手術データ、検査結果、退院時処方、外来記録、および入院イベントの抽出。 |
| 院内薬剤調剤システム | Study hospital | Local institutional pharmacy information system | PDC算出のための退院時処方、外来補充日、調剤量、および薬剤供給情報の抽出。 |
| 免疫測定分析装置 | Beckman Coulter | Access 2 Immunoassay System | 血清25-ヒドロキシビタミンDの測定プラットフォーム。 |
| 服薬アドヒアランスワークシート | Study site | Local spreadsheet template | PDC、補充間隔、中断期間、持続状況、および拡張ソース感度分析の算出。 |
| セキュアデータキャプチャプラットフォーム | REDCap Consortium / study hospital | REDCap or local institutional EDC | データ入力、監査証跡、ロールベースアクセス、クエリ解決、および解析データセットのエクスポート。 |
| 統計ソフト | IBM | IBM SPSS Statistics 27.0 | 記述統計、ベースライン比較、および使用された品質管理分析。 |
| 統計ソフト | R Foundation for Statistical Computing | R, version recorded in analysis log | 回帰分析、混合効果モデル、Kaplan–Meier曲線、Coxモデル、競合リスクモデル、多重代入法、および感度分析。 |
| 構造化フォローアップスクリプト | Study site | Local document set | 1週間、1ヶ月、3ヶ月、6ヶ月、12ヶ月、18ヶ月、および24ヶ月時点での電話またはクリニックでのフォローアップ。 |
| トリガー・レスポンスログ | Study site | Local document set | GI不耐容、補充忘れ、治療ギャップ、レジメンの再評価、切り替え決定、および是正処置の記録。 |
参考文献
- Haentjens P, et al. Meta-analysis: excess mortality after hip fracture among older women and men. Ann Intern Med. 2010;152:380-390.
- Banefelt J, et al. Risk of imminent fracture following a previous fracture in a Swedish database study. Osteoporos Int. 2019;30:601-609.
- Conley RB, et al. Secondary fracture prevention: consensus clinical recommendations from a multistakeholder coalition. J Bone Miner Res. 2020;35:36-52.
- Caro JJ, Ishak KJ, Huybrechts KF, Raggio G, Naujoks C. The impact of compliance with osteoporosis therapy on fracture rates in actual practice. Osteoporos Int. 2004;15:1003-1008.
- Siris ES, et al. Impact of osteoporosis treatment adherence on fracture rates in North America and Europe. Am J Med. 2009;122:S3-S13.
- Siris ES, et al. Adherence to bisphosphonate therapy and fracture rates in osteoporotic women: relationship to vertebral and nonvertebral fractures from 2 US claims databases. Mayo Clin Proc. 2006;81:1013-1022.
- Keshishian A, et al. Examining the effect of medication adherence on risk of subsequent fracture among women with a fragility fracture in the U.S. Medicare population. J Manag Care Spec Pharm. 2017;23:1178-1190.
- Reyes BJ, et al. Postacute management of older adults suffering an osteoporotic hip fracture: a consensus statement from the International Geriatric Fracture Society. Geriatr Orthop Surg Rehabil. 2020;11:2151459320935100.
- Siris ES, et al. Association between gastrointestinal events and compliance with osteoporosis therapy. Bone Rep. 2015;4:5-10.
- Kennel KA, Drake MT. Adverse effects of bisphosphonates: implications for osteoporosis management. Mayo Clin Proc. 2009;84:632-638.
- Marsh D, et al. Coordinator-based systems for secondary prevention in fragility fracture patients. Osteoporos Int. 2011;22:2051-2065.
- Le HV, et al. Fracture liaison service: a multidisciplinary approach to osteoporosis management. Osteoporos Int. 2024;35:1719-1727.
- Hiligsmann M, et al. Determinants, consequences and potential solutions to poor adherence to anti-osteoporosis treatment: results of an expert group meeting organized by the European Society for Clinical and Economic Aspects of Osteoporosis, Osteoarthritis and Musculoskeletal Diseases and the International Osteoporosis Foundation. Osteoporos Int. 2019;30:2155-2165.
- von Elm E, et al. The Strengthening the Reporting of Observational Studies in Epidemiology statement: guidelines for reporting observational studies. Lancet. 2007;370:1453-1457.
- Prieto-Merino D, et al. Estimating proportion of days covered using real-world online medicine suppliers' datasets. J Pharm Policy Pract. 2021;14:113.
- Cadarette SM, Burden AM. Measuring and improving adherence to osteoporosis pharmacotherapy. Curr Opin Rheumatol. 2010;22:397-403.
- Kendler DL, et al. Repeating measurement of bone mineral density when monitoring with dual-energy X-ray absorptiometry: 2019 ISCD official position. J Clin Densitom. 2019;22:489-500.
- Fine JP, Gray RJ. A proportional hazards model for the subdistribution of a competing risk. J Am Stat Assoc. 1999;94:496-509.
- van Buuren S, Groothuis-Oudshoorn K. mice: multivariate imputation by chained equations in R. J Stat Softw. 2011;45:1-67.
- Ganda K, et al. Models of care for the secondary prevention of osteoporotic fractures: a systematic review and meta-analysis. Osteoporos Int. 2013;24:393-406.
- Lems WF, et al. EULAR/EFORT recommendations for management of patients older than 50 years with a fragility fracture and prevention of subsequent fractures. Ann Rheum Dis. 2017;76:802-810.
- Lam WY, Fresco P. Medication adherence measures: an overview. Biomed Res Int. 2015;2015:217047.
- Lyles KW, et al. Zoledronic acid and clinical fractures and mortality after hip fracture. N Engl J Med. 2007;357:1799-1809.
- Bliuc D, et al. Mortality risk associated with low-trauma osteoporotic fracture and subsequent fracture in men and women. JAMA. 2009;301:513-521.
- Hemming K, et al. The stepped wedge cluster randomised trial: rationale, design, analysis, and reporting. BMJ. 2015;350:h391.
アクセスが制限されています。このコンテンツを表示するにはログインするか、トライアルを開始してください。