본 연구는 고관절 골절 후 간호사 주도의 위장관 내약성 맞춤형 골다공증 관리 경로를 평가합니다. 이 관리 경로는 위험 층화, 약제 선택, 체계적인 추적 관찰 및 트리거 기반 최적화를 활용하여 24개월 동안 치료의 연속성, 복약 순응도 및 결과 포착 능력을 향상시키는 것을 목표로 합니다.
이 콘텐츠를 보려면 JoVE 구독이 필요합니다. 로그인하거나 오늘 무료 평가판을 시작하세요.
이 논문에서
요약
초록
고령자는 고관절 골절 후 후속 취약성 골절의 위험이 높지만, 퇴원 후 골다공증 치료가 지연, 중단 또는 중단되는 경우가 빈번합니다. 본 단일 센터, 비무작위 종단적 구현 연구에서는 고관절 골절의 수술적 치료를 받은 고령자를 대상으로 간호사 주도의 위장관(GI) 내약성 맞춤형 골다공증 관리 경로를 평가했습니다. 총 147명의 참가자가 등록되었으며, 이 중 73명은 간호사 주도 경로 그룹에, 74명은 통상적 관리 그룹에 배정되었습니다. 중재 단계에는 퇴원 시 위장관 내약성 위험 계층화, 안전성 검증, 내약성 맞춤형 처방 선택, 표준화된 환자 교육, 1주 및 1, 3, 6, 12, 18, 24개월 차의 구조화된 추적 관찰, 그리고 치료 재평가를 위한 사전 정의된 기준이 포함되었습니다. 결과 지표로는 구현 충실도, 적시 치료 시작, 약물 복용 비율(PDC)로 측정한 약물 순응도, 치료 지속성, 골밀도(BMD) 변화, 위장관 이상 반응 및 첫 번째로 확인된 후속 취약성 골절이 포함되었습니다. 통상적 관리와 비교했을 때, 간호사 주도 경로는 위장관 위험 계층화, 교육 체크리스트 완료, 안전성 실험실 검토, 적시 치료 시작, 추적 관찰 완료 및 이중 에너지 X선 흡수법(DXA) 평가에서 더 높은 비율을 달성했습니다. 평균 PDC와 PDC ≥0.80을 달성한 참가자의 비율은 24개월의 추적 관찰 기간 내내 중재 그룹에서 일관되게 더 높았습니다. 요추와 전체 고관절 BMD는 경로 그룹에서 더 큰 개선을 보인 반면, 대퇴경부 BMD 변화는 더 작았습니다. 후속 취약성 골절에 대한 사건 발생 시간 분석은 중재 그룹에 유리했으나, 제한된 사건 수와 비무작위 연구 설계로 인해 주의해서 해석해야 합니다. 이러한 결과는 간호사 주도의 위장관 내약성 맞춤형 골다공증 관리 경로가 실행 가능하며, 고관절 골절 후 치료 연속성을 개선할 수 있음을 보여줍니다. BMD 및 재골절 결과에 미치는 영향을 확인하기 위해 더 대규모의 다센터 무작위 연구가 필요합니다.
서론
고령자의 고관절 골절은 기능 저하, 장애, 시설 입소 및 사망률 증가와 관련이 있어 주요한 공중 보건 과제로 꼽힙니다1. 첫 고관절 골절 이후, 특히 골절 초기 단계에서 후속 취약성 골절의 위험이 매우 높기 때문에, 이차 골절 예방은 장기 회복의 필수적인 요소가 됩니다2. 현재의 임상 가이드라인은 골절 후 관리에 항골다공증 약물 치료를 포함할 것을 권고하고 있으나, 퇴원 후 치료 시작 및 장기 지속률은 여전히 일관되지 않은 실정입니다3. 이러한 실행 격차는 급성 수술 치료에서 지속적인 골절 예방 관리로의 전환을 제한합니다.
골다공증 치료의 효과는 시간이 지남에 따라 적절한 약물 노출을 유지하는 것에 달려 있습니다. 골밀도(BMD)의 개선과 골절 위험의 감소는 일반적으로 단순히 치료를 시작하는 것보다 지속적인 복약 순응도와 치료 유지율이 필요합니다4. 골다공증 관리에서 낮은 순응도는 흔히 나타나며, 이는 치료 효과의 감소와 관련이 있습니다5. 실제 임상 연구에서 일반적으로 인정되는 순응도 임계값보다 낮은 약물 복용률은 후속 골절 위험의 증가와 연관이 있는 것으로 나타났습니다6. 결과적으로, 순응도는 핵심적인 의료 프로세스 지표일 뿐만 아니라 골격 결과의 중간 결정 요인으로 작용합니다7. 특히 고관절 골절 이후에는 노쇠, 다제약물 복용, 간병인 의존도, 제한된 이동성, 그리고 파편화된 퇴원 후 추적 관찰로 인해 회복이 복잡해지는 경우가 많아 장기적인 순응도를 유지하는 것이 매우 어렵습니다8.
위장관(GI) 불내성은 지속적인 골다공증 치료의 중요한 장벽이 됩니다. 경구용 비스포스포네이트는 특정한 투여 조건이 필요하며, 위식도 역류 증상, 연하곤란, 자세 제한, 변비 또는 상부 위장관 질환 병력이 있는 고령 환자에게는 내약성이 낮을 수 있습니다9. 위장관 증상은 복약 누락, 감독 없는 치료 중단 또는 영구적인 치료 포기로 이어질 수 있습니다10. 추적 관찰이 일관되지 않거나 약물 처방 갱신 정보가 병원과 지역 약국 시스템에 분산되어 있을 때 이러한 문제는 발견되지 않은 채로 남을 수 있습니다. 퇴원 전 위장관 위험 요인을 식별하고 불내성 신호를 적시의 치료 재평가로 연결하는 구조화된 케어 경로(care pathway)는 피할 수 있는 치료 중단을 줄이는 데 도움이 될 수 있습니다.
간호사 주도의 골절 연계 서비스 및 골절 후 관리 모델은 취약성 골절 이후의 골다공증 평가, 환자 교육, 치료 시작 및 케어 조정을 개선하는 것으로 나타났습니다11. 간호사는 체계적인 교육을 제공하고, 증상을 모니터링하며, 간병인과 소통하고, 약물 처방 갱신을 추적하며, 치료 관련 장벽이 발생했을 때 의사나 약사의 재평가를 조정하기에 적합한 위치에 있습니다12. 하지만 많은 골절 후 관리 모델이 진단과 치료 시작을 강조함에도 불구하고, 위장관(GI) 내약성을 처방 선택 및 장기 추적 관찰의 체계적인 구성 요소로 통합한 경우는 상대적으로 적습니다13. 위장관 위험 층화와 지속적인 복약 순응도 모니터링을 통합하는 것은, 장기간의 항골다공증 치료가 필요하지만 복잡한 경구 치료법을 견디는 데 어려움을 겪을 수 있는 고관절 골절 회복기 고령자에게 특히 가치 있을 수 있습니다.
따라서 본 연구에서는 고관절 골절 수술 치료를 받은 노인을 대상으로 간호사 주도하에 위장관(GI) 내약성을 반영하여 조정한 골다공증 관리 경로를 평가하였습니다. 이 관리 경로에는 퇴원 시 위장관 위험도 평가, 안전성 확인, 내약성에 따른 치료법 선택, 표준화된 환자 교육, 체계적인 장기 추적 관찰 및 치료 최적화를 위한 사전 정의된 기준이 포함되었습니다. 본 연구에서는 24개월 동안의 이행 충실도, 약물 복용 순응도 및 지속성, 골밀도 변화, 위장관 이상 반응 및 첫 번째 후속 취약성 골절 발생 여부를 평가하였습니다. 치료 할당이 무작위 배정이 아닌 관리 경로의 이행을 기반으로 이루어졌으므로, 후속 골절 결과에 대한 분석은 확증적이기보다는 탐색적이며 가설 생성적인 것으로 간주되었습니다.
액세스가 제한되었습니다. 이 콘텐츠를 보려면 로그인하거나 체험판을 시작하세요.
프로토콜
The study was approved by the Ethics Committee of Ziyang Central Hospital, West China Hospital Ziyang Branch, Sichuan University (Approval ID: 2026(115)). Written informed consent was obtained from all participants or their legally authorized representatives before enrollment. All procedures were conducted in accordance with the Declaration of Helsinki and institutional guidelines for clinical research involving human participants.
Study design and setting
This single-center, non-randomized, parallel-group controlled implementation study evaluated a nurse-led gastrointestinal (GI) tolerability–adapted anti-osteoporosis care pathway for older adults following surgical treatment of hip fracture. The study was conducted at Ziyang Central Hospital, West China Hospital Ziyang Branch, Sichuan University, between January 2021 and December 2024. Participants were followed for 24 months after hospital discharge. The study was reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines14. Participant screening, group allocation, follow-up schedule, and analysis-set construction are summarized in Figure 1. The prespecified outcome definitions and 24-month assessment schedule are summarized in Supplementary Table 1.
Participants were allocated based on the implementation of the nurse-led pathway rather than by randomization. Patients admitted before pathway implementation (January 2021–December 2022) received usual care, whereas those admitted after implementation (January 2023–December 2024) were managed using the nurse-led pathway. To minimize temporal bias, identical eligibility criteria, follow-up schedules, outcome definitions, DXA assessment windows, adherence calculations, and refracture adjudication procedures were applied to both groups. The calendar period was included in the adjusted and sensitivity analyses.
Participants
Consecutive inpatients aged ≥65 years admitted with a low-energy femoral neck or intertrochanteric hip fracture were screened for eligibility. Low-energy fractures were defined as fractures resulting from a fall from standing height or lower.
Participants were eligible if they were ≥65 years of age, underwent surgical treatment for a low-energy femoral neck or intertrochanteric fracture, survived to hospital discharge, were considered eligible for anti-osteoporosis therapy after assessment of renal function, corrected calcium, and vitamin D status, had complete baseline clinical and medication data, were able to participate in follow-up directly or through a caregiver, and provided written informed consent.
Participants were excluded if they sustained high-energy trauma, had pathological fractures secondary to malignancy or metabolic bone disease other than osteoporosis, had an expected survival of <6 months, had severe renal impairment (estimated glomerular filtration rate <30 mL/min/1.73 m2), uncorrected hypocalcemia, active upper GI bleeding, severe esophageal stricture, unstable gastrointestinal disease requiring urgent treatment, prior anti-osteoporosis therapy for >3 months during the preceding year, lacked reliable follow-up or caregiver support, or declined participation.
Baseline assessment
Baseline assessments were completed during the index hospitalization, preferably within 48 h before discharge. Demographic and clinical variables included age, sex, body mass index, fracture type, surgical procedure, time from admission to surgery, length of hospital stay, smoking status, alcohol consumption, previous fragility fracture, comorbidities, medication history, caregiver availability, and baseline GI risk factors. Comorbidity burden was assessed using the Charlson Comorbidity Index, and frailty was evaluated using the Clinical Frailty Scale.
Baseline laboratory investigations included serum calcium, albumin, corrected calcium, phosphate, creatinine, estimated glomerular filtration rate, alkaline phosphatase, 25-hydroxyvitamin D, and parathyroid hormone, where available. Medication review focused on nonsteroidal anti-inflammatory drugs, antiplatelet agents, anticoagulants, proton pump inhibitors, glucocorticoids, sedatives, and previous anti-osteoporosis medications.
Bone mineral density (BMD) was assessed using dual-energy X-ray absorptiometry (DXA) before discharge whenever feasible. If pre-discharge DXA could not be performed, scanning was completed within 4–6 weeks after discharge and considered the baseline assessment. Measurements were obtained at the lumbar spine, femoral neck, and total hip, with the contralateral non-fractured hip preferentially selected for hip measurements.
Usual care
Participants assigned to the usual-care group received routine perioperative management, standard discharge counseling, physician-directed anti-osteoporosis therapy, and routine outpatient follow-up in accordance with institutional practice. Structured GI risk stratification, nurse-led treatment selection, proactive refill monitoring, and predefined treatment-modification algorithms were not incorporated into usual care.
Nurse-led GI tolerability–adapted pathway
The nurse-led pathway was initiated before discharge and continued throughout the 24-month follow-up period. A specialist osteoporosis nurse coordinated care among orthopedic surgeons, geriatricians or endocrinologists, pharmacists, rehabilitation staff, DXA and laboratory services, and community healthcare providers. The workflow for GI risk assessment, treatment selection, follow-up, and regimen modification is illustrated in Figure 2.
Before discharge, GI tolerability was categorized as low, moderate, or high risk according to predefined clinical criteria (Supplementary Table 2). Risk classification incorporated gastrointestinal history, swallowing ability, ability to remain upright after medication administration, concomitant medications, and current GI symptoms.
Treatment selection was individualized according to GI risk, renal function, corrected calcium concentration, 25-hydroxyvitamin D status, fracture risk, patient preference, and anticipated follow-up compliance. Patients at low GI risk were preferentially prescribed oral bisphosphonates with standardized administration instructions. Patients at moderate risk received oral therapy only when administration requirements could be reliably followed; otherwise, non-oral antiresorptive therapy was recommended. Patients classified as high GI risk preferentially received intravenous zoledronic acid or subcutaneous denosumab after confirmation of treatment safety and physician approval. Calcium and vitamin D supplementation were recommended unless contraindicated.
Before discharge, the specialist nurse completed a standardized education checklist covering medication administration, dosing schedule, calcium and vitamin D supplementation, recognition of warning symptoms, refill procedures, follow-up appointments, and contact information. Patients receiving oral bisphosphonates received additional education on fasting administration with water, maintaining an upright posture for at least 30 min after dosing, separating from food and calcium supplements, and promptly reporting GI symptoms.
Trigger-based regimen optimization
Treatment optimization followed the decision algorithm shown in Figure 2. Gastrointestinal triggers included new or worsening reflux, nausea, vomiting, epigastric pain, abdominal pain, dysphagia, constipation, suspected GI bleeding, or any GI symptom interfering with medication adherence. Adherence triggers included missed prescription refills; treatment interruptions exceeding 30 days for oral therapy; delayed injections or infusions exceeding 30 days; early PDC <0.80; patient-reported discontinuation; or caregiver-reported treatment difficulties.
Mild symptoms prompted reinforcement of medication administration techniques, pharmacist review of concomitant medications, dietary and constipation management, and repeat assessment within 7–14 days. Persistent symptoms or recurrent non-adherence prompted multidisciplinary reassessment involving the treating physician, pharmacist, and specialist nurse. Management included temporary treatment interruption, gastroprotective therapy when appropriate, transition from oral to injectable therapy, simplification of the treatment regimen, or referral for community nursing support. Severe symptoms, suspected GI bleeding, progressive dysphagia, dehydration, or hospitalization required urgent physician assessment and discontinuation or modification of therapy.
Outcomes and follow-up
The primary outcome was medication continuity, assessed using the proportion of days covered (PDC), adherence target attainment, and treatment persistence. Secondary outcomes included changes in bone mineral density (BMD) at prespecified skeletal sites and the time to first confirmed subsequent fragility fracture. Safety outcomes included gastrointestinal (GI) adverse events, other treatment-related adverse events, regimen switching, temporary treatment interruption, permanent treatment discontinuation, adverse event-related hospitalization, and death. Outcome definitions and the 24-month assessment schedule are provided in Supplementary Table 1.
Follow-up assessments were performed at 1 week and at 1, 3, 6, 12, 18, and 24 months after discharge in both study groups. At each follow-up, medication exposure, refill status, adherence barriers, GI symptoms, other adverse events, falls, suspected refractures, hospitalizations, deaths, and treatment modifications were recorded. DXA examinations were repeated at 12 and 24 months whenever feasible.
Medication adherence and persistence
Medication adherence was assessed using the proportion of days covered (PDC), which estimates medication availability over a defined observation period15. The observation period began on the date of discharge following the index hip-fracture admission and ended at 24 months, death, withdrawal, or the last confirmed follow-up, whichever occurred first. Time-specific PDC values were calculated at 1, 3, 6, 12, 18, and 24 months. PDC was calculated as the number of covered medication days divided by the total eligible follow-up days, capped at 1.00. A PDC ≥0.80 was considered to indicate adequate adherence, consistent with commonly accepted thresholds in osteoporosis research16. PDC was interpreted as a measure of medication availability rather than confirmed medication ingestion.
Medication dispensing and refill data were obtained from hospital outpatient pharmacy records, discharge prescriptions, electronic medical records, external prescription documentation, community pharmacy receipts, medication packages presented or photographed during follow-up, and structured nursing records. External pharmacy use without documentary verification was documented but excluded from the primary PDC analysis and included only in the expanded-source sensitivity analysis. For oral therapies, covered days were calculated based on the dispensed quantity and the prescribed dosing interval. Each confirmed denosumab injection contributed 180 covered days, whereas each confirmed zoledronic acid infusion contributed 365 covered days. Overlapping medication supplies were carried forward without double-counting.
Treatment persistence was defined as continuous anti-osteoporosis therapy without a clinically meaningful treatment gap. Non-persistence was defined as an interruption exceeding 60 days for oral therapy or more than 90 days beyond the scheduled administration date for injectable or infusion therapies. The date, duration, cause, and corrective action associated with each interruption were recorded. Permanent discontinuation was defined as the absence of anti-osteoporosis medication coverage for the remainder of the follow-up period after treatment interruption.
BMD assessment
Bone mineral density was measured at the lumbar spine, femoral neck, and total hip using dual-energy X-ray absorptiometry (DXA). Absolute BMD change was expressed in g/cm2, and relative BMD change was calculated as:
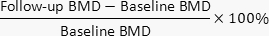
Site-specific BMD changes were classified using the least significant change approach for serial DXA interpretation17. An increase in BMD was defined as a relative gain >3.0% from baseline, whereas a decrease was defined as a relative loss >3.0%. Changes between −3.0% and +3.0% were classified as stable BMD. Participants without valid baseline and follow-up DXA measurements at the same anatomical site were excluded from site-specific BMD analyses but remained eligible for adherence and refracture analyses.
Refracture ascertainment
A subsequent fragility fracture was defined as a new low-energy fracture occurring after discharge from the index hip-fracture admission. At each follow-up visit, participants were screened for suspected refractures by recording new falls, focal pain, emergency department visits, hospitalizations, imaging examinations, or fracture diagnoses made at other institutions. Refractures were confirmed using imaging reports, hospital records, discharge summaries, or external medical documentation. Events reported only during interviews, without radiographic or medical-record confirmation, were classified as suspected refractures and excluded from the primary analysis.
The event date was defined as the injury date when available, or, if unavailable, as the date of the first medical encounter. Only the first confirmed refracture was included in the primary time-to-event analysis. Fracture location, confirmation source, and the interval between symptom onset and confirmation were recorded. All refracture events were independently reviewed by two clinicians, and disagreements were resolved by a senior orthopedic specialist.
GI adverse-event grading
Gastrointestinal adverse events were graded using a predefined four-level clinical severity scale. Grade 1 events consisted of mild symptoms that did not require treatment interruption or additional medication. Grade 2 events comprised moderate symptoms requiring additional medical management, pharmacist or physician review, intensified follow-up, or treatment interruption of ≤14 days. Grade 3 events included symptoms resulting in discontinuation of the current regimen, treatment interruption exceeding 14 days, outpatient or emergency evaluation, or a change in the route of administration. Grade 4 events represented serious GI complications, including suspected or confirmed GI bleeding, gastrointestinal perforation, severe dehydration, or hospitalization. The relationship between each event and anti-osteoporosis therapy was classified by the treating physician as unrelated, possibly related, probably related, or definitely related.
Implementation fidelity and KPI thresholds
Implementation fidelity was evaluated using predefined indicators, including completion of GI risk stratification, discharge education checklist completion, baseline safety laboratory review, treatment initiation within 1 month and within 90 days, calcium and vitamin D supplementation when indicated, completion of scheduled follow-up, DXA completion, documentation of GI adverse-event assessments, completion of trigger-based interventions, and completeness of refracture adjudication. Prespecified key performance indicator (KPI) thresholds and corrective-action criteria are summarized in Figure 3 and Supplementary Table 3.
The predefined KPI targets were as follows: GI risk stratification completion ≥90% by discharge or within 1 week; discharge education checklist completion ≥85%; baseline safety laboratory review ≥85% before treatment selection; treatment initiation ≥70% within 1 month and ≥85% within 90 days; follow-up completion ≥80% through 6 months and ≥75% at 24 months; DXA completion ≥70% at 24 months; documented GI adverse-event assessment ≥85%; and confirmed refracture adjudication ≥95%. Failure to achieve predefined KPI targets triggered additional patient contact, caregiver engagement, staff retraining, pharmacist collaboration, community nursing support, or reassessment of the treatment regimen.
Sample size
The sample size calculation was based on the primary adherence outcome. Pilot data from the study center and published osteoporosis adherence studies suggested a mean 24-month PDC of 0.55 in the usual-care group and 0.68 in the pathway group, corresponding to an anticipated between-group difference of 0.13. Assuming a pooled standard deviation of 0.25, a two-sided α of 0.05, and 80% statistical power, a minimum of 59 participants per group was required. Allowing for a 20% attrition rate over the 24-month follow-up period, the target enrollment was approximately 74 participants per group. The final study cohort comprised 147 participants, including 73 in the pathway group and 74 in the usual-care group. The study was not powered to detect differences in refracture outcomes; therefore, refracture analyses were considered secondary and exploratory.
Statistical analysis
Statistical analyses were performed using R version 4.3.2 and SPSS version 27.0. All statistical tests were two-sided, and a P < 0.05 was considered statistically significant. Continuous variables are presented as the mean ± standard deviation or median (interquartile range), as appropriate, whereas categorical variables are presented as frequencies and percentages. Between-group comparisons were performed using Student's t-test or the Mann–Whitney U test for continuous variables and the chi-square or Fisher's exact test for categorical variables. Baseline comparability was assessed using P values and standardized mean differences.
The primary analysis followed the intention-to-treat principle, with all participants analyzed according to their original group allocation. A per-protocol analysis was also performed after excluding participants with major protocol deviations, withdrawal of consent, or no post-discharge adherence data available.
PDC was analyzed both as a continuous outcome and as a binary variable, using the predefined adherence threshold of PDC ≥ 0.80. Continuous PDC values were evaluated using linear regression, whereas binary adherence outcomes were analyzed using log-binomial regression or modified Poisson regression with robust standard errors. Multivariable models were adjusted for age, sex, fracture type, surgical procedure, Charlson Comorbidity Index, previous fragility fracture, baseline GI risk category, estimated glomerular filtration rate, baseline 25-hydroxyvitamin D concentration, baseline BMD, and calendar period.
Longitudinal BMD changes were analyzed using linear mixed-effects models with fixed effects for treatment group, time, and the group-by-time interaction, together with participant-specific random intercepts. Separate analyses were performed for the lumbar spine, total hip, and femoral neck. Time to first confirmed refracture was evaluated using Kaplan–Meier survival curves, the log-rank test, and Cox proportional hazards regression. The proportional hazards assumption was assessed using Schoenfeld residuals. Because the number of refracture events was limited, hazard ratio estimates were interpreted as exploratory. Death before refracture was evaluated using Fine–Gray competing-risk regression18.
Missing data were summarized by study group, variable, follow-up time point, and reason for missingness. Multiple imputation by chained equations was used for missing covariates and repeated non-event outcomes when the missing-at-random assumption was considered plausible19. Because follow-up completion varied across study groups, prespecified sensitivity analyses for missing-not-at-random were performed. For adherence analyses, a conservative worst-case scenario classified participants lost to follow-up in the pathway group as non-adherent and those lost to follow-up in the usual-care group as adherent at 24 months. For BMD analyses, missing pathway-group DXA values were imputed to the 10th percentile of observed changes, whereas missing usual-care values were imputed to the 90th percentile. For refracture analyses, a conservative event-assignment scenario assumed that participants lost to follow-up in the pathway group experienced a refracture at the midpoint between their last contact and 24 months, whereas participants lost to follow-up in the usual-care group were censored at their last confirmed follow-up. A tipping-point analysis was performed by varying the assumed outcomes among participants lost to follow-up until the principal between-group conclusions were no longer statistically or clinically meaningful.
Prespecified subgroup analyses evaluated the effects of age, sex, GI risk category, renal function, baseline BMD category, and previous fragility fracture. Interaction terms were assessed within the regression models, and all subgroup analyses were considered exploratory.
액세스가 제한되었습니다. 이 콘텐츠를 보려면 로그인하거나 체험판을 시작하세요.
결과
코호트 등록, 배정 및 추적 관찰 캡처
수술로 치료받은 고관절 골절 노인 총 198명을 대상으로 적격성 심사를 실시하였습니다. 선정 기준을 충족하지 않았거나(n = 29), 참여를 거부하거나 고지된 동의서를 제공하지 않았으며(n = 12), 심각한 동반 질환이 있거나 기대 생존 기간이 6개월 미만이었거나(n = 6), 또는 간병인이 없거나 유효한 연락처 정보가 없어 추적 관찰을 완료할 수 없었던(n = 4) 참여자 51명을 제외하였습니다. 최종 연구 코호트는 간호사 주도 위장관(GI) 내약성 적응 경로 그룹 73명과 통상 치료 그룹 74명을 포함하여 총 147명의 참여자로 구성되었습니다. 참여자 심사, 그룹 할당, 추적 관찰 및 분석 세트 구성 과정은 그림 1에 도식화되어 있습니다. 통상 치료 그룹 참여자들은 간호사 주도 경로 도입 전에 등록되었으며, 경로 그룹 참여자들은 도입 후에 등록되었습니다...
액세스가 제한되었습니다. 이 콘텐츠를 보려면 로그인하거나 체험판을 시작하세요.
토론
이 단일 센터, 비무작위 구현 연구는 고관절 골절의 수술적 치료를 받은 고령자를 대상으로 간호사 주도의 위장관(GI) 내약성 맞춤형 항골다공증 치료 경로를 평가하였습니다. 가장 일관된 결과는 치료 프로세스 실행과 조제 기반 복약 순응도에서 관찰되었습니다. 통상적인 치료와 비교하여, 치료 경로 그룹은 위장관 위험 층화, 퇴원 교육, 안전성 실험실 검토, 치료 시작, 추적 관찰 포착 및 24개월 동안의 처방일수 비율(PDC) 기반 순응도가 더 높았습니다. 이러한 결과는 이차 골절 예방 프로세스를 개선하는 데 있어 구조화된 골절 후 치료 모델의 역할과 일치합니다20. BMD 변화와 재골절 관련 사건 발생 시간 추정치는 방향성 면에서 긍정적이었으나, 그룹 간 DXA 완료율의 차이가 있었고 표본 크기가 적었으며 재골절 사건 수가 제한적이었으므로 해석에 주의가 필요합니다.
본 경로(pathway)는 주로 급성 수술 단계 이후, 즉 골다공증 치료가 ...
액세스가 제한되었습니다. 이 콘텐츠를 보려면 로그인하거나 체험판을 시작하세요.
공개 사항
저자들은 본 연구와 관련하여 경쟁 관계에 있는 재정적 이해관계나 이해상충이 없음을 밝힙니다.
감사의 글
저자들은 환자 스크리닝, 경로 구현 및 종단적 추적 관찰 과정에서 지원을 아끼지 않은 연구 센터의 간호 인력, 정형외과 팀 및 추적 관찰 담당자들에게 감사를 표합니다. 또한, 본 연구에 참여해 주신 모든 환자와 그 가족분들께 감사드립니다. 본 연구는 다음 기관의 지원을 받아 수행되었습니다: 청두시 롱콴이구 (지원 번호 WJKY2025020).
액세스가 제한되었습니다. 이 콘텐츠를 보려면 로그인하거나 체험판을 시작하세요.
재료
| 이름 | 회사 | 카탈로그 번호 | 댓글 |
|---|---|---|---|
| 25-hydroxyvitamin D 분석 | Beckman Coulter | Access 25(OH) Vitamin D Total Kit, B24838 | 골흡수 억제 요법 전 기저치 비타민 D 평가 및 안전성 확인. |
| 증례 보고서 양식 | 연구 기관 | 로컬 문서 세트 | 적격성, 기저 특성, 골절 세부 사항, 약물 복용 이력, 추적 관찰 상태, 이상 반응 및 결과의 표준화된 수집. |
| 화학 분석기 | Roche Diagnostics | cobas 8000 modular analyzer series, cobas c 702 module | 혈청 칼슘, 알부민, 인산염, 크레아티닌, 알칼리성 인산분해효소 및 기타 일반 화학 지표 측정. |
| 퇴원 교육 체크리스트 | 연구 기관 | 로컬 문서 세트 | 약물 교육, 투여 지침, 경고 증상, 처방 갱신 계획 및 추적 관찰 일정의 표준화된 기록. |
| DXA 분석 소프트웨어 | GE HealthCare | enCORE software platform | 관심 영역(ROI) 정의, BMD 계산 및 연속 DXA 비교. |
| DXA 골밀도 측정기 | GE HealthCare | Lunar iDXA | 기저치, 12개월 및 24개월 시점의 요추, 대퇴골 경부 및 전체 고관절 골밀도 측정. |
| 외부 처방 갱신 문서 | 외부 병원 / 지역 약국 | 해당 없음 | 외부 처방전, 지역 약국 영수증, 약물 포장 또는 간병인이 제공한 처방 갱신 기록 확인. |
| 위장관 내약성 위험 체크리스트 | 연구 기관 | 로컬 문서 세트 | 위장관 증상, 위장관 질환 이력, 삼킴 능력, 직립 자세 가능 여부, 위장관 위험 약물, 변비 및 다제복용 기록. |
| 병원 전자 의무 기록 시스템 | 연구 병원 | 로컬 기관 EMR/HIS | 입원 데이터, 수술 데이터, 검사 결과, 퇴원 처방, 외래 기록 및 입원 이벤트 추출. |
| 병원 약국 조제 시스템 | 연구 병원 | 로컬 기관 약제 정보 시스템 | PDC 계산을 위한 퇴원 처방, 외래 처방 갱신 날짜, 조제 수량 및 약물 공급 정보 추출. |
| 면역 분석기 | Beckman Coulter | Access 2 Immunoassay System | 혈청 25-hydroxyvitamin D 측정 플랫폼. |
| 약물 복약 순응도 워크시트 | 연구 기관 | 로컬 스프레드시트 템플릿 | PDC, 처방 갱신 간격, 중단 기간, 지속성 상태 및 확장 소스 민감도 분석 계산. |
| 보안 데이터 캡처 플랫폼 | REDCap Consortium / 연구 병원 | REDCap 또는 로컬 기관 EDC | 데이터 입력, 감사 추적, 역할 기반 액세스, 쿼리 해결 및 분석 데이터셋 내보내기. |
| 통계 소프트웨어 | IBM | IBM SPSS Statistics 27.0 | 기술 통계, 기저치 비교 및 품질 관리 분석에 사용. |
| 통계 소프트웨어 | R Foundation for Statistical Computing | R, version recorded in analysis log | 회귀 분석, 혼합 효과 모델, Kaplan–Meier 곡선, Cox 모델, 경쟁 위험 모델, 다중 대체 및 민감도 분석. |
| 구조화된 추적 관찰 스크립트 | 연구 기관 | 로컬 문서 세트 | 1주, 1개월, 3개월, 6개월, 12개월, 18개월 및 24개월 시점의 전화 또는 내원 추적 관찰. |
| 트리거-응답 로그 | 연구 기관 | 로컬 문서 세트 | 위장관 내약성 부족, 처방 갱신 누락, 치료 간격, 처방 재평가, 변경 결정 및 시정 조치 기록. |
참고문헌
- Haentjens P, et al. Meta-analysis: excess mortality after hip fracture among older women and men. Ann Intern Med. 2010;152:380-390.
- Banefelt J, et al. Risk of imminent fracture following a previous fracture in a Swedish database study. Osteoporos Int. 2019;30:601-609.
- Conley RB, et al. Secondary fracture prevention: consensus clinical recommendations from a multistakeholder coalition. J Bone Miner Res. 2020;35:36-52.
- Caro JJ, Ishak KJ, Huybrechts KF, Raggio G, Naujoks C. The impact of compliance with osteoporosis therapy on fracture rates in actual practice. Osteoporos Int. 2004;15:1003-1008.
- Siris ES, et al. Impact of osteoporosis treatment adherence on fracture rates in North America and Europe. Am J Med. 2009;122:S3-S13.
- Siris ES, et al. Adherence to bisphosphonate therapy and fracture rates in osteoporotic women: relationship to vertebral and nonvertebral fractures from 2 US claims databases. Mayo Clin Proc. 2006;81:1013-1022.
- Keshishian A, et al. Examining the effect of medication adherence on risk of subsequent fracture among women with a fragility fracture in the U.S. Medicare population. J Manag Care Spec Pharm. 2017;23:1178-1190.
- Reyes BJ, et al. Postacute management of older adults suffering an osteoporotic hip fracture: a consensus statement from the International Geriatric Fracture Society. Geriatr Orthop Surg Rehabil. 2020;11:2151459320935100.
- Siris ES, et al. Association between gastrointestinal events and compliance with osteoporosis therapy. Bone Rep. 2015;4:5-10.
- Kennel KA, Drake MT. Adverse effects of bisphosphonates: implications for osteoporosis management. Mayo Clin Proc. 2009;84:632-638.
- Marsh D, et al. Coordinator-based systems for secondary prevention in fragility fracture patients. Osteoporos Int. 2011;22:2051-2065.
- Le HV, et al. Fracture liaison service: a multidisciplinary approach to osteoporosis management. Osteoporos Int. 2024;35:1719-1727.
- Hiligsmann M, et al. Determinants, consequences and potential solutions to poor adherence to anti-osteoporosis treatment: results of an expert group meeting organized by the European Society for Clinical and Economic Aspects of Osteoporosis, Osteoarthritis and Musculoskeletal Diseases and the International Osteoporosis Foundation. Osteoporos Int. 2019;30:2155-2165.
- von Elm E, et al. The Strengthening the Reporting of Observational Studies in Epidemiology statement: guidelines for reporting observational studies. Lancet. 2007;370:1453-1457.
- Prieto-Merino D, et al. Estimating proportion of days covered using real-world online medicine suppliers' datasets. J Pharm Policy Pract. 2021;14:113.
- Cadarette SM, Burden AM. Measuring and improving adherence to osteoporosis pharmacotherapy. Curr Opin Rheumatol. 2010;22:397-403.
- Kendler DL, et al. Repeating measurement of bone mineral density when monitoring with dual-energy X-ray absorptiometry: 2019 ISCD official position. J Clin Densitom. 2019;22:489-500.
- Fine JP, Gray RJ. A proportional hazards model for the subdistribution of a competing risk. J Am Stat Assoc. 1999;94:496-509.
- van Buuren S, Groothuis-Oudshoorn K. mice: multivariate imputation by chained equations in R. J Stat Softw. 2011;45:1-67.
- Ganda K, et al. Models of care for the secondary prevention of osteoporotic fractures: a systematic review and meta-analysis. Osteoporos Int. 2013;24:393-406.
- Lems WF, et al. EULAR/EFORT recommendations for management of patients older than 50 years with a fragility fracture and prevention of subsequent fractures. Ann Rheum Dis. 2017;76:802-810.
- Lam WY, Fresco P. Medication adherence measures: an overview. Biomed Res Int. 2015;2015:217047.
- Lyles KW, et al. Zoledronic acid and clinical fractures and mortality after hip fracture. N Engl J Med. 2007;357:1799-1809.
- Bliuc D, et al. Mortality risk associated with low-trauma osteoporotic fracture and subsequent fracture in men and women. JAMA. 2009;301:513-521.
- Hemming K, et al. The stepped wedge cluster randomised trial: rationale, design, analysis, and reporting. BMJ. 2015;350:h391.
액세스가 제한되었습니다. 이 콘텐츠를 보려면 로그인하거나 체험판을 시작하세요.