본 무작위 대조 연구는 표준 간호 케어에 국소 Huzhang Sanhuang 처방을 추가하는 것이 항암 화학요법으로 유발된 정맥염 환자의 증상 완화, 염증 및 안전성 결과에 개선 효과가 있는지 평가합니다.
방법 논문
항암화학요법으로 유발된 정맥염에 대한 표준 간호와 병행한 국소 호장산황(Huzhang Sanhuang) 적용의 효과: 무작위 대조 연구
52 조회수
⸱
2026년 9월 11일
이 논문에서
요약
초록
항암화학요법 유발 정맥염(CIP)은 말초 정맥 항암화학요법의 흔한 합병증으로, 통증, 국소 염증, 치료 중단 및 삶의 질 저하를 유발할 수 있습니다. 본 무작위 대조 시험에서는 표준 간호와 병행한 국소 Huzhang Sanhuang(HZSH) 처방의 CIP 관리 효능과 안전성을 평가하였습니다. CIP(1등급 이상)를 가진 입원 환자 94명을 1:1 비율로 무작위 배정하여 14일 동안 국소 HZSH 처방과 표준 간호를 병행한 군(실험군, n = 47) 또는 50% 황산마그네슘 습포와 표준 간호를 병행한 군(대조군, n = 47)으로 나누었습니다. 사전 설정된 결과 지표에는 정맥염 등급, 시각적 아날로그 척도(VAS) 통증 점수, 고감도 C-반응성 단백질(hs-CRP), 인터루킨-6(IL-6), 증상 소실 시간 및 안전성 지표가 포함되었습니다. 14일째에 실험군 환자들은 대조군보다 정맥염 중증도에서 유의하게 더 큰 개선을 보였습니다(2등급 이상의 위험비, 0.42; 95% 신뢰구간, 0.20–0.87; P = 0.012). 또한 실험군은 VAS 통증 점수, hs-CRP 수치 및 IL-6 농도에서 유의하게 더 큰 감소를 나타냈습니다(모두 P < 0.01). Kaplan–Meier 분석 결과, 실험군에서 다수의 국소 증상이 더 빠르게 소실됨을 확인하였습니다. 치료 순응도는 두 그룹 모두 높았으며, 심각한 이상 반응이나 주요 안전성 문제는 관찰되지 않았습니다. 이러한 결과는 표준 간호와 병행한 국소 HZSH 처방이 임상적 회복을 가속화하고 국소 증상을 완화하며 항암화학요법 유발 정맥염 환자의 염증 부담을 줄여주는 안전하고 효과적인 통합 간호 중재임을 시사합니다.
서론
화학요법 유발 정맥염(CIP)은 말초 정맥 화학요법을 받는 악성 종양 환자에게서 가장 흔하게 발생하는 합병증 중 하나입니다1. 종양학적 치료에서 중심정맥관과 매립형 포트의 사용이 증가하고 있으나, 비용적 제약, 시술상의 편의성 및 환자 개별적인 혈관 상태로 인해 단기 화학요법 및 일차 의료 환경에서는 여전히 말초 정맥 확보가 흔히 이루어집니다. 이러한 환경에서 vincristine, oxaliplatin, docetaxel과 같은 세포독성 제제는 높은 삼투압, pH 불균형 및 직접적인 혈관 독성으로 인해 상당한 내피 세포 손상을 일으킬 수 있으며, 이로 인해 국소 염증 반응이 유발될 수 있습니다2,3. 임상적으로 CIP는 통증, 홍반, 부종 및 경결로 나타날 수 있으며, 심한 경우 국소 조직 괴사로 진행될 수 있습니다. 이러한 합병증은 치료 일정을 중단시키고 항종양 치료를 지연시키며, 반복적인 천자와 혈관 손상으로 인한 환자의 고통을 증가시켜 궁극적으로 삶의 질을 저하시킬 수 있습니다4.
현재 CIP의 간호 관리는 주로 정맥 주입 요법 표준과 사지 거상, 국소 냉압법 또는 온압법, 말초 유치 바늘의 표준화된 관리 등 일상적인 지지 요법을 따릅니다5. 일반적인 국소 중재로는 황산마그네슘 습포, 무코폴리사카라이드 폴리설페이트 연고 및 하이드로콜로이드 드레싱이 포함됩니다6,7. 그러나 이러한 접근 방식에는 실질적인 한계가 있습니다. 황산마그네슘 드레싱은 삼투 효과를 통해 부종을 감소시킬 수 있으나, 빈번한 교체가 필요하며 피부 건조증이나 가려움증을 유발할 수 있습니다. 기존의 국소 제제는 어느 정도 국소 혈액 순환을 개선할 수 있지만, 심한 작열감, 지속적인 경결 또는 더 심각한 염증 반응이 있는 환자에게는 그 효과가 제한적인 경우가 많습니다. 또한 이용 가능한 증거에 따르면, 단일 양식의 간호 조치나 국소 화학 제제만으로는 혈관 내피 회복을 충분히 지원하고 혈전 위험을 포함한 하류 혈관 합병증을 줄이기에 부족할 수 있음을 시사합니다8,9. 따라서 염증을 줄이고 통증을 완화하며 국소 혈관 복구를 지원하기 위한 실용적이고 임상적으로 적용 가능한 통합 간호 전략이 필요합니다10.
전통 중의학(TCM)에서 화학요법 관련 혈관 손상은 열독의 축적과 혈액 정체를 수반하는 상태로 흔히 이해되며, 국소 혈관 손상과 혈액 순환 장애가 주요 병리학적 특징으로 꼽힙니다11,12. 호장삼황(Huzhang Sanhuang) 처방은 Polygonum cuspidatum, Rheum palmatum, Phellodendron amurense, Scutellaria baicalensis와 같은 약재를 포함하며, 전통적으로 청열, 해독, 활혈, 거어, 소종 및 통증 완화에 사용되어 왔습니다. 현대 약리학적 연구들은 이러한 효과에 대한 타당한 생물학적 근거를 제공합니다. Polygonum cuspidatum의 활성 성분(레스베라트롤 관련 화합물 포함)은 염증 신호를 억제하고 산화 스트레스 관련 내피 세포 손상을 줄이는 것으로 보고되었으며, Rheum palmatum은 국소 미세순환과 조직 수복을 지원할 수 있습니다13. 또한, Phellodendron amurense 및 Scutellaria baicalensis에서 유래한 베르베린(berberine) 및 바이칼린(baicalin)과 같은 화합물은 항염증 및 항균 효과가 있는 것으로 기록되어 있습니다. 이 한약 복합 제형을 국소적으로 사용할 경우, 특정 경구용 또는 주사제와 관련된 전신적 부작용을 피하면서 병변 부위에 국소적인 항염증 미세환경을 조성하는 데 도움이 될 수 있습니다14.
이러한 배경에서, 본 무작위 대조 연구는 입원한 CIP 환자를 대상으로 표준 간호 및 국소 호장삼황(Huzhang Sanhuang) 처방 병용 요법의 임상적 유효성과 안전성을 평가하기 위해 설계되었습니다15. 환자들은 표준 간호와 일상적인 국소 치료를 받는 대조군 또는 동일한 표준 간호와 더불어 호장삼황 국소 처방을 받는 실험군으로 무작위 배정되었습니다. 주요 기대 효과는 병용 중재를 통해 정맥염의 중증도를 낮추고 통증, 발적 및 부종의 해소를 가속화하는 것이었습니다. 본 연구는 대조군 설계와 사전 정의된 결과 측정 지표를 사용하여 CIP에 대한 통합적 간호 접근법에 대한 보다 강력한 근거를 제공하고, 현대 종양 지원 간호 실무에서 중의학(TCM) 기반 국소 케어의 표준화된 적용을 뒷받침하는 것을 목표로 합니다.
프로토콜
Approval was obtained from the Ethics Committee of the Second Affiliated Hospital of Nanjing University of Chinese Medicine (Jiangsu Provincial Second Traditional Chinese Medicine Hospital) before initiating participant recruitment (Approval no. 2025SEZKY-033-02). All study procedures were conducted in accordance with the Declaration of Helsinki. The study purpose, procedures, potential benefits, and possible risks were explained to each eligible participant, and written informed consent was obtained before enrollment.
1. Protect participant confidentiality
- Assign study identification codes
- Assign a unique study identification code to each participant immediately after enrollment. Use the assigned code throughout the study.
- Enter the study identification code on all case report forms, intervention records, laboratory records, and study databases. Do not record participant names in the analysis dataset.
- Secure personally identifiable information
- Store participant names, contact information, hospital identification numbers, and consent forms separately from coded research data. Link identifiable information to the study identification code only through a secure participant-code list.
- Limit access to personally identifiable information to authorized research personnel. Store paper records in locked cabinets and protect electronic records with passwords and access controls.
- Do not disclose participant-identifying information in study reports, statistical outputs, presentations, or publications. Use coded or aggregated data when reporting study findings.
- Document study events prospectively
- Document each protocol deviation when it occurs. Record the date, nature, reason, corrective action, and effect on study participation.
- Document each participant's withdrawal prospectively in the case report form and study log. Record the withdrawal date and reason without altering previously collected data.
- Record all adverse events in the case report forms and nursing records. Document the onset, severity, duration, management, outcome, and assessed relationship to the study intervention.
2. Study design and participant enrollment
- Study design
- Conduct a prospective, randomized, controlled, single-center clinical trial at the Second Affiliated Hospital of Nanjing University of Chinese Medicine from January 2025 to December 2025. Compare topical Huzhang Sanhuang formula plus standard nursing care with 50% magnesium sulfate wet dressing plus the same standard nursing care.
- Initiate the assigned intervention immediately after confirming chemotherapy-induced phlebitis (CIP) and completing baseline assessment. Continue treatment for 14 consecutive days and perform outcome assessments on Day 0, Day 7, and Day 14.
- Identify hospitalized patients who develop CIP after peripheral intravenous chemotherapy during routine chemotherapy infusion rounds and intravenous therapy rounds. Evaluate each patient for study eligibility.
- Explain the study objectives, procedures, risks, and benefits to each eligible participant. Obtain written informed consent before enrollment.
- Collect demographic information, tumor treatment status, phlebitis grade, visual analog scale (VAS) pain score, and inflammatory biomarker measurements before randomization.
- Participant screening
- Calculate the sample size using the primary endpoint, defined as the proportion of participants with persistent grade II or higher phlebitis at Day 14. Assume an event rate of 45% in the control group and 15% in the experimental group with a two-sided α of 0.05 and 80% statistical power.
- Require at least 36 participants per treatment group based on the sample size calculation. Increase the target sample size by approximately 20% to compensate for anticipated withdrawals or protocol deviations and enroll 94 participants (47 per group).
- Include adults aged 18 years or older who develop grade I or higher phlebitis at the peripheral intravenous catheter insertion site during chemotherapy. Confirm that each participant is conscious, capable of reporting symptoms, and able to complete scheduled follow-up assessments.
- Obtain written informed consent from each eligible participant before enrollment. Assign each participant a unique study identification number.
- Exclude patients with a known allergy to either topical preparation, severe contact dermatitis, skin ulceration or infection at the treatment site, severe eczema, or extensive local skin damage. Exclude patients with severe systemic infection, unstable organ failure, cognitive impairment, communication difficulties, or concurrent topical treatments that could influence study outcomes.
- Withdraw participants who revoke consent, miss more than 20% of scheduled topical applications, or receive prohibited topical medications during the study. Withdraw participants who develop severe local skin reactions requiring discontinuation or who cannot complete follow-up because of transfer or hospital discharge.
- Record the reason, date, and timing of each withdrawal in the study records. Document all protocol deviations and adverse events before study completion.
3. Randomization, allocation concealment, and blinding
- Randomization and allocation concealment
- Ask an independent researcher who is not involved in participant recruitment, intervention delivery, or outcome assessment to generate a computer-based random allocation sequence before participant enrollment. Allocate participants to the experimental or control group in a 1:1 ratio.
- Place each treatment assignment in a sequentially numbered, opaque, sealed envelope. Seal each envelope securely before participant enrollment begins.
- Ask trained research nurses to screen potential participants according to the eligibility criteria. Confirm eligibility and obtain written informed consent before enrollment.
- Collect all baseline demographic and clinical data before revealing the treatment allocation. Verify that all required baseline assessments have been completed.
- Ask the study coordinator to open the next sequentially numbered envelope only after participant enrollment and completion of the baseline assessment. Record the envelope number and treatment assignment in the study records.
- Communicate the assigned treatment to the intervention nurse immediately after opening the allocation envelope. Begin the assigned intervention according to the study schedule.
- Record the allocation date, envelope sequence number, assigned treatment group, and responsible study personnel in the study documentation.
- Blinding and bias control
- Assign different study personnel to deliver the topical interventions and perform outcome assessments. Prevent outcome assessors from participating in treatment administration.
- Use identical assessment forms and standardized evaluation procedures for all scheduled study visits. Apply the same assessment criteria to both treatment groups.
- Keep outcome assessors unaware of participant treatment allocation whenever feasible. Avoid discussing treatment assignments during outcome assessments.
- Replace treatment groups with coded identifiers before statistical analysis. Keep the treatment code concealed until completion of the primary statistical analyses.
- Perform all efficacy and safety assessments according to the predefined protocol. Record all observations immediately after each assessment without reference to previous results.
NOTE: Do not blind participants because the Huzhang Sanhuang formula and 50% magnesium sulfate dressing differ in appearance, texture, and odor. Limit blinding to outcome assessment and statistical analysis whenever feasible.
4. Topical intervention procedures
- Overall intervention framework
- Provide all participants with the same standard nursing care throughout the study. Vary only the assigned topical treatment between the two groups.
- Begin the assigned topical treatment immediately after confirming grade I or higher chemotherapy-induced phlebitis and completing the baseline assessment. Continue treatment for 14 consecutive days.
- Administer the assigned topical treatment twice daily, once in the morning and once in the evening, at approximately fixed times each day. Where clinically feasible, maintain an interval of approximately 12 h between the two applications. Perform outcome assessments on Day 0, Day 7, and Day 14 before the morning application.
- Standardize treatment delivery across participants by using the same predefined procedures for skin preparation, treatment coverage, dressing retention, documentation, and safety monitoring. Maintain an application thickness of approximately 2 mm for the Huzhang Sanhuang paste, extend both topical treatments approximately 1 cm beyond the visible lesion margin, and leave each dressing in place for 4 h. Record the actual application and removal times after each treatment.
- Prepare the Huzhang Sanhuang formula
- Obtain 100 g each of Polygonum cuspidatum (Huzhang), Rheum palmatum (Dahuang), Phellodendron amurense (Huangbai), and Scutellaria baicalensis (Huangqin). Verify each herb according to the Chinese Pharmacopeia before preparation.
- Record the supplier, batch number, authentication result, and quality certificate for each herbal ingredient before use.
- Add 4,000 mL of purified water to the herbal mixture at a crude herb-to-water ratio of 1:10 (w/v). Soak the mixture for 30 min before extraction.
- Heat the soaked herbal mixture to gentle boiling (approximately 95–100 °C). Continue decoction for 30 min.
- Filter the decoction through an appropriate filter. Concentrate the filtrate at 70–80 °C until a homogeneous, semisolid paste suitable for topical application is obtained.
- Inspect the paste for uniform appearance and absence of visible contamination or phase separation. Confirm that the paste has a consistent semisolid consistency suitable for topical application.
- Transfer the paste into sterile sealed containers. Store the preparation at 2–8 °C and prepare a fresh batch every 48 h.
- Apply approximately 0.20 g/cm2 of herbal paste to achieve a layer approximately 2 mm thick. Extend the application approximately 1 cm beyond the visible lesion margin.
- Administer the Huzhang Sanhuang formula (Experimental group)
- Inspect the affected skin before each application. Assess erythema, swelling, pain, papules, blistering, exudation, and pruritus.
- Clean the treatment site gently with sterile normal saline. Dry the skin using sterile gauze before applying the herbal paste.
- Spread the Huzhang Sanhuang paste evenly over the inflamed area to a thickness of approximately 2 mm. Extend the application approximately 1 cm beyond the visible lesion margin.
NOTE: Do not apply pressure directly over the inflamed vein during application. Ensure complete coverage of the affected area. - Cover the treated area with sterile gauze. Secure the dressing using hypoallergenic tape without applying compression.
- Leave the topical preparation in place for 4 h. Remove the dressing at the end of the treatment period.
- Remove any remaining herbal paste with sterile normal saline. Dry the skin gently using sterile gauze.
- Repeat the application twice daily for 14 consecutive days. Administer treatments at approximately the same time each day.
- Record the application time, treatment completion, skin tolerance, and protocol deviations after each application. Report any clinically significant local reactions immediately.
- Administer the control treatment
- Inspect, clean, and dry the affected area using the same procedure applied to the experimental group.
- Soak sterile gauze thoroughly with 50% magnesium sulfate solution. Remove excess solution before application.
- Place the soaked gauze over the inflamed area. Extend the dressing approximately 1 cm beyond the lesion margin.
- Cover the wet dressing with dry sterile gauze. Secure the dressing using hypoallergenic tape without compression.
- Leave the dressing in place for 4 h. Remove the dressing at the end of the scheduled treatment period.
- Clean the skin gently with sterile normal saline after dressing removal. Dry the area with sterile gauze.
- Repeat the treatment twice daily for 14 consecutive days. Maintain the same treatment schedule used in the experimental group.
- Record treatment completion, dressing tolerance, local skin reactions, and protocol deviations after each application. Use identical documentation procedures for both treatment groups.
5. Standard nursing care
- Train the nursing staff
- Train all participating nurses before enrolling the first participant using the same written protocol and standardized demonstration. Review the phlebitis grading criteria, skin preparation, treatment coverage, dressing application and removal, 4-h retention requirement, safety monitoring, adverse-event reporting, and documentation procedures.
- Require each participating nurse to perform the study-related procedures under supervision before independently administering study treatment. Confirm procedural competency using the same predefined treatment checklist and correct any deviations before independent participant care is permitted.
- Provide standard nursing care
- Inspect the peripheral intravenous catheter insertion site during each nursing shift. Assess pain, erythema, swelling, induration, burning sensation, and catheter patency using the standardized phlebitis grading criteria16.
- Monitor participants for worsening phlebitis, suspected extravasation, local infection, or other infusion-related complications. Report clinically significant deterioration promptly to the responsible investigator or treating physician.
- Instruct participants to protect the affected limb and avoid pressure, scratching, or unnecessary manipulation of the inflamed area. Advise participants to report worsening pain, swelling, redness, blistering, exudation, or other new symptoms immediately.
- Record phlebitis grade, nursing interventions, participant tolerance, and clinically significant findings during each scheduled assessment. Apply identical nursing procedures to both treatment groups throughout the study.
6. Outcome assessment and measurements
- Assess all study outcomes at baseline (Day 0), Day 7, and Day 14. Complete each assessment before the morning topical application using standardized assessment forms.
- Assess phlebitis severity
- Evaluate phlebitis severity using the predefined Grade 0–IV classification. Assess pain, erythema, swelling, burning sensation, induration, and exudation before assigning the phlebitis grade17.
- Determine whether participants have persistent Grade II or higher phlebitis on Day 14. Record phlebitis grades at each scheduled assessment.
- Ask participants to rate pain using a 10-cm visual analog scale (VAS), where 0 indicates no pain, and 10 indicates the worst imaginable pain. Record the VAS score at each scheduled assessment.
- Measure inflammatory biomarkers
- Collect fasting venous blood samples between 06:00 and 08:00 at baseline (Day 0) and Day 14 using the same sampling procedure at both time points. Label each specimen with the participant study identification code, collection time, and transport the samples promptly to the central laboratory.
- Allow the collected blood samples to clot at room temperature for approximately 30 min. Process all specimens within 2 h of collection. Centrifuge the samples at 1,500 × g for 10 min at 4 °C using a refrigerated benchtop centrifuge.
- Separate the serum immediately after centrifugation and inspect each specimen for hemolysis, lipemia, or other visible abnormalities that could interfere with analysis. Analyze the separated serum on the day of collection; do not subject samples to long-term frozen storage or repeated freeze–thaw cycles.
- Measure interleukin-6 (IL-6) using an electrochemiluminescence immunoassay according to the manufacturer's instructions. Perform a high-sensitivity C-reactive protein (hs-CRP) measurement using the validated assay routinely employed by the central laboratory.
- Use the same sampling, processing, and analytical procedures for baseline and Day 14 specimens. Perform instrument calibration and internal quality control in accordance with the manufacturer's instructions and the central laboratory's standard operating procedures. Record biomarker results only after the corresponding analytical run satisfies the predefined laboratory quality-control criteria.
- Calculate the number of days from treatment initiation until pain decreases to a VAS score of ≤1 and redness and swelling remain absent or mild without progression for at least 24 h. Record the time to symptom resolution for each participant.
- Evaluate Traditional Chinese Medicine (TCM) syndrome scores at each scheduled assessment using the predefined scoring criteria. Calculate the total score for each participant.
- Calculate the efficacy index according to changes in the total TCM syndrome score. Classify treatment responses using the predefined efficacy categories and calculate the total effective rate.
- Standardize outcome assessment
- Train both outcome evaluators before participant enrollment using the predefined Grade 0-IV phlebitis criteria and TCM syndrome scoring criteria. Review the definitions of pain, erythema, swelling, burning sensation, induration, and exudation to establish a consistent interpretation of each grading category.
- Ask the two trained evaluators to independently assess phlebitis grade and TCM syndrome score using identical standardized assessment forms. Whenever feasible, maintain the same evaluator pair across scheduled assessments. Keep the evaluators unaware of treatment allocation whenever possible.
- Resolve discrepant assessments by discussion and consensus. If consensus cannot be reached, request adjudication by a senior investigator who is not involved in treatment administration. Record the final adjudicated score in the case report form.
7. Data collection and quality control
- Collect study data
- Collect baseline demographic and clinical information immediately after enrollment and before randomization. Record participant characteristics, tumor treatment status, phlebitis grade, VAS pain score, inflammatory biomarker levels, TCM syndrome score, and other relevant clinical variables using standardized case report forms.
- Complete follow-up assessments on Day 7 and Day 14 according to the study schedule. Record treatment completion, outcome measures, nursing observations, adverse events, and protocol deviations at each assessment.
- Manage study data
- Enter all study data into the electronic database using independent double-data entry. Compare the two datasets and resolve discrepancies by reviewing the original source documents.
- Review completed case report forms for completeness and consistency before database entry. Correct identified errors promptly and document all modifications according to the study data-management procedures.
- Maintain data quality
- Review study records regularly to identify missing, inconsistent, or implausible data. Verify questionable entries against the original case report forms and nursing records.
- Resolve all outstanding data queries before the database lock. Finalize the verified dataset before initiating the statistical analysis.
8. Safety monitoring
- Monitor treatment safety
- Inspect the treatment area before each topical application and at each scheduled assessment. Evaluate erythema, swelling, blistering, dermatitis, exudation, pruritus, pain, and other local skin reactions.
- Document the onset, severity, duration, management, outcome, and relationship of each adverse event to the study intervention. Record all findings in the case report form.
- Manage adverse events
- Classify adverse events as mild, moderate, or severe according to the predefined study criteria. Refer clinically significant events to an independent investigator for review.
- Stop the assigned topical treatment if severe irritation, suspected infection, allergic reaction, or other clinically significant intolerance develops. Provide appropriate medical management and document the reason for treatment discontinuation.
- Reassess the treatment site after completion of the 14-day intervention. Document any persistent or delayed adverse reactions before study completion.
9. Statistical analysis
- Prepare the study dataset
- Perform the primary efficacy analysis according to the intention-to-treat principle. Perform supportive analyses using the per-protocol population and evaluate safety in all participants who receive at least one topical treatment.
- Present continuous variables as mean ± standard deviation or median (interquartile range), as appropriate. Present categorical variables as frequencies and percentages.
- Compare continuous variables using the independent-samples t-test or Mann–Whitney U test, as appropriate. Compare categorical variables using the chi-square test or Fisher's exact test.
- Compare the proportion of participants with persistent grade II or higher phlebitis on Day 14 between treatment groups. Report effect estimates with 95% confidence intervals and corresponding P values.
- Compare VAS pain scores, hs-CRP concentrations, IL-6 concentrations, TCM syndrome scores, and clinical efficacy between groups using appropriate parametric or nonparametric statistical tests. Analyze time-to-symptom resolution using Kaplan–Meier survival analysis with the log-rank test.
- Perform additional analyses
- Adjust for clinically relevant baseline variables when appropriate using multivariable regression models18. Include prespecified variables such as baseline phlebitis grade, puncture site, and chemotherapy-drug irritability when applicable19. Report adjusted effect estimates with 95% confidence intervals.
- Compare the results of the intention-to-treat and per-protocol analyses to evaluate the robustness of the study findings.
- Handle missing data and statistical significance
- Handle missing outcome data using the predefined statistical analysis plan. Perform sensitivity analyses when missing data are present.
- Perform all statistical analyses using SPSS Statistics version 26.0. Use two-sided statistical tests and consider P < 0.05 statistically significant.
결과
A total of 94 participants were randomized equally to the experimental and control groups (47 participants per group). Participant screening, randomization, follow-up, and analysis are summarized in Figure 1. The standardized intervention workflow, including topical treatment, standard nursing care, scheduled assessments, and safety monitoring, is illustrated in Figure 2. Baseline phlebitis grade, visual analog scale (VAS) pain score, high-sensitivity C-reactive protein (hs-CRP), interleukin-6 (IL-6), and Traditional Chinese Medicine (TCM) syndrome score were comparable between groups (all P > 0.05; Table 1).
Phlebitis severity improved progressively in both groups; however, participants receiving the Huzhang Sanhuang formula demonstrated greater improvement, with a larger proportion achieving grade 0–I during follow-up (Figure 3; Table 2). At Day 7, persistent grade ≥II phlebitis was observed in 25.5% of the experimental group and 44.7% of the control group (RR, 0.57; 95% CI, 0.32–1.02; P = 0.052). By Day 14, the incidence decreased to 17.0% and 40.4%, respectively (RR, 0.42; 95% CI, 0.20–0.87; P = 0.012; Table 2). Complete phlebitis grade distributions at Day 7 and Day 14 are presented in Table 2, demonstrating that persistent grade ≥II phlebitis, indicative of a suboptimal treatment response, occurred less frequently in the experimental group.
Pain intensity decreased throughout the intervention in both groups, with significantly greater improvement in the experimental group (Figure 4). Mean VAS scores were significantly lower in the experimental group than in the control group at both Day 7 (2.8 ± 0.9 vs. 3.6 ± 1.0; P < 0.001) and Day 14 (1.4 ± 0.7 vs. 2.2 ± 0.8; P < 0.001; Table 3).
Inflammatory biomarkers also declined more markedly following treatment with the Huzhang Sanhuang formula (Figure 5). At Day 14, mean hs-CRP concentrations were 8.7 ± 3.1 mg/L in the experimental group and 11.7 ± 3.4 mg/L in the control group (P < 0.001). Mean IL-6 concentrations were 4.9 ± 1.8 pg/mL and 6.1 ± 2.0 pg/mL, respectively (P = 0.003; Table 3).
Kaplan–Meier analyses demonstrated faster resolution of erythema, swelling, burning sensation, cord-like induration, pain, and the composite symptom endpoint in the experimental group (Figure 6; Table 4). Median remission times were shorter for erythema (4.8 vs. 6.7 days), swelling (5.8 vs. 8.1 days), burning sensation (3.6 vs. 5.4 days), cord-like induration (7.2 vs. 10.1 days), and pain (3.8 vs. 6.1 days). Hazard ratios consistently favored the experimental intervention (HR, 1.48–1.71; all P < 0.05). Integrated treatment effects across phlebitis severity, pain, inflammatory biomarkers, and symptom resolution are summarized in Table 3.
Both groups exhibited reductions in TCM syndrome scores by Day 14, with greater improvements in erythema, swelling, burning sensation, pain or tenderness, cord-like induration, and total syndrome score in the experimental group (Table 5A). The experimental group also demonstrated a higher proportion of cured and markedly effective cases, resulting in a numerically higher overall effective rate than the control group (95.7% vs. 85.1%; RR, 1.12; 95% CI, 0.98–1.29; P = 0.080) (Table 5B). These findings were consistent with the improvements in the integrated efficacy outcomes summarized in Table 3.
Safety and implementation outcomes are presented in Table 6 and Figure 7. No serious treatment-related adverse events were observed. Local adverse events were infrequent and comparable between groups (10.6% vs. 12.8%; P = 1.000). Reported events were predominantly mild and reversible, including pruritus, rash or erythema, burning or stinging sensations, and occasional contact dermatitis or blistering.
Treatment adherence remained high in both groups, reaching 95.6% ± 4.8% in the experimental group and 92.4% ± 5.9% in the control group (P = 0.005; Table 6; Figure 7). High adherence (≥90%) was achieved by 89.4% of participants in the experimental group and 78.7% in the control group (P = 0.260). These findings indicate that the intervention was implemented consistently, with excellent treatment adherence and no evidence of clinically significant local intolerance.
Multivariable analysis demonstrated that assignment to the experimental group remained independently associated with greater odds of improvement in phlebitis after adjustment for prespecified covariates (adjusted OR, 2.64; 95% CI, 1.21–5.74; P = 0.015; Table 7). Sensitivity analysis produced similar findings (adjusted OR, 2.31; 95% CI, 1.08–4.96; P = 0.032), supporting the robustness of the treatment effect. Baseline phlebitis grade ≥II was independently associated with a lower probability of improvement, whereas age, sex, body mass index, diabetes, smoking status, baseline VAS score, chemotherapy irritability, catheter gauge, infusion duration, and previous phlebitis history were not significantly associated with treatment response (Table 7).
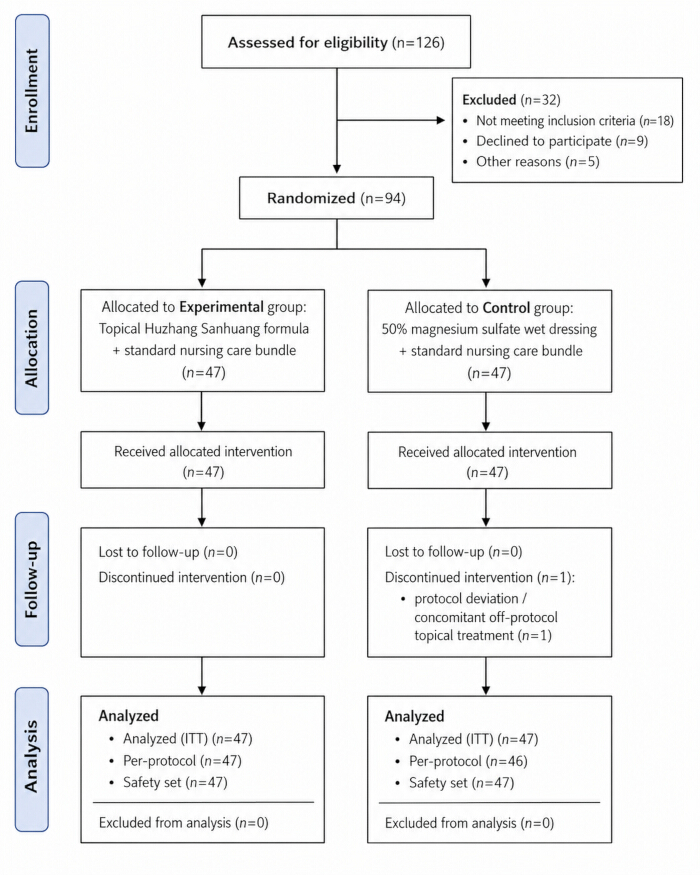
Figure 1: CONSORT flow diagram of participant enrollment, randomization, follow-up, and analysis sets. Flowchart showing screening, eligibility assessment, randomization (1:1), group allocation, follow-up, and analysis populations in the study. The diagram identifies participant counts in the experimental group (topical Huzhang Sanhuang formula plus standard nursing care) and the control group (50% magnesium sulfate wet dressing plus standard nursing care), and specifies the intention-to-treat (ITT), per-protocol, and safety analysis populations. Please click here to view a larger version of this figure.
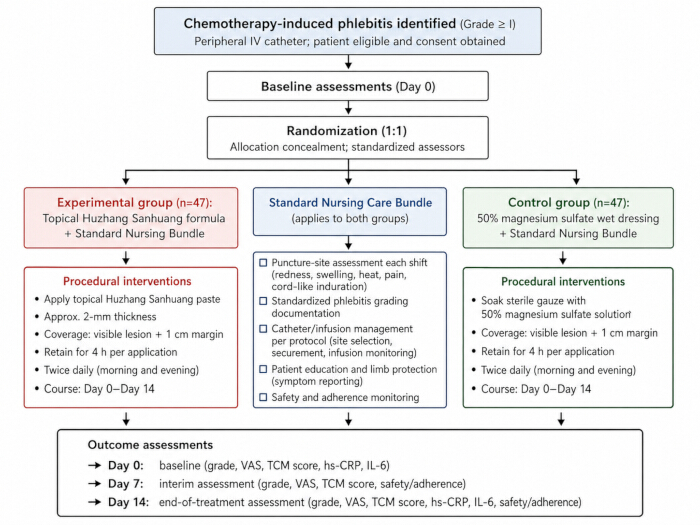
Figure 2: Standardized intervention workflow for topical Huzhang Sanhuang formula application within the nursing care bundle. Procedural schematic of the intervention pathway, including baseline assessment, group allocation, topical treatment, standardized nursing care, scheduled assessments, and safety/adherence monitoring. The experimental group received topical Huzhang Sanhuang formula, and the control group received 50% magnesium sulfate wet dressing, both extending 1 cm beyond the lesion margin, retained for 4 h per application, and administered twice daily for 14 days. Assessments were performed on Day 0, Day 7, and Day 14. Please click here to view a larger version of this figure.
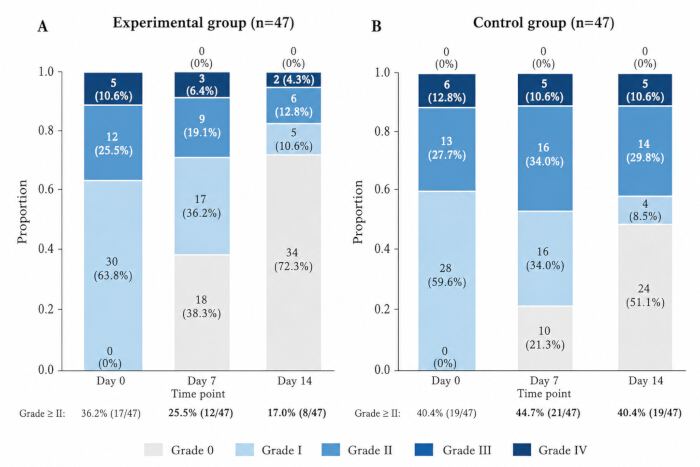
Figure 3: Distribution of phlebitis grades (0–IV) at baseline, Day 7, and Day 14 in the experimental and control groups. (A) Experimental group. Distribution of phlebitis grades (0–IV) at baseline, Day 7, and Day 14. (B) Control group. Distribution of phlebitis grades (0–IV) at baseline, Day 7, and Day 14. Please click here to view a larger version of this figure.
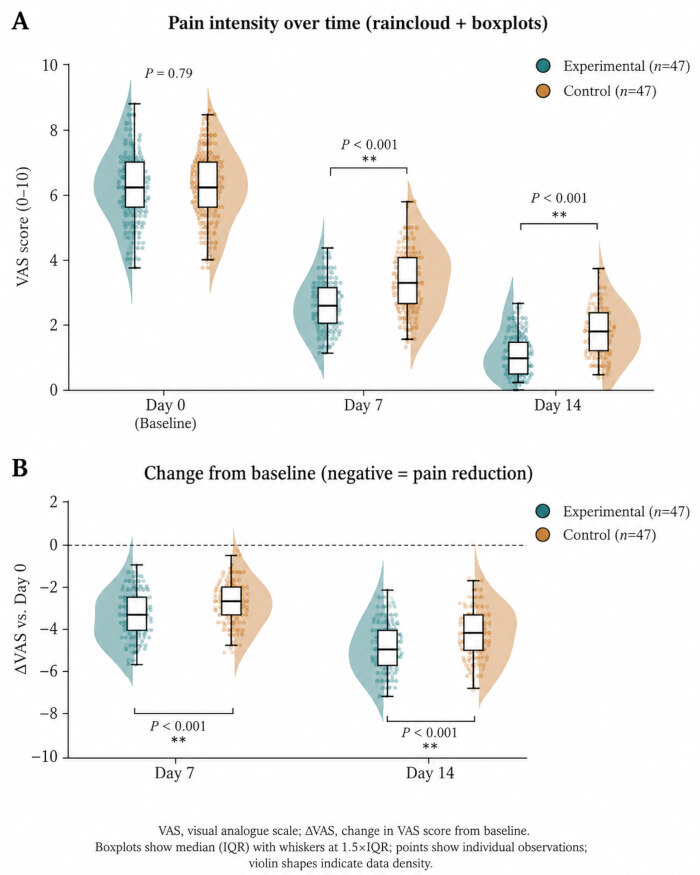
Figure 4: Time-course trajectories of pain intensity (VAS) during treatment (Day 0, Day 7, and Day 14) by group. Longitudinal visualization of pain scores measured by the Visual Analog Scale (VAS, 0–10). The figure shows within-group pain reduction over time and between-group separation in pain trajectories, with the experimental group demonstrating earlier and larger pain relief. Please click here to view a larger version of this figure.
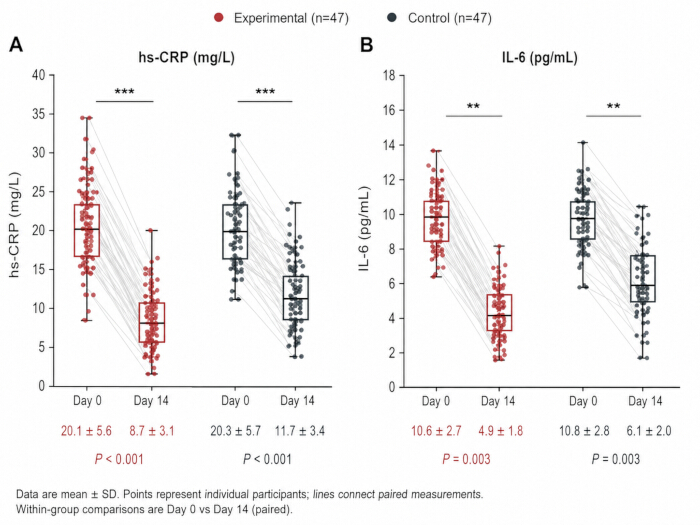
Figure 5: Pre-post changes in inflammatory biomarkers (hs-CRP and IL-6) in the experimental and control groups (Day 0 vs. Day 14). Paired or grouped visualization of hs-CRP and IL-6 levels at baseline and end of treatment. The figure shows biomarker reduction in both groups, with a greater decrease in the experimental group, supporting the intervention's anti-inflammatory effect. Please click here to view a larger version of this figure.
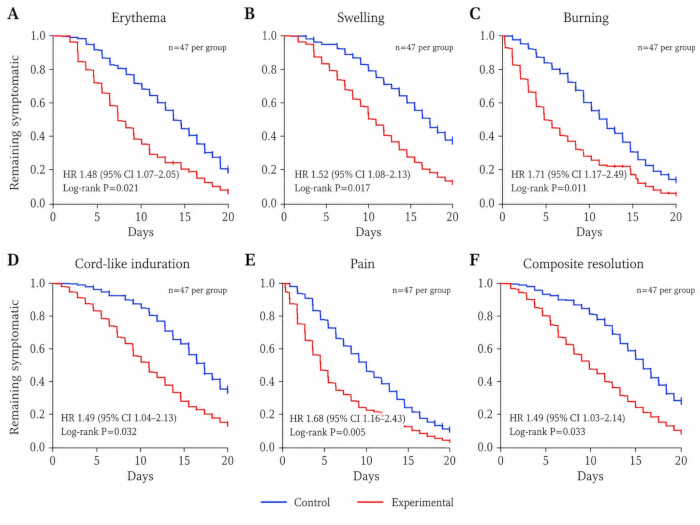
Figure 6: Kaplan–Meier curves for time to symptom resolution by group. Kaplan–Meier plots showing time to resolution of erythema, swelling, burning sensation, cord-like induration, pain, and the composite symptom endpoint in the experimental and control groups. Curves are compared using the log-rank test, and earlier separation between curves indicates faster symptom remission in the experimental group. Please click here to view a larger version of this figure.
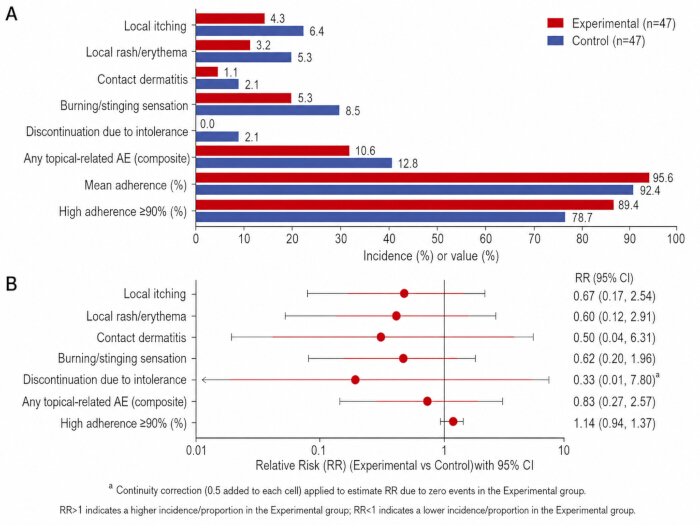
Figure 7: Safety profile, tolerability, and adherence outcomes for topical therapy in both groups. Summary visualization of safety and process outcomes. (A) Mean adherence to the prescribed topical applications, presented descriptively. (B) Safety and categorical adherence outcomes, including the incidence of local topical treatment-related adverse events, discontinuation due to intolerance, and the proportion of participants achieving high adherence (≥90%), were summarized as relative risks (RRs) with 95% confidence intervals (CIs). Please click here to view a larger version of this figure.
Table 1: Baseline demographic and clinical characteristics of participants in the experimental and control groups. Continuous variables are presented as mean ± standard deviation (SD), and categorical variables are presented as number (%). Between-group comparisons were performed using the independent-samples t test for continuous variables and the chi-square test or Fisher's exact test for categorical variables, as appropriate. P values are two-sided. Please click here to download this Table.
Table 2: Changes in phlebitis severity over time and prespecified between-group comparisons. (A) Distribution of phlebitis grades (0–IV) at baseline (Day 0), Day 7, and Day 14 in the experimental and control groups, including the proportion of participants with moderate-to-severe phlebitis (Grade ≥II). (B) Between-group comparisons of overall phlebitis grade distributions using the Mann–Whitney U test and comparisons of Grade ≥II incidence using relative risks (RRs) with 95% confidence intervals (CIs). Please click here to download this Table.
Table 3: Integrated summary of primary and secondary efficacy outcomes at baseline, Day 7, and Day 14. Outcomes include phlebitis severity, pain intensity, inflammatory biomarkers, time to symptom resolution, TCM syndrome scores, and clinical efficacy. Effect estimates are reported as relative risks (RRs), mean differences (MDs), hazard ratios (HRs), or Mann–Whitney U comparisons, as appropriate, with corresponding 95% confidence intervals (CIs) and P values. Please click here to download this Table.
Table 4: Time to resolution of individual phlebitis symptoms and overall composite resolution. Median time to symptom resolution is presented with the interquartile range (IQR). Between-group comparisons were performed using Cox proportional hazards models and summarized as hazard ratios (HRs) with 95% confidence intervals (CIs). P values were derived from log-rank tests. Please click here to download this Table.
Table 5: Traditional Chinese medicine (TCM) syndrome score components and clinical efficacy outcomes. (A) Mean TCM syndrome component scores at baseline and Day 14 in the experimental and control groups, with between-group comparisons at Day 14. (B) Clinical efficacy categories based on percentage reduction in total TCM syndrome score and comparison of overall treatment effectiveness between groups. Continuous variables are presented as mean ± SD and categorical variables as number (%). Please click here to download this Table.
Table 6: Safety, tolerability, adherence, protocol deviations, and concomitant treatments during the study period. Local treatment-related adverse events, discontinuations, adherence outcomes, protocol deviations, and concomitant therapy use are presented as counts (%) or means ± SD. Between-group comparisons are summarized using relative risks (RRs) or mean differences (MDs) with 95% confidence intervals (CIs), together with corresponding P values. Please click here to download this Table.
Table 7: Multivariable logistic regression analysis of treatment response at Day 14. Adjusted odds ratios (ORs) with 95% confidence intervals (CIs) are presented for the primary intention-to-treat (ITT) and per-protocol (PP) sensitivity analyses. Treatment response was defined as phlebitis grade 0–I at Day 14, whereas persistent grade ≥II was classified as non-response. Covariates included baseline demographic and clinical characteristics specified a priori. Please click here to download this Table.
토론
본 연구의 주요 방법론적 결과는 국소 Huzhang Sanhuang 처방을 항암 화학요법으로 유발된 정맥염의 표준화된 간호 경로에 재현 가능하게 통합할 수 있다는 것입니다20. 이 방법의 성공적인 구현은 정맥염의 중증도, 통증, 증상 완화, 염증성 바이오마커, 치료 순응도 및 안전성의 일관된 개선을 통해 가장 잘 입증됩니다. 본 연구에서 Huzhang Sanhuang 처방을 받은 참가자들은 기존의 국소 치료를 받은 그룹보다 14일 차에 지속적인 grade ≥II 정맥염 발생률이 낮았고, 증상 완화 속도가 더 빨랐으며, 통증 강도의 감소 폭이 더 컸고, hs-CRP 및 IL-6 농도가 더 낮게 나타났습니다. 이러한 이점은 높은 치료 순응도와 낮은 국소 부작용 발생률을 유지하면서 달성되었습니다.
통계적 유의성 외에도, 관찰된 치료 효과는 임상적으로 의미가 있을 수 있습니다. VAS 통증 점수의 0.8점 감소는 환자의 편안함에 있어 완만하지만 잠재적으로 중요한 개선을 나타내며, hs-CRP 및 IL-6의 감소는 국소 염증 반응의 완화를 시사합니다. 더욱 중요한 것은, 증상 완화 기간을 약 1.8–2.9일 단축함으로써 환자의 불편함을 줄이고 말초 정맥 화학요법을 중단 없이 원활하게 진행할 수 있다는 점입니다.
재현성을 보장하기 위해 몇 가지 절차적 단계가 매우 중요합니다. 국소 제제물을 가시적인 염증 부위에 균일하게 도포하고, 병변 가장자리에서 약 1 cm 정도 더 넓게 도포하십시오. 도포 두께를 일정하게 유지하고, 각 드레싱을 4 h 동안 유지하며, 14일 연속으로 하루에 두 번 치료를 실시하십시오. 두 연구 그룹 모두에서 천자 부위 평가, 카테터 관리, 증상 모니터링, 환자 교육 및 결과 평가를 표준화하십시오. 약초 제제, 도포 범위, 유지 시간 또는 간호 절차의 가변성은 치료의 일관성을 떨어뜨리고 중재 효과의 해석을 어렵게 할 수 있습니다21.
문제 해결은 주로 국소 내약성과 프로토콜 준수 여부에 집중해야 합니다. 드레싱을 교체할 때마다 적용 부위를 검사하여 홍반, 가려움증, 구진, 삼출물, 수포, 통증 증가 또는 감염 징후가 악화되는지 확인하십시오. 뚜렷한 자극이 발생하거나 감염이 의심되는 경우 국소 치료를 중단하고 임상 평가를 진행하며, 적용을 누락했거나 기타 프로토콜을 준수하지 않은 사항은 즉시 기록하십시오. 치료에도 불구하고 2등급 이상의 정맥염이 지속되는 경우, 단순히 국소 요법을 계속하기보다는 임상적 재평가가 필요한 최적이지 않은 반응으로 간주해야 합니다.
50% 황산마그네슘 습포를 이용한 기존의 국소 관리와 비교했을 때, Huzhang Sanhuang 요법은 더 빠른 증상 완화와 더불어 여러 임상 및 염증 지표에서 더 큰 개선을 나타냈습니다. 이전의 무작위 연구에서도 국소 참기름 도포가 화학요법 유발 정맥염의 통증 강도를 감소시킬 수 있음을 입증하여22, 국소 보완 요법의 잠재적 역할23을 뒷받침하였습니다. 주로 증상 완화에 집중한 이러한 접근 방식들과 달리, 본 요법은 정맥염의 중증도, 통증, 염증성 바이오마커 및 증상 완화에서 일관된 이점을 보였습니다. 그럼에도 불구하고, 재현성을 보장하기 위해서는 표준화된 한약 조제, 배치 간 일관성, 보관 조건 및 도포 절차의 성공적인 구현이 필요합니다.
이 방법은 또한 여러 가지 실질적인 장점을 제공합니다. 비침습적이며, 일상적인 간호 관리에 쉽게 통합될 수 있고, 별도의 치료 경로가 필요하지 않습니다. 1일 2회 도포 일정은 높은 치료 순응도로 이어졌으며, 이는 본 프로토콜이 반복적인 말초 정맥 항암 화학요법을 받는 입원 환자들에게 적용 가능하다는 것을 시사합니다. 통증, 홍반, 부종 및 삭선형 경결의 더 빠른 개선은 환자의 불편함을 줄이고 예정되지 않은 간호 중재의 필요성을 감소시킬 수 있습니다.
이 방법을 적용할 때 몇 가지 제한 사항을 고려해야 합니다. 본 연구는 단일 센터에서 중간 규모의 표본 크기로 수행되었습니다. 국소 제제들의 외관과 냄새가 서로 달랐기 때문에 참가자 눈가림법을 적용하는 것이 불가능했으며, 추적 관찰은 단기 결과로 제한되었습니다. 또한, 일부 참가자들은 14일 차에도 grade ≥ II 정맥염 증상을 계속 보였으며, 이는 중증이거나 지속적인 사례의 경우 중재 효과가 낮을 수 있음을 시사합니다. 본 연구는 화학요법으로 인한 자극성, 카테터 특성 또는 개별 피부 민감도에 따라 치료 효능에 차이가 있는지 판단할 수 있는 통계적 검정력을 갖추지 않았습니다.
향후 다기관 연구에서는 표준화된 배치 품질 기준과 더 긴 추적 관찰 기간을 활용하여 조제 및 도포 프로토콜을 검증해야 합니다. 특히 지속적인 고등급 정맥염, 증상 완화 지연 또는 국소 불내성을 보이는 환자들에게 세심한 주의를 기울여야 합니다. 전반적으로, 국소 Huzhang Sanhuang 처방은 표준 간호의 실용적이고 재현 가능한 보조 요법으로 보이며, 그 효과는 일관된 조제, 표준화된 도포, 체계적인 안전성 모니터링 및 최적의 반응이 나타나지 않을 때의 적시 재평가 여부에 달려 있습니다.
94명의 참가자를 대상으로 한 이 전향적 무작위 대조 연구에서, 표준 간호 관리와 병행한 국소 Huzhang Sanhuang 처방은 화학요법 유발 정맥염에 대해 동일한 간호 경로 내에서 시행된 기존의 국소 치료보다 우수한 임상적 성능을 보였습니다. 중재군에서는 정맥염 중증도의 개선 정도가 더 컸으며, 통증 완화가 더 빨랐고, 증상 해소 시간이 더 짧았으며, hs-CRP 및 IL-6 농도의 감소 폭이 더 컸습니다. 또한, TCM 증후군 점수가 더 많이 개선되었고, 수치상으로 더 높은 전체 유효율과 높은 치료 순응도 및 양호한 안전성 프로파일을 나타냈습니다.
이러한 결과는 화학요법으로 유발된 정맥염에 대해 표준 간호 Care의 보조 수단으로서 국소 Huzhang Sanhuang 처방의 사용이 타당함을 뒷받침합니다. 이 요법은 종양학적 지지 요법에서 증상 조절을 개선하고 회복을 촉진하기 위한 실용적이고 내약성이 좋으며 임상적으로 유의미한 접근 방식입니다. 일반화 가능성을 확인하고 환자 선정 및 시행 전략을 최적화하기 위해 추가적인 다기관 연구가 필요합니다.
공개 사항
원고 작성 과정에서 언어 교정 목적으로만 DeepSeek가 사용되었습니다. 연구 설계, 데이터 분석, 결과 해석 또는 결론 도출에는 사용되지 않았습니다. 모든 과학적 내용은 저자들에 의해 검토 및 승인되었으며, 저자들이 원고에 대한 모든 책임을 집니다.
감사의 글
저자들은 이 무작위 대조 시험에 참여해주신 모든 환자와 그 가족분들께 감사드립니다. 또한 모집, 표준 치료 및 국소 중재의 수행, 추적 관찰, 데이터 수집에 기여해주신 간호 인력분들께 감사를 표합니다. 무작위 배정, 데이터 관리 및 품질 관리를 지원해주신 통계 및 연구 관리 담당자분들의 도움에 감사드립니다.
재료
| 이름 | 회사 | 카탈로그 번호 | 댓글 |
|---|---|---|---|
| 100-메쉬 스테인리스강 여과체 | Hospital Pharmacy, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-FLT-100 | 농축 전 탕약을 여과하는 데 사용됨. 모든 조제 배치에 동일한 100-메쉬 규격을 사용함. |
| 50% 황산마그네슘 용액 | Hospital Pharmacy, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-MGSO4-2025-01 (simulated in-house batch) | 대조군 중재제. 50% w/v 용액으로 조제함; 멸균 거즈에 적셔 가시적 병변과 1-cm의 여유 영역을 덮고, 4시간 동안 유지하며, 14일 동안 하루 2회 적용함. |
| 증례 보고서, 중재 기록지 및 간호 체크리스트 | Study Team, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-CIP-CRF-V1.0 | 스크리닝, 무작위 배정, 국소 도포, 간호 번들 완료 여부, 순응도, 프로토콜 이탈, 결과 및 이상 반응을 기록하는 연구 전용 서식. |
| 중국 약전 | Chinese Pharmacopoeia Commission | 2020 Edition, Part I | Polygonum cuspidatum, Rheum palmatum, Phellodendron amurense 및 Scutellaria baicalensis의 감별 및 품질 평가를 위한 표준 참조서. |
| 디지털 온도 측정기 | Testo SE & Co. KGaA | testo 925, 0563 0925 | 탕약 온도(약 95–100 °C)와 농축 온도(70–80 °C)를 모니터링하는 데 사용됨. |
| 전자 분석 저울 | Mettler-Toledo International Inc. | ME204E | 각 생약 100 g을 정량하고 최종 농축 페이스트 질량을 확인하는 데 사용됨. 판독 가능 범위: 0.1 mg. |
| 고감도 C-반응성 단백질 분석법 및 분석기 | Roche Diagnostics | Tina-quant Cardiac hs-CRP III, 09188240190; cobas c 702 | 0일 차와 14일 차에 공복 정맥혈의 hs-CRP를 측정하는 데 사용됨. 가능한 한 동일한 분석기와 시약 로트를 사용함. |
| Huzhang Sanhuang 국소 페이스트 도포 측정 가이드 | Study Team, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-AG-01 | 가시적 염증 부위와 병변 경계 너머 1 cm 영역에 약 2-mm 두께로 약 0.20 g/cm²를 도포하기 위한 표준 가이드. |
| 저자극성 종이 수술용 테이프 | 3M Company | 3M Micropore 1530-1, 2.5 cm × 9.1 m | 실험군 및 대조군 국소 도포 시 압박 없이 멸균 거즈를 고정하는 데 사용됨. |
| IBM SPSS Statistics | IBM Corporation | Version 26.0 | 카이제곱/Fisher 정확 검정, t 검정, 비모수 검정, 선형 혼합 모델, Kaplan–Meier/log-rank 분석, Cox 회귀 및 로지스틱 회귀를 포함하여 사전 지정된 분석에 사용된 통계 소프트웨어. |
| 인터루킨-6 분석법 및 분석기 | Roche Diagnostics | Elecsys IL-6, 07027532190; cobas e 801 | 0일 차와 14일 차에 공복 정맥혈의 IL-6를 측정하는 데 사용됨. 가능한 한 동일한 분석기와 시약 로트를 사용함. |
| 말초 정맥 카테터, 22G | Becton, Dickinson and Company | BD Insyte Autoguard 22G × 1.00 in, 381423 | 항암화학요법 투여에 사용되는 말초 정맥 유치 카테터; 삽입 부위, 삽관 방향 및 유치 시간을 기록함. |
| 말초 정맥 카테터, 24G | Becton, Dickinson and Company | BD Insyte-N Autoguard 24G × 0.56 in, 381411 | 항암화학요법 투여에 사용되는 말초 정맥 유치 카테터; 삽입 부위, 삽관 방향 및 유치 시간을 기록함. |
| 약국 전용 냉장고 | Qingdao Haier Biomedical Co., Ltd. | HYC-310 | 조제된 Huzhang Sanhuang 페이스트를 2–8 °C에서 보관함. 각 배치는 48시간 이내에 사용하고 2일마다 새로 조제함. |
| Phellodendron amurense 수피 (황백) | Anhui Xiehecheng Pharmaceutical Decoction Pieces Co., Ltd. | Simulated lot HB20250115 | 조제 배치당 100 g을 사용함. 중국 약전에 따라 감별하며 공급처, 로트 번호, 감별 결과 및 분석 증명서를 기록함. |
| Polygonum cuspidatum 뿌리 및 근경 (호장근) | Anhui Xiehecheng Pharmaceutical Decoction Pieces Co., Ltd. | Simulated lot HZ20250112 | 조제 배치당 100 g을 사용함. 중국 약전에 따라 감별하며 공급처, 로트 번호, 감별 결과 및 분석 증명서를 기록함. |
| 초순수 시스템 | Merck KGaA | Milli-Q IQ 7000 | 400-g 생약 혼합물당 4,000 mL의 초순수를 공급하며, 이는 생약 대 물 비율 1:10 (w/v)에 해당함. |
| Rheum palmatum 뿌리 및 근경 (대황) | Anhui Xiehecheng Pharmaceutical Decoction Pieces Co., Ltd. | Simulated lot DH20250110 | 조제 배치당 100 g을 사용함. 중국 약전에 따라 감별하며 공급처, 로트 번호, 감별 결과 및 분석 증명서를 기록함. |
| Scutellaria baicalensis 뿌리 (황금) | Anhui Xiehecheng Pharmaceutical Decoction Pieces Co., Ltd. | Simulated lot HQ20250118 | 조제 배치당 100 g을 사용함. 중국 약전에 따라 감별하며 공급처, 로트 번호, 감별 결과 및 분석 증명서를 기록함. |
| 밀폐형 광구 보관병, 500 mL | Thermo Fisher Scientific | Nalgene HDPE bottle, 2114-0016 | 농축된 Huzhang Sanhuang 페이스트를 보관하는 데 사용됨. 각 병에 조제일, 배치 번호, 보관 온도 및 유효 시간을 표시함. |
| 멸균 거즈 스왑, 10 cm × 10 cm, 8겹 | Winner Medical Co., Ltd. | Simulated item code WN-GS1010-8 | Huzhang Sanhuang 페이스트를 덮거나 50% 황산마그네슘 습포를 준비하는 데 사용됨. |
| 멸균 생리식염수, 0.9% 염화나트륨, 500 mL | Baxter Healthcare Corporation | VIAFLEX container, simulated reference 2B1323Q | 국소 도포 전 및 드레싱 제거 후 병변 피부를 세척하는 데 사용됨. |
| 온도 조절 농축 장치 | Shanghai Yarong Biochemical Instrument Factory | RE-52AA rotary evaporator | 여과된 탕약을 70–80 °C에서 약 1,000 g의 균질한 페이스트(생약 약 0.40 g/g 페이스트에 해당)로 농축하는 데 사용됨. |
| 전통 중의학 증후군 점수표 | Study Team, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-TCM-01 | 국소 발적/홍반, 부종, 작열감, 통증/압통 및 끈 모양의 경결을 포함하는 표준 서식이며, 각 항목은 0에서 3점까지 점수를 매김. |
| 시각 아날로그 척도(VAS) 자 | Study Team, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-VAS-01, 10-cm scale | 0일 차, 7일 차, 14일 차에 통증 강도를 0(통증 없음)에서 10(상상 가능한 최악의 통증)까지 평가하는 데 사용됨. |
| 수성 탕약 장치 | Beijing Donghuayuan Medical Equipment Co., Ltd. | YJX20/1+1D | 400-g 생약 혼합물을 4,000 mL 초순수에 30분 동안 담근 후, 완만한 끓음(약 95–100 °C) 상태에서 30분 동안 달이는 데 사용됨. |
참고문헌
- Hou JW, Hu ZY. Efficacy of Sihuang Zijin powder colloid in treating infusion phlebitis in patients with tumors: a randomized controlled study. J Inflamm Res. 2025;18:8119-8129.
- Li J, et al. Development and validation of a nomogram for predicting intravenous amiodarone-induced phlebitis: a prospective cohort study. Health Sci Rep. 2025;8(11):e71557.
- Li F, et al. Severe phlebitis and cutaneous necrosis following peripheral administration of high-concentration potassium chloride: a case report and vascular access management implications. Sci Prog. 2025;108(1):368504251314081.
- Henedy WM, et al. A quasi-experimental study on conservative nursing measures for preventing phlebitis in chemotherapy patients. Sci Rep. 2025;15(1):45226.
- Nasiri M, et al. Is the topical application of sesame oil (Sesamum indicum L.) combined with standard care valuable and safe for managing infusion-related phlebitis: evidence from a systematic review with meta-analysis of randomized controlled trials. Complement Ther Med. 2025;88:103122.
- Zhao Y, et al. Effect of external application of Chinese medicine liquid on preventing phlebitis caused by intravenous indwelling needle: a retrospective study. Biotechnol Genet Eng Rev. 2024;40(3):2862-2873.
- Safikani Mohammadzadeh N, et al. Comparing the effects of sesame oil vs. nitroglycerin ointment on the incidence of chemotherapy-induced phlebitis: a single-blind clinical trial. Asian Pac J Cancer Prev. 2023;24(4):1113-1117.
- Sakakida T, et al. Midline catheter use for cancer patients receiving 5-FU chemotherapy: prospective study of safety and outcomes. Oncologist. 2025;30(5):oyaf108.
- Cernuda-Martínez JA, et al. Clinical-epidemiological predictors of phlebitis associated with peripheral intravenous catheters in Spanish hospitals: results of a national cohort study. Int J Nurs Stud Adv. 2025;9:100355.
- Amble K, et al. Implementation of an infection prevention care bundle for peripheral intravenous catheters (PIVCs): a quality improvement study to enhance PIVC quality and reduce complications. Nurs Rep. 2025;15(11):379.
- Okyay B, Basak T. The effect of cold gel pack application in the prevention of amiodarone-related phlebitis. Nurs Crit Care. 2024;29(6):1739-1743.
- Aksoy F, Bayram SB. The effect of warm moist compresses in peripheral intravenous catheter-related phlebitis. Eur J Oncol Nurs. 2023;67:102438.
- Nickel B, et al. Infusion therapy standards of practice, 9th edition. J Infus Nurs. 2024;47(1 Suppl 1):S1-S285.
- Li J, et al. Implementation of a peripheral intravenous catheter bundle to reduce phlebitis and hospital-onset Staphylococcus aureus bacteremia: a quality improvement project. Infect Prev Pract. 2025;7(4):100495.
- Seid K, et al. Incidence of peripheral intravenous cannula-induced phlebitis and its determinants among admitted patients in Ethiopia: systematic review and meta-analysis. Discov Med. 2024;1:89.
- El-Sayad HE, Aboalizm SE, Abd Elhy AH. Effect of preventive measures on chemotherapy-induced phlebitis among patients with cancer. Menoufia Nurs J. 2023;8(1):187-202.
- Torné-Ruiz A, et al. Assessment, treatment, and follow-up of phlebitis related to peripheral venous catheterisation: a Delphi study in Spain. Healthcare (Basel). 2024;12(3):378.
- Ertaş Akyüz G, Turan N. Association between peripheral intravenous catheters and clinical characteristics in the development of phlebitis. J Vasc Access. 2024;26(2):540-546.
- Beyene Z, et al. Time to phlebitis onset and its predictors among admitted patients with peripheral intravenous cannulas at Debre Markos Comprehensive Specialized Hospital, Northwest Ethiopia, 2024/2025: a prospective follow-up study. PLoS One. 2025;20(11):e0336176.
- Zhang Y, et al. Sanhuang ointment prolongs indwelling time and promotes vein injury repair in patients receiving intravenous infusion via peripheral venous indwelling needles. Pak J Pharm Sci. 2024;37(5).
- Brørs G, et al. Amiodarone-induced phlebitis: incidence and adherence to a clinical practice guideline. Eur J Cardiovasc Nurs. 2023;22(8):824-831.
- Shamloo MBB, et al. Effects of topical sesame (Sesamum indicum) oil on the pain severity of chemotherapy-induced phlebitis in patients with colorectal cancer: a randomized controlled trial. Complement Ther Clin Pract. 2019;35:78-85.
- Gülşen M, Arslan S. Effects of open-label sesame oil applied to cardiac surgery patients in preventing amiodarone-induced phlebitis: a randomized controlled trial. Nurs Crit Care. 2025;30(2):e13085.