이 무작위 대조 시험에서는 복강경 근치성 위절제술을 받는 130명의 환자를 대상으로 마약성 진통제 절약 다모달 진통법과 전통적인 마약성 진통법을 비교하였습니다. 두 그룹 간의 위장관 회복, cine-MRI 운동성 측정치, 통증 결과 및 마약성 진통제 소비량을 비교 분석하였습니다.
연구 논문
복강경 위절제술 후 오피오이드 절감 진통법: 탐색적 임상 결과 및 Cine-MRI를 이용한 소장 운동성 평가
이 논문에서
요약
초록
본 전향적 무작위 대조 시험에서는 복강경 근치적 위절제술을 받는 130명의 환자를 대상으로, 각 군에 65명씩 배정하여 마약성 진통제를 절감한 다모달 통증 조절법과 기존의 마약성 진통제 조절법을 비교하였습니다. 위장관 운동성은 수술 후 24, 48, 72시간에 cine-MRI를 사용하여 평가하였습니다. 수술 후 장폐색(POI)은 마약성 진통제 절감군에서 6/65명(9.2%), 기존 조절군에서 17/65명(26.2%)에게 발생하였습니다. 군 간 비교 결과, 양측 Fisher 정확 검정 p = 0.0201, 보정되지 않은 위험비 0.35 (95% CI, 0.15–0.84), 그리고 위험도 차이는 −16.9%포인트였습니다. 수술 후 평가 전반에서 마약성 진통제 절감군의 cine 자기공명영상(Cine-MRI) 수축 빈도, 수축 진폭 및 운동성 점수가 더 높게 나타났습니다. 또한, 마약성 진통제 절감군은 마약성 진통제 노출량과 통증 점수가 더 낮았으며 위장관 회복 시간이 더 짧았습니다. 이러한 결과는 복강경 위절제술 후 주술기 전략으로서 다모달 마약성 진통제 절감법의 사용을 뒷받침하며, 수술 후 위장관 운동성의 동적 평가를 위한 cine-MRI의 잠재적 가치를 입증합니다.
서론
수술 후 장폐색(POI)은 수술 후 위장관 회복이 저해된 상태를 의미하지만, 이에 대한 조작적 정의와 평가 시점은 연구마다 상이합니다1,2. 수술적 스트레스, 염증, 자율 신경 경로 및 주변기 약물 투여는 POI의 다요인성 병태생리에 기여합니다3,4. 말초 µ-오피오이드 수용체 활성화는 장의 추진력을 억제할 수 있으며, 이는 적절한 진통 효과를 유지하면서 오피오이드 노출을 줄여야 하는 근거가 됩니다. 그럼에도 불구하고 임상적 진단은 개별적인 회복 이정표 및 영상 의학적 장 운동 측정치와 구분되어야 합니다.
위절제술 후의 강화 회복(Enhanced recovery)은 진통 요법을 영양 공급, 조기 보행 및 기타 주술기 조치와 통합하여 시행합니다5. 전복강경 원위 위절제술 후 다중 모드 경로(multimodal pathway)를 적용한 무작위 대조 시험에서는 더 빠른 기능적 회복이 보고되었으나, 각 구성 요소의 개별적인 기여도는 분리하여 확인하지 못했습니다6. 여러 외과 전문 분야를 대상으로 한 TASMAN 전향적 코호트 연구 결과, 퇴원 시 마약성 진통제 처방과 통증 완화에 대한 만족도 사이에 유의미한 상관관계가 없음을 발견했으며, 관찰 연구 설계로 인해 인과 관계 추론에는 한계가 있습니다7. 비뇨기과적 검토에서도 시술별 다중 모드 접근법의 유효성을 지지하고 있습니다8. 마약성 진통제 절감(Opioid sparing)을 반드시 마약성 진통제의 강제적 제거와 동일시해서는 안 됩니다. dexmedetomidine 기반의 마약성 진통제 없는 수술 중 마취를 평가한 POFA 임상 시험은 심각한 서맥 발생으로 인해 중단되었으며, 위장관 회복 측면에서 이점이 입증되지 않았습니다9. 한 체계적 문헌 고찰에 따르면 마약성 진통제 없는 마취 시 수술 후 구역 및 구토는 감소했으나, 임상적으로 중요한 진통 효과는 없었으며 안전성에 대한 불확실성이 있는 것으로 나타났습니다10.
위절제술 특이적 무작위 대조 시험을 통해 카테터 기반의 늑하 복횡근 평면 마취, 단회 늑하 차단술 및 횡돌기간 차단술의 효과가 평가되었습니다11,12,13. 이러한 기법들은 해부학적 표적과 투여 일정에서 차이가 있으며, 복벽 차단술은 주로 체성 통증을 해결하며 다모드 진통법의 한 구성 요소를 이룹니다14. 가스 배출 및 경구 섭취와 같은 임상적 지표는 회복의 실질적인 지표를 제공하지만, 장벽의 운동성을 직접적으로 정량화하지는 못합니다. Cine-MRI는 전리 방사선 없이 동적 평가를 가능하게 합니다. 이전 연구들에서는 소장의 정량적 측정, 운동 등록 방법, 관찰자 간 변동성 및 수술 후 소장 영상화에 대해 기술하여15,16,17,18, 수술 후 위장관 운동성 평가에 대한 추가적인 적용 가능성을 뒷받침하였습니다.
본 임상 시험에서는 복강경 근치적 위절제술 후 오피오이드 절약 다모드 진통법과 전통적인 오피오이드 진통법을 비교하였습니다. 일차 목적은 보고된 POI의 발생률을 비교하는 것이었습니다. 이차 목적은 연속적인 cine-MRI 운동성 측정치, 통증, 오피오이드 소비량 및 임상적 회복을 비교하는 것이었습니다. 영상 결과는 POI에 대한 검증된 진단 검사라기보다 위장관 회복의 보완적 측정치로 간주되었습니다.
프로토콜
The study protocol was approved by the Clinical Research Ethics Committee of Guangdong Medical University Affiliated Hospital (approval number: PJKT2025-316; approval date: December 10, 2023). Written informed consent was obtained from all participants before study procedures were performed. After ethics approval was obtained, patients scheduled for elective laparoscopic radical gastrectomy were screened for eligibility between December 2023 and December 2025.
Study design
A two-group, parallel randomized comparison of opioid-sparing multimodal analgesia and conventional opioid analgesia was conducted in patients undergoing laparoscopic radical gastrectomy. The study schedule is shown in Figure 1, and the eligibility, allocation, treatment, and follow-up procedures are documented in Figure 2.
Gastrointestinal motility was assessed at 24, 48, and 72 h after surgery. Clinical recovery and analgesic outcomes were recorded at the prespecified assessment time points. Figure 1 summarizes the intervention components and assessment schedule.
Participants and sample size
Inclusion criteria were age 18–75 years, American Society of Anesthesiologists (ASA) physical status I–III, pathologically diagnosed gastric cancer without distant metastasis, planned laparoscopic radical gastrectomy, ability to provide informed consent, and suitability for MRI.
The stated exclusion criteria were applied, including previous intestinal obstruction or intestinal surgery, MRI contraindications, long-term opioid use or dependence, severe hepatic or renal impairment (Child–Pugh class C or creatinine clearance <30 mL/min), severe cardiopulmonary disease, psychiatric conditions preventing participation, inability to complete follow-up or MRI, and pregnancy or breastfeeding.
The planned sample size was determined before study initiation based on the expected difference in the primary outcome between the two groups. PASS software (version 15, NCSS, LLC, USA) was used for the initial sample size estimate. However, the original input parameters, assumptions, and effect-size estimates used for this calculation were not available for independent verification. Therefore, the final recruitment target was set at 130 participants, with 65 participants allocated to each group. All randomized participants were included in the intention-to-treat analysis.
Randomization and masking
An independent statistician generated the random allocation sequence, and group assignments were placed in opaque sealed envelopes. Envelopes were opened after eligibility confirmation and enrollment procedures were completed. Because the analgesic interventions involved different routes of administration, anesthesiologists and surgeons responsible for perioperative management were not blinded to group allocation. Outcome assessors, cine-MRI readers, and data analysts were blinded to group assignment. Outcome assessments were performed by personnel who were not involved in treatment allocation
Anesthesia and analgesia
The conventional group received patient-controlled intravenous analgesia (PCIA) containing sufentanil (2 µg/mL) according to the institutional postoperative analgesia protocol. The PCIA settings were as follows: background infusion rate of 2 mL/h, bolus dose of 2 mL, lockout interval of 15 min, and a maximum dose limit of 20 mL over 4 h. Nonsteroidal anti-inflammatory drugs (parecoxib 40 mg intravenously every 12 h) were administered as rescue analgesics when predefined criteria were met.
The opioid-sparing group received ultrasound-guided bilateral transversus abdominis plane blocks and rectus sheath blocks using 0.2% ropivacaine (20 mL per side for the transversus abdominis plane block and 10 mL per side for the rectus sheath block; total dose 120 mg) combined with dexamethasone (5 mg). Postoperative analgesia included continuous infusion of a multimodal analgesic solution (e.g., lidocaine 1 mg/kg/h and/or other institutional standard components) at 2 mL/h, intravenous dexmedetomidine (a loading dose of 0.5 µg/kg followed by an infusion rate of 0.2 µg/kg/h for 24 h), and intravenous acetaminophen (1 g every 8 h).
Cine-MRI acquisition and analysis
Cine-MRI was performed on a 3.0 T scanner at 24, 48, and 72 h after surgery. A two-dimensional balanced steady-state free-precession sequence was used with repetition time 3.4 ms, echo time 1.2 ms, flip angle 75°, slice thickness 8–10 mm, matrix 256 x 256, field of view 400–450 mm, and temporal resolution 0.3 s/frame. Three 30 s acquisitions were obtained with respiratory gating. Patients fasted for 6 h before each cine-MRI examination and received an oral bowel-distension preparation consisting of 1 L polyethylene glycol solution (macrogol 4000 formulation) approximately 60 min before imaging acquisition.
Two independent readers, blinded to group allocation, used semi-automated cine-MRI analysis software (MATLAB-based in-house software, version R2023a) to analyze representative jejunal and ileal segments. For each patient, representative jejunal segment(s) and representative ileal segment(s) were analyzed, with each segment measuring approximately 5 cm in length. Jejunal and ileal segments were selected based on clear visualization of the bowel wall, adequate luminal distension, and absence of severe motion artifacts or overlapping bowel loops. Representative segments were defined as bowel segments that were continuously visualized throughout the cine-MRI acquisition period and exhibited sufficient peristaltic activity for quantitative assessment. Measurements included contraction frequency, contraction amplitude, and motility grade. Motility grade was assigned using a three-level ordinal scale: 1, no peristalsis; 2, weak peristalsis; and 3, normal peristalsis. Contraction frequency was calculated as the number of visible bowel contractions divided by the observation duration and expressed as contractions per minute. Contraction amplitude was calculated as the maximal change in bowel diameter between the contracted and relaxed states during the cine-MRI acquisition and was expressed in millimeters. The measurements from the two readers were averaged for analysis.
Outcomes and postoperative management
POI was designated as the primary outcome and was assessed during the first 7 postoperative days. Two independent clinicians who were blinded to treatment allocation diagnosed POI on the basis of clinically significant delayed gastrointestinal recovery, characterized by one or more of the following: persistent intolerance of oral intake; nausea or vomiting requiring clinical intervention; inadequate recovery of bowel function; or other clinically significant gastrointestinal dysfunction requiring additional management. The I-FEED score was used as a standardized measure of postoperative gastrointestinal function, with scores of 0–2 indicating normal gastrointestinal function, 3–5 indicating postoperative gastrointestinal intolerance, and ≥6 indicating postoperative gastrointestinal dysfunction. The I-FEED score was not used as a standalone diagnostic threshold for POI19.
Outcome assessors were trained and masked to group assignment. Pain and quality-of-recovery assessments were collected by interview, and cine-MRI examinations were interpreted by masked readers. Postoperative management included routine clinical monitoring, analgesia, antiemetic treatment, nutritional support, fluid and electrolyte management, and escalation of care when clinically indicated. Rescue analgesia was administered when postoperative pain was inadequately controlled despite the assigned analgesic regimen. Rescue antiemetic treatment was administered for clinically significant nausea or vomiting requiring treatment. Numerical rating scale (NRS) pain was assessed at predefined postoperative time points, and Quality of Recovery-15 (QoR-15) was used to evaluate postoperative recovery quality20,21,22.
Statistical analysis
Statistical analyses were performed using SPSS version 26.0. Continuous variables were assessed for distributional characteristics and summarized as mean ± standard deviation or median (interquartile range), as appropriate. Between-group comparisons used independent-samples t tests or Mann–Whitney U tests. Categorical variables were compared using χ2 tests or two-sided Fisher's exact tests. Longitudinal outcomes measured at multiple postoperative time points were analyzed using a two-way repeated-measures analysis of variance (ANOVA), with postoperative time as the within-subjects factor and treatment group as the between-subjects factor. The group-by-time interaction was evaluated to determine whether changes over time differed between groups. The assumption of sphericity was assessed using Mauchly’s test, and the Greenhouse–Geisser correction was applied when the assumption was violated. Post hoc pairwise comparisons were performed with Bonferroni adjustment for multiple comparisons. Binary outcomes are presented with risk estimates and 95% confidence intervals where appropriate. All tests were two-sided, with p < 0.05 considered statistically significant. Opioid doses were converted to morphine milligram equivalents (MME) using published equianalgesic conversion guidelines23. Sufentanil doses were converted using the conversion factor of 1 µg sufentanil = 10 mg intravenous morphine equivalents. The same conversion approach was applied consistently for all participants.
For the reported analysis, sufentanil was converted using the stated conversion factor of 1 µg sufentanil = 10 mg intravenous morphine equivalents, and total MME was calculated from the administered sufentanil dose using this factor.
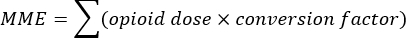
결과
Participant flow
The target sample size was determined before study initiation based on the planned comparison of the primary outcome between the two groups. Sample-size estimation was performed using PASS software (version 15, NCSS, LLC, USA). However, the original input parameters and assumptions used for the calculation could not be independently verified from the available study records. Therefore, the final sample size was retained as the prespecified recruitment target, and the uncertainty regarding the reproducibility of the original sample-size calculation is acknowledged as a limitation. A total of 130 patients were randomized, with 65 allocated to each group. The flow chart reports that all allocated patients received the intervention and were included in the intention-to-treat analysis, with no losses to follow-up.
Baseline characteristics
Baseline and perioperative characteristics are summarized in Table 1. In the opioid-sparing and conventional groups, respectively, mean age was 59.3 ± 8.7 and 60.1 ± 9.2 years, the proportion of men was 64.6% and 61.5%, and mean body mass index was 22.4 ± 3.1 and 22.7 ± 2.9 kg/m2.
ASA physical status, tumor stage, comorbidities, hemoglobin, surgical duration, blood loss, and lymph-node yield are described in Table 1. Baseline characteristics are presented descriptively; no baseline significance tests are used to claim equivalence or rule out confounding.
Primary outcome: incidence of postoperative ileus (POI)
POI occurred in 6/65 patients (9.2%) in the opioid-sparing group and 17/65 patients (26.2%) in the conventional group (Table 2). POI cases were identified according to the prespecified diagnostic criteria described in the protocol section. The between-group comparison yielded a two-sided Fisher exact p = 0.0201, an unadjusted risk ratio of 0.35 (95% CI, 0.15–0.84), and a risk difference of −16.9 percentage points (opioid-sparing minus conventional).
Contraction frequency and amplitude were higher in the opioid-sparing group at 24, 48, and 72 h (all reported p < 0.001). Motility grading scores were also higher (24 h, p = 0.002; 48 and 72 h, p < 0.001; Table 3).
The imaging outcomes and clinical recovery milestones showed consistent between-group trends, with higher cine-MRI motility measures accompanying faster gastrointestinal recovery in the opioid-sparing group.
Visualized gastrointestinal motility by cine-MRI
Serial cine-MRI measurements are summarized in Table 3. A quantitative presentation of the reported group-level values is provided in Figure 3.
Figure 3 shows contraction frequency, contraction amplitude, and motility grading scores at 24, 48, and 72 h. Points indicate group means, and error bars indicate standard deviations. These summaries describe differences between-group differences and do not reproduce individual patient image sequences.
At 48 h, contraction frequency was 1.45 ± 0.42 versus 0.93 ± 0.37 contractions/min, amplitude was 5.9 ± 1.6 versus 3.8 ± 1.4 mm, and motility score was 2.3 ± 0.6 versus 1.7 ± 0.5 in the opioid-sparing and conventional groups, respectively (reported p < 0.001 for each comparison). No inter-reader reliability coefficient, repeatability analysis, or diagnostic sensitivity estimate is available in the reported results.
Opioid consumption
Figure 4 summarizes perioperative and postoperative opioid exposure in the two study groups.
Reported median perioperative opioid exposure expressed as morphine milligram equivalents (MME) was 36.8 (interquartile range, 27–48) in the opioid-sparing group and 108.4 (74–125) in the conventional group (reported p < 0.01). The difference between these reported medians corresponds to a 66.1% lower median exposure in the opioid-sparing group.
Median postoperative MME values on postoperative days 1, 2, and 3 were 10.4, 6.9, and 2.8 in the opioid-sparing group and 46.2, 29.5, and 17.8 in the conventional group, respectively.
Postoperative pain scores and rescue analgesia
Resting numerical rating scale (NRS) scores were lower in the opioid-sparing group at all reported time points (Figure 5A; Table 4). At 12, 24, 48, and 72 h, mean scores were 2.4 ± 0.6 versus 3.0 ± 0.7, 2.1 ± 0.5 versus 2.7 ± 0.6, 1.6 ± 0.6 versus 2.2 ± 0.7, and 1.1 ± 0.5 versus 1.5 ± 0.6, respectively.
Movement NRS scores were also lower in the opioid-sparing group (Figure 5B; Table 4). At 12, 24, 48, and 72 h, mean scores were 3.2 ± 0.7 versus 3.9 ± 0.8, 2.8 ± 0.6 versus 3.5 ± 0.7, 2.1 ± 0.7 versus 2.8 ± 0.8, and 1.4 ± 0.6 versus 1.9 ± 0.7, respectively.
Rescue analgesia within 72 h was required by 11/65 patients (16.9%) in the opioid-sparing group and 27/65 patients (41.5%) in the conventional group (two-sided Fisher exact p = 0.0035). Median rescue analgesic administrations were 0 (0–1) and 1 (0–2), respectively (p = 0.001; Table 4).
Quality of recovery and clinical recovery milestones
Quality-of-recovery scores and gastrointestinal recovery times are summarized in Figure 6 and Table 5. The reported QoR-15 scores on postoperative days 1, 2, 3, and 7 were 106.3 ± 10.9 versus 88.4 ± 12.6, 119.7 ± 9.7 versus 99.2 ± 11.3, 136.8 ± 8.4 versus 126.1 ± 9.8, and 141.2 ± 9.1 versus 133.5 ± 10.4 in the opioid-sparing and conventional groups, respectively (all reported p < 0.001; Figure 6). Higher scores indicate better-reported recovery.
Median time to first flatus was 28 (22–35) versus 48 (38–62) h; time to first defecation was 52 (42–68) versus 78 (65–96) h; and time to tolerance of solid food was 72 (60–85) versus 96 (84–118) h in the opioid-sparing and conventional groups, respectively (all p < 0.001; Table 5).
Secondary clinical outcomes and complications
Secondary clinical outcomes were compared between the two groups, with emphasis on hospital stay, postoperative nausea and vomiting, rescue antiemetic use, readmission, and postoperative complications.
Table 6 summarizes hospital stay, postoperative nausea and vomiting, rescue antiemetic use, and readmission. Table 7 summarizes other postoperative complications.
Median postoperative hospital stay was 6 (5–7) versus 8 (7–10) days (p < 0.001). Postoperative nausea and vomiting occurred in 12/65 patients (18.5%) in the opioid-sparing group and 29/65 (44.6%) in the conventional group (two-sided Fisher's exact p = 0.0023). Rescue antiemetic use was 12.3% versus 33.8%, and 30-day readmission was 1.5% versus 6.2%, respectively.
Table 7 summarizes wound infection (2/65 versus 4/65), pulmonary infection (1/65 versus 3/65), and urinary retention (2/65 versus 5/65). Two-sided Fisher's exact p-values were 0.6801, 0.6191, and 0.4401, respectively. No anastomotic leaks or 30-day deaths occurred in either group.
Data Availability:
The data supporting the findings of this study are available in Zenodo at https://zenodo.org/records/22686172.
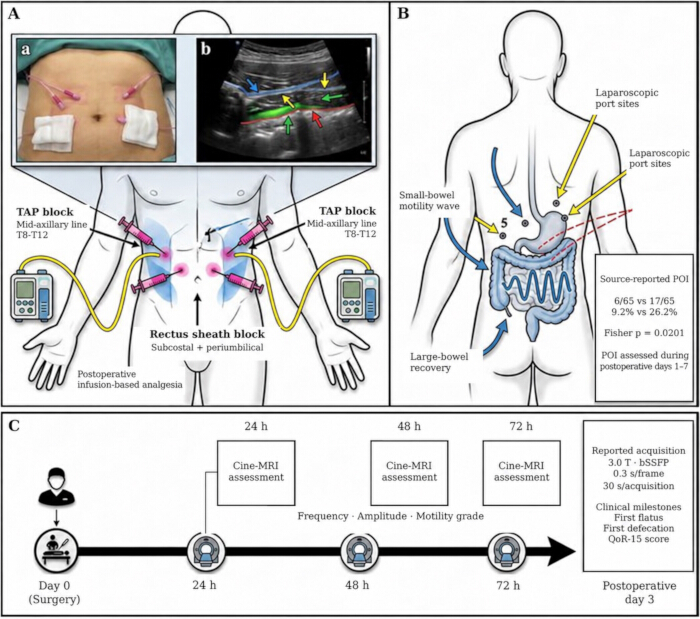
Figure 1: Opioid-sparing analgesia and postoperative gastrointestinal recovery assessment schedule. (A) Components of the opioid-sparing analgesic intervention, including transversus abdominis plane blocks, rectus sheath blocks, and postoperative analgesic management. (B) Postoperative gastrointestinal recovery assessment, including the reported incidence of postoperative ileus (POI) and related gastrointestinal outcomes. (C) Cine-MRI assessment schedule at 24, 48, and 72 h after surgery, with evaluation of intestinal motility parameters and clinical recovery milestones. Please click here to view a larger version of this figure.
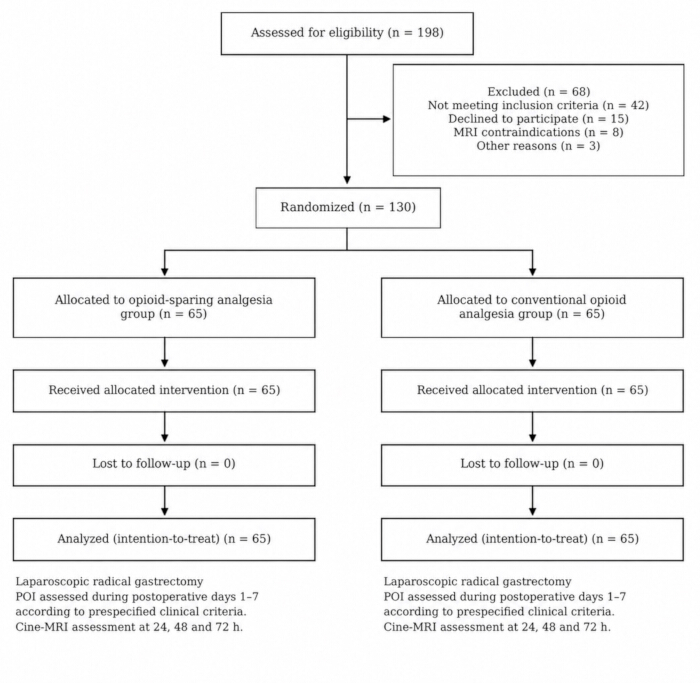
Figure 2: Participant flow. Of 198 patients assessed for eligibility, 68 were excluded, and 130 were randomized. Each group included 65 patients in the intention-to-treat analysis. Please click here to view a larger version of this figure.
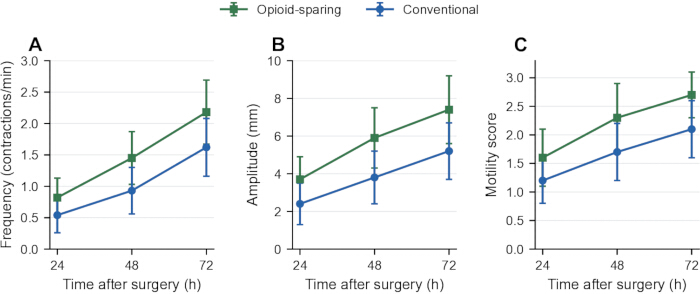
Figure 3: Serial cine-MRI motility measurements. (A) Contraction frequency. (B) Contraction amplitude. (C) Motility grading score. Points and error bars represent mean ± standard deviation; n = 65 per group. Statistical comparisons were performed using two-way repeated-measures ANOVA with Bonferroni-adjusted post hoc comparisons. Please click here to view a larger version of this figure.
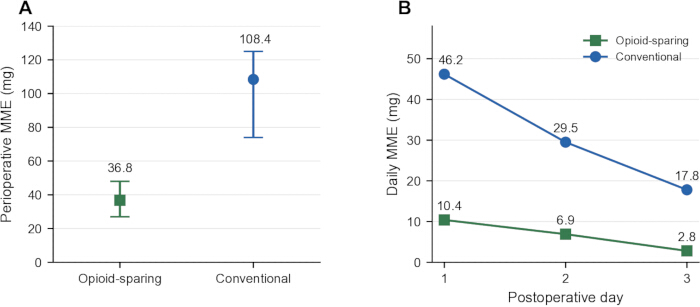
Figure 4: Opioid exposure. (A) Perioperative morphine milligram equivalents (MME), shown as median with interquartile range. (B) Median MME on postoperative days 1–3; n = 65 per group. Please click here to view a larger version of this figure.
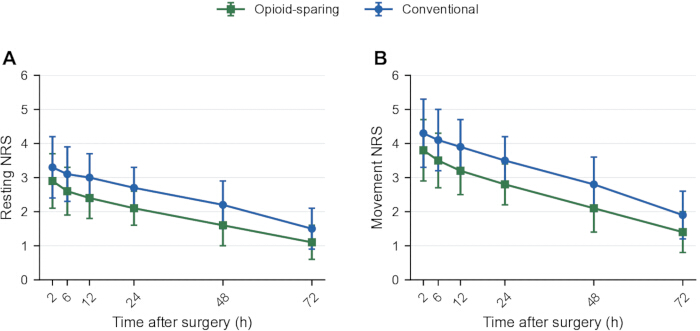
Figure 5: Postoperative pain. (A) Resting numerical rating scale (NRS). (B) Movement NRS. Points and error bars represent mean ± standard deviation; n = 65 per group. Please click here to view a larger version of this figure.
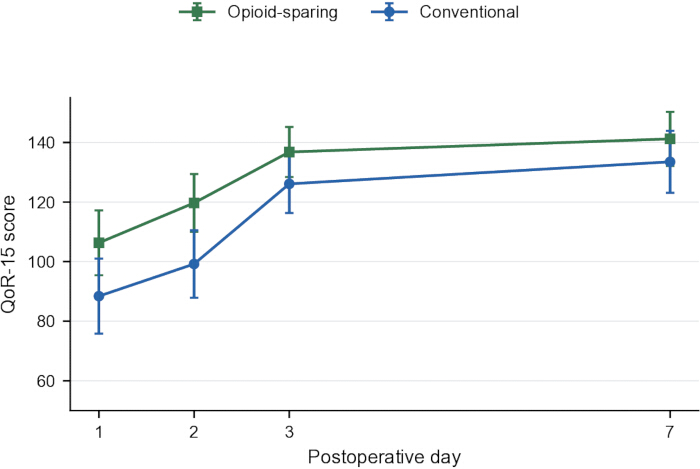
Figure 6: Quality of recovery. QoR-15 scores on postoperative days 1, 2, 3, and 7 are shown as mean ± standard deviation; n = 65 per group. Higher scores indicate better recovery. Please click here to view a larger version of this figure.
| Characteristics | Opioid-sparing analgesia group (n = 65) | Conventional opioid analgesia group (n = 65) |
| Age (years), mean ± SD | 59.3 ± 8.7 | 60.1 ± 9.2 |
| Sex, n (%) | ||
| - Male | 42 (64.6) | 40 (61.5) |
| - Female | 23 (35.4) | 25 (38.5) |
| Body mass index (kg/m2), mean ± SD | 22.4 ± 3.1 | 22.7 ± 2.9 |
| ASA physical status, n (%) | ||
| - I | 12 (18.5) | 10 (15.4) |
| - II | 40 (61.5) | 42 (64.6) |
| - III | 13 (20.0) | 13 (20.0) |
| Tumor stage (AJCC 8th), n (%) | ||
| - I | 18 (27.7) | 17 (26.2) |
| - II | 25 (38.5) | 27 (41.5) |
| - III | 22 (33.8) | 21 (32.3) |
| Comorbidities, n (%) | ||
| - Hypertension | 28 (43.1) | 30 (46.2) |
| - Diabetes mellitus | 15 (23.1) | 14 (21.5) |
| - Chronic obstructive pulmonary disease | 7 (10.8) | 8 (12.3) |
| Preoperative hemoglobin (g/dL), mean ± SD | 12.8 ± 1.4 | 12.6 ± 1.5 |
| Surgical duration (min), mean ± SD | 192.4 ± 28.6 | 195.7 ± 30.2 |
| Intraoperative blood loss (mL), mean ± SD | 148.2 ± 45.9 | 152.3 ± 47.1 |
| Lymph nodes resected, median (IQR) | 28 (24–32) | 27 (23–31) |
Table 1: Baseline and perioperative characteristics. Data are mean ± standard deviation, median (interquartile range), or n (%), as labeled. Abbreviations: ASA = American Society of Anesthesiologists; AJCC = American Joint Committee on Cancer; BMI = body mass index. Group size is 65 in each arm.
| Outcomes | Opioid-sparing analgesia group (n = 65) | Conventional opioid analgesia group (n = 65) | p value |
| Postoperative ileus (POI), n (%) | 6 (9.2) | 17 (26.2) | 0.0201 |
Table 2: Incidence of postoperative ileus. Data are n (%) with 65 patients per group. Between-group comparison used a two-sided Fisher's exact test. POI was defined according to the prespecified clinical criteria described in the protocol section.
| Parameter | Time Point | Opioid-sparing analgesia group (n = 65) | Conventional opioid analgesia group (n = 65) | p value |
| Contraction frequency (contractions/min) | 24 h | 0.82 ± 0.31 | 0.54 ± 0.28 | <0.001 |
| 48 h | 1.45 ± 0.42 | 0.93 ± 0.37 | <0.001 | |
| 72 h | 2.18 ± 0.51 | 1.62 ± 0.46 | <0.001 | |
| Contraction amplitude (mm) | 24 h | 3.7 ± 1.2 | 2.4 ± 1.1 | <0.001 |
| 48 h | 5.9 ± 1.6 | 3.8 ± 1.4 | <0.001 | |
| 72 h | 7.4 ± 1.8 | 5.2 ± 1.5 | <0.001 | |
| Motility grading score (1–3) | 24 h | 1.6 ± 0.5 | 1.2 ± 0.4 | 0.002 |
| 48 h | 2.3 ± 0.6 | 1.7 ± 0.5 | <0.001 | |
| 72 h | 2.7 ± 0.4 | 2.1 ± 0.5 | <0.001 |
Table 3: Serial cine-MRI motility measurements. Data are mean ± standard deviation. Motility scores are graded as 1 = no peristalsis; 2 = weak peristalsis; and 3 = normal peristalsis. Group size is 65 per arm.
| Parameter | Time Point | Opioid-sparing analgesia group (n = 65) | Conventional opioid analgesia group (n = 65) | p value |
| Resting NRS, mean ± SD | 2 h | 2.9 ± 0.8 | 3.3 ± 0.9 | 0.012 |
| 6 h | 2.6 ± 0.7 | 3.1 ± 0.8 | 0.003 | |
| 12 h | 2.4 ± 0.6 | 3.0 ± 0.7 | <0.001 | |
| 24 h | 2.1 ± 0.5 | 2.7 ± 0.6 | <0.001 | |
| 48 h | 1.6 ± 0.6 | 2.2 ± 0.7 | 0.001 | |
| 72 h | 1.1 ± 0.5 | 1.5 ± 0.6 | 0.008 | |
| Dynamic (movement) NRS, mean ± SD | 2 h | 3.8 ± 0.9 | 4.3 ± 1.0 | 0.007 |
| 6 h | 3.5 ± 0.8 | 4.1 ± 0.9 | 0.002 | |
| 12 h | 3.2 ± 0.7 | 3.9 ± 0.8 | <0.001 | |
| 24 h | 2.8 ± 0.6 | 3.5 ± 0.7 | <0.001 | |
| 48 h | 2.1 ± 0.7 | 2.8 ± 0.8 | <0.001 | |
| 72 h | 1.4 ± 0.6 | 1.9 ± 0.7 | 0.004 | |
| Patients requiring rescue analgesia, n (%) | 0–72 h | 11 (16.9) | 27 (41.5) | 0.0035 |
| Number of rescue doses per patient, median (IQR) | 0–72 h | 0 (0–1) | 1 (0–2) | 0.001 |
Table 4: Postoperative pain scores and rescue analgesia. NRS values are mean ± standard deviation; rescue use is n (%); rescue administrations are median (interquartile range). Group size is 65 per arm. Abbreviations: NRS = numerical rating scale; SD = standard deviation; IQR = interquartile range.
| Milestone | Opioid-sparing analgesia group (n = 65) | Conventional opioid analgesia group (n = 65) | p value |
| Time to first flatus (h) | 28 (22–35) | 48 (38–62) | <0.001 |
| Time to first defecation (h) | 52 (42–68) | 78 (65–96) | <0.001 |
| Time to tolerance of solid diet (h) | 72 (60–85) | 96 (84–118) | <0.001 |
Table 5: Gastrointestinal recovery milestones. Values are median (interquartile range), in hours, with 65 patients per group.
| Parameter | Opioid-sparing analgesia group (n = 65) | Conventional opioid analgesia group (n = 65) | p value |
| Postoperative hospital stay, days, median (IQR) | 6 (5–7) | 8 (7–10) | <0.001 |
| Postoperative nausea and vomiting, n (%) | 12 (18.5) | 29 (44.6) | 0.0023 |
| Rescue antiemetic use, % | 12.3 | 33.8 | — |
| 30-day readmission, % | 1.5 | 6.2 | — |
Table 6: Secondary clinical outcomes. Hospital stay is median (interquartile range); postoperative nausea and vomiting are n (%); rescue antiemetic use and readmission are percentages. Group size is 65 per arm.
| Parameter | Opioid-sparing analgesia group (n = 65) | Conventional opioid analgesia group (n = 65) | p value |
| Wound infection, n (%) | 2 (3.1) | 4 (6.2) | 0.6801 |
| Pulmonary infection, n (%) | 1 (1.5) | 3 (4.6) | 0.6191 |
| Urinary retention, n (%) | 2 (3.1) | 5 (7.7) | 0.4401 |
| Anastomotic leakage, n (%) | 0 (0) | 0 (0) | — |
| 30-day mortality, n (%) | 0 (0) | 0 (0) | — |
Table 7: Other postoperative complications. Data are n (%), with 65 patients per group. Between-group comparisons for nonzero events used two-sided Fisher's exact tests.
토론
연구 결과, 마약성 진통제 절감 다모드 진통법은 복강경 위절제술 후 더 낮은 POI 발생률, 마약성 진통제 노출 감소, 더 낮은 수술 후 통증 점수 및 더 빠른 위장관 회복과 연관이 있는 것으로 나타났습니다. POI 발생률은 마약성 진통제 절감군에서 9.2%, 기존 대조군에서 26.2%였으며, 이는 보정되지 않은 위험비 0.35 및 위험 차이 −16.9%포인트에 해당합니다.
연구 결과의 방향성은 다모드 오피오이드 절감 진통법(multimodal opioid-sparing analgesia)의 이론적 근거와 일치합니다. Lin과 동료들의 위절제술 임상 시험은 카테터 기반의 국소 마취 기법에 대한 시술별 근거를 제공하며11, 다학제적 관찰 증거와 비뇨기과적 검토는 다른 환경에서도 불필요한 오피오이드 노출을 최소화해야 함을 뒷받침합니다7,8. 오피오이드 프리 마취(opioid-free anesthesia)의 근거는 오피오이드 감량이 단독 목표로 추구되기보다는 균형 잡힌 수술 전후 관리와 통합되어 이루어져야 함을 시사합니다9,10.
장내 µ-오피오이드 수용체 활성 감소는 장 기능 개선에 기여하는 타당한 요인입니다4. 주요 복부 수술 후 말초 길항제인 alvimopan의 무작위 배정 임상시험이 이러한 생물학적 근거를 뒷받침하지만, 해당 연구는 다른 약물과 수술 대상군을 평가했습니다24. 본 시험은 다모달 패키지를 비교했으므로, 개별 구성 요소를 분리하거나 오피오이드 감소를 통한 매개 효과를 입증할 수 없습니다. 수액 요법은 복강경 위절제술에서 별도로 검토되었으나, 인용된 임상시험의 제한적 전략으로는 합병증 측면에서 전반적인 이점이 입증되지 않았습니다25. 조기 경장 영양 또한 하부 위장관 수술 후 연구되었으나, 근거가 이질적이며 일반적으로 확신도가 낮았습니다26. 이러한 결과는 공동 중재 사항을 보고할 필요성을 강조하며, 본 연구에서 alvimopan 요법이나 해당 수액 또는 영양 프로토콜이 사용되었다고 가정해서는 안 됩니다.
Cine-MRI는 장의 움직임을 직접적으로 묘사함으로써 증상 기반 결과에 보완적인 정보를 제공할 수 있습니다. 이전 연구들은 정량적 소장 운동성 평가, 등록 기반 정량화 및 관찰자 기반 분석의 기술적 타당성을 입증하였습니다15,16,17. 본 연구에서 cine-MRI 측정은 선택된 공장 및 회장 분절에 집중하였으며, 시간에 따른 수술 후 운동성 변화를 특성화하는 데 사용되었습니다. 표준화된 획득 방식, 분절 선택 및 판독 절차는 향후 다기관 적용 시 재현성을 더욱 향상시킬 수 있을 것입니다.
몇 가지 제한 사항을 고려해야 합니다. 본 연구는 130명의 무작위 배정 환자를 대상으로 한 단일 센터 연구였으므로 일반화에 한계가 있을 수 있습니다. 또한, 모집 목표는 연구 시작 전에 결정되었으나, 초기 표본 크기 계산에 입력된 값들을 독립적으로 검증할 수 없었기에 초기 추정치의 재현성을 평가하는 데 제약이 있었습니다. 발생 사건 수가 적어 흔치 않은 합병증 및 재입원 결과에 대한 정밀도 또한 제한적입니다. 아울러, 칼륨 및 마그네슘 이상을 포함한 수술 전후 전해질 이상과 패혈증 관련 사건에 대한 완전한 환자 수준의 데이터를 확보하지 못해 보정 과정에 반영할 수 없었습니다. 이러한 요인들은 수술 후 위장관 기능에 독립적인 영향을 미칠 수 있으며, 잠재적인 측정되지 않은 교란 변수가 될 수 있습니다. 향후 연구에서는 수술 후 위장관 회복에 미치는 영향을 더 정확하게 평가하기 위해 전해질 상태와 감염성 합병증에 대한 표준화된 평가를 포함해야 합니다. 또한, cine-MRI 측정은 전체 위장관이 아닌 선택된 공장 및 회장 분절에서 이루어졌으며, 본 연구에는 독립적인 진단 정확도 분석이 포함되지 않았습니다. 재현성과 임상적 적용 가능성을 더욱 평가하기 위해 표준화된 cine-MRI 획득 및 분석 절차를 갖춘 대규모 다기관 연구가 필요합니다.
결론적으로, 마약성 진통제 사용을 줄인 다모달 진통법은 복강경 근치적 위절제술 후 유리한 위장관 회복, 낮은 마약성 진통제 노출 및 개선된 통증 관련 결과와 관련이 있었습니다. Cine-MRI는 수술 후 위장관 운동성에 대한 동적 정량 측정을 제공하며, 기존의 임상적 회복 지표를 보완할 수 있을 것입니다. 이러한 발견의 일반화 가능성을 확립하고 영상 기반 평가 프로토콜을 최적화하기 위해 추가적인 다기관 평가가 필요합니다.
공개 사항
저자들은 선언할 이해관계 충돌이 없습니다. 그림 작성 및 시각화를 위해 Python과 Matplotlib이 사용되었습니다. 그림을 생성하기 위한 코드 개발 과정에서 AI 보조 코드 지원 도구가 사용되었습니다. 생성된 모든 그림은 저자들에 의해 검토 및 검증되었으며, 저자들은 제시된 내용의 정확성과 무결성에 대해 모든 책임을 집니다.
저자 기여도:
Yijun Liu: 개념화, 방법론, 조사, 데이터 큐레이션, 초안 작성. Xinjuan Tan: 조사, 데이터 큐레이션, 시각화. Jian Mo: 방법론, 정식 분석, 시각화. Danchun Chen: 조사, 자원, 프로젝트 관리. Guixi Mo: 개념화, 감독, 프로젝트 관리, 검토 및 편집 작성. 모든 저자는 최종 원고를 검토하고 승인하였습니다.
감사의 글
본 임상 시험 기간 동안 매우 귀중한 도움을 주신 참여 환자분들과 마취과 의료진분들께 깊은 감사를 표합니다. 또한, cine-MRI 평가와 지속적인 모니터링에 기술적 지원을 제공해 주신 방사선과 팀에 특별한 감사를 전합니다. 본 연구는 광동현대병원관리연구소(Guangdong Institute of Modern Hospital Management) 2025-2026년도 연례 특별 연구 프로젝트(프로젝트 번호: GDXDYGS2025037)의 관대한 지원을 받아 수행되었습니다. 본 연구의 성공적인 실행과 시각화된 수술 후 평가의 발전을 가능하게 한 재정적 지원에 깊이 감사드립니다.
재료
| 이름 | 회사 | 카탈로그 번호 | 댓글 |
|---|---|---|---|
| 3.0 T MRI 스캐너 | Siemens Healthineers, Erlangen, Germany | MAGNETOM Skyra 3.0 T | 24, 48, 72시간에 Cine-MRI 측정; 2D balanced steady-state free-precession 시퀀스: TR 3.4 ms, TE 1.2 ms, flip angle 75°, slice thickness 8–10 mm, matrix 256 × 256, FOV 400–450 mm, 시간 분해능 0.3 s/frame, 30초 간격의 3회 획득, 호흡 동기화 적용. |
| 정맥 투여용 아세트아미노펜 | B. Braun Medical, Germany | Paracetamol (acetaminophen) solution for infusion; 카탈로그/배치 번호 미보고 | 마약성 진통제 절감 진통 요법에 사용된 정맥 투여 비마약성 진통제. |
| 이상반응 공통 용어 기준 (CTCAE) | 해당 없음 | Version 5.0 | 이상반응 등급 분류 체계. |
| 덱사메타손 | Fresenius Kabi, Germany | Dexamethasone sodium phosphate injection; 카탈로그/배치 번호 미보고 | 복벽 차단술을 위해 로피바카인과 함께 보조제로 사용. |
| 덱스메데토미딘 | Jiangsu Hengrui Medicine Co., Ltd., China | Dexmedetomidine hydrochloride injection; 카탈로그/배치 번호 미보고 | 마약성 진통제 절감 진통 요법에 사용된 정맥 투여 보조제. |
| 플루르비프로펜 악세틸 | Jiangsu Hengrui Medicine Co., Ltd., China | Flurbiprofen axetil injection; 카탈로그/배치 번호 미보고 | 배정된 진통 요법에도 불구하고 수술 후 통증이 적절히 조절되지 않을 때 사용된 구제 진통제. |
| I-FEED 평가 도구 | 해당 없음 | 양식/버전 미보고 | 수술 후 위장관 기능을 평가하기 위해 기술된 도구. |
| MATLAB 기반 자체 제작 Cine-MRI 분석 소프트웨어 | MathWorks, Natick, MA, USA | MATLAB R2023a | 두 명의 독립적인 판독자가 공장 및 회장의 Cine-MRI 분석(수축 빈도, 수축 진폭 및 운동성 등급 포함)에 사용. |
| 모르핀 | Northeast Pharmaceutical Group Shenyang No. 1 Pharmaceutical Co., Ltd., China | Morphine hydrochloride injection; 카탈로그/배치 번호 미보고 | 전통적인 환자 조절 정맥 진통 요법의 옵션으로 지정된 마약성 진통제. |
| 숫자 등급 척도 (NRS) | 해당 없음 | 양식/언어 미보고 | 2, 6, 12, 24, 48, 72시간에서의 안정 시 및 움직임 시 통증 평가. |
| PASS | NCSS, LLC | 15 | 표본 크기 계산에 사용된 소프트웨어. |
| 환자 조절 정맥 진통 펌프 | WOO YOUNG MEDICAL Co., Ltd., Republic of Korea | 현재 기록에 모델 정보 없음 | 전통적인 수술 후 마약성 진통제 투여에 사용. |
| 폴리에틸렌 글리콜 (macrogol 4000) 경구 제제 | Beaufour Ipsen Industrie, France | Forlax/macrogol 4000 oral powder for oral solution | 장 확장 준비물로 사용; Cine-MRI 획득 약 60분 전에 1 L 경구 용액 투여. |
| 휴대용 지속 주입 펌프 | Smiths Medical, USA | 현재 기록에 모델 정보 없음 | 마약성 진통제 절감군에서 수술 후 주입 기반 진통 요법에 사용. |
| 회복 질 Quality of Recovery-15 (QoR-15) 설문지 | 해당 없음 | 버전/언어 미보고 | 수술 후 1, 2, 3, 7일차의 회복 질 평가. |
| 로피바카인 | AstraZeneca, Sweden | Ropivacaine hydrochloride injection; 카탈로그/배치 번호 미보고 | 복횡근면 및 복직근초 차단술에 사용된 0.2% 로피바카인. |
| SPSS | IBM | 26 | 통계 분석에 사용된 소프트웨어. |
| 수펜타닐 | Yichang Humanwell Pharmaceutical Co., Ltd., China | Sufentanil citrate injection; 카탈로그/배치 번호 미보고 | 전통적인 환자 조절 정맥 진통 요법에 사용된 마약성 진통제. |
| 초음파 시스템 | Shenzhen Mindray Bio-Medical Electronics Co., Ltd., Shenzhen, China | 고주파 선형 프로브가 장착된 M9 초음파 시스템 | 양측 복횡근면 및 복직근초 차단술 유도에 사용. |
참고문헌
- Vather R, Trivedi S, Bissett I. Defining postoperative ileus: results of a systematic review and global survey. J Gastrointest Surg. 2013;17(5):962–72.
- Hedrick TL et al. American Society for Enhanced Recovery and Perioperative Quality Initiative Joint Consensus Statement on Postoperative Gastrointestinal Dysfunction Within an Enhanced Recovery Pathway for Elective Colorectal Surgery. Anesth Analg. 2018;126(6):1896–907.
- Vather R, O'Grady G, Bissett IP, Dinning PG. Postoperative ileus: mechanisms and future directions for research. Clin Exp Pharmacol Physiol. 2014;41(5):358–70.
- Bauer AJ, Boeckxstaens GE. Mechanisms of postoperative ileus. Neurogastroenterol Motil. 2004;16(Suppl 2):54–60.
- Mortensen K et al. Consensus guidelines for enhanced recovery after gastrectomy: Enhanced Recovery After Surgery (ERAS®) Society recommendations. Br J Surg. 2014;101(10):1209–29.
- Kang SH et al. Multimodal Enhanced Recovery After Surgery (ERAS) Program is the Optimal Perioperative Care in Patients Undergoing Totally Laparoscopic Distal Gastrectomy for Gastric Cancer: A Prospective, Randomized, Clinical Trial. Ann Surg Oncol. 2018;25(11):3231–8.
- Collaborative T. Impact of opioid-free analgesia on pain severity and patient satisfaction after discharge from surgery: multispecialty, prospective cohort study in 25 countries. Br J Surg. 2024;111(1):znad421.
- Samenezhad S, Rafighi D. Opioid-sparing pain management in urologic surgery: A comprehensive narrative review of ERAS protocols and multimodal strategies. Perioper Care Oper Room Manag. 2026;42:100609.
- Beloeil H et al. Balanced Opioid-free Anesthesia with Dexmedetomidine versus Balanced Anesthesia with Remifentanil for Major or Intermediate Noncardiac Surgery. Anesthesiology. 2021;134(4):541–51.
- Salomé A, Harkouk H, Fletcher D, Martinez V. Opioid-Free Anesthesia Benefit-Risk Balance: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. J Clin Med. 2021;10(10):2069.
- Lin Z, Chen Z, Li Y. Analgesic efficacy of an opioid-free postoperative pain management strategy versus a conventional opioid-based strategy following laparoscopic radical gastrectomy: an open-label, randomized, controlled, non-inferiority trial. World J Surg Oncol. 2024;22:54.
- Wu Y et al. The analgesic efficacy of subcostal transversus abdominis plane block compared with thoracic epidural analgesia and intravenous opioid analgesia after radical gastrectomy. Anesth Analg. 2013;117(2):507–13.
- Chen Q et al. Intertransverse process block versus subcostal transversus abdominis plane block in patients undergoing laparoscopic radical gastrectomy: a prospective randomized controlled trial. BMC Anesthesiol. 2025;25:9.
- Chin KJ et al. Essentials of Our Current Understanding: Abdominal Wall Blocks. Reg Anesth Pain Med. 2017;42(2):133–83.
- Choi JY et al. Technical Feasibility of Quantitative Measurement of Various Degrees of Small Bowel Motility Using Cine Magnetic Resonance Imaging. Korean J Radiol. 2023;24(11):1093–101.
- Odille F et al. Quantitative assessment of small bowel motility by nonrigid registration of dynamic MR images. Magn Reson Med. 2012;68(3):783–93.
- Hameed M et al. Inter- and intra-observer variability of software quantified bowel motility measurements of small bowel Crohn's disease: findings from the MOTILITY trial. Insights Imaging. 2025;16:111.
- Patak MA et al. Non-invasive measurement of small-bowel motility by MRI after abdominal surgery. Gut. 2007;56(7):1023–5.
- Alsharqawi N et al. Validity of the I-FEED score for postoperative gastrointestinal function in patients undergoing colorectal surgery. Surg Endosc. 2020;34(5):2219–26.
- Hjermstad MJ et al. Studies comparing Numerical Rating Scales, Verbal Rating Scales, and Visual Analogue Scales for assessment of pain intensity in adults: a systematic literature review. J Pain Symptom Manage. 2011;41(6):1073–93.
- Stark PA, Myles PS, Burke JA. Development and psychometric evaluation of a postoperative quality of recovery score: the QoR-15. Anesthesiology. 2013;118(6):1332–40.
- Myles PS, Myles DB. An Updated Minimal Clinically Important Difference for the QoR-15 Scale. Anesthesiology. 2021;135(5):934–5.
- Dowell D, Ragan KR, Jones CM, Baldwin GT, Chou R. CDC Clinical Practice Guideline for Prescribing Opioids for Pain—United States, 2022. MMWR Recommendations and Reports. 2022;71(3):1–95.
- Wolff BG et al. Alvimopan, a novel, peripherally acting mu opioid antagonist: results of a multicenter, randomized, double-blind, placebo-controlled, phase III trial of major abdominal surgery and postoperative ileus. Ann Surg. 2004;240(4):728–35.
- Kusaka Y, Ueno T, Minami T. Effect of restrictive versus liberal fluid therapy for laparoscopic gastric surgery on postoperative complications: a randomized controlled trial. J Anesth. 2025;39(1):101–10.
- Herbert G et al. Early enteral nutrition within 24 hours of lower gastrointestinal surgery versus later commencement for length of hospital stay and postoperative complications. Cochrane Database Syst Rev. 2019;7:CD004080.