본 리뷰에서는 미세환경 조절, 자극 반응성, 면역 공학, 3D/4D 프린팅, 인공지능 기반 설계 및 개인 맞춤형 골 수복의 중개적 과제에 중점을 두고, 골 재생을 위한 스마트 생체 재료 전략을 요약합니다.
이 논문에서
요약
초록
스마트 생체재료의 급격한 발전은 복합 골 결손, 불유합 골절 및 종양 절제 후 재건을 위한 새로운 치료 경로를 열어주었습니다. 기존의 골 대체재는 흔히 불충분한 생체 활성, 기계적 불일치, 치유 미세환경 조절 능력의 부족이라는 문제점을 가지고 있습니다. 이와 대조적으로, 스마트 생체재료는 외부 자극(빛, 전기, 자기장 또는 기계적 힘)이나 내부 신호(ROS, pH 또는 효소 활성)에 반응하여 물리화학적 특성을 동적으로 조정할 수 있어, 세포 행동과 국소 미세환경 역학을 정밀하게 제어할 수 있게 합니다. 면역 공학 재료, 특히 대식세포를 재생 촉진형 M2 표현형으로 분극화하도록 설계된 재료의 최근 발전은 염증을 완화하고 골 형성을 가속화하는 데 유망한 가능성을 보여주었습니다. 동시에 3D/4D 프린팅 기술은 스캐폴드 구조, 분해 프로파일 및 생체 활성 인자의 공간적 분포에 대한 프로그래밍 가능한 제어를 가능하게 하여 개인 맞춤형 치료 전략을 지원합니다. 인공지능 기반의 재료 발견 및 구조 최적화는 차세대 고성능 골 재생 생체재료의 설계 범위를 더욱 확장하고 있습니다. 본 리뷰는 자극 반응 메커니즘, 면역 조절 전략, 첨단 제조 기술 및 AI 기반 설계에 중점을 두고 골 재생을 위한 스마트 생체재료의 최근 진척 상황을 종합적으로 합성하여 제공하며, 임상 적용을 위한 주요 장벽과 향후 방향을 제시합니다. 본 리뷰에서 스마트 생체재료(smart biomaterial)는 포괄적인 용어로 사용되며, 자극 반응형 생체재료(stimulus-responsive biomaterial)는 외부 트리거(빛, 자기, 전기, 기계적 자극, pH, ROS 또는 효소)에 반응하는 하위 분류를 나타내고, 지능형 생체재료(intelligent biomaterial)는 스마트 생체재료와 동의어로 취급됩니다. 이 용어들은 서로 무분별하게 혼용되어 사용되지 않습니다.
서론
거대 골 결손, 골절 불유합 및 종양 절제 후 재건은 정형외과 분야에서 가장 까다로운 과제 중 하나로 남아 있으며, 전 세계적으로 상당한 이환율과 장애를 초래하고 있습니다1,2. 자가이식, 동종이식, 금속 임플란트 및 기존 생체 세라믹을 포함한 전통적인 치료법이 임상적 결과를 어느 정도 개선했으나, 공여 부위의 부족, 면역 거부 반응, 감염 위험, 불충분한 생체 활성 및 복잡한 재생 미세환경을 조절하는 능력의 한계라는 제약이 여전히 존재합니다3,4,5. 이러한 한계는 광범위한 분절 결손, 염증 관련 골 손실 및 환자 맞춤형 구조 재건이 필요한 상황에서 특히 두드러지며, 이 경우 기존 재료로는 정밀한 복구와 기능적 재생 요구를 더 이상 충족시킬 수 없습니다6.
골 조직 공학의 급격한 발전은 스마트 생체 재료의 등장을 촉진했습니다. 정적인 재료와 달리, 스마트 생체 재료는 빛, 전기장 또는 자기장, 기계적 힘과 같은 외부 자극이나 활성 산소(ROS), 산성 pH, 또는 비정상적인 효소 활성을 포함한 내부 병리적 신호에 반응하여 물리화학적 특성을 동적으로 조정할 수 있습니다3,7,8,9,10. 이러한 반응성은 세포 행동, 염증 연쇄 반응 및 재생 과정을 정밀하게 조절할 수 있게 합니다. 이와 병행하여, 면역 공학의 부상은 대식세포 분극, T-세포 기능 및 사이토카인 네트워크를 조절할 수 있는 재료를 도입함으로써, 염증, 수복 및 리모델링의 단계별 조절을 가능하게 하여 골 치유를 현저히 향상시켰습니다4,11. 3D/4D 프린팅의 발전은 스캐폴드 구조, 기계적 특성, 생성 활성 인자의 공간적 분포, 그리고 동적인 형상 변형까지 맞춤형 제어를 가능하게 하여 고도로 개인화된 치료 전략을 지원합니다11,12,13. 또한, 재료 스크리닝, 구조 최적화 및 개별 디자인에 인공지능(AI)을 통합함으로써 차세대 스마트 골 재생 생체 재료의 개발 주기가 가속화되고 있습니다14 (그림 1).
전임상 및 동물 연구에서의 이러한 유망한 발전에도 불구하고, 임상 적용으로 나아가는 데에는 여전히 상당한 장벽이 존재합니다. 여기에는 생체 내 다중 자극 반응의 내재적 복잡성, 재료의 분해 역학과 골 재생의 시간적 순서 간의 불일치, 면역 조절 기능의 불안정성, 대량 생산의 어려움 및 표준화된 규제 프레임워크의 부재 등이 포함됩니다15. 따라서 기초 원리를 명확히 하고 중개 연구의 진전을 안내하기 위해서는 현재의 설계 전략, 자극 반응 메커니즘, 면역 조절 접근법 및 첨단 제조 기술에 대한 체계적인 종합 분석이 필수적입니다.
이러한 고려 사항을 바탕으로, 본 연구진은 스마트 생체 재료의 설계가 치유 과정 전반에 걸쳐 단일한 정적 기능을 제공하기보다는 염증, 수복, 재형성이라는 골 손상 치유의 세 가지 연속적인 단계와 일치해야 한다고 제안합니다. 따라서 본 논의는 주로 다음과 같은 몇 가지 측면에 초점을 맞춥니다: (i) 골 치유의 각 단계별 생물학적 요구 사항 및 스마트 생체 재료의 관련 설계 원칙; (ii) 필요에 따라 활성화될 수 있는 핵심 화학 반응 및 물리적 신호; (iii) 맞춤형 응용을 지원하는 제조 및 계산 플랫폼(3D/4D 프린팅, AI 보조 설계, 장기 칩); 그리고 (iv) 적용 전 극복해야 할 임상 전환 장벽입니다. 화학적 조성이나 응용 분야에 따라 재료를 분류한 최근의 리뷰 논문들과 달리, 본 리뷰는 치유 단계에 맞춘 설계 프레임워크를 특징으로 하며, in vitro 연구부터 대동물 시험 및 임상 연구에 이르기까지 각 재료 유형에 대한 증거 수준을 명확하게 비교합니다.
리뷰 및 관점
Biological basis of bone healing and microenvironmental regulation
Bone healing is a highly coordinated regenerative process that proceeds through overlapping phases of inflammation, tissue repair, and remodeling. These phases are not independent events but a continuous biological program controlled by immune cells, osteogenic cells, vascular cells, extracellular matrix components, and local biochemical and mechanical cues16,17. In the early inflammatory phase, tissue injury initiates hematoma formation and rapid recruitment of neutrophils and macrophages. These cells remove necrotic tissue and release inflammatory mediators, including tumor necrosis factor, interleukin-1, and interleukin-6, which help initiate vascular ingrowth and recruit osteoprogenitor cells to the defect site18,19,20. This early inflammatory response is necessary for repair initiation, but its duration and intensity must be tightly controlled. Excessive or persistent inflammation can impair osteogenic differentiation, delay angiogenesis, and contribute to non-union or defective regeneration (Figure 2).
As inflammation resolves, bone repair enters a reparative phase characterized by the coordinated activity of chondrocytes, fibroblasts, osteoblasts, mesenchymal stem cells, and endothelial cells. During this phase, cartilaginous callus formation, extracellular matrix deposition, angiogenesis, and mineralization progressively bridge the defect and establish a structural template for new bone formation16,21. Growth factors such as bone morphogenetic proteins and vascular endothelial growth factor are central to this process because they support osteogenic commitment and neovascularization22,23. The final remodeling phase involves the replacement of immature repair tissue with mature bone through balanced osteoblast-mediated matrix formation and osteoclast-mediated resorption17,24. This stage may continue for months or years and is essential for restoring bone architecture and mechanical strength.
The immune microenvironment is increasingly recognized as a major determinant of bone-regeneration quality. Macrophages are particularly important because their phenotype changes dynamically during healing. M1-like macrophages support early defense, debris clearance, and inflammatory signaling, whereas M2-like macrophages promote inflammation resolution, angiogenesis, osteogenic differentiation, and tissue remodeling25,26,27. T lymphocytes also contribute to this process. Regulatory T cells can suppress excessive immune activation and establish a permissive regenerative environment, while CD4⁺ and CD8⁺ T cells influence macrophage activity, vascular formation, and bone metabolism28,29,30. Therefore, successful bone repair depends not only on osteogenic stimulation but also on coordinated immune regulation.
Smart biomaterials are uniquely positioned to interact with this complex microenvironment. Unlike passive scaffolds, which primarily provide structural support, smart biomaterials can be designed to regulate surface chemistry, topography, stiffness, porosity, degradation behavior, and bioactive factor delivery in response to the biological needs of the defect site. Surface functional groups, wettability, and nano-/micro-scale architecture can influence macrophage recognition, adhesion, spreading, and polarization, thereby promoting a transition from prolonged inflammation toward a pro-regenerative immune state31,32. Meanwhile, matrix stiffness, elastic modulus, pore architecture, and spatial biochemical gradients can modulate mesenchymal stem cell adhesion, migration, and osteogenic differentiation33,34. Interconnected pore networks further support vascular invasion, nutrient diffusion, and trabecular bone penetration35. Thus, the central principle of smart biomaterial design is to align material properties with the temporal and spatial requirements of bone healing.
The biological events described above impose explicit, time-resolved design constraints on smart biomaterials. First, the inflammatory phase demands that biomaterials minimize foreign-body response and actively resolve inflammation, which has motivated the incorporation of ROS scavengers (e.g., ceria nanoparticles, TEMPO-conjugated hydrogels), pH-responsive anti-inflammatory release (e.g., Schiff-base linkers cleaved at pH 5.5–6.5 in the acidic wound microenvironment), and immunomodulatory surface chemistries that bias macrophage recruitment toward a pro-resolving phenotype. Second, the reparative phase requires sustained and spatially patterned delivery of osteogenic and angiogenic cues, leading to the development of growth-factor-loaded microspheres, affinity-based release systems (e.g., heparin-binding peptides for BMP-2), and electrostatically patterned substrates that guide MSC alignment. Third, the remodeling phase requires mechanical compatibility with host bone and on-demand degradation, motivating the development of stiff-to-soft dynamic hydrogels, mineral-coated scaffolds, and stress-adaptive 4D-printed geometries. Importantly, these three design rules are not independent: a material that resolves inflammation early will not be effective in the reparative phase if it has already degraded. This temporal coupling is the central design challenge that motivates the smart biomaterial concept and that distinguishes this review from static biomaterial surveys.
A further design consideration is the patient-specific variability in healing trajectories, driven by age, sex, comorbidities (osteoporosis, diabetes, smoking), genetic polymorphisms in BMP and VEGF pathways, and defect geometry. This variability is the rationale for the personalized, closed-loop biomaterial systems discussed in the Emerging technologies and clinical translation section, in which real-time monitoring of healing biomarkers (e.g., pH, temperature, enzymatic activity) triggers on-demand release of growth factors or adapts mechanical properties.
Finally, the design rules derived from biology must be explicitly compared against the evidence base for each material class. The following sections, therefore, adopt a design rule → material example → evidence level (in vitro/small animal/large animal/clinical) structure throughout, addressing a key gap in current smart-biomaterial reviews.
Stimulus-responsive smart biomaterials for bone regeneration
Stimulus-responsive biomaterials represent a major class of smart biomaterials because they can convert external physical cues or endogenous pathological signals into programmable material responses. These responses may include changes in degradation rate, mechanical properties, surface characteristics, drug release, growth-factor presentation, or cellular interactions3,15,36,37 (Figure 3). In bone regeneration, this property is particularly valuable because the defect microenvironment changes substantially over time. Early inflammatory lesions may contain excessive reactive oxygen species, acidic pH, and proteolytic enzymes, whereas later repair stages require angiogenesis, osteogenic differentiation, mineral deposition, and mechanical remodeling. Stimulus-responsive materials can therefore provide phase-adapted regulation rather than static support.
Externally responsive biomaterials are activated by applied physical stimuli, including light, electrical stimulation, magnetic fields, ultrasound, mechanical loading, and piezoelectric signals. Light-responsive systems, especially near-infrared-responsive materials, have received considerable attention because near-infrared light can trigger photothermal conversion, photochemical reactions, and controlled release of therapeutic molecules38,39,40. In bone defects complicated by tumor resection or infection, photothermal materials may provide dual functions: local tumor ablation or antibacterial activity, followed by promotion of bone repair15,40. However, this strategy also faces translational challenges. Light penetration is limited in deep tissues, thermal dose must be carefully controlled to avoid collateral damage, and clinical implementation requires integration of optical devices into surgical or postoperative workflows41. Therefore, light-responsive systems may be most suitable for superficial, surgically exposed, or device-accessible defects.
Electrical and piezoelectric biomaterials are inspired by the natural electromechanical properties of bone. Bone is a mechanosensitive tissue, and mechanical loading can generate bioelectrical signals that influence bone remodeling and mass maintenance42. Conductive polymers, carbon-based nanomaterials, and electrically active scaffolds can modulate cell membrane potential, intracellular signaling, osteogenic differentiation, and mineralization43,44,45. Piezoelectric biomaterials further bridge mechanical and electrical regulation by converting deformation into localized electrical stimulation46,47. This is highly relevant for load-bearing defects, where physiological movement and mechanical stress are part of the healing environment. By integrating mechanical support with bioelectrical regulation, these materials may enhance osteogenesis without relying entirely on soluble growth factors. Nevertheless, stimulation intensity, duration, device compatibility, and long-term safety require careful optimization before clinical translation.
Magnetic-responsive biomaterials offer another route for remote, spatially controlled regulation. By incorporating magnetic nanoparticles, such as iron oxide-based components, scaffolds, or hydrogels can respond to external magnetic fields, enabling guided drug delivery, enhanced cell recruitment, improved angiogenesis, and osteogenic stimulation43,48. Compared with light-responsive systems, magnetic stimulation may offer deeper tissue penetration and noninvasive remote control. However, the dose, distribution, degradation, and long-term retention of magnetic particles must be evaluated thoroughly. Mechanically responsive materials are also highly relevant to bone repair. By tuning stiffness, elasticity, pore geometry, and surface architecture, these systems can mimic the mechanical microenvironment of native bone and activate mechanotransduction pathways involved in osteogenic differentiation45,49. Together, externally responsive materials provide high temporal controllability, but their success depends on safe stimulation parameters, device integration, reproducibility, and patient compliance.
Internally responsive biomaterials are activated by pathological or regenerative signals within the local microenvironment. Reactive oxygen species-responsive materials are particularly important because excessive oxidative stress is common in chronic inflammation, osteoporosis, tumor-associated bone defects, and impaired healing50,51. Persistent reactive oxygen species accumulation damages cells, disrupts osteogenic signaling, and disturbs the balance between bone formation and resorption. By incorporating oxidation-labile linkages, reactive oxygen species-degradable crosslinkers, or antioxidant-loaded nanostructures, these materials can selectively degrade or release therapeutic agents in oxidative environments52,53. Reactive oxygen species-responsive hydrogels and nanoparticles have shown potential for reducing inflammation, restoring osteogenic signaling, and enhancing osteoblast activity54.
pH-responsive biomaterials are designed to exploit acidic microenvironments in inflammatory, infectious, or tumor-associated bone lesions. Inorganic components, calcium phosphate systems, polymer networks, and hydrogels can be engineered to dissolve, swell, or release drugs preferentially under mildly acidic conditions55,56,57,58. This allows localized delivery of antibacterial agents, antitumor drugs, antioxidants, growth factors, or osteogenic molecules while limiting unnecessary release in healthy tissues. Enzyme-responsive biomaterials target elevated proteolytic activity, particularly matrix metalloproteinases, which are involved in extracellular matrix remodeling and tissue repair. By incorporating enzyme-cleavable crosslinkers or peptide sequences, hydrogels and scaffolds can release osteogenic or immunomodulatory factors on demand while maintaining structural support during early healing59,60,61. Compared with externally responsive systems, internally responsive materials resemble closed-loop platforms because they are activated by disease- or repair-associated cues. However, microenvironmental heterogeneity, patient-to-patient variability, insufficient stimulus intensity, and long-term stability remain major obstacles10,62. Major stimulus-responsive biomaterial strategies discussed above are summarized in Table 1.
Immunoengineering strategies for bone regeneration
Immunoengineering has become a central strategy in the design of smart biomaterials because the immune system actively regulates every stage of bone healing. The goal of immunoengineered biomaterials is not simply to suppress inflammation but to guide immune responses in a stage-specific manner. A well-designed immunomodulatory scaffold should permit early protective inflammation, prevent chronic inflammatory damage, promote the transition to tissue repair, and support osteogenesis and angiogenesis4,63. This concept is particularly important for large defects, infection-associated defects, aging-related impaired healing, and inflammatory bone loss, where immune dysregulation often compromises regeneration.
Macrophages are the most widely studied immune targets in bone-regenerative biomaterials. During the early phase of repair, M1-like macrophages secrete pro-inflammatory cytokines, including tumor necrosis factor-α, interleukin-1, and interleukin-6. These cytokines contribute to pathogen clearance, necrotic tissue removal, and recruitment of reparative cells64,65,66. However, persistent M1-like activation may amplify inflammation, inhibit osteogenic differentiation, and impair vascularization. As healing progresses, macrophages normally shift toward an M2-like reparative phenotype, characterized by secretion of interleukin-10, transforming growth factor-β, vascular endothelial growth factor, and bone morphogenetic proteins63,67,68. These mediators support inflammation resolution, matrix reconstruction, angiogenesis, and new bone formation. Timely and appropriately scaled M2-like polarization is therefore a key determinant of successful repair, whereas prolonged M1 dominance is associated with delayed healing and non-union69,70,71. Smart biomaterials can influence macrophage behavior through multiple material-level cues. Surface charge, functional group density, wettability, stiffness, roughness, and nano-/micro-topography can affect macrophage adhesion, morphology, spreading, and activation state68,72,73. For example, specific surface architectures may reduce excessive inflammatory activation while promoting a pro-repair phenotype. In addition, biomaterials can be engineered to deliver immunomodulatory molecules such as interleukin-4, interleukin-13, microRNAs, or other bioactive agents that reinforce M2-like polarization74. These strategies allow biomaterials to act as immune-instructive platforms rather than inert implants.
Cytokine and chemokine regulation further expands the potential of immunoengineered biomaterials. Bone healing requires dynamic cytokine changes: early pro-inflammatory signaling initiates repair, whereas later anti-inflammatory and pro-regenerative signaling support tissue formation69,70,71. Controlled release of interleukin-4 or interleukin-13 can reduce persistent inflammation and promote macrophage transition toward a reparative phenotype74. Sequential release of transforming growth factor-β, vascular endothelial growth factor, and bone morphogenetic proteins can coordinate matrix reconstruction, angiogenesis, and osteogenesis75,76. This temporally programmed approach may be superior to continuous single-factor release because it better reflects the physiological sequence of bone healing.
Chemokines are also valuable for recruiting immune and progenitor cells to the defect site. Monocyte chemoattractant protein-1 can attract macrophages and mesenchymal progenitor cells through CCR2-mediated signaling, thereby supporting early immune modulation and repair initiation77,78. C-X-C motif chemokine ligand 12 can promote stem cell homing and provide a sustained cell source for osteogenesis79,80. By creating spatial chemokine gradients, biomaterials can actively organize cellular recruitment instead of relying on passive cell infiltration. Nevertheless, immune modulation must be carefully balanced. Excessive suppression of early inflammation may impair clearance of damaged tissue, whereas uncontrolled chemokine release may prolong immune infiltration. Similarly, excessive or poorly timed M2-like polarization may compromise immune surveillance. Therefore, next-generation immunoengineered biomaterials should pursue dynamic, reversible, and multitarget immune regulation, integrating macrophage modulation, stem-cell recruitment, angiogenesis, and osteogenic stimulation in a coordinated framework81,82.
Recent osteoimmunology research has substantially revised the classical M1/M2 paradigm. Macrophage phenotypes are now understood to exist on a continuum rather than as discrete M1/M2 states, and single-cell transcriptomic studies of fracture callus have identified at least 5–7 transcriptionally distinct macrophage subpopulations that emerge and resolve at different times during healing. Among these, osteomacs—tissue-resident macrophages lining bone surfaces—play non-redundant roles in osteoblast maintenance and have been proposed as a distinct target for biomaterial-based immunomodulation.
Beyond macrophages, the immune response during bone healing involves coordinated activity of neutrophils, dendritic cells, T cells, and osteoclasts. Neutrophil extracellular traps (NETs) in early inflammation, when dysregulated, delay the M1→M2 transition. Dendritic cells bridge innate and adaptive immunity and modulate mesenchymal stem cell (MSC) recruitment. T cells, particularly Tregs, promote bone formation via IL-10 and CTLA-4 signaling, whereas Th17 cells can be pro-osteoclastogenic. The temporal heterogeneity of these populations argues for stage-specific, not generic, immunomodulatory design.
Although the M1→M2 transition is widely viewed as beneficial, recent evidence indicates that excessive or prolonged M2-like polarization can impair bone regeneration. M2 macrophages secrete TGF-β, IL-10, and PDGF, which, at sustained high levels, have been associated with heterotopic ossification, marrow adipogenesis, and fibrous encapsulation rather than functional bone integration. This underscores the need for time-limited immunomodulation, in which the biomaterial actively resolves inflammation during the first 7–10 days and then ceases to drive M2 polarization, allowing the natural transition to remodeling. We suggest that future smart biomaterials should incorporate built-in off-switches (e.g., enzymatically degradable immunomodulatory motifs) that prevent sustained M2 polarization beyond the reparative phase. The immunoengineering strategies discussed in this section are summarized in Table 2.
3D/4D printing and personalized bone repair
Personalized bone regeneration requires biomaterials that match not only biological needs but also the anatomical and mechanical characteristics of individual defects. Three-dimensional printing has become a powerful tool for this purpose because it allows patient-specific scaffold design based on clinical imaging, digital reconstruction, and precise additive manufacturing83,84,85,86. Computed tomography and magnetic resonance imaging can be used to reconstruct the geometry, curvature, volume, and load-bearing requirements of a bone defect. These data can then guide the fabrication of scaffolds that fit irregular anatomical structures and provide appropriate mechanical support85,86,87. This is particularly important for mandibular reconstruction, segmental long-bone defects, craniofacial repair, and post-tumor resection defects, where anatomical precision strongly influences functional outcomes.
At the microscale, 3D printing enables control over pore size, porosity, pore interconnectivity, and internal architecture. These parameters are critical for cell migration, vascular invasion, nutrient diffusion, waste removal, and new bone deposition88. Gradient structures can mimic the heterogeneous architecture of native bone, balancing dense regions for mechanical support with porous regions for biological integration89,90. Biodegradable printed scaffolds may further reduce long-term complications associated with permanent metallic implants, including stress shielding, chronic inflammation, and the need for secondary removal91,92. Thus, 3D printing provides a platform for integrating structural precision with biological function.
Another important advantage of 3D printing is spatial control over biomolecules, cells, and material composition. Growth factors such as bone morphogenetic proteins and vascular endothelial growth factor can be incorporated into predefined regions of a scaffold to create functional zones that promote osteogenesis and angiogenesis in a coordinated manner91,93. This strategy is especially valuable because bone regeneration requires simultaneous vascularization and mineralization. Spatially organized delivery can direct different cell behaviors in different regions of the scaffold, resembling the cortical-trabecular organization of native bone. In addition, 3D printing allows integration of multiple materials with different degradation rates, stiffness values, or bioactive functions, creating scaffolds that are both mechanically supportive and biologically instructive94.
Four-dimensional printing builds on 3D printing by introducing time-dependent changes in structure or function. Using shape-memory polymers or stimuli-responsive materials, 4D-printed constructs can change their configuration, stiffness, porosity, degradation behavior, or release kinetics in response to environmental cues such as temperature, pH, ions, hydration, or body fluids83,86,95. This dynamic responsiveness may be especially useful for irregular defects, minimally invasive implantation, and staged bone healing. For example, a compact scaffold could be implanted through a smaller surgical window and then expand or conform to the defect geometry in situ. Similarly, a 4D-printed scaffold could adjust its release behavior as the microenvironment transitions from an inflammatory to a reparative phase83,96. However, 4D printing remains less clinically mature than 3D printing. Long-term shape stability, predictable response behavior, scalable manufacturing, sterilization, mechanical reliability, and biosafety must be rigorously evaluated before broad clinical translation83,84,97.
Emerging technologies and clinical translation
The future development of smart biomaterials is increasingly linked to artificial intelligence, organoid systems, bone-on-a-chip models, and real-time monitoring technologies. Artificial intelligence, especially machine learning and deep learning, can accelerate biomaterial discovery by analyzing large datasets that connect material composition, structure, mechanical properties, degradation behavior, and biological outcomes98,99. Instead of relying solely on trial-and-error experimentation, machine-learning models can predict candidate materials with favorable biocompatibility, osteogenic potential, immune-regulatory capacity, and mechanical performance. Artificial intelligence can also support scaffold optimization by integrating clinical variables such as defect type, patient age, comorbidities, imaging features, and expected mechanical loading100,101,102. This may allow the field to move from generalized scaffold design toward individualized material selection (Figure 4).
Organoid and bone-on-a-chip technologies provide more physiologically relevant platforms for evaluating smart biomaterials. Traditional two-dimensional cultures cannot fully reproduce cell-cell interactions, three-dimensional architecture, vascular-like networks, immune regulation, or dynamic mechanical and biochemical gradients. Bone organoids and microfluidic bone-on-a-chip systems can better model osteogenesis, angiogenesis, immune-cell interactions, and material-tissue responses under controlled conditions103,104. These systems may be particularly useful for screening biomaterial formulations, testing drug or growth-factor combinations, and reducing reliance on early animal experiments. Their high-throughput potential could accelerate optimization of complex smart biomaterial systems102.
Despite encouraging preclinical results, only a small fraction of smart biomaterials have reached late-stage clinical trials or commercialization. Table 3 summarizes the current translational landscape, listing representative technologies, their highest preclinical evidence level, clinical trial status (if any), and major remaining challenges. Two patterns emerge: (i) mechanical and electrical stimulation are the only strategies with regulatory approval (e.g., FDA-cleared low-intensity pulsed ultrasound (LIPUS) devices, FDA-cleared PEMF devices), whereas responsive chemistries (pH-, ROS-, enzyme-triggered) remain largely at the small-animal stage; (ii) multifunctional combination products (e.g., BMP-releasing 3D-printed scaffolds) face the highest regulatory and manufacturing barriers due to the complexity of combination-product approval pathways.
Across all seven stimulus-responsive strategies discussed in 'Stimulus-responsive smart biomaterials for bone regeneration', we estimate that >70% of publications report only in vitro (EL-1) or small-animal (EL-2, rodent critical-size defect <5 mm) data, fewer than 15% include large-animal validation (EL-3, rabbit/dog/sheep/pig defect ≥5 mm), and only a handful have advanced to registered clinical trials (EL-4) or regulatory approval (EL-5). This disproportion between in vitro promise and clinical translation is a central challenge for the field and motivates the standardized assessment frameworks proposed in 'Conclusions'.
The application of AI to smart biomaterial design has expanded rapidly beyond simple compositional screening. Six specific AI capabilities are particularly relevant to bone regeneration. (i) Generative AI for biomaterial discovery: variational autoencoders and diffusion models can propose novel polymer chemistries, peptide sequences, or composite formulations with desired mechanical, degradation, and bioactivity properties, complementing traditional design-of-experiments. (ii) Digital twins of bone defect healing: patient-specific finite-element and agent-based models, calibrated by imaging and biomarker data, can simulate healing trajectories and predict optimal scaffold geometry and release kinetics. (iii) Machine learning-guided scaffold optimization: surrogate models trained on high-throughput printing data accelerate the design of pore architecture, lattice topology, and multimaterial interfaces. (iv) Predictive modeling of degradation behavior: physics-informed neural networks predict in vivo degradation rates under patient-specific loading, inflammation, and pH conditions, addressing a key translational bottleneck. (v) Explainable AI (XAI): SHAP, LIME, and attention mechanisms are beginning to make AI-driven design recommendations interpretable, which is essential for regulatory acceptance. (vi) Data scarcity and federated learning: the field faces a chronic shortage of large, labeled biomaterial-performance datasets; federated and self-supervised approaches, together with synthetic data generation, are emerging as solutions.
Real-time monitoring technologies may further transform bone repair from static follow-up into dynamic therapeutic management. Implantable sensors and smart implants can monitor local stress, strain, temperature, pH, oxygen concentration, or healing-related signals after implantation105,106,107. Wireless data transmission and Internet-of-Things-based systems could allow clinicians to detect delayed healing, abnormal loading, infection risk, or implant failure earlier than conventional imaging-based follow-up. When combined with responsive biomaterials, these monitoring systems may eventually create closed-loop therapeutic platforms that sense local conditions and adjust treatment accordingly.
Current limitations and unresolved challenges
Despite substantial progress, the field faces several unresolved challenges. (i) Disproportion between in vitro and clinical evidence: as noted in the section 'Emerging technologies and clinical translation,' >70% of smart biomaterial studies remain at EL-1/EL-2, and the leap to clinical translation is hindered by the scarcity of GLP-compliant large-animal safety data. (ii) Oversimplified immune models: the M1/M2 dichotomy, although pedagogically useful, no longer captures the spectrum of macrophage phenotypes revealed by single-cell transcriptomics. (iii) Limited integration of patient-specific variables: most designs assume a generic healing trajectory and do not account for age, sex, comorbidity, or genetic background. (iv) Lack of standardized assessment: cross-study comparison is impeded by the absence of harmonized protocols for biosafety, immunogenicity, degradation kinetics, and mechanical reliability. (v) Regulatory ambiguity for combination products: smart biomaterials that combine a device, a drug, and a biologic fall into complex regulatory categories whose approval pathways remain ill-defined in many jurisdictions. Addressing these limitations will require coordinated action from materials scientists, immunologists, clinicians, regulators, and industry partners.
Methodological limitations and reporting standards in smart biomaterial research
While smart biomaterials hold considerable promise, the gap between laboratory demonstration and clinical benefit remains the most important unsolved problem. A bias toward publishing positive in vitro results, combined with limited replication and few registered preclinical studies, inflates the field's perceived maturity. The community would benefit from a shift toward registered study designs and standardized reporting.
결론
Smart biomaterials are reshaping bone regeneration by moving beyond passive structural support to actively regulate the local repair microenvironment. Stimulus-responsive platforms respond to external cues (light, electrical signals, magnetic fields, mechanical loading) and internal pathological signals (ROS, acidic pH, enzymatic activity), enabling precise spatiotemporal control of therapeutic release and cellular behavior. In parallel, immunoengineered biomaterials guide macrophage polarization and immune-cell recruitment to foster a regenerative microenvironment. The integration of 3D/4D printing, AI-driven design, organoid models, and bone-on-a-chip systems further expands the potential for personalized bone repair.
However, the current evidence base remains predominantly preclinical. Most studies rely on in vitro systems or small-animal models, and robust clinical data are scarce; these gaps must be acknowledged when interpreting the promising outcomes reported in the literature. Clinical translation is further limited by biosafety concerns, degradation-product toxicity, manufacturing reproducibility, and regulatory complexity.
Recent complementary studies further enrich this framework: Vignolo et al.108 discussed strategies for craniofacial tissue engineering and scalable bone regeneration; Cai et al.109 summarized advances in biomimetic bone scaffold development; Patel et al.110 reviewed bone morphogenetic protein-related therapies for medication-related osteonecrosis of the jaw; and Viraji et al.111 reported a wireless bioelectric stimulation strategy for bone regeneration.
Future advancements should focus on six strategic priorities: (1) developing temporally programmable, multifunctional systems that recapitulate the inflammation–repair–remodeling cascade; (2) engineering closed-loop platforms that integrate real-time biosensors with responsive actuators; (3) utilizing clinically relevant large-animal models and patient-derived disease constructs; (4) establishing standardized assessment protocols aligned with ARRIVE-like reporting guidelines; (5) advancing patient-specific designs by synergizing artificial intelligence with individual imaging and genomic data; and (6) bridging the translational gap through Good Laboratory Practice (GLP)-compliant safety evaluations, Good Manufacturing Practice (GMP) manufacturing, and proactive regulatory engagement. Ultimately, next-generation smart biomaterials capable of microenvironmental responsiveness, immune modulation, and personalized customization hold significant promise for delivering precise therapeutic interventions for complex bone defects, non-union fractures, and post-oncologic reconstruction.
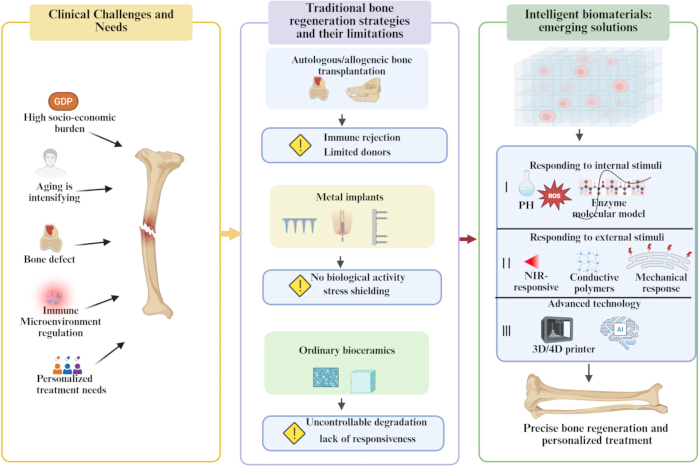
Figure 1: Clinical demands, limitations of conventional strategies, and smart biomaterial-based solutions in bone regeneration. Population aging, rising incidence of bone defects, immune dysregulation, and personalized therapeutic needs underscore the need for improved bone repair. Traditional treatments—such as autografts/allografts, metal implants, and standard bioceramics—are limited by donor scarcity, immune rejection, stress shielding, low bioactivity, and uncontrolled degradation. Smart biomaterials overcome these shortcomings by responding to endogenous (pH, ROS, enzymes) and external stimuli (light, electrical, and mechanical cues), and by integrating advanced 3D/4D printing technologies to enable precise and personalized bone regeneration. Figure created by BioRender. https://BioRender.com Please click here to view a larger version of this figure.
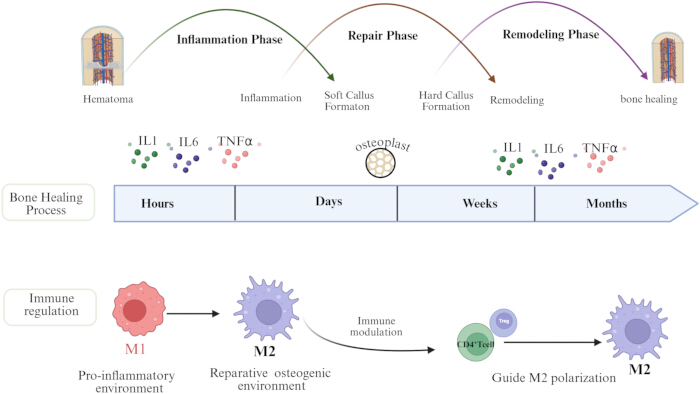
Figure 2: Temporal progression of bone healing and the stage-specific roles of immune regulation. Bone healing proceeds through the inflammatory, repair, and remodeling phases, accompanied by dynamic changes in cellular activities and cytokine levels (e.g., IL-1, IL-6, TNF-α). Early inflammation is dominated by M1 macrophages, which establish a pro-inflammatory microenvironment. As healing advances, macrophages transition toward the M2 phenotype, promoting osteogenesis and tissue repair. T cells—particularly regulatory T cells (Tregs)—further modulate M2 polarization, maintain immune homeostasis, and facilitate coordinated bone regeneration. Figure created by BioRender. https://BioRender.com Please click here to view a larger version of this figure.
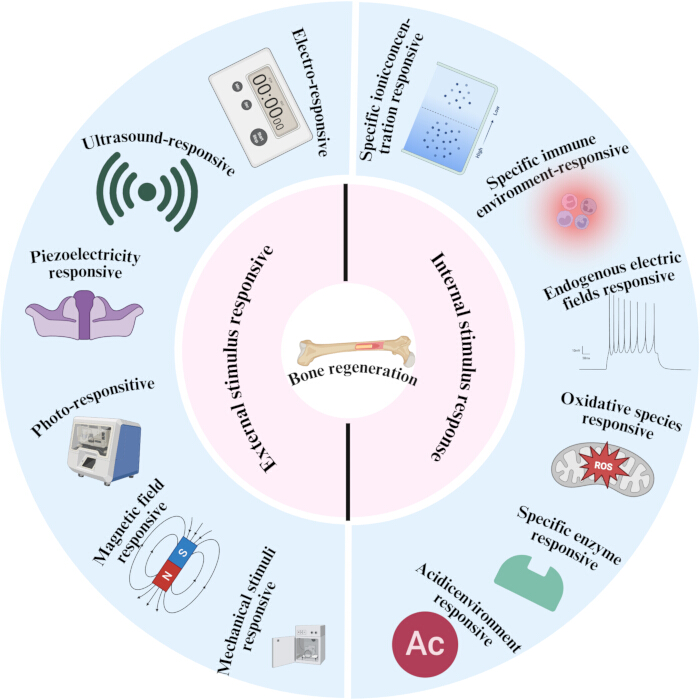
Figure 3: Schematic illustration of external and internal stimulus-responsive smart biomaterials for bone regeneration. The left panel depicts materials responsive to external physical stimuli—including light, electrical signals, magnetic fields, ultrasound, and mechanical/piezoelectric cues—while the right panel shows biomaterials responsive to internal microenvironmental signals such as ROS, pH, enzymatic activity, ion concentrations, endogenous electric fields, and immune microenvironmental changes. Together, these distinct classes of stimuli-responsive materials promote bone regeneration through multiple coordinated mechanisms. Figure created by BioRender. https://BioRender.com. Please click here to view a larger version of this figure.
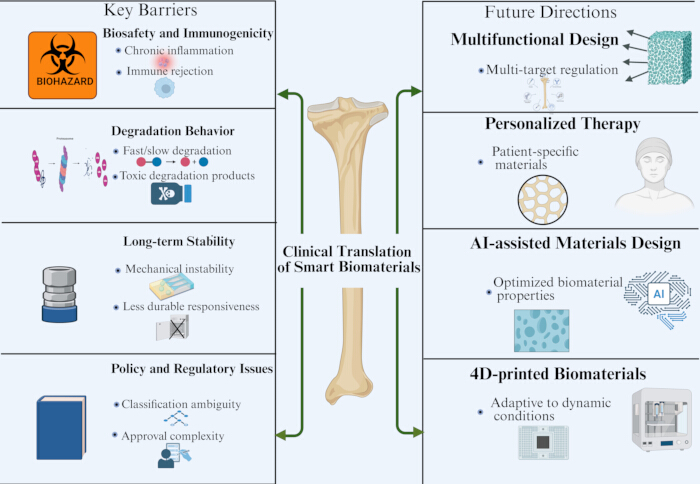
Figure 4: Key barriers and future directions for the clinical translation of smart biomaterials in bone regeneration. The left panel summarizes major bottlenecks hindering clinical translation, including biosafety and immunogenicity concerns, uncertainties in degradation kinetics, insufficient long-term mechanical and functional stability, and the regulatory complexity associated with multifunctional composite systems. The right panel highlights emerging future directions, such as multi-target synergistic material designs, patient-specific personalized therapies, AI-driven material optimization, and 4D-printed constructs capable of dynamically adapting to the in vivo environment. Figure created by BioRender. https://BioRender.com. Please click here to view a larger version of this figure.
| Stimulus Type | Representative Materials | Key Biological Effects | Advantages / Limitations | References |
| Light (NIR) | BP nanosheets, AuNRs, PDA coatings, ICG-loaded hydrogels | Tumor ablation (PTT); antibacterial activity; controlled drug/GF release; MSC osteogenesis | Pros: High spatiotemporal precision; on-demand activation; dual antibacterial + osteogenic | 38,39,40,41 |
| (External) | Cons: Limited deep-tissue penetration; thermal dose control; suitable mainly for superficial defects | |||
| Electrical & Piezoelectric | Conductive polymers (PPy, PEDOT), CNTs, piezoceramics (BaTiO₃, PVDF) | Enhanced MSC osteogenic differentiation; increased ALP activity; mineral deposition; angiogenesis | Pros: Mimics native bone electromechanics; no exogenous GF required; suitable for load-bearing defects | 43,44,45,46,47 |
| (External) | Cons: Stimulation parameter optimization unclear; long-term biosafety; patient compliance | |||
| Magnetic | IONPs (Fe₃O₄, γ-Fe₂O₃), magnetic hydrogels, magnetoelectric composites | Guided drug delivery; enhanced cell recruitment; angiogenesis; osteogenic stimulation | Pros: Deep tissue penetration; noninvasive remote control; spatial targeting; no ionizing radiation | 43,44,45,46,47,48 |
| (External) | Cons: Particle dose and long-term retention concerns; potential iron overload; standardization lacking | |||
| Mechanical | Tunable-stiffness hydrogels, elastomeric scaffolds, stress-adaptive polymers | MSC lineage commitment; matrix deposition; mechanically-driven osteogenesis | Pros: Directly mimics bone mechanical niche; passive (no external power); integrates with physiological loading | 45,46,47,48,49 |
| (External) | Cons: Static vs. dynamic loading complexity; patient-specific mechanical requirements; fatigue over time | |||
| Ultrasound | LIPUS devices, ultrasound-responsive microbubbles | Accelerated fracture healing; enhanced angiogenesis; increased callus formation | Pros: Clinically approved (Exogen®); noninvasive; established safety; good patient compliance | 15 |
| (External) | Cons: Mechanism incompletely understood; efficacy varies by defect type; optimal parameters not standardized | |||
| ROS-Responsive | PPS-based polymers, TK-linked hydrogels, ceria NPs, PDA-coated scaffolds | Localized antioxidant release; inflammation reduction; restored osteogenic signaling; M1→M2 transition | Pros: Closed-loop (activated by pathology); targets chronic inflammation and ROS-rich defects; selective degradation | 50,51,52,53,54 |
| (Internal) | Cons: ROS heterogeneity between patients; insufficient stimulus intensity in some defects; burst vs. sustained release | |||
| pH-Responsive | CaP nanoparticles, chitosan-based hydrogels, Schiff-base-crosslinked networks | Site-specific drug/GF release at acidic defect sites; antibacterial delivery; antitumor drug release | Pros: Exploits endogenous acidosis (inflammation, infection, tumor); localized delivery; reduced systemic toxicity | 55,56,57,58 |
| (Internal) | Cons: pH gradient variability; burst release risk; limited specificity (inflammatory vs. tumor pH overlap) | |||
| Enzyme-Responsive (MMP) | MMP-sensitive PEG hydrogels, peptide-functionalized scaffolds | On-demand GF/cytokine release during tissue remodeling; cell-mediated scaffold remodeling; MSC recruitment | Pros: Cell-driven release kinetics; matches tissue remodeling timeline; maintains structural support early | 59,60,61 |
| (Internal) | Cons: Enzyme level variability; patient-to-patient differences; long-term stability of peptide linkers; manufacturing complexity |
Table 1: Stimulus-responsive comparison table. This table compares externally and internally responsive smart biomaterials across stimulus categories, triggering mechanisms, representative material platforms, key biological effects, advantages, and translational limitations. Externally responsive strategies (light/near-infrared, electrical/piezoelectric, magnetic, mechanical, and ultrasound) provide high spatiotemporal control through applied physical stimuli but require device integration and patient compliance. Internally responsive strategies (reactive oxygen species, pH, and enzyme/matrix metalloproteinase) function as closed-loop platforms activated by pathological or regenerative signals within the local microenvironment, offering pathology-specific regulation but facing challenges posed by microenvironmental heterogeneity and patient-to-patient variability. Please click here to download this Table.
| Immunomodulatory Dimension | Key Immune Cells / Factors | Smart Biomaterial-Based Modulation Strategies | Primary Biological Effects on Bone Healing | Key Design Principles | Potential Risks and Translational Challenges | References |
| Inflammatory Phase Immune Activation | M1 macrophages; TNF-α, IL-1, IL-6 | Surface chemical functionalization; micro-/nano-topographical modulation | Clearance of necrotic tissue; initiation of angiogenesis and tissue repair | Allow transient, controlled pro-inflammatory signaling | Prolonged inflammation may impair bone healing | 64,65,66, 68,69,70,71,72,73 |
| Immune transition during the reparative phase | M2 macrophages, IL-10, TGF-β | Surface functionalization; IL-4/miRNA delivery | Suppress inflammation; promote osteogenesis and angiogenesis | Promote M2 polarization after inflammatory clearance | Excessive M2 polarization may impair immune surveillance | 63, 67, 68, 74 |
| Osteogenic–angiogenic coupling | VEGF,BMPs | Biodegradable scaffolds; multilayer coatings; sequential release | Osteogenesis; angiogenesis; matrix remodeling | Coordinated osteogenic–angiogenic signaling is required | Osteogenic–angiogenic signaling requires coordination | 22, 23, 75, 76 |
| Temporal immune programming | IL-4/IL-13 → TGF-β/VEGF → BMPs | Programmable degradable materials; staged release | Coordinate inflammation–repair–remodeling | Avoid single release; enable staged control | High complexity; manufacturing and stability | 69,70,71,72,73,74,75,76 |
| Immune cell recruitment | MCP-1/CCR2, CXCL12 | Chemokine gradients; factor binding | Recruit macrophages and MSCs | Coordinate recruitment and polarization | Cell source heterogeneity; individual variability | 77,78,80 |
| Multitarget immune remodeling | Macrophages + stem cells + osteoblasts | Factor combinations; spatial release control | Improve the local immune–regenerative microenvironment | Integrate temporal and spatial heterogeneity | Balancing standardization and personalization | 63, 77,78,79,80,81,82 |
Table 2: Immunoengineering strategies for bone regeneration. This table summarizes major immunoengineering strategies used in smart biomaterial-assisted bone regeneration, including regulation of inflammatory activation, macrophage phenotype transition, osteogenic–angiogenic coupling, temporal immune programming, immune-cell recruitment, and multitarget immune remodeling. Key immune cells, regulatory factors, biomaterial-based modulation approaches, biological effects, design principles, and potential translational challenges are listed. Please click here to download this Table.
| Decision criteria | 3D-printed bone scaffolds | 4D-printed bone scaffolds | References |
| Core design principles | Image-based, statically matched implants | Introduce temporal dynamics for adaptive regulation | 83,84,85,86,95 |
| Primary technological basis | CT/MRI-driven reconstruction; layer-by-layer fabrication | Stimuli-responsive materials and programmable structures | 83,84,85,86,87, 95 |
| Degree of personalization | Personalized anatomy and mechanics; fixed after implantation | Dynamic in vivo adjustment of form and function | 85,86,87, 92, 95,96,97 |
| Ability to mimic bone microarchitecture | Controlled porosity to mimic cortical–trabecular bone | Dynamic adaptation during bone repair | 88,89,90, 95, 96 |
| Spatial control of bioactive factors | Spatial gradients of BMPs and VEGF | Environment-responsive temporal release | 91, 93, 94, 96 |
| Mechanical–biological functional synergy | Balance mechanical support and cell infiltration | Dynamic mechanical adaptation during healing | 88,90,91, 93,94,95 |
| Adaptability to complex defects | For defined, load-bearing bone defects | For irregular or dynamic defects | 85,86,87, 92, 95,96,97 |
| Surgical and implantation advantages | Mature preoperative design; clear implantation | In situ adaptation reduces surgical complexity | 83, 85,86,87, 92, 96, 97 |
| Primary clinical application stage | Most mature, near-clinical technology | Exploratory, early-stage translation | 83, 84, 95,96,97 |
| Potential limitations | Limited dynamic responsiveness | Stability, controllability, and long-term safety need evaluation | 83, 84, 95, 97 |
| Decision recommendations | Large, load-bearing defects needing precise mechanics | Irregular defects needing adaptive control | 85,86,87, 89, 90, 92, 95,96,97 |
Table 3: Comparison of 3D and 4D printing strategies for personalized bone regeneration. This table compares 3D- and 4D-printed bone scaffolds with respect to design principles, technological basis, personalization capacity, bone microarchitecture mimicry, spatial or temporal control of bioactive factors, mechanical–biological synergy, adaptability to complex defects, surgical advantages, clinical maturity, limitations, and recommended application scenarios. Please click here to download this Table.
공개 사항
저자들은 선언할 이해관계 충돌이 없습니다.
감사의 글
본 연구는 공공, 상업 또는 비영리 자금 지원 기관으로부터 어떠한 특정 연구비 지원도 받지 않았습니다.
참고문헌
- Global, regional, and national burden of bone fractures in 204 countries and territories, 1990-2019: a systematic analysis from the Global Burden of Disease Study 2019. Lancet Healthy Longev. 2021;2(9):e580-e92.
- Yi Y, He X, Wu Y, Wang D. Global, regional, and national burden of incidence, prevalence, and years lived with disability for facial fractures from 1990 to 2019: a systematic analysis for the Global Burden of Disease study 2019. BMC Oral Health. 2024;24(1):435.
- Wei H, Cui J, Lin K, Xie J, Wang X. Recent advances in smart stimuli-responsive biomaterials for bone therapeutics and regeneration. Bone Research. 2022;10(1):17.
- Su N, Villicana C, Yang F. Immunomodulatory strategies for bone regeneration: A review from the perspective of disease types. Biomaterials. 2022;286:121604.
- Xue C, Chen L, Wang N, Chen H, Xu W, Xi Z, et al. Stimuli-responsive hydrogels for bone tissue engineering. BMT. 2024;5(3).
- Hoveidaei AH, Sadat-Shojai M, Nabavizadeh SS, Niakan R, Shirinezhad A, MosalamiAghili S, et al. Clinical challenges in bone tissue engineering - A narrative review. Bone. 2025;192:117363.
- Clark JR, Al Maruf DSA, Tomaskovic-Crook E, Cheng K, Lewin WT, Xin H, et al. Mechanobiologically-optimized non-resorbable artificial bone for patient-matched scaffold-guided bone regeneration. Nature Communications. 2025;16(1):9422.
- Xing Y, Qiu L, Liu D, Dai S, Sheu CL. The role of smart polymeric biomaterials in bone regeneration: a review. Front Bioeng Biotechnol. 2023;11:1240861.
- Song P, Zhou D, Wang F, Li G, Bai L, Su J. Programmable biomaterials for bone regeneration. Materials Today Bio. 2024;29:101296.
- Yang K, Wu Z, Zhang K, Weir MD, Xu HHK, Cheng L, et al. Unlocking the potential of stimuli-responsive biomaterials for bone regeneration. Front Pharmacol. 2024;15:1437457.
- Bai Y, Wu N, Li X, Liu Z, Li K, Jiao T, et al. Recent progress of 3D printed responsive scaffolds for bone repair: A review. Mater Today Bio. 2025;35:102351.
- Yang D, Xu Z, Huang D, Luo Q, Zhang C, Guo J, et al. Immunomodulatory multifunctional janus collagen-based membrane for advanced bone regeneration. Nature Communications. 2025;16(1):4264.
- Yang F, Jia J, Xiao Y, Feng P. Advances in 3D/4D printing of bone scaffolds and their shape/properties adaptability. Review of Materials Research. 2025;1(4):100088.
- Zhou B, Li X, Pan Y, He B, Gao B. Artificial intelligence-assisted next-generation biomaterials: From design and preparation to medical applications. Colloids and Surfaces B: Biointerfaces. 2025;255:114970.
- Montoya C, Du Y, Gianforcaro AL, Orrego S, Yang M, Lelkes PI. On the road to smart biomaterials for bone research: definitions, concepts, advances, and outlook. Bone Research. 2021;9(1):12.
- Steppe L, Megafu M, Tschaffon-Müller MEA, Ignatius A, Haffner-Luntzer M. Fracture healing research: Recent insights. Bone Reports. 2023;19:101686.
- Choi IA, Umemoto A, Mizuno M, Park-Min K-H. Bone metabolism – an underappreciated player. npj Metabolic Health and Disease. 2024;2(1):12.
- Schlundt C, Fischer H, Bucher CH, Rendenbach C, Duda GN, Schmidt-Bleek K. The multifaceted roles of macrophages in bone regeneration: A story of polarization, activation and time. Acta Biomaterialia. 2021;133:46-57.
- Capobianco CA, Hankenson KD, Knights AJ. Temporal dynamics of immune-stromal cell interactions in fracture healing. FRONTIERS IN IMMUNOLOGY. 2024;15.
- Yang L, Shi F, Cao F, Wang L, She J, He B, et al. Neutrophils in Tissue Injury and Repair: Molecular Mechanisms and Therapeutic Targets. MedComm (2020). 2025;6(5):e70184.
- Zhang H, Qiao W, Liu Y, Yao X, Zhai Y, Du L. Addressing the challenges of infectious bone defects: a review of recent advances in bifunctional biomaterials. Journal of Nanobiotechnology. 2025;23(1):257.
- Geng Y, Duan H, Xu L, Witman N, Yan B, Yu Z, et al. BMP-2 and VEGF-A modRNAs in collagen scaffold synergistically drive bone repair through osteogenic and angiogenic pathways. Communications Biology. 2021;4(1):82.
- Qi J, Wu H, Liu G. Novel Strategies for Spatiotemporal and Controlled BMP-2 Delivery in Bone Tissue Engineering. Cell Transplantation. 2024;33:09636897241276733.
- Sims NA. Osteoclast-derived coupling factors: origins and state-of-play Louis V Avioli lecture, ASBMR 2023. J Bone Miner Res. 2024;39(10):1377-85.
- Zhang D, Dang Y, Deng R, Ma Y, Wang J, Ao J, et al. Research Progress of Macrophages in Bone Regeneration. J Tissue Eng Regen Med. 2023;2023:1512966.
- Chen S, Saeed AFUH, Liu Q, Jiang Q, Xu H, Xiao GG, et al. Macrophages in immunoregulation and therapeutics. Signal Transduction and Targeted Therapy. 2023;8(1):207.
- Bi Z, Cai Y, Shi X, Chen J, Li D, Zhang P, et al. Macrophage-mediated immunomodulation in biomaterial-assisted bone repair: Molecular insights and therapeutic prospects. Chemical Engineering Journal. 2024;488:150631.
- Griffith JW, Luster AD. No bones about it: regulatory T cells promote fracture healing. J Clin Invest. 2025;135(2).
- Nayer B, Tan JL, Alshoubaki YK, Lu Y-Z, Legrand JMD, Lau S, et al. Local administration of regulatory T cells promotes tissue healing. Nature Communications. 2024;15(1):7863.
- Chen RY, Zhang XM, Li B, Tonetti MS, Yang YJ, Li Y, et al. Progranulin-dependent repair function of regulatory T cells drives bone-fracture healing. JOURNAL OF CLINICAL INVESTIGATION. 2025;135(2).
- Chen L, Yao Z, Zhang S, Tang K, Yang Q, Wang Y, et al. Biomaterial-induced macrophage polarization for bone regeneration. Chinese Chemical Letters. 2023;34(6):107925.
- Chocholata PK, Dvorakova J, Babuska V, Cedikova M. Biomaterial Strategies of Macrophage Behaviour in Bone Regeneration. Regenerative Engineering and Translational Medicine. 2025.
- El-Rashidy AA, El Moshy S, Radwan IA, Rady D, Abbass MMS, Dörfer CE, et al. Effect of Polymeric Matrix Stiffness on Osteogenic Differentiation of Mesenchymal Stem/Progenitor Cells: Concise Review. Polymers (Basel). 2021;13(17).
- Rajendran AK, Sankar D, Amirthalingam S, Kim HD, Rangasamy J, Hwang NS. Trends in mechanobiology guided tissue engineering and tools to study cell-substrate interactions: a brief review. Biomaterials Research. 2023;27(1):55.
- Aydin MS, Marek N, Luciani T, Mohamed-Ahmed S, Lund B, Gjerde C, et al. Impact of Porosity and Stiffness of 3D Printed Polycaprolactone Scaffolds on Osteogenic Differentiation of Human Mesenchymal Stromal Cells and Activation of Dendritic Cells. ACS Biomaterials Science & Engineering. 2024;10(12):7539-54.
- Ni X, Xing X, Deng Y, Li Z. Applications of Stimuli-Responsive Hydrogels in Bone and Cartilage Regeneration. Pharmaceutics [Internet]. 2023; 15(3):[982 p.].
- Liang L, Li X, Liang H, Zhang J, Lu Q, Zhou G, et al. Navigating oxidative stress in oral bone regeneration: mechanisms and reactive oxygen species-regulating biomaterial strategies. Regenerative Biomaterials. 2025;12:rbaf091.
- Tong L, Liao Q, Zhao Y, Huang H, Gao A, Zhang W, et al. Near-infrared light control of bone regeneration with biodegradable photothermal osteoimplant. Biomaterials. 2019;193:1-11.
- Wang X, Shao J, Abd El Raouf M, Xie H, Huang H, Wang H, et al. Near-infrared light-triggered drug delivery system based on black phosphorus for in vivo bone regeneration. Biomaterials. 2018;179:164-74.
- Song J, Zhang J, Xie L, Wu N, Wu L, Liu J, et al. Insights into black phosphorus-based nanomaterials for bone therapy: From construction strategies to functions and beyond. APL Materials. 2025;13(4):041119.
- Jing HH, Patel M, Adnan M, Sasidharan S. Light-responsive nanotherapeutic carbon dots: a next generation tool for cancer phototherapy. Journal of the National Cancer Center. 2025.
- Ribeiro TP, Flores M, Madureira S, Zanotto F, Monteiro FJ, Laranjeira MS. Magnetic Bone Tissue Engineering: Reviewing the Effects of Magnetic Stimulation on Bone Regeneration and Angiogenesis. Pharmaceutics. 2023;15(4).
- Samadi A, Salati MA, Safari A, Jouyandeh M, Barani M, Singh Chauhan NP, et al. Comparative review of piezoelectric biomaterials approach for bone tissue engineering. Journal of Biomaterials Science, Polymer Edition. 2022;33(12):1555-94.
- Ni X, Cui Y, Salehi M, Nai MLS, Zhou K, Vyas C, et al. Piezoelectric Biomaterials for Bone Regeneration: Roadmap from Dipole to Osteogenesis. Advanced Science. 2025;12(32):e14969.
- Joo S, Gwon Y, Kim S, Park S, Kim J, Hong S. Piezoelectrically and Topographically Engineered Scaffolds for Accelerating Bone Regeneration. ACS Applied Materials & Interfaces. 2024;16(2):1999-2011.
- Zaszczyńska A, Zabielski K, Gradys A, Kowalczyk T, Sajkiewicz P. Piezoelectric Scaffolds as Smart Materials for Bone Tissue Engineering. Polymers [Internet]. 2024; 16(19):[2797 p.].
- Farjaminejad S, Dingle AM. The role of electrical stimulation in bone regeneration: mechanistic insights and therapeutic advances. Bioelectronic Medicine. 2025;11(1):18.
- Dasari A, Xue J, Deb S. Magnetic Nanoparticles in Bone Tissue Engineering. Nanomaterials [Internet]. 2022; 12(5):[757 p.].
- Li W, Mo Y, Xie S, Fu L, Ye Y, Zhou Y, et al. Self-reinforced piezoelectric chip for scaffold-free repair of critical-sized bone defects. Nature Communications. 2025;16(1):5800.
- Shafiq M, Chen YJ, Hashim R, He CL, Mo XM, Zhou XJ. Reactive Oxygen Species-Based Biomaterials for Regenerative Medicine and Tissue Engineering Applications. FRONTIERS IN BIOENGINEERING AND BIOTECHNOLOGY. 2021;9.
- Ren X, Liu H, Wu X, Weng W, Wang X, Su J. Reactive Oxygen Species (ROS)-Responsive Biomaterials for the Treatment of Bone-Related Diseases. Front Bioeng Biotechnol. 2021;9:820468.
- Dos Santos RL, Ahmed A, Hunn BE, Addison AE, Marques DW, Bruce KA, et al. Oxidation-responsive, settable bone substitute composites for regenerating critically-sized bone defects. BIOMATERIALS SCIENCE. 2025;13(8):1975-92.
- Miszuk J, Hu J, Wang Z, Onyilagha O, Younes H, Hill C, et al. Reactive oxygen-scavenging polydopamine nanoparticle coated 3D nanofibrous scaffolds for improved osteogenesis: Toward an aging in vivo bone regeneration model. Journal of Biomedical Materials Research Part B: Applied Biomaterials. 2024;112(8):e35456.
- Huang Q, Qu Y, Tang M, Lan K, Zhang Y, Chen S, et al. ROS-responsive hydrogel for bone regeneration: Controlled dimethyl fumarate release to reduce inflammation and enhance osteogenesis. Acta Biomater. 2025;195:183-200.
- Zarur M, Seijo-Rabina A, Goyanes A, Concheiro A, Alvarez-Lorenzo C. pH-responsive scaffolds for tissue regeneration: In vivo performance. Acta Biomaterialia. 2023;168:22-41.
- Zhao C, Qazvini NT, Sadati M, Zeng Z, Huang S, De La Lastra AL, et al. A pH-Triggered, Self-Assembled, and Bioprintable Hybrid Hydrogel Scaffold for Mesenchymal Stem Cell Based Bone Tissue Engineering. ACS Applied Materials & Interfaces. 2019;11(9):8749-62.
- Qiu C, Wu Y, Guo Q, Shi Q, Zhang J, Meng Y, et al. Preparation and application of calcium phosphate nanocarriers in drug delivery. Mater Today Bio. 2022;17:100501.
- Chen H, Tan W, Tong T, Shi X, Ma S, Zhu G. A pH-Responsive Asymmetric Microfluidic/Chitosan Device for Drug Release in Infective Bone Defect Treatment. Int J Mol Sci. 2023;24(5).
- Xie K, Liu Z, Chen K, Che J, Wang Y. A matrix metalloproteinase-responsive hydrogel with spatially orchestrated delivery of stem cells and raleukin for enhanced bone regeneration. Materials Today Bio. 2025;35:102475.
- Zhang M, Yu T, Li J, Yan H, Lyu L, Yu Y, et al. Matrix Metalloproteinase-Responsive Hydrogel with On-Demand Release of Phosphatidylserine Promotes Bone Regeneration Through Immunomodulation. Adv Sci (Weinh). 2024;11(20):e2306924.
- Lutolf MP, Lauer-Fields JL, Schmoekel HG, Metters AT, Weber FE, Fields GB, et al. Synthetic matrix metalloproteinase-sensitive hydrogels for the conduction of tissue regeneration: Engineering cell-invasion characteristics. Proceedings of the National Academy of Sciences. 2003;100(9):5413-8.
- Lin M, Qi X. Advances and Challenges of Stimuli-Responsive Nucleic Acids Delivery System in Gene Therapy. Pharmaceutics. 2023;15(5).
- Dong C, Tan G, Zhang G, Lin W, Wang G. The function of immunomodulation and biomaterials for scaffold in the process of bone defect repair: A review. Front Bioeng Biotechnol. 2023;11:1133995.
- Frade BB, Dias RB, Gemini Piperni S, Bonfim DC. The role of macrophages in fracture healing: a narrative review of the recent updates and therapeutic perspectives. Stem Cell Investig. 2023;10:4.
- Song Z, Cheng Y, Chen M, Xie X. Macrophage polarization in bone implant repair: A review. Tissue and Cell. 2023;82:102112.
- Kushioka J, Chow SK-H, Toya M, Tsubosaka M, Shen H, Gao Q, et al. Bone regeneration in inflammation with aging and cell-based immunomodulatory therapy. Inflammation and Regeneration. 2023;43(1):29.
- Zhu G, Zhang T, Chen M, Yao K, Huang X, Zhang B, et al. Bone physiological microenvironment and healing mechanism: Basis for future bone-tissue engineering scaffolds. Bioactive Materials. 2021;6(11):4110-40.
- Sanati M, Pieterman I, Levy N, Akbari T, Tavakoli M, Najafabadi AH, et al. Osteoimmunomodulation by bone implant materials: harnessing physicochemical properties and chemical composition. BIOMATERIALS SCIENCE. 2025;13(11):2836-70.
- Cai D, Gao W, Li Z, Zhang Y, Xiao L, Xiao Y. Current Development of Nano-Drug Delivery to Target Macrophages. Biomedicines [Internet]. 2022; 10(5):[1203 p.].
- Schlundt C, El Khassawna T, Serra A, Dienelt A, Wendler S, Schell H, et al. Macrophages in bone fracture healing: Their essential role in endochondral ossification. Bone. 2018;106:78-89.
- Maruyama M, Rhee C, Utsunomiya T, Zhang N, Ueno M, Yao Z, et al. Modulation of the Inflammatory Response and Bone Healing. Front Endocrinol (Lausanne). 2020;11:386.
- Batool F, Özçelik H, Stutz C, Gegout P-Y, Benkirane-Jessel N, Petit C, et al. Modulation of immune-inflammatory responses through surface modifications of biomaterials to promote bone healing and regeneration. Journal of Tissue Engineering. 2021;12:20417314211041428.
- Yang TX, Fang ZR, Zhang J, Zheng SN. Physical cues in biomaterials modulate macrophage polarization for bone regeneration: a review. FRONTIERS IN BIOENGINEERING AND BIOTECHNOLOGY. 2025;13.
- Zhang J, Shi H, Zhang N, Hu L, Jing W, Pan J. Interleukin-4-loaded hydrogel scaffold regulates macrophages polarization to promote bone mesenchymal stem cells osteogenic differentiation via TGF-β1/Smad pathway for repair of bone defect. Cell Prolif. 2020;53(10):e12907.
- Szwed-Georgiou A, Płociński P, Kupikowska-Stobba B, Urbaniak MM, Rusek-Wala P, Szustakiewicz K, et al. Bioactive Materials for Bone Regeneration: Biomolecules and Delivery Systems. ACS Biomaterials Science & Engineering. 2023;9(9):5222-54.
- Ruth S, Extension KP. Cytokine Modulation with Biomaterials: Engineering the Immune Response for Tissue Repair and Regeneration. 2024;4:37-41.
- Ishikawa M, Ito H, Kitaori T, Murata K, Shibuya H, Furu M, et al. MCP/CCR2 signaling is essential for recruitment of mesenchymal progenitor cells during the early phase of fracture healing. PLoS One. 2014;9(8):e104954.
- Brylka LJ, Schinke T. Chemokines in Physiological and Pathological Bone Remodeling. Front Immunol. 2019;10:2182.
- Yellowley C. CXCL12/CXCR4 signaling and other recruitment and homing pathways in fracture repair. Bonekey Rep. 2013;2:300.
- Liu SB, Liu Y, Zheng ZZ, Li BL, Shao JJ, Liu X, et al. Stem cell homing as a promising strategy for bone regeneration: focus on biomaterials. European Cells and Materials. 2025;51:83-102.
- Li J, Qu Y, Chu B, Wu T, Pan M, Mo D, et al. Research Progress on Biomaterials with Immunomodulatory Effects in Bone Regeneration. Adv Sci (Weinh). 2025;12(33):e01209.
- Zhao J, Sun Q, Gu J, Xu X, Xia M, Xia H, et al. From “immune silence” to “immune dialogue”: modification strategies for bone substitutes based on bone immunomodulatory characteristics. Frontiers in Cell and Developmental Biology. 2025;Volume 13 - 2025.
- Zhang X, Yang Y, Yang Z, Ma R, Aimaijiang M, Xu J, et al. Four-Dimensional Printing and Shape Memory Materials in Bone Tissue Engineering. Int J Mol Sci. 2023;24(1).
- Sun J, Chen C, Zhang B, Yao C, Zhang Y. Advances in 3D-printed scaffold technologies for bone defect repair: materials, biomechanics, and clinical prospects. Biomed Eng Online. 2025;24(1):51.
- Beisekenov N, Azamatov B, Sadenova M, Dogadkin D, Kaliyev D, Rudenko S, et al. Data-Driven Design and Additive Manufacturing of Patient-Specific Lattice Titanium Scaffolds for Mandibular Bone Reconstruction. J Funct Biomater. 2025;16(9).
- Gladman AS, Matsumoto EA, Nuzzo RG, Mahadevan L, Lewis JA. Biomimetic 4D printing. Nat Mater. 2016;15(4):413-8.
- Liu Y-Y, Echeverry-Rendón M. 3D-printed biodegradable polymer scaffolds for tissue engineering: An overview, current stage and future perspectives. Next Materials. 2025;8:100647.
- Kuss MA, Wu S, Wang Y, Untrauer JB, Li W, Lim JY, et al. Prevascularization of 3D printed bone scaffolds by bioactive hydrogels and cell co-culture. J Biomed Mater Res B Appl Biomater. 2018;106(5):1788-98.
- Yang ZH, Wang CJ, Gao H, Jia LR, Zeng H, Zheng LW, et al. Biomechanical Effects of 3D-Printed Bioceramic Scaffolds With Porous Gradient Structures on the Regeneration of Alveolar Bone Defect: A Comprehensive Study. FRONTIERS IN BIOENGINEERING AND BIOTECHNOLOGY. 2022;10.
- Karimi M, Asadi-Eydivand M, Abolfathi N, Chehrehsaz Y, Solati-Hashjin M. The effect of pore size and layout on mechanical and biological properties of 3D-printed bone scaffolds with gradient porosity. Polymer Composites. 2023;44(2):1343-59.
- Park JY, Shim JH, Choi SA, Jang J, Kim M, Lee SH, et al. 3D printing technology to control BMP-2 and VEGF delivery spatially and temporally to promote large-volume bone regeneration. JOURNAL OF MATERIALS CHEMISTRY B. 2015;3(27):5415-25.
- Chang C-M, Huang S-F, Wang H-W, Yu L-Y, Huang T-H, Lo C-L, et al. 3D-printed patient-specific titanium implant for mandibular reconstruction with local drug release: Optimization, in vivo evaluation, and functional assessment. IJB. 2025;11(5).
- Chen S, Shi Y, Zhang X, Ma J. Evaluation of BMP-2 and VEGF loaded 3D printed hydroxyapatite composite scaffolds with enhanced osteogenic capacity in vitro and in vivo. Mater Sci Eng C Mater Biol Appl. 2020;112:110893.
- Barati D, Shariati SRP, Moeinzadeh S, Melero-Martin JM, Khademhosseini A, Jabbari E. Spatiotemporal release of BMP-2 and VEGF enhances osteogenic and vasculogenic differentiation of human mesenchymal stem cells and endothelial colony-forming cells co-encapsulated in a patterned hydrogel. J Control Release. 2016;223:126-36.
- Yang F, Ding W, Jia J, Shuai C, Feng P. 4D printing for bone implant: Progress, advantages and challenges. Progress in Materials Science. 2026;157:101591.
- Wang C, Lai J, Li K, Zhu S, Lu B, Liu J, et al. Cryogenic 3D printing of dual-delivery scaffolds for improved bone regeneration with enhanced vascularization. Bioactive Materials. 2021;6(1):137-45.
- Qu G, Huang J, Gu G, Li Z, Wu X, Ren J. Smart implants: 4D-printed shape-morphing scaffolds for medical implantation. IJB. 2023;9(5).
- Fan J, Xu J, Wen X, Sun L, Xiu Y, Zhang Z, et al. The future of bone regeneration: Artificial intelligence in biomaterials discovery. Materials Today Communications. 2024;40:109982.
- Eber P, Sillmann YM, Guastaldi FPS. Beyond 3D Printing: How AI is Shaping the Future of Craniomaxillofacial Bone Tissue Engineering. ACS Biomater Sci Eng. 2025;11(6):3095-8.
- Jeznach O, Tabakoğlu S, Zaszczyńska A, Sajkiewicz P. Review on machine learning application in tissue engineering: What has been done so far? Application areas, challenges, and perspectives. Journal of Materials Science. 2024;59:21222-50.
- Javaid S, Gorji HT, Soulami KB, Kaabouch N. Identification and ranking biomaterials for bone scaffolds using machine learning and PROMETHEE. Research on Biomedical Engineering. 2023;39(1):129-38.
- Kolomenskaya E, Butova V, Poltavskiy A, Soldatov A, Butakova M. Application of Artificial Intelligence at All Stages of Bone Tissue Engineering. Biomedicines [Internet]. 2024; 12(1):[76 p.].
- Hu Y, Zhang H, Wang S, Cao L, Zhou F, Jing Y, et al. Bone/cartilage organoid on-chip: Construction strategy and application. Bioact Mater. 2023;25:29-41.
- Whelan IT, Burdis R, Shahreza S, Moeendarbary E, Hoey DA, Kelly DJ. A microphysiological model of bone development and regeneration. Biofabrication. 2023;15(3).
- Mansoorifar A, Gordon R, Bergan R, Bertassoni LE. Bone-on-a-chip: microfluidic technologies and microphysiologic models of bone tissue. Adv Funct Mater. 2021;31(6).
- Yogev D, Goldberg T, Arami A, Tejman-Yarden S, Winkler TE, Maoz BM. Current state of the art and future directions for implantable sensors in medical technology: Clinical needs and engineering challenges. APL Bioeng. 2023;7(3):031506.
- Xu C, Liang S, Fan D, Zhu X, Huang M, Zhong T, et al. A self-powered, implantable bone-electronic interface for home-based therapeutic strategy of bone regeneration. Nano Energy. 2024;124:109470.
- Vignolo SM, Roth DM, Wu L, et al. Strategies for craniofacial tissue engineering: innovations for scalable bone regeneration. Plast Aesthet Res. 2025;12:20.
- Cai PF, Ding YF, Wang CQ, et al. Advancing biomimetic bone scaffolds: from electrospun 2D membranes to functional 3D nanofiber constructs. Biomed Technol. 2025;11:100099.
- Patel PA, Nassar SI, Nguyen SA, et al. The use of bone morphogenic protein and related therapies in the management of medication-related osteonecrosis of the jaw: a scoping review. Plast Aesthet Res. 2025;12:13.
- Viraji HA, Abeygunawardane A, Adikary SU, et al. Wireless bioelectric stimulation for bone regeneration using magnetoelectric PVDF/BaTiO₃–Fe₈₀Ga₂₀ laminates. Biomed Technol. 2025;12:100121.