본 연구는 2계층 프레임워크인 일차 신호(호흡, 심박수, 신체 움직임)와 PSG를 통해 검증이 필요한 알고리즘 모델로 추정한 파생 파라미터(수면 구조, 미세 각성)로부터 15가지 다차원 수면 특징을 추출함으로써, 다섯 가지 한방 수면장애(TCM insomnia) 패턴을 객관적으로 특성화하는 비접촉식 밀리미터파 레이더 프레임워크를 제안합니다.
리뷰 논문
밀리미터파 레이더 기반 불면증의 중의학 변증 탐색 및 분석
62 조회수
⸱
2026년 9월 11일
이 논문에서
요약
초록
한의학(TCM)의 불면증 변증에서 연속적이고 객관적인 야간 징후 데이터가 부족한 문제를 해결하기 위해, 본 연구는 밀리미터파 레이더를 기반으로 한 불면증 증후군의 객관적 특성 분석 방법과 디지털-지능형 식별 경로를 탐색합니다. 본 리뷰는 2008년 1월부터 2026년 8월까지 CNKI, Wanfang, PubMed 및 Web of Science를 체계적으로 검색하여 한의학적 불면증 변증 및 치료, 심박 변이도 및 자율신경 기능, 그리고 밀리미터파 레이더를 이용한 비접촉식 수면/호흡 모니터링에 관한 문헌을 다루었습니다. 5가지 주요 불면증 증후군의 한의학적 병인론을 출발점으로 삼고 현대 수면 생리학을 통합하여, 내부적인 “증후군-자율신경/징후” 연관 메커니즘을 도출하였습니다. 레이더로 포착된 비접촉 운동 신호는 호흡, 심박수, 신체 움직임과 같은 1차 생체 징후 시퀀스로 변환됩니다. 이러한 1차 신호를 기반으로 수면 구조, 자율신경 기능, 호흡 패턴, 신체 움직임 행동의 4가지 차원을 포괄하는 15가지 정량적 지표 세트를 도출하였습니다. 이 중 1차 지표는 직접 추출 또는 단순 통계로 얻으며, 수면 구조, 미세 각성 및 무호흡-저호흡 지수(AHI) 지표는 알고리즘 모델에 의해 추정되므로 수면다원검사(PSG)를 통한 검증이 필요합니다. 5가지 불면증 증후군을 레이더 신호 특징과 연결하는 병인-생리 매핑 모델을 구축하여 15가지 표준 파라미터를 갖춘 한의학 수면 디지털 표현 체계를 형성하였으며, 이는 비접촉 신호를 통해 증후군 간의 미세한 차이를 분리하기 위한 이론적 계산 근거를 제공합니다. 밀리미터파 레이더는 전통적인 사진(四診) 진단법의 효과적인 확장 수단이 될 수 있으며, 불면증 변증을 위해 비침습적이고 연속적인 야간 데이터 보완을 제공할 수 있습니다. 본 연구에서 구축한 지표 체계와 이론적 프레임워크는 향후 임상 데이터 검증 및 가정용 디지털-지능형 한의학 수면 평가 장치 개발을 위한 방법론적 토대를 마련합니다.
서론
수면 장애는 전 세계적인 공중 보건 문제가 되었습니다. 전통 중의학(TCM)에서 불면증은 “Bu Mei”(불면) 범주로 분류됩니다. 중의학의 변증논치 체계는 음양의 불균형을 중심으로 하며, 각 개인에게 맞춘 개별화된 진단과 치료를 강조합니다. 전통적인 TCM 변증은 망, 문, 문, 절의 사진(四診) 방법(시진, 청진/후진, 문진, 촉진)에 기반한 의사의 경험에 의존합니다. TCM의 현대화가 진행됨에 따라, 현대적 센싱 기술을 활용하여 변증 정보의 객관적 획득과 정량적 분석을 달성하는 것이 “디지털-지능형” TCM 임상 연구의 핵심 방향이 되었습니다1.
전통적인 수면다원검사(PSG)와 웨어러블 기기(스마트 밴드, 스마트워치, ECG 패치 등)는 모두 센서 착용이 필요합니다. 이러한 방식은 상당한 수면 방해와 뚜렷한 "첫날 밤 효과(first-night effect)"를 유발할 수 있어, 장기적인 지속적 홈 모니터링에는 적합하지 않습니다. 밀리미터파 레이더는 호흡과 심박수라는 두 가지 핵심 활성 징후를 비접촉 방식으로 직접 감지할 수 있으며, 거리 및 속도 측정을 통해 인간의 움직임 신호를 식별할 수 있습니다. 최근의 연구들은 PSG와 중간에서 높은 수준의 일치도를 보이는 레이더 기반 수면 단계 분석의 가능성을 입증했습니다2,3. 마찬가지로, 레이더로 도출한 심박 변이도(HRV)는 여러 연구에서 심전도(ECG)를 통해 검증되었으며, 시간 영역 및 주파수 영역 파라미터에서 수용 가능한 일치도를 보여주었습니다4,5. 레이더 기반의 호흡 사건 감지 및 무호흡-저호흡 지수(AHI) 추정도 탐색되었으며, PSG와 비교하여 0.8 이상의 상관관계가 보고되었습니다6,7. 그러나 수면 단계, 미세각성 지수 및 AHI와 같은 도출 파라미터는 직접 측정할 수 없으며, 추가적인 알고리즘 기반 추정과 PSG를 통한 검증이 필요합니다. 레이더 기반의 미세각성 감지는 수면 단계 분석 및 호흡 사건 모니터링에 비해 상대적으로 덜 발달된 상태입니다8.
인체의 생체 신호에 대한 밀리미터파 레이더 모니터링과 한의학(TCM) 수면 패턴 분류 이론을 바탕으로, 본 리뷰에서는 밀리미터파 레이더 기술과 한의학 수면 패턴 변증의 심층적인 통합을 탐구합니다. 본 연구의 목적은 레이더 기반 수면 모니터링의 현황을 요약하고, 레이더로 도출된 생리학적 파라미터와 일반적인 한의학 불면증 증후군 사이의 가능한 매핑 관계를 검토하며, 이러한 디지털 한의학 변증 접근 방식의 한계와 향후 방향을 논의하는 것입니다. 한의학 변증의 추상적인 개념을 레이더가 인식할 수 있는 객관적인 생리학적 파라미터로 변환함으로써, 본 연구는 이 분야의 추가 연구 및 임상 실무를 위한 실행 가능한 솔루션과 개념적 프레임워크를 제공합니다.
리뷰 및 관점
Theoretical mapping between millimeter-wave radar and TCM syndrome differentiation
Theoretical basis of TCM sleep pattern classification
Traditional Chinese medicine (TCM) classifies insomnia (Bu Mei) primarily into five pattern types: Liver Fire Disturbing the Heart pattern, Phlegm-Heat Harassing the Heart, Heart-Spleen Deficiency pattern, Heart-Kidney Non-Interaction pattern, and Heart-Gallbladder Qi Deficiency pattern9. The Lingshu · Kouwen states, “When yang qi is exhausted, and yin qi is abundant, the eyes close and sleep ensues; when yin qi is exhausted, and yang qi is abundant, one awakens.” Normal sleep depends on the dynamic balance in which yang qi enters yin. When this balance is disrupted—either yang hyperactivity preventing its entry into yin, or yin deficiency failing to contain yang—sleep disorders emerge. From the perspective of the nutrient (Ying) and defensive (Wei) qi theory, defensive qi exhibits a circadian rhythm: “During the day it circulates twenty-five times in the yang, and at night it circulates twenty-five times in the yin”10. The orderly alternation of defensive qi's day-night circulation forms the physiological foundation of the sleep-wake rhythm. Dysfunction of nutrient and defensive qi circulation leads to sleep disorders. Therefore, yin-yang disharmony constitutes the core pathogenesis of insomnia.
Theoretical framework of radar signals and TCM syndrome differentiation
Emotions, body movement frequency, and HRV
The close relationship between emotions and the autonomic nervous system is a fundamental consensus in physiological psychology. “Emotional restlessness” is pathophysiologically manifested as sympathetic excitation, leading to increased involuntary limb movements and decreased heart rate variability (HRV)11; radar-based body movement detection and HRV analysis can therefore indirectly quantify this state. From the perspective of TCM syndrome differentiation, Zhang et al.12 found that HRV time-domain and frequency-domain indices in patients with liver depression with phlegm obstruction pattern and liver depression with qi stagnation pattern were significantly lower than those in the normal control group (P < 0.01).
Respiration, respiratory rate, and respiratory variability
The bidirectional relationship between respiratory patterns and emotions has been widely confirmed by modern psychophysiology. For example, Jerath et al.13 pointed out that respiratory waveform spectra correlate with emotional states, and that respiration both reflects and regulates emotions bidirectionally. From the perspective of TCM theory, Tian et al.14 combined TCM emotional theory with millimeter-wave radar respiratory signal detection, systematically demonstrating the rationality and feasibility of using respiration as a digitized collection indicator for emotions.
Heart-spirit, qi, blood, and sleep medicine
The “hyperarousal” hypothesis of insomnia is the core theory explaining the pathological mechanisms of insomnia in contemporary sleep medicine. Wang et al.15 found that the primary mechanism underlying the onset and maintenance of insomnia is hyperarousal, manifested at three levels: cortical arousal, autonomic arousal, and somatic arousal. This provides the basis for mapping “heart-spirit restlessness → prolonged sleep latency and frequent microarousals” with the latter inferred from heart rate and body movement signals16. Specifically, cortical arousal can be quantified through electroencephalography, while somatic arousal manifests as an increase in body movement frequency17, providing the foundation for this mapping. Kuo et al.18 discovered that EEG beta power during non-rapid eye movement (NREM) sleep shows a significant positive correlation with the low-frequency/high-frequency (LF/HF) ratio, which reflects sympathetic-parasympathetic balance (r = 0.40 ± 0.06), and this coupling is even tighter than during rapid eye movement (REM) sleep. This implies that microarousals are accompanied by heart rate fluctuations and transient changes in autonomic state.
Regarding the association between the “Qi and Blood” dimension and heart rate and HRV, Zhang et al.19 pointed out that heart rate variability is an important objective indicator for evaluating autonomic nervous function, capable of reflecting the sleep status of insomnia patients. This provides a basis for inferring the state of qi and blood abundance or depletion through radar-monitored heart rate levels and HRV parameters by means of “assessing the interior through observation of the exterior”20.
Mapping logic between radar signals and TCM syndrome differentiation
Based on the framework, the following mapping logic can be established (Table 1). The core of this mapping logic is that the functional states within the dimensions of TCM syndrome differentiation can be operationally translated into parameters at the modern physiological level through millimeter-wave radar.
Furthermore, building upon the macroscopic mapping established in Table 1 and focusing specifically on the five major pattern types of insomnia, the core pathogenesis of each pattern can be further integrated with modern pathophysiological interpretations to derive a set of differentiating features that can be captured by radar (Table 2).
However, the content presented in Table 2 still constitutes qualitative feature descriptions at the pattern-type level and has not yet been transformed into specific numerical indicators that can be directly output by a radar signal processing pipeline. To automate pattern discrimination from raw radar data, these features must be converted into computable variables with defined calculation methods, time windows, and TCM associations. The next subsection will, toward this objective, define and extract the key features one by one.
Before detailing the feature extraction pipeline, it is crucial to clarify the hierarchical nature of the parameters discussed in this framework. We distinguish between two levels of signals: Level 1 comprises primary signals that are directly and robustly extractable from the raw millimeter-wave radar data through established physical principles (e.g., phase and range measurements). These include respiration rate and rhythm, heart rate, and body movement events. Level 2 comprises secondary, derived parameters that cannot be measured directly but are estimated from Level 1 signals using algorithmic models. These include sleep stages (N1, N2, N3, REM), microarousal indices, and the apnea-hypopnea index (AHI). The estimation of these parameters requires sophisticated signal processing and machine learning models, and their accuracy must be rigorously validated against gold-standard PSG data.
Multidimensional sleep feature extraction using millimeter-wave radar and its correlation with TCM pattern differentiation
Sleep architecture characteristics
The following sleep architecture features (F1–F4, F13) are derived parameters obtained from a sleep staging model that uses radar-based cardiorespiratory and movement signals as inputs. Recent radar-based sleep staging studies have reported Cohen’s kappa values ranging from approximately 0.5 to 0.7 for four-class (Wake, REM, Light sleep, Deep sleep) staging when compared with PSG21,22. Nevertheless, their accuracy depends on the model’s performance, population characteristics, and radar configuration, and still requires PSG validation in TCM-specific cohorts.
Sleep onset latency (F1) is defined as the interval from lights off to the first three continuous NREM epochs. It is a core indicator measuring the efficiency of “yang entering yin.” The Suwen · Zhi Zhen Yao Da Lun states, “All manic and agitated states are attributable to fire,” and the Jingyue Quanshu states, “When true yin, essence, and blood are insufficient, and yin and yang fail to interact, the spirit cannot rest peacefully in its abode.” Those with kidney yin deficiency and heart fire blazing alone also toss and turn, unable to sleep, because yin fails to constrain yang. Modern sleep medicine defines sleep onset latency >30 min as difficulty falling asleep23, which is highly consistent with the core chief complaints of the Liver Fire Disturbing the Heart pattern and Heart-Kidney Non-Interaction patterns24.
Sleep efficiency (F2) is the ratio of total sleep time to total time in bed. Decreased sleep efficiency can be observed in all types of insomnia, but the mechanisms differ: in Liver Fire Disturbing the Heart pattern and Heart Fire Flaming Upward types, difficulty falling asleep prolongs time in bed with insufficient effective sleep25; in Phlegm-Heat Harassing the Heart, sleep fragmentation leads to difficulty maintaining sleep26; in Heart-Spleen Deficiency pattern and Heart-Gallbladder Qi Deficiency, frequent dreaming and easy awakening accumulate wakefulness time27. Reed28 noted that sleep efficiency below 85% is one of the core diagnostic features of insomnia. Although this indicator is not specific to any one pattern, it is a basic parameter for evaluating overall sleep quality.
Deep sleep proportion (F3) is estimated as the percentage of N3 stage duration relative to total sleep time (TST). In TCM, N3 sleep is considered the time when “yang qi is most deeply stored.” The Lingshu · Ying Weis Shenghui states, “When ying qi is depleted and wei qi attacks internally, one is not alert during the day and cannot sleep at night.” Those with Heart-Spleen Deficiency pattern have insufficient qi and blood, the heart-spirit lacks nourishment, and deep sleep cannot accumulate; in Heart-Kidney Non-Interaction, yin fails to constrain yang, and deficiency fire disturbs internally, causing N3 to be frequently interrupted. Baglioni et al.29 demonstrated that primary insomnia patients exhibit sleep continuity disruption, with significant reductions in slow-wave sleep (SWS) and REM sleep30.
REM proportion (F4) reflects the integrity of rapid eye movement sleep. The Lei Jing says, “The hun is associated with dreamlike and trance-like states,” indicating that REM sleep is closely related to the liver's function of storing the hun31. In Heart-Gallbladder Qi Deficiency, due to timidity of gallbladder qi and loss of decisiveness, the spirit has no master, and REM sleep may be reduced due to proneness to startle. Baglioni et al.29 also confirmed a significant reduction in REM sleep in insomnia patients. Because the association between REM proportion and Heart-Gallbladder Qi Deficiency still requires more clinical evidence, it is marked as “possibly decreased (↓).” Although Table 2 also lists possible REM reduction under Heart-Kidney Non-Interaction, this should be interpreted as a secondary consequence of yin deficiency with fire hyperactivity and sleep fragmentation, rather than as a primary differentiating feature of that pattern.
Number of sleep-wake transitions (F13) is the total frequency of returning to stage wakefulness (W) from any sleep stage, serving as a direct indicator of sleep continuity. The Jingyue Quanshu describes Heart-Spleen Deficiency pattern as “sleep that is not sound, with frequent dreaming and easy awakening”32, and Heart-Gallbladder Qi Deficiency as “prone to fright and easily startled, with deficiency irritability and insomnia”33. The International Classification of Sleep Disorders, Third Edition (ICSD-3)23 uses the number of awakenings throughout the night as objective evidence for a sleep maintenance disorder. Frequent transitions to stage W are the digital representation of “frequent dreaming and easy awakening” and “easy to be startled and awakened”34, transforming the qualitative judgment of heart-spirit restlessness in TCM inspection into quantifiable temporal events.
Characteristics of autonomic function
Autonomic function characteristics, through quantitative analysis of heart rate and heart rate variability, reflect the functional states of “the heart governing the blood and vessels” and “the heart storing the spirit,” serving as a continuous extension of “pulse manifestation” information from TCM pulse palpation into the unconscious state during the night35.
Mean nocturnal heart rate (F5) is the average heart rate across the entire night. The Suwen · Wu Zang Sheng Cheng Pian states, “All blood belongs to the heart.” Heart rate, as the fundamental rhythm by which heart qi propels the circulation of blood, directly reflects the sufficiency or deficiency of qi and blood as well as the presence of heat. Shi et al.36 noted that in liver depression transforming into fire and Phlegm-Heat Harassing the Heart, the function of the sympathetic-adrenomedullary system is hyperactive; in yin deficiency with fire hyperactivity, sympathetic excitability is enhanced; and in Heart-Spleen Deficiency pattern, patients generally exhibit functional depression. Clinical studies have shown that patients with insomnia and liver depression who transform into fire tend to exhibit sympathetic hyperactivity37. Based on this, we hypothesize that the mean nocturnal heart rate in the Liver Fire Disturbing the Heart pattern may be elevated, corresponding to the TCM presentation of a ‘wiry and rapid pulse.’ Similarly, in the Heart-Spleen Deficiency pattern, deficiency of qi and blood may lead to weakened cardiac propulsion, and a relatively low nocturnal heart rate is inferred; however, direct radar-based evidence is lacking, and this association requires clinical validation.
Heart rate variability SDNN (F6) is the standard deviation of normal sinus R-R intervals, reflecting the overall regulatory capacity of the autonomic nervous system. Several groups have demonstrated that radar-based extraction of R-R intervals and subsequent HRV analysis can achieve close agreement with ECG-derived HRV in laboratory settings38,39, supporting the feasibility of using radar for continuous nocturnal autonomic assessment. Previous studies have reported reduced HRV in insomnia patients, particularly in those with liver depression-related patterns. Extrapolating these findings to radar-based monitoring, we propose that Liver Fire Disturbing the Heart pattern may be associated with decreased SDNN and RMSSD. However, this is a theoretical inference; whether radar-derived HRV parameters can replicate these findings in TCM-differentiated cohorts must be tested. A reduced SDNN value indicates diminished flexibility and adaptability of the autonomic nervous system, which aligns with the overall TCM pathogenesis of “yin-yang disharmony.” Chen et al.37 grouped insomnia patients by TCM pattern types for HRV analysis and found considerable differences in heart rate variability among the different patterns. Lin et al.40 indicated that HRV abnormalities in insomnia patients primarily manifest as decreased parasympathetic function and hyperactive sympathetic function.
Heart rate variability RMSSD (F7) is the root mean square of successive differences between adjacent R-R intervals, predominantly reflecting parasympathetic (vagal) activity. The Lingshu · Lun Yong states, “The cowardly person... has an insufficient and lax gallbladder.” In Heart-Gallbladder Qi Deficiency, insufficient gallbladder qi lowers the threshold for stress responses. The vagus nerve is a core pathway regulating the startle response, and a decrease in its activity implies a weakened buffering capacity against external stimuli. Dodds et al.41, in a systematic review, indicated that insomnia patients exhibit HRV impairment, including significantly reduced RMSSD and pNN50. Therefore, a decrease in RMSSD can be observed in the Heart-Gallbladder Qi Deficiency pattern, such that even minor disturbances can trigger awakenings.
Nocturnal heart rate variation trend (F14) takes the mean heart rate during the first hour after sleep onset as the baseline, calculates the change in mean heart rate hour by hour, and fits a linear slope. In healthy sleep, as yang qi enters yin, the heart rate exhibits a natural decreasing trend (dipper pattern). The Leizheng Zhicai states, “The heart governs fire, and the kidney governs water; only fire can control water, and only water can control fire.” In Heart-Kidney Non-Interaction, deficient kidney water fails to ascend and nourish heart fire, and deficiency fire floats internally without being stored, resulting in a persistently elevated nocturnal heart rate. Nano et al.42 noted abnormal nocturnal autonomic regulation in insomnia patients, with increased sympathetic activity and decreased vagal activity being typical manifestations of autonomic dysfunction in insomnia. This feature transforms the TCM pathogenesis of “yin deficiency with fire hyperactivity” into an objective description of the dynamic trend of nocturnal heart rate.
Respiratory characteristics
Respiratory characteristics, through the three dimensions of rate, rhythm, and abnormal events, provide a digital tool for assessing “breath” in TCM auscultation, and are particularly highly associated with the pathological mechanism of the Phlegm-Heat Harassing the Heart pattern.
Mean respiratory rate (F8) is the arithmetic mean of respiratory rate across the entire night. Jerath et al.13 pointed out that there is a bidirectional pathway between respiratory rhythm and autonomic regulation, and that the spectral characteristics of respiratory waveforms are closely related to various emotional states such as anxiety, anger, and stress. TCM holds that “the lung governs qi and manages respiration,” and that rapid breathing mostly belongs to heat or excess patterns. The Mai Jing states, “Heat causes rapid breathing.” When phlegm-heat accumulates internally, lung qi fails to diffuse, requiring an increased respiratory rate to compensate for the obstruction of the qi mechanism; thus, the mean respiratory rate may be elevated.
Respiratory rate coefficient of variation (F9) is the ratio of the standard deviation of respiratory rate to its mean, reflecting the stability of respiratory rhythm. When phlegm-dampness obstructs the lung and the airway is impeded, the respiratory center's response to blood gas changes becomes unstable, manifesting as alternating fast and slow breathing, rhythm disturbance, and an increased coefficient of variation. The Suwen · Bi Lun states, “In heart bi, the vessels are obstructed, with restlessness and palpitations below the heart, sudden upward qi and panting.” Those with Liver Fire Disturbing the Heart pattern may also experience shortness and irregularity of breath due to chest and hypochondriac distension; therefore, an increased respiratory coefficient of variation can also be observed.
Apnea-hypopnea index (F15) is the total number of apnea and hypopnea events per hour. The Suwen · Ni Diao Lun states, “Those who cannot lie flat and whose breathing is noisy are caused by the reverse of Yangming,” which highly corresponds to the modern concept of sleep apnea. In those with internal generation of phlegm-dampness, phlegm obstructs the airway, and airflow limitation is more likely to occur during muscle relaxation at night; hence, F15 is closely associated with the Phlegm-Heat Harassing the Heart pattern. As a derived parameter, the radar‑based AHI should be computed using a validated detection algorithm, and its performance must be benchmarked against PSG‑measured AHI before clinical application. One clinical study using PSG reported that patients with obstructive sleep apnea-hypopnea syndrome (OSAHS) classified as Phlegm-Heat pattern had significantly higher AHI and oxygen desaturation index than other TCM patterns. This provides indirect support for associating Phlegm-Heat Harassing the Heart with elevated AHI. However, whether radar-estimated AHI can replicate this association has not been investigated and must be prospectively validated43.
Body movement and behavioral characteristics
Body movement and behavioral characteristics transform the qualitative observations of limb restlessness and sleep-disrupting tossing and turning in TCM “inspection of the physical form” into automatically detectable quantitative events. Total body movement count (F10) and body movement index (F11) are the total number of body movement events across the entire night and the frequency per hour, respectively. The Mai Yao Jing Wei Lun states, “The five zang organs are the foundation of the body's strength.” Limb restlessness reflects internal disharmony among the zang-fu organs. In those with Liver Fire Disturbing the Heart pattern, “irritability and proneness to anger” may manifest during sleep as high-frequency, low-amplitude limb twitches and turning over44; in Phlegm-Heat Harassing the Heart, “tossing and turning without rest” is accompanied by frequent large-scale postural changes, and the classic statement in the Neijing that “when the stomach is not harmonized, sleep is restless” precisely describes the increased body movement associated with this pattern. The American Academy of Sleep Medicine (AASM) has published clinical practice guidelines45 clearly positioning actigraphy as an effective tool for objectively assessing sleep disorders. A body movement index >5 events/h indicates marked restlessness during sleep and can be regarded as the objective threshold for “sleep restlessness.”
Microarousal index (F12) is defined as the number of brief arousal events lasting 3–15 s per hour. Microarousals are electrophysiological markers of cortical arousal; although subtle, they are sufficient to disrupt sleep continuity. Cortical arousal, autonomic arousal, and somatic arousal together constitute the physiological basis of insomnia17. Increased microarousals have been reported in insomnia patients15,46. Based on the TCM pathogenesis of timidity and proneness to startle, we hypothesize that microarousal frequency may be particularly elevated in Heart-Gallbladder Qi Deficiency, but direct evidence for this specific pattern is lacking and remains to be validated. The Shen Shi Zun Sheng Shu states, “When the heart and gallbladder are fearful and timid, one is easily startled by events.” Such patients exhibit startle responses to even minor external stimuli, manifesting as an ultra-high density of microarousal events and extremely shallow and fragile sleep. This feature transforms the subjective description of “timidity and proneness to startle” into quantifiable neurophysiological events47,48. However, it is important to note that the microarousal index is a derived parameter that must be estimated from radar signals using specific detection algorithms and requires validation against PSG‑based arousal scoring.
Calculation methods for key TCM sleep features based on millimeter-wave radar
The design of multidimensional sleep features based on millimeter-wave radar follows the deductive logic of “pathogenesis → pathophysiological mapping → objective indicators.” Each feature is defined according to physiological principles and can be specified to meet the needs of TCM syndrome differentiation. In the following, the features are grouped by functional category into four sets—sleep architecture characteristics, autonomic function characteristics, respiratory characteristics, and body movement and behavioral characteristics—and their calculation methods and associations with TCM syndrome differentiation are elaborated (Table 3).
The features listed in Table 3 are calculated using the entire night as one statistical period. For multinight data collected continuously from each subject, in addition to calculating single-night features, it is also necessary to compute the multinight mean and the night-to-night coefficient of variation, so as to capture both the stable performance and the fluctuation characteristics of the pattern in the temporal dimension. Furthermore, some features can be further derived into secondary indicators. For example, the LF/HF ratio can be derived from F6 and F7 (requiring frequency-domain analysis support), and the ratio of deep sleep to REM sleep can be derived from F3 and F4, all of which provide a richer feature space for the subsequent pattern classification model. The overall framework of radar‑based TCM syndrome differentiation is summarized in Figure 1. The advantages of this grouping arrangement are twofold: Organizing features by functional category allows the extraction pipeline to naturally correspond to the signal processing modules. Each feature is explicitly annotated with its direction of association (increase or decrease) with TCM pattern types, providing an interpretable theoretical framework for input variable selection and feature importance analysis in subsequent machine learning models.
결론
Millimeter-wave radar enables non-contact, minimally intrusive conversion of three classical TCM diagnostic concepts—inspecting the physical form, observing the breath, and discerning movement—into continuous, quantitative physiological parameters. Building on this capability, a theoretical diagnostic pathway was proposed that warrants further clinical validation: from radar-derived features to pathophysiological mapping, and finally to pattern classification. This paper proposes a theoretical framework for how vital signs captured by radar may multi-dimensionally reflect the core pathogenic characteristics of the five major insomnia patterns. However, the proposed feature-pattern associations are not validated diagnostic thresholds; they are inferred from TCM pathogenesis and modern sleep physiology and require prospective validation in TCM-specific cohorts before clinical use. Nevertheless, practical limitations of radar monitoring include sensitivity to environmental motion, body position, and signal loss. These factors can reduce real-world reliability, underscoring the need for careful signal processing and quality assurance.
The objectivity underlying millimeter-wave radar-based sleep monitoring in relation to TCM pattern differentiation is manifested in three key aspects. First, non-intrusive, non-contact data acquisition eliminates subjective bias and avoids monitoring interference with the subject. Second, for primary signals (respiration, heart rate, and body movement), feature calculation grounded in the physical principles of radar ranging and phase discrimination ensures standardization and reproducibility. For derived parameters (sleep stages, microarousal index, AHI, and related sleep architecture metrics), standardized algorithms and rigorous validation against PSG are required before clinical interpretation. Third, a 15-parameter multidimensional feature space supports probabilistic pattern classification via machine learning, thereby circumventing the arbitrariness inherent to any single indicator. Thus, radar may serve as an adjunct extension of the four TCM diagnostic methods during sleep, but not as a standalone diagnostic tool.
Future work should include multicenter clinical validation in TCM-specific insomnia cohorts, multimodal integration with tongue and pulse diagnosis, interpretable machine learning, and longitudinal home-based monitoring. Although radar directly captures respiration, heart rate, and body movement, derived sleep metrics remain estimated parameters requiring algorithmic modeling and PSG validation before serving as TCM syndrome differentiation evidence.
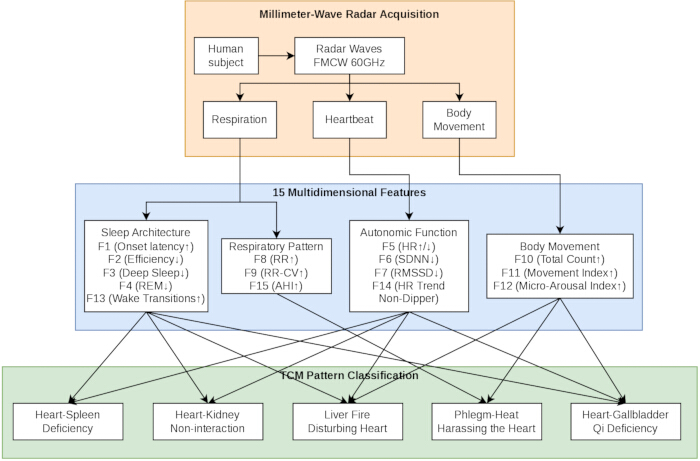
Figure 1: Overview of the millimeter‑wave radar-based TCM insomnia pattern differentiation framework. The diagram shows a three‑stage workflow: Top layer: non‑contact radar acquisition of respiration, heartbeat, and body movement. Frequency-modulated continuous wave (FMCW), a radar signal technology used here at 60 GHz. Middle layer: extraction of 15 features across four domains (sleep architecture, autonomic function, respiratory pattern, body movement). F4: REM = rapid eye movement, F5: HR = heart rate, F6: SDNN = standard deviation of normal-to-normal intervals, F7: RMSSD = root mean square of successive differences, F8: RR = respiratory rate, F9: RR-CV = coefficient of variation of respiratory rate, F15: AHI = apnea-hypopnea index. Bottom layer: mapping these features to the five major TCM insomnia patterns based on the pathogenesis‑physiology‑radar signal logic (Table 2 and Table 3). Please click here to view a larger version of this figure.
| TCM Syndrome Differentiation Dimension | Radar-Measurable Parameters | Mapping Logic |
| Emotion (Restlessness / Calmness) | Body movement frequency, number of turns, HRV | Restlessness and agitation → high-frequency body movements, low HRV |
| Breathing (Coarse / Fine / Rapid / Stable) | Respiratory rate, respiratory depth variability | Coarse and rapid breathing → high respiratory rate, high variability |
| Heart-Spirit (Calm / Disturbed) | Sleep latency, number of micro-arousals | Heart-spirit restlessness → prolonged sleep latency, frequent micro-arousals |
| Qi and Blood (Sufficiency / Deficiency) | Heart rate level, heart rate variability (HRV) | Qi deficiency may present altered HRV; direction requires clinical validation |
Table 1: Mapping logic between TCM syndrome differentiation dimensions and millimeter-wave radar. The table defines how four TCM dimensions (emotion, breathing, heart‑spirit, qi‑blood) are translated into radar‑measurable parameters and quantitative mapping logic, providing the theoretical foundation for non‑contact objective sleep assessment. HRV = heart rate variability.
| TCM Pattern Type | Core Pathogenesis | Modern Pathophysiological Mapping | Differentiating Features in Millimeter-Wave Signals |
| Liver Fire Disturbing the Heart | Liver depression transforming into fire; heat disturbs the heart-spirit | Sympathetic excitation | (1) Prolonged sleep latency (increased duration of stage W); (2) Elevated mean nocturnal heart rate; (3) Decreased heart rate variability (HRV), impaired autonomic regulation; (4) Increased high-frequency, low-amplitude body movement events; frequent body movements during stage W; |
| Phlegm-Heat Harassing the Heart | Phlegm-dampness accumulation, depression transforming into heat, disturbing the heart-spirit | Sleep fragmentation | (1) Elevated micro-arousal index, increased N1 stage proportion, marked sleep fragmentation; (2) Irregular respiratory pattern, increased coefficient of variation of respiratory rate; (3) Frequent large-scale body movements, increased postural changes; |
| Heart-Spleen Deficiency | Excessive rumination, insufficient generation of qi and blood, heart-spirit deprived of nourishment | Qi and blood insufficiency | (1) Low mean nocturnal heart rate; (2) Increased proportion of light sleep (N1/N2 stages), reduced deep sleep; (3) Increased number of NREM-REM and sleep-wake stage transitions, reflecting dream-disturbed and easily interrupted sleep; |
| Heart-Kidney Non-Interaction | Kidney yin deficiency, heart fire blazing alone, heart and kidney failing to coordinate | Yin deficiency with fire hyperactivity | (1) Prolonged sleep latency (increased duration of stage W); (2) Nocturnal heart rate sustained at high levels with considerable fluctuation, displaying a non-dipper pattern; (3) Significantly reduced proportion of N3 deep sleep; REM proportion may be secondarily reduced or variable; |
| Heart-Gallbladder Qi Deficiency | Heart and gallbladder qi deficiency, loss of decisiveness, spirit lacking a master | Timidity and proneness to startle | (1) Heightened sensitivity to external environmental disturbances, startle responses with abrupt jerks, decreased arousal threshold during N1 stage; (2) Frequent micro-arousal events, increased intermittent transitions from N1 and N2 to wakefulness, extremely shallow and fragile sleep; (3) Prolonged wake after sleep onset (WASO), difficulty returning to sleep after awakening; (4) REM proportion may be reduced; |
Table 2: Differentiating feature set of the five TCM insomnia pattern types based on millimeter-wave radar. The table maps each of the five insomnia patterns to its core TCM pathogenesis, modern pathophysiological interpretation, and specific radar‑derived differentiating features (sleep latency, heart rate/HRV, respiratory pattern, body movements, micro‑arousals, and sleep architecture). This provides the feature‑level foundation for objective pattern classification. Features such as sleep latency, sleep-stage proportions, microarousal index, sleep fragmentation, and WASO are derived/estimated parameters requiring validated algorithms and PSG benchmarking; other features such as heart rate, HRV, respiratory rate/pattern, and body movement indices are primary or simple statistical features obtained from radar signals. Abbreviations (American Academy of Sleep Medicine sleep staging) are defined as: W = wakefulness; N1 = non-rapid eye movement Stage 1; N2 = non-rapid eye movement Stage 2; N3 = non-rapid eye movement Stage 3; REM = rapid eye movement; WASO = wake after sleep onset.
| Feature No. | Feature Name | Signal Type | Calculation Method | TCM Syndrome Differentiation Association |
| F1 | Sleep onset latency | Derived | Interval from "lights off" to the first continuous three NREM epochs | Liver Fire Disturbing the Heart ↑, Heart-Kidney Non-Interaction ↑ |
| F2 | Sleep efficiency | Derived | Total sleep time / Total time in bed × 100% | May decrease in all patterns |
| F3 | Deep sleep proportion | Derived | N3 duration / Total sleep time × 100% | Heart-Spleen Deficiency ↓, Heart-Kidney Non-Interaction ↓ |
| F4 | REM proportion | Derived | REM duration / Total sleep time × 100% | Heart-Gallbladder Qi Deficiency may ↓ (primary); Heart-Kidney Non-Interaction may also ↓ (secondary/non-specific) |
| F5 | Mean nocturnal heart rate | Primary | Mean heart rate across the entire night (bpm) | Liver Fire Disturbing the Heart ↑, Heart-Spleen Deficiency ↓ |
| F6 | Heart rate variability SDNN | Primary | Standard deviation of normal sinus R-R intervals (ms) | Liver Fire Disturbing the Heart ↓, Heart-Spleen Deficiency normal/variable (inconclusive) |
| F7 | Heart rate variability RMSSD | Primary | Root mean square of successive R-R interval differences (ms) | Reflects parasympathetic activity; Heart-Gallbladder Qi Deficiency ↓ |
| F8 | Mean respiratory rate | Primary | Mean respiratory rate across the entire night (breaths/min) | Phlegm-Heat Harassing the Heart may ↑ |
| F9 | Respiratory rate coefficient of variation | Primary | Standard deviation of respiratory rate / Mean | Phlegm-Heat Harassing the Heart ↑, Liver Fire Disturbing the Heart ↑ |
| F10 | Total body movement count | Primary | Total number of limb movement events across the night | Liver Fire Disturbing the Heart ↑, Phlegm-Heat Harassing the Heart ↑ |
| F11 | Body movement index | Primary | Number of body movement events per hour | >5 events/h indicates sleep restlessness |
| F12 | Micro-arousal index | Derived | Number of micro-arousal events per hour (brief arousals of 3–15 seconds) | May increase in all patterns; especially prominent in Heart-Gallbladder Qi Deficiency pattern |
| F13 | Number of sleep–wake transitions | Derived | Number of transitions from any sleep stage back to Wake | Heart-Spleen Deficiency ↑, Heart-Gallbladder Qi Deficiency ↑ |
| F14 | Nocturnal heart rate variation trend | Primary | Heart rate slope from sleep onset to awakening | Heart-Kidney Non-Interaction (nocturnal heart rate fails to decline) |
| F15 | Apnea–hypopnea index (AHI) | Derived | Number of apnea + hypopnea events per hour | Phlegm-Heat Harassing the Heart may ↑ |
Table 3: Millimeter-wave radar-based multidimensional sleep feature extraction and its association with TCM syndrome differentiation. The table categorizes features into primary signals (directly extracted from radar) and derived/estimated parameters (calculated via algorithmic models). Arrows (↑/↓) indicate the expected direction of change for each feature in the corresponding TCM pattern. Here, “Primary” indicates parameters directly extractable from radar signals or computed via simple statistics; “Derived” indicates parameters that require algorithmic modeling (e.g., sleep staging, event detection) and must be validated against polysomnography (PSG). NREM = Non‑Rapid Eye Movement; R-R = R‑Wave to R‑Wave interval (the time between successive R‑wave peaks on the ECG, representing the cardiac cycle length). For Heart-Spleen Deficiency, no consistent HRV pattern has been established in the current literature; SDNN may remain within the normal range or show only mild variability. This label indicates uncertainty.
공개 사항
저자들은 공개할 이해관계 충돌이 없습니다.
감사의 글
본 연구는 중국 국가자연과학재단(General Program, Grant No. 82374576), 지역 대학 및 대학 역량 강화 프로그램, 상하이시 과학기술위원회(Grant No. 23010504900), 그리고 Shanghai Rongtai Health Technology Co., Ltd.와의 협력 프로젝트인 “밀리미터파 레이더 기반 생체 신호 수집 장치 설계 및 수면 질 평가 모델 구축”(Grant No. E4‑H2411399)의 지원을 받아 수행되었습니다.
참고문헌
- Chen B, et al. Thoughts on traditional Chinese medicine syndrome differentiation and treatment of sleep disorders based on the “one principle, four aspects” theory. Space Med Med Eng. 2025;36:337–42.
- Mohammadjany A, Miar-Naimi H. High-gain Vivaldi-enhanced FMCW radar for robust through-wall human and object detection. Sens Imaging. 2025;26:148.
- Qu K, Wei L, Zhang R. Noncontact cardiac activity detection based on single-channel ISM band FMCW radar. Biosensors (Basel). 2023;13(11):982.
- Cui R, Cui W, Cai Y, Yan Y. Non-contact reconstruction of ECG signals using FMCW radar and SS-S2SA network. IEICE Trans Commun. 2025;E108-B:208–19.
- Toda D, et al. ECG signal reconstruction using FMCW radar and a convolutional neural network for contactless vital-sign sensing. IEICE Trans Commun. 2023;E106-B:65–73.
- Yue S, et al. BodyCompass. Proc ACM Interact Mob Wearable Ubiquitous Technol. 2020;4(2):1–25.
- Sun L, Wang W, Wang Y, Guo W, Chen Z, Zeng J, Zhang J, Li G, Lei W, Yue H. Validation of a low-load monitoring system based on millimeter-wave radar and pulse oximetry vs. polysomnography for obstructive sleep apnea diagnosis[J]. Sleep Health, 2025; 11(6): 868–876.
- Hao Z, et al. mmWave-RM: a respiration monitoring and pattern classification system based on mmWave radar. Sensors (Basel). 2024;24(13):4315.
- Li GD, Hu XY, Yuan Y, Meng XJ, Huang YT, Cao HJ. Is traditional Chinese medicine syndrome differentiation important in primary insomnia? An exploratory review with matching recombination indirect comparisons and network meta-analysis[J]. European Journal of Integrative Medicine, 2025.
- Li ZH, et al. Traditional Chinese medicine syndrome study of 1,006 patients with early-morning awakening insomnia based on factor analysis and cluster analysis. Chin J Inf Tradit Chin Med. 2026.
- Kreibig SD. Autonomic nervous system activity in emotion: a review. Biol Psychol. 2010;84(3):394–421.
- Zhang Q, et al. Characteristics of heart rate variability in patients with anxiety and depression of different traditional Chinese medicine syndrome types. J Med Res. 2008;37:77–80.
- Jerath R, Beveridge C. Respiratory rhythm, autonomic modulation, and the spectrum of emotions: the future of emotion recognition and modulation. Front Psychol. 2020;11:1980.
- Tian Y, et al. Scientific analysis of traditional Chinese medicine emotional data based on millimeter-wave radar. Chin Arch Tradit Chin Med. 2025;43.
- Wang R, Tang JY. Research progress on the relationship between insomnia and microarousal. Acta Acad Med Sin. 2021;43(6):945–9.
- Zhang C, Xiao LL, Liu DQ, Wang Y. Research progress in traditional Chinese medicine treatment of short-term insomnia from the perspective of heart and spleen. J Hebei North Univ Nat Sci Ed. 2026;42(1):62–4.
- Bonnet MH, Arand DL. Hyperarousal and insomnia: state of the science. Sleep Med Rev. 2010;14(1):9–15.
- Kuo TBJ, Chen CY, Hsu YC, Yang CCH. EEG beta power and heart rate variability describe the association between cortical and autonomic arousals across sleep. Auton Neurosci. 2016;194:32–7.
- Zhang XN, et al. Research progress on insomnia and heart rate variability. J Psychiatry. 2025;38(2):205–8.
- Bao F, et al. Effect of Chaihu Longgu Muli Decoction combined with wrist-ankle acupuncture on traditional Chinese medicine syndrome scores, sleep quality, and negative emotions in patients with insomnia of liver depression transforming into fire type. Prog Mod Biomed. 2026;26(5):714–9.
- Park J, Yang S, Chung G, et al. Ultra-Wideband Radar-Based Sleep Stage Classification in Smartphone Using an End-to-End Deep Learning[J]. IEEE Access, 2024.
- Kwon HB, Choi SH, Lee D, et al. Attention-Based LSTM for Non-Contact Sleep Stage Classification Using IR-UWB Radar[J]. IEEE Journal of Biomedical and Health Informatics, 2021, 25(10): 3844-3853.
- Sateia MJ. International classification of sleep disorders, third edition: highlights and modifications. Chest. 2014;146(5):1387–94.
- National Key R&D Program Project Group on “New TCM Diagnosis and Treatment Scheme and Mechanism Research for Chronic Insomnia”, et al. Expert consensus on traditional Chinese medicine diagnosis and treatment of adult chronic insomnia. China J Tradit Chin Med Pharm. 2026;41(3):524–8.
- Ding HR, et al. Correlation between anxiety, depression, and traditional Chinese medicine constitution in young and middle-aged patients with insomnia. China Med Her. 2026;23(1):45–50.
- Wang TS, Xue PL. Discussion on traditional Chinese medicine syndrome differentiation and treatment of insomnia based on endogenous “five pathogenic factors”. Jiangsu J Tradit Chin Med. 2026;58(1):27–30.
- Li PH, Ding J, Han Y. Diagnosis, treatment, and management of insomnia from the perspective of traditional Chinese medicine. Shanghai Med J. 2025;48(12):799–802.
- Reed DL, Sacco WP. Measuring sleep efficiency: what should the denominator be? J Clin Sleep Med. 2016;12(2):263–6.
- Baglioni C, et al. Sleep changes in the disorder of insomnia: a meta-analysis of polysomnographic studies. Sleep Med Rev. 2014;18(3):195–213.
- Deng JH, et al. Research progress on traditional Chinese medicine therapies and mechanisms of action for insomnia. J Liaoning Univ Tradit Chin Med. 2025.
- Peng B, Xu SJ, Gao Y. Research progress on treatment of insomnia based on traditional Chinese medicine time rhythm. Guid J Tradit Chin Med Pharm. 2025;31(10):114–9.
- Liu HX. Effect of comprehensive auricular acupoint therapy combined with traditional Chinese medicine emotional nursing on insomnia in hypertensive patients with liver yang hyperactivity. Chin J Health Care. 2025;43(2):134–7.
- Wang S, Yang YC, Ju BZ. Discussion on traditional Chinese medicine pathogenesis and treatment of insomnia based on “yang not entering yin”. J Chronic Dis Integr Tradit Chin West Med. 2025;2(4):44–8.
- Liu CH, Yao D, Wang JM, Li TB. Discussion on the relationship of yin-yang and qi-blood between melasma and insomnia and the idea of treating different diseases with the same method based on traditional Chinese medicine theory. World J Sleep Med. 2025;12(6):1669–73.
- Yuan Y, et al. Discussion on the “three spirits simultaneous regulation” method for treating heart-spleen deficiency insomnia based on the “body-qi-spirit” theory. J Liaoning Univ Tradit Chin Med. 2026.
- Shi HX, Fu WN. The importance of correct syndrome differentiation viewed from the relationship between insomnia syndrome differentiation and autonomic nervous function [conference presentation]. Presented at: 11th Academic Annual Conference of the Psychiatric Disease Committee of the Chinese Association of Integrative Medicine; 2012.
- Chen TG, Li HY, Guo CJ, Sun SC. Analysis of heart rate variability differences in insomnia patients with different traditional Chinese medicine syndrome types. World J Sleep Med. 2017;4:202–205.
- Lee Y, Lee K, Ahmed S, Cho SH. Feasibility of early assessment for psychological distress: HRV-based evaluation using IR-UWB radar. Sensors (Basel). 2024;24(19):6210.
- Yu G, et al. Non-contact seismocardiogram measurement and HRV analysis using cardiac beamforming with FMCW radar. Front Physiol. 2025;16:1733573.
- Lin WT, et al. Research progress on heart rate variability and insomnia and its non-pharmacological treatment. Chin J Nerv Ment Dis. 2024;50(2):123–8.
- Dodds KL, et al. Heart rate variability in insomnia patients: a critical review of the literature. Sleep Med Rev. 2017;33:88–100.
- Nano MM, Fonseca P, Vullings R, Aarts RM. Measures of cardiovascular autonomic activity in insomnia disorder: a systematic review. PLoS One. 2017;12(10):e0186716.
- Zhang Y, et al. Clinical characteristics of 180 patients with obstructive sleep apnea hypopnea syndrome. Chin J Integr Med Cardio-Cerebrovasc Dis. 2015;13(5):575–7.
- Li ZH, et al. Discussion on Polygala tenuifolia in treating insomnia of kidney failing to store will based on “calming kidney will”. Acta Chin Med Pharmacol. 2026;54(3):39–42.
- Smith MT, et al. Use of actigraphy for the evaluation of sleep disorders and circadian rhythm sleep-wake disorders: an American Academy of Sleep Medicine clinical practice guideline. J Clin Sleep Med. 2018;14(7):1231–7.
- Ghermezian A, Nami M, Shalbaf R, Khosrowabadi R, Nasehi M, Kamali AM. Sleep micro-macro-structures in psychophysiological insomnia: PSG study[J]. Sleep and Vigilance, 2023:1–9.
- Deng DQ, et al. Discussion on construction of the “sleep medicine” specialty system based on experience of treating insomnia from “triple energizer qi transformation”. China Med Her. 2026;23(10):121–7.
- Song YW, Zhong GH. Experience of treating insomnia based on “three differentiations in one”. China Mod Dr. 2026;64(1):81–3.