This cross-sectional study of 4,010 elderly patients in Guangzhou (2022–2024) found that Haemophilus influenzae was the predominant pathogen detected by Loop-Mediated Isothermal Amplification (LAMP), with Gram-negative bacilli predominating. Pathogen distribution varied significantly by gender, age, season, specimen type, and department, supporting tailored clinical management and infection control strategies.
연구 논문
Pathogen Spectrum and Epidemiological Characteristics Detected by Multiplex Loop-Mediated Isothermal Amplification in Elderly Patients in Guangzhou
* These authors contributed equally
이 논문에서
요약
초록
Lower respiratory tract infections (LRTIs) contribute substantially to morbidity and mortality in the elderly. This study aimed to investigate the distribution and epidemiological features of 10 common respiratory pathogens detected by multiplex Loop-Mediated Isothermal Amplification (LAMP) in elderly patients in Guangzhou, China, from 2022 to 2024, to support precise clinical management, rational antimicrobial use, and regional infection control. A cross-sectional study was performed, enrolling 4,010 elderly patients who underwent respiratory pathogen testing by multiplex LAMP from April 2022 to March 2024 at Guangdong Provincial People’s Hospital. Multiplex LAMP was used to detect 10 major pathogens. Epidemiological characteristics were analyzed across genders, ages, seasons, months, specimen types, and departments. At least one pathogen was detected in 1,474 (36.76%) patients. Single detection was dominant (72.18%, 1,064/1,474). The detection rates of Haemophilus influenzae, Klebsiella pneumoniae, Pseudomonas aeruginosa, Acinetobacter baumannii, Staphylococcus aureus, Stenotrophomonas maltophilia, Escherichia coli, Streptococcus pneumoniae, Mycobacterium tuberculosis complex, and Mycoplasma pneumoniae were 11.40%, 10.75%, 8.10%, 5.89%, 5.41%, 3.02%, 2.66%, 2.64%, 0.56%, and 0.33%, respectively. The detection rates of Kpn and Mtb were significantly higher in males (P < 0.05). Significant age-group differences were observed for Sau, Eco, Pae, Aba, and Sma (P < 0.001) and for Kpn (P = 0.028). Kpn and Pae showed significant seasonal variation (P < 0.05). Pae positivity peaked in April 2022 (36.54%). Significant differences across specimen types and departments were observed for several pathogens (P < 0.05). Haemophilus influenzae was the most prevalent pathogen detected by multiplex LAMP in this elderly cohort in Guangzhou. Single-pathogen detection was the predominant pattern. These findings provide a basis for empirical antimicrobial therapy and regional epidemiological surveillance in elderly patients undergoing respiratory pathogen testing.
서론
Lower respiratory tract infections (LRTIs) remain a major global public health challenge and one of the leading causes of death across all age groups1. According to the Global Burden of Disease 2021 Study, LRTIs ranked as the seventh leading cause of death worldwide, imposing a heavy socioeconomic burden2. The etiology of LRTIs is complex, with bacteria as the predominant pathogens, followed by viruses, mycoplasma, chlamydia, and fungi3. Early and accurate pathogen identification helps optimize antimicrobial therapy, shorten hospital stays, and reduce medical costs4. The distribution of respiratory pathogens is influenced by host factors (e.g., age, gender, immune status) and environmental factors (e.g., season, climate, geographic region). In elderly populations, advanced age and comorbidities are associated with a higher prevalence of drug-resistant and opportunistic Gram-negative bacilli. Seasonal variation has also been documented for several bacterial pathogens, with warm and humid conditions potentially favoring the environmental survival of Pseudomonas aeruginosa and Klebsiella pneumoniae. In addition, pathogen detection rates may differ by specimen types due to variations in sample origin and quality. The elderly population is characterized by declining immune function and frequent comorbidities, leading to higher susceptibility to LRTIs and increased risk of severe illness and mortality5. Epidemiological evidence indicates that, influenced by multiple factors such as geographical environment and climatic characteristics, the epidemiological patterns of respiratory pathogens exhibit significant variations across different regions6,7. Regional epidemiological data are critical for developing targeted prevention and control strategies.
Guangzhou boasts a developed economy, dense population, and a warm, humid climate. These factors may collectively influence the transmission and distribution of pathogens8. However, systematic studies on the pathogen spectrum of elderly patients undergoing respiratory pathogen testing in this region remain limited, especially those simultaneously covering common bacteria, mycobacteria, and atypical pathogens. Existing regional data are largely derived from small cohorts or conventional culture-based methods with limited pathogen coverage, and none have comprehensively delineated the multi-dimensional epidemiological characteristics of respiratory pathogens in this population using a large-scale multiplex molecular approach. To our knowledge, this is the first study in South China to employ multiplex loop-mediated isothermal amplification (LAMP) in a cohort of 4,010 elderly patients undergoing respiratory pathogen testing to simultaneously profile the distribution, detection patterns, and epidemiological characteristics by genders, ages, seasons, specimen types, and departments of 10 key respiratory pathogens, including Mycobacterium tuberculosis complex and atypical bacteria. By filling this evidence gap, our findings advance existing knowledge by providing high-resolution, region-specific epidemiological data that support precise clinical management and targeted infection control for elderly patients with LRTIs in warm, humid subtropical regions.
프로토콜
The study was reviewed and approved by the Ethics Review Committee of Guangdong Provincial People’s Hospital (Approval Number: KY2025-1310-01). Given the retrospective nature of this study and the use of de-identified laboratory data, the requirement for informed consent was waived by the Ethics Review Committee.
Study design and participants
A cross-sectional study was conducted at Guangdong Provincial People's Hospital, a tertiary hospital in Guangzhou. A total of 4,010 unique elderly patients (both inpatients and outpatients) who underwent respiratory pathogen testing by multiplex LAMP between April 2022 and March 2024 were consecutively included, with only the first eligible specimen per patient retained (all repeat specimens from the same patient were excluded regardless of time interval). Consequently, the dataset comprises 4,010 specimens from 4,010 unique patients. This was a retrospective, laboratory information system (LIS)-based epidemiological analysis.
Epidemiological stratification: To characterize the full epidemiological profile, positive rates were analyzed by gender, age, season, month, specimen type, and department. Departmental information was retrieved from the LIS and categorized as respiratory wards/clinics, intensive care units (ICU), and other departments. Clinical diagnosis was not systematically analyzed because the diagnostic information captured in the LIS was frequently nonspecific or represented patients' chronic comorbidities rather than the specific classification of the acute respiratory infection (e.g., recorded as “pneumonia” without distinction between community-acquired and hospital-acquired etiology). Consequently, reliable classification into CAP, HAP, or HCAP was not feasible.
Patients were stratified into four age groups: 60–69 years (n = 1,874), 70–79 years (n = 1,236), 80–89 years (n = 577), and ≥90 years (n = 323). By genders: 2,844 males and 1,166 females. By seasons: spring (March–May, n = 956), summer (June–August, n = 878), autumn (September–November, n = 988), winter (December–February, n = 1,188). By specimen types: sputum (n = 2,642), bronchoalveolar lavage fluid (BALF, n = 421), irrigation fluid (n = 882), and others (n = 65). By departments: respiratory wards/clinics (n = 1,640), intensive care units (ICU, n = 1,132), and other departments (n = 1,238).
Inclusion criteria were: age ≥60 years; respiratory specimen submitted for multiplex LAMP testing at the Department of Laboratory Medicine; and complete demographic information (age and gender) available in the LIS.
Exclusion criteria were: repeat specimens from the same patient (only the first eligible specimen was retained, regardless of time interval); incomplete demographic records; and specimens failing laboratory quality control.
Detection scope
In this study, not all patients underwent comprehensive testing for the 10 pathogens; such testing was performed based on clinical indications. As a result, the denominator (total number of tests performed) varies depending on the pathogen and is listed separately for each pathogen. These findings reflect the epidemiological distribution of the pathogens identified through multiplex LAMP testing in elderly patients with suspected lower respiratory tract infections.
Specimen collection, processing, and preservation
Sputum, bronchial washing fluid, and bronchoalveolar lavage fluid (BALF) specimens were collected following standard clinical protocols9. Morning sputum was preferred, and specimens were obtained before antimicrobial administration whenever possible. For sputum specimens, patients were instructed to rinse their mouths with clean water, take a deep breath, and cough forcefully to expectorate deep respiratory tract secretions into a sterile collection container. Bronchial washing fluid (irrigation fluid) and BALF were collected during bronchoscopy, typically performed in patients with suspected deep lung infections, inadequate sputum specimens, or when non-infectious pulmonary conditions (e.g., malignancy, interstitial lung disease) required exclusion.
Specimen quality control was performed prior to nucleic acid extraction. Sputum specimens were screened by Gram staining to assess quality, with specimens containing <10 squamous epithelial cells and >25 leukocytes per low-power field considered acceptable. Lower respiratory tract secretion specimens were liquefied by adding an equal volume of 4% Sodium hydroxide (NaOH) and incubating at 37 °C for 30 min; for viscous specimens, additional NaOH was added, and the liquefaction time was extended until the sample was completely liquefied without solid or filamentous material.
Nucleic acid extraction was performed using the Nucleic Acid Extraction Reagent following the manufacturer's instructions. Briefly, 1 mL of the liquefied specimen was transferred to a 1.5 mL sterile centrifuge tube and centrifuged at 15,777 g for 5 min. The supernatant was discarded, and 1 mL of wash solution was added to resuspend the precipitate. After thorough vortexing, the mixture was centrifuged again at 15,777 g for 5 min, and the supernatant was completely removed. Subsequently, 50–100 µL of nucleic acid extraction solution was added to the precipitate, vortexed thoroughly, and incubated at 95 °C for 5 min. The mixture was then centrifuged at 15,777 g for 5 min, and the supernatant containing the extracted nucleic acid was transferred to a clean centrifuge tube and stored at -20 °C for subsequent detection. Extracted nucleic acids should ideally be tested immediately; if not possible, storage at -20 °C should not exceed 2 months, and repeated freeze-thaw cycles should be avoided.
Specimens for nucleic acid detection were processed immediately upon receipt. Fresh specimens could be stored at 4 °C for no longer than a week, while DNA samples could be stored at -20 °C for ≤2 months.
Pathogen detection
Pathogen detection was performed using the Respiratory Pathogen Nucleic Acid Detection Kit (isothermal amplification microfluidic chip method) on the Isothermal Amplification Nucleic Acid Analyzer, with the assay conducted on a microfluidic disk chip.
Target pathogens included Streptococcus pneumoniae (Spn), Staphylococcus aureus (Sau), Escherichia coli (Eco), Klebsiella pneumoniae (Kpn), Pseudomonas aeruginosa (Pae), Acinetobacter baumannii (Aba), Stenotrophomonas maltophilia (Sma), Haemophilus influenzae (Hin), Mycobacterium tuberculosis complex (Mtb), and Mycoplasma pneumoniae (Mpn).
Detection principle
This assay employs multiplex LAMP technology combined with microfluidic chip technology. Each microfluidic chip contains 24 reaction chambers, with specific primers embedded in designated reaction chambers for each target pathogen. The 24 reaction chambers comprised 10 pathogen-target chambers, 1 positive external control, 1 positive internal control, 9 negative-control chambers, and 3 blank chambers. The amplification reaction relies on Bst Deoxyribonucleic Acid (DNA) polymerase with strand displacement activity, which catalyzes the synthesis of large amounts of new DNA strands using specially designed primers targeting six distinct regions of the target gene at a constant temperature of 65 °C. EvaGreen fluorescent dye was incorporated into the reaction system; in its free state, the dye forms aggregates that do not fluoresce upon excitation. When bound to double-stranded DNA, the dye intercalates and emits strong fluorescence upon excitation, with fluorescence intensity proportional to the amount of amplified product. A positive result was indicated by the detection of an “S”-shaped amplification curve in the corresponding reaction chamber.
Assay procedure
The isothermal amplification reaction system was prepared by adding 20 µL of isothermal amplification reagent and 34.5 µL of template DNA (or control) to a 200 µL centrifuge tube, with thorough mixing by vortexing and brief centrifugation. The microfluidic chip was equilibrated to room temperature, and 50 µL of the prepared reaction mixture was loaded onto the chip via the sample inlet using a pipette. After the main channel was completely filled, a sealing film was applied to the inlet and outlet, and the film was pressed firmly with a clean pipette tip in one direction to ensure tight adhesion. The loaded chip was then centrifuged at 3,944 g for 30 s to distribute the sample evenly into the reaction chambers.
Prior to detection, the analyzer was powered on, and the light source was preheated for 10 min. Click the "Unload" button to steadily place the chip cover upward onto the pallet; ensure that the pallet's central positioning device aligns with the large central hole of the chip, and insert the pallet positioning cylinder through the central notch of the chip to secure it. Then, click the "Load" button to load the chip into the nucleic acid analyzer. Sample information was entered into the application control software, including chip number, sample number, and sample type. Detection was initiated by clicking the “Start Detection” button. The instrument automatically executed the preset temperature program: preheating at 37 °C for 3 min, followed by isothermal amplification at 65 °C for 47 min. During the reaction, the instrument rotated the microfluidic chip via a stepper motor, sequentially passing each reaction chamber through the optical detection port, and collected real-time fluorescence signals using a confocal spatial filtering method. Fluorescence data were transmitted to the computer workstation in real-time via an Ethernet connection, and the software automatically generated amplification curves and performed qualitative result interpretation.
Quality control
Each chip contained one manufacturer-supplied positive external control containing a yeast-derived target and the corresponding primers, one positive internal control (human-specific primers), and nine negative controls. A valid test required: positive external control showing a positive result; positive internal control showing a positive result (or negative if human genomic DNA content was low, indicating insufficient cell number); and all negative controls showing negative results. If any of these criteria were not met, the test was considered invalid and was repeated.
Result interpretation
The software automatically analyzed the fluorescence data using the maximum second derivative method combined with other algorithms to calculate the Tp value (positive time) for each target. The Tp value was defined as the time difference between the first inflection point of the “S”-shaped amplification curve (indicating entry into the rapid amplification phase) and the origin. For valid results, a “+” indicated detection of the target pathogen, while a “−” indicated non-detection. The lower limit of detection for this assay was 5×10² copies/reaction.
Statistical analysis
Statistical analysis was performed using Statistical Package for the Social Sciences (SPSS) software. Categorical data were presented as counts and percentages. The 95% confidence intervals (95% CIs) for positive rates were calculated using the Wald method via the Ratios procedure in SPSS. When the expected frequency in all cells was ≥5, the Pearson χ2 test results were reported. For 2×2 tables with an expected frequency <5, the continuity-corrected χ² test was used; for tables larger than 2×2 with cells of expected frequency <5, Fisher's exact probability method was employed, with P < 0.05 considered statistically significant.
결과
Representative results of the multiplex LAMP assay on the microfluidic disk chip
Representative microfluidic chip readouts demonstrating successful implementation of the multiplex LAMP assay are shown in Figure 1. In all valid panels, the purple curve represents the positive external control (yeast genes and primers), and the blue curve represents the positive internal control (human-specific primers). Valid controls amplified normally. The Eco target (green) showed clear positive amplification, slightly later than the external control. All other targets and blanks remained negative. External and internal controls were valid. The Hin target (red) exhibited a delayed but distinct positive curve. Non-target chambers stayed flat. External and internal controls were valid. The Pae target (yellow) amplified earlier, followed by Kpn (gray). All other targets were negative. External and internal controls amplified correctly. All pathogen targets, negative controls, and blanks remained at baseline with no amplification. Neither external nor internal control showed amplification; all curves stayed at baseline. Despite negative controls being flat, the failed positive control rendered the assay invalid (Figure 1).
Overall positive rates of respiratory pathogens among elderly patients
The positivity rates of Hin, Kpn, Pae, Aba, Sau, Sma, Eco, Spn, Mtb, and Mpn were 11.40% (95% CI: 10.41–12.38%), 10.75% (95% CI: 9.79–11.71%), 8.10% (95% CI: 7.26–8.95%), 5.89% (95% CI: 5.16–6.61%), 5.41% (95% CI: 4.71–6.11%), 3.02% (95% CI: 2.49–3.55%), 2.66% (95% CI: 2.16–3.16%), 2.64% (95% CI: 2.15–3.14%), 0.56% (95% CI: 0.32–0.79%), and 0.33% (95% CI: 0.15–0.51%), respectively. Hin exhibited the highest detection rate, followed by Kpn and Pae; Mtb and Mpn showed the lowest rates (Table 1).
The total number of tests varied depending on the pathogen, as not all patients were tested for the full 10-respiratory-tract-pathogen testing panel. Eco, Mtb, and Mpn were tested in 3,952 patients, whereas the remaining seven pathogens were tested in all 4,010 patients.
Positive rates stratified by genders, ages, seasons, specimen types, and departments
The positivity rates for Kpn and Mtb showed statistically significant differences between genders (P < 0.05), with male patients exhibiting a significantly higher positivity rate than females.
The positivity rates for Sau, Eco, Kpn, Pae, Aba, and Sma showed statistically significant differences across the four age groups (60–69,70–79,80–89, and ≥90 years), as detailed in Table 2. For Sau, statistically significant differences were observed between the 60–69 and 80–89 age groups (χ2 = 9.772, P = 0.002), between the 60–69 and ≥90 age groups (χ2 = 28.873, P < 0.001), and between the 70–79 and ≥90 age groups (χ2 = 20.466, P < 0.001). For Eco, statistically significant differences were noted between the 60–69 and 80–89 age groups (χ2 = 8.013, P = 0.005), between the 60–69 and ≥90 age groups (χ2 = 21.719, P < 0.001), and between the 70–79 and ≥90 age groups (χ2 = 12.191, P < 0.001). For Kpn, significant overall differences were observed across age groups (P < 0.05). For Pae, statistically significant differences were observed between the 60–69 and 80–89 age groups (χ2 = 11.743, P < 0.001), between the 60–69 and ≥90 age groups (χ2 = 23.772, P < 0.001), and between the 70–79 and ≥90 age groups (χ2 = 12.966, P < 0.001). For Aba, statistical differences were observed between the groups 60–69 and 80-89 (χ2 = 15.933, P < 0.001), as well as between groups 60–69 and ≥90 (χ2 = 7.956, P = 0.005). Similarly, statistical differences were found for Sma between groups 60–69 and 80–89 (χ2 = 11.366, P < 0.001) and between groups 60–69 and ≥90 (χ2 = 11.231, P < 0.001).
Statistical differences were observed between Kpn in spring and autumn (χ2 = 9.693, P = 0.002), summer and winter (χ2 = 7.688, P = 0.006), and autumn and winter (χ2 = 12.807, P < 0.001). Similarly, statistical differences were observed between Pae in summer and winter (χ2 = 11.133, P < 0.001).
There were statistically significant differences in the detection rates of Sau in sputum specimens, BALF, and irrigation fluid (χ2 = 9.156/14.743, P = 0.002/P < 0.001). Similarly, Eco showed statistically significant differences in detection rates in sputum specimens and irrigation fluid (χ2 = 20.804, P < 0.001), as well as in irrigation fluid specimens compared to other specimens (χ2 = 7.376, P = 0.007). Kpn exhibited statistically significant differences in detection rates across sputum specimens, BALF, and irrigation fluid (χ2 = 11.137/14.549, all P < 0.001). Pae demonstrated statistically significant differences in detection rates across sputum specimens, BALF, and irrigation fluid (χ2 = 11.995/27.548, all P < 0.001). Aba showed statistically significant differences in detection rates across sputum specimens, BALF, and irrigation fluid (χ2 = 20.261/40.115, all P < 0.001). Sma exhibited statistically significant differences in detection rates across sputum specimens, BALF, and irrigation fluid (χ2 = 8.445/20.691, P = 0.004/P < 0.001). Hin also demonstrated statistically significant differences in detection rates across sputum specimens, BALF, and irrigation fluid (χ2 = 30.207/20.274, all P < 0.001). Mtb showed statistically significant differences in detection rates across sputum specimens and BALF (χ2 = 26.275, P < 0.001), as well as in BALF and irrigation fluid (χ2 = 8.077, P = 0.004).
There were statistically significant differences in the detection rates of Sau in respiratory wards /clinics, ICU, respiratory wards/clinics, and other departments (χ2 = 11.574/35.944, both P < 0.001). There were statistically significant differences in the detection rates of Eco in respiratory wards /clinics, ICU, respiratory wards/clinics, and other departments (χ2 = 16.408/26.678, both P < 0.001). There were statistically significant differences in the detection rates of Kpn in respiratory wards /clinics, ICU, respiratory wards/clinics, and other departments (χ2 = 29.526/29.229, both P < 0.001). There were statistically significant differences in the detection rates of Pae in respiratory wards /clinics, ICU, respiratory wards/clinics, and other departments (χ2 = 35.377/29.086, both P < 0.001). There were statistically significant differences in the detection rates of Aba in respiratory wards /clinics, ICU, respiratory wards/clinics, and other departments (χ2 = 34.723/37.413, both P < 0.001). There were statistically significant differences in the detection rates of Sma in respiratory wards /clinics, and ICU, respiratory wards/clinics, and other departments, ICU, and other departments (χ2 = 35.033/9.450/7.424, P < 0.001/P = 0.002/P = 0.006). There were statistically significant differences in the detection rates of Hin in respiratory wards /clinics, and ICU, respiratory wards/clinics, and other departments, ICU, and other departments (χ2 = 6.296/39.521/61.712, P = 0.012/P < 0.001/P < 0.001). There were statistically significant differences in the detection rates of Mtb in respiratory wards /clinics and the ICU (χ2 = 6.577, P = 0.010). For Mpn, significant overall differences were observed across department groups (P < 0.05).
Monthly variation in pathogen detection among elderly patients, April 2022–March 2024
Spn exhibited the highest positivity rate in December 2022, reaching 6.25% (6/96). Sau showed the highest positivity rate in April 2022, at 17.31% (9/52). Eco recorded the highest positivity rate in October 2022, at 5.15% (7/136). Kpn achieved the highest positivity rate in August 2022, at 19.00% (19/100). Pae demonstrated the highest positivity rate in April 2022, at 36.54% (19/52). Aba recorded the highest positivity rate in January 2023, at 11.00% (22/200). Sma exhibited the highest positivity rate in April 2022, at 9.62% (5/52). Hin achieved the highest positivity rate in March 2024, at 20.60% (55/267). The overall positivity rates for Mtb and Mpn were relatively low (Figure 2).
Single-pathogen detection and multiple-pathogen detection patterns
Among the 4,010 patients, 1,474 (36.76%) tested positive for at least one pathogen. Single-pathogen detection was the predominant pattern, accounting for 72.18% (1,064/1,474 positive patients), with Hin being the most common single pathogen (320 patients), followed by Kpn (198 patients) and Pae (169 patients). Multiple-pathogen detection accounted for 27.82% (410/1,474), comprising 283 double detections, 107 triple detections, and 20 quadruple or higher-order detections. The most frequent co-detection pattern was Kpn plus Hin (43 patients). Notably, the combination of Kpn, Pae, and Sma was the predominant triple-pathogen pattern (13 patients), and Kpn plus Pae plus Aba plus Sma was the most common quadruple detection (5 patients) (Table 3).
Conclusion
In this large-scale retrospective analysis of 4,010 elderly patients undergoing respiratory pathogen testing in Guangzhou, multiplex LAMP detected at least one pathogen in 36.76% of patients, with single-pathogen detection as the predominant pattern. Haemophilus influenzae was the most prevalent pathogen, while Enterobacteriaceae and non-fermentative Gram-negative bacilli (NFGNB) (Klebsiella pneumoniae, Pseudomonas aeruginosa, and Acinetobacter baumannii) collectively accounted for approximately 25%. Pathogen distribution varied significantly by gender, age, season, specimen type, and department. These findings provide high-resolution, region-specific epidemiological evidence to inform empirical antimicrobial therapy and targeted infection control strategies for elderly populations in subtropical regions.
Data Availability:
All raw data supporting the findings of this study are submitted along with the manuscript. Due to restrictions imposed by the Ethics Review Committee of Guangdong Provincial People's Hospital (Approval Number: KY2025-1310-01) and the sensitive nature of individual patient clinical information, the individual-level raw data cannot be made publicly available. Requests for de-identified individual-level data may be directed to the corresponding author and will be reviewed by the Ethics Review Committee.
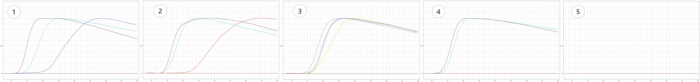
Figure 1: Representative results of the multiplex LAMP assay on the microfluidic disk chip. In all panels, the purple curve indicates the positive external control (yeast genes and primers), the blue curve indicates the positive internal control (human-specific primers), and the remaining colored curves represent individual target pathogens. (1) Single-pathogen detection of Escherichia coli (Eco, green) with valid external and internal controls. (2) Single-pathogen detection of Haemophilus influenzae (Hin, red) with valid external and internal controls. (3) Double-pathogen detection of Pseudomonas aeruginosa (Pae, yellow) and Klebsiella pneumoniae (Kpn, gray) with valid external and internal controls. (4) Valid negative result with correct amplification of external and internal controls and no amplification in any target chamber. (5) Invalid result due to external control failure (all curves flat, including purple external control and blue internal control), necessitating repeat testing. The x-axis represents reaction time (min); the y-axis represents relative fluorescence intensity. Please click here to view a larger version of this figure.
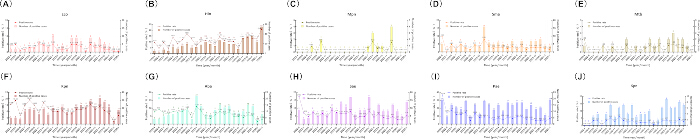
Figure 2: Monthly variation in pathogen detection among elderly patients, April 2022–March 2024. (A–J) display the temporal distribution for each pathogen. (A) Escherichia coli (Eco), (B) Haemophilus influenzae (Hin), (C) Mycoplasma pneumoniae (Mpn), (D) Stenotrophomonas maltophilia (Sma), (E) Mycobacterium tuberculosis complex (Mtb), (F) Klebsiella pneumoniae (Kpn), (G) Acinetobacter baumannii (Aba), (H) Staphylococcus aureus (Sau), (I) Pseudomonas aeruginosa (Pae), and (J) Streptococcus pneumoniae (Spn). In each panel, the x-axis indicates the month of specimen collection; the left y-axis represents the positive rate (%); and the right y-axis represents the number of positive patients. Colored bars show the number of positive patients per month; the colored line with markers shows the corresponding monthly positive rate (%). Please click here to view a larger version of this figure.
| pathogens | denominator | positive | positive rate (%) | negative | negative rate (%) | 95% CI (%) |
| Spn | 4010 | 106 | 2.64 | 3904 | 97.36 | 2.15–3.14 |
| Sau | 4010 | 217 | 5.41 | 3793 | 94.59 | 4.71–6.11 |
| Eco | 3952 | 105 | 2.66 | 3847 | 97.34 | 2.16–3.16 |
| Kpn | 4010 | 431 | 10.75 | 3579 | 89.25 | 9.79–11.71 |
| Pae | 4010 | 325 | 8.10 | 3685 | 91.90 | 7.26–8.95 |
| Aba | 4010 | 236 | 5.89 | 3774 | 94.11 | 5.16–6.61 |
| Sma | 4010 | 121 | 3.02 | 3889 | 96.98 | 2.49–3.55 |
| Hin | 4010 | 457 | 11.40 | 3553 | 88.60 | 10.41–12.38 |
| Mtb | 3952 | 22 | 0.56 | 3930 | 99.44 | 0.32–0.79 |
| Mpn | 3952 | 13 | 0.33 | 3939 | 99.67 | 0.15–0.51 |
Table 1: Overall positive rates of respiratory pathogens among elderly patients. Data are presented as the total number tested (denominator), the number of positive patients, the positive rate (%), the number of negative patients, the negative rate (%), and the 95% confidence interval (95% CI). Abbreviations: Spn = Streptococcus pneumoniae; Sau = Staphylococcus aureus; Eco = Escherichia coli; Kpn = Klebsiella pneumoniae; Pae = Pseudomonas aeruginosa; Aba = Acinetobacter baumannii; Sma, Stenotrophomonas maltophilia; Hin = Haemophilus influenzae; Mtb = Mycobacterium tuberculosis complex; Mpn = Mycoplasma pneumoniae.
| Items | Spn | Sau | Eco | Kpn | Pae | Aba | Sma | Hin | Mtb | Mpn | |
| genders | |||||||||||
| male | 82 (2.88) | 143 (5.03) | 78 (2.78) | 337 (11.85) | 228 (8.02) | 172 (6.05) | 91 (3.20) | 334 (11.74) | 20 (0.71) | 10 (0.36) | |
| female | 24 (2.06) | 74 (6.35) | 27 (2.36) | 94 (8.06) | 97 (8.32) | 64 (5.49) | 30 (2.57) | 123 (10.55) | 2 (0.17) | 3 (0.26) | |
| χ² | 2.187 | 2.808 | 0.565 | 12.368 | 0.101 | 0.466 | 1.110 | 1.170 | 4.258 | 0.027 | |
| P | 0.139 | 0.094 | 0.452 | <0.001 | 0.750 | 0.495 | 0.292 | 0.279 | 0.039 | 0.869 | |
| age groups | |||||||||||
| 60–69 | 55 (2.93) | 79 (4.22) | 34 (1.84) | 187 (9.98) | 121 (6.46) | 82 (4.38) | 39 (2.08) | 213 (11.37) | 9 (0.49) | 8 (0.43) | |
| 70–79 | 30 (2.43) | 58 (4.69) | 29 (2.38) | 123 (9.95) | 96 (7.77) | 78 (6.31) | 38 (3.07) | 156 (12.62) | 6 (0.49) | 4 (0.33) | |
| 80–89 | 12 (2.08) | 43 (7.45) | 22 (3.89) | 75 (13) | 62 (10.75) | 50 (8.67) | 27 (4.68) | 56 (9.71) | 6 (1.06) | 1 (0.18) | |
| ≥90 | 9 (2.79) | 37 (11.46) | 20 (6.23) | 46 (14.24) | 46 (14.24) | 26 (8.05) | 17 (5.26) | 32 (9.91) | 1 (0.31) | 0 (0) | |
| χ² | 1.581 | 34.228 | 24.285 | 9.129 | 28.756 | 18.898 | 16.640 | 4.182 | 2.758 | 1.126 | |
| P | 0.664 | <0.001 | <0.001 | 0.028 | <0.001 | <0.001 | <0.001 | 0.242 | 0.410 | 0.789 | |
| seasons | |||||||||||
| spring | 21 (2.20) | 58 (6.07) | 20 (2.23) | 86 (9.00) | 80 (8.37) | 42 (4.39) | 25 (2.62) | 120 (12.55) | 3 (0.33) | 0 (0) | |
| summer | 17 (1.94) | 51 (5.81) | 23 (2.62) | 109 (12.41) | 89 (10.14) | 63 (7.18) | 25 (2.85) | 96 (10.93) | 6 (0.68) | 5 (0.57) | |
| autumn | 31 (3.14) | 52 (5.26) | 37 (3.74) | 133 (13.46) | 83 (8.40) | 59 (5.97) | 27 (2.73) | 104 (10.53) | 6 (0.61) | 4 (0.40) | |
| winter | 37 (3.11) | 56 (4.71) | 25 (2.10) | 103 (8.67) | 73 (6.14) | 72 (6.06) | 44 (3.70) | 137 (11.53) | 7 (0.59) | 4 (0.34) | |
| χ² | 4.410 | 2.245 | 6.571 | 18.533 | 11.200 | 6.560 | 2.801 | 2.213 | 1.208 | 5.313 | |
| P | 0.220 | 0.523 | 0.087 | <0.001 | 0.011 | 0.087 | 0.423 | 0.529 | 0.770 | 0.131 | |
| specimen types | |||||||||||
| sputum | 74 (2.80) | 176 (6.66) | 91 (3.50) | 331 (12.53) | 265 (10.03) | 211 (7.99) | 107 (4.05) | 365 (13.82) | 8 (0.31) | 5 (0.19) | |
| bronchoalveolar lavage fluid | 8 (1.90) | 12 (2.85) | 6 (1.43) | 29 (6.89) | 20 (4.75) | 8 (1.90) | 5 (1.19) | 18 (4.28) | 10 (2.39) | 1 (0.24) | |
| irrigation fluid | 23 (2.61) | 28 (3.17) | 5 (0.57) | 69 (7.82) | 38 (4.31) | 17 (1.93) | 8 (0.91) | 71 (8.05) | 4 (0.46) | 7 (0.80) | |
| others | 1 (1.54) | 1 (1.54) | 3 (4.62) | 2 (3.08) | 2 (3.08) | 0 (0) | 1 (1.54) | 3 (4.62) | 0 (0) | 0 (0) | |
| χ² | 0.998 | 24.719 | 30.413 | 27.121 | 38.785 | 71.450 | 31.675 | 49.192 | 18.179 | 6.482 | |
| P | 0.795 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | 0.065 | |
| departments | |||||||||||
| respiratory wards and clinics | 38 (2.32) | 51 (3.11) | 18 (1.11) | 117 (7.13) | 79 (4.82) | 48 (2.93) | 23 (1.40) | 159 (9.70) | 16 (0.99) | 10 (0.62) | |
| intensive care units | 27 (2.39) | 65 (5.74) | 37 (3.32) | 151 (13.34) | 122 (10.78) | 89 (7.86) | 60 (5.30) | 79 (6.98) | 2 (0.180) | 1 (0.090) | |
| others | 41 (3.31) | 101 (8.16) | 50 (4.11) | 163 (13.17) | 124 (10.02) | 99 (8.00) | 38 (3.07) | 219 (17.69) | 4 (0.33) | 2 (0.16) | |
| χ² | 3.121 | 35.465 | 26.784 | 37.798 | 40.730 | 43.867 | 34.788 | 75.137 | 9.427 | 6.111 | |
| P | 0.210 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | <0.001 | 0.009 | 0.048 | |
Table 2: Positive rates stratified by genders, ages, seasons, specimen types, and departments. Data are presented as n (%). The total number of patients for each characteristic is as follows: male (n = 2,844), female (n = 1,166); age 60–69 years (n = 1,874), 70–79 years (n = 1,236), 80–89 years (n = 577), ≥90 years (n=323); spring (n = 956), summer (n = 878), autumn (n = 988), winter (n = 1,188); sputum (n = 2,642), bronchoalveolar lavage fluid (n = 421), irrigation fluid (n = 882), others (n = 65); respiratory wards/clinics (n = 1,640), intensive care units (ICU, n = 1,132), and other departments (n = 1,238). P < 0.05 was considered statistically significant. For Eco, Mtb, and Mpn, percentages were calculated using the number of patients actually tested for each pathogen within the corresponding subgroup; these denominators were therefore slightly lower than the total subgroup sizes shown above. Abbreviations: Spn = Streptococcus pneumoniae; Sau = Staphylococcus aureus; Eco = Escherichia coli; Kpn = Klebsiella pneumoniae; Pae = Pseudomonas aeruginosa; Aba = Acinetobacter baumannii; Sma = Stenotrophomonas maltophilia; Hin = Haemophilus influenzae; Mtb = Mycobacterium tuberculosis complex; Mpn = Mycoplasma pneumoniae.
| Single-pathogen detection | n | Double-pathogen detection | n | Triple-pathogen detection | n | Quadruple- and quintuple-pathogen detection | n |
| Aba | 106 | Aba+Hin | 5 | Eco+Aba+Hin | 1 | Eco+Kpn+Aba+Sma | 3 |
| Eco | 52 | Aba+Sma | 9 | Eco+Aba+Sma | 2 | Eco+Kpn+Pae+Aba | 1 |
| Hin | 320 | Eco+Aba | 6 | Eco+Kpn+Aba | 6 | Eco+Pae+Aba+Sma | 1 |
| Kpn | 198 | Eco+Hin | 3 | Eco+Kpn+Pae | 2 | Kpn+Pae+Aba+Sma | 5 |
| Mpn | 11 | Eco+Kpn | 13 | Eco+Pae+Aba | 1 | Sau+Eco+Kpn+Pae | 2 |
| Mtb | 17 | Eco+Pae | 2 | Eco+Pae+Hin | 1 | Sau+Kpn+Aba+Sma | 1 |
| Pae | 169 | Hin+Mpn | 1 | Eco+Pae+Sma | 1 | Sau+Kpn+Pae+Aba | 3 |
| Sma | 35 | Hin+Mtb | 2 | Kpn+Aba+Hin | 6 | Spn+Kpn+Aba+Hin | 1 |
| Sau | 106 | Kpn+Aba | 27 | Kpn+Aba+Sma | 3 | Spn+Sau+Kpn+Hin | 1 |
| Spn | 50 | Kpn+Hin | 43 | Kpn+Pae+Aba | 12 | Sau+Kpn+Pae+Aba+Sma | 1 |
| Kpn+Mtb | 2 | Kpn+Pae+Hin | 4 | Spn+Sau+Kpn+Aba+Sma | 1 | ||
| Kpn+Pae | 22 | Kpn+Pae+Sma | 13 | ||||
| Kpn+Sma | 10 | Pae+Aba+Hin | 2 | ||||
| Pae+Aba | 9 | Pae+Aba+Sma | 3 | ||||
| Pae+Hin | 9 | Sau+Aba+Hin | 1 | ||||
| Pae+Mtb | 1 | Sau+Aba+Sma | 1 | ||||
| Pae+Sma | 20 | Sau+Eco+Hin | 2 | ||||
| Sma+Hin | 2 | Sau+Eco+Kpn | 2 | ||||
| Sau+Aba | 9 | Sau+Kpn+Aba | 3 | ||||
| Sau+Eco | 3 | Sau+Kpn+Hin | 6 | ||||
| Sau+Hin | 14 | Sau+Kpn+Pae | 8 | ||||
| Sau+Kpn | 14 | Sau+Pae+Aba | 5 | ||||
| Sau+Pae | 16 | Sau+Pae+Hin | 1 | ||||
| Sau+Sma | 7 | Sau+Pae+Sma | 2 | ||||
| Spn+Aba | 1 | Spn+Kpn+Hin | 6 | ||||
| Spn+Eco | 1 | Spn+Kpn+Mpn | 1 | ||||
| Spn+Hin | 19 | Spn+Kpn+Pae | 3 | ||||
| Spn+Kpn | 8 | Spn+Pae+Hin | 1 | ||||
| Spn+Pae | 4 | Spn+Sma+Hin | 1 | ||||
| Spn+Sau | 1 | Spn+Sau+Aba | 1 | ||||
| Spn+Sau+Hin | 5 | ||||||
| Spn+Sau+Pae | 1 |
Table 3: Single-pathogen detection and multiple-pathogen detection patterns. Of 4,010 patients, 1,474 (36.76%) were positive for at least one pathogen. Single-pathogen detection was defined as the detection of only one target pathogen; multiple-pathogen detection was defined as the detection of two or more target pathogens. Abbreviations: Spn = Streptococcus pneumoniae; Sau = Staphylococcus aureus; Eco = Escherichia coli; Kpn = Klebsiella pneumoniae; Pae = Pseudomonas aeruginosa; Aba = Acinetobacter baumannii; Sma = Stenotrophomonas maltophilia; Hin = Haemophilus influenzae; Mtb = Mycobacterium tuberculosis complex; Mpn = Mycoplasma pneumoniae.
토론
This study aimed to determine the prevalence of pathogens associated with lower respiratory tract infections in our hospital. Between 2022 and 2024, a total of 4,010 patients were analyzed, among whom pathogens were detected in 1,474 patients (36.76%). Recently published articles indicate that the positivity rate is similar to that reported in this study10. In this study, Haemophilus influenzae ranked first with a detection rate of 11.4%, a finding that differs from many studies focusing on adult or full-age population community-acquired pneumonia. Traditional concepts and certain domestic guidelines indicate that Streptococcus pneumoniae is the most common bacterial pathogen causing community-acquired pneumonia (CAP) and the leading cause of death from lower respiratory tract infections11. However, the findings of this study are consistent with recent research results on elderly hospitalized patients. Multiple domestic and international studies have demonstrated that in elderly patients with underlying conditions such as chronic obstructive pulmonary disease (COPD), Hin is a significant pathogen causing lower respiratory tract infections, with clinical manifestations including pneumonia and acute exacerbations of chronic respiratory diseases12. The likely reason is that Hin is a common colonizing bacterium in the oropharynx. In elderly populations, compromised immune function and impaired respiratory defense mechanisms (e.g., reduced mucociliary clearance and diminished cough reflex), coupled with the use of medical devices (such as inhalation devices), increase the risk of its transition from colonization to infection13. This finding suggests that in the empirical treatment of elderly patients in the Guangzhou region, adequate attention should be paid to antimicrobial regimens covering Hin.
Furthermore, the combined detection rates of Enterobacteriaceae and NFGNB such as Kpn, Pae, and Aba reached approximately 25%, significantly higher than that of Spn (2.64%) and Mpn (0.33%). Although Spn, Mpn, and Hin are frequently implicated in community-acquired pneumonia and Kpn, Pae, and Aba are commonly associated with hospital-acquired pneumonia in the literature14, we could not reliably classify detections as community-acquired versus hospital-/healthcare-associated from the available clinical data. Therefore, we refrain from inferring the source of infection based solely on pathogen identity, and the high prevalence of Gram-negative bacilli in this cohort should be interpreted cautiously. This finding is consistent with global and Chinese epidemiological trends regarding the shift of infectious pathogens in elderly hospitalized patients toward Gram-negative bacilli15, particularly multidrug-resistant strains (e.g., Kpn, Aba)16. The detection rate of Kpn is higher in males than in females (11.85% vs. 8.06%)17, which may be attributed to certain risk factors associated with respiratory infections, such as smoking, alcohol consumption, and COPD. Significant differences were observed in the detection rates of Sau and various Gram-negative bacilli across different age groups. The positivity rate increased rapidly with advancing age, being particularly high among individuals aged 90 and above. Advanced age, comorbidities, prolonged hospital stays, and frequent invasive procedures are the primary risk factors for infections caused by drug-resistant and opportunistic pathogens18,19. These findings may support differentiated infection-risk assessment and pathogen consideration in elderly patients with varying degrees of frailty.
The detection rates of Kpn and Pae exhibit seasonal variations, typically being higher during summer and autumn, which aligns with the seasonal trends in Gram-negative bacillus infections observed in several studies. A retrospective study analyzing 8,746 sputum specimens collected between 2008 and 2019 found that the isolation frequencies of Pae and Kpn in hospitalized patients' sputum specimens were significantly higher during summer and autumn compared to winter and spring. The study confirmed a positive correlation between the monthly average temperature and the isolation frequencies of Pae (r = 0.2198, p = 0.0081) and Kpn (r = 0.3443, p = 0.00002), as well as a positive correlation between humidity and the Kpn isolation rate (r = 0.2602, p = 0.0016)20. The warm and humid environment may facilitate the survival and spread of these bacteria in both environmental settings and medical devices, suggesting that hospital infection prevention and control measures should be seasonally tailored and intensified21. Significant differences in pathogen detection rates were observed across specimen types. Sputum specimens showed significantly higher positivity rates for the most common respiratory pathogens. The lower detection rates in bronchoalveolar lavage fluid and irrigation fluid may reflect, in part, that bronchoscopic specimens were obtained from a more heterogeneous patient population—including patients undergoing evaluation for non-infectious pulmonary conditions. This heterogeneity should be considered when interpreting these findings. Among the specimen types analyzed, sputum showed higher positivity rates for several common respiratory pathogens. Nevertheless, in patients with severe or deep lung infections where sputum is unobtainable, these specimens remain essential for targeted pathogen detection.
Significant differences in pathogen detection rates were observed across care settings. Notably, the detection rates of Sau, Eco, Kpn, Pae, Aba, and Sma were markedly higher in ICU patients compared with respiratory wards/clinics, whereas Hin showed the highest positivity in respiratory wards/clinics, reflecting the distinct pathogen profiles between critically ill ICU patients and general respiratory inpatients. The detection rates of Mtb and Mpn were relatively low. However, the former was more frequently detected in males (0.71% vs. 0.17%), which may be attributed to differences in exposure history, social behavior, occupational risks, and healthcare-seeking behaviors. Based on a case-control study from the National Tuberculosis Epidemiological Survey in Vietnam, the adjusted odds ratio for males compared to females was 3.0 [95% CI 1.7–5.0]22. The low detection rate of the latter in the elderly population aligns with its age distribution characteristics; however, elderly patients often present with atypical symptoms and exhibit low diagnostic sensitivity, necessitating vigilance against its potential role as an atypical pathogen causing cluster outbreaks in enclosed settings (e.g., nursing homes, hospitals)23. Additionally, while the departments of patients were analyzed, clinical diagnosis could not be reliably categorized into community-acquired versus hospital-acquired infection due to incomplete and nonspecific diagnostic entries in the LIS. This limits our ability to correlate pathogen profiles with specific clinical syndromes.
In this study, 72.18% (1,064/1,474) of the patients had single-pathogen detection, while 27.82% had multiple-pathogen detection. Single-pathogen detection was the predominant detection pattern, consistent with literature reports. A large retrospective study involving 1,703 hospitalized patients with community-acquired pneumonia with identified pathogens found that multiple-pathogen detection accounted for 14% of patients with identified pathogens (single-pathogen detection accounted for 86%)24. These findings suggest that identification of a predominant pathogen may be useful in the diagnostic evaluation of non-severe elderly outpatients or general inpatients.
This study has several limitations. Firstly, it is a single-center cross-sectional study primarily reflecting the situation of a large general hospital, resulting in relatively limited generalizability of the findings. Secondly, reliance on nucleic acid amplification testing, while improving detection rates, cannot distinguish between colonization and infection, a fundamental limitation of molecular detection methods25. Thirdly, this study was limited to the 10 pathogens covered by the multiplex LAMP panel and did not include common respiratory viruses, fungi, or other bacterial species. Consequently, the true prevalence of polymicrobial infections involving viral or fungal pathogens may be underestimated, and the observed bacterial predominance reflects the scope of the assay rather than the complete etiological spectrum of respiratory infections in this population. Fourthly, this study was a retrospective analysis of laboratory testing data from both inpatients and outpatients, rather than a clinically defined cohort of patients with confirmed LRTI. Because patients were selected based on clinician-ordered LAMP testing, the study population may not be representative of the broader elderly LRTI population. Clinician ordering patterns, driven by disease severity, comorbidity burden, and local practice habits, introduce selection bias that limits the generalizability of our findings to all elderly patients with lower respiratory tract infections. The inclusion of outpatients and the lack of systematic clinical information (e.g., definitive diagnosis classification) limit the ability to distinguish between community-acquired and hospital-acquired infection. Moreover, because the 10-target panel was not uniformly applied to all patients, the denominators differ across pathogens, and comparisons of absolute detection rates should be interpreted with caution.
In summary, this study elucidated the positive rate distribution and comparative characteristics of 10 respiratory pathogens among 4,010 elderly patients in the Guangzhou region, providing robust support for developing more precise and effective prevention and control strategies. Future research should integrate clinical diagnosis, microbial culture, and antimicrobial susceptibility testing to conduct more comprehensive investigations and further elucidate the pathogenesis of respiratory infections in elderly patients, with the aim of achieving more targeted and effective prevention and treatment strategies.
공개 사항
The authors declare no conflict of interest. No artificial intelligence (AI) tools were used in the preparation of this manuscript or its figures.
감사의 글
The authors thank the staff of the Department of Laboratory Medicine at Guangdong Provincial People's Hospital for their technical support and assistance in specimen processing.
재료
| 이름 | 회사 | 카탈로그 번호 | 댓글 |
|---|---|---|---|
| 4% Sodium hydroxide (NaOH) solution | User-prepared / Hospital pharmacy | https://www.macklin.cn/products/S817977 | For liquefaction of viscous respiratory specimens. |
| Centrifuge (capable of 12,000 rpm / 15,777 × g and 6,000 rpm / 3,944 × g) | Thermo Scientific | https://www.thermofisher.cn/cn/zh/home/life-science/lab-equipment/lab-centrifuges/models/gp-standard-centrifuges.html | For specimen processing |
| Microfluidic disk chips | Provided with Respiratory Pathogen Detection Kit (302010) | https://www.capitalbiotech.com/product/6/%E8%AF%95%E5%89%82%E7%9B%92/%E6%84%9F%E6%9F%93%E6%80%A7%E7%96%BE%E7%97%85.html | 24 reaction chambers per chip; single-use. |
| Nucleic Acid Extraction Reagent | CapitalBio Technology (Chengdu, China) | 360090 | For nucleic acid extraction from respiratory specimens. Store at room temperature (10–30°C). |
| Nucleic Acid Extraction Tubes | Provided with Respiratory Pathogen Detection Kit (360090) | N/A | For nucleic acid extraction from respiratory specimens |
| Respiratory Pathogen Nucleic Acid Detection Kit (isothermal amplification microfluidic chip method) | CapitalBio Technology (Chengdu, China) | 302010 | For qualitative detection of 10 respiratory pathogens. Store at −20°C ± 5°C, 12-month shelf life. |
| RTisochip-W Application Control Software | CapitalBio Technology (Chengdu, China) | Version 1.0 | For instrument control, sample information entry, real-time fluorescence monitoring, and automated result interpretation. |
| RTisochip-W Isothermal Amplification Nucleic Acid Analyzer | CapitalBio Technology (Chengdu, China) | https://www.capitalbiotech.com/product/30/%E4%BB%AA%E5%99%A8%E5%B9%B3%E5%8F%B0/%E5%BE%AE%E6%B5%81%E6%8E%A7%E6%8A%80%E6%9C%AF%E5%B9%B3%E5%8F%B0.html | Isothermal amplification and real-time fluorescence detection system. Medical device registration:  20193220539. |
| Sealing film | Provided with Respiratory Pathogen Detection Kit (302010) or equivalent | https://www.capitalbiotech.com/product/6/%E8%AF%95%E5%89%82%E7%9B%92/%E6%84%9F%E6%9F%93%E6%80%A7%E7%96%BE%E7%97%85.html | For sealing chip inlets/outlets after sample loading. |
| SPSS Statistics | IBM (Armonk, NY, USA) | Version 26.0 | For statistical analysis. |
| Sterile 1.5 mL centrifuge tubes | Axygen | https://ecatalog.corning.com/life-sciences/b2b/US/en/General-Labware/Tubes/Microcentrifuge-Tubes/Axygen%C2%AE-MaxyClear-SnapLock-Microcentrifuge-Tubes/p/MCT-150-C | For specimen processing and nucleic acid storage. |
| Vortex mixer | Kylin-Bell | http://en.ql-lab.com/product/82.html | For thorough mixing of reagents and specimens. |
| Wash solution | Provided with Nucleic Acid Extraction Reagent (360090) or equivalent | CapitalBio Technology 360090 | For washing precipitate during nucleic acid extraction. |
| Water bath or metal bath | Yooning | https://www.yooning.com/en/pro_desc_2098.html | For 37°C incubation (liquefaction) and 95°C heating (nucleic acid extraction). |
참고문헌
- GBD 2023 Lower Respiratory Infections and Antimicrobial Resistance Collaborators. Global burden of lower respiratory infections and aetiologies, 1990–2023: a systematic analysis for the Global Burden of Disease Study 2023. Lancet Infect Dis. 2026;26(4):343–361.
- GBD 2021 Causes of Death Collaborators. Global burden of 288 causes of death and life expectancy decomposition in 204 countries and territories and 811 subnational locations, 1990–2021: a systematic analysis for the Global Burden of Disease Study 2021. Lancet. 2024;403(10440):2100–2132.
- Maraki S, et al. Prevalence and antimicrobial resistance trends among lower respiratory tract pathogens in Crete, Greece, 2017–2022. Infect Chemother. 2024;56(4):492–501.
- Li J, Zhang H, Xu Q, Huang Z. Analysis of the results of 13 combined pathogen detection in 3966 hospitalised children with acute lower respiratory tract infection. Sci Rep. 2025;15(1):11936.
- Safiri S, et al. Global burden of lower respiratory infections during the last three decades. Front Public Health. 2023;10:1028525.
- Santella B, et al. Sepsis: a retrospective cohort study of bloodstream infections. Antibiotics (Basel). 2020;9(12):851.
- Zhu F, Peng M, Chen A, Zhu QY. Research progress on the current status of respiratory pathogen infections and their detection methods. Front Microbiol. 2026;17:1712752.
- Zhang R, et al. Association of climatic variables with risk of transmission of influenza in Guangzhou, China, 2005–2021. Int J Hyg Environ Health. 2023;252:114217.
- Rainen L , et al. Clinical and Laboratory Standards Institute. MM13-A—Collection, Transport, Preparation, and Storage of Specimens for Molecular Methods; Approved Guideline.[J]. 2005.
- Duan N, Du J, Huang C, Li H. Microbial distribution and antibiotic susceptibility of lower respiratory tract infections patients from pediatric ward, adult respiratory ward, and respiratory intensive care unit. Front Microbiol. 2020;11:1480.
- Li M, Song Z, Wan W, Zhou H. Burden of non-COVID-19 lower respiratory infections in China (1990–2021): a global burden of disease study analysis. Respir Res. 2025;26(1):125.
- Elias C, Nunes MC, Saadatian-Elahi M. Epidemiology of community-acquired pneumonia caused by Streptococcus pneumoniae in older adults: a narrative review. Curr Opin Infect Dis. 2024;37(2):144–153.
- Shuai T, et al. The safety and efficacy of non-typeable Haemophilus influenzae and Moraxella catarrhalis vaccine in chronic obstructive pulmonary disease: a systematic review and meta-analysis of randomized controlled trials. Front Med (Lausanne). 2025;12:1572726.
- Wang JZ, et al. Epidemiological and etiological characteristics of 1266 patients with severe acute respiratory infection in central China, 2018–2020: a retrospective survey. BMC Infect Dis. 2024;24(1):426.
- Li F, et al. Comparison of bacteremic pneumonia caused by Escherichia coli and Klebsiella pneumoniae: a retrospective study. Saudi Med J. 2024;45(3):241–251.
- Singh S, Sharma A, Nag VL. Bacterial pathogens from lower respiratory tract infections: a study from Western Rajasthan. J Family Med Prim Care. 2020;9(3):1407–1412.
- Li F, et al. Clinical characteristics and prognosis of hospital-acquired Klebsiella pneumoniae bacteremic pneumonia versus Escherichia coli bacteremic pneumonia: a retrospective comparative study. Infect Drug Resist. 2023;16:4977–4994.
- Jwa H, Beom JW, Lee JH. Predictive factors of methicillin-resistant Staphylococcus aureus infection in elderly patients with community-onset pneumonia. Tuberc Respir Dis. 2017;80(2):201–209.
- Kanchanasuwan S, et al. Clinical characteristics, outcomes, and risk factors for mortality in patients with Stenotrophomonas maltophilia bacteremia. J Clin Med. 2022;11(11):3085.
- Kito Y, et al. Seasonal variation in the prevalence of Gram-negative bacilli in sputum and urine specimens from outpatients and inpatients. Fujita Med J. 2022;8(2):46–51.
- Blot K, et al. Gram-negative central line-associated bloodstream infection incidence peak during the summer: a national seasonality cohort study. Sci Rep. 2022;12(1):5202.
- Santella B, et al. Lower respiratory tract pathogens and their antimicrobial susceptibility pattern: a 5-year study. Antibiotics (Basel). 2021;10(7):851.
- Nguyen HV, et al. Influence of sex and sex-based disparities on prevalent tuberculosis, Vietnam, 2017–2018. Emerg Infect Dis. 2023;29(5):967–976.
- Cillóniz C, et al. Risk factors and outcomes associated with polymicrobial infection in community-acquired pneumonia. Arch Bronconeumol. 2025;61(7):408–416.
- Koçer İ, Demirbakan H, Aktaş A. Temporal dynamics and forecasting of respiratory viral infections during and after the SARS-CoV-2 pandemic (2020–2027): a Loop-Mediated Isothermal Amplification (LAMP) and ARIMA-based study. Front Microbiol. 2025;16:1674529.