This protocol describes a retrospective cohort study evaluating sacubitril/valsartan versus amlodipine in elderly patients with coronary artery disease and hypertension.
Onderzoeksartikel
Sacubitril/Valsartan Improves Cardiovascular Outcomes in Elderly Patients with Coronary Artery Disease and Hypertension: A Retrospective Cohort Study
In dit artikel
Samenvatting
Samenvatting
Elderly patients with concurrent coronary artery disease (CAD) and hypertension face elevated risks of cardiovascular events and require therapies that balance efficacy, safety, and tolerability. Sacubitril/valsartan has demonstrated benefits in heart failure management, but evidence regarding its long-term cardiovascular outcomes in this specific population remains limited. This retrospective cohort study enrolled 150 elderly patients with CAD and hypertension to compare the effects of sacubitril/valsartan versus amlodipine, both combined with conventional therapy. The primary endpoint was the incidence of major adverse cardiovascular events (MACE) over 12 months. Two MACE definitions were applied in this study. Primary analysis used our predefined composite endpoint, including aggravated heart failure and arrhythmia events. A sensitivity analysis adopted the conventional MACE definition (myocardial infarction, stroke, cardiovascular death, revascularization), excluding isolated ventricular premature beats. Secondary endpoints included blood pressure control, cardiac function parameters, and treatment-related adverse events. Results showed that patients treated with sacubitril/valsartan had a significantly lower incidence of MACE (10.26% vs. 27.14%, P = 0.008), superior blood pressure control, and improved left ventricular ejection fraction (LVEF) compared to the amlodipine group. Cox proportional hazards regression (Cox regression) analysis identified sacubitril/valsartan treatment as an independent protective factor against cardiovascular adverse events (hazard ratio (HR) = 0.38, 95% confidence interval (CI): 0.18–0.80, P = 0.011). Both regimens were well-tolerated, with no severe adverse events reported. These findings indicate that sacubitril/valsartan is an effective and safe therapeutic option for elderly patients with CAD and hypertension, reducing long-term cardiovascular risk while improving blood pressure control and cardiac function.
Inleiding
Against the background of rapid population aging in China, the burden of cardiovascular diseases among elderly individuals has been rising steadily. Coronary artery disease (CAD) combined with hypertension represents one of the most common composite cardiovascular disorders in clinical practice1,2. These two conditions act synergistically: hypertension accelerates coronary atherosclerosis, while CAD impairs blood pressure regulation, jointly increasing the risk of severe cardiovascular adverse events, threatening the health of elderly patients, and imposing a substantial burden on healthcare systems2,3.
Clinical management of elderly patients with CAD and hypertension presents distinct challenges. Elderly individuals undergo physiological degeneration, with declined hepatic and renal function, reduced drug metabolism and tolerance, and frequent comorbidities including diabetes, hyperlipidemia, and osteoporosis, leading to widespread polypharmacy4. Therefore, therapeutic strategies must balance efficacy, safety, and tolerability: they should effectively control blood pressure, delay atherosclerotic progression, avoid additional drug-related damage, and protect cardiac and renal function.
Currently, the main classes of antihypertensive medications in clinical use encompass calcium channel blockers, angiotensin-converting enzyme inhibitors, and angiotensin II receptor blockers. However, some elderly patients fail to achieve adequate blood pressure control or experience intolerable adverse reactions such as dizziness, hindering long-term standard treatment and compromising long-term prognosis5,6.
Sacubitril/valsartan is a pioneering fixed-dose combination agent. It operates through a dual mechanism, simultaneously inhibiting neprilysin and angiotensin II receptors, thereby achieving synergistic antihypertensive effects, anti-remodeling activity, and myocardial protection. Sacubitril inhibits neprilysin, reducing the degradation of vasoactive peptides such as natriuretic peptides and bradykinin, thereby promoting vasodilation and diuresis and inhibiting myocardial fibrosis. Valsartan selectively blocks angiotensin II receptors, thereby inhibiting vasoconstriction, reducing myocardial oxygen demand, and further preserving cardiac function. Initially approved for heart failure, sacubitril/valsartan has been widely validated to reduce mortality and rehospitalization while improving cardiac function7,8,9. In recent years, its application in hypertension has expanded considerably, especially in patients with concomitant cardiovascular diseases. Nevertheless, long-term retrospective evidence regarding its efficacy, cardiovascular outcomes, and safety in elderly patients with CAD and hypertension remains insufficient to meet clinical demands.
Accordingly, this study retrospectively analyzed clinical data, treatment records, and follow-up information from 150 elderly patients with CAD and hypertension, aiming to explore the association between sacubitril/valsartan treatment and long-term cardiovascular outcomes, evaluate its clinical efficacy and safety, and provide an evidence base for clinical decision-making in this high-risk population.
Protocol
The study was approved by the Ethics Committee of The Third Affiliated Hospital of Jiaxing University (Zhejiang Rongjun Hospital; Approval ID: 2026-088). All procedures were performed in accordance with institutional ethical guidelines and the Declaration of Helsinki. Given the retrospective study design, the institutional review board waived the requirement for written informed consent. To protect patient confidentiality, all clinical data used in the analysis were fully anonymized before statistical processing.
Study population
A retrospective cohort analysis was conducted involving 150 geriatric patients diagnosed with both coronary artery disease (CAD) and hypertension who were admitted to the Department of Geriatrics between October 2023 and January 2025. Eligible participants were required to have comprehensive medical records, complete follow-up documentation, and complete clinical examination results. The final analytical population comprised patients who completed the 12-month follow-up, including 78 patients in the observation group and 70 patients in the control group. Loss to follow-up was treated as an outcome after enrollment rather than as an exclusion criterion.
Inclusion criteria
Patients were eligible if they were ≥60 years of age and had been hospitalized for ≥3 days in the Department of Geriatrics; met the diagnostic criteria for hypertension according to the 2018 Chinese Guidelines for the Prevention and Treatment of Hypertension10, with a disease duration of ≥1 year; met the diagnostic criteria for CAD, confirmed by coronary angiography or equivalent imaging examination; had complete clinical data and were able to complete the 12-month follow-up; and had no severe mental disorders and demonstrated good medication adherence (Morisky score ≥6)11.
Exclusion criteria
Patients were excluded if they had an allergy to the study medications or a history of severe adverse drug reactions; severe hepatic or renal insufficiency, malignant tumor, severe arrhythmia, New York Heart Association (NYHA) class III–IV heart failure, or other severe systemic diseases12; severe cardiovascular events or cardiovascular intervention within the preceding 3 months; coagulation disorders, autoimmune diseases, or other conditions that could affect the study results; incomplete clinical data; or senile dementia or an inability to cooperate with follow-up and evaluation. The study flow is illustrated in Figure 1.
Grouping
The observation group (n = 78) received sacubitril/valsartan plus conventional treatment, whereas the control group (n = 70) received amlodipine plus conventional treatment. Because this was a retrospective cohort study, treatment allocation was determined by attending physicians based on clinical condition, comorbidities, and treatment tolerability rather than by randomization, which may have introduced selection bias.
Several measures were used to minimize bias. Strict inclusion and exclusion criteria were applied; baseline characteristics were confirmed to be balanced (all p > 0.05); the loss-to-follow-up rate was maintained at 2.78%; comparability between patients who were lost to follow-up and those who remained in the study was verified; and statistical analyses were performed under blinded conditions. All data were de-identified using numerical codes, and statisticians remained blinded to group allocation throughout the analytical process.
Conventional treatment
Clinical medical records for both groups were retrospectively reviewed to confirm the treatment regimens administered13. Antiplatelet therapy consisted of oral aspirin enteric-coated tablets at 100 mg once daily. According to the medical records, patients who were intolerant to aspirin, primarily because of gastrointestinal discomfort, were switched to clopidogrel at 75 mg once daily.
Lipid-modulating and plaque-stabilizing therapy consisted of oral atorvastatin calcium at 20 mg once daily before bedtime. Lipid levels were monitored regularly during treatment, and the dosage was adjusted based on low-density lipoprotein cholesterol (LDL-C) levels, with a maximum of 40 mg/day.
Myocardial perfusion therapy consisted of oral isosorbide dinitrate at 10 mg three times daily. Medical records indicated that sublingual nitroglycerin at 0.5 mg per dose had been administered as needed to relieve episodes of angina pectoris.
Basic nursing and lifestyle interventions included guidance regarding a low-salt, low-fat, and low-sugar diet, with daily salt intake limited to ≤5 g and avoidance of spicy and greasy foods. Moderate exercise, including walking and tai chi, was encouraged, whereas strenuous activity was prohibited. Smoking cessation, limited alcohol consumption, adequate sleep, and avoidance of emotional agitation were advised. Blood pressure was measured three times at 1-min intervals after 5 min of quiet rest, and the mean of the three measurements was recorded as the final blood pressure value. Blood pressure and heart rate were monitored regularly, and patients and family members received instructions regarding appropriate sphygmomanometer use and documentation. All interventions were traceable through the medical records.
Observation-group treatment
According to the retrospective medical record review, the observation group received additional oral sacubitril/valsartan in combination with conventional treatment. Because of reduced treatment tolerance among geriatric patients, treatment was initiated at 50 mg twice daily. Doses were administered 30 min after breakfast and dinner. After 2–4 weeks of treatment, blood pressure and treatment tolerance were closely monitored. According to the medical records, the dosage was gradually increased to 100 mg twice daily in patients with uncontrolled blood pressure (systolic blood pressure ≥130 mmHg or diastolic blood pressure ≥80 mmHg) who had no apparent adverse reactions. The maximum daily dosage did not exceed 200 mg.
Medication was administered regularly without unauthorized discontinuation, dose reduction, or adjustment. Medical records indicated that patients who developed adverse reactions, including hypotension (systolic blood pressure <110 mmHg), underwent timely dose adjustment or temporary treatment suspension. Treatment feasibility was subsequently reassessed after symptomatic management14,15.
Control-group treatment
The control group received additional oral amlodipine in combination with conventional treatment. Treatment was initiated at 5 mg once daily in the morning. After 2 weeks, the dosage was adjusted based on blood pressure control, with a maximum of 10 mg once daily. Medication was maintained regularly without unauthorized changes16.
Blood pressure measurement
Resting office blood pressure was measured three times at each visit, with a 5-min rest interval between measurements. The mean of the three readings was recorded as the representative blood pressure value. Measurements were obtained at baseline and at 3, 6, and 12 months.
Echocardiographic assessment
Transthoracic echocardiography was performed by certified sonographers. Left ventricular ejection fraction (LVEF) was calculated using the biplane Simpson method. Left ventricular end-diastolic diameter (LVEDD) was measured from the parasternal long-axis view at end-diastole.
Follow-up schedule
Follow-up data were extracted from medical records and follow-up forms. Follow-up began on the day of discharge and ended in January 2026. Follow-up frequency complied with geriatric clinical protocols. At 1 and 3 months after treatment, telephone follow-up was conducted to document medication adherence, adverse reactions, and blood pressure control, with detailed records maintained.
At 6 and 12 months, patients returned to the geriatrics outpatient clinic for measurement of blood pressure and heart rate, echocardiography, complete blood count, hepatic and renal function tests, lipid profiling, and other laboratory examinations to evaluate disease status and treatment efficacy. LVEF and LVEDD were measured using the biplane Simpson method. All examination reports were archived.
Follow-up data collection
A dedicated researcher recorded follow-up information and completed the relevant forms. Retrospectively extracted data during follow-up included blood pressure, heart rate, cardiac function parameters, adverse reactions, medication adherence, cardiovascular adverse events, and lifestyle changes. These procedures were used to maintain data completeness, authenticity, and traceability.
For patients with limited mobility who were unable to attend clinic visits, medical staff arranged home visits. When patients could not be contacted by telephone, assistance was obtained from family members and community health centers to maximize follow-up coverage and reduce loss to follow-up.
Management of events during follow-up
Targeted treatment was provided when cardiovascular adverse events, including myocardial infarction and worsening heart failure, occurred during follow-up. For severe adverse reactions, the treatment regimen was adjusted, symptomatic management was provided, and subsequent resolution was documented. For patients lost to follow-up, reasons such as relocation, loss of contact, and death were recorded.
Cardiovascular adverse events
All outcome indicators were evaluated through review of electronic medical records, follow-up materials, and examination reports. The standardized major adverse cardiovascular event (MACE) definition used in the study included myocardial infarction, heart failure progression, atrial fibrillation, and cardiovascular death; benign ventricular premature beats were excluded. The frequency and proportion of cardiovascular adverse events were determined.
Heart failure progression was defined as an increase of at least one NYHA functional class accompanied by dyspnea, lower-extremity edema, or other typical symptoms, based on previously established criteria. Cardiovascular death was defined as death attributable to cardiovascular conditions, including myocardial infarction, heart failure, and severe arrhythmias, as confirmed through medical records and follow-up information.
To improve comparability with the published literature, an additional sensitivity analysis was performed using the conventional international MACE definition of myocardial infarction, stroke, cardiovascular death, and revascularization, with isolated benign ventricular premature beats excluded.
Blood pressure control
Systolic blood pressure (SBP), diastolic blood pressure (DBP), and target attainment rates at baseline and at 6 and 12 months were retrospectively analyzed. The blood pressure target was defined as SBP <130 mmHg and DBP <80 mmHg in accordance with the 2018 Chinese Guidelines for the Prevention and Treatment of Hypertension for geriatric patients with CAD and hypertension. Blood pressure variability was also assessed to evaluate the stability of blood pressure control.
Cardiac function
LVEF and LVEDD at baseline and at 6 and 12 months were assessed by echocardiography. LVEF was used as an indicator of left ventricular systolic function, whereas LVEDD was used to assess the degree of left ventricular remodeling.
Adverse reactions
The occurrence and proportion of adverse reactions were documented, primarily including dizziness, fatigue, dry cough, and lower-extremity edema. The time of onset, clinical characteristics, interventions, and recovery status were recorded.
Correlation analysis
Factors potentially associated with cardiovascular outcomes, including sacubitril/valsartan treatment, age, disease duration, and diabetes mellitus, were assessed for associations with cardiovascular adverse events.
Statistical analysis
Statistical analyses were performed using R v4.2.1 (RRID). Transthoracic echocardiography was performed using a color Doppler ultrasound diagnostic system. Nonparametric statistical methods were used for data that were not normally distributed or exhibited unequal variances. Continuous variables were reported as the mean ± standard deviation (x̄ ± s). Between-group comparisons at identical time points were performed using independent-samples t-tests, whereas within-group changes over time were evaluated using paired t-tests.
Repeated-measures analysis of variance (ANOVA) was used for dynamic parameters, including blood pressure and cardiac function, to evaluate the main effects of group and time, as well as the group × time interaction. When a significant interaction was identified, post hoc pairwise comparisons were performed using the LSD-t test. A Bonferroni correction was applied to control for multiple comparisons and reduce type I error inflation.
Categorical variables were presented as counts and percentages [n (%)]. Between-group comparisons of categorical variables were performed using the χ2 test, continuity-corrected χ2 test, or Fisher's exact test, as appropriate.
The multivariable Cox proportional hazards regression model was optimized according to the events-per-variable (EPV) principle. To minimize model overfitting and stabilize hazard ratio estimates, only two clinically relevant covariates, treatment regimen and advanced age (≥75 years), were included in the primary regression model. With 27 MACE events, the resulting EPV ratio was 13.5, exceeding the conventional threshold of 10 events per variable. The proportional hazards assumption was evaluated using Schoenfeld residuals. A penalized Cox regression sensitivity analysis was also performed to assess the robustness of the predictive model and the reliability of the hazard ratio estimates. A two-sided p < 0.05 was considered statistically significant for all analyses.
Resultaten
Sacubitril/valsartan treatment was associated with a lower incidence of composite MACE, improved blood pressure control, and better cardiac function parameters compared with amlodipine in geriatric patients with CAD and hypertension. Although composite MACE incidence was significantly lower in the sacubitril/valsartan group, no individual MACE subtype demonstrated a statistically significant between-group difference. Adverse event rates were comparable between the groups. These findings supported the primary hypothesis that sacubitril/valsartan was associated with greater cardiovascular protection in this high-risk geriatric population.
Baseline characteristics
No statistically significant between-group differences in baseline characteristics were identified (all p > 0.05), indicating adequate comparability between the groups (Table 1).
Follow-up outcomes
All 78 patients in the observation group completed follow-up without loss to follow-up or dropout, resulting in a 100% follow-up rate. In the control group, 2 of 72 patients were lost to follow-up due to relocation or loss to contact; 70 patients completed follow-up, corresponding to a 97.22% follow-up rate and a 2.78% loss-to-follow-up rate.
Independent-samples t-tests and chi-square tests showed no statistically significant differences in baseline demographic and clinical characteristics, including age, disease duration, blood pressure, cardiac function, and comorbidities, between the two patients lost to follow-up and the patients who completed follow-up (all p > 0.05), indicating no substantial selection bias associated with loss to follow-up.
Incidence of cardiovascular adverse events
Following 12 months of follow-up, 8 cardiovascular adverse events were documented in the observation group, corresponding to an overall incidence of 10.26%. In the control group, 19 events were documented, corresponding to an overall incidence of 27.14%. The overall incidence of cardiovascular adverse events was significantly lower in the observation group than in the control group (χ2 = 7.060, p = 0.008).
In the observation group, myocardial infarction occurred in 1 patient (1.28%), a 78-year-old male patient who experienced an exertion-induced event and improved after emergency thrombolysis and anti-heart failure treatment without death. Aggravated heart failure occurred in 3 patients (3.85%) aged ≥75 years with diabetes mellitus; cardiac function and symptoms improved after treatment adjustment and enhanced diuresis. Arrhythmia occurred in 3 patients (3.85%), including 2 cases of ventricular premature beats and 1 case of atrial fibrillation, and was controlled after adjustment of antiarrhythmic medication. Cardiovascular-related death occurred in 1 patient (1.28%), an 82-year-old female patient with severe pulmonary infection who died of acute heart failure after unsuccessful resuscitation.
In the control group, myocardial infarction occurred in 4 patients (5.71%); 2 patients improved after emergency interventional therapy, whereas 2 patients died because of severe illness. Aggravated heart failure occurred in 6 patients (8.57%) with a disease duration of ≥10 years; symptoms improved after active treatment in 3 patients, whereas persistent disease progression requiring long-term bed rest occurred in 3 patients. Arrhythmia occurred in 7 patients (10.00%), including 4 cases of ventricular premature beats and 3 cases of atrial fibrillation; some cases required combination therapy with two antiarrhythmic medications for control. Cardiovascular-related death occurred in 2 patients (2.86%) aged ≥75 years with multiple comorbidities and was attributed to acute myocardial infarction and severe arrhythmia.
Sensitivity analysis using the conventional standardized MACE definition, excluding isolated ventricular premature beats, was additionally performed to improve comparability with previous clinical studies. After exclusion of minor benign arrhythmia events, the standardized MACE incidence remained significantly lower in the sacubitril/valsartan observation group than in the amlodipine control group, with a consistent between-group trend and statistical significance, supporting the observed cardiovascular-protective association of sacubitril/valsartan in geriatric patients with CAD and hypertension (Table 2).
Kaplan–Meier survival analysis was performed to visualize the temporal pattern of first MACE occurrence and to compare cumulative event risk between groups; between-group differences were assessed using the log-rank test. Kaplan–Meier curves for time to first MACE are presented in Figure 2. The sacubitril/valsartan group demonstrated a significantly lower cumulative risk of 12-month MACE than the amlodipine group (log-rank p = 0.008), consistent with the categorical incidence findings.
Blood pressure control
Repeated-measures ANOVA revealed significant main effects of group assignment for SBP (F = 42.86, p < 0.001, ηp2 = 0.382) and DBP (F = 36.52, p < 0.001, ηp2 = 0.345), indicating significantly lower overall blood pressure levels in the observation group than in the control group. Significant main effects of time were also observed for SBP (F = 189.64, p < 0.001, ηp2 = 0.721) and DBP (F = 156.37, p < 0.001, ηp2 = 0.684), indicating significant reductions in blood pressure over the treatment period in both groups. Significant group × time interactions were identified for SBP (F = 8.92, p < 0.001, ηp2 = 0.106) and DBP (F = 7.65, p < 0.001, ηp2 = 0.093), indicating different patterns of blood pressure reduction between the groups, with greater reductions in the observation group.
Pairwise comparisons demonstrated that SBP and DBP at 6 and 12 months after treatment initiation were significantly lower than the respective baseline values in both groups (all p < 0.05). Blood pressure target attainment rates were also significantly higher than those at baseline (all p < 0.05), indicating effective blood pressure management with both treatment regimens. At the same follow-up time points, the observation group had significantly lower SBP and DBP and a significantly higher blood pressure target attainment rate than the control group (all p < 0.05). These findings indicated a greater antihypertensive effect associated with sacubitril/valsartan than with amlodipine, with more stable blood pressure control and a higher rate of target blood pressure attainment (Table 3).
Cardiac function indexes
Repeated-measures ANOVA revealed significant main effects of group assignment for LVEF (F = 51.24, p < 0.001, ηp2 = 0.421) and LVEDD (F = 43.78, p < 0.001, ηp2 = 0.376), indicating greater overall improvement in cardiac function in the observation group than in the control group. Significant main effects of time were also identified for LVEF (F = 217.53, p < 0.001, ηp2 = 0.754) and LVEDD (F = 182.69, p < 0.001, ηp2 = 0.702), indicating progressive improvement in cardiac function over the treatment period in both groups. Significant group × time interactions were observed for LVEF (F = 10.37, p < 0.001, ηp2 = 0.118) and LVEDD (F = 8.94, p < 0.001, ηp2 = 0.102), indicating different trajectories of cardiac function improvement between the groups, with greater improvement in the observation group.
Post hoc pairwise comparisons demonstrated significantly increased LVEF and significantly reduced LVEDD at 6 and 12 months compared with baseline values in both groups (all p < 0.05). These findings indicated that both treatment regimens were associated with improved cardiac function and reduced ventricular remodeling in geriatric patients with CAD and hypertension. At the same follow-up time points, the observation group demonstrated significantly higher LVEF and lower LVEDD than the control group (all p < 0.05). These findings indicated greater improvement in cardiac function and ventricular remodeling with sacubitril/valsartan than with amlodipine (Table 4).
Incidence of adverse reactions
No severe adverse reactions, including severe hypotension, hepatic or renal impairment, or anaphylactic shock, occurred in either group during treatment. All reported adverse reactions were mild and resolved after symptomatic management without treatment interruption.
A total of 7 adverse reactions occurred in the observation group, corresponding to an incidence of 8.97%. Dizziness occurred in 3 patients (3.85%) during the first 1–2 weeks of treatment and was considered associated with rapid blood pressure reduction; symptoms resolved after reducing the initial sacubitril/valsartan dose and with instructions regarding slow positional changes. Fatigue occurred in 2 patients (2.56%), was mild, did not interfere with daily activities, and resolved spontaneously during continued treatment. Dry cough occurred in 2 patients (2.56%), was mild and unaccompanied by expectoration or chest tightness, and resolved without discontinuation of treatment.
A total of 8 adverse reactions occurred in the control group, corresponding to an incidence of 11.43%. Dizziness occurred in 4 patients (5.71%) during the initial treatment period and resolved after adjusting the timing of amlodipine administration. Fatigue occurred in 2 patients (2.86%), was mild, and resolved spontaneously. Lower-extremity edema occurred in 2 patients (2.86%), was mild, and resolved after elevation of the lower extremities and a reduction in sodium intake, without dose adjustment.
No statistically significant between-group difference was detected in the incidence of adverse reactions (χ2 = 0.25, p = 0.62), indicating comparable tolerability between sacubitril/valsartan and amlodipine in geriatric patients with CAD and hypertension (Table 5).
Correlation between sacubitril/valsartan treatment and cardiovascular outcomes
Cox proportional hazards regression analysis was performed with cardiovascular adverse event occurrence as the dependent variable (event = 1; non-event = 0). After model optimization, two core covariates, treatment regimen and age ≥75 years, were included to maintain stable model fitting and an adequate events-per-variable ratio. Penalized Cox regression sensitivity analysis produced consistent hazard ratio estimates and statistical trends, supporting the robustness of the primary multivariable Cox model.
Multivariable regression analysis identified sacubitril/valsartan treatment as an independent protective factor associated with long-term cardiovascular adverse events in geriatric patients with CAD and hypertension (HR = 0.38, 95% CI: 0.18–0.80, p = 0.011). An HR of 0.38 corresponded to a 62% lower hazard of cardiovascular adverse events among patients treated with sacubitril/valsartan compared with patients treated with amlodipine. Advanced age (≥75 years) was identified as an independent risk factor for cardiovascular adverse events (p < 0.05; Table 6).
DATA AVAILABILITY:
All de-identified individual baseline, follow-up, and outcome data generated in the study were provided in Supplementary File 1.
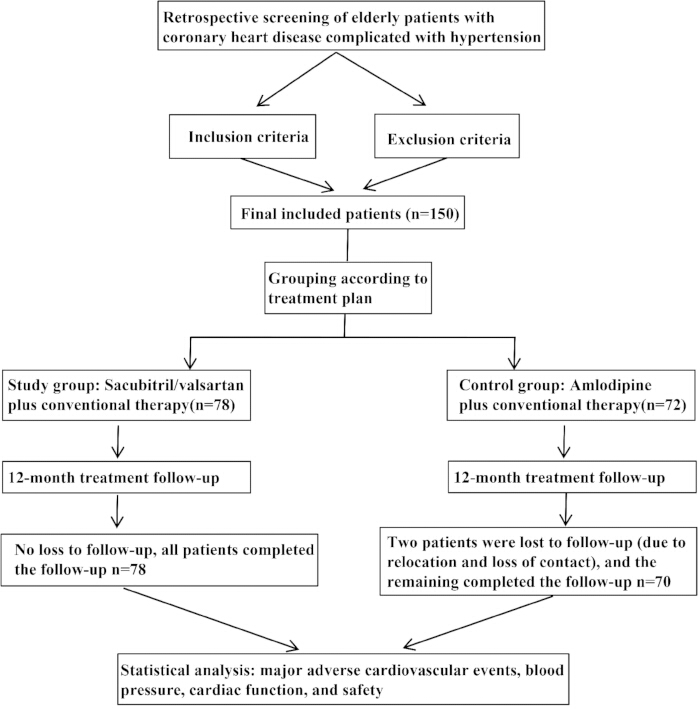
Figure 1: Research flowchart. Schematic diagram illustrating patient screening, enrollment, treatment-group allocation, and 12-month follow-up in the retrospective cohort study. Please click here to view a larger version of this figure.
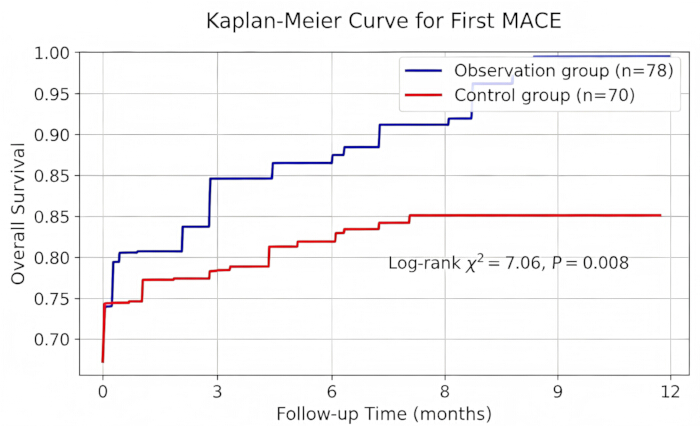
Figure 2: Kaplan–Meier survival curves for time to first major adverse cardiovascular event. Kaplan–Meier survival curves showing time to first major adverse cardiovascular event (MACE) in geriatric patients with coronary artery disease and hypertension treated with sacubitril/valsartan or amlodipine. Cumulative MACE risk was compared between groups using the log-rank test (p = 0.008). Please click here to view a larger version of this figure.
| Variable | Observation Group | Control Group | P value |
| (n = 78) | (n = 70) | ||
| Sex, n | 0.852 | ||
| Male | 42 | 39 | |
| Female | 36 | 33 | |
| Age, years | 60–82, mean ± SD: 71.35 ± 6.28 | 61–83, mean ± SD: 72.14 ± 6.51 | 0.417 |
| Age ≥75 years, n | 29 | 27 | 0.852 |
| Disease duration, years | 3–15, mean ± SD: 8.62 ± 3.15 | 4–16, mean ± SD: 8.97 ± 3.32 | 0.489 |
| Disease duration ≥10 years, n | 32 | 30 | 0.761 |
| Comorbid diabetes mellitus, n | 28 | 25 | 0.683 |
| Comorbid hyperlipidemia, n | 35 | 33 | 0.815 |
| Baseline SBP, mmHg | 152.36 ± 10.52 | 153.12 ± 10.78 | 0.662 |
| Baseline DBP, mmHg | 93.45 ± 8.26 | 94.12 ± 8.53 | 0.618 |
| Baseline LVEF, % | 51.23 ± 5.36 | 50.89 ± 5.42 | 0.694 |
| Baseline LVEDD, mm | 56.34 ± 4.28 | 56.78 ± 4.35 | 0.557 |
| Medication adherence score | 7.82 ± 0.95 | 7.75 ± 1.02 | 0.673 |
Table 1: Baseline characteristics of patients. Comparison of demographic and clinical characteristics between the observation group (n = 78) and the control group (n = 70).
| Group | n | Myocardial Infarction | Aggravated Heart Failure | Arrhythmia | Cardiovascular-Related Death | Total Incidence [n (%)] |
| Observation | 78 | 1 (1.28) | 3 (3.85) | 3 (3.85) | 1 (1.28) | 8 (10.26) |
| Control | 70 | 4 (5.71) | 6 (8.57) | 7 (10.00) | 2 (2.86) | 19 (27.14) |
| χ² | - | 2.015 | 2.134 | 3.026 | 0.458 | 7.06 |
| P | - | 0.156 | 0.144 | 0.082 | 0.498 | 0.008 |
Table 2: Incidence of cardiovascular adverse events. Comparison of the incidence of major adverse cardiovascular events (MACE) between the two groups after 12 months of follow-up.
| Group | n | Time Point | Systolic Blood Pressure | Diastolic Blood Pressure | Target Achievement Rate [n (%)] |
| (mmHg, x̄±s) | (mmHg, x̄±s) | ||||
| Observation Group | 78 | Before treatment | 152.36 ± 10.52 | 93.45 ± 8.26 | 12 (15.38) |
| 6 months after treatment | 128.45 ± 8.37*,# | 78.62 ± 6.15*,# | 65 (83.33)*,# | ||
| 12 months after treatment | 125.32 ± 7.89*,# | 76.54 ± 5.98*,# | 69 (88.46)*,# | ||
| Control Group | 70 | Before treatment | 153.12 ± 10.78 | 94.12 ± 8.53 | 10 (14.29) |
| 6 months after treatment | 135.67 ± 9.12* | 82.34 ± 6.78* | 48 (68.57)* | ||
| 12 months after treatment | 132.45 ± 8.67* | 80.12 ± 6.34* | 52 (74.29)* | ||
| Main effect of group | F = 42.86,P < 0.001,ηp2 = 0.382 | F = 36.52,P < 0.001,ηp2 = 0.345 | - | ||
| Main effect of time point | F = 189.64,P < 0.001,ηp2 = 0.721 | F = 156.37,P < 0.001,ηp2 = 0.684 | - | ||
| Group × time interaction effect | F = 8.92,P < 0.001,ηp2 = 0.106 | F = 7.65,P < 0.001,ηp2 = 0.093 | - | ||
Table 3: Blood pressure control. Changes in systolic blood pressure (SBP), diastolic blood pressure (DBP), and target attainment rates over time in both groups.
| Group | n | Time Point | LVEF (%, x̄±s) | LVEDD |
| (mm, x̄±s) | ||||
| Observation Group | 78 | Before treatment | 51.23 ± 5.36 | 56.34 ± 4.28 |
| 6 months after treatment | 58.45 ± 5.78*,# | 52.15 ± 3.87*,# | ||
| 12 months after treatment | 62.34 ± 6.12*,# | 49.87 ± 3.56*,# | ||
| Control Group | 70 | Before treatment | 50.89 ± 5.42 | 56.78 ± 4.35 |
| 6 months after treatment | 54.32 ± 5.56* | 54.23 ± 3.98* | ||
| 12 months after treatment | 57.65 ± 5.89* | 52.45 ± 3.78* | ||
| Main effect of group | F = 51.24,P < 0.001,ηp2 = 0.421 | F=43.78,P < 0.001,ηp2=0.376 | ||
| Main effect of time point | F = 217.53,P < 0.001,ηp2 = 0.754 | F = 182.69,P < 0.001,ηp2 = 0.702 | ||
| Group × time interaction effect | F = 10.37,P < 0.001,ηp2 = 0.118 | F = 8.94,P < 0.001,ηp2 = 0.102 | ||
Table 4: Cardiac function indexes. Changes in left ventricular ejection fraction (LVEF) and left ventricular end-diastolic diameter (LVEDD) over time in both groups.
| Group | n | Dizziness | Fatigue | Dry Cough | Lower Extremity Edema | Total Incidence [n (%)] |
| Observation | 78 | 3 (3.85) | 2 (2.56) | 2 (2.56) | 0 (0.00) | 7 (8.97) |
| Control | 70 | 4 (5.71) | 2 (2.86) | 0 (0.00) | 2 (2.86) | 8 (11.43) |
| χ² | - | 0.386 | 0.015 | 1.987 | 1.987 | 0.25 |
| P | - | 0.534 | 0.902 | 0.158 | 0.158 | 0.62 |
Table 5: Incidence of adverse reactions. Comparison of the incidence of treatment-related adverse reactions between the two groups.
| Independent Variable | Coding Definition | HR | 95%CI | χ² | P |
| Sacubitril/valsartan treatment | Yes = 1, No = 0 (reference: amlodipine) | 0.38 | 0.18–0.80 | 6.452 | 0.011 |
| Age | ≥75 years = 1, <75 years = 0 | 2.15 | 1.03–4.48 | 4.125 | 0.041 |
| Disease duration | ≥10 years = 1, <10 years = 0 | 2.32 | 1.12–4.82 | 5.136 | 0.023 |
| Diabetes mellitus | Yes = 1, No = 0 | 2.56 | 1.21–5.42 | 6.012 | 0.014 |
Table 6: Association between sacubitril/valsartan treatment and cardiovascular outcomes. Multivariable Cox proportional hazards regression analysis of factors associated with cardiovascular adverse events.
Supplementary File 1: De-identified individual baseline, follow-up, and outcome data generated in the study. Please click here to download this file.
Discussie
Geriatric patients with both CAD and hypertension typically exhibit age-related physiological decline, a high comorbidity burden, and reduced drug tolerability. Clinical management of this population requires a balance among antihypertensive efficacy, cardiac protection, and safety. This retrospective study with 12 months of follow-up used standardized inclusion and exclusion criteria, consistent blood pressure and echocardiographic assessment time points, and standardized adverse-event adjudication criteria to compare cardiovascular outcomes associated with sacubitril/valsartan and amlodipine. Although conventional antihypertensive agents can control blood pressure to some extent, limitations remain in improving cardiac function and reducing the incidence of long-term adverse cardiovascular events17,18,19,20.
Sacubitril/valsartan is a dual-mechanism antihypertensive agent with pharmacological effects mediated by its two components. Sacubitril inhibits neprilysin activity, thereby reducing the degradation of vasoactive substances such as natriuretic peptides and bradykinin. These effects promote vasodilation and diuresis, reduce blood pressure, suppress myocardial fibrosis, attenuate ventricular remodeling, and preserve myocardial function. Valsartan selectively blocks angiotensin II receptors, thereby inhibiting vasoconstriction, reducing myocardial workload, and enhancing antihypertensive effects. Angiotensin II-mediated endothelial injury is also attenuated, potentially delaying the progression of coronary atherosclerosis21,22,23. The complementary actions of these components provide both blood pressure reduction and cardiac protection, supporting the potential clinical relevance of sacubitril/valsartan for geriatric patients with CAD and hypertension.
After 12 months of follow-up, the overall incidence of cardiovascular adverse events was significantly lower in the observation group than in the control group. Although composite MACE incidence was significantly lower in the sacubitril/valsartan group, no individual MACE subtype demonstrated a statistically significant between-group difference. These findings suggested that sacubitril/valsartan was associated with a lower overall risk of cardiovascular events, including myocardial infarction, heart failure progression, and arrhythmias, and potentially with improved long-term cardiovascular outcomes. These results were consistent with previous investigations24,25,26,27,28,29,30.
Blood pressure control is a major therapeutic objective in geriatric patients with CAD and hypertension. Adequate blood pressure management can substantially reduce the risk of adverse cardiovascular outcomes31,32. Systolic and diastolic blood pressure values at 6 and 12 months after treatment initiation were significantly lower in the observation group than in the control group, whereas blood pressure target attainment rates were significantly higher in the observation group. These findings indicated that sacubitril/valsartan was associated with greater and more sustained reductions in blood pressure than amlodipine.
The complementary mechanisms of sacubitril and valsartan may contribute to stable blood pressure control and reduced blood pressure variability. Such effects may be particularly relevant in geriatric patients because reduced vascular elasticity and impaired blood pressure regulation are common in this population. Excessive blood pressure fluctuations may contribute to angina pectoris and arrhythmias. A low-initial-dose, gradual-titration strategy was used to account for age-related declines in hepatic and renal function33,34,35,36,37,38. This protocol modification was implemented during routine clinical follow-up to improve treatment tolerability. Incomplete historical echocardiographic records were identified in a small subset of patients and were addressed through standardized retrospective chart review. No serious protocol deviations were identified during data collection.
Cardiac dysfunction and ventricular remodeling are common pathological abnormalities in geriatric patients with CAD and hypertension and are major risk factors for adverse cardiovascular events39,40,41. Consequently, cardiac protection and attenuation of ventricular remodeling are important considerations during antihypertensive treatment. Echocardiographic findings demonstrated significantly higher LVEF and significantly lower LVEDD in the observation group than in the control group at 6 and 12 months after treatment (p < 0.05), indicating greater improvement in cardiac function and attenuation of ventricular remodeling associated with sacubitril/valsartan.
This finding may be related to the cardioprotective mechanisms of sacubitril/valsartan. Neprilysin inhibition increases natriuretic peptide levels, which may inhibit cardiomyocyte apoptosis, reduce myocardial fibrosis, attenuate ventricular remodeling, and enhance myocardial contractility22,42,43,44,45,46. Collectively, the findings indicated that sacubitril/valsartan was associated with reductions in blood pressure and favorable changes in cardiac function parameters in geriatric patients with CAD and hypertension.
Safety is an important consideration in pharmacotherapy for geriatric patients because reduced hepatic and renal function, polypharmacy, and reduced drug tolerance are common. The selection of well-tolerated antihypertensive agents is therefore important for long-term treatment47,48. The safety analysis demonstrated no statistically significant difference in the incidence of adverse reactions between the groups. All reported adverse reactions were mild, primarily dizziness and fatigue, and no severe adverse reactions occurred. All adverse reactions resolved after symptomatic management without treatment interruption.
The observation group had a dry cough incidence of 2.56%. All cases were mild and nonproductive, without expectoration or chest tightness, and did not require discontinuation of treatment. The control group had a lower-extremity edema incidence of 2.86%. All cases were mild and resolved after leg elevation and sodium restriction without dose adjustment. These findings indicated comparable tolerability between sacubitril/valsartan and amlodipine in geriatric patients with CAD and hypertension.
Cox proportional hazards regression analysis identified sacubitril/valsartan treatment as an independent protective factor associated with cardiovascular adverse events in geriatric patients. Advanced age (≥75 years) was also identified as an independent risk factor for cardiovascular adverse events. Patients aged ≥75 years may have more advanced physiological decline, myocardial ischemia, cardiac dysfunction, and altered drug metabolism, potentially contributing to an increased cardiovascular event risk49,50. These findings indicated the importance of close clinical monitoring among older patients at increased cardiovascular risk.
The clinical relevance of the study was based on the use of real-world geriatric data to evaluate the treatment efficacy and cardiovascular outcomes of sacubitril/valsartan in geriatric patients with CAD and hypertension, using a retrospective long-term follow-up design. The study reflected routine clinical practice and provided evidence regarding treatment outcomes in this population.
Several limitations should be considered. First, this was a single-center retrospective study with a relatively modest sample size of 150 patients, which may have introduced selection bias. The retrospective, nonrandomized design was inherently susceptible to confounding by indication. Although the observed baseline variables were balanced, unmeasured confounding factors, including subtle differences in baseline heart failure severity, renal function, and adherence to undocumented medications, could have influenced treatment allocation and clinical outcomes. Consequently, causal inference was limited, and the findings should be considered hypothesis-generating. Multicenter randomized controlled trials are required to validate these observations. Generalization to other ethnic populations or healthcare settings also requires caution because cardiovascular risk profiles, medication access, and clinical practice patterns may differ.
Second, the initial multivariable Cox regression model included four covariates and had a suboptimal events-per-variable ratio of 6.75, which may have led to model overfitting and unstable hazard ratio estimates. The final model was optimized by retaining two core clinical covariates, resulting in an EPV of 13.5. Penalized Cox regression sensitivity analysis was also performed to assess the robustness of the findings. The relatively wide 95% confidence interval for the treatment effect may have reflected the limited number of endpoint events.
Third, the original MACE definition included aggravated heart failure and arrhythmic events, including ventricular premature beats, differing from conventional MACE definitions that typically focus on myocardial infarction, stroke, cardiovascular death, and revascularization. To improve comparability with the literature, sensitivity analysis was performed using a standardized MACE definition that excluded minor isolated ventricular premature beats.
Fourth, the follow-up duration was limited to 12 months, which was relatively short for this geriatric cohort. Longer follow-up periods of 2–3 years may provide a more comprehensive evaluation of long-term efficacy and safety.
Fifth, multiple secondary endpoints were evaluated. Although the Bonferroni correction was applied to control the type I error rate, the possibility of bias associated with multiple testing could not be completely eliminated. Secondary outcomes should therefore be interpreted as exploratory findings.
Sixth, the single-center retrospective design did not include an a priori prospective sample size calculation. The limited sample size and nonsignificant differences among individual MACE subtypes may have reflected insufficient statistical power rather than the absence of differences between treatments.
Seventh, the dose–response relationship of sacubitril/valsartan was not evaluated. Future studies could investigate dose-dependent associations with efficacy and safety to inform clinical dosing strategies.
Eighth, patient-reported outcomes, including quality of life, were not assessed. Inclusion of patient-reported outcomes in future studies could provide a more comprehensive assessment of clinical benefit.
Multicenter, large-scale retrospective or prospective investigations are warranted to validate these findings. Future research could also evaluate longer follow-up periods, dose-dependent treatment effects, and patient-reported outcomes to provide a more comprehensive assessment of efficacy and safety.
Openbaarmakingen
The authors declare that they have no financial conflicts of interest.
Materialen
| Naam | Bedrijf | Catalogusnummer | Opmerkingen |
|---|---|---|---|
| Amlodipine tablets | Pfizer Inc, NY, USA | NDC 0069-1530-68 | 5 mg tablets, oral antihypertensive medication |
| Aspirin enteric-coated tablets | CSPC Pharmaceutical Group Limited | National Medical Product Approval Number:H20153035 | 100 mg tablets, antiplatelet therapy |
| Atorvastatin calcium tablets | Zydus | NDC 70771-1875-9 | 20 mg tablets, lipid-modulating therapy |
| Clopidogrel tablets | Zydus | NDC 70771-1062 | 75 mg tablets, antiplatelet therapy (aspirin-intolerant patients) |
| Echocardiography | Siemens | Sequoia | Used for measuring LVEF and LVEDD |
| Isosorbide dinitrate tablets | Bausch Health US LLC | NDC 0187-0152-01 | 10 mg tablets, myocardial perfusion improvement |
| Morisky Medication Adherence Scale | American team led by Dr. Donald E. Morisky | - | Used to assess medication adherence |
| Nitroglycerin sublingual tablets | Zydus Lifesciences | NDC 70771-1718-1 | 0.5 mg tablets, as-needed relief for angina |
| Sacubitril/valsartan sodium tablets | Novartis Pharma Stein AG | National Medical Product Approval Number:H20171198 | 100 mg tablets, study medication |
| Sphygmomanometer | Riester | 1251-107 | Used for blood pressure measurement |
| SPSS software | IBM | Version 26.0 | Used for statistical analysis |
Referenties
- Fadah K, Hechanova A, Mukherjee D. Epidemiology, pathophysiology, and management of coronary artery disease in the elderly. Int J Angiol. 2022;31(4):244-250.
- Chen Y, et al. Patients with comorbid coronary artery disease and hypertension: a cross-sectional study with data from the NHANES. Ann Transl Med. 2022;10(13):745.
- Mahtta D, Elgendy IY, Pepine CJ. Optimal medical treatment of hypertension in patients with coronary artery disease. Expert Rev Cardiovasc Ther. 2018;16(11):815-823.
- Visseren FLJ, et al. 2021 ESC Guidelines on cardiovascular disease prevention in clinical practice. Eur Heart J. 2021;42(34):3227-3337.
- Todd OM, et al. Pharmacologic treatment of hypertension in older adults. Clin Geriatr Med. 2024;40(4):629-644.
- Ambrož M, et al. Older age, polypharmacy, and low systolic blood pressure are associated with more hypotension-related adverse events in patients with type 2 diabetes treated with antihypertensives. Front Pharmacol. 2021;12:728911.
- Pascual-Figal D, et al. Sacubitril-valsartan, clinical benefits and related mechanisms of action in heart failure with reduced ejection fraction: a review. Front Cardiovasc Med. 2021;8:754499.
- Pontremoli R, Borghi C, Perrone Filardi P. Renal protection in chronic heart failure: focus on sacubitril/valsartan. Eur Heart J Cardiovasc Pharmacother. 2021;7(5):445-452.
- Rajzer P, Biegus J. Sacubitril/valsartan in a wide spectrum of heart failure patients (from mechanisms of action to outcomes in specific populations). Heart Fail Rev. 2025;30(2):387-405.
- 2018 Chinese Guidelines for Prevention and Treatment of Hypertension—A report of the Revision Committee of Chinese Guidelines for Prevention and Treatment of Hypertension. J Geriatr Cardiol. 2019;16(3):182-241.
- Ibrahim KM, et al. The association between medication experiences and beliefs and low medication adherence in patients with chronic disease from two different societies: the USA and the Sultanate of Oman. Pharmacy (Basel). 2021;9(1).
- Bogaerts JMK, et al. Effects of the discontinuation of antihypertensive treatment on neuropsychiatric symptoms and quality of life in nursing home residents with dementia (DANTON): a multicentre, open-label, blinded-outcome, randomised controlled trial. Age Ageing. 2024;53(7).
- Byrne RA, et al. 2023 ESC Guidelines for the management of acute coronary syndromes. Eur Heart J Acute Cardiovasc Care. 2024;13(1):55-161.
- Kim H, et al. Clinical evidence of initiating a very low dose of sacubitril/valsartan: a prospective observational analysis. Sci Rep. 2021;11(1):16335.
- Iwashima Y, et al. Efficacy and safety of sacubitril/valsartan after switching from azilsartan in hemodialysis patients with hypertension. J Clin Hypertens (Greenwich). 2023;25(3):304-308.
- Kim K, Moon JH, Ahn CH, Lim S. Effect of olmesartan and amlodipine on serum angiotensin-(1-7) levels and kidney and vascular function in patients with type 2 diabetes and hypertension. Diabetol Metab Syndr. 2023;15(1):43.
- Benetos A, Petrovic M, Strandberg T. Hypertension management in older and frail older patients. Circ Res. 2019;124(7):1045-1060.
- Jones DW, et al. 2025 AHA/ACC/AANP/AAPA/ABC/ACCP/ACPM/AGS/AMA/ASPC/NMA/PCNA/SGIM Guideline for the prevention, detection, evaluation, and management of high blood pressure in adults: a report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. J Am Coll Cardiol. 2025;86(18):1567-1678.
- Pajewski NM, et al. Intensive vs standard blood pressure control in adults 80 years or older: a secondary analysis of the Systolic Blood Pressure Intervention Trial. J Am Geriatr Soc. 2020;68(3):496-504.
- Peeters LEJ, et al. Pharmacokinetic and pharmacodynamic considerations in the treatment of the elderly patient with hypertension. Expert Opin Drug Metab Toxicol. 2019;15(4):287-297.
- Myhre PL, et al. B-type natriuretic peptide during treatment with sacubitril/valsartan: the PARADIGM-HF trial. J Am Coll Cardiol. 2019;73(11):1264-1272.
- Mustafa NH, et al. Molecular mechanisms of sacubitril/valsartan in cardiac remodeling. Front Pharmacol. 2022;13:892460.
- Trivedi RK, et al. Combined angiotensin receptor-neprilysin inhibitors improve cardiac and vascular function via increased NO bioavailability in heart failure. J Am Heart Assoc. 2018;7(5).
- Yandrapalli S, Khan MH, Rochlani Y, Aronow WS. Sacubitril/valsartan in cardiovascular disease: evidence to date and place in therapy. Ther Adv Cardiovasc Dis. 2018;12(8):217-231.
- Yamamoto K, et al. Efficacy and safety of sacubitril/valsartan versus amlodipine in Japanese patients with essential hypertension: a randomized, multicenter, open-label, noninferiority study (PARASOL Study). J Clin Hypertens (Greenwich). 2025;27(1):e14938.
- Shaddy R, et al. Sacubitril/valsartan in pediatric heart failure (PANORAMA-HF): a randomized, multicenter, double-blind trial. Circulation. 2024;150(22):1756-1766.
- Zhou W, et al. The efficacy and safety of sacubitril/valsartan in chronic kidney disease: a systematic review and meta-analysis. Int Urol Nephrol. 2024;56(1):181-190.
- Basile C, et al. Sacubitril/valsartan reduces cardiac decompensation in heart failure with preserved ejection fraction: a meta-analysis. J Cardiovasc Med (Hagerstown). 2023;24(1):44-51.
- Zhang H, Huetteman AT, Reyes EA, Appelbaum JS. Effects of sacubitril-valsartan in patients with various types of heart failure: a meta-analysis. J Cardiovasc Pharmacol. 2023;81(6):434-444.
- Wu HX, et al. Efficacy and safety of sacubitril/valsartan in the treatment of middle-aged and elderly patients with hypertension: a systematic review and meta-analysis of randomized controlled trials. Ann Palliat Med. 2022;11(5):1811-1825.
- Seidu S, Willis H, Kunutsor SK, Khunti K. Intensive versus standard blood pressure control in older persons with or without diabetes: a systematic review and meta-analysis of randomised controlled trials. J R Soc Med. 2023;116(4):133-143.
- Zhang DY, et al. Ambulatory blood pressure monitoring, European guideline targets, and cardiovascular outcomes: an individual patient data meta-analysis. Eur Heart J. 2025;46(30):2974-2987.
- Zhang L, Chen Q, Ren G. A propensity score-matched retrospective study on sacubitril/valsartan use and 6-month readmission rates in patients with acute heart failure. PeerJ. 2025;13:e20055.
- Nägele MP, et al. Vascular endothelial effects of sacubitril/valsartan in heart failure with reduced ejection fraction: randomized controlled trial. JACC Adv. 2024;3(12):101392.
- Skow LF, et al. Mid-life vascular risk and rate of physical function decline among older adults: the Atherosclerosis Risk in Communities (ARIC) Study. J Gerontol A Biol Sci Med Sci. 2024;79(2).
- Ahmed B, Rahman AA, Lee S, Malhotra R. The implications of aging on vascular health. Int J Mol Sci. 2024;25(20).
- Guasti L, et al. Management of hypertension in the elderly and frail patient. Drugs Aging. 2022;39(10):763-772.
- Martin SS, et al. 2025 Heart disease and stroke statistics: a report of US and global data from the American Heart Association. Circulation. 2025;151(8):e41-e660.
- Mołek-Dziadosz P, et al. Left ventricular remodeling in atrial fibrillation is associated with elevated NAP-2 and 3-nitrotyrosine. Biomark Med. 2025;19(5):157-164.
- Lange A, et al. Left heart remodelling in hypertensive patients: a comprehensive echocardiography and computed tomography study. Front Cardiovasc Med. 2023;10:1295537.
- Alves QL, de Jesus RLC, Silva DF. Beneficial effects induced by TRPM8 channels activation to treat myocardial infarction. Am J Hypertens. 2020;33(3):214-217.
- Shen J, Fan Z, Sun G, Qi G. Sacubitril/valsartan (LCZ696) reduces myocardial injury following myocardial infarction by inhibiting NLRP3-induced pyroptosis via the TAK1/JNK signaling pathway. Mol Med Rep. 2021;24(3).
- Peng S, et al. LCZ696 ameliorates oxidative stress and pressure overload-induced pathological cardiac remodeling by regulating the Sirt3/MnSOD pathway. Oxid Med Cell Longev. 2020;2020:9815039.
- Hu F, et al. Sacubitril/valsartan attenuated myocardial inflammation, fibrosis, apoptosis and promoted autophagy in doxorubicin-induced cardiotoxicity mice via regulating the AMPKα-mTORC1 signaling pathway. Mol Cell Biochem. 2025;480(3):1891-1908.
- Gan J, et al. Sacubitril/valsartan ameliorates cardiac function and ventricular remodeling in CHF rats via the inhibition of the tryptophan/kynurenine metabolism and inflammation. Sci Rep. 2024;14(1):12377.
- Acquaro M, et al. Sacubitril/valsartan effects on arrhythmias and left ventricular remodelling in heart failure: an observational study. Vascul Pharmacol. 2023;152:107196.
- Kang MG, et al. Fimasartan versus perindopril with and without diuretics in the treatment of elderly patients with essential hypertension (Fimasartan in the Senior Subjects [FITNESS]): study protocol for a randomized controlled trial. Trials. 2019;20(1):389.
- Otto CM. Heartbeat: balance of safety and efficacy of antihypertensive treatment in elderly patients. Heart. 2019;105(14):1049-1050.
- Kuzuya M. Effect of drugs on nutritional status and drug-nutrition interactions in older patients. Geriatr Gerontol Int. 2023;23(7):465-477.
- Wu X, et al. Physiologically based pharmacokinetic model for older adults and its application in geriatric drug research. Curr Drug Metab. 2023;24(3):211-222.