This review summarizes the inflammatory mechanisms of COPD and the regulatory effects of moxibustion, focusing on TLR4/NF‑κB and IL‑33/ST2 pathways.
Artigo de revisão
Progress on the Anti-inflammatory Mechanisms of Moxibustion in Chronic Obstructive Pulmonary Disease: A Narrative Review of Current Evidence
Neste artigo
Resumo
Resumo
Chronic obstructive pulmonary disease (COPD), a major cause of morbidity and mortality worldwide, is driven by persistent airway inflammation involving complex pathways. Despite advances in conventional therapies, challenges remain in the effective control of steroid-resistant inflammation and systemic complications. Moxibustion is a traditional Chinese therapy that has shown promise in alleviating COPD-related inflammation by targeting these pathways. Clinical studies have suggested that moxibustion can regulate inflammatory cells (macrophages, neutrophils, Th17 cells, and regulatory T [Treg] cells) and mediators (TNF-α, IL-6, and IL-8), and these mechanisms correlate with improved lung function, reduced exacerbations, and enhanced immune balance. However, current evidence is limited by small sample sizes, heterogeneous methodologies, and a lack of high-quality randomized controlled trials (RCTs), resulting in an unclear independent therapeutic efficacy of moxibustion for COPD. While preliminary findings highlight its potential as an adjunct therapy, rigorous multicenter RCTs are imperative with large sample sizes and standardized protocols to validate its anti-inflammatory efficacy, elucidate dose-response relationships, and comprehensively evaluate safety profiles. This review aims to integrate traditional medical theory with modern immune inflammation biology, and summarize progress on the mechanism of inflammation regulation of moxibustion in the treatment of COPD. It mainly puts forward the view that moxibustion may treat COPD through TLR4/NF-κB pathway and IL-33/ST2 pathway, and points out the limitations of the existing related research. It emphasizes the need for more direct mechanism explanation and clinical research to verify.
Introdução
COPD is a prevalent chronic respiratory condition characterized by persistent airflow limitation. It is associated with high rates of disability and mortality and ranks as the third leading cause of death globally. The primary symptoms include chronic cough, sputum production, shortness of breath, wheezing, and chest tightness. COPD is also prone to recurrent acute exacerbations, which can trigger acute respiratory failure and diminish patients' quality of life1,2. Additionally, previous meta-analyses have highlighted the substantial burden of COPD in Asia, with high readmission rates further underscoring the need for effective adjunctive therapies such as moxibustion3. Current treatments for COPD typically involve the use of bronchodilators, phosphodiesterase-4 inhibitors, corticosteroids, and symptomatic therapy.
In the complex pathogenesis of COPD, chronic airway inflammation is a significant mechanism contributing to its development and serves as a central link and key driving factor in disease progression4,5. The activation of inflammatory cells and the release of inflammatory mediators play crucial roles in the onset, progression, and prognosis of COPD. In recent years, anti-inflammatory therapy has emerged as an effective and critical approach in the clinical management of COPD. However, the clinical efficacy of anti-inflammatory therapy is still limited due to steroid resistance and systemic inflammation. The main reason is that the underlying inflammation of COPD is difficult to effectively control through existing therapies, especially since the inflammation of most patients is often resistant to corticosteroid treatment. In addition, the inflammatory response in COPD patients is not limited to the lungs and may also lead to systemic adverse effects, further complicating treatment6,7. Therefore, on the basis of the understanding of COPD pathogenesis and acute exacerbations, identifying therapeutic targets for intervention and prevention to improve treatment outcomes and enhance the quality of life for patients has become an urgent necessity. Notably, this pathway’s overactivation closely correlates with the traditional Chinese medicine concept of “blood stasis”, which is one of the core pathogenesis of COPD in traditional Chinese medicine and is closely associated with chronic inflammation and microcirculatory disorder8.
Moxibustion is a traditional Chinese medical therapy with a rich historical and cultural background. The “Huangdi Neijing” states “Where acupuncture is not suitable, moxibustion is appropriate”. Through its characteristic “warming and dredging meridians” effect, preliminary clinical studies suggest that moxibustion alone and moxibustion combined with other treatments can improve lung function and quality of life in patients with COPD with good safety9, and these effects are closely related to the regulation of inflammation10. Although the intervention effect of moxibustion and the mechanism of inflammation regulation are not particularly extensive at present, it remains significant to provide therapeutic targets and theoretical basis for moxibustion in the treatment of COPD. The purpose of this narrative review is to summarize the inflammatory mechanism of COPD and the regulatory effect of moxibustion treatment, so as to provide a theoretical basis and potential therapeutic target for moxibustion as an adjunctive therapy for both stable and acute exacerbation stages of COPD.
Revisão e perspetiva
Materials and methods
To ensure a transparent and reproducible synthesis, a systematic literature search was conducted in PubMed, Embase, Cochrane Library, Web of Science, China National Knowledge Infrastructure (CNKI), Wanfang Data, Chinese Science and Technology Journal Database (VIP), and China Biology Medicine (CBM) from inception to July 21, 2026, using MeSH and free‑text terms related to COPD, moxibustion, inflammation, TLR4/NF‑κB, IL‑33/ST2, and Th17/Treg. The review included full-length RCTs and mechanistic studies involving patients with stable COPD or AECOPD that reported lung function, quality of life, inflammatory biomarkers, or exacerbation frequency. Reviews and case reports were excluded. Evidence from acupuncture-only interventions, non-COPD disease models, and animal studies was considered only as indirect mechanistic evidence and was not treated as direct evidence of moxibustion efficacy in COPD. Two reviewers independently extracted data on study design, population, intervention details, outcomes, and adverse events; findings were synthesized narratively owing to substantial heterogeneity in protocols and outcome measures.
Inflammatory mechanisms of COPD
Inflammatory cells and mediators in stable COPD. The stable phase of COPD is characterized by infiltration of macrophages, neutrophils, CD8⁺ T lymphocytes, and, in some phenotypes, eosinophils11. Macrophages are increased in number and activity in the airways and release TNFα, IL8, and oxidants, contributing to pulmonary tissue damage and airway remodeling12,13,14. T lymphocytes, especially CD8⁺ cells, contribute to epithelial and alveolar injury and correlate with disease severity15,16,17. An imbalance of Th1/Th2 and Th17/Treg cells has been observed in a subset of COPD patients and may further perpetuate chronic inflammation, though its prevalence and dominance vary across inflammatory phenotypes18,19. Key inflammatory mediators include TNFα, IL6, IL8, TGFβ, and matrix metalloproteinases, which are involved in both inflammation and tissue remodeling20,21,22. The TLR4/NFκB pathway is an important inflammatory signaling pathway: lipopolysaccharide (LPS) and other ligands activate TLR4, leading to NFκB nuclear translocation and transcription of proinflammatory cytokines23,24 Additionally, neutrophil extracellular traps and dysfunction of histone deacetylase 2 contribute to steroid resistance and persistent inflammation25,26,27,28.
Inflammatory mechanisms in acute exacerbation of COPD (AECOPD). During AECOPD, neutrophils and eosinophils increase markedly, and airway epithelial cells release IL33, which activates type 2 innate lymphoid cells (ILC2s) and promotes Th2type cytokine production (IL5, IL13)11,28,29. This IL33/ST2/ILC2 axis drives eosinophilic inflammation and mucus hypersecretion30,31,32. Moreover, systemic levels of TNFα, IL6, IL8, and Creactive protein rise significantly, and damageassociated molecular patterns such as high-mobility group box 1 (HMGB1) are released, amplifying the inflammatory cascade28,33,34. Emerging evidence also highlights the role of necroptosis and the NLRP3 inflammasome in amplifying tissue damage during exacerbations35,36. The interaction between the TLR4/NFκB and IL33/ST2 pathways is particularly notable during exacerbations: preclinical evidence from in vitro and animal models suggests that TLR4 activation upregulates IL33 expression, while IL33 in turn enhances ILC2 activity, potentially establishing a synergistic loop that amplifies airway inflammation37,38. However, direct human evidence for this loop is limited and needs to be further inferred and studied.
Evidence for the effectiveness of moxibustion in COPD and its regulation of inflammation
Given the central role of the TLR4/NF-κB and IL‑33/ST2 pathways in driving COPD airway inflammation, interventions that modulate these signals may offer therapeutic benefit. Moxibustion, a traditional Chinese therapy with established anti‑inflammatory properties, has been evaluated in this context. Numerous randomized controlled trials (RCTs) and metaanalyses have evaluated moxibustion as an adjunctive therapy for both stable COPD and AECOPD. A metaanalysis by Lou et al. showed that adjunctive moxibustion significantly reduces acute exacerbation frequency, improves forced expiratory volume in one second (FEV₁) and the sixminute walk distance (6MWD)39. Another metaanalysis on heatsensitive moxibustion reported promising long-term effects and acceptable safety outcomes40. Nevertheless, such results are constrained by the quality heterogeneity and inconsistent follow‑up durations across included trials. In a multicenter RCT, Yifei moxibustion (applied along the Du meridian) significantly lowered COPD assessment test (CAT) scores and improved patientreported outcomes41. In patients with AECOPD, thunderfire moxibustion combined with conventional medicine improved blood gas parameters, lung function, and promoted Th17/Treg immune balance, reducing subsequent exacerbation frequency10. Grainsized moxibustion at Zusanli (ST36) shortened antibiotic use and decreased Creactive protein levels42.
Table 1 summarizes key RCTs on moxibustion for COPD. The included studies reported improvements in clinical outcomes, especially those that examined changes in inflammatory biomarkers, providing evidence to support in-depth study of pathway specificity10,37,38,42,43,44,45,46,47. Across relevant studies10,38,43,45,46, moxibustion was associated with reductions in proinflammatory mediators (TNFα, IL6, IL8) and modulation of immune cells (increased CD4⁺, CD4⁺/CD8⁺ ratio, and Treg proportion; decreased Th17 proportion). However, important limitations exist: sample sizes are uniformly small, all studies are singlecenter, moxibustion protocols (acupoints, duration, frequency, moxa amount) are highly heterogeneous, and shamcontrols are absent. Moreover, most trials combined moxibustion with other interventions (herbal decoctions, pharmacotherapy, or rehabilitation), precluding isolation of its independent effect. Direct pathwayspecific molecular assays in human samples are scarce, and blinding of outcome assessment was rarely reported.
Potential mechanisms of moxibustion in regulating COPD inflammation
Regulation of inflammatory cells and immune balance. Moxibustion has been shown to enhance systemic immune function by increasing serum immunoglobulins (IgA, IgG, IgM) and improving Tcell subsets48,49. Thunderfire moxibustion promotes Th17/Treg balance in AECOPD patients, with increased Treg proportion and IL10 levels, and decreased Th17 proportion and IL17 levels10. Acupoint application combined with moxibustion plus pulmonary rehabilitation also elevated CD4⁺ and CD4⁺/CD8⁺ ratios50. Above findings from human COPD studies provide direct clinical evidence for immune modulation by moxibustion. Additionally, the evidence derives from animal models or other disease settings and is therefore indirect point to additional mechanisms, including upregulation of immunoregulatory molecules, acupoint‑specific stimulation, and thermal effects, that may collectively contribute to an improved inflammatory environment. In animal models, local moxibustion at ST36 increased the expression of CD83, an immune regulatory molecule, and alleviated arthritis51. Electroacupuncture at BL13 and ST36 inhibited NLRP3 inflammasome activation and IL1βcontaining exosome release in COPD emphysema mice45. The thermal effect of moxibustion (≥43 °C) can activate transient receptor potential vanilloid 1 (TRPV1), which mediates antiinflammatory responses52. Although these indirect mechanisms are also inherent features of moxibustion, their specific role in COPD inflammatory regulation remains to be validated in human‑relevant models using moxibustion as the direct intervention.
Inhibition of inflammatory mediators. Moxibustion reduces the levels of multiple proinflammatory cytokines in serum and bronchoalveolar lavage fluid. In stable COPD patients, heatsensitive moxibustion decreased TNFα and HMGB153,54, while thunderfire moxibustion lowered Creactive protein, IL8, and TNFα, and increased immunoglobulins55. These observations suggest that moxibustion may modulate systemic inflammatory markers in patients with COPD at the mediator level. There are also indirect clues from animal experiments or disease models other than COPD that bioactive substances produced during mugwort burning, together with local acupoint stimulation, may act synergistically to suppress the inflammatory response. In a rat model of acute lung injury, Artemisia argyi polyphenol extract reduced TNFα and IL6 in bronchoalveolar lavage fluid. Moxibustion at ST36 also alleviated foot swelling and decreased serum TNFα and IL1β in arthritis models51. The essential oils and flavonoids released during moxa combustion have bronchodilatory, antitussive, and expectorant effects and can regulate Tolllike receptor signaling56,57,58,59. As intrinsic to moxibustion practice, the actual role of these indirect mechanisms on the inflammatory environment of COPD remains uncertain, and direct studies in relevant models are needed to establish their translational relevance.
Intervention on key signaling pathways.
TLR4/NFκB pathway. Moxibustion is closely associated with the TLR4/NFκB pathway. Network pharmacology and molecular docking analyses predict that transdermal components of Artemisia argyi target transient receptor potential channels and TLR signaling in COPD59. During moxibustion, flavonoid compounds increase and can downregulate TLR4MyD88NFκB signaling, reducing IL12, TNFα, and TNFβ expression60. In a rheumatoid arthritis model, moxibustion inhibited macrophage M1 polarization via the TLR4/MyD88/NFκB pathway, associated with Tcell immunoglobulin and mucincontaining protein3 regulation61. Though this observation originates from a different disease context, it provides indirect support for the pathway‑modulating capacity of moxibustion in inflammatory disorders. Beyond direct pathway modulation, moxibustion may activate the antioxidant nuclear factor erythroid 2-related factor 2 (Nrf2) pathway, thereby reducing oxidative stress that amplifies COPD inflammation. This has been demonstrated in diabetic neuropathy and colitis models62,63, but requires validation in COPD. Figure 1 illustrates how moxibustion may downregulate TLR4/NFκB signaling to alleviate COPD inflammation.
IL33/ST2 pathway. Moxibustion can modulate IL33 expression. In asthmatic rats, moxibustion significantly reduced IL33 mRNA in lung tissue, improved lung function, and decreased eosinophil infiltration64. Asthma and COPD share overlapping characteristics in terms of airway inflammation types. Therefore, both possess certain referential value. Since IL33 is induced by cigarette smoke, pathogens, and allergens, and drives ILC2dependent eosinophilic inflammation in COPD, inhibition of IL33/ST2 signaling may reduce acute exacerbations65,66,67,68,69. Moxibustion may also affect the crosstalk between TLR4/NFκB and IL33/ST2 pathways via microRNA146a (miR146a). miR146a is a negative regulator that suppresses both TLR4 function and IL33 responses70,71. Acupuncture has been shown to increase miR146a expression72, suggesting a potential shared mechanism for moxibustion, though direct evidence in COPD is lacking. Given that moxibustion and acupuncture share the common feature of acupoint stimulation, this finding from acupuncture offers a plausible hypothesis for moxibustion. Nonetheless, the two modalities differ in intervention type (thermal vs. needle stimulation), and whether moxibustion exerts similar miR‑146a‑mediated effects in COPD requires direct investigation. Figure 2 depicts the IL33/ST2/ILC2 pathway and the putative regulatory sites of moxibustion.
Overall, available evidence suggests that moxibustion may exert multitarget antiinflammatory effects in COPD by regulating immune cell balance (Th17/Treg), suppressing proinflammatory mediators, and modulating TLR4/NFκB and IL33/ST2 signaling, likely through both thermal (TRPV1) and chemical (flavonoids, volatile oils) mechanisms, as well as neuroimmune reflexes73.
Conclusões
The evidence reviewed indicates that moxibustion may influence COPD-associated airway inflammation at the levels of immune-cell activity, inflammatory mediator production, and intracellular signaling. Findings from clinical and preclinical studies suggest that thermal stimulation, constituents released during moxa combustion, and neuroimmune regulation may act through several interconnected mechanisms. Among these, modulation of the TLR4/NF-κB and IL-33/ST2 pathways may contribute to the observed effects on steroid-resistant inflammation and acute exacerbations. Nevertheless, translation of these findings into clinical practice remains limited by insufficient direct mechanistic evidence, uncertainty regarding pharmacokinetic processes, variation in moxibustion procedures, and the scarcity of high-quality clinical trials. Further studies should investigate causal mechanisms rather than relying primarily on associations between treatment and changes in inflammatory biomarkers. Standardized and reproducible protocols should also be developed and evaluated through adequately powered multicenter randomized controlled trials. Multi-omics approaches and artificial intelligence may facilitate the identification of pathway interactions, refinement of acupoint and dose selection, and stratification of patients according to inflammatory endotypes. Current clinical and experimental findings therefore provide preliminary support for the proposed regulation of TLR4/NF-κB- and IL-33/ST2-mediated inflammatory networks by moxibustion. Confirmation of this mechanism and its clinical relevance will require rigorous mechanistic research, consistent intervention standards, and robust clinical evidence.
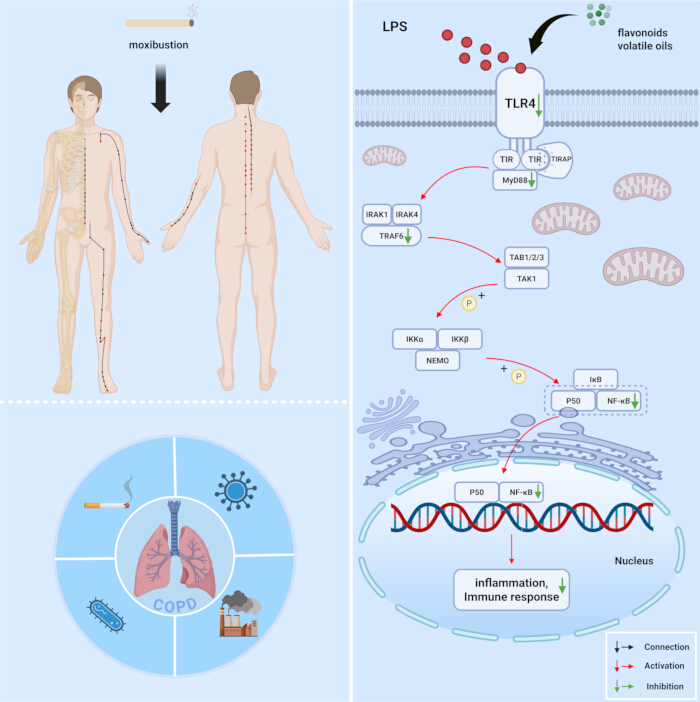
Figure 1: Proposed regulation of TLR4/NF-κB signaling by moxibustion in COPD. The diagram illustrates the lipopolysaccharide-induced TLR4/MyD88/TRAF6/NF-κB inflammatory signaling cascade and the proposed inhibitory effects of flavonoids and volatile oils released during moxibustion. Red arrows indicate activation, green arrows indicate inhibition, and black arrows indicate connections. Created with BioRender.com. Abbreviations: COPD = chronic obstructive pulmonary disease; IκB = inhibitor of nuclear factor kappa B; IKK = IκB kinase; LPS = lipopolysaccharide; MyD88 = myeloid differentiation primary response 88; NF-κB = nuclear factor kappa B; TIR = Toll/interleukin-1 receptor; TIRAP = TIR domain-containing adaptor protein; TLR4 = Toll-like receptor 4; TRAF6 = tumor necrosis factor receptor-associated factor 6. Please click here to view a larger version of this figure.
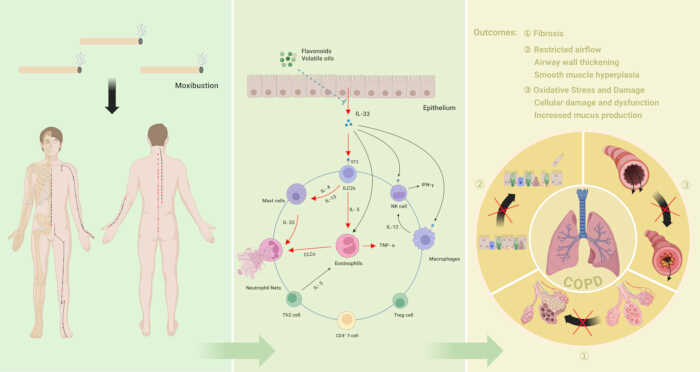
Figure 2: Proposed regulation of the IL-33/ST2/ILC2 inflammatory pathway by moxibustion in COPD. The diagram illustrates the proposed effects of moxibustion on epithelial IL-33 release, immune-cell responses, and COPD-related outcomes, including fibrosis, restricted airflow, airway-wall thickening, smooth-muscle hyperplasia, oxidative stress, cellular damage, and mucus production. Red arrows indicate activation, blue lines indicate cellular interactions, and black arrows marked with crosses indicate inhibition of the associated pathological changes. Created with BioRender.com. Abbreviations: CLCs = Charcot–Leyden crystals; COPD = chronic obstructive pulmonary disease; ILC2s = group 2 innate lymphoid cells; IFN-γ = interferon gamma; IL = interleukin; NK = natural killer; ST2 = suppression of tumorigenicity 2; Th2 = T helper 2; TNF-α = tumor necrosis factor alpha; Treg = regulatory T cell. Please click here to view a larger version of this figure.
Table 1: Randomized controlled trials of moxibustion for COPD and its regulation of inflammation. The table summarizes the study populations, treatment strategies, acupoint selection, treatment duration, outcome measures, adverse events, and principal findings of the included trials. Abbreviations: AECOPD = acute exacerbation of chronic obstructive pulmonary disease; CAT = COPD assessment test; CCL18 = C-C motif chemokine ligand 18; CD = cluster of differentiation; COPD = chronic obstructive pulmonary disease; CRP = C-reactive protein; FEV₁ = forced expiratory volume in 1 s; FEV₁/FVC = ratio of forced expiratory volume in 1 s to forced vital capacity; FVC = forced vital capacity; IL = interleukin; mMRC = modified Medical Research Council dyspnea scale; PEF = peak expiratory flow; PVR = pulmonary vascular resistance; RCT = randomized controlled trial; SpO₂ = peripheral oxygen saturation; TCM = traditional Chinese medicine; Th17 = T helper 17 cell; TNF-α = tumor necrosis factor alpha; Treg = regulatory T cell; 30sSST = 30 s sit-to-stand test; 6MWD = 6 min walk distance; NR = not reported. ↑denotes increase or improvement, and ↓ denotes decrease or reduction. Please click here to download this file.
Divulgações
The authors declare no competing interests.
Agradecimentos
This work was supported by the Science and Technology Planning Project of Guangdong Province (2023B1212060063); the Guangdong Basic and Applied Basic Research Foundation (2024A1515012150); the Noncommunicable Chronic Diseases-National Science and Technology Major Project (2024ZD0529005); the Guangzhou Municipal Science and Technology Bureau (2025A03J4069); and the Laibin City Scientific Research and Technology Development Program Project (LKG260135, LKG260132).
Referências
- Mannino DM. The changing definition and perception of COPD. Respir Care. 2022;67(6):750–755. doi: 10.4187/respcare.10059.
- May SM, Li JT. Burden of chronic obstructive pulmonary disease: healthcare costs and beyond. Allergy Asthma Proc. 2015;36(1):4–10. doi: 10.2500/aap.2015.36.3812.
- Lin P et al. A systematic review and meta-analysis of chronic obstructive pulmonary disease in Asia: risk factors for readmission and readmission rate. BMC Pulm Med. 2024;24(1):388. doi: 10.1186/s12890-024-03203-6.
- Wu J, Wang P, Shi Y, Han D. Advancing treatment strategies: a comprehensive review of drug delivery innovations for chronic inflammatory respiratory diseases. Pharmaceutics. 2023;15(8):2151. doi: 10.3390/pharmaceutics15082151.
- Ye C et al. Association between systemic immune-inflammation index and chronic obstructive pulmonary disease: a population-based study. BMC Pulm Med. 2023;23(1):295. doi: 10.1186/s12890-023-02583-5.
- Venkatesan P. GOLD COPD report: 2024 update. Lancet Respir Med. 2024;12(1):15–16. doi: 10.1016/S2213-2600(23)00461-7.
- Ye J, Yao P, Shi X, Yu X. A systematic literature review and meta-analysis on the impact of COPD on atrial fibrillation patient outcome. Heart Lung. 2022;51:67–74. doi: 10.1016/j.hrtlng.2021.09.001.
- Shi Y et al. Research progress on classic Chinese medicine compounds and monomers in the treatment of chronic obstructive pulmonary disease. World Chin Med. 2024;19(11):1693–1700. doi: 10.3969/j.issn.1673-7202.2024.11.026.
- Luo Q et al. Observations on the efficacy of moxibustion and acupuncture point injection as main treatment for stable chronic obstructive pulmonary disease. Shanghai J Acupunct Moxibustion. 2012;31(12):871–873. doi: 10.3969/j.issn.1005-0957.2012.12.871.
- Pan X et al. Therapeutic observation of thunder-fire moxibustion in treating acute exacerbation of chronic obstructive pulmonary disease and its effect on peripheral blood Th17/Treg immune balance. Shanghai J Acupunct Moxibustion. 2024;43(4):374–380. doi: 10.13460/j.issn.1005-0957.2024.04.0374.
- Barnes PJ. Immunology of asthma and chronic obstructive pulmonary disease. Nat Rev Immunol. 2008;8(3):183–192. doi: 10.1038/nri2254.
- de Boer WI et al. Transforming growth factor beta1 and recruitment of macrophages and mast cells in airways in chronic obstructive pulmonary disease. Am J Respir Crit Care Med. 1998;158(6):1951–1957. doi: 10.1164/ajrccm.158.6.9803053.
- Huang AX, Lu LW, Liu WJ, Huang M. Plasma inflammatory cytokine IL-4, IL-8, IL-10, and TNF-alpha levels correlate with pulmonary function in patients with asthma-chronic obstructive pulmonary disease overlap syndrome. Med Sci Monit. 2016;22:2800–2808. doi: 10.12659/MSM.896458.
- Larsson K. Inflammatory markers in COPD. Clin Respir J. 2008;2(Suppl 1):84–87. doi: 10.1111/j.1752-699X.2008.00089.x.
- Hodge G, Hodge S. Steroid-resistant CD8+CD28null NKT-like pro-inflammatory cytotoxic cells in chronic obstructive pulmonary disease. Front Immunol. 2016;7:617. doi: 10.3389/fimmu.2016.00617.
- Li R, Song W, Mei D. Prognostic value of CD14 expression in peripheral blood mononuclear cell membrane in patients with severe COPD complicated with pulmonary infection. Iran J Immunol. 2024;21(3):234–242. doi: 10.22034/iji.2024.102320.2783.
- Ono Y et al. Characterization of IL-6R-expressing monocytes in the lung of patients with chronic obstructive pulmonary disease. Respir Investig. 2024;62(5):856–866. doi: 10.1016/j.resinv.2024.07.013.
- Barnes PJ. Targeting cytokines to treat asthma and chronic obstructive pulmonary disease. Nat Rev Immunol. 2018;18(7):454–466. doi: 10.1038/s41577-018-0006-6.
- Ito JT et al. Effect of exercise training on modulating the Th17/Treg imbalance in individuals with severe COPD: a randomized controlled trial. Pulmonology. 2025;31(1):2441069. doi: 10.1080/25310429.2024.2441069.
- Barnes PJ et al. Pulmonary biomarkers in chronic obstructive pulmonary disease. Am J Respir Crit Care Med. 2006;174(1):6–14. doi: 10.1164/rccm.200510-1659PP.
- Churg A, Cosio M, Wright JL. Mechanisms of cigarette smoke-induced COPD: insights from animal models. Am J Physiol Lung Cell Mol Physiol. 2008;294(4):L612–L631. doi: 10.1152/ajplung.00390.2007.
- MacNee W, Donaldson K. Mechanism of lung injury caused by PM10 and ultrafine particles with special reference to COPD. Eur Respir J Suppl. 2003;40:47s–51s. doi: 10.1183/09031936.03.00403203.
- Wang L et al. Hydrogen sulfide attenuates cigarette smoke-induced pyroptosis through the TLR4/NF-kappaB signaling pathway. Int J Mol Med. 2022;49(5):56. doi: 10.3892/ijmm.2022.5112.
- Chen X et al. Effects of moxibustion on intestinal barrier function and TLR4/NF-kappaB p65 signaling pathway in obese rats. Chin Acupunct Moxibustion. 2024;44(4):449–454, 459. doi: 10.13703/j.0255-2930.20230529-k0003.
- Yao H, Rahman I. Role of histone deacetylase 2 in epigenetics and cellular senescence: implications in lung inflammaging and COPD. Am J Physiol Lung Cell Mol Physiol. 2012;303(7):L557–L566. doi: 10.1152/ajplung.00175.2012.
- He R et al. The role of HDAC3 and its inhibitors in regulation of oxidative stress and chronic diseases. Cell Death Discov. 2023;9(1):131. doi: 10.1038/s41420-023-01399-w.
- Yu JJ et al. An essential role for IL-17 in preventing pathogen-initiated bone destruction: recruitment of neutrophils to inflamed bone requires IL-17 receptor-dependent signals. Blood. 2007;109(9):3794–3802. doi: 10.1182/blood-2005-09-010116.
- Chen J et al. DNA of neutrophil extracellular traps promote NF-kappaB-dependent autoimmunity via cGAS/TLR9 in chronic obstructive pulmonary disease. Signal Transduct Target Ther. 2024;9(1):163. doi: 10.1038/s41392-024-01881-6.
- Silver JS et al. Inflammatory triggers associated with exacerbations of COPD orchestrate plasticity of group 2 innate lymphoid cells in the lungs. Nat Immunol. 2016;17(6):626–635. doi: 10.1038/ni.3443.
- Riera-Martínez L et al. The role of IL-33/ST2 in COPD and its future as an antibody therapy. Int J Mol Sci. 2023;24(10):8702. doi: 10.3390/ijms24108702.
- Taruselli MT et al. IL-33 induces cellular and exosomal miR-146a expression as a feedback inhibitor of mast cell function. J Immunol. 2024;212(8):1277–1286. doi: 10.4049/jimmunol.2200916.
- Zhou Y, Xu Z, Liu Z. Role of IL-33-ST2 pathway in regulating inflammation: current evidence and future perspectives. J Transl Med. 2023;21(1):902. doi: 10.1186/s12967-023-04782-4.
- Di Stefano A et al. Increased expression of nuclear factor-kappaB in bronchial biopsies from smokers and patients with COPD. Eur Respir J. 2002;20(3):556–563. doi: 10.1183/09031936.02.00272002.
- Mallia P et al. Experimental rhinovirus infection as a human model of chronic obstructive pulmonary disease exacerbation. Am J Respir Crit Care Med. 2011;183(6):734–742. doi: 10.1164/rccm.201006-0833OC.
- Gairola S, Sinha A, Kaundal RK. Linking NLRP3 inflammasome and pulmonary fibrosis: mechanistic insights and promising therapeutic avenues. Inflammopharmacology. 2024;32(1):287–305. doi: 10.1007/s10787-023-01389-5.
- Lu P et al. Mitochondrial DNA induces nucleus pulposus cell pyroptosis via the TLR9-NF-kappaB-NLRP3 axis. J Transl Med. 2023;21(1):389. doi: 10.1186/s12967-023-04266-5.
- Qin G. Clinical research of six-hole box moxibustion in the treatment of acute exacerbation of chronic obstructive pulmonary disease. Chin Med Mod Distance Educ China. 2024;22(8):118–121. doi: 10.3969/j.issn.1672-2779.2024.08.039.
- Yu S, Fan H. Effects of beneficial lung and gentle moxibustion combined with Sanfu paste on the efficacy, CASA score, and lung function of patients with stable COPD (lung and kidney qi deficiency type). J Sichuan Tradit Chin Med. 2023;41(11):197–200.
- Lou JL et al. Clinical efficacy and safety of moxibustion as adjuvant therapy for COPD in stable phase: a meta-analysis. Chin Acupunct Moxibustion. 2021;41(4):451–457. doi: 10.13703/j.0255-2930.20200213-k0004.
- Sheng H, Zhu M. Meta-analysis of heat-sensitive moxibustion in the treatment of chronic obstructive pulmonary disease. Shanghai Med Pharm J. 2021;42(6):35–38, 59. doi: 10.3969/j.issn.1006-1533.2021.06.011.
- Wang M et al. A multicenter randomized controlled study of the effects of beneficial lung moxibustion on quality of survival and satisfaction with outcomes in patients with stable chronic obstructive pulmonary disease. J Tradit Chin Med. 2019;60(14):1202–1208. doi: 10.13288/j.11-2166/r.2019.14.009.
- Fu L, Xu TS. Clinical observation of grain-sized moxibustion for acute attack of chronic obstructive pulmonary disease due to accumulation of phlegm and stasis. Shanghai J Acupunct Moxibustion. 2014;33(12):1089–1090. doi: 10.13460/j.issn.1005-0957.2014.12.1089.
- Yang X. Nursing effect of acupuncture and moxibustion combined with traditional Chinese medicine nursing on patients with chronic obstructive pulmonary disease in stable stage. Chin Foreign Med Res. 2023;2(11):99–101.
- Xuan Y, Zhang X, Liu C, Li Y. Observation on effect of mild moxibustion on patients with stable chronic obstructive pulmonary disease. Pract J Card Cereb Pneumal Vasc Dis. 2019;27(S1):219–221.
- Meng X et al. Clinical study on modified Du moxibustion combined with tiotropium bromide inhalation powder for stable chronic obstructive pulmonary disease with lung-kidney yang deficiency syndrome. Hebei J Tradit Chin Med. 2023;45(9):1486–1489, 1493.
- Chen Z, Zheng W. Clinical study on Jianpi Huatan decoction combined with Yifei moxibustion in the treatment of stable-stage COPD. Chin Foreign Med Res. 2022;20(23):9–12. doi: 10.14033/j.cnki.cfmr.2022.23.003.
- Wen X, Chen C, Liang M. Clinical research of moxa cone moxibustion for improving quality of life in patients with chronic obstructive pulmonary disease in the stable phase. World Chin Med. 2013;8(6):658–660. doi: 10.3969/j.issn.1673-7202.2013.06.024.
- Chen J, Long S. Clinical observation of moxibustion in the treatment of acute episodes of elderly chronic bronchitis. Shaanxi J Tradit Chin Med. 2017;38(10):1460–1462. doi: 10.3969/j.issn.1000-7369.2017.10.070.
- Zhang Y, Cai SC, Xu W, Chu EX. Effect of long-snake moxibustion on immune function in elderly patients with chronic obstructive pulmonary disease. Shanghai J Acupunct Moxibustion. 2014;33(11):1011–1012. doi: 10.13460/j.issn.1005-0957.2014.11.1011.
- Rao L, Huang C, Huang C, Zeng W. Application of Chinese medicine acupoint application and acupoint moxibustion combined with pulmonary rehabilitation training in patients with chronic obstructive pulmonary disease. Med Innov China. 2023;20(21):129–133. doi: 10.3969/j.issn.1674-4985.2023.21.029.
- Li Y et al. Ccrl2-centred immune-related lncRNA-mRNA co-expression network revealed the local skin immune activation mechanism of moxibustion on adjuvant arthritis mice. Life Sci. 2023;329:121910. doi: 10.1016/j.lfs.2023.121910.
- Wang X, Wang YS, Wang YY. An exploration of research ideas on the lipid regulation mechanism of moxibustion based on its warm and hot stimulation effects. Lishizhen Med Mater Med Res. 2016;27(10):2462–2463. doi: 10.3969/j.issn.1008-0805.2016.10.055.
- Liang Y. Clinical observation of 44 patients with stable chronic obstructive pulmonary disease treated with heat-sensitive suspension moxibustion at acupoints. J Tradit Chin Med. 2018;59(9):765–768. doi: 10.13288/j.11-216/r.2018.09.012.
- Lu P. Effect of thermal moxibustion on pulmonary function and serum TNF-alpha and HMGB1 levels in patients with stable chronic obstructive pulmonary disease. CJGMCM. 2021;36(6):960–962. doi: 10.3969/j.issn.1003-8914.2021.06.040.
- Fan L et al. Clinical study of thunder-fire moxibustion for stable chronic obstructive pulmonary disease based on acupoint identification. Mod J Integr Tradit Chin West Med. 2021;30(8):861–864. doi: 10.3969/j.issn.1008-8849.2021.08.014.
- Deng H, Shen X. The mechanism of moxibustion: ancient theory and modern research. Evid Based Complement Alternat Med. 2013;2013:379291. doi: 10.1155/2013/379291.
- Coyle ME, Wu L, Zhang AL, Xue CC. Moxibustion plus pharmacotherapy for chronic obstructive pulmonary disease. Aust J Acupunct Chin Med. 2016;10(1):12–20.
- Xie Q et al. Studies on the respiratory pharmacology of essential oil extracted from Artemisia argyi II: antianaphylactic effects. Chin J Mod Appl Pharm. 1999;16(5):3–6. doi: 10.13748/j.cnki.issn1007-7693.1999.05.002.
- Zhang X, Zhang X, Zhi X, Mao Z. Mechanism of transdermal absorption of moxibustion components in COPD intervention based on network pharmacology and molecular docking. Chin J Libr Inf Sci Tradit Chin Med. 2023;47(4):26–35. doi: 10.3969/j.issn.2095-5707.202211095.
- Yan J et al. Traditional Chinese medicine intervention in sepsis based on the TLR4 signaling pathway: a review. Chin J Exp Tradit Med Formulae. 2024;30(19):282–291. doi: 10.13422/j.cnki.syfjx.20231811.
- Luo K et al. Moxibustion inhibits macrophage M1 polarization through the Toll-like receptor 4/myeloid differentiation factor 88/nuclear factor kappa B signaling pathway by regulating T-cell immunoglobulin and mucin-containing protein 3 in rheumatoid arthritis. J Tradit Chin Med. 2024;44(6):1227–1235.
- Li J et al. Therapeutic effects of moxibustion simultaneously targeting Nrf2 and NF-kappaB in diabetic peripheral neuropathy. Appl Biochem Biotechnol. 2019;189(4):1167–1182. doi: 10.1007/s12010-019-03052-8.
- Wang X et al. Moxibustion regulates the BRG1/Nrf2/HO-1 pathway by inhibiting microRNA-222-3p to prevent oxidative stress in intestinal epithelial cells in ulcerative colitis and colitis-associated colorectal cancer. J Immunol Res. 2024;2024:8273732. doi: 10.1155/2024/8273732.
- Zhou JY et al. Effects of acupuncture and moxibustion on lung function and airway inflammation in asthmatic rats. Chin J Integr Tradit West Med. 2023;43(4):469–475. doi: 10.7661/j.cjim.20220214.103.
- Wang HH, Cheng SL. From biomarkers to novel therapeutic approaches in chronic obstructive pulmonary disease. Biomedicines. 2021;9(11):1638. doi: 10.3390/biomedicines9111638.
- Xia J et al. Increased IL-33 expression in chronic obstructive pulmonary disease. Am J Physiol Lung Cell Mol Physiol. 2015;308(7):L619–L627. doi: 10.1152/ajplung.00305.2014.
- Allinne J et al. IL-33 blockade affects mediators of persistence and exacerbation in a model of chronic airway inflammation. J Allergy Clin Immunol. 2019;144(6):1624–1637.e10. doi: 10.1016/j.jaci.2019.08.039.
- Kosloski MP et al. Pharmacokinetics and pharmacodynamics of itepekimab in healthy adults and patients with asthma: phase I first-in-human and first-in-patient trials. Clin Transl Sci. 2022;15(2):384–395. doi: 10.1111/cts.13157.
- Walzl G et al. Inhibition of T1/ST2 during respiratory syncytial virus infection prevents T helper cell type 2- but not Th1-driven immunopathology. J Exp Med. 2001;193(7):785–792. doi: 10.1084/jem.193.7.785.
- Mortazavi-Jahromi SS, Aslani M, Mirshafiey A. A comprehensive review of miR-146a molecular mechanisms in a wide spectrum of immune and nonimmune inflammatory diseases. Immunol Lett. 2020;227:8–27. doi: 10.1016/j.imlet.2020.07.008.
- Mann M et al. An NF-kappaB-microRNA regulatory network tunes macrophage inflammatory responses. Nat Commun. 2017;8(1):851. doi: 10.1038/s41467-017-00972-z.
- Zhang J et al. Acupuncture decreases NF-kappaB p65, miR-155, and miR-21 and increases miR-146a expression in chronic atrophic gastritis rats. Evid Based Complement Alternat Med. 2016;2016:9404629. doi: 10.1155/2016/9404629.
- Cho ZH et al. Neural substrates, experimental evidence, and functional hypothesis of acupuncture mechanisms. Acta Neurol Scand. 2006;113(6):370–377. doi: 10.1111/j.1600-0404.2006.00600.x.