Este protocolo descreve um modelo de roedor sem o uso de óculos ou sutura das pálpebras para induzir miopia por meio de injeções subconjuntivais de TGF-β2, que ativa o eixo NLRP3/IL-1β-MMP2 provocando alongamento axial, enquanto um regime dividido de registro biométrico minimiza artefatos da anestesia para obter dados de alta fidelidade.
Artigo de método
Estabelecimento de um Modelo de Miopia em Roedores Induzido por TGF-β Utilizando Injeções Subconjuntivais
Neste artigo
Resumo
Resumo
A miopia é uma preocupação importante de saúde pública global caracterizada por alongamento axial excessivo e remodelação da matriz extracelular (ECM) da esclera. Embora modelos experimentais sejam essenciais para investigar esses mecanismos, os métodos tradicionais de desfoque óptico em pequenos roedores apresentam limitações técnicas. Aqui, um modelo farmacológico padronizável de miopia foi estabelecido e avaliado por meio de injeções subconjuntivais repetidas de fator de crescimento transformador beta (TGF-β). Para alcançar uma entrega direcionada, foi desenvolvida uma técnica cirúrgica de estabilização com as duas mãos para everter a pálpebra superior, permitindo que uma agulha de 33 gauge atinja a conjuntiva palpebral em um ângulo raso de 20°–30°. Por meio de triagem in vivo em ratos, identificou-se o TGF-β2 (500 pg/olho) como um potente indutor do crescimento posterior do olho. A titulação subsequente de resposta à dose em camundongos revelou um perfil em forma de U invertido. Na coorte principal de validação, a dose mais baixa (250 pg/olho) induziu alongamento axial acentuado (0,197 ± 0,012 mm) e desvios refrativos miópicos (−1,58 ± 0,63 D). Em nível molecular, a administração repetitiva de TGF-β2 ativou a cascata do inflamassoma da família de receptores tipo NOD contendo domínio pirina 3 (NLRP3) / interleucina-1β (IL-1β) na retina e aumentou a expressão da metaloproteinase da matriz 2 (MMP2) em ambas as espécies. Associado a um regime de registro biométrico dividido em dois dias, que minimiza artefatos associados à anestesia, este protocolo fornece uma plataforma confiável e escalável para avaliar intervenções anti-miopia.
Introdução
A miopia tornou-se uma preocupação importante de saúde pública global, com sua prevalência projetada para afetar quase 50% da população mundial até 20501,2. O principal fator patológico subjacente à miopia progressiva é o alongamento axial excessivo do olho, que provoca remodelação ativa da matriz extracelular e degeneração tecidual, levando ao afinamento estrutural das camadas oculares posteriores3. Essas alterações dinâmicas incluem tanto o remodelamento estrutural (caracterizado pela degradação da matriz extracelular da esclera, perda de colágeno e afinamento das camadas posteriores) quanto o remodelamento funcional (marcado pela redução da rigidez biomecânica, alteração da perfusão coroidal e sinalização inflamatória retino-RPE aberrante), os quais conjuntamente aumentam o risco vitalício de complicações que ameaçam a visão e de deficiência visual irreversível, incluindo maculopatia miópica, descolamento de retina, glaucoma e catarata prematura4,5,6,7. Apesar dos consideráveis encargos clínicos e socioeconômicos dessa condição, os mecanismos moleculares upstream precisos que regulam o crescimento ocular aberrante ainda não são completamente compreendidos. Portanto, elucidar as vias de sinalização que impulsionam o alongamento axial e desenvolver modelos animais reprodutíveis e padronizados são etapas fundamentais para identificar novos alvos terapêuticos e conter a epidemia global de miopia.
Embora a miopia por privação de forma (FDM) e a miopia induzida por lentes (LIM) sejam consideradas padrões-ouro para investigar o desfoque óptico e a emetropização8,9,10,11, implementar esses modelos de desfoque óptico em roedores pequenos — particularmente camundongos — apresenta desafios técnicos substanciais. O comportamento ativo de grooming dos camundongos frequentemente leva à soltura das lentes, exigindo medidas paliativas estressantes, como coleiras protetoras12Além disso, a fricção mecânica, a sutura das pálpebras e as alterações do microambiente sob o ocluder frequentemente causam complicações corneanas secundárias, como opacidade ou ulceração corneana.13,14,15Embora os modelos FDM e LIM continuem sendo paradigmas fundamentais para investigar o desfoque visual, complicações secundárias na superfície ocular—como opacidade corneana, fricção mecânica ou irritação devido à sutura palpebral—podem interferir nas medições biométricas ópticas15Esses artefatos procedimentais comprometem a estabilidade do filme lacrimal e a transparência corneana, levando a taxas mais altas de exclusão experimental e aumento do ruído nas medições13,16. Em contraste, a indução farmacológica contorna obstrutores físicos, preservando a clareza corneana e facilitando biometria óptica e ultrassônica confiável e reprodutível. Na miopia, o alongamento ocular excessivo é impulsionado por remodelação alterada da matriz extracelular (ECM) da esclera posterior17, onde o fator de crescimento transformador-beta (TGF-β) isoformas atuam como reguladores-chave da síntese de colágeno e proteoglicanas18,19. Evidências emergentes sugerem que a TGF-β a sinalização pode interagir com a inflamação ocular de baixo grau e com a degradação da matriz mediada pela metaloproteinase 2 da matriz (MMP2)20, potencialmente contribuindo para o remodelamento escleral e alongamento axial21,22,23,24. Isso é apoiado por níveis elevados de fator de crescimento transformador-beta 2 (TGF-β2), interleucina-6 (IL-6) e MMP2 relatados no humor aquoso de olhos míopes25,26,27, bem como a ativação do TGF-β / fator nuclear kappa B (NF-κB) / eixo MMP2 em modelos experimentais20,21. Embora esses achados reflitam uma sinalização molecular intraocular dinâmica durante a progressão da miopia, as contribuições anatômicas relativas para os marcadores no humor aquoso—seja pela secreção anterior local, fluxo de depósito subconjuntival ou difusão vítrea posterior—ainda precisam ser plenamente esclarecidas. No entanto, é necessário reconhecer o escopo e as limitações inerentes deste modelo farmacológico. Porque a TGF- subconjuntivalβ a entrega contornou o desfoque óptico e as vias de processamento visual, este modelo é o mais apropriado para dissecar cascatas bioquímicas downstream—especificamente TGF-β2 / Receptor semelhante a NOD, domínio pirina contendo 3 (NLRP3) / interleucina-1β (IL-1β) / Remodelação da MEC escleral mediada por MMP2 — e triagem de agentes terapêuticos candidatos que visam vias inflamatórias ou de degradação da matriz. Inversamente, não é apropriado para investigar transdução de sinal visual ascendente, sinalização óptica da retina para a esclera ou mecanismos de emetropização induzidos pela luz ambiental, nos quais os modelos tradicionais de FDM ou LIM permanecem indispensáveis.
Para abordar essas lacunas metodológicas, foi estabelecido e validado um modelo de miopia utilizando injeções subconjuntivais repetidas de TGF-β em ratos e camundongos, oferecendo uma abordagem aprimorada que minimiza o trauma mecânico e a irritação da superfície ocular. Ao contornar a necessidade de ocluders físicos, este protocolo proporciona controle preciso sobre a dosagem farmacológica e os cronogramas experimentais, reduzindo substancialmente os possíveis fatores de confusão comportamentais associados ao uso de dispositivos montados na cabeça. Neste estudo, avaliou-se a potência de três isoformas recombinantes humanas de TGF-β (que apresentam reatividade cruzada funcional validada em tecidos de roedores, com suporte na conservação da sequência28) em ratos e mapeou-se a cinética não linear da resposta à dose de TGF-β2 em camundongos. Importante, este regime padronizado induziu eficientemente a miopia fenotípica — caracterizada pelo alongamento axial e desvios refrativos miópicos simultâneos — e ativou o inflamassoma da família de receptores tipo NOD no domínio pirina contendo 3 (NLRP3) / interleucina-1β (IL-1β) e o eixo MMP2. Em última análise, este protocolo fornece uma estrutura viável e molecularmente definida para direcionar a remodelação escleral downstream, detalhando ao mesmo tempo seus limites operacionais específicos.
Protocolo
All animal experiments were conducted in accordance with the guidelines and regulations of the Institutional Animal Care and Use Committee (IACUC) of China Medical University (CMU). All procedures complied with the Association for Research in Vision and Ophthalmology (ARVO) Statement for the Use of Animals in Ophthalmic and Vision Research. Full approval from the CMU-IACUC was obtained prior to the initiation of all experiments. Animals were euthanized at the experimental endpoint in strict accordance with the guidelines of the Institutional Animal Care and Use Committee (IACUC) of China Medical University (CMU) and local animal welfare regulations.
1. Animals and ethical approval
- Obtain male Brown Norway (BN) rats (3–4 weeks of age, 60–80 g) and male C57BL/6 (B6) mice (3–4 weeks of age, 15–20 g) from an appropriate laboratory animal supplier.
- House all animals in a controlled environment (12 h light/dark cycle, 22 °C ± 2 °C, 50% ± 10% relative humidity) with ad libitum access to standard chow and water.
- Allow a minimum of 3 days of acclimatization prior to initiating any experimental procedure.
- Assign rats or mice randomly to treatment groups: vehicle control group and TGF-β2 injection group. Use a minimum of N = 5 animals per cohort to ensure adequate statistical power.
NOTE: A between-subjects design was used. Both eyes of an individual animal received identical treatments (either bilateral vehicle control [1–2 µL BSS] or bilateral active rhTGF-β2).- Measure bilateral ocular parameters (axial length and refractive error) for each animal.
NOTE: Ensure written CMU-IACUC approval is secured and that all personnel performing procedures are appropriately trained and certified.
- Measure bilateral ocular parameters (axial length and refractive error) for each animal.
2. Preparation of TGF-β2 solution
NOTE: Perform all reconstitution and dilution steps inside a certified biosafety cabinet using strict aseptic techniques.
- Reconstitute lyophilized recombinant human TGF-β2 in sterile 50% glycerol containing 0.1% bovine serum albumin (BSA) to prepare a 100 µg/mL stock solution.
- Prepare working solutions by performing serial dilutions of the stock solution in sterile Balanced Salt Solution (BSS).
- For rat cohorts (500 pg dose), dilute the stock solution to a final concentration of 250 ng/mL (250 pg/µL) for a 2 µL injection volume per eye.
- For mouse dose-response cohorts, prepare three independent working solutions at concentrations of 250 ng/mL, 375 ng/mL, and 500 ng/mL (250, 375, and 500 pg/µL) for a 1 µL injection volume per eye.
- Prepare single-use 15–20 µL aliquots in sterile microcentrifuge tubes, snap-freeze in liquid nitrogen, and store at -20 °C. Thaw aliquots on ice immediately prior to use.
CAUTION: Liquid nitrogen can cause severe cold burns and presents an asphyxiation hazard. Wear appropriate cryogenic PPE and handle it in a well-ventilated area in accordance with institutional safety procedures. - Prepare the vehicle control solution in parallel using sterile BSS supplemented with an equivalent matrix of 50% glycerol and 0.1% BSA.
3. Subconjunctival injection procedure
- Place animals in an induction chamber with 3–4% isoflurane for anesthetic induction. Subsequently, transfer the animal to a nose cone delivering 1.5–2% isoflurane for anesthetic maintenance.
CAUTION: Isoflurane is a volatile anesthetic. Use an appropriate scavenging system and handle it in accordance with institutional occupational health and safety procedures. - Verify an adequate depth of anesthesia by confirming the absence of a toe-pinch withdrawal reflex.
- Position the animal prone under a fiber-optic spotlight. Gently grasp, elevate, and slightly evert the superior eyelid using fine-tipped microforceps to fully expose the palpebral conjunctiva and conjunctival fornix (Figure 1B).
- Pre-wet a 10 µL glass micro-syringe and 33-gauge needle 2–3 times with the working solution to eliminate dead space. Load the target volume (2 µL for rats or 1 µL for mice) and purge all microbubbles.
CAUTION: Handle needles and other sharps carefully and dispose of them in an approved sharps container in accordance with institutional regulations. - Orient the 33-G needle with the bevel facing upward (bevel-up) and target the designated insertion site on the exposed palpebral conjunctival surface (Figure 1B,C).
- Insert the needle tip through the conjunctival epithelium at a shallow 20°–30° angle (Figure 1C).
- Gently advance the needle through the narrow submucosal space past the conjunctival fornix into the palpebral subconjunctival domain (Figure 1C).
CRITICAL STEP (structures to avoid): Strictly avoid penetrating the underlying meibomian glands or accidentally perforating deeper ocular structures. Visually confirm proper superficial placement under the spotlight by ensuring the needle bevel remains visible beneath the translucent conjunctival surface throughout advancement. - Slowly inject the solution over 5–10 s. Hold the needle in place for an additional 5 s before slowly withdrawing to prevent fluid backflow.
NOTE: Proper subconjunctival delivery is confirmed by immediate localized conjunctival elevation and blanching (bleb formation).- If a bleb fails to form or significant leakage occurs, perform a single re-injection at the inferior palpebral conjunctival space and record the deviation in the experimental log.
NOTE: Limit re-injections strictly to one attempt per eye per session; exclude animals with persistent delivery failure from longitudinal analysis.
- If a bleb fails to form or significant leakage occurs, perform a single re-injection at the inferior palpebral conjunctival space and record the deviation in the experimental log.
- Sanitize the micro-syringe cavity between individual animal injections within the same group by flushing 3 times with sterile 70% ethanol, followed by 5 times with sterile saline.
- Inspect the 33-G needle tip under magnification every 3–5 injections, and replace the needle immediately if tip dulling or bending occurs.
- Inject all vehicle-control animals first, before handling or injecting treatment cohorts, to eliminate the risk of pharmacological cross-contamination. Repeat the syringe sanitization cycle prior to transitioning to treatment groups.
- Rinse the syringe barrel and plunger with a dedicated micro-syringe cleaning solution, then with ultrapure water and absolute ethanol after each experimental session, and store dry.
- Repeat subconjunctival injections once weekly for 3 consecutive weeks (Days 0, 7, and 14). Perform longitudinal biometric assessments at baseline (Days −1 and 0) and endpoint (Days 20 and 21) as detailed in Section 4.
- Place the animal in a warm recovery cage lined with paper towels following the injection. Monitor the animal continuously until full sternal recumbency and normal ambulatory activity are regained.
- Inspect eyes under a stereomicroscope post-recovery to exclude intraocular hemorrhage, corneal opacity, or acute mechanical trauma. Monitor animals daily for signs of distress or localized infection.
4. Model validation methods
- Ocular refractive error assessment
- Place rodents on a thermostatically controlled heating pad to maintain physiological body temperature and prevent anesthetic cataracts. Maintain animals under light isoflurane anesthesia (1–1.5%) via a nose cone to ensure consistent anesthetic depth.
- Instill 1 drop of Mydrin-P (0.5% tropicamide and 0.5% phenylephrine hydrochloride) into each eye 10–15 min prior to measurement to induce complete cycloplegia and pupillary dilation.
- Position the animal in sternal recumbency under dim, indirect ambient lighting. Apply sterile BSS continuously right up to the moment of optical acquisition to preserve corneal transparency.
- Measure ocular refraction using an automated infrared photorefractometer within a strict 5–10 min window post-anesthetic induction. For BN rats, gently retract the eyelids manually to fully expose the dilated pupil during acquisition.
- Acquire three independent optical readings per eye and average the values to determine the baseline or endpoint refractive error.
CRITICAL STEP (Timing & Sequence): Conduct photorefraction on Day 1 of the evaluation sequence (Day –1 for baseline; Day 20 for endpoint) under dim lighting prior to any contact procedures. Performing photorefraction after contact ultrasonography or acoustic gel application severely disrupts corneal optics, scatters infrared light, and invalidates automated refractive readings.
- Axial length measurement via high-frequency B-scan ultrasonography
- On the following day (Day 0 for baseline or Day 21 for endpoint), evaluate ocular axial length under light isoflurane anesthesia (1–1.5%) using a handheld 16 MHz linear ultrasound probe calibrated to rodent tissue acoustic velocity (1532–1550 m/s).
- For B6 mice (direct corneal interface): Apply a baseline protective layer of Ginpol carbomer gel (0.2%) directly onto the cornea, followed by a layer of standard acoustic gel.
NOTE: Ensure the gel layer completely covers the corneal surface without introducing trapped air bubbles, which cause acoustic attenuation. - For BN Rats (transpalpebral interface): Position the animal with closed eyelids, apply ultrasound gel onto the outer eyelid surface, and acquire measurements transpalpebrally.
NOTE: Transpalpebral measurement eliminates direct corneal contact, significantly reducing the risk of corneal abrasion in larger rodent eyes.
- For B6 mice (direct corneal interface): Apply a baseline protective layer of Ginpol carbomer gel (0.2%) directly onto the cornea, followed by a layer of standard acoustic gel.
- Align the ultrasound probe and measure axial length along the central optical axis from the anterior ocular interface to the posterior scleral echo wall.
- Acquire ten independent replicate B-scan traces per eye and calculate the mean axial length.
- Gently flush residual acoustic gel from the eye using sterile BSS immediately following acquisition to prevent post-procedural corneal irritation.
CRITICAL STEP (zero-pressure touch): Place the ultrasound probe onto the gel interface with an extremely light, zero-pressure touch. Any downward physical pressure on the corneal apex artificially compresses the anterior chamber depth and introduces false axial length shortening. - Record the averaged axial length and refractive error measurements for subsequent analysis.
- On the following day (Day 0 for baseline or Day 21 for endpoint), evaluate ocular axial length under light isoflurane anesthesia (1–1.5%) using a handheld 16 MHz linear ultrasound probe calibrated to rodent tissue acoustic velocity (1532–1550 m/s).
Resultados
Establishment and anatomical validation of the subconjunctival injection model
To address technical variability associated with optical goggling or eyelid suturing, the subconjunctival space was validated between the palpebral and bulbar conjunctivae as a targeted localized drug reservoir (Figure 1A). Anatomical access via the superior fornix provided consistent exposure of the target site while maintaining ocular surface integrity (Figure 1B). Successful model establishment was confirmed by specific operational and biometric criteria, including the immediate transillumination verification of a localized, fluid-filled submucosal bleb (chemosis) over the target palpebral subconjunctival space without scleral perforation, tissue hemorrhage, or meibomian gland injury (Figure 1C), as well as longitudinal biometric verification of concurrent axial elongation (Δ AL > 0.15 mm in mice; >0.40 mm in rats) accompanied by a myopic refractive shift (Δ Refraction < −1.0 D) at Day 21 relative to vehicle-treated controls. Conversely, unsuccessful or suboptimal outcomes were identified by specific technical and physiological failure modes. Technical failure—such as premature fluid reflux upon needle withdrawal or inadvertent deep eyelid/orbital tissue penetration—resulted in minimal or absent bleb formation, leading to inadequate pharmacological retention and failure to induce myopic shifts; animals displaying persistent leakage were documented and excluded according to Protocol Step 3.8.1. Additionally, ocular surface complications from deep needle misplacement or excessive mechanical traction caused localized subconjunctival hemorrhage or corneal trauma, introducing confounding inflammatory responses. Suboptimal phenotypic outcomes were also observed during dose-response evaluations, where administration of suprathreshold concentrations (e.g., 500 pg/eye in mice) yielded an attenuated U-shaped response with reduced axial elongation, underscoring the physiological requirement for strict dose optimization. Verified localized drug retention under these standardized criteria ensured high-fidelity tissue targeting for downstream biometric and molecular analyses.
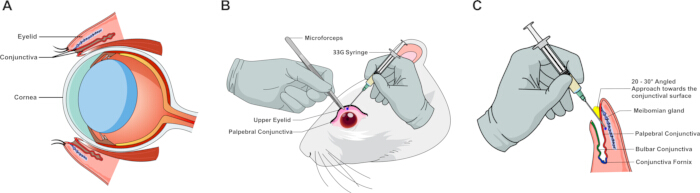
Figure 1: Anatomical landmarks and schematic illustration of the subconjunctival injection procedure in rodents. (A) Sagittal cross-section of the rodent eye depicting primary anatomical landmarks, including the eyelid, cornea, conjunctival sac, and targeted subconjunctival space. (B) Surgical demonstration of tissue stabilization and palpebral conjunctiva exposure using microforceps; the blue dot indicates the target needle insertion site for microinjection using a 33-gauge syringe. (C) High-magnification schematic illustrating the needle orientation and insertion trajectory relative to the palpebral conjunctival surface, conjunctival fornix, and underlying ocular structures. Please click here to view a larger version of this figure.
Screening of TGF-β isoforms in rats and dose-response titration of TGF-β2 in mice for axial elongation
Experiments were conducted in sequential, independent experimental cohorts comprising the dose-screening cohorts (Figure 2) and primary validation cohorts (Figure 3). Bilateral parameters were measured across cohorts, with individual animals (N) designated as the primary biological replicate. Inter-eye dependencies (OD versus OS within the same animal) were accounted for using two-way repeated-measures ANOVA or mixed-effects models, where appropriate. Continuous data are presented as mean ± SD. Differences between control and treatment groups were evaluated using two-tailed Student's t-tests, one-way ANOVA, or two-way repeated-measures ANOVA, where appropriate. A p-value < 0.05 was considered statistically significant.
To determine the most potent transforming growth factor-β (TGF-β) isoform and establish an optimal dosage regimen for inducing axial elongation, the effects of repeated subconjunctival injections in rat and mouse cohorts from baseline (Day 0) to Day 21 (Figure 2) were evaluated. Biometric recordings were performed using the two-day split regimen to prevent anesthesia-induced artifacts.
Three recombinant human TGF-β isoforms (TGF-β1, TGF-β2, and TGF-β3) were first screened in the rat cohort at a standardized concentration of 500 pg/eye (Figure 2A). One-way ANOVA, followed by post hoc multiple comparisons, revealed that all three isoforms significantly stimulated posterior ocular growth compared with the vehicle-treated control group over the 21-day period. While both TGF-β1 (0.444 ± 0.042 mm) and TGF-β3 (0.454 ± 0.049 mm) promoted significant axial elongation (p < 0.05 and p < 0.01 versus the control of 0.328 ± 0.071 mm, respectively), TGF-β2 induced the greatest axial length increase (0.486 ± 0.074 mm) and demonstrated the highest statistical significance (p < 0.001), establishing it as the most effective inducer of the myopic phenotype.
Based on the rat screening results, a dose-response titration of TGF-β2 in the mouse cohort was performed, testing three concentrations: 250, 375, and 500 pg/eye (Figure 2B). Subconjunctival TGF-β2 delivery resulted in an inverted U-shaped dose-response profile. The lowest dose (250 pg/eye) yielded the most significant acceleration in axial elongation compared to vehicle controls (0.177 ± 0.038 mm versus 0.044 ± 0.011 mm; p < 0.0001). At higher doses (375 and 500 pg/eye), the magnitude of axial length change progressively diminished, although it remained significantly higher than controls (0.123 ± 0.029 mm; p < 0.001 and 0.095 ± 0.024 mm; p < 0.01, respectively).
Together, these data establish a weekly subconjunctival regimen of 500 pg/eye for rats and 250 pg/eye for mice as the optimal parameters for subsequent structural and molecular investigations.
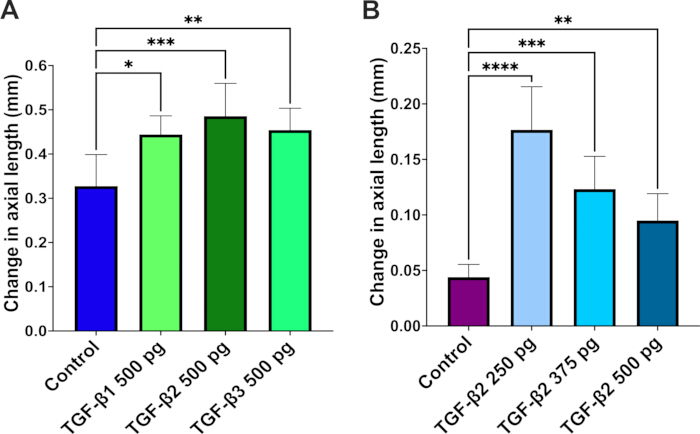
Figure 2: Dose-selection screening of transforming growth factor-β (TGF-β) isoforms and concentrations on axial length in rat and mouse eyes. (A) Change in axial length in rats (initial screening cohort), calculated as the difference between baseline (Day 0, before the first injection) and the final endpoint (Day 21), after three sequential subconjunctival injections of TGF-β1, TGF-β2, or TGF-β3 (500 pg/eye administered on Days 0, 7, and 14), compared with vehicle-treated controls. (B) Change in axial length in mice (dose-screening cohort), calculated as the difference between baseline (Day 0) and Day 21, after three sequential subconjunctival injections of TGF-β2 at three distinct concentrations (250, 375, or 500 pg/eye administered on Days 0, 7, and 14), compared with vehicle-treated controls. Data are presented as mean ± SD (N = 5 animals/group, representing 10 eyes per group). Statistical significance was evaluated by one-way ANOVA followed by post hoc multiple comparisons; *p < 0.05, **p < 0.01, ***p < 0.001, ****p < 0.0001 versus the vehicle control group. Please click here to view a larger version of this figure.
Repeated subconjunctival TGF-β2 injections induce ocular axial elongation and myopic shifts in rats and mice
To evaluate the biometric impact of repetitive subconjunctival TGF-β2 delivery (3 weekly injections), longitudinal changes in ocular axial length and refractive error from baseline to Week 3 in both rat and mouse models (Figure 3) were monitored. The two-day split protocol (refractive status captured on Day 20, followed by B-scan ultrasonography on Day 21) minimized potential anesthetic artifacts and ocular stress. Both species exhibited phenotypic shifts consistent with experimental myopia development following this multi-dose regimen.
In the rat cohort, animals receiving repeated subconjunctival injections of 500 pg/eye TGF-β2 showed a significantly greater increase in axial length over the 21-day period compared to vehicle controls (0.466 ± 0.045 mm versus 0.388 ± 0.032 mm; p < 0.01; Figure 3A). This elongation was accompanied by a significant myopic shift in refractive error (p < 0.05; Figure 3B). While vehicle-control eyes exhibited an expected slight hyperopic drift (+0.31 ± 0.93 D), TGF-β2–treated eyes transitioned into a myopic refractive state (−1.38 ± 0.91 D).
Consistent with the rat data, mice treated with 250 pg/eye TGF-β2 also demonstrated distinct structural and refractive changes. Axial elongation was significantly enhanced in TGF-β2–treated mice compared to vehicle controls (0.197 ± 0.012 mm versus 0.110 ± 0.014 mm; p < 0.0001; Figure 3C). Furthermore, this structural elongation resulted in a significant myopic shift (p < 0.05; Figure 3D), effectively reversing the natural hyperopic refraction seen in control mice (+2.25 ± 1.77 D) to a myopic profile (−1.58 ± 0.63 D).
To verify inter-ocular response symmetry and confirm that pooling bilateral ocular measurements does not introduce statistical bias, axial elongation dynamics were evaluated separately for left (OS, n = 5) and right (OD, n = 5) eyes within each group (Supplementary Figure 1). In both rats (Supplementary Figure 1A) and mice (Supplementary Figure 1B), no statistically significant difference was observed between OS and OD eyes within either the vehicle-control or TGF-β2–treated cohorts, confirming symmetrical response dynamics across eyes. Furthermore, both OS and OD eyes in TGF-β2–treated animals demonstrated consistent and robust axial elongation relative to their corresponding vehicle controls (p < 0.05 for rats; p < 0.0001 for mice), supporting the validity of accounting for bilateral measurements in the primary biometric analysis.
Collectively, these findings demonstrate that repeated subconjunctival administration of TGF-β2 effectively drives posterior ocular growth and a corresponding myopic refractive shift in both rodent models (Figure 3 and Supplementary Figure 1).
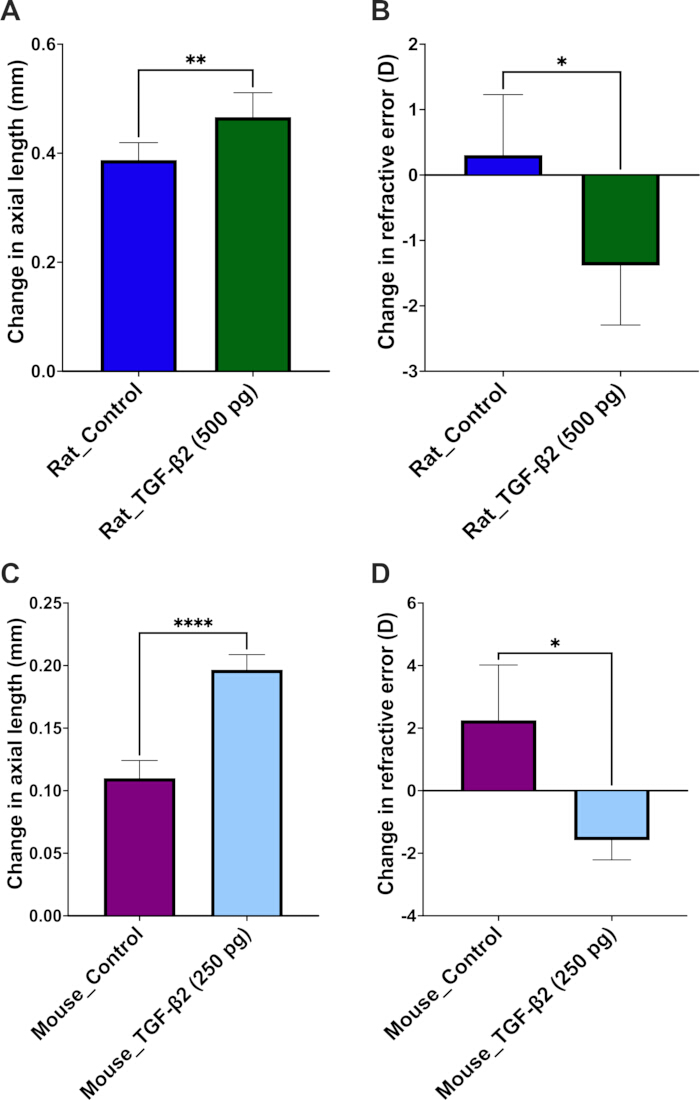
Figure 3: Primary validation of TGF-β2 effects on axial elongation and refractive error in independent rat and mouse cohorts. (A) Change in axial length in rats, calculated as the difference between baseline and the Week 3 final endpoint in eyes receiving subconjunctival TGF-β2 (500 pg/eye administered sequentially on Days 0, 7, and 14) or vehicle control. (B) Change in refractive error in the same rat eyes, delineating a significant myopic shift in the TGF-β2-treated group compared with the vehicle-control group. (C) Change in axial length in mice (independent primary validation cohort), calculated as the difference between baseline and the Week 3 final endpoint in eyes receiving subconjunctival TGF-β2 (250 pg/eye administered on Days 0, 7, and 14) or vehicle control. (D) Change in refractive error in the same mouse eyes, revealing a corresponding negative dioptric shift under optimal TGF-β2 induction. Data are presented as mean ± SD (N = 5 animals/group, representing 10 eyes per group). Statistical significance was rigorously evaluated using unpaired two-tailed t-tests; *p < 0.05, **p < 0.01, ****p < 0.0001 versus the corresponding vehicle control group. Please click here to view a larger version of this figure.
Subconjunctival TGF-β2 administration upregulates scleral MMP2 expression during experimental myopia progression
To assess downstream tissue remodeling along the retino-scleral axis, matrix metalloproteinase 2 (MMP2) expression in scleral cross-sections following subconjunctival TGF-β2 administration (Figure 4) was evaluated. Quantitative immunofluorescence analysis of posterior ocular sections in the rat model demonstrated a significant upregulation of MMP2 protein levels within the scleral stroma of TGF-β2–treated eyes (500 pg/eye) at Day 21 compared with vehicle controls (p < 0.0001; Figure 4A, B).
A prominent MMP2 fluorescent signal was localized throughout the scleral matrix underlying the retinal pigment epithelium (RPE) and choroidal layers, confirming localized MMP2-associated extracellular matrix (ECM) remodeling in the outer ocular coat during experimental myopia development. These structural changes in the sclera prompted further investigation into upstream molecular alterations within the adjacent retina.
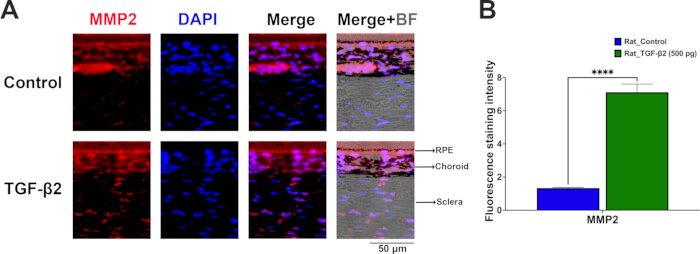
Figure 4: Subconjunctival TGF-β2 administration upregulates MMP2 expression in the rat sclera. (A) Representative immunofluorescence images of posterior ocular cross-sections showing scleral MMP2 expression (red) in vehicle-control and TGF-β2–treated (500 pg/eye) rats at Day 21. Cell nuclei were counterstained with DAPI (blue). Brightfield overlay (Merge+BF) delineates the anatomical boundaries of the RPE, choroid, and sclera. Scale bar = 50 µm. (B) Quantitative analysis of fluorescence staining intensity confirming a significant increase in scleral MMP2 expression in TGF-β2–treated rat eyes. Data are presented as mean ± SD (N = 3 independent biological replicates per group, 1 eye per animal). Statistical significance was evaluated using an unpaired two-tailed t-test; ****p < 0.0001 versus the vehicle control group. Abbreviations: RPE, retinal pigment epithelium; BF, brightfield. Please click here to view a larger version of this figure.
TGF-β2 induction upregulates MMP2 and inflammasome-related proteins in both rat and mouse retinas
To investigate the downstream molecular alterations induced by repetitive subconjunctival injections, immunofluorescence staining on posterior ocular sections from both Brown Norway rats and C57BL/6 mice at Day 21 (Figure 5A–D) was performed. All evaluations were performed on sagittal retinal sections strictly aligned to the optic nerve head to ensure consistent spatial orientation. Quantitative analysis revealed that weekly TGF-β2 administration significantly altered specific protein expression profiles across the retinal laminae in both species compared to vehicle controls (Figure 5E,F).
In the rat model, administration of 500 pg/eye TGF-β2 led to a significant increase in retinal TGF-β2 levels (p < 0.0001; Figure 5A,E). This upregulation was accompanied by elevated expression of matrix metalloproteinase 2 (MMP2) (p < 0.0001; Figure 5B,E), indicating active extracellular matrix remodeling. Furthermore, TGF-β2 treatment activated the retinal inflammatory cascade, evidenced by the upregulation of the inflammasome sensor NLRP3 (p < 0.0001; Figure 5C,E) and the pro-inflammatory cytokine IL-1β (p < 0.0001; Figure 5D,E).
Similarly, mice treated with 250 pg/eye TGF-β2 exhibited consistent upward trends in these biomarkers (Figure 5F). Retinal TGF-β2 (p < 0.01; Figure 5A,F) and MMP2 (p < 0.001; Figure 5B,F) expressions were significantly elevated. The inflammasome pathway was also activated in the mouse retina, with significant increases in NLRP3 expression (p < 0.01; Figure 5C,F) and a pronounced upregulation of IL-1β (p < 0.0001; Figure 5D,F) compared to near-undetectable baseline levels in the control group.
Together, these findings demonstrate that subconjunctival TGF-β2 administration promotes retinal MMP2-mediated matrix remodeling drivers and activates the NLRP3/IL-1β inflammasome pathway in the posterior retina of both rodent species.
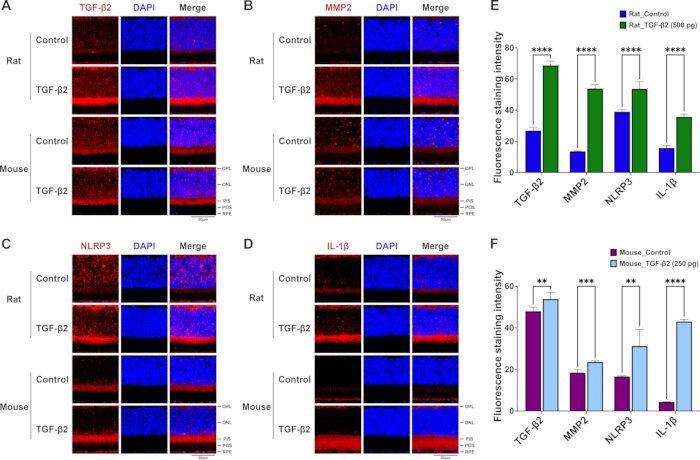
Figure 5: Repeated subconjunctival TGF-β2 administration upregulates MMP2 and inflammasome-related protein expression in the posterior retina of rats and mice. (A–D) Representative immunofluorescence images of retinal sagittal sections from control and TGF-β2–treated groups in rats (upper panels) and mice (lower panels), stained for (A) TGF-β2, (B) MMP2, (C) NLRP3, and (D) IL-1β (red), with nuclei counterstained by DAPI (blue). Scale bar = 50 µm. The representative fields selectively showcase the alterations within the outer retinal layers, highlighting prominent protein expression spanning from the outer plexiform layer (OPL) down to the basal retinal pigment epithelium (RPE) complex. (E) Quantification of fluorescence staining intensity for TGF-β2, MMP2, NLRP3, and IL-1β in rat retinas from the control group and the TGF-β2–treated group (500 pg). (F) Quantification of fluorescence staining intensity for TGF-β2, MMP2, NLRP3, and IL-1β in mouse retinas from the control group and the TGF-β2–treated group (250 pg). Data are presented as mean ± SD (N = 3 independent biological replicates per group, 1 eye per animal). Statistical significance was rigorously evaluated using unpaired two-tailed t-tests; **p < 0.01, ***p < 0.001, ****p < 0.0001 versus the respective vehicle-control group. Abbreviations: OPL, outer plexiform layer; ONL, outer nuclear layer; PIS, photoreceptor inner segments; POS, photoreceptor outer segments; RPE, retinal pigment epithelium. Please click here to view a larger version of this figure.
Supplementary Figure 1: Inter-ocular symmetry and evaluation of bilateral data pooling following subconjunctival TGF-β2 administration. (A) Comparative analysis of axial length changes between left eyes (OS, n = 5) and right eyes (OD, n = 5) in rats receiving vehicle control or bilateral subconjunctival TGF-β2 (500 pg/eye). (B) Corresponding inter-ocular comparison between OS (n = 5) and OD (n = 5) eyes in mice under vehicle control or bilateral TGF-β2 treatment (250 pg/eye). Statistical testing confirmed no significant difference between OS and OD eyes within the same treatment cohort, validating that bilateral measurement pooling does not introduce interocular bias. Simultaneously, both OS and OD eyes in TGF-β2–treated animals exhibited significant axial elongation relative to their respective vehicle controls. Data are presented as mean ± SD (N = 5 animals per group, representing 5 OS and 5 OD eyes per group). Statistical significance was evaluated using two-way repeated-measures ANOVA followed by Sidak’s post hoc test; *p < 0.05, ****p < 0.0001 versus the corresponding vehicle control. Abbreviations: OS, oculus sinister (left eye); OD, oculus dexter (right eye). Please click here to download this file.
Supplementary Figure 2: Safety evaluation of structural retinal integrity and electrophysiological function following subconjunctival TGF-β2 administration. (A) Representative hematoxylin and eosin (H&E)-stained sagittal retinal cross-sections from control and TGF-β2–treated mice (250 pg/eye) and rats (500 pg/eye) at Day 21, demonstrating preserved retinal layer architecture across species (N = 3 independent biological replicates per group). Scale bars = 20 µm. (B) Representative scotopic electroretinography (ERG) waveforms recorded from mice at Day 21, comparing vehicle control eyes (grey line) and TGF-β2–treated eyes (red line). Comparable a-wave and b-wave response dynamics confirm preserved retinal light responsiveness and electrophysiological safety (N = 3 mice per group, representing 6 eyes per group). Abbreviations: GCL, ganglion cell layer; INL, inner nuclear layer; ONL, outer nuclear layer. Please click here to download this file.
Discussão
A notable finding in the study is the non-linear, inverted U-shaped dose-response profile elicited by TGF-β2 in the mouse cohort, where the lowest administered dose (250 pg/eye) induced the most prominent axial elongation (Figure 2B). This biphasic phenomenon is characteristic of many potent cytokine signaling pathways, including the TGF-β superfamily29,30. Excessively high concentrations of exogenous TGF-β2 may lead to receptor saturation or trigger intracellular negative feedback loops—such as the upregulation of inhibitory SMAD family member 7 (Smad7) or receptor-mediated endocytosis—thereby attenuating downstream biological responses31,32. The immunofluorescence data further support this pharmacological window; while the 250 pg dose in mice (and 500 pg in rats) resulted in a moderate elevation in retinal TGF-β2 retention, it simultaneously triggered a robust downstream inflammatory cascade (Figure 5F). This suggests that the optimized low-dose threshold resides within a highly sensitive physiological window, maximizing targeted tissue efficacy while avoiding ligand-induced desensitization or localized suppression33. Therefore, these findings highlight the necessity of rigorous dose titration when establishing reproducible rodent models of chemical-induced myopia.
Compared with traditional form-deprivation myopia (FDM) or hyperopic defocus lens-induced myopia (LIM) models—which require customized hardware and are prone to lens displacement, grooming-induced detachment, and corneal complications—the subconjunctival protocol offers direct pharmacological control and minimal equipment costs13,34. Consistent with prior work showing that periocular delivery modulates scleral and retinal TGF-β signaling35, these data demonstrate posterior-segment biological responses following anterior subconjunctival TGF-β2 administration (Figure 4 and Figure 5). This efficient posterior targeting is attributed to the unique ocular scale and fluid dynamics of small rodents. Given the compact axial length of rodent eyes (~3 mm in mice and ~6 mm in rats), subconjunctival administration bathes a relatively large proportion of the episcleral plane. Driven by high transscleral permeability and the anatomical continuity of the sub-Tenon space, the injected formulation may diffuse across the sclera and choroid toward the posterior pole. Crucially, this route is associated with biological effects in posterior ocular tissues while avoiding the severe risks of globe perforation and optic nerve injury inherent to deep posterior sub-Tenon or intravitreal injections in small rodents. This approach avoids the mechanical and behavioral confounds of head-mounted lenses13,36, as well as the well-documented risks of retinal detachment and endophthalmitis associated with intravitreal injection37,38. Furthermore, partitioning the biometric measurements into two brief sessions improves upon conventional single-session paradigms. Prolonged anesthetic exposure frequently causes ocular disruptions—such as anesthetic cataracts in mice and spontaneous palpebral closure in rats—which compromise the accuracy of refractive and axial measurements39,40. By separating the refractive error (Days –1 and 20) and axial length (Days 0 and 21) assessments, the protocol is designed to minimize potential cumulative ocular stress and maintain consistent imaging conditions, which may help mitigate intra-experimental variability. To further eliminate potential confounding variables arising from systemic cross-contamination—such as systemic vascular absorption or lymphatic transport affecting non-target tissue—as well as contralateral sympathetic responses, a strictly between-subject design was implemented. By administering bilateral vehicle control or bilateral active rhTGF-β2 within individual animals, this paradigm prevents interocular contamination while ensuring robust pharmacological evaluation. Consistently, separate biometric analyses of the paired left and right eyes confirmed high inter-ocular symmetry, validating that bilateral data pooling did not introduce statistical or physiological bias across treatment cohorts (Supplementary Figure 1).
This rodent model effectively recapitulates the TGF-β2–driven inflammatory and matrix-remodeling axis previously established in studies by the authors in tree shrews and Brown Norway rats21,41. Previous investigations by the authors showed that exogenous TGF-β or TGF-β2 amplified intraocular inflammation—specifically via NF-κB and IL-1β activation—while upregulating MMP2 expression, depleting scleral collagen I, and driving axial elongation42,43. Conversely, dampening complement and inflammasome activity via complement decay-accelerating factor (CD55) suppressed both localized inflammation and myopia progression41,44. Similar chronic inflammatory signatures, marked by elevated MMP2 activation and subsequent collagen I loss, are also evident in classical form-deprivation models and in patients with pathological high myopia42,43,45,46. Importantly, rather than functioning as an isolated or universal primary inducer operating uniformly across all tissues, TGF-β (specifically the TGF-β2 isoform) acts as a context-dependent signaling bridge. It links early-stage retinal/RPE inflammatory signaling—specifically via NLRP3 inflammasome and complement activation—to downstream scleral extracellular matrix (ECM) execution21,41. Recognizing this spatiotemporal transition resolves apparent literature inconsistencies regarding TGF-β expression, as its dynamics shift between early local inflammatory amplification in the retina/RPE and late MMP-mediated matrix degradation in the sclera47,48. Specifically, while the structural execution of scleral ECM degradation ultimately dictates physical eye elongation (Figure 4), the molecular findings highlight the outer retina and RPE as the primary upstream signaling origin (Figure 5). Here, while the present study exclusively utilized quantitative immunofluorescence (IF) to map the in situ spatial distribution and laminar upregulation of these markers, the overall gene and protein dynamics (via RT-qPCR and Western blot, respectively) of this retinal phosphorylated nuclear factor kappa B (p-NF-κB)/IL-1β/tumor necrosis factor-alpha (TNF-α)/NLRP3 cascade under identical TGF-β2 induction paradigms have been independently established in the previous studies by the authors46,49. Subconjunctival TGF-β2 activates the NLRP3/IL-1β–MMP2 cascade within the retina/RPE, which propagates across the retino-choroidal-scleral axis to drive downstream scleral MMP2 expression and matrix remodeling. These parallels strongly support the central role of low-grade inflammation and MMP-mediated remodeling of the scleral extracellular matrix (ECM) in accelerated eye growth.
Despite these procedural advantages, several limitations of the present protocol warrant consideration. First, as a purely pharmacological model driven by exogenous cytokine delivery, this approach bypasses the optical defocus and retina-to-sclera light signal transduction pathways characteristic of traditional form-deprivation myopia (FDM) or lens-induced myopia (LIM) models16,50. Consequently, while highly suitable for targeting downstream biochemical cascades—specifically the inflammatory-MMP2 remodeling axis—it is complementary to, rather than a replacement for, models investigating upstream visual processing or optical manipulations51. Second, although subconjunctival injection avoids systemic toxicity and intravitreal risks, the requirement for repeated micro-injections (once weekly for 3 weeks) introduces transient localized mechanical perturbation and brief anesthesia exposure, which could subtly influence ocular surface homeostasis if not rigorously executed38,52. Achieving reproducible induction of experimental myopia via this route relies heavily on precise technical execution during subconjunctival delivery. The primary technical determinant of success is the correct shallow bevel insertion beneath the palpebral conjunctiva to establish a localized, well-circumscribed submucosal bleb (chemosis). Verification via immediate transillumination ensures that fluid remains within the tissue plane, preventing inadvertent scleral perforation, deep orbital extravasation, or microvascular laceration. To prevent post-injection fluid reflux or active leakage—a common failure mode that compromises effective pharmacological dosing—the micro-needle should be held in situ for 5 s post-delivery before slow, steady withdrawal under visual control. In cases where immediate reflux, insufficient bleb height, or inadvertent tissue hemorrhage occurs upon withdrawal, animals should be documented and excluded according to pre-specified criteria to avoid confounding variability. Adherence to these strict technical benchmarks guarantees high-fidelity, targeted posterior drug retention while minimizing ocular surface trauma. Furthermore, while the absolute refractive status (e.g., -1.58 D in mice and -1.38 D in rats) in rodent models may appear modest relative to their high baseline dioptric power, the net myopic shifts relative to vehicle controls are substantial (+3.83 D in mice and +1.69 D in rats; both p < 0.05) and strictly concordant with structural axial elongation and downstream scleral MMP2 upregulation across both species. Importantly, safety and physiological tolerability evaluations confirmed the non-cytotoxic nature of this low-dose subconjunctival administration paradigm. Histological cross-sections (H&E) revealed well-preserved retinal layer architecture across both mice and rats, while scotopic electroretinography (ERG) at Day 21 demonstrated intact a-wave and b-wave responses without implicit time delays or amplitude depression (Supplementary Figure 2), confirming that localized TGF-β2 delivery induces targeted axial elongation without causing structural retinopathy or electrophysiological impairment. Third, the endpoint evaluations at Week 3 capture acute-to-subacute inflammatory responses and matrix remodeling; long-term studies are needed to determine whether these phenotypic changes persist post-treatment or exhibit recovery dynamics following washout41,53. Finally, while direct pharmacokinetic and ocular tissue penetration analyses of exogenous TGF-β2 were beyond the scope of this model validation study, the robust and consistent biometric shifts (axial elongation and refractive error change), alongside the specific retinal/RPE molecular activations established in the previous studies by authors46,49, support effective biological action in posterior ocular structures. Future studies incorporating further protein expression profiling (e.g., Western blotting), RT-qPCR, or fluorescently tagged TGF-β2 tracking will further clarify its precise tissue distribution and clearance kinetics. Recognizing these boundaries will guide researchers in selecting this model for appropriate therapeutic screening and mechanistic validation.
By demonstrating that subconjunctival TGF-β2 activates the NLRP3/IL-1β–MMP2 axis within the outer retina and retinal pigment epithelium (RPE) of both Brown Norway rats and C57BL/6 mice, the protocol provides a pharmacologically defined framework that validates these inflammatory and matrix-remodeling pathways across rodent species. Consequently, the TGF-β2–induced model serves as a reliable platform for standardizing the induction of axial elongation, dissecting retino-scleral signaling cascades, and screening preclinical interventions targeting TGF-β2, complement components, the inflammasome, or MMP2.
Divulgações
Os autores não têm divulgações nem conflitos de interesses a declarar relevantes para este estudo. Ferramentas linguísticas assistidas por IA foram utilizadas exclusivamente para edição gramatical e refinamento da sintaxe em inglês durante a preparação do manuscrito. Nenhuma ferramenta de IA generativa foi usada na aquisição de dados, processamento de imagens, análise quantitativa ou construção de figuras.
Agradecimentos
Experiments and data analysis were performed in part through the use of the Medical Research Core Facilities, Office of Research & Development, at China Medical University, Taichung, Taiwan, R.O.C. The authors sincerely thank the National Center for Biomodels (NCB, NIAR, Taiwan) and BioLASCO Taiwan Co., Ltd. for their exceptional technical support in contract breeding and animal supply services. Additionally, the schematic architecture and microsurgical procedures illustrated in Figure 1 were designed and custom-tailored using high-resolution vector assets from Mind the Graph (mindthegraph.com, Premium License) and were professionally compiled and refined utilizing Affinity Designer (Serif Europe Ltd.). Research funding was provided in part by the National Science and Technology Council, Taiwan, R.O.C. (NSTC-112-2314-B-039-029; 115-2320-B-039-056), China Medical University Hospital, Taichung, Taiwan (DMR-114-091; DMR-115-117), and China Medical University, Taichung, Taiwan (CMU114-MF-78; CMU-114-ASIA-10). The funders had no role in the study design, data collection and analysis, the decision to publish, or preparation of the manuscript. The sponsor or funding organization had no role in the design or conduct of this research.
Materiais
| Nome | Empresa | Número de catálogo | Comentários |
|---|---|---|---|
| Refrator fotônico infravermelho automatizado | StriaTech GmbH (Tübinger, Alemanha) | ST-PR.01 | Com predefinições específicas para espécies de ratos e camundongos |
| Solução Salina Balanceada (BSS) | Alcon Laboratories, Inc. (Fort Worth, EUA) | N/A | Solução estéril para irrigação intraocular |
| Albumina Sérica Bovina (BSA) | Sigma-Aldrich (St. Louis, EUA) | A3059 | Pó liofilizado, fração V a 0,1% |
| Ratos Brown Norway (BN) | BioLASCO Taiwan Co., Ltd. e/ou o Centro Nacional de Biomodelos | https://www.biolasco.com.tw/product/brown-norway-rats/ | |
| Camundongos C57BL/6 (B6) | BioLASCO Taiwan Co., Ltd. e/ou o Centro Nacional de Biomodelos | https://www.ncb.niar.org.tw/p3_animal2_detail.asp?cid=1&nid=3&ppage=0&type=1 | |
| Solução de DAPI (1 mg/mL) | Thermo Scientific (Thermo Fisher Scientific, Waltham, EUA) | 62248 | Utilizada em diluição de trabalho de 1:500 para imunofluorescência. |
| Etanol absoluto (≥99,5%) | J.T.Baker (Avantor Performance Materials, Radnor, EUA) | N/A | Reagente grau, 75% para enxágue, 20%–100% para desidratação |
| Iluminador com ponta fina (150 W, com dois braços articuláveis) | Stoelting Co. (Wood Dale, EUA) | N/A | Fonte de luz de alta intensidade |
| Microforceps de ponta fina | Stephens Instruments (Lexington, EUA) | S5-1375 | Retas, serrilhadas, com pino-guia |
| Gel oftálmico Ginpol | Winston Medical Supply Co., Ltd. (Tainan, Taiwan) | N/A | Carbômero 0,2%, proteção da córnea |
| Glicerol (biologia molecular, ≥99,0%) | Sigma-Aldrich (St. Louis, EUA) | G5516 | Reagente grau, matriz de trabalho a 50% |
| Anticorpo secundário de cabra anti-coelho IgG (H+L), Alexa Fluor Plus 555 | Invitrogen (Thermo Fisher Scientific, Waltham, EUA) | A32732 | Utilizado em diluição de trabalho de 1:800 para imunofluorescência. |
| Sistema portátil de eletroretinografia multiespécies (HMSERG) | OcuScience (Henderson, EUA) | Modelo 2000 (HMsERG-2000), sistema de eletroretinografia com flash de campo total para roedores com software ERGView. | |
| Fixador de Hartman′s (Fixador Davidson) | Sigma-Aldrich (St. Louis, EUA) | H0290 | Cocktail de fixação rápida para geometria ocular |
| Probeta de ultrassom de alta frequência | ASUSTeK Computer Inc. (Taipei, Taiwan) | LU710LH | Portátil, frequência de 16 MHz |
| Agulha de microinjeção (33-G) | Hamilton Company (Reno, EUA) | 7803-05 | Estilo de ponta 4, ângulo de bisel raso |
| Seringa de microinjeção (10 µL) | Hamilton Company (Reno, EUA) | 80014 (#1701) | Seringa gastight de microlitros |
| Solução oftálmica Mydrin-P | Santen Pharmaceutical Co., Ltd. (Osaka, Japão) | N/A | Tropicamida 0,5% / Fenilefrina 0,5% |
| Soro de cabra normal | Jackson ImmunoResearch Laboratories, Inc. (West Grove, EUA) | 005-000-121 | Utilizado como solução bloqueadora a 10% para imunofluorescência. |
| Software de aquisição de fotorrefrator | StriaTech GmbH (Tübinger, Alemanha) | N/A | Processamento automatizado do equivalente esférico médio |
| Anticorpo monoclonal de coelho anti-IL1 beta (HL1421) | GeneTex, Inc. (Irvine, EUA) | GTX636887 | Utilizado em diluição de trabalho de 1:500 para imunofluorescência. |
| Anticorpo policlonal de coelho anti-MMP2 | GeneTex, Inc. (Irvine, EUA) | GTX104577 | Utilizado em diluição de trabalho de 1:500 para imunofluorescência. |
| Anticorpo policlonal de coelho anti-NLRP3 | Abcam (Cambridge, Reino Unido) | ab214185 | Utilizado em diluição de trabalho de 1:400 para imunofluorescência. |
| Anticorpo policlonal de coelho anti-TGF-beta 2 | AbboMax, Inc. (San Jose, EUA) | 500-3784 | Utilizado em diluição de trabalho de 1:250 para imunofluorescência. |
| TGF-β1 humano recombinante | PeproTech (Thermo Fisher Scientific, Cranbury, EUA) | 100-21 | Pó liofilizado, alta pureza |
| TGF-β2 humano recombinante | PeproTech (Thermo Fisher Scientific, Cranbury, EUA) | 100-35 | Pó liofilizado, alta pureza |
| TGF-β3 humano recombinante | PeproTech (Thermo Fisher Scientific, Cranbury, EUA) | 100-36 | Pó liofilizado, alta pureza |
| Gel ultrassônico estéril Aquasonic 100 | Parker Laboratories, Inc. (Fairfield, EUA) | N/A | Matriz acústica de acoplamento padrão |
| Software de imagem por ultrassom | ASUSTeK Computer Inc. (Taipei, Taiwan) | N/A | Para visualização em tempo real em modo B e uso de paquímetros |
Referências
- Holden BA, et al. Myopia: a growing global problem with sight-threatening complications. Community eye health. 2015;28(90):35.
- Holden BA, et al. Global prevalence of myopia and high myopia and temporal trends from 2000 through 2050. Ophthalmology. 2016;123(5):1036-42.
- McMonnies CW. An examination of the relation between intraocular pressure, fundal stretching, and myopic pathology. Clinical and Experimental Optometry. 2016;99(2):113-9.
- Fledelius HC. Myopia and significant visual impairment: global aspects [Presentation]. Presented at: 7th International Conference on Myopia; Taipei, Taiwan; 1998.
- Park SC, Liebmann JM, Ritch R. Glaucoma in myopia. Pathologic Myopia: Springer; 2013. p. 283-92.
- Gale J, Ikuno Y. Ii. B. Myopic Vitreopathy. Vitreous: In Health and Disease: Springer; 2014. p. 113-29.
- Saw SM, Gazzard G, Shih-Yen EC, Chua WH. Myopia and associated pathological complications. Ophthalmic and Physiological Optics. 2005;25(5):381-91.
- Tkatchenko TV, Shen Y, Tkatchenko AV. Mouse Experimental Myopia Has Features of Primate Myopia. Investigative Ophthalmology & Visual Science. 2010;51(3):1297-303.
- Morgan IG, Ashby RS, Nickla DL. Form deprivation and lens-induced myopia: are they different? Ophthalmic Physiol Opt. 2013;33(3):355-61.
- Barathi VA, Boopathi VG, Yap EP, Beuerman RW. Two models of experimental myopia in the mouse. Vision Res. 2008;48(7):904-16.
- Zhao HL, Wang RQ, Wu MQ, Jiang J. Dynamic changes of ocular biometric parameters: a modified form-deprivation myopia model of young guinea pigs. Int J Ophthalmol. 2011;4(5):484-8.
- Wu XH, et al. Unaltered retinal dopamine levels in a C57BL/6 mouse model of form-deprivation myopia. Invest Ophthalmol Vis Sci. 2015;56(2):967-77.
- Faulkner AE, Kim MK, Iuvone PM, Pardue MT. Head-mounted goggles for murine form deprivation myopia. J Neurosci Methods. 2007;161(1):96-100.
- Wang Y, Zhang Y, Tian N. Cause and Management of Suture-related Ocular Complications after Buried-suture Double-eyelid Blepharoplasty. J Plast Reconstr Aesthet Surg. 2021;74(12):3431-6.
- Pang K, Lennikov A, Yang M. Hypoxia adaptation in the cornea: Current animal models and underlying mechanisms. Animal Model Exp Med. 2021;4(4):300-10.
- Schaeffel F, Feldkaemper M. Animal models in myopia research. Clinical and Experimental Optometry. 2015;98(6):507-17.
- Harper AR, Summers JA. The dynamic sclera: extracellular matrix remodeling in normal ocular growth and myopia development. Exp Eye Res. 2015;133:100-11.
- Jobling AI, Nguyen M, Gentle A, McBrien NA. Isoform-specific changes in scleral transforming growth factor-beta expression and the regulation of collagen synthesis during myopia progression. J Biol Chem. 2004;279(18):18121-6.
- Vranka JA, Kelley MJ, Acott TS, Keller KE. Extracellular matrix in the trabecular meshwork: intraocular pressure regulation and dysregulation in glaucoma. Exp Eye Res. 2015;133:112-25.
- Tien P-T, et al. Diacerein inhibits myopia progression through lowering inflammation in retinal pigment epithelial cell. Mediators of Inflammation. 2021;2021(1):6660640.
- Ku H, et al. The role of transforming growth factor beta in myopia development. Molecular immunology. 2024;167:34-42.
- Yin X, Ge J. The role of scleral changes in the progression of myopia: a review and future directions. Clinical Ophthalmology. 2025:1699-707.
- Schippert R, Brand C, Schaeffel F, Feldkaemper MP. Changes in scleral MMP-2, TIMP-2 and TGFβ-2 mRNA expression after imposed myopic and hyperopic defocus in chickens. Experimental eye research. 2006;82(4):710-9.
- Xin J, et al. Crosstalk between myopia and inflammation: a mini review. International journal of medical sciences. 2024;21(9):1589.
- Zhang K, et al. Elevated Transforming Growth Factor-β2 in the Aqueous Humor: A Possible Explanation for High Rate of Capsular Contraction Syndrome in High Myopia. Journal of Ophthalmology. 2016;2016(1):5438676.
- Zhang M, et al. Complement and local ocular inflammatory response: Chronic immune factors in myopia. Science Progress. 2025;108(3):00368504251383046.
- Meng L, et al. Aqueous Humour Cytokines as Predictors of Axial Elongation in High Myopia: A 2-Year Longitudinal Cohort Study. Clinical & Experimental Ophthalmology. 2026;54(6):756-768.
- Miller DA, et al. Murine transforming growth factor-β2 cDNA sequence and expression in adult tissues and embryos. Molecular Endocrinology. 1989;3(7):1108-14.
- Langer JC, Henckaerts E, Orenstein J, Snoeck HW. Quantitative trait analysis reveals transforming growth factor-beta2 as a positive regulator of early hematopoietic progenitor and stem cell function. J Exp Med. 2004;199(1):5-14.
- Shinar DM, Rodan GA. Biphasic effects of transforming growth factor-beta on the production of osteoclast-like cells in mouse bone marrow cultures: the role of prostaglandins in the generation of these cells. Endocrinology. 1990;126(6):3153-8.
- Heldin CH, Moustakas A. Signaling Receptors for TGF-β Family Members. Cold Spring Harb Perspect Biol. 2016;8(8).
- Zhao B, Chen YG. Regulation of TGF-β Signal Transduction. Scientifica (Cairo). 2014;2014:874065.
- Akhurst RJ. Targeting TGF-β Signaling for Therapeutic Gain. Cold Spring Harb Perspect Biol. 2017;9(10).
- Pardue MT, Stone RA, Iuvone PM. Investigating mechanisms of myopia in mice. Exp Eye Res. 2013;114:96-105.
- Cordeiro MF, Gay JA, Khaw PT. Human Anti-Transforming Growth Factor-β2 Antibody: A New Glaucoma Anti-Scarring Agent. Investigative Ophthalmology & Visual Science. 1999;40(10):2225-34.
- Guo ZV, et al. Procedures for Behavioral Experiments in Head-Fixed Mice. PLOS ONE. 2014;9(2):e88678.
- Jager RD, Aiello LP, Patel SC, Cunningham ET, Jr. Risks of intravitreous injection: a comprehensive review. Retina. 2004;24(5):676-98.
- Lommatzsch AP, et al. Endophthalmitis als schwere Komplikation der intravitrealen Medikamentengabe. Klin Monbl Augenheilkd. 2013;230(11):1130-4.
- Li XT, Qin Y, Zhao JY, Zhang JS. Acute lens opacity induced by different kinds of anesthetic drugs in mice. Int J Ophthalmol. 2019;12(6):904-8.
- Tkatchenko TV, Tkatchenko AV. Ketamine-xylazine anesthesia causes hyperopic refractive shift in mice. J Neurosci Methods. 2010;193(1):67-71.
- Lin S-C, et al. The Function of Transforming Growth Factor 2 in Facilitating Inflammas ome Activation to Enhance the Development of Myopia via Complement Sys tem. Cells. 2025;14(16):1295.
- Wei CC, et al. Allergic Conjunctivitis-induced Retinal Inflammation Promotes Myopia Progression. EBioMedicine. 2018;28:274-86.
- Wei CC, et al. Corrigendum to "Allergic Conjunctivitis-induced Retinal Inflammation Promotes Myopia Progression" [EBioMedicine 28 (2018) 274-286]. EBioMedicine. 2019;41:717-8.
- Lin HJ, et al. Role of Chronic Inflammation in Myopia Progression: Clinical Evidence and Experimental Validation. EBioMedicine. 2016;10:269-81.
- Lin HJ, et al. Sclera-related gene polymorphisms in high myopia. Mol Vis. 2009;15:1655-63.
- Lin CF, et al. Harnessing Lactiplantibacillus plantarum EP21 and its membrane vesicles to inhibit myopia development. Gut Microbes. 2025;17(1):2534677.
- Chou Y-L, et al. Complement decay-accelerating factor inhibits inflammation-induced myopia development. Molecular Immunology. 2024;171:47-55.
- Ku H, et al. Myopia development in tree shrew is associated with chronic inflammatory reactions. Current Issues in Molecular Biology. 2022;44(9):4303-13.
- Chou Y-L, et al. Vitamin D3 Reshapes Gut Microbiota and Metabolite Profiles in a Rat Model of Inflammation-Induced Myopia. Biomolecules. 2026;16(7):939.
- Wallman J, Winawer J. Homeostasis of eye growth and the question of myopia. Neuron. 2004;43(4):447-68.
- Morgan IG, et al. IMI Risk Factors for Myopia. Investigative Ophthalmology & Visual Science. 2021;62(5).
- Wildsoet C, et al. IMI-interventions for controlling myopia onset and progression report. Investigative Ophthalmology and Visual Science. 2019;60(3):M106-M31.
- Rada JAS, Shelton S, Norton TT. The sclera and myopia. Experimental eye research. 2006;82(2):185-200.
Reimpressões e permissões
Este artigo foi publicado
Vídeo em breve