This review integrates mechanistic, phenotypic, and interventional evidence on microvascular obstruction after reperfusion and proposes a temporal framework for aligning patient enrichment, treatment timing, and trial endpoints.
Artigo de revisão
Microvascular Obstruction After Reperfusion in ST-Segment Elevation Myocardial Infarction: A Structured Narrative Review
Neste artigo
Resumo
Resumo
Primary percutaneous coronary intervention (pPCI) restores epicardial coronary flow in ST-segment elevation myocardial infarction (STEMI), but microvascular and tissue-level reperfusion may remain impaired. Cardiovascular magnetic resonance (CMR)-defined microvascular obstruction (MVO) and intramyocardial hemorrhage (IMH) both mark severe reperfusion injury but reflect distinct tissue processes. This structured narrative review synthesizes evidence on MVO mechanisms, multimodal phenotypes, and interventions. Available evidence implicates interacting contributions from distal embolization, endothelial barrier and vasomotor dysfunction, pericyte-mediated capillary constriction, immunothrombosis, and tissue edema. IMH reflects more extensive microvascular destruction with erythrocyte extravasation. Angiography, electrocardiography, invasive physiology, angiography-derived indices, echocardiography, and CMR assess different pathophysiologic levels. Discordance between modalities is therefore not necessarily contradictory. Across trials, improvements in surrogate endpoints have often not translated into long-term clinical benefit, partly because of mechanistic heterogeneity and misaligned treatment timing and endpoints. A conceptual, reperfusion-centered T− to T5 research framework is proposed for serial within-patient assessment. It links early physiology, inflammatory and thrombotic biomarkers, acute-phase CMR, and long-term remodeling. Future trials should align mechanistic enrichment, intervention timing, and endpoint selection to establish a continuous evidence chain from target engagement to clinical outcomes.
Introdução
Primary percutaneous coronary intervention has markedly improved epicardial reperfusion in STEMI. However, reopening the infarct-related artery does not ensure restoration of myocardial tissue perfusion. Early experimental and clinical observations established that capillary perfusion failure can persist within the infarct zone despite restored epicardial flow. This phenomenon is termed no-reflow1,2. Current consensus recognizes coronary MVO as a major tissue phenotype of ischemia-reperfusion injury. MVO may reflect distal embolization, endothelial barrier disruption, vasomotor dysfunction, extrinsic capillary compression, pericyte-mediated constriction, and immunothrombosis. IMH indicates more severe microvascular destruction with erythrocyte extravasation3,4. The clinical challenge arises not from a lack of candidate mechanisms but from inconsistent definitions, measurement levels, and observation windows. Angiographic no-reflow, impaired ST-segment resolution, elevated invasive microvascular resistance, angiography-derived indices, and CMR-defined MVO often correlate but are not interchangeable5,6,7,8,9,10,11. Treating any single result as proof of restored microcirculation can therefore misclassify the mechanism and misalign trial endpoints.
This structured narrative review integrates mechanisms, multimodal phenotypes, and interventional evidence related to MVO and IMH. It also proposes a research framework centered on reperfusion as time zero. The review examines why modalities may yield divergent findings and how phenotype, intervention timing, and outcome selection can be aligned more precisely. PubMed was searched from database inception through August 20, 2026. Targeted searches and citation tracking were updated through September 2, 2026, to identify recent articles, key randomized trials, and registered studies. Search concepts included STEMI, pPCI, MVO, no-reflow, coronary microvascular dysfunction, IMH, endothelial glycocalyx, pericytes, immunothrombosis, neutrophil extracellular traps (NETs), index of microcirculatory resistance (IMR), CMR, and related interventions. Priority was given to directly relevant human clinical studies, randomized trials, mechanistic imaging or physiology studies, consensus documents, and preclinical studies that directly addressed key pathophysiologic processes. Studies addressing the mechanisms, assessment, prognosis, and interventions related to microvascular injury after reperfusion in STEMI were selected. Preclinical studies informed the discussion of underlying mechanisms and potential therapeutic targets. When interpreting the findings, the study population, design, measurement timing, and endpoints were considered. Mechanistic findings and effects on surrogate endpoints were distinguished from clinical outcomes. This structured narrative review did not include dual independent screening or a formal risk-of-bias assessment.
Evidence extraction addressed five dimensions: population, reperfusion or measurement timing, microvascular endpoints, tissue endpoints, and clinical outcomes. For key quantitative claims, sample sizes, analysis populations, effect estimates, confidence intervals, and P values were checked against the original reports. A meta-analysis was not performed because the review integrates heterogeneous mechanistic and measurement frameworks. The evidence-identification and verification workflow is summarized in Supplementary Figure 1.
Revisão e perspetiva
Conceptual boundaries and dynamic evolution
No-reflow, microvascular dysfunction, MVO, and IMH
No-reflow denotes inadequate tissue perfusion after recanalization. Coronary microvascular dysfunction refers to functional abnormalities in microvascular resistance or flow reserve. MVO denotes focal regions of absent or severely impaired microvascular perfusion within infarcted myocardium, identified by CMR or histology. IMH denotes erythrocyte extravasation through disrupted microvessels, followed by accumulation of blood degradation products in the myocardial interstitium. Acquisition protocol and sequence selection influence detection of MVO and IMH. Reports should therefore specify the sequence, imaging time, and quantification method12. MVO may reflect structural microvascular injury, whereas concomitant IMH reflects intramyocardial bleeding. The two phenotypes are related but not synonymous. IMH usually occurs within severe MVO and is associated with larger infarcts, greater edema, and worse remodeling. However, not all MVO contains IMH, and CMR sequences differ in sensitivity to hemorrhage. T2* imaging is more specific for blood degradation products. T2-weighted imaging and T2 mapping may reflect both edema and hemorrhage13,14.
Clinical significance
The presence and extent of acute-phase MVO are associated with death, hospitalization for heart failure, and adverse left ventricular remodeling. In a pooled individual-patient analysis, each 1% increase in MVO relative to left ventricular mass was associated with higher 1-year risks of all-cause death and hospitalization for heart failure, with some associations persisting after adjustment for infarct size15. On serial CMR, residual MVO refers to a defect that remains detectable on a subsequent examination, whereas transient MVO resolves. Gadelmawla et al. synthesized seven cohorts comprising 2,180 patients. Compared with transient MVO, persistent MVO was associated with higher risks of major adverse cardiovascular events and death, lower left ventricular ejection fraction (LVEF), and larger infarcts. The risk of heart failure readmission was higher with persistent MVO than with no MVO, but did not differ significantly between persistent and transient MVO. Definitions of persistent MVO varied across studies, including residual defects on follow-up scans and definitions based on enhancement patterns within a single acute examination. This distinction should be considered when interpreting the pooled prognostic associations16.
Evidence for incremental prediction comes from Zhou et al., who retrospectively studied 504 patients with follow-up CMR at least 60 days after pPCI. Persistent MVO was defined by its presence on follow-up late gadolinium enhancement imaging, which served as the study baseline. Adding persistent MVO to a model containing New York Heart Association functional class, LVEF, and late gadolinium enhancement extent increased the C-index from 0.78 to 0.82 (p = 0.01) for a composite of heart failure-related death, transplantation, left ventricular assist device implantation, and heart failure hospitalization17. These findings support incremental prognostic information beyond ventricular function and infarct burden in this cohort. Reducing MVO itself does not guarantee improved long-term outcomes.
Multilevel phenotypes and their clinical applications
The corrected Thrombolysis in Myocardial Infarction frame count (cTFC) and myocardial blush grade (MBG) describe flow velocity and tissue perfusion, respectively18,19. Circulating glycocalyx markers, standardized CMR, histology, coagulation measures, and other microvascular phenotypes provide complementary information at different biologic levels20,21,22,23,24,25,26. These measures have prognostic associations but differ in pathophysiologic meaning and temporal sensitivity27. Table 1 distinguishes the major concepts and the questions each can address.
A reperfusion-centered temporal coordinate
A T− to T5 coordinate system is used to compare intervention and measurement timing across studies. Time zero is the first prospectively documented restoration of forward epicardial flow. T− denotes the ischemic period before reperfusion; T0, 0 to <30 min; T1, 30 min to <6 h; and T2, 6 to <24 h. T3 spans 24 to <72 h; T4, 72 h to 7 d; and T5, >7 d and subsequent remodeling. The proposed T− to T5 framework is a conceptual research tool for organizing serial assessments and trial design rather than a validated clinical classification. Its time windows are pragmatic reference intervals, and the underlying biological processes may overlap. Figure 1 summarizes candidate mechanisms, multimodal phenotypes, and proposed assessment windows.
Mechanistic network of MVO
Endothelial barrier and vasomotor dysfunction
Ischemia and reperfusion can disrupt the endothelial glycocalyx and intercellular junctions. These processes increase permeability, impair nitric oxide-dependent vasodilation, and promote leukocyte adhesion and local coagulation. In a prospective human observational study, circulating markers of glycocalyx degradation were associated with post-PCI slow flow20. Angiopoietin-like 4-mediated preservation of vascular integrity reduced no-reflow and infarct size in preclinical models. Preclinical studies of Tongxinluo also linked barrier preservation to attenuated reperfusion injury28,29. Human evidence remains observational, whereas experimental studies support further investigation of endothelial protection.
Pericyte-mediated capillary constriction
After coronary recanalization, focal capillary obstruction can persist at pericyte locations. In cultured primary cardiac pericytes, compressive force increased cytosolic calcium, and this response was inhibited by antagonists of transient receptor potential melastatin 4 and 7 (TRPM4/TRPM7)30. In a rat ischemia-reperfusion model, approximately 40% of capillaries in the affected region remained blocked, with blockage sites disproportionately close to pericyte somata. Adenosine increased capillary diameter and improved perfusion31. Studies in mice identify G protein-coupled receptor 39 (GPR39) as a potential therapeutic target32, but no validated method identifies a pericyte-dominant phenotype in living patients.
Immunothrombosis and distal microembolization
Immunothrombosis links inflammation with thrombus formation. In culprit arteries from patients with STEMI, NET burden and deoxyribonuclease activity were associated with ST-segment resolution and infarct size33. NETs from culprit coronary arteries can also carry functional tissue factor that enhances coagulation in experimental assays34. In a rat ischemia-reperfusion model, deoxyribonuclease I (DNase I) combined with recombinant tissue-type plasminogen activator (rt-PA) reduced NET accumulation and the no-reflow area, whereas neither agent alone significantly reduced no-reflow35. Proteomic studies, inflammatory biomarker analyses, and studies of intracoronary microparticles show associations among thromboinflammatory signaling, IMH, and MVO36,37,38. Translational studies implicate functional autoantibodies and pro-nerve growth factor in microvascular injury39,40. These findings remain heterogeneous and do not establish a single causal sequence in patients.
In a human pharmacodynamic study, colchicine suppressed NET formation after percutaneous coronary intervention in patients with acute coronary syndromes41. Mesenchymal stromal cell-derived exosomes also reduce NETs and ischemia-reperfusion injury in preclinical models42. Greater platelet-fibrin clot strength is associated with angiographic no-reflow and long-term events in human studies43. Chemerin15 reduced neutrophil-mediated vascular inflammation and myocardial injury in preclinical models44. Together, these findings support an immunothrombotic contribution to MVO but do not yet define an actionable clinical phenotype.
Tissue edema, microvascular disruption, and IMH
Post-reperfusion edema increases interstitial pressure and may compress already injured capillaries. Further disruption of endothelial and basement membrane integrity permits erythrocyte extravasation and produces IMH. Subsequent iron deposition, oxidative stress, and persistent inflammation may prolong injury and contribute to adverse remodeling3,4. These processes overlap with endothelial injury, pericyte constriction, and immunothrombosis rather than forming a fixed, unidirectional cascade.
Mechanistic integration and heterogeneity
Table 2 maps candidate mechanisms to core processes, observable phenotypes, evidence levels, and potential intervention points. Patients with CMR-defined MVO may nevertheless have different dominant processes. High thrombus burden with intraprocedural slow flow supports a predominantly embolic or thrombotic phenotype. Persistently elevated IMR after pPCI despite acceptable angiography is compatible with a resistance-dominant component, but IMR is not mechanism-specific. Marked edema with IMH indicates severe tissue destruction. Most patients probably have several mechanisms operating simultaneously.
Multimodal phenotypic assessment
Angiography and electrocardiography
TIMI flow, cTFC, MBG, and ST-segment resolution can be assessed soon after reperfusion. They identify overt slow flow, inadequate tissue perfusion, and impaired electrophysiologic recovery. Their advantages are immediacy and low incremental cost. Limitations include sensitivity to injection technique, heart rate, blood pressure, collateral flow, conduction abnormalities, and reader variability. None directly visualizes tissue injury within the infarct core.
Invasive and angiography-derived microvascular physiology
The index of microcirculatory resistance (IMR), measured immediately after pPCI during hyperemia, quantifies microvascular resistance. It is associated with subsequent MVO and infarct evolution45. Coronary flow reserve (CFR) is influenced by both epicardial and microvascular circulations. Microvascular resistance reserve (MRR) is designed to reduce the influence of epicardial stenosis and resting conditions. Angiography-derived indices estimate microvascular resistance without pressure-wire instrumentation. Conventional TIMI flow and cTFC characterize contrast passage through epicardial arteries, while MBG describes myocardial contrast opacification. Newer angiography-derived indices use computational estimates of pressure and flow to infer microvascular resistance. These approaches differ in the construct measured and technical requirements: visual grading or frame counting depends on acquisition quality, whereas resistance estimation additionally depends on software and model assumptions46. One intracoronary nicorandil study reported reduced angiography-derived microvascular resistance (AMR)47. The 12-patient IC-HOT-MICRO pilot study reported improved angiography-derived index of microcirculatory resistance (Angio-IMR) after supersaturated oxygen therapy48. These findings support early mechanistic use of angiography-derived indices. Their thresholds, reproducibility, and incremental prognostic value require validation in larger cohorts. Circulating β1-adrenergic receptor autoantibodies may complement mechanistic stratification, but they remain research tools rather than stand-alone diagnostic tests49.
CMR, echocardiography, and functional imaging
CMR assesses infarct size, MVO, IMH, myocardial edema, and ventricular structure and function within one examination. Serial CMR can assess subsequent remodeling. It is therefore central to tissue phenotyping. Acute-phase CMR is commonly performed 2–7 days after pPCI, but MVO and edema evolve dynamically. Cross-study comparisons must report the exact imaging time, sequence, and quantification criteria. CFR measured by transthoracic Doppler echocardiography correlates with guidewire-derived measurements and may support noninvasive follow-up50. CMR feature tracking and layer-specific speckle-tracking echocardiography provide complementary functional information51. These methods cannot replace CMR tissue characterization of MVO and IMH. They can, however, identify dissociation between functional recovery and structural injury.
Integrated interpretation
Discordance between modalities usually reflects different measurement targets and time points rather than failure of any test. Direct comparisons show that angiography, electrocardiography, and CMR do not classify microvascular injury identically52. Intraprocedural angiography and IMR characterize contemporaneous flow and resistance. CMR several days later quantifies the resulting tissue injury. Follow-up imaging and clinical outcomes determine whether injury persists and affects remodeling. Table 3 presents the proposed multimodal temporal matrix.
Interventions to protect the microcirculation
The interventions below are distinguished by study design and endpoint level: randomized clinical evidence, preliminary human mechanistic or observational evidence, and predominantly preclinical evidence. Within randomized studies, clinical-event outcomes are distinguished from imaging, physiological, and pharmacodynamic endpoints. Barrier-protective, pericyte-targeted, exosome, and Chemerin15 approaches discussed above remain largely preclinical.
Pre-reperfusion or systemic interventions
The PULSE-MI trial randomized 742 patients. The modified intention-to-treat analysis included 530 patients, and 295 underwent microvascular physiologic assessment. Prehospital methylprednisolone reduced C-reactive protein at 24 h, but immediate post-pPCI IMR did not differ significantly from placebo53. Thus, anti-inflammatory pharmacodynamic activity did not coincide with improved early microvascular function. The randomized ASSAIL-MI proof-of-concept trial reported greater CMR-assessed myocardial salvage after interleukin-6 receptor inhibition. Evidence for clinical benefit remains insufficient54.
The CMR substudy of the randomized CONDI-2/ERIC-PPCI trial found no significant effect of remote ischemic conditioning on acute MVO or 6-month infarct size. A single-center CMR substudy of the randomized AT-STEMI trial of high-dose atorvastatin pretreatment also showed no clear benefit55,56. Systemic interventions without mechanistic enrichment are vulnerable to variation in treatment-to-balloon time, baseline inflammation, and missing imaging endpoints.
Nicorandil and vasomotor interventions
The CHANGE trial randomized 238 patients to intravenous nicorandil or placebo. Nicorandil reduced adjusted infarct mass at 5–7 d and 6 months. Early MVO occurred in 32 of 99 patients (32.3%) versus 47 of 102 patients (46.1%)57. The subsequent CLEAN randomized trial, with a clinical-event primary endpoint, enrolled 1,503 patients at 49 hospitals. The 12-month primary composite endpoint occurred in 13.1% of both groups, with no significant clinical benefit58. These findings distinguish early tissue effects, effect magnitude, and durable modification of remodeling as separate questions.
Mechanical and procedural strategies
The SALINE technique delivers saline selectively into the coronary circulation through a thrombus aspiration catheter to treat intraprocedural no-reflow. Evidence remains limited to technical and observational studies59. Its potential role is rapid treatment of established slow flow, not routine prophylaxis for all patients with STEMI. The TOTAL randomized trial with clinical-event endpoints showed that routine manual thrombus aspiration did not improve major clinical outcomes and increased stroke risk. It should therefore not be used universally60. Separately, in a pilot randomized trial of prolonged balloon inflation during stent deployment, MVO was reported in 2 of 30 patients versus 10 of 20 patients among those who underwent CMR. However, only 50 of the 120 randomized patients completed CMR, and the small, unequal analyzable groups preclude a firm efficacy conclusion61. An early single-center study suggested that ischemic postconditioning improved reperfusion indices62. The larger randomized DANAMI-3-iPOST trial did not reduce death or hospitalization for heart failure63. Procedural effects may depend on initial TIMI flow, ischemic time, infarct location, and consistency of execution.
Intracoronary adenosine, nitroprusside, and fibrinolysis
A recent randomized, triple-blind trial suggested that intracoronary adenosine improved selected angiographic no-reflow measures. However, it did not assess IMR or CMR-defined MVO64. In the randomized CMR-endpoint REFLO-STEMI trial, neither adenosine nor nitroprusside produced consistent CMR benefit. The clinical event signal with adenosine also argues against routine use65. T-TIME randomized 440 patients to placebo, 10 mg alteplase, or 20 mg alteplase. The primary CMR outcome at 2–7 d was available for 396 patients. Mean MVO extent was 2.3%, 2.6%, and 3.5% of left ventricular mass, respectively. Neither alteplase dose reduced MVO66. A prespecified physiologic substudy found no significant between-group difference in immediate post-pPCI IMR67. In patients with 4–6 h of ischemia, the higher-dose association with greater MVO was exploratory and unadjusted for multiplicity. It should not be interpreted as definitive evidence of harm68.
Supersaturated oxygen and other device-based therapies
Joshi et al. described a randomized trial protocol evaluating the feasibility and mechanistic effects of supersaturated oxygen therapy delivered through radial artery access69. The trial is registered with ClinicalTrials.gov70. Further evaluation of this transradial approach should integrate standardized CMR, microvascular physiology, and clinical outcomes. Table 4 summarizes representative interventions and their design implications.
Discussion
Why improvements in surrogate endpoints often fail to translate into clinical benefit
Previous trials reveal three recurrent mismatches. First, enrollment is usually based on STEMI rather than a defined microvascular mechanism. This approach dilutes potentially responsive patients within a mechanistically heterogeneous population. Second, intervention timing may not match the intended target. Treatments intended to limit embolization must precede or coincide with embolic injury. Interventions targeting iron deposition and remodeling could be evaluated during T4–T5, depending on the target and study objective. Third, endpoints may not match the target. Angiographic slow flow, IMR, MVO, IMH, and clinical events represent different pathophysiologic levels. No single surrogate can establish therapeutic value.
Unresolved controversies
Three controversies remain: how overlapping MVO and IMH influence recovery, how early resistance measurements should be integrated with later tissue imaging, and which patients may benefit from a specific protective intervention. Current evidence does not support one fixed microvascular-protective treatment for all patients. Future studies should enroll identifiable high-risk or mechanistically enriched populations.
Research priorities
The first priority is prospective serial within-patient assessment with a prespecified reperfusion time zero. Where feasible, a research cohort could undergo standardized angiography and physiology at T0, thrombotic, inflammatory, and endothelial biomarker assessment at T1–T2, CMR for MVO and IMH at T3–T4, and assessment of remodeling and clinical outcomes at T5. This proposed research schedule would test associations between early abnormalities and subsequent injury and outcomes, while assessing feasibility, reproducibility, and added information beyond established clinical and CMR measures. Findings could then be tested in independent cohorts. These assessments are proposed for prospective evaluation of the framework, not as requirements for routine clinical care.
Randomized trials should organize target engagement, microvascular function, tissue injury, and clinical outcomes into a hierarchical endpoint chain. Early mechanistic trials can use IMR, AMR, or pharmacodynamic markers to confirm biologic activity. MVO, IMH, and infarct size can then assess tissue-level effects. Concordant and sufficiently large effects on earlier mechanistic and tissue endpoints can help justify larger trials powered to assess clinical outcomes. Mechanistic stratification can be probabilistic rather than mutually exclusive. Prespecified states may include embolic or thrombotic dominance, resistance or vasomotor dominance, barrier or edema dominance, hemorrhagic injury dominance, and mixed phenotypes. Patients may meet criteria across several dimensions. This approach is more consistent with current evidence than treating all patients with MVO as one population.
Evidence boundaries
This structured narrative review relied primarily on PubMed and did not use dual independent screening or formal risk-of-bias grading. The evidence spans cellular experiments, animal models, human biomarkers, invasive physiology, and CMR. It therefore cannot establish a definitive within-patient causal sequence. Publication details for recent online-first articles and trial-registration status may change. The available evidence supports conceptual integration, while the proposed framework requires prospective validation.
Conclusões
Restoration of epicardial flow by pPCI does not ensure microvascular and tissue-level reperfusion. MVO and IMH are related but noninterchangeable tissue phenotypes. Endothelial barrier and vasomotor dysfunction, pericyte-mediated constriction, immunothrombosis, distal embolization, and tissue edema may interact across patients and time windows. Angiography and physiology characterize early flow and resistance, while CMR identifies tissue injury and subsequent remodeling. Biomarkers and functional imaging provide complementary information, making the timing and purpose of each measurement central to interpretation. Clinical translation requires a continuous within-patient evidence chain linking mechanism, timing, function, tissue injury, and outcome. Randomized clinical-event evidence should be distinguished from human mechanistic findings and preclinical target validation; improvements in surrogate endpoints alone do not establish patient benefit. The T− to T5 conceptual research framework organizes these complementary observations around reperfusion. Prospective serial assessments can evaluate its feasibility, reproducibility, and added prognostic information. Mechanistic enrichment, intervention timing, and endpoint alignment should guide the next generation of microvascular-protection studies.
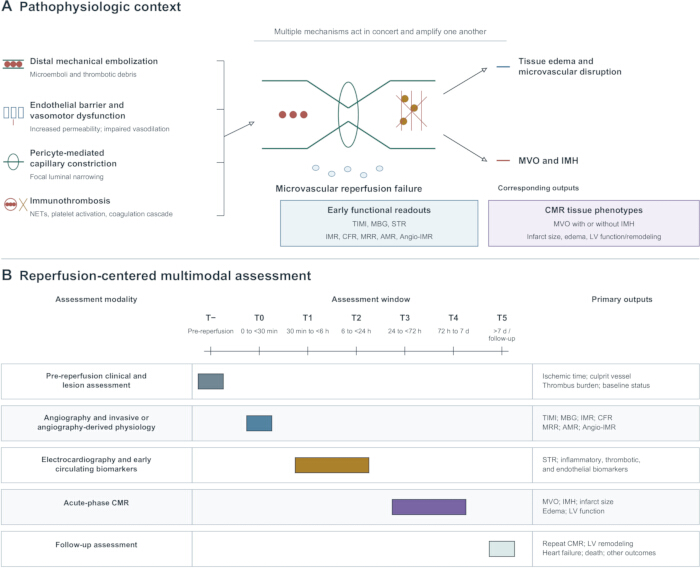
Figure 1: Candidate mechanisms, multimodal phenotypes, and assessment windows of microvascular injury after reperfusion in STEMI. (A) Distal embolization, endothelial barrier and vasomotor dysfunction, pericyte-mediated constriction, and immunothrombosis interact and converge on microvascular reperfusion failure. Tissue edema, microvascular disruption, and CMR-defined MVO and IMH are shown as associated tissue consequences. (B) The proposed reperfusion-centered T− to T5 research framework aligns serial assessment, angiography and physiology, electrocardiography and biomarkers, acute CMR, and follow-up outcomes with their principal measurement windows. Abbreviations: AMR = angiography-derived microvascular resistance; Angio-IMR = angiography-derived index of microcirculatory resistance; CFR = coronary flow reserve; CMR = cardiovascular magnetic resonance; IMH = intramyocardial hemorrhage; IMR = index of microcirculatory resistance; LV = left ventricular; MBG = myocardial blush grade; MRR = microvascular resistance reserve; MVO = microvascular obstruction; STR = ST-segment resolution; TIMI = Thrombolysis in Myocardial Infarction. Please click here to view a larger version of this figure.
Supplementary Figure 1: Evidence identification and verification workflow. The four-stage workflow covers literature discovery, evidence prioritization, verification of original reports and trial records, and structured narrative synthesis. Quantitative claims were checked against the original reports, and recent trial status was checked against registry records. Please click here to download this file.
| Concept | Primary construct measured | Common measures | Primary use | Key limitations |
| Angiographic no-reflow | Inadequate myocardial reperfusion after epicardial recanalization, manifested by reduced TIMI flow and/or poor myocardial blush after exclusion of mechanical causes | TIMI flow grade 0–2; prolonged cTFC; MBG 0–1 | Immediate intraprocedural identification and management | Influenced by technique, hemodynamics, and interpretation; not equivalent to CMR-defined MVO |
| Coronary microvascular dysfunction | Increased microvascular resistance or impaired flow reserve | IMR; CFR; MRR; AMR; Angio-IMR | Quantification of functional abnormalities and early risk | Threshold- and time-dependent; does not show the spatial distribution of tissue injury |
| CMR-defined MVO | Hypointense core within the enhanced infarct zone | Early or late gadolinium-enhanced CMR | Assessment of tissue-injury extent, prognosis, and trial endpoints | Influenced by imaging time, sequence, and quantification threshold |
| Intramyocardial hemorrhage | Erythrocyte extravasation after microvascular disruption | T2* imaging preferred; T2-weighted imaging and T2 mapping supportive | Identification of severe hemorrhagic injury | Not all MVO is accompanied by IMH; sequences are not interchangeable |
| Impaired ST-segment resolution | Electrophysiologic evidence of inadequate tissue reperfusion | STR at 60–90 min after pPCI | Rapid bedside risk stratification | Influenced by the baseline electrocardiogram and conduction abnormalities |
Table 1: MVO-related concepts, measurement levels, and clinical applications. The table distinguishes angiographic no-reflow, functional microvascular dysfunction, CMR-defined MVO, IMH, and impaired ST-segment resolution according to the construct measured, principal use, and key limitations. Abbreviations: AMR = angiography-derived microvascular resistance; Angio-IMR = angiography-derived index of microcirculatory resistance; CFR = coronary flow reserve; CMR = cardiovascular magnetic resonance; IMH = intramyocardial hemorrhage; IMR = index of microcirculatory resistance; MBG = myocardial blush grade; MRR = microvascular resistance reserve; MVO = microvascular obstruction; pPCI = primary percutaneous coronary intervention; STR = ST-segment resolution; TIMI = Thrombolysis in Myocardial Infarction.
| Mechanism | Core process | Observable phenotype | Current evidence | Research or therapeutic direction |
| Distal embolization and intravascular obstruction | Plaque and thrombus debris, microparticles, and platelet-fibrin aggregates | High thrombus burden; slow flow; reduced MBG | Relatively strong angiographic and human associative evidence | Selective embolic protection or local therapy; routine thrombus aspiration is unsupported |
| Endothelial barrier and vasomotor dysfunction | Glycocalyx shedding, junctional disruption, impaired nitric oxide responsiveness, and increased permeability | Slow flow; elevated resistance; edema; increased glycocalyx markers | Human associations plus preclinical mechanistic evidence | Barrier protection before reperfusion and early vasoactive therapy |
| Pericyte-mediated constriction | Local calcium signaling and contraction causing capillary narrowing | Elevated microvascular resistance in humans, which is nonspecific; focal capillary narrowing or obstruction in preclinical microscopy | Predominantly cellular and animal evidence | Pericyte relaxation and GPR39/TRP pathways; validated human biomarkers are needed |
| Immunothrombosis | NETs, tissue factor, platelets, and VWF/ADAMTS13 imbalance | Hypercoagulability; inflammation; slow flow; MVO | Human associations plus preclinical interventional evidence | Target NETs, platelets, or coagulation while balancing bleeding risk |
| Tissue edema and microvascular disruption | Interstitial edema, capillary compression, microvascular disruption, and erythrocyte extravasation | CMR-defined MVO, IMH or low T2* signal, and adverse remodeling | Relatively strong human imaging evidence | Limit acute injury and promote hemorrhage clearance and repair |
Table 2: Candidate mechanisms, observable phenotypes, and potential intervention points in MVO. Evidence categories reflect the balance of human, imaging, and preclinical support and should not be interpreted as formal certainty ratings. Abbreviations: ADAMTS13 = a disintegrin and metalloproteinase with a thrombospondin type 1 motif, member 13; CMR = cardiovascular magnetic resonance; IMH = intramyocardial hemorrhage; MBG = myocardial blush grade; MVO = microvascular obstruction; NETs = neutrophil extracellular traps; TRP = transient receptor potential; VWF = von Willebrand factor.
| Time window | Principal pathophysiologic question | Suggested assessments | Research application |
| T−: before reperfusion | Thrombus burden, ischemic time, and baseline inflammatory or endothelial status | Preprocedural imaging; baseline electrocardiography; blood sampling; clinical variables | Enrich high-risk mechanisms and document pretreatment status |
| T0: 0 to <30 min | Epicardial flow, myocardial blush, and immediate microvascular resistance | TIMI flow grade and cTFC; MBG; IMR, CFR, MRR, and AMR | Evaluate intraprocedural embolization, vasomotor function, and target engagement |
| T1: 30 min to <6 h | Early functional recovery and inflammatory or thrombotic response | STR; research-only repeat physiology; blood sampling | Confirm early pharmacodynamic and functional direction |
| T2: 6 to <24 h | Edema, cellular injury, and amplification of inflammation | Biomarkers; echocardiography; selected early CMR | Characterize the evolution of tissue injury |
| T3: 24 to <72 h | Formation of MVO or IMH and evolution of the infarct core | CMR; echocardiographic strain | Capture a key mechanistic tissue endpoint |
| T4: 72 h to 7 d | Common acute-phase tissue phenotypes | Standardized CMR: infarct size, MVO, IMH, and LVEF | Support cross-study comparison and risk stratification |
| T5: >7 d | Persistent MVO, iron deposition, repair, and remodeling | Follow-up CMR or echocardiography; heart failure; clinical events | Determine whether tissue effects translate into long-term benefit |
Table 3: Reperfusion-centered temporal matrix for multimodal assessment. T− to T5 are study-design coordinates anchored to the first documented restoration of forward epicardial flow and do not constitute a disease staging system. Abbreviations: AMR = angiography-derived microvascular resistance; CFR = coronary flow reserve; CMR = cardiovascular magnetic resonance; cTFC = corrected TIMI frame count; IMH = intramyocardial hemorrhage; IMR = index of microcirculatory resistance; LVEF = left ventricular ejection fraction; MBG = myocardial blush grade; MRR = microvascular resistance reserve; MVO = microvascular obstruction; STR = ST-segment resolution; TIMI = Thrombolysis in Myocardial Infarction.
| Study | Intervention and timing | Key endpoints | Main findings | Design implication |
| PULSE-MI | Prehospital methylprednisolone; T− | IMR; CRP | Lower CRP; no significant difference in immediate post-pPCI IMR | Pharmacodynamic activity does not establish improved microvascular function |
| ASSAIL-MI | Interleukin-6 receptor inhibition; T− | CMR-assessed myocardial salvage | Proof-of-concept signal for greater myocardial salvage | Requires validation with clinical outcomes and mechanistic enrichment |
| CONDI-2/ERIC-PPCI | Remote ischemic conditioning; T− | Acute MVO; 6-month infarct size | No significant difference | CMR completion within a large-trial substudy affects precision |
| CHANGE | Intravenous nicorandil; T−/T0 | Adjusted infarct mass; early MVO | Lower adjusted infarct mass and lower early MVO incidence | Imaging effects require concordant clinical validation |
| CLEAN | Intravenous nicorandil; T−/T0 | 12-month composite cardiovascular outcome | 13.1% in both groups; no significant difference | The neutral CLEAN result does not confirm that earlier imaging signals translate into clinical benefit; cross-trial differences preclude direct inference. |
| TOTAL | Routine manual thrombus aspiration; T0 | Major clinical outcomes; stroke | No clinical benefit; increased stroke risk | Does not support routine use in unselected patients |
| DANAMI-3-iPOST | Ischemic postconditioning; T0 | Death or hospitalization for heart failure | No significant reduction | Procedural complexity and effect may depend on initial flow |
| REFLO-STEMI | Intracoronary adenosine or nitroprusside; T0 | CMR-defined MVO; clinical outcomes | No consistent CMR benefit; no support for routine use | Drug, dose, timing, and endpoint level must be aligned |
| T-TIME | Intracoronary alteplase; T0 | CMR-defined MVO at 2–7 d; immediate IMR | No overall reduction in MVO or IMR | Does not support routine low-dose fibrinolysis without enrichment |
| SSO2 Radial MI | Transradial supersaturated oxygen; T0–T1 | Safety and feasibility; CMR and remodeling | Randomized trial protocol; efficacy results were not reported in the cited publication | Evaluate the safety, feasibility, and mechanistic effects of the transradial approach |
Table 4: Representative microvascular-protective interventions and implications for trial design. The table contrasts treatment timing, endpoint level, and the distinction between pharmacodynamic, imaging, physiologic, and clinical effects. Abbreviations: CMR = cardiovascular magnetic resonance; CRP = C-reactive protein; IMR = index of microcirculatory resistance; MVO = microvascular obstruction; pPCI = primary percutaneous coronary intervention; SSO2 = supersaturated oxygen.
Divulgações
The authors declare no conflicts of interest.
Agradecimentos
This work was supported by the project “Construction of an Integrated Research Platform for Post-PCI Chest Pain and Investigation of the Biological Basis of Traditional Chinese Medicine Syndrome Differentiation and Treatment” (grant no. 2023ZD0505701).
Referências
- Kloner RA, Ganote CE, Jennings RB. The no-reflow phenomenon after temporary coronary occlusion in the dog. J Clin Invest. 1974;54:1496-1508.
- Ito H et al. Lack of myocardial perfusion immediately after successful thrombolysis: a predictor of poor recovery of left ventricular function in anterior myocardial infarction. Circulation. 1992;85:1699-1705.
- Cenko E et al. Pathophysiology, prevention, and management of coronary microvascular obstruction: a clinical consensus statement of the ESC Working Group on Coronary Pathophysiology and Microcirculation, the ESC Working Group on Thrombosis, and the European Association of Percutaneous Cardiovascular Interventions (EAPCI) of the ESC. Eur Heart J. 2026;47:4215-4241.
- Vora KP et al. Microvascular obstruction and intramyocardial hemorrhage in reperfused myocardial infarctions: pathophysiology and clinical insights from imaging. JACC Cardiovasc Imaging. 2024;17:795-810.
- McAlindon E et al. Microvascular dysfunction determines infarct characteristics in patients with reperfused ST-segment elevation myocardial infarction: The MICROcirculation in Acute Myocardial Infarction (MICRO-AMI) study. PLoS One. 2018;13:e0203750.
- Xu MC, Zhao M. Changes of coronary blood flow before and after post-dilation following primary percutaneous coronary intervention in patients with STEMI. Medicine (Baltimore). 2024;103:e40646.
- Zhang Z et al. Microcirculatory resistance based on a single angiographic view in ST-segment elevation myocardial infarction patients. BMC Cardiovasc Disord. 2025;25:357.
- Ding S et al. Impact of early ST-segment changes on cardiac magnetic resonance-verified intramyocardial haemorrhage and microvascular obstruction in ST-elevation myocardial infarction patients. Medicine (Baltimore). 2015;94:e1438.
- Shavadia JS et al. Novel biomarkers, ST-elevation resolution, and clinical outcomes following primary percutaneous coronary intervention. J Am Heart Assoc. 2020;9:e016033.
- De Bruyne B et al. Microvascular resistance reserve for assessment of coronary microvascular function: JACC Technology Corner. J Am Coll Cardiol. 2021;78:1541-1549.
- Eerdekens R et al. Prognostic value of microvascular resistance reserve after percutaneous coronary intervention in patients with myocardial infarction. J Am Coll Cardiol. 2024;83:2066-2076.
- Kramer CM et al. Standardized cardiovascular magnetic resonance imaging (CMR) protocols: 2020 update. J Cardiovasc Magn Reson. 2020;22:17.
- Wu Z et al. Intramyocardial hemorrhage leads to higher MACE rate by increasing myocardial infarction volume in patients with STEMI. Int J Gen Med. 2024;17:275-285.
- Liu T et al. Intramyocardial hemorrhage and the wave front of reperfusion injury compromising myocardial salvage. J Am Coll Cardiol. 2022;79:35-48.
- de Waha S et al. Relationship between microvascular obstruction and adverse events following primary percutaneous coronary intervention for ST-segment elevation myocardial infarction: an individual patient data pooled analysis from seven randomized trials. Eur Heart J. 2017;38:3502-3510.
- Gadelmawla AF et al. Prognostic impact of persistent microvascular obstruction on cardiac magnetic resonance after STEMI: a systematic review and meta-analysis. Int J Cardiol. 2026;456:134523.
- Zhou P et al. Prognostic value of persistent microvascular obstruction on follow-up cardiac MRI after reperfused STEMI. JACC Asia. Published online July 17, 2026. https://doi.org/10.1016/j.jacasi.2026.06.014.
- Gibson CM et al. TIMI frame count: a quantitative method of assessing coronary artery flow. Circulation. 1996;93:879-888.
- van 't Hof AWJ et al. Angiographic assessment of myocardial reperfusion in patients treated with primary angioplasty for acute myocardial infarction: myocardial blush grade. Circulation. 1998;97:2302-2306.
- Niu Y et al. Association of endothelial glycocalyx degradation with post-PCI slow flow phenomenon in STEMI patients: a prospective observational study. Cardiovasc Diagn Ther. 2026;16:48.
- Piotrowska-Kownacka D et al. Microvascular obstruction evaluation using cardiovascular magnetic resonance (CMR) in ST-elevated myocardial infarction (STEMI) patients. Pol J Radiol. 2015;80:536-543.
- Robbers LFHJ et al. Magnetic resonance imaging-defined areas of microvascular obstruction after acute myocardial infarction represent microvascular destruction and haemorrhage. Eur Heart J. 2013;34:2346-2353.
- Lechner I et al. Clinical outcomes associated with various microvascular injury patterns identified by CMR after STEMI. J Am Coll Cardiol. 2024;83:2052-2062.
- Carrick D et al. Myocardial hemorrhage after acute reperfused ST-segment-elevation myocardial infarction: relation to microvascular obstruction and prognostic significance. Circ Cardiovasc Imaging. 2016;9:e004148.
- Eerenberg ES et al. The role of ADAMTS13 in acute myocardial infarction: cause or consequence? Cardiovasc Res. 2016;111:194-203.
- Birdal O et al. The relationship between clinical outcomes and calculated thrombus burden before and after initial flow in patients with ST-segment elevation myocardial infarction. Eurasian J Med. 2022;54:145-149.
- Wu KC et al. Prognostic significance of microvascular obstruction by magnetic resonance imaging in patients with acute myocardial infarction. Circulation. 1998;97:765-772.
- Galaup A et al. Protection against myocardial infarction and no-reflow through preservation of vascular integrity by angiopoietin-like 4. Circulation. 2012;125:140-149.
- Qi K et al. Cardiac microvascular barrier function mediates the protection of Tongxinluo against myocardial ischemia/reperfusion injury. PLoS One. 2015;10:e0119846.
- Methner C et al. The role of transient receptor potential melastatin channels in compressive force-induced contraction of primary cardiac pericytes. Physiol Rep. 2025;13:e70396.
- O'Farrell FM et al. Capillary pericytes mediate coronary no-reflow after myocardial ischaemia. eLife. 2017;6:e29280.
- Methner C, Cao Z, Mishra A, Kaul S. Mechanism and potential treatment of the no-reflow phenomenon after acute myocardial infarction: role of pericytes and GPR39. Am J Physiol Heart Circ Physiol. 2021;321:H1030-H1041.
- Mangold A et al. Coronary neutrophil extracellular trap burden and deoxyribonuclease activity in ST-elevation acute coronary syndrome are predictors of ST-segment resolution and infarct size. Circ Res. 2015;116:1182-1192.
- Stakos DA et al. Expression of functional tissue factor by neutrophil extracellular traps in culprit artery of acute myocardial infarction. Eur Heart J. 2015;36:1405-1414.
- Ge L et al. Neutrophil extracellular traps in ischemia-reperfusion injury-induced myocardial no-reflow: therapeutic potential of DNase-based reperfusion strategy. Am J Physiol Heart Circ Physiol. 2015;308:H500-H509.
- Qi Y et al. Proteomic evaluation of the thrombosis-inflammation interplay in STEMI with MVO. BMC Cardiovasc Disord. 2025;25:255.
- Tiller C et al. Association of intramyocardial hemorrhage with inflammatory biomarkers in patients with ST-segment elevation myocardial infarction. JACC Adv. 2025;4:101647.
- Porto I et al. Intracoronary microparticles and microvascular obstruction in patients with ST elevation myocardial infarction undergoing primary percutaneous intervention. Eur Heart J. 2012;33:2928-2938.
- Iop L et al. Functional autoantibodies and coronary microvascular obstruction in STEMI: a translational link between immune mechanisms and prognostic outcomes. Front Cardiovasc Med. 2026;13:1739236.
- Siao CJ et al. ProNGF, a cytokine induced after myocardial infarction in humans, targets pericytes to promote microvascular damage and activation. J Exp Med. 2012;209:2291-2305.
- Vaidya K et al. Colchicine inhibits neutrophil extracellular trap formation in patients with acute coronary syndrome after percutaneous coronary intervention. J Am Heart Assoc. 2021;10:e018993.
- Feng Y et al. MSC-derived exosomes mitigate myocardial ischemia/reperfusion injury by reducing neutrophil infiltration and the formation of neutrophil extracellular traps. Int J Nanomedicine. 2024;19:2071-2090.
- Omar M et al. Association and prognostic implications of no-reflow phenomenon and hypercoagulability in patients with ST-segment elevation myocardial infarction. JACC Asia. 2025;5:1487-1501.
- Cash JL et al. Chemerin15 inhibits neutrophil-mediated vascular inflammation and myocardial ischemia-reperfusion injury through ChemR23. EMBO Rep. 2013;14:999-1007.
- De Maria GL et al. Index of microcirculatory resistance as a tool to characterize microvascular obstruction and to predict infarct size regression in patients with STEMI undergoing primary PCI. JACC Cardiovasc Imaging. 2019;12:837-848.
- Grigorov R, Yambolov S. Fluoroscopic methods of assessment of coronary microvascular dysfunction – a review of literature. Bulgarian Cardiology. 2025;31:32-41.
- Yu Q et al. Intracoronary nicorandil improves coronary microcirculatory function after primary PCI in first-episode STEMI: an angiography-derived evaluation using AMR and QFR. Front Cardiovasc Med. 2026;13:1786130.
- Caullery B et al. Supersaturated oxygen therapy for coronary microvascular dysfunction in patients with ST-segment elevation myocardial infarction: the IC-HOT-MICRO pilot study. J Soc Cardiovasc Angiogr Interv. 2026;5:104269.
- Cao N et al. Prognostic value of β1 adrenergic receptor autoantibodies for microvascular obstruction in patients with STEMI post-PCI: a prospective cohort study. J Transl Autoimmun. 2024;9:100261.
- Milasinovic D et al. Correlation of non-invasive transthoracic Doppler echocardiography with invasive Doppler wire-derived coronary flow reserve and their impact on infarct size in patients with ST-segment elevation myocardial infarction treated with primary percutaneous coronary intervention. J Clin Med. 2024;13:2484.
- Wang C et al. Direct comparison of coronary microvascular obstruction evaluation using CMR feature tracking and layer-specific speckle tracking echocardiography in STEMI patients. Int J Cardiovasc Imaging. 2024;40:237-247.
- Nijveldt R et al. Functional recovery after acute myocardial infarction: comparison between angiography, electrocardiography, and cardiovascular magnetic resonance measures of microvascular injury. J Am Coll Cardiol. 2008;52:181-189.
- Marquard JM et al. Prehospital pulse-dose glucocorticoid on index of microvascular resistance in patients with ST-segment elevation myocardial infarction: a sub-study of the PULSE-MI trial. J Inflamm. 2025;22:12.
- Broch K et al. Randomized trial of interleukin-6 receptor inhibition in patients with acute ST-segment elevation myocardial infarction. J Am Coll Cardiol. 2021;77:1845-1855.
- Francis R et al. Effect of remote ischaemic conditioning on infarct size and remodelling in ST-segment elevation myocardial infarction patients: the CONDI-2/ERIC-PPCI CMR substudy. Basic Res Cardiol. 2021;116:59.
- Kim EK et al. Effects of high-dose atorvastatin pretreatment in patients with ST-segment elevation myocardial infarction undergoing primary percutaneous coronary intervention: a cardiac magnetic resonance study. J Korean Med Sci. 2015;30:435-441.
- Qian G et al. Effects of nicorandil administration on infarct size in patients with ST-segment-elevation myocardial infarction undergoing primary percutaneous coronary intervention: the CHANGE trial. J Am Heart Assoc. 2022;11:e026232.
- Huang D et al. Intravenous nicorandil in patients with ST-segment elevation myocardial infarction undergoing primary PCI: the CLEAN randomized clinical trial. J Am Coll Cardiol. 2026;88:1196-1207.
- Grancini L et al. The SALINE technique for the treatment of the no-reflow phenomenon during percutaneous coronary intervention in STEMI. J Clin Med. 2023;12:2405.
- Jolly SS et al. Randomized trial of primary PCI with or without routine manual thrombectomy. N Engl J Med. 2015;372:1389-1398.
- Ma M et al. A randomized controlled clinical trial of prolonged balloon inflation during stent deployment strategy in primary percutaneous coronary intervention for ST-segment elevation myocardial infarction: a pilot study. BMC Cardiovasc Disord. 2022;22:30.
- Mukherjee P, Jain M. Effect of ischemic postconditioning during primary percutaneous coronary intervention for patients with ST-segment elevation myocardial infarction: a single-center cross-sectional study. Ann Card Anaesth. 2019;22:347-352.
- Engstrøm T et al. Effect of ischemic postconditioning during primary percutaneous coronary intervention for patients with ST-segment elevation myocardial infarction: a randomized clinical trial. JAMA Cardiol. 2017;2:490-497.
- Baharvand F et al. Impact of intracoronary adenosine on the no-reflow phenomenon: a randomized, triple-blind, placebo-controlled clinical trial. Am Heart J Plus. 2025;60:100650.
- Nazir SA et al. Strategies to attenuate micro-vascular obstruction during P-PCI: the randomized reperfusion facilitated by local adjunctive therapy in ST-elevation myocardial infarction trial. Eur Heart J. 2016;37:1910-1919.
- McCartney PJ et al. Effect of low-dose intracoronary alteplase during primary percutaneous coronary intervention on microvascular obstruction in patients with acute myocardial infarction: a randomized clinical trial. JAMA. 2019;321:56-68.
- Maznyczka AM et al. Effects of intracoronary alteplase on microvascular function in acute myocardial infarction. J Am Heart Assoc. 2020;9:e014066.
- McCartney PJ et al. Low-dose alteplase during primary percutaneous coronary intervention according to ischemic time. J Am Coll Cardiol. 2020;75:1406-1421.
- Joshi FR et al. Supersaturated oxygen therapy using radial artery access to prevent left ventricular remodeling after anterior ST-segment elevation myocardial infarction: a randomized, controlled trial. Am Heart J Plus. 2025;55:100556.
- ClinicalTrials.gov. Heart Attack Blood Oxygen Therapy Trial (SSO2 Radial MI). NCT06662890. Trial registration record. https://clinicaltrials.gov/study/NCT06662890.