This systematic review protocol defines a reproducible framework for identifying, classifying, and mapping digital interventions for frailty or pelvic floor dysfunction in older adults while keeping clinically distinct populations and outcomes separate.
Исследовательская статья
Digital Interventions for Frailty and Pelvic Floor Dysfunction in Older Adults: A Systematic Review Protocol
В этой статье
Краткое содержание
Аннотация
Evidence on digital interventions for frailty and pelvic floor dysfunction (PFD) is methodologically fragmented because studies usually enroll one condition rather than older adults with both diagnoses. This article presents a systematic review protocol and evidence-mapping framework for two prespecified, condition-specific evidence streams. PubMed/MEDLINE, Embase, the Cochrane Central Register of Controlled Trials, Web of Science, CINAHL, CNKI, and Wanfang were searched from inception to January 31, 2026. Randomized trials were separated from nonrandomized evidence, and frailty and PFD outcomes were not combined in a single effect estimate. Source verification did not identify a study that required concurrent diagnoses of frailty and PFD, and did not establish a connected study-level network for quantitative synthesis. Published condition-specific reviews suggest that digital interventions may improve selected outcomes in PFD or frailty populations, but certainty varies, and those findings cannot be extrapolated to a dual-condition population. Accordingly, representative results are presented as a condition-specific evidence map and synthesis-decision framework; no pooled dual-condition effect, network estimate, or treatment ranking is reported. The protocol emphasizes traceable study identification, population alignment, outcome compatibility, and a prespecified gate for pairwise or network meta-analysis.
Введение
Population aging has made frailty an important challenge in geriatric medicine1. Frailty reflects reduced physiological reserve across multiple systems and is associated with adverse health outcomes. Pelvic floor dysfunction (PFD), including urinary incontinence, pelvic organ prolapse, and fecal incontinence, is also common in later life. Frailty and PFD may coexist, but an association between the conditions does not mean that all patients with either condition have both diagnoses2,3,4. Age-related loss of muscle mass and strength may affect both general physical function and pelvic floor support5,6. Neurological change, inflammation, multimorbidity, and functional dependence may also influence continence and rehabilitation capacity7,8,9. These shared mechanisms support studying coordinated care while preserving clear diagnostic criteria for each population.
Digital health technologies, including mobile applications, tele-rehabilitation, and wearable devices, may expand access to home-based assessment and rehabilitation10,11,12. Potential advantages include reminders, remote supervision, feedback, and personalized progression; however, effectiveness depends on the population, intervention content, comparator, adherence, and outcome definition13,14.
Evidence for virtual reality, app-based management, remote monitoring, and other digital approaches is heterogeneous15,16. Differences in technology, human support, intervention intensity, digital literacy, and age-friendly design complicate comparison across studies. A rigorous synthesis must therefore distinguish delivery technology from the clinical content being delivered and must avoid assuming that a higher-technology intervention is necessarily more effective.
Conventional pairwise meta-analysis compares interventions that have been evaluated directly. Network meta-analysis can additionally combine direct and indirect comparative evidence, but only when studies form a connected network and the transitivity assumption is plausible. Treatment ranking should be described using the surface under the cumulative ranking curve (SUCRA), not the unrelated term area under the curve. SUCRA summarizes rank probabilities and does not by itself establish statistically significant superiority.
An evidence map complements quantitative synthesis by displaying the amount, distribution, and certainty of evidence across interventions and outcomes. In this topic, the map should preserve the distinction between frailty, PFD, and the much narrower dual-condition population. The objective of this protocol is to make those distinctions explicit and to provide a transparent decision rule for when pairwise synthesis, network meta-analysis, or narrative mapping is appropriate. Systematic review and evidence mapping standards17,18,19,20,21 alongside reporting guidelines22,23 were followed. Search strategies were structured using PICO principles24, while risk of bias and certainty prerequisites were based on established evaluation tools25,26,27.
Протокол
Literature search strategy and protocol registration
PubMed/MEDLINE, Embase, the Cochrane Central Register of Controlled Trials, Web of Science, CINAHL, CNKI, and Wanfang were searched from inception to January 31, 2026. Searches were constructed separately for frailty and PFD and were combined only for evidence mapping. Controlled vocabulary and free-text terms represented older adults, frailty or PFD, digital interventions, and randomized trials. Table 1 presents the PubMed search framework. Complete platform-specific export files and final database record counts were not retained. Search records were managed in EndNote 21, and deduplication was performed using automated matching followed by manual confirmation. EndNote was used for reference management and duplicate removal, not plagiarism detection.
Inclusion/exclusion criteria and study selection process
Eligibility criteria
Two parallel populations were defined: (A) adults aged 60 years or older with frailty or prefrailty established using a recognized instrument, and (B) adults aged 60 years or older with a clinically defined PFD, including urinary incontinence, pelvic organ prolapse, or fecal incontinence. Participants diagnosed with both conditions were classified as a prespecified dual-condition subgroup. Digitally mediated rehabilitation or self-management interventions were included if they were compared with usual care, a waiting list, or a nondigital active comparator. For efficacy synthesis, randomized controlled trials with extractable outcome data were included. The frailty and PFD streams were not combined into a single effect estimate.
Exclusion criteria
Records were excluded if they lacked a retrievable full report or unique study identifier, represented aggregate reviews or pooled trial groups rather than individual trials, failed the prespecified age or diagnostic criteria, or evaluated interventions without a digital component. Nonrandomized studies were excluded from the efficacy meta-analysis but could be retained in a separately labeled evidence map. A primary reason was assigned to each full-text exclusion when the source record could be verified; however, the original exclusion log was not retained.
Data extraction and taxonomy of digital interventions
Screening and extraction workflow
The author (also the sole reviewer) screened titles and abstracts and the available full texts, applied the prespecified eligibility criteria, extracted study identifiers and design, population, intervention, and outcome fields, and performed source verification. No independent second reviewer or adjudicator participated, and inter-reviewer agreement was not calculated. This single-reviewer process was considered a methodological limitation.
Intervention taxonomy
Interventions were coded according to technology carrier, delivery model, rehabilitation content, human-support intensity, feedback, adherence support, and personalization. Clinically distinct interventions were kept separate unless their content and co-interventions were sufficiently similar. Table 2 presents the coding framework. Categories were not treated as network nodes without source-verifiable, clinically comparable trials.
Quality assessment
Risk-of-bias assessment
RoB 2 was prespecified for outcome-level assessment of eligible randomized trials. Study-level signaling-question responses and domain judgments were not retained; therefore, no pooled risk-of-bias summary or certainty rating was reported. The absence of a duplicate independent assessment was considered a methodological limitation.
Statistical analysis plan
Effect measures
Each clinical condition and outcome domain was analyzed separately. A mean difference was used when studies employed the same instrument, whereas a standardized mean difference (Hedges' g) was used when different instruments measured the same construct. Cross-instrument synthesis was not labeled as a weighted mean difference. Risk ratios or odds ratios were used for binary outcomes. Every estimate was to be reported with a 95% confidence interval, along with an indication of whether it was derived from a direct pairwise analysis or a network model.
Network-analysis gate
Network meta-analysis was to be attempted only after confirming that eligible randomized trials formed a connected network. Before modeling, plausible effect modifiers—including age, diagnostic criteria, baseline severity, intervention dose, co-interventions, and follow-up—were to be compared across treatment comparisons. If transitivity was not considered credible or the network was too sparse, pairwise or narrative synthesis was to be used instead. If treatment ranking was reported, numeric SUCRA values with rank probabilities or rankograms were to be provided, together with a statement that ranking was not a test of superiority.
Heterogeneity and robustness
Pairwise heterogeneity was to be quantified using I² and τ² only if a clinically compatible study-level dataset was established. Eligibility assessment and source verification did not yield data suitable for quantitative synthesis; therefore, no heterogeneity, subgroup, meta-regression, sensitivity, or small-study-effect analysis was performed.
Результаты
Study selection and source verification
The search, deduplication, screening, and exclusion steps are summarized in the PRISMA flow diagram (Figure 1). The study-selection record contained 10,842 identified records, 2,540 duplicates removed, 8,302 records screened, 122 reports sought, 18 reports not retrieved, 104 full texts assessed, 83 full texts excluded, and 21 records designated as included. Source verification of the 21 listed records identified aggregate reviews or pooled groups, explicitly nonrandomized designs, out-of-scope populations, and entries lacking complete citations or unique identifiers. Some records concerned conditions such as type 2 diabetes rather than frailty or PFD. No listed record required concurrent diagnoses of frailty and PFD. After application of the eligibility criteria, no source-verifiable study-level dataset supported a dual-condition efficacy synthesis. Table 3 reports the verification status of each listed record.
Condition-specific evidence and coding framework
The taxonomy separates app-guided training, videoconferencing or telerehabilitation, wearable or sensor-assisted training, remote monitoring, and other digitally supported care. These categories function as evidence-mapping labels rather than treatment nodes unless individual studies and intervention components are source-verifiable and clinically comparable. This approach prevents clinically different programs from being grouped solely because they share a digital delivery channel.
Outcome-level risk-of-bias results are not reported because the signaling-question responses and study-level RoB 2 matrix were unavailable. Figure 2 reproduces the available risk-of-bias visualization without alteration, but the judgments could not be independently reconstructed and are not used for certainty assessment. Table 4 records the missing certainty-assessment inputs.
Published evidence for pelvic floor dysfunction
Published systematic reviews and trials establish the clinical rationale for conservative and eHealth interventions in pelvic floor management28,29,30,31 and emphasize digital health access considerations32. A published systematic review of eHealth interventions for female PFD included 24 randomized trials and 3,691 participants, but its populations included women with PFD or at risk of PFD and were not restricted to frail older adults33,34,35,36. Individual trials have reported that videoconferencing can be comparable with conventional continence care in older women and that app- or device-supported pelvic floor muscle training can improve adherence or selected symptom outcomes37,38,39,40,41. These studies support a condition-specific rationale but do not establish effects in patients with both frailty and PFD.
Source verification did not yield a complete set of study-level means, standard deviations, event counts, follow-up times, and outcome directions for PFD. Figure 3 is retained without alteration as the available visualization, but its displayed estimates could not be reproduced and are not used to support a pooled effect. PFD findings are summarized narratively from the cited condition-specific reviews and randomized trials.
Published evidence for frailty
Recent condition-specific reviews provide mixed evidence. One 2026 review of 23 studies involving 3,426 frail older adults reported an improvement in frailty scores (SMD -0.42, 95% CI -0.72 to -0.12), whereas another 2026 review of 17 randomized trials concluded that evidence for overall frailty and several age-related outcomes remained limited or mixed34,35. An earlier review identified only four eligible studies and concluded that the evidence was insufficient for firm conclusions36. Figure 4 is retained without alteration as the available frailty-outcome visualization, but its study-level inputs could not be reproduced, and the displayed pooled estimate is not interpreted in this review. These external results illustrate why outcome definitions and study populations must be kept separate.
Eligible trials did not form a source-verifiable connected network; therefore, global inconsistency, node-splitting, and transitivity analyses were not performed. Figure 5 is retained without alteration as the available network visualization, but its study identifiers, edge counts, and effect-modifier distributions could not be verified, and the graph is not used for network inference. Table 5 presents the quantitative synthesis feasibility assessment.
Quantitative synthesis decision
The prespecified network-analysis gate was not met because a source-verifiable, connected study-level network was not established. Consequently, no league table, pairwise or network effect matrix, or direct or indirect network estimate is reported. Table 6 maps intervention categories to condition-specific evidence streams without estimating comparative effects. No reproducible SUCRA ranking was calculated. Figure 6 is retained without alteration as the available ranking visualization, but its numerical inputs and rank uncertainty could not be reconstructed, and the curves are not interpreted as evidence of superiority. A valid ranking analysis would require numerical SUCRA values, rank uncertainty, comparative effect estimates, and certainty ratings from a connected network.
Evidence mapping and certainty
Evidence was mapped in separate strata for frailty, PFD, and concurrent frailty with PFD, with intervention and outcome categories coded independently. Figure 7 is retained without alteration as the available bubble visualization, because source-verifiable study and participant counts could not be reconstructed for every listed record, its positions and bubble sizes are not used for quantitative inference. The evidence map, therefore, emphasizes distribution and gaps rather than numerical density.
Certainty ratings were not assigned because study-level risk-of-bias judgments, directness, heterogeneity, and precision could not be reconstructed. The term 'frailty status' is used consistently. Sparse or indirect comparisons remain narrative and are not described as robust comparative evidence.
Synthesis outcome
Leave-one-out, subgroup, meta-regression, Egger, and Begg analyses were not conducted because no study-level quantitative synthesis was performed. Small-study-effect tests would also have limited power with few studies and were not used as evidence of the absence of publication bias. Table 7 records the final decision for each planned analysis.
The synthesis-decision process resulted in narrative, condition-specific evidence mapping. No pooled estimate, treatment ranking, or network meta-analysis is reported for older adults with concurrent frailty and PFD. Digital interventions in frailty and PFD are therefore interpreted separately, with no cross-condition treatment hierarchy.
The author thanks the Women's Hospital, Zhejiang University School of Medicine, for institutional academic support. During manuscript preparation, an OpenAI large language model was used for language editing, formatting assistance, and targeted source verification. No AI tool was used to generate or alter study data or statistical results. The author reviewed the AI-assisted output and remains responsible for the accuracy, integrity, and final content of the manuscript. This research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
DATA AVAILABILITY:
The supporting data and materials are publicly available on Zenodo https://zenodo.org/records/22144709. All data analyzed in this study were derived from previously published articles, all of which are cited in the manuscript. Further inquiries can be directed to the corresponding author. The original database exports, deduplication log, full-text exclusion list, study-level extraction dataset, RoB 2 matrix, statistical input data, and executable R or Stata scripts are not available. No statistical input file or analysis code was generated because no quantitative synthesis was conducted. The article reports the source-verification results and cited published evidence.
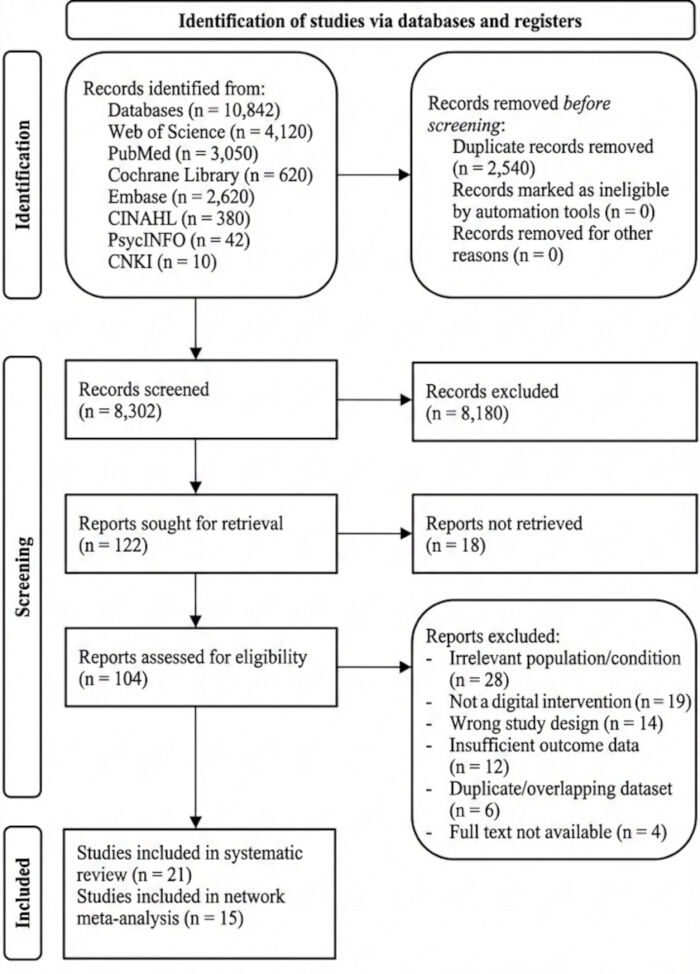
Figure 1: Recorded PRISMA study-selection flow. The diagram shows identification, screening, retrieval, eligibility, exclusion reasons, and records designated as included. The counts could not be independently reconstructed because the original search and screening files were not retained. Please click here to view a larger version of this figure.
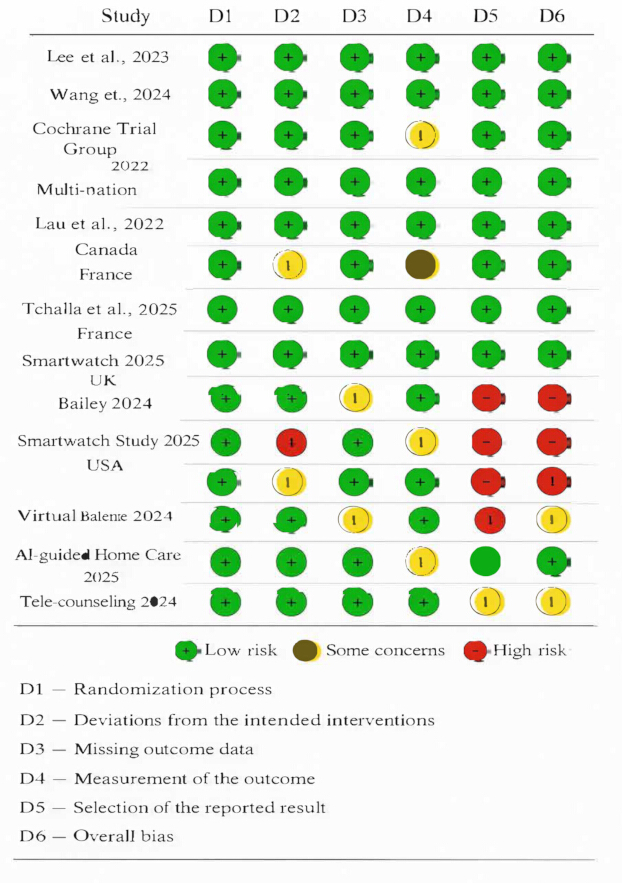
Figure 2: Available risk-of-bias visualization for the listed randomized trials. The signaling-question responses and study-level RoB 2 matrix were unavailable; therefore, the displayed domain judgments could not be independently reconstructed and are not used for certainty assessment. Please click here to view a larger version of this figure.
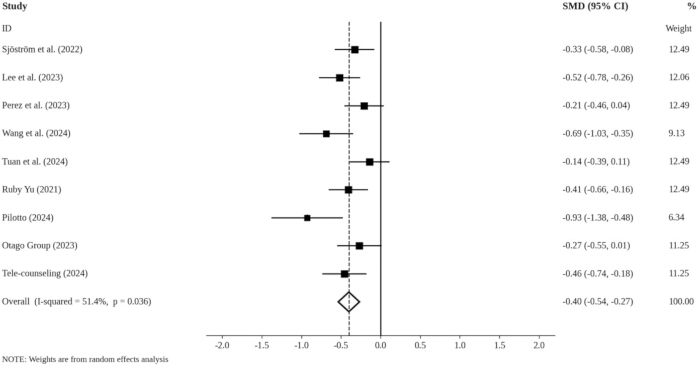
Figure 3: Available forest plot for pelvic-floor-dysfunction symptom outcomes. Study-level inputs required to reproduce the displayed estimates were unavailable; the plot is not used to support a pooled effect in this review. Please click here to view a larger version of this figure.
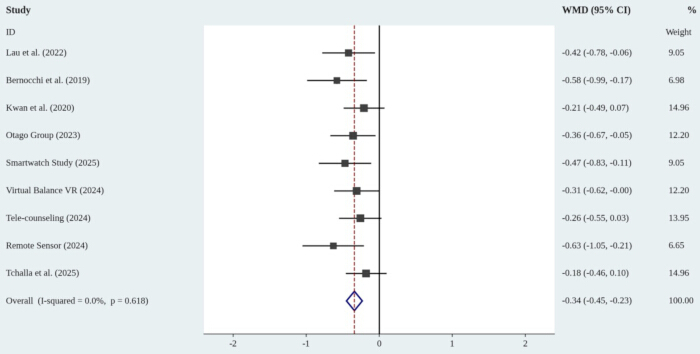
Figure 4: Available forest plot for frailty-related outcomes. Study-level inputs required to reproduce the displayed estimates were unavailable; the plot is not used to support a pooled effect in this review. Please click here to view a larger version of this figure.
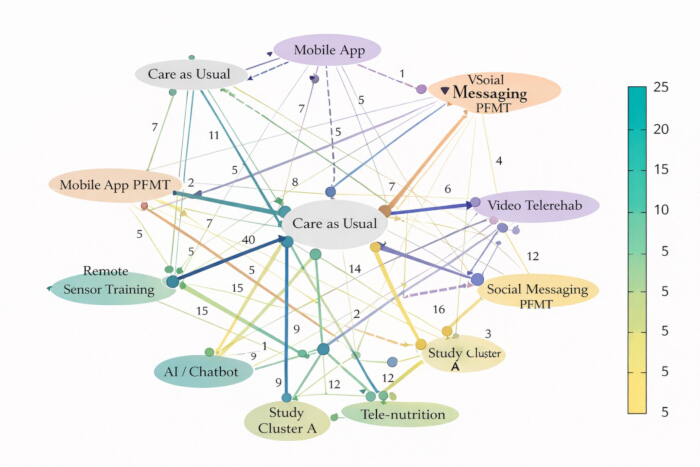
Figure 5: Available network visualization of digital-intervention categories. The underlying study identifiers, edge counts, and effect-modifier distributions were unavailable; the graph is descriptive and is not used for network inference. Please click here to view a larger version of this figure.
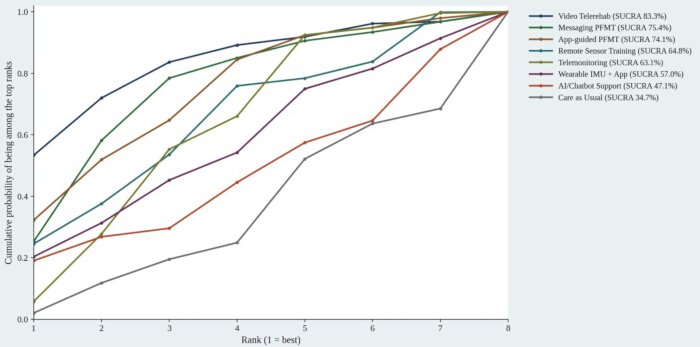
Figure 6: Available SUCRA curves for digital-intervention categories. Ranking inputs and rank uncertainty were unavailable; the curves are retained as a descriptive visualization and are not interpreted as evidence of superiority. Please click here to view a larger version of this figure.
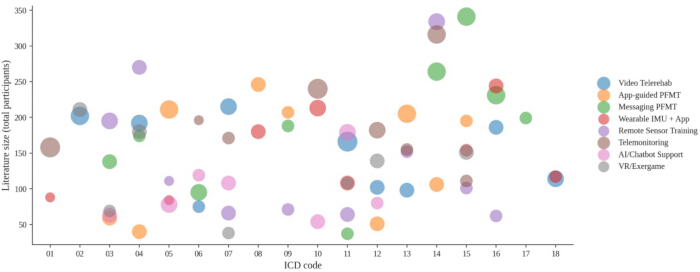
Figure 7: Available bubble visualization of intervention categories and coded outcomes. Study and participant counts could not be reconstructed; bubble positions and sizes are not used for quantitative inference. Please click here to view a larger version of this figure.
| Set | Search Terms (Keywords and MeSH) | Recorded result count |
| #1 | (Population: Frailty) | |
| 1.1 | "Frailty"[MeSH Terms] OR "Frail Elderly"[MeSH Terms] | 28,451 |
| 1.2 | "frailty syndrome"[Title/Abstract] OR "frail"[Title/Abstract] OR "pre-frail"[Title/Abstract] | 54,213 |
| 1.3 | "sarcopenia"[Title/Abstract] OR "frailty status"[Title/Abstract] | 19,304 |
| 1.4 | #1.1 OR #1.2 OR #1.3 | 72,159 |
| #2 | (Condition: Pelvic Floor Dysfunction) | |
| 2.1 | "Pelvic Floor Disorders"[MeSH Terms] OR "Urinary Incontinence"[MeSH Terms] | 42,108 |
| 2.2 | "Pelvic Organ Prolapse"[MeSH Terms] OR "Fecal Incontinence"[MeSH Terms] | 18,924 |
| 2.3 | "pelvic floor dysfunction"[Title/Abstract] OR "stress incontinence"[Title/Abstract] | 22,145 |
| 2.4 | "pelvic floor muscle"[Title/Abstract] OR "overactive bladder"[Title/Abstract] | 15,487 |
| 2.5 | #2.1 OR #2.2 OR #2.3 OR #2.4 | 68,413 |
| #3 | (Intervention: Digital Interventions) | |
| 3.1 | "Telemedicine"[MeSH Terms] OR "Mobile Applications"[MeSH Terms] | 65,421 |
| 3.2 | "Digital health"[Title/Abstract] OR "mHealth"[Title/Abstract] OR "eHealth"[Title/Abstract] | 48,231 |
| 3.3 | "Tele-rehabilitation"[Title/Abstract] OR "tele-nursing"[Title/Abstract] | 12,354 |
| 3.4 | "Wearable devices"[Title/Abstract] OR "smartphones"[Title/Abstract] | 34,102 |
| 3.5 | "Virtual reality"[Title/Abstract] OR "Biofeedback"[Title/Abstract] | 18,452 |
| 3.6 | "Mobile apps"[Title/Abstract] OR "interactive technology"[Title/Abstract] | 14,219 |
| 3.7 | #3.1 OR #3.2 OR #3.3 OR #3.4 OR #3.5 OR #3.6 | 156,742 |
| #4 | (Study Filter: Randomized Controlled Trials) | |
| 4.1 | "Randomized Controlled Trial"[Publication Type] OR "Clinical Trial"[Publication Type] | 682,143 |
| 4.2 | "randomized"[Title/Abstract] OR "placebo"[Title/Abstract] OR "randomly"[Title/Abstract] | 841,257 |
| 4.3 | #4.1 OR #4.2 | 954,120 |
| #5 | (Age Filter: Older Adults) | |
| 5.1 | "Aged"[MeSH Terms] OR "Aged, 80 and over"[MeSH Terms] | 984,231 |
| 5.2 | "elderly"[Title/Abstract] OR "older adults"[Title/Abstract] OR "senior"[Title/Abstract] | 742,108 |
| 5.3 | #5.1 OR #5.2 | 1,254,192 |
| #6 | (Intersection) | |
| 6.1 | #1.4 AND #2.5 AND #3.7 AND #4.3 AND #5.3 | 427 |
Table 1: PubMed search framework. The table lists population, condition, digital-intervention, randomized-trial, and age concepts used to structure the search. *Recorded search counts could not be independently reconstructed because the original database exports and complete search log were unavailable. The PubMed total does not reconcile with Figure 1.
| Category | Item | Operational definition / coding rule | Typical delivery format | Human support level |
| Taxonomy | App-guided PFMT | Smartphone application delivers structured PFMT modules with self-directed practice | Application plus home training | Low to moderate |
| Taxonomy | Messaging mini-program PFMT | PFMT delivered through social messaging or a mini-program with scheduled check-ins | Mini-program plus chat | Moderate |
| Taxonomy | Video telerehabilitation | Real-time or scheduled video sessions supervise exercise technique and progression | Video visits plus materials | Moderate to high |
| Taxonomy | Wearable/sensor-augmented training | Wearables or sensors capture activity, balance, or muscle-performance metrics for feedback | Wearable or sensor plus application | Low to moderate |
| Taxonomy | Remote monitoring and case management | Symptoms or physiological measures are reported remotely for clinician review and plan adjustment | Platform plus alerts | Moderate |
| Taxonomy | VR/exergaming rehabilitation | Gamified immersive or screen-based tasks target balance, strength, or adherence | VR or exergame | Low to moderate |
| Taxonomy | AI/chatbot-assisted support | Algorithmic or conversational support provides reminders, education, or triage prompts | Application or chatbot | Low; escalate when clinically indicated |
| Functional component | Structured training library | Standardized PFMT, exercise, or self-management modules are delivered in video or text | Application or video modules | Any |
| Functional component | Reminders and prompts | Automated notifications or scheduled prompts support practice or monitoring | Push, SMS, or in-application | Any |
| Functional component | Adherence tracking | Completed sessions are logged manually or captured automatically | Logs or dashboard | Any |
| Functional component | Symptom monitoring diary | Participants record symptoms, function, fatigue, or wellbeing at prespecified intervals | In-application forms | Any |
| Functional component | Feedback dashboard | Progress summaries display adherence, symptoms, or performance over time | Charts or reports | Any |
| Functional component | Telecoaching/teleconsultation | A clinician or nurse provides coaching by video, telephone, or messaging at a defined frequency | Video, telephone, or chat | Moderate to high |
| Functional component | Goal setting and action planning | Individual goals and graded tasks are linked to an action plan | In-application goals | Any |
| Functional component | Personalization rules | Intensity or progression changes according to baseline status or ongoing data | Adaptive logic | Any |
| Functional component | Educational content | Structured education addresses technique, self-care, lifestyle, or safety | Micro-lessons | Any |
| Functional component | Objective monitoring | Wearables or phone sensors capture steps, gait, balance, or related measures | Wearable or phone | Any |
| Functional component | Safety screening and alerts | Red-flag checks and escalation rules identify potential harm or clinical deterioration | Alerts or triage | Clinician pathway required |
| Functional component | Clinician portal/data review | A provider-facing dashboard supports monitoring and adjustment | Portal or report | Moderate |
| Functional component | Social/peer support | Peer, group, or caregiver support is embedded in the intervention | Group or community | Low to moderate |
| Functional component | Data export/interoperability | Structured summaries can be exported or linked to other systems | CSV, PDF, or structured report | Any |
Table 2: Coding framework for digital interventions. Categories are defined by delivery technology, rehabilitation content, human support, feedback, adherence support, and personalization.
| Listed entry | Reported design | Reported population | Bibliographic status | Scope/design assessment | Decision for synthesis | Verification requirement | Source / note |
| Sjöström et al., 2022 | RCT | Women with urinary incontinence | Exact citation not supplied | Potential PFD stream only; dual diagnosis not shown | Exclude pending verification | Provide title, journal, DOI/PMID, and outcome data | A related Sjöström research program exists, but the listed year/sample must be matched exactly. |
| Perez et al., 2023 | RCT | Stress urinary incontinence | Exact citation not supplied | Potential PFD stream only | Exclude pending verification | Provide full citation and trial identifier | No author/journal/title was supplied. |
| Lee et al., 2023 | RCT | Mixed urinary incontinence | Exact citation not supplied | Potential PFD stream only | Exclude pending verification | Provide full citation and trial identifier | No author/journal/title was supplied. |
| Wang et al., 2024 | RCT | Older women with PFD | Exact citation not supplied | Potential PFD stream only | Exclude pending verification | Provide full citation and trial identifier | WeChat intervention requires source-level verification. |
| Cochrane Trial Group 2022 | Meta-RCT | PFD patients | Aggregate/placeholder label | Not an individual randomized trial | Exclude | Replace with each eligible primary trial | A pooled review or trial group cannot be entered as one RCT. |
| Tchalla et al., 2025 | RCT | Older adults | Exact citation not supplied | Frailty/PFD diagnosis not documented | Exclude pending verification | Provide full citation and diagnostic criteria | Readmission alone does not establish frailty or PFD eligibility. |
| Lau et al., 2022 | RCT | Older adults with hypertension | Exact citation not supplied | Population not defined by frailty or PFD | Exclude from target synthesis | Provide source only if a prespecified frailty diagnosis is documented | Hypertension is not a proxy for frailty. |
| Sun et al., 2019 | RCT | Older adults with type 2 diabetes | Verified publication, but out of scope | No frailty or PFD target population | Exclude | Do not pool as frailty/PFD evidence | https://pubmed.ncbi.nlm.nih.gov/30609983/ |
| Bernocchi et al., 2019 | RCT | Older adults at fall risk | Exact citation not supplied | PFD not documented; frailty diagnosis unclear | Exclude pending verification | Provide full citation and frailty criteria | Fall risk is not equivalent to a frailty diagnosis. |
| Kwan et al., 2020 | RCT | Cognitive frailty | Exact citation not supplied | Potential frailty stream only | Exclude pending verification | Provide full citation and outcome instrument | Cannot contribute to a PFD network. |
| Otago Group 2023 | Pilot RCT | Frail older adults | Group/placeholder label | Potential frailty stream only | Exclude pending verification | Provide named authors, title, journal, and identifier | Study label is not a complete citation. |
| Smartwatch Study 2025 | Cluster RCT | Frailty | Placeholder-style label | Potential frailty stream only | Exclude pending verification | Provide full citation, cluster unit, and adjusted effect | Cluster design requires cluster-adjusted analysis. |
| Virtual Balance VR 2024 | RCT | Frail older adults | Placeholder-style label | Potential frailty stream only | Exclude pending verification | Provide full citation and frailty criteria | Study label is not a complete citation. |
| AI-guided Home Care 2025 | RCT | Chronic frailty | Placeholder-style label | Potential frailty stream only | Exclude pending verification | Provide full citation and intervention details | Study label is not a complete citation. |
| Tele-counseling 2024 | RCT | Frail older adults | Placeholder-style label | Potential frailty stream only | Exclude pending verification | Provide full citation and trial identifier | Study label is not a complete citation. |
| Remote sensor training 2024 | RCT | Frailty | Placeholder-style label | Potential frailty stream only | Exclude pending verification | Provide full citation and outcome data | Not included in the recorded meta-analysis, but still requires verification for mapping. |
| Tele-nutrition 2025 | RCT | Frail older adults | Placeholder-style label | Potential frailty stream only | Exclude pending verification | Provide full citation and trial identifier | Study label is not a complete citation. |
| Cognitive assist tele-health 2024 | RCT | Frail older adults | Placeholder-style label | Potential frailty stream only | Exclude pending verification | Provide full citation and trial identifier | Study label is not a complete citation. |
| Social support chatbot 2025 | RCT | Social frailty | Placeholder-style label | Construct differs from physical frailty/PFD | Exclude pending verification | Provide full citation and prespecified outcome domain | Social frailty should not be pooled automatically with physical frailty. |
| Tele-rehab observational 2021 | Cohort | Post-surgery PFD | Nonrandomized by recorded description | Ineligible for RCT efficacy synthesis | Exclude from meta-analysis | May retain only in separately labeled evidence map | Use a design-appropriate risk-of-bias tool if retained. |
| Digital education program 2022 | Quasi-experimental | Older women | Nonrandomized by recorded description | Ineligible for RCT efficacy synthesis; PFD diagnosis unclear | Exclude from meta-analysis | May retain only after source and population verification | Do not classify as an RCT. |
Table 3: Study source-verification matrix. Each listed record is classified by bibliographic verifiability, design, population alignment, and eligibility for quantitative synthesis.
| Certainty domain | Required information | Availability | Assessment | Consequence |
| Risk of bias | Outcome-level RoB 2 signaling responses and judgments | Unavailable | Not rated | No certainty category assigned |
| Directness | Population, intervention, comparator, and outcome alignment | Incomplete for listed records | Not rated | Condition-specific evidence is not generalized to concurrent frailty and PFD |
| Heterogeneity | Compatible study-level effects and variance estimates | Unavailable | Not calculated | I-squared and tau-squared not reported |
| Precision | Reproducible effect estimates and confidence intervals | Unavailable | Not rated | Displayed legacy estimates are not used for inference |
| Network inconsistency | Connected loops with direct and indirect estimates | Not established | Not tested | No node-splitting or global inconsistency result |
| Transitivity | Distribution of plausible effect modifiers by comparison | Unavailable | Not assessed | No network ranking |
| Publication bias | Adequate number of study-level effects | Unavailable | Not tested | No Egger or Begg inference |
Table 4: Certainty-assessment prerequisites. The table records the availability of risk-of-bias, directness, heterogeneity, precision, and publication-bias inputs.
| Requirement | Prespecified criterion | Observed status | Decision | Implication |
| Eligible study set | Source-verifiable randomized trials meeting age and diagnostic criteria | Not established | Quantitative synthesis not initiated | Use condition-specific narrative evidence mapping |
| Bibliographic verification | Complete citation and unique study identifier for every included record | Incomplete | Unverified entries excluded | Prevents aggregate or placeholder labels from being analyzed as trials |
| Study-level outcomes | Extractable group data, time points, instruments, and analysis populations | Unavailable | No effect estimation | Forest-plot values are not interpreted as reproducible pooled effects |
| Outcome compatibility | Common construct and clinically comparable follow-up | Not established | No SMD/MD pooling | Frailty and PFD outcomes remain separate |
| Network connectivity | At least one connected network of eligible treatment comparisons | Not established | No network meta-analysis | No direct/indirect effect matrix |
| Transitivity | Effect modifiers sufficiently comparable across comparisons | Not assessable | No ranking or inconsistency inference | Age, diagnosis, severity, dose, and co-interventions require study-level review |
| Risk of bias | Outcome-level RoB 2 signaling responses and duplicate judgments | Unavailable | No pooled RoB summary | Certainty of evidence not rated |
| Analysis inputs and code | Statistical input data plus executable analysis scripts | Unavailable | R and Stata not used | Software versions are not applicable |
Table 5: Quantitative-synthesis feasibility matrix. The table records whether eligibility, source verification, connectivity, transitivity, outcome compatibility, and analysis-file requirements were met.
| Intervention category | Frailty stream | PFD stream | Concurrent frailty + PFD | Potential outcome domains | Synthesis role |
| App-guided pelvic floor muscle training | Not applicable unless frailty is documented | Condition-specific evidence available | Not verified | Urinary symptoms; pelvic-floor function; adherence; quality of life | Narrative PFD mapping |
| Videoconferencing / telerehabilitation | Potentially relevant after source verification | Condition-specific evidence available | Not verified | Function; technique; symptoms; adherence; service access | Separate condition-specific mapping |
| Wearable or sensor-assisted training | Potentially relevant | Potentially relevant | Not verified | Activity; gait; balance; muscle performance; adherence | Exploratory evidence mapping |
| Remote monitoring and case management | Potentially relevant | Potentially relevant | Not verified | Symptoms; function; safety alerts; health-service use | Exploratory evidence mapping |
| VR / exergaming | Potentially relevant after frailty verification | No verified PFD synthesis set | Not verified | Balance; strength; engagement; falls-related outcomes | Narrative frailty mapping |
| AI / chatbot-assisted support | Potentially relevant | Potentially relevant | Not verified | Education; reminders; self-management; triage | Exploratory evidence mapping |
| Usual care / nondigital active control | Comparator | Comparator | Comparator only if dual diagnosis is verified | Condition-specific comparator outcomes | Comparator label; not a digital node |
Table 6: Condition-specific evidence-mapping matrix. Intervention classes are mapped to eligible population streams and potential outcome domains without estimating comparative effects.
| Planned analysis | Minimum requirement | Reporting |
| Pairwise meta-analysis | At least two clinically compatible, source-verifiable trials | Condition-specific narrative synthesis |
| Network meta-analysis | Connected eligible network with plausible transitivity | No direct or indirect network estimates |
| Forest-plot interpretation | Reproducible study effects, variances, and analysis populations | Captions state the reproducibility limitation |
| SUCRA ranking | Connected network, rank probabilities, and uncertainty | No claim of treatment superiority |
| Inconsistency testing | Connected loops and direct/indirect estimates | No global or node-splitting inference |
| Subgroup / meta-regression | Sufficient studies and prespecified study-level covariates | No effect-modifier claim |
| Sensitivity analysis | Reproducible primary quantitative model | No leave-one-out or model-switching result |
| Small-study-effect testing | Adequate number of independent study effects | No Egger or Begg inference |
Table 7: Synthesis decision log. The table records which planned quantitative analyses were not performed and the reason for each decision.
Обсуждение
This review indicates that digital interventions for PFD and for frailty constitute two related but clinically distinct evidence bases. Published reviews suggest potential benefits in condition-specific populations, but those findings do not demonstrate efficacy in older adults diagnosed with both disorders33,34,35,36. Pooling across incompatible populations would undermine the clinical interpretation of direct or indirect comparisons.
Source verification was decisive for determining synthesis eligibility. Eligible records require a complete citation and unique identifier, and numerical results must be traceable to a report, time point, instrument, and analysis population. Applying these criteria prevented aggregate reviews, incomplete labels, and nonrandomized studies from being treated as individual randomized trials and led to narrative rather than quantitative synthesis.
A second critical step is outcome harmonization. Frailty instruments such as the Fried phenotype, frailty index, and physical-performance measures are not interchangeable by default; similarly, urinary-incontinence symptoms, pelvic-floor strength, and quality of life represent different constructs. Standardization can address scale differences only when instruments measure the same underlying outcome. Clinical judgment and prespecified outcome domains remain necessary.
Network meta-analysis requires more than a connected graph: plausible effect modifiers must be similarly distributed across comparisons, and sparse loops limit the power of inconsistency tests. Treatment rankings should therefore be interpreted only after examining comparative effects, confidence or credible intervals, and certainty of evidence.
This review has four important limitations: it was not prospectively registered in PROSPERO; screening, extraction, and source verification were conducted by one reviewer; the original search exports, exclusion log, study-level extraction dataset, RoB 2 matrix, and analysis files were unavailable; and no source-verifiable dual-condition study-level dataset was established. These limitations prevented independent reconstruction of the PRISMA counts, risk-of-bias judgments, and quantitative analyses and increase the risk of selection and information bias. The condition-specific narrative findings should not be generalized to older adults with concurrent frailty and PFD.
In conclusion, digital interventions may benefit selected outcomes in condition-specific frailty or PFD populations, but the evidence identified here does not support a pooled effect or treatment hierarchy for older adults with concurrent frailty and PFD. A reproducible quantitative synthesis requires traceable search records, duplicate independent review, complete study-level extraction and risk-of-bias data, and a clinically coherent connected network. Until those requirements are met, condition-specific narrative interpretation is the appropriate synthesis.
Раскрытие информации
The author has no competing interests to declare.
Author Contributions:
Xia Lei: conceptualization; methodology; literature searching and source verification; data curation of the source-verification records; writing - original draft; writing - review and editing; visualization; and project administration. No additional contributors participated in screening, extraction, risk-of-bias assessment, or statistical analysis.
Благодарности
The author thanks the Women's Hospital, Zhejiang University School of Medicine, for institutional academic support. During manuscript preparation, an OpenAI large language model was used for language editing, formatting assistance, and targeted source verification. No AI tool was used to generate or alter study data or statistical results. The author reviewed the AI-assisted output and remains responsible for the accuracy, integrity, and final content of the manuscript. This research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
Материалы
| Имя | Компания | Каталожный номер | Комментарии |
|---|---|---|---|
| Cochrane Risk of Bias tool | Cochrane Methods | RoB 2 | Prespecified framework for outcome-level risk-of-bias assessment; signaling responses and the study-level matrix are unavailable |
| EndNote | Clarivate | 21 | Reference management and duplicate removal |
| GRADE framework | GRADE Working Group | GRADE-NMA | Prespecified certainty-of-evidence framework; no rating was undertaken because the required study-level inputs are unavailable |
| Literature databases: CINAHL; CNKI; Cochrane CENTRAL; Embase; PubMed/MEDLINE; Wanfang; Web of Science | Multiple providers | Searched from inception through 31 January 2026 | Databases used for the condition-specific search streams; original export files were not retained |
| R | R Foundation for Statistical Computing | Not used / Not applicable | No quantitative synthesis or network meta-analysis was conducted |
| Stata | StataCorp | Not used / Not applicable | No statistical analysis or data processing was conducted |
Ссылки
- Hoogendijk EO, et al. Frailty in older adults. Lancet. 2019;394(10206):1365-75.
- Dent E, et al. Management of frailty: opportunities, challenges, and future directions. Lancet. 2019;394(10206):1376-86.
- Suskind AM. Frailty and the management of pelvic floor disorders in older women. Curr Opin Urol. 2017;27(3):274-80.
- Veronese N, et al. Frailty is associated with incident urinary incontinence in older adults. Neurourol Urodyn. 2018;37(1):433-40.
- Cruz-Jentoft AJ, et al. Sarcopenia: revised European consensus on definition and diagnosis. Age Ageing. 2019;48(1):16-31.
- Bo K, et al. Evidence-based physical therapy for the pelvic floor. Neurourol Urodyn. 2015;34(3):254-63.
- Ferrucci L, Fabbri E. Inflammageing: chronic inflammation in ageing, cardiovascular disease, and frailty. Nat Rev Cardiol. 2018;15(9):505-22.
- O'Caoimh R, et al. Prevalence of frailty at population level in European ADVANTAGE Joint Action Member States: a systematic review and meta-analysis. Ann Ist Super Sanita. 2018;54(3):226-38.
- Kojima G. Frailty as a predictor of hospitalisation among community-dwelling older people: a systematic review and meta-analysis. J Epidemiol Community Health. 2019;73(11):997-1003.
- Mair FS, Murray E. Promoting innovation and evidence-based approaches in digital health. Lancet. 2016;388(10057):2231-2.
- Marcolino MS, et al. The impact of mHealth interventions: systematic review of systematic reviews. JMIR Mhealth Uhealth. 2018;6(1):e23.
- Wuytack F et al. Efficacy of telehealth-delivered interventions for urinary incontinence: a systematic review. J Telemed Telecare. 2018;24(7):452-63.
- Asch DA, Muller RW, Volpp KG. Automated hovering in health care—watching over the 5000 hours. N Engl J Med. 2020;383(4):362-8.
- Nilaus V, Bille AB, Ovesen C, Schiotz HA. Digital health interventions for urinary incontinence in women: a systematic review. Int Urogynecol J. 2021;32(8):2099-110.
- Radhakrishnan K, et al. Barriers and facilitators for sustainability of tele-homecare programs: a systematic review. Health Serv Res. 2017;52(4):1361-75.
- Kruse CS, et al. Telehealth and patient satisfaction: a systematic review and narrative analysis. BMJ Open. 2018;8(8):e016242.
- Tonin FS, Rotta I, Mendes AM, Pontarolo R. Network meta-analysis: a technique to gather evidence from direct and indirect comparisons. Pharm Pract (Granada). 2017;15(1):943.
- Hutton B, et al. The PRISMA extension statement for reporting of systematic reviews incorporating network meta-analyses of health care interventions: checklist and explanations. Ann Intern Med. 2015;162(11):777-84.
- Rouse B, Chaimani A, Li T. Network meta-analysis: an introduction for clinicians. Intern Emerg Med. 2017;12(1):103-11.
- Miake-Lye IM, Hempel S, Shanman R, Shekelle PG. What is an evidence map? A systematic review of published evidence maps and their definitions, methods, and products. Syst Rev. 2016;5(1):28.
- Snilstveit B et al. Evidence gap maps: a tool for promoting evidence-informed policy and strategic research agendas. J Clin Epidemiol. 2016;79:120-9.
- Page MJ, et al. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ. 2021;372:n71.
- Schiavo JH. PROSPERO: an international register of systematic review protocols. Med Ref Serv Q. 2019;38(2):171-80.
- Eriksen MB, Frandsen TF. The impact of patient, intervention, comparison, outcome (PICO) as a search strategy tool on literature search quality: a systematic review. J Med Libr Assoc. 2018;106(4):420-31.
- Sterne JAC, et al. RoB 2: a revised tool for assessing risk of bias in randomised trials. BMJ. 2019;366:l4898.
- Salanti G et al. Evaluating the quality of evidence from a network meta-analysis. PLoS One. 2014;9(7):e99682.
- Brignardello-Petersen R, et al. GRADE approach to drawing conclusions from a network meta-analysis using a partially contextualised framework. BMJ. 2018;360:k201.
- Bo K, Nygaard IE. There is not yet strong evidence that exercise regimens other than pelvic floor muscle training can reduce stress urinary incontinence in women: a systematic review. J Physiother. 2018;64(4):224-32.
- Dumoulin C, Cacciari LP, Hay-Smith EJC. Pelvic floor muscle training versus no treatment, or inactive control treatments, for urinary incontinence in women. Cochrane Database Syst Rev. 2018;10(10):CD005654.
- Conze T, et al. eHealth interventions for the treatment of urinary incontinence in women: a systematic review and meta-analysis. Mhealth. 2021;7:23.
- Loohuis AMM, et al. Effectiveness of a customized, app-based treatment for women with urinary incontinence: a randomized controlled trial. Ann Fam Med. 2021;19(5):411-9.
- Crawford A, Serhal E. Digital health equity and COVID-19: the innovation curve cannot rest on the vulnerability curve. J Med Internet Res. 2020;22(7):e19361.
- Xu P et al. The effectiveness of eHealth interventions on female pelvic floor dysfunction: a systematic review and meta-analysis. Int Urogynecol J. 2022;33(12):3325-54.
- Liang MY et al. The effect of digital health interventions in older adults with frailty: a systematic review and meta-analysis. Int J Nurs Stud Adv. 2026;10:100470.
- Tay T, et al. The impact of digitally-enabled interventions on frailty and other age-related outcomes: systematic review and meta-analysis. Digit Health. 2026;12:20552076251410997.
- Han HW, et al. E-health interventions for older adults with frailty: a systematic review. Ann Rehabil Med. 2023;47(5):348-57.
- Hui E, Lee PS, Woo J. Management of urinary incontinence in older women using videoconferencing versus conventional management: a randomized controlled trial. J Telemed Telecare. 2006;12(7):343-7.
- Weinstein MM, Dunivan G, Guaderrama NM, Richter HE. Digital therapeutic device for urinary incontinence: a randomized controlled trial. Obstet Gynecol. 2022;139(4):606-15.
- de Araujo CC, Brito LGO, Marques AA, Juliato CRT. Use of a mobile application for pelvic floor muscle training in women with urinary incontinence: a randomized controlled trial. Int Urogynecol J. 2024;35(3):589-98.
- Kijmanawat A, et al. Mobile application based pelvic floor muscle training for treatment of stress urinary incontinence: an assessor-blind randomized controlled trial. J Clin Med. 2023;12(22):7003.
- Araujo CC, Marques AA, Juliato CRT. The adherence of home pelvic floor muscle training using a mobile device application for women with urinary incontinence: a randomized controlled trial. Female Pelvic Med Reconstr Surg. 2020;26(11):697-703.