This protocol demonstrates a modified percutaneous endoscopic interlaminar discectomy using dual-channel assistance to achieve single-portal visualization with auxiliary bony decompression.
Методическая статья
Dual-Channel Percutaneous Endoscopic Interlaminar Discectomy with Auxiliary Bony Decompression
* These authors contributed equally
В этой статье
Краткое содержание
Аннотация
Percutaneous endoscopic interlaminar discectomy (PEID) is frequently limited by hypertrophic lamina and lateral recess stenosis that confine instrument maneuverability within a single working cannula. Unilateral biportal endoscopy (UBE) overcomes these anatomical constraints but requires dedicated arthroscopes, larger incisions, and a distinct learning curve. Here we describe a modified dual-channel PEID technique that preserves standard single-portal instrumentation while achieving biportal-like working freedom and expanded instrument access for bony decompression through dynamic, bidirectional interchangeability of a single endoscope-cannula assembly between two ipsilateral 7.5 mm portals. A secondary sleeve-free channel is established 1.5–2.0 cm cranial to the primary portal to facilitate aggressive laminotomy and medial facetectomy using conventional osteotomes and Kerrison rongeurs, while the primary portal maintains continuous endoscopic visualization. The endoscope-cannula assembly is reversibly transferred between portals to optimize viewing angles for sequential decompression of the lamina, ligamentum flavum, and superior articular process, followed by standard discectomy and neural decompression through the primary working channel. Quantitative computed tomography (CT) analysis in an index patient with L5/S1 disc herniation and ligamentum flavum hypertrophy demonstrated a bony decompression volume of 695.1 mm3, laminectomy thickness of 6.79 mm, and superior articular process undercutting of 13.70 mm. This technique bridges the capability gap between conventional PEID and UBE for patients with concomitant bony stenosis, achieving extensive lateral recess decompression without dedicated biportal equipment or additional specialized instrumentation.
Введение
Percutaneous endoscopic interlaminar discectomy (PEID) is widely used for posterior lumbar disc herniation. However, when confronted with hypertrophic lamina, ossified ligamentum flavum, or lateral recess stenosis, the rigid working cannula and limited trajectory often render conventional single-portal PEID technically demanding and insufficient for complete decompression1,2,3. Unilateral biportal endoscopy (UBE) addresses these limitations through separate viewing and working portals4,5,6, but requires specialized instrumentation, larger incisions, and a distinct learning curve7,8, limiting its adoption in centers equipped mainly for single-portal systems. Other hybrid strategies have pursued intermediate solutions. One-hole split endoscopy (OSE) separates the endoscope and instruments within a single incision, combining the working freedom of biportal surgery with a smaller incision and a shallow learning curve9. Arthroscopy-assisted uniportal spinal surgery (AUSS), also termed uni-portal non-coaxial endoscopic spine surgery, similarly accommodates an arthroscope and working instruments within one portal and permits free exchange between viewing and working trajectories10. In the cervical spine, hybrid techniques have combined a uniportal endoscope with a biportal working channel to gain an additional working corridor11. These approaches, however, either retain a rigid cannula around the working instruments (OSE and AUSS) or require a dedicated arthroscopic biportal platform (cervical hybrid), and none preserves a standard single-portal PEID instrument set throughout.
We describe a modified PEID technique employing a dual-channel strategy: the primary channel maintains endoscopic visualization and neural decompression, while a secondary ipsilateral channel enables efficient bony removal. This preserves familiar PEID instrumentation and avoids the need for a dedicated biportal platform or additional specialized equipment, while providing biportal-like working freedom for bony decompression. Technical nuances, patient positioning, and instrument coordination are detailed below; the procedural workflow is illustrated in Figure 1, and the rationale is summarized in the accompanying video for the surgical procedure. The novelty of this modification lies in the combination of three features that, to our knowledge, have not been previously described together: (i) dynamic, reversible transfer of a single endoscope-cannula assembly between two ipsilateral 7.5 mm portals, such that each portal alternates between viewing and working functions; (ii) a secondary sleeve-free channel that accepts conventional osteotomes and Kerrison rongeurs without a protective cannula; and (iii) preservation of standard single-portal PEID instrumentation without any arthroscopic or dedicated biportal equipment.
This technique is suitable for single-level lumbar disc herniation (L4-L5 or L5-S1) with concomitant bony stenosis, where conventional single-portal PEID may be insufficient. Key anatomical selection features that may favor this technique include ligamentum flavum hypertrophy (>4 mm on magnetic resonance imaging (MRI), normal typically ≤3.1 mm)12 and lateral recess stenosis (<4 mm)13, which typically reflects hypertrophy of the superior articular process14—descriptive criteria drawn from the literature rather than validated thresholds specific to this procedure. Caution is advised in patients with cauda equina syndrome, active infection, spondylolisthesis grade ≥ II with instability, prior ipsilateral laminectomy with extensive epidural fibrosis, uncorrected coagulopathy, isolated central canal stenosis requiring bilateral decompression, morbid obesity (BMI > 35 kg/m2), or multilevel pathology. The normative basis for these values is as follows: the 4-mm ligamentum flavum cut-off derives from normative MRI data in which the upper limit of normal is approximately 3.1 mm12, and the 4 mm lateral recess criterion reflects published quantitative radiologic thresholds in which recess heights of 3–4 mm are considered suggestive of stenosis14. Likewise, the BMI caution is an empirical safety boundary informed by meta-analytic evidence that obesity prolongs operative time and modestly increases recurrence risk after endoscopic lumbar surgery15, compounded by the added technical difficulty of endoscopic bony decompression through thickened soft tissue.
Протокол
All procedures described in this protocol were performed in compliance with the guidelines of the Human Research Ethics Committee of Shenzhen Nanshan People's Hospital and the Declaration of Helsinki. Written informed consent was obtained from all patients prior to surgery. The surgical instruments used for the procedure are shown in Figure 2.
1. Patient selection and preoperative planning
- Perform preoperative localization under fluoroscopic guidance. Place a locator needle to identify the skin projection of the maximal interlaminar space. Mark this projection as the Primary Portal entry point on the skin surface (Figure 3A).
- Place a second skin mark 1.5–2.0 cm cranially along the same sagittal trajectory to designate the Auxiliary Portal (Figure 3B).
- Adjust the C-arm to ensure the interlaminar space is maximally visualized and superimposed over the target disc space on the anteroposterior projection. Confirm the trajectory angle for both portals.
2. Anesthesia and patient positioning
- Administer general anesthesia with orotracheal intubation to ensure patient immobility during the endoscopic manipulation and bony decompression phases.
- Position the patient prone on a radiolucent operating table. Apply appropriate padding to relieve pressure on the chest and iliac crests.
- Maneuver the C-arm fluoroscopy unit to achieve coaxial alignment where the interlaminar space is superimposed over the target disc space on anteroposterior (AP) projection. Ensure the interlaminar window and the disc space are brought into the same radiographic plane.
NOTE: Extensive laminectomy to flatten the lamina is unnecessary for the posterior interlaminar approach. This radiographic confluence ensures a direct trajectory for subsequent instrument passage through the interlaminar window toward the herniated disc, minimizing the need for angular adjustments during endoscopic navigation.
3. Intraoperative localization
- Reconfirm the previously marked skin points under C-arm fluoroscopy following anesthesia, patient positioning, and sterile preparation.
- Insert an 18 G spinal needle at the Primary Portal entry site under fluoroscopic guidance. Target the maximal interlaminar space projection (Figure 3C,D).
- Confirm the trajectory on both AP views. Introduce a guide wire, followed by sequential dilation.
4. Primary portal establishment and initial dissection
- Perform sequential dilation using a four-grade dilation system to achieve a final working channel accommodating a working cannula of 7.5 mm outer diameter. Place and secure the dedicated working tube.
- Introduce the integrated single-portal endoscope (0° or 30°) through the Primary Portal.
- Perform systematic soft tissue dissection using bipolar radiofrequency probes and endoscopic forceps. Clear muscle, adipose tissue, and fascia until the dorsal surface of the lamina and the ventral aspect of the ligamentum flavum are clearly exposed (Figure 1B,C and Figure 4A).
NOTE: This exposure is critical because the Auxiliary Portal puncture is performed only after this bony surface has been adequately exposed under direct endoscopic visualization.
5. Auxiliary portal placement under endoscopic guidance
- Maintain the endoscope at the Primary Portal. Insert an 18 G spinal needle through the Auxiliary Portal skin mark.
- Advance the needle through the paraspinal musculature toward the previously exposed lamina surface under direct endoscopic visualization.
- Confirm endoscopic convergence when the needle tip enters the visual field and contacts the dorsal lamina at the junction of the hypertrophic bone and flavum (Figure 4B).
- Replace the needle with a guide wire following confirmation of convergence.
- Perform sequential dilation through the Auxiliary Portal using the same four-grade dilator set. Establish a channel of identical 7.5 mm caliber to the Primary Portal (Figure 4C).
6. Decompression protocol
- Maintain the endoscope-cannula assembly at either the Primary Portal or the Auxiliary Portal as dictated by the decompression target. Introduce an osteotome through the uncannulated opposite portal tract.
- Perform initial laminotomy via controlled mallet strikes. Target the caudal margin of the upper lamina or the cranial margin of the lower lamina, and the medial aspect of the superior articular process to address lateral recess stenosis (Figure 1D and Figure 4D).
NOTE: Before each advancement of the osteotome, confirm under direct endoscopic vision the ligamentum flavum–bone junction and the lateral margin of the dural sac, and never advance the instrument beyond the visualized field. Keep the osteotome parallel to the lamina and advance with short, controlled mallet strikes, limiting each bite to a few millimeters and never deeper than the visible cortical surface. Keep all bone resection medial to the medial margin of the facet joint and lateral to the lateral margin of the dural sac. - Enlarge the bone window using standard Kerrison rongeurs. Sequentially bite the hypertrophic lower lamina edge, thickened ligamentum flavum insertion, and overhanging medial facet to expand the lateral recess and release the main body of the flavum (Figure 4E).
- Transfer the endoscope-cannula assembly to the Auxiliary Portal. Convert the Primary Portal into a sleeve-free instrument conduit. Configuration: endoscope and working cannula at the Auxiliary Portal; sleeve-free instrument tract at the Primary Portal.
NOTE: While the assembly remains at the Auxiliary Portal, this mirror-image orientation provides a cephalad viewing angle for resection of the cranial laminar edge and proximal flavum insertion. Non-cannulated instruments advanced through the sleeve-free Primary Portal enable precise undercutting of the superior articular process from a caudal-to-cranial trajectory. - Return the endoscope-cannula assembly from the Auxiliary Portal to the Primary Portal, converting the Auxiliary Portal into a sleeve-free instrument conduit. Employ the endoscopic bone drill coaxially through the cannulated Primary Portal, sharing the cannula with the endoscope, to finely remove residual bony fragments and smooth sharp edges. Utilize Kerrison rongeurs advanced through the sleeve-free Auxiliary Portal tract to refine the decompression (Figure 4F). Configuration: endoscope, working cannula, and bone drill at the Primary Portal; sleeve-free instrument tract at the Auxiliary Portal.
NOTE: With the endoscope-cannula assembly back at the Primary Portal, coaxial drilling through the same cannula aligns the visual axis with the instrument trajectory, permitting controlled removal of residual fragments and smoothing of sharp bony edges under direct vision. Simultaneously, Kerrison rongeurs advanced through the sleeve-free Auxiliary Portal tract allow angled refinement of the decompression from the opposite side (Figure 4G). - Utilize pituitary forceps to grasp and extract detached or residual ligamentum flavum fragments through either portal under direct visualization. Remove, particularly, the thinner inner layers and free-floating fragments to ensure complete decompression of the lateral recess and epidural space.
- Observe the following bony decompression boundaries: limit resection to the cranial-caudal extent of ligamentum flavum insertion; stop lateral extension at the medial margin of the inferior articular process to preserve facet joint integrity16,17.
- Proceed with ventral decompression until dorsal flavum exposure and lateral recess patency are achieved.
- Undercut the hypertrophic superior articular process rather than resecting it en bloc to maintain posterior tension band integrity.
- Do not extend resection medially beyond the lateral margin of the dural sac to prevent epidural bleeding and postoperative fibrosis.
NOTE: The sleeve-free corridor reduces iatrogenic muscle compression and affords greater angulation freedom for bone-cutting tools. However, abandon the sleeve-free tract and complete the remaining bony work through a cannulated portal whenever the ligamentum flavum–bone interface or the lateral margin of the dural sac cannot be kept under continuous direct vision, or whenever epidural venous bleeding cannot be promptly controlled. Once the planned decompression boundaries are reached, discontinue further bone removal and proceed to neural decompression.
7. Neural decompression and discectomy
- Confirm completion by verifying free mobility of the traversing nerve root and restoration of epidural pulsation.
- Clear the operative field of bone debris with thorough irrigation. Secure hemostasis using bipolar radiofrequency probes.
- Meticulously resect the residual ligamentum flavum and epidural adipose tissue using endoscopic forceps and radiofrequency devices until the dural sac and traversing nerve root are adequately exposed.
- Leave the Auxiliary Portal open to vent irrigation fluid and maintain low intracanal pressure. During initial access, soft-tissue dissection, and laminotomy, maintain irrigation at a hydrostatic pressure of 30–50 cm H₂O; once the dural sac is exposed during extended sleeve-free decompression, reduce the pressure to 22–30 cm H₂O to limit fluid extravasation and intracanal pressure while preserving endoscopic visibility.
- Gently mobilize the dural sac medially using the endoscopic nerve dissector to delineate the cleavage plane between the neural elements and the posterior annulus.
- Rotate the beveled tip of the working cannula to gently retract the nerve root and dural sac medially, creating a stable operative corridor toward the disc space.
NOTE: Alternatively, employ the nerve dissector to sweep the nerve root dorsally and medially, ensuring continuous visualization of the neural structures throughout the discectomy phase. - Engage the herniated nucleus pulposus using pituitary forceps introduced through the Primary Portal. Approach from the shoulder region of the nerve root (Figure 1F and Figure 4H).
- Carefully grasp and remove the disc material in a piecemeal fashion.
- Open the posterior annulus using pituitary forceps if access to the disc space is required for additional decompression.
- Continue the discectomy until the nerve root is completely decompressed and demonstrates free mobility upon gentle probing.
- Transfer the endoscope-cannula assembly briefly from the Primary Portal to the Auxiliary Portal for a second-look survey from the opposite angle before closing.
NOTE: This alternative trajectory exposes any residual fragments concealed in the root axilla or shoulder and confirms lateral recess patency without repositioning the patient or disturbing the neural retractor.
Результаты
To evaluate the technical feasibility and quantitative decompression capability of the dual-channel modification, the procedure was performed in a 75-year-old female patient with left-sided L5/S1 disc herniation (paracentral to foraminal zone) complicated by ligamentum flavum hypertrophy. Preoperative clinical evaluation revealed a visual analog scale (VAS) score of 6/10 for radicular pain, a positive straight leg raising test at 40° on the left, and grade 4 strength of the left extensor hallucis longus (EHL). No significant sensory deficit was detected in the S1 dermatome (Table 1).
The total operative duration was 183 min (3 h 3 min), reflecting the initial learning curve for this technique. Intraoperative blood loss was minimal (10 mL). Hemodynamics remained stable throughout the procedure. Continuous irrigation was maintained by passive gravity-fed infusion of normal saline (0.9% NaCl) from a hung bag at a hydrostatic pressure of 30–50 cm H₂O and a flow rate of 150–250 mL/min. The 30–50 cm H₂O setting was used during initial access, soft-tissue dissection, and laminotomy, and the pressure was reduced to 22–30 cm H₂O during extended sleeve-free decompression after dural sac exposure. C-arm fluoroscopy was used for 3–5 cycles during the initial localization, needle confirmation, and working-cannula placement phases. Pre- and postoperative T2-weighted MRI findings are shown in Figure 5.
Pre- and postoperative 1 mm thin-slice CT scans (bone window) were imported into 3D Slicer software18,19(version 5.10.0). Rigid registration was performed using the SlicerElastix module 20(revision 507db19) with the "Rigid" registration preset (Figure 6E). Preoperative three-dimensional reconstruction localized the target surgical zone at the left L5/S1 interlaminar and lateral recess region (Figure 6A). Postoperative reconstruction demonstrated the decompression corridor created via the dual-channel strategy (Figure 6B). After registration, the bone windows of the target vertebra were aligned and compared slice by slice. On the preoperative series, the bony segment that was absent after surgery was manually delineated in the Segment Editor module to create the initial decompression mask. The mask was then overlaid onto the postoperative volume, and its boundaries were manually refined by direct visual comparison to obtain the final mask. Laminectomy thickness (6.790 mm) was defined as the maximal distance from the preoperative bone contour to the postoperative bone surface, measured on the axial slice at the level of maximal decompression (Figure 6C). The maximal undercutting depth of the superior articular process (13.70 mm) was measured using the same criterion at the corresponding maximal level (Figure 6D). Volumetric reconstruction was performed in the Segment Statistics module, and integration of the postoperative CT bone window with the segmented decompression mask yielded a total bony decompression volume of 695.1 mm3 (Figure 6F). These quantitative data demonstrate the amount and location of bone removed through the auxiliary channel, consistent with the achievement of lateral recess patency in this case.
Immediate postoperative assessment demonstrated prompt relief of radicular pain. On postoperative day 1, the VAS score decreased to 3/10, the straight leg raise test improved to 70° (negative), and the left EHL strength recovered to grade 4+. Clinical improvement was maintained at 3 month follow-up, including reductions in pain and disability scores and improvement in walking capacity (Supplementary Table S1). Detailed item-level ODI outcomes are provided in Supplementary Table S2.
Overall, the postoperative course was favorable. The patient experienced a transient symptomatic flare on postoperative day 2, consistent with a small, self-limited paravertebral hematoma with minimal intraspinal extension21. Given that the sleeve-free working tract lacks the tamponade effect of a cannula against cancellous bone, this event cannot be excluded as a technique-related risk and should not be regarded simply as an incidental complication of spinal endoscopy. Complete resolution was achieved conservatively within 3 days, without neurological deficit or need for surgical evacuation. No dural tear, nerve root injury, or surgical site infection occurred.
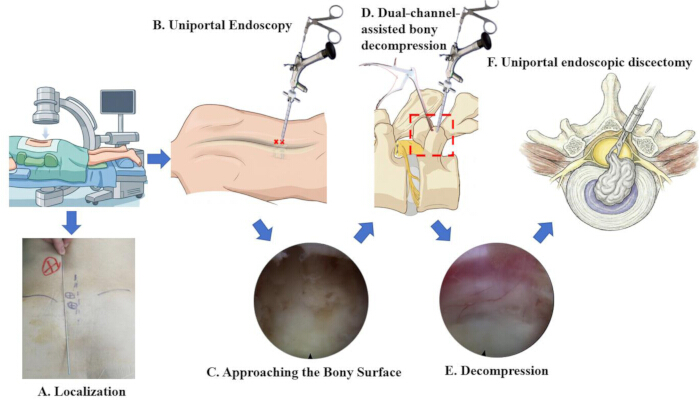
Figure 1. Procedural workflow of the dual-channel modified PEID technique. (A) Patient positioning and C-arm fluoroscopy. (B) Surface marking of the Primary and Auxiliary Portals. (C) Soft-tissue dissection and bony exposure via the Primary Portal. (D) Sleeve-free bony decompression through the Auxiliary Portal. (E) Decompression completed under dual-portal assistance (Auxiliary and Primary portals). (F) Uniportal discectomy via the Primary Portal. The procedural workflow is also demonstrated in the accompanying video. Abbreviation: PEID = percutaneous endoscopic interlaminar discectomy. Please click here to view a larger version of this figure.
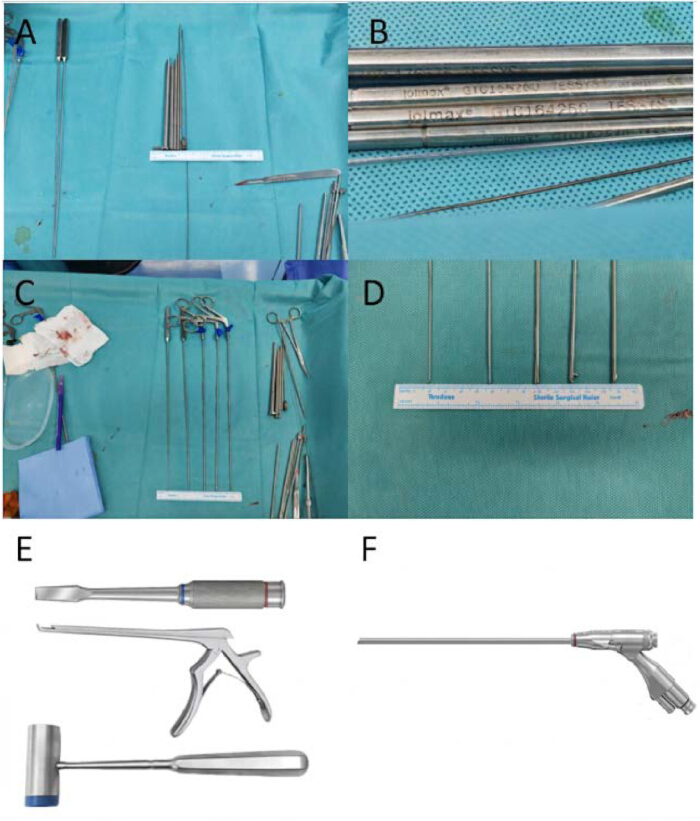
Figure 2. Surgical instrument configuration. (A) Initial access instruments: Nerve dissector, working cannula, serial dilators, 18 G spinal needle, and guide wire. (B) Working cannula and serial dilators. (C) Endoscopic instrument set. (D) Endoscopic instruments: nerve dissector, Endo-Kerrison rongeurs, pituitary forceps. (E) Standard bony instruments: osteotome, Kerrison rongeurs, surgical mallet. (F) Integrated endoscopic system with camera and light source. Please click here to view a larger version of this figure.

Figure 3. Preoperative localization and fluoroscopic confirmation. (A) C-arm AP view with locator needle at the maximal interlaminar space. (B) Skin markings: Primary Portal at the interlaminar projection; Auxiliary Portal 1.5–2.0 cm cranially. (C) Fluoroscopic confirmation of 18 G needle placement at the Primary Portal. (D) Post-dilation AP view confirming working cannula position. Abbreviation: AP = anteroposterior. Please click here to view a larger version of this figure.
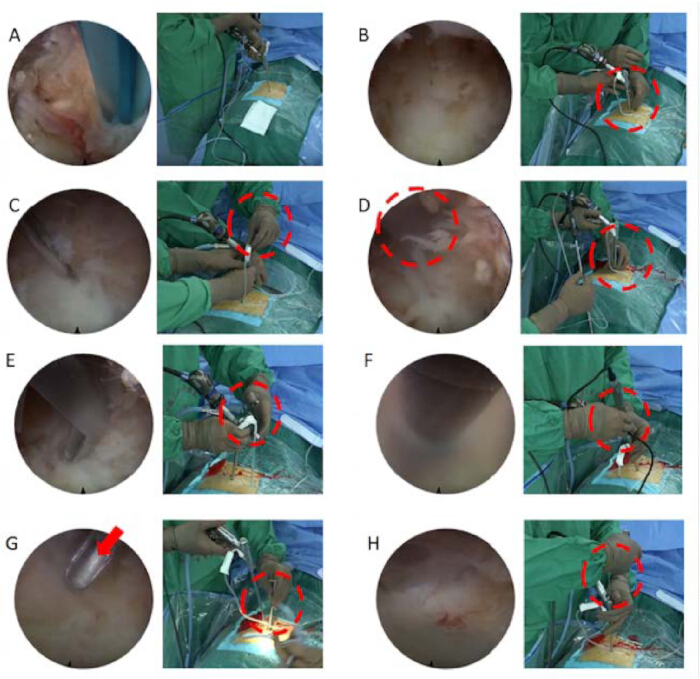
Figure 4. Intraoperative endoscopic and instrument views. (A) Soft-tissue dissection exposing the lamina and ligamentum flavum. (B) Auxiliary Portal needle converging onto the lamina. (C) Dilated Auxiliary Portal as instrument corridor. (D) Osteotome and mallet performing laminotomy. (E) Kerrison rongeurs enlarging the bony window. (F) Endoscopic bone drill refining decompression. (G) Mirror-image orientation from the Auxiliary Portal. (H) Pituitary forceps removing herniated disc material. Please click here to view a larger version of this figure.
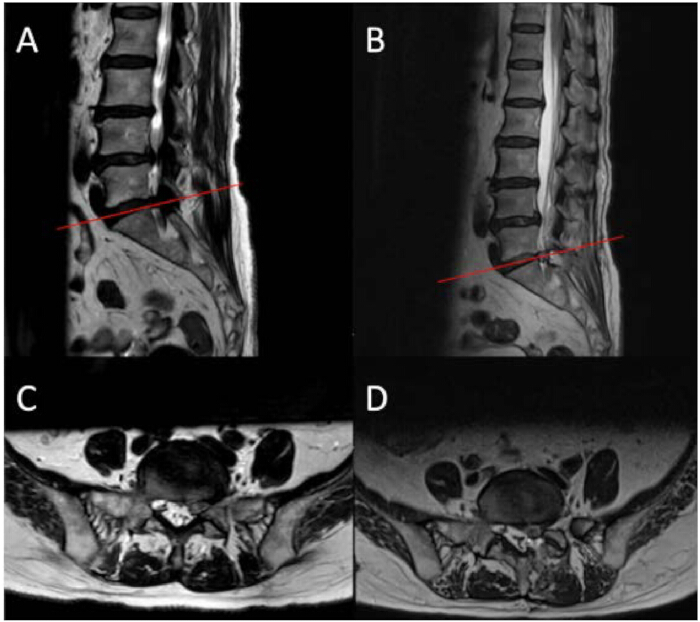
Figure 5. Pre- and postoperative T2-weighted MRI. (A) Preoperative sagittal image showing disc herniation (red line indicates axial level in C). (B) Postoperative sagittal image showing decompression and paravertebral hyperintense signal (red line indicates axial level in D). (C) Preoperative axial image showing left paracentral disc herniation with lateral recess compromise. (D) Postoperative axial image showing decompression corridor and intraspinal hyperintense signal. Abbreviation: MRI = magnetic resonance imaging. Please click here to view a larger version of this figure.
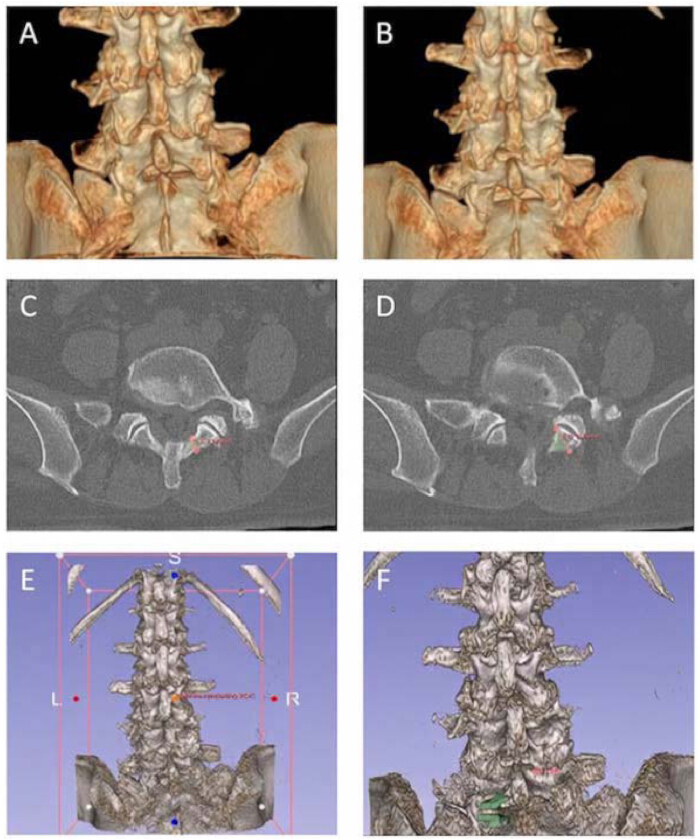
Figure 6. Quantitative bony decompression analysis via 3D Slicer. (A) Preoperative 3D CT: target surgical zone. (B) Postoperative 3D CT: decompression corridor. (C) Axial subtraction at maximal decompression level: laminectomy thickness 6.790 mm. (D) Axial subtraction at maximal undercutting level: superior articular process depth 13.70 mm. (E) Postoperative 3D CT following registration. (F) Volumetric reconstruction of decompression corridor. Abbreviations: 3D = three-dimensional; CT = computed tomography. Please click here to view a larger version of this figure.
| Category | Parameter | Value / Finding | ||
| Demographics | Age | 75 years | ||
| Sex | Female | |||
| ASA Physical Status | ASA II | |||
| Clinical Presentation | Chief Complaint | Progressive left-sided sciatica | ||
| Symptom Duration | 14 months | |||
| Prior Conservative Treatment | Refractory / Failed | |||
| Preoperative Assessment | VAS Score (Radicular Pain) | 6 | ||
| Straight Leg Raising Test | 40° (Left, Positive) | |||
| Motor Strength (Left EHL) | Grade 4 | |||
| Sensory Deficit (S1 Dermatome) | None detected | |||
| Radiological Diagnosis | Target Level | L5/S1 | ||
| Pathology | Left-sided lumbar disc herniation (paracentral to foraminal zone) | |||
| Surgical Parameters | Date of Surgery | 2025-03-26 | ||
| Anesthesia | General anesthesia with orotracheal intubation | |||
| Position | Prone | |||
| Operative Duration | 183 min (initial learning-curve case) | |||
| Estimated Blood Loss | 10 mL | |||
| Irrigation Pressure | 30–50 cm H₂O during initial access/soft-tissue dissection/laminotomy, then 22–30 cm H₂O after dural-sac exposure during extended sleeve-free decompression | |||
| Irrigation Flow Rate | 150-250 mL/min | |||
| C-arm Fluoroscopy Cycles | 3-5 cycles | |||
| Postoperative Course (POD 1) | VAS Score | 3 | ||
| Straight Leg Raising Test | 70° (Left, Negative) | |||
| Motor Strength (Left EHL) | Grade 4+ | |||
| Complication (POD 2) | Event | Transient symptomatic flare (lower extremity soreness and distending pain) | ||
| VAS Score | 5 | |||
| Imaging Finding | Paravertebral hematoma with minimal intraspinal extension (T2/STIR hyperintense) | |||
| Management | Conservative (analgesia + neurological monitoring) | |||
| Outcome | Spontaneous resolution without surgical evacuation | |||
| Discharge (POD 8) | Date | 2025-04-03 | ||
| VAS Score | 3 | |||
| Neurological Status | Intact, no motor deficit | |||
| Complications | No dural tear, nerve root injury, or infection | |||
Table 1: Patient demographics, clinical characteristics, and perioperative data. Abbreviations: ASA = American Society of Anesthesiologists; VAS = visual analog scale; EHL = extensor hallucis longus; POD = postoperative day; STIR = short tau inversion recovery.
Supplementary Table S1. Comparison of preoperative, early postoperative, and 3-month follow-up outcomes. Abbreviations: VAS = visual analog scale; POD = postoperative day; ODI = Oswestry Disability Index; SLR = straight leg raise; EHL = extensor hallucis longus; N = not assessed at the corresponding time point.Please click here to download this file.
Supplementary Table S2. Item-level Oswestry Disability Index scores. Abbreviation: ODI = Oswestry Disability Index.Please click here to download this file.
Обсуждение
Conventional PEID confines all instruments within a single working cannula, making aggressive bony decompression impractical when hypertrophic lamina or lateral recess stenosis narrows the interlaminar corridor1,2. The present modification establishes a secondary sleeve-free channel while preserving standard PEID instrumentation; a single endoscope-cannula assembly is dynamically interchanged between two ipsilateral 7.5 mm portals to optimize visualization and instrument trajectory. Conceptually, this approach mirrors hybrid dual-channel strategies previously described in cervical spine surgery, where the integration of uniportal endoscopic visualization with biportal-style working channels achieved satisfactory decompression while preserving the benefits of both platforms11. This design differs in several respects from previously described hybrid strategies. One-hole split endoscopy9 separates the endoscope from the instruments within a single incision, but the working trajectory remains constrained by a rigid split cannula and OSE-specific powered instrumentation. Arthroscopy-assisted uniportal spinal surgery10 consolidates viewing and working within one non-coaxial portal, yet requires a dedicated arthroscope, a larger fascial incision, and an arthroscope that is not interchangeable with the working cannula as a unit. The cervical hybrid technique11 adds a uniportal endoscope to a biportal setup but depends on a full biportal arthroscopic platform. In contrast, the present technique uses two independent percutaneous portals, interchanges the entire endoscope-cannula assembly between them to obtain opposing viewing angles, and performs aggressive bony removal through a sleeve-free channel using the osteotomes and Kerrison rongeurs already available in a standard PEID set.
This design achieves multiplanar bony removal with biportal-like working freedom4,5, potentially offering an alternative for patients who would otherwise require conversion to open or biportal surgery22. Continuous coaxial access to the endoscopic drill and pituitary forceps via interchangeable portals enables instrument synergy not explicitly available in fixed-portal systems. Postoperative CT volumetrics (695.1 mm3 decompression volume, 6.79 mm laminectomy thickness) quantify the extent of bony removal achieved through the auxiliary corridor and illustrate lateral recess patency in this index case. The 183 min operative duration reflects initial spatial recalibration during the learning curve of this first case; operative time may decrease with experience, although this requires confirmation in a consecutive case series. Fluoroscopy demand (3–5 cycles) remains comparable to conventional PEID because auxiliary portal placement is guided endoscopically rather than radiographically. In comparative series, techniques of the biportal family (AUSS, OSE) have shown favorable decompression efficiency relative to fixed-cannula uniportal systems, albeit generally through larger incisions9,10. A recent systematic review likewise concluded that biportal approaches offer superior dural sac expansion and instrument maneuverability, whereas uniportal techniques reduce operative time and blood loss23. The present modification attempts to capture the decompression freedom of the biportal family while retaining the instrumentation, irrigation management, and 7.5 mm portal diameter of conventional PEID.
Three specific hazards require attention. First, the sleeve-free auxiliary portal sacrifices the tamponade effect of a working cannula against cancellous bone and the epidural venous plexus, predisposing to postoperative paravertebral hematoma with minimal intraspinal extension in elderly patients with hypertrophic bone21. We encountered this complication in the index patient as a transient symptomatic flare on postoperative day 2; it resolved completely within 3 days with conservative management and without neurological deficit or need for surgical evacuation, but we consider it a technique-specific cautionary point rather than a minor complication of spinal endoscopy. Probable contributing mechanisms include persistent oozing from osteotome-impact cancellous bone across a sleeve-free tract, the two portal tracts doubling potential bleeding channels, and transient loss of direct visual control of the tract walls each time the endoscope-cannula assembly is transferred to the opposite portal. Meticulous bipolar hemostasis, reduced irrigation pressure to 22–30 cm H2O during extended decompression21, and postoperative negative-pressure drainage until 24 h output falls below 50 mL24 are recommended. Bone wax application to exposed cancellous surfaces may be considered as an adjunct when cancellous oozing persists, as supported by previous spinal surgery literature25. If the bailout triggers (sleeve-free) stated above are met—loss of continuous vision of the ligamentum flavum–bone interface or the dural sac margin, or uncontrollable epidural venous bleeding—the surgeon should abandon the sleeve-free tract and complete the remaining work through the cannulated portal before closing, and inspect both portal tracts for bleeding under endoscopic vision after hemostasis. Neurological status should be monitored during the first 48 h postoperatively, and any new deficit should prompt urgent MRI.
This proof-of-concept report is inherently limited by its single-case design. The quantitative metrics and indication thresholds require prospective validation in a comparative cohort. Enrollment of a consecutive series is underway to define the learning-curve plateau, refine patient selection, and compare perioperative parameters with matched controls undergoing conventional PEID or UBE. Long-term follow-up will determine whether the observed decompression volume correlates with sustained lateral recess patency and prevention of restenosis.
This modified dual-channel strategy bridges the capability gap between conventional PEID and UBE for selected patients with concomitant bony stenosis, achieving extensive lateral recess decompression without dedicated biportal instrumentation or additional specialized equipment. Prospective validation is required to confirm its safety profile and long-term clinical efficacy.
Раскрытие информации
The authors have no conflicts of interest to declare.
Благодарности
This work was supported by the Major Science and Technology Project of the Shenzhen Health System (Grant No. NSZD2025015), the Gansu Provincial Natural Science Foundation (Grant No. 24JRRF008), the Jiuquan City Science and Technology Program Project (Grant No. 2026MB1010), and the Guangdong Basic and Applied Basic Research Foundation (Grant No. 2026A1515011835).
Материалы
| Имя | Компания | Каталожный номер | Комментарии |
|---|---|---|---|
| 3D Slicer, version 5.10.0 | 3D Slicer / Brigham and Women's Hospital | N/A | Open-source image computing platform (slicer.org); used for CT registration, segmentation, and volumetric analysis |
| Bipolar radiofrequency probe | joimax | JVP32024 | Vaporflex bipolar probe (ball tip), WL 320 mm / OD 2.4 mm; for hemostasis and soft-tissue coagulation; used with the Endovapor®2 generator |
| C-arm fluoroscopy system | Ziehm Imaging | N/A | Mobile C-arm fluoroscopy system (Ziehm Vision RFD) for intraoperative AP and lateral X-ray imaging |
| Endo-Kerrison rongeurs, shaft 40° (pistol handle) | joimax | EKS32351540 | For bony decompression under endoscopic visualization via the working cannula |
| Endoscope, single-portal (0°/30°), with integrated endoscopic system (SpineTIP) | Karl Storz SE & Co. KG, Tuttlingen, Germany | 28163 FKD | Includes camera and light source (Figure 2F); camera platform of the IMAGE1 S series; working sheath 28163 FKD |
| Endoscopic bone drill | joimax | DCC114021 | Side-cutting drill (over-the-wire); for fine bony removal and edge smoothing |
| Guide wire, beveled tip | joimax | TGWS50018 | Superelastic, beveled tip, L 500 mm / OD 1.8 mm; stiff shaft for sequential dilation guidance |
| Guiding tube, 1st grade | joimax | GTC232838 | Length 231.5 mm, inner diameter 2.8 mm, outer diameter 3.8 mm |
| Guiding tube, 2nd grade | joimax | GTC182840 | Length 180 mm, inner diameter 2.8 mm, outer diameter 4.0 mm |
| Guiding tube, 3rd grade | joimax | GTC164250 | Length 165 mm, inner diameter 4.2 mm, outer diameter 5.0 mm |
| Guiding tube, 4th grade | joimax | GTC155260 | Length 155 mm, inner diameter 5.2 mm, outer diameter 6.0 mm |
| Infusion set, sterile | N/A | N/A | Standard sterile infusion set for gravity-fed saline irrigation (generic item) |
| Negative-pressure drainage system | N/A (no commercial device) | N/A | Improvised closed drainage assembled from standard sterile disposables (drainage tube connected to a sterile collection bag); negative pressure maintained by keeping the collection bag below the surgical field (siphon effect); removed when 24-h output falls below 50 mL (Discussion) |
| Nerve dissector (joimax TESSYS) | joimax | TEFP32020 | Used for initial access (Figure 2A) and for delineating the cleavage plane between the neural elements and the annulus; gently mobilizes and retracts the dural sac and nerve root (Protocol 7.5 and NOTE after 7.5) |
| Normal saline, 0.9% (NaCl) | N/A | N/A | Irrigation fluid; standard pharmaceutical-grade 0.9% NaCl from any manufacturer |
| Osteotome | N/A | N/A | For sleeve-free bony decompression via the Auxiliary Portal; generic/standard instrument with no specific catalog number — any equivalent model of the same specification can be used |
| Pituitary forceps, angled | joimax | THF322041 | Spoon-shaped, 45° curved, 320 mm; for nucleus pulposus removal and soft-tissue dissection (Protocol 4.3, 7.3) |
| Pituitary forceps, straight | joimax | THF322541 | Straight spoon-shaped, 2.5 mm × 320 mm; for nucleus pulposus removal and soft-tissue dissection (Protocol 4.3, 7.3) |
| SlicerElastix module (revision 507db19) | 3D Slicer Extensions (elastix) | N/A | Rigid registration of pre- and postoperative CT ("Rigid" preset) |
| Spinal needle, 18 G | N/A | N/A | For initial percutaneous localization and portal placement; generic/standard instrument with no specific catalog number — any equivalent model of the same specification can be used |
| Standard Kerrison rongeurs | N/A | N/A | For sleeve-free bony decompression via the Auxiliary Portal; generic/standard instrument with no specific catalog number — any equivalent model of the same specification can be used |
| Surgical mallet | N/A | N/A | For controlled osteotome strikes during laminotomy; generic/standard instrument with no specific catalog number — any equivalent model of the same specification can be used |
| Working cannula | joimax | WTS176575 | Length 170 mm, inner diameter 6.5 mm, outer diameter 7.5 mm; final operative channel |
Ссылки
- Gunjotikar S, et al. Evolution, current trends, and latest advances of endoscopic spine surgery. J Clin Med. 2024;13(11):3143.
- Ding Y, et al. Finite element analysis of endoscopic cross-overtop decompression for single-segment lumbar spinal stenosis based on real clinical cases. Front Bioeng Biotechnol. 2024;12:1393005.
- Liu J, et al. Comparison of clinical efficacy between percutaneous endoscopic large channels nerve decompression through translaminar approach and percutaneous endoscopy conventional channels nerve decompression through transforaminal approach for the treatment of degenerative L4/5 spinal stenosis: a retrospective study. BMC Musculoskelet Disord. 2025;26(1):493.
- Zuo R, et al. The clinical efficacy of biportal endoscopy is comparable to that of uniportal endoscopy via the interlaminar approach for the treatment of L5/S1 lumbar disc herniation. Front Surg. 2022;9:1014033.
- Sun W, et al. Efficacy and safety of unilateral biportal endoscopy compared with transforaminal route percutaneous endoscopic lumbar decompression in the treatment of lumbar spinal stenosis: minimum 1-year follow-up. J Pain Res. 2025;18:1071-80.
- Park DK, Weng C, Zakko P, Choi DJ. Unilateral biportal endoscopy for lumbar spinal stenosis and lumbar disc herniation. JBJS Essent Surg Tech. 2023;13(2):e22.00020.
- Chen L, et al. The learning curve of unilateral biportal endoscopic (UBE) spinal surgery by CUSUM analysis. Front Surg. 2022;9:873691.
- Zhou S, et al. Comparison of short-term clinical outcomes and muscle injury in patients with lumbar spinal stenosis undergoing arthroscopic-assisted uni-portal spinal surgery, unilateral biportal endoscopic surgery, and percutaneous interlaminar lumbar discectomy: a six-month follow-up. J Orthop Surg Res. 2025;20(1):684.
- Tan F, et al. Analysis of effectiveness of one-hole split endoscopy technique in treatment of lumbar spinal stenosis. Zhongguo Xiu Fu Chong Jian Wai Ke Za Zhi. 2024;38(3):337-42.
- Zhang H, et al. Clinical efficacy and safety of arthroscopic-assisted uniportal spinal surgery versus percutaneous endoscopic lumbar decompression in lumbar spinal stenosis: a retrospective study. Orthop Surg. 2026;18(2):261-9.
- Yan M, et al. Comparison of clinical efficacies between three endoscopic surgeries in treating cervical spondylopathy. Chin J Spine Spinal Cord. 2023;33(7):610-8.
- Chokshi FH, Quencer RM, Smoker WR. The "thickened" ligamentum flavum: is it buckling or enlargement? AJNR Am J Neuroradiol. 2010;31(10):1813-6.
- Steurer J, et al. Quantitative radiologic criteria for the diagnosis of lumbar spinal stenosis: a systematic literature review. BMC Musculoskelet Disord. 2011;12:175.
- An SJ, et al. Facet joint hypertrophy is a misnomer: a retrospective study. Medicine (Baltimore). 2018;97(24):e11090.
- Wangthawil W, et al. Endoscopic spine surgery for obesity-related surgical challenges: a systematic review and meta-analysis of current evidence. Asian Spine J. 2026;20(2):202-10.
- Li T, et al. The effect of more than 50% resection of the inferior articular process on spinal stability in unilateral single-segment interlaminar endoscopic lumbar discectomy. Global Spine J. 2026:21925682261446557.
- Pao JL. A review of unilateral biportal endoscopic decompression for degenerative lumbar canal stenosis. Int J Spine Surg. 2021;15(Suppl 3):S65-71.
- Fedorov A, et al. 3D Slicer as an image computing platform for the Quantitative Imaging Network. Magn Reson Imaging. 2012;30(9):1323-41.
- Chen X, et al. Development of a surgical navigation system based on 3D Slicer for intraoperative implant placement surgery. Med Eng Phys. 2017;41:81-9.
- Klein S, et al. elastix: a toolbox for intensity-based medical image registration. IEEE Trans Med Imaging. 2010;29(1):196-205.
- Kim JE, Choi DJ, Park EJ. Evaluation of postoperative spinal epidural hematoma after biportal endoscopic spine surgery for single-level lumbar spinal stenosis: clinical and magnetic resonance imaging study. World Neurosurg. 2019;126:e786-92.
- Qu X, et al. Efficacy of endoscopic interlaminar decompression in lumbar spinal stenosis: a retrospective study. Sci Rep. 2024;14(1):26956.
- Jitpakdee K, et al. Minimally invasive endoscopy in spine surgery: where are we now? Eur Spine J. 2023;32(9):2755-68.
- Cui P, et al. Advancing the timing of drainage removal: a comprehensive analysis of different drainage removal criteria in patients undergoing short-level lumbar fusion surgery. BMC Surg. 2024;24(1):422.
- Kim JG, et al. Evaluating the efficacy of water-soluble bone wax (Tableau Wax) in reducing blood loss in spinal fusion surgery: a randomized, controlled, pilot study. Medicina (Kaunas). 2023;59(9):1644.
Перепечатки и разрешения
