Acute brain trauma is a severe injury that has no adequate treatment to date. Multiphoton microscopy allows studying longitudinally the process of acute brain trauma development and probing therapeutical strategies in rodents. Two models of acute brain trauma studied with in vivo two-photon imaging of brain are demonstrated in this protocol.
Method Article
Acute Brain Trauma in Mice Followed By Longitudinal Two-photon Imaging
In This Article
Summary
Abstract
Although acute brain trauma often results from head damage in different accidents and affects a substantial fraction of the population, there is no effective treatment for it yet. Limitations of currently used animal models impede understanding of the pathology mechanism. Multiphoton microscopy allows studying cells and tissues within intact animal brains longitudinally under physiological and pathological conditions. Here, we describe two models of acute brain injury studied by means of two-photon imaging of brain cell behavior under posttraumatic conditions. A selected brain region is injured with a sharp needle to produce a trauma of a controlled width and depth in the brain parenchyma. Our method uses stereotaxic prick with a syringe needle, which can be combined with simultaneous drug application. We propose that this method can be used as an advanced tool to study cellular mechanisms of pathophysiological consequences of acute trauma in mammalian brain in vivo. In this video, we combine acute brain injury with two preparations: cranial window and skull thinning. We also discuss advantages and limitations of both preparations for multisession imaging of brain regeneration after trauma.
Introduction
Acute brain injury is a significant public health problem with high incidence of injury in motor vehicle crashes, falls or assaults, and high prevalence of subsequent chronic disability. Therapeutic approaches to the treatment of brain injury remain totally symptomatic, thus limiting the effectiveness of prehospital, surgical and critical care. This makes the social and economic impact of brain injury particularly severe. For a variety of reasons, most of the clinical trials failed to demonstrate improvement in recovery after brain injury using novel therapeutic approaches.
Animal models are crucial for developing new therapeutic strategies towards a stage where drug efficacy can be predicted in patients with brain injuries. At present, several well established animal models of head trauma exist, including controlled cortical impact1, fluid percussion injury2, dynamic cortical deformation3, weight-drop4, and photo injury5. A number of experimental models have been used to study certain morphological, molecular and behavioral aspects of head trauma-associated pathology. However, no single animal model is entirely successful in validating new therapeutic strategies. Development of reliable, reproducible and controlled animal models of brain injury is necessary to assess the complex pathological processes.
The novel combination of the latest microscopic imaging technologies and genetically-encoded fluorescent reporters offers an unprecedented opportunity to investigate all phases of brain injury, which include primary injury, spreading of the primary injury, secondary injury, and regeneration. In particular, in vivo two-photon microscopy is a unique nonlinear optical technology that allows real-time visualization of cellular and even subcellular structures in deep cortical layers of rodent brain. Several types of cells and organelles can be imaged simultaneously by combining different fluorescent markers. Using this powerful tool, we can visualize dynamic morphological and functional changes in living brain under posttraumatic conditions. The advantages of in vivo two-photon microscopy in studying brain injury were recently demonstrated by Kirov and colleagues6. Using a mild focal cortical contusion model, these authors showed that acute dendritic injury in the pericontusional cortex is gated by the decline in the local blood flow. Moreover, they demonstrated that the metabolically compromised cortex around the contusion site is further damaged by the spreading depolarization. This secondary damage affects synaptic circuitry, making the consequences of traumatic brain injury more severe.
Here, we propose the method of stereotaxic prick with a syringe needle, which could be combined with simultaneous topical drug application, as an advanced model for local brain injury and as a tool to study pathophysiological consequences of acute trauma in mammalian brain in vivo.
Protocol
All the procedures presented here were performed according to local guidance for animal care (The Finnish Act on Animal Experimentation 62/2006). Animal license (ESAVI/2857/04.10.03/2012) was obtained from local authority (ELÄINKOELAUTAKUNTA-ELLA). Adult mice of 1-3 months age, weight 24-38 g, were kept in individual cages in the certified University’s animal facility and provided with food and water ad libitum.
1. Brain Injury Imaging Through a Cranial Window
- Anesthetizing animals and preparing the operation field
- Anesthetize mice by peritoneal injection of a mixture of ketamine (Ketalar, 80 mg/kg) and xylazine (Rompun, 10 mg/kg) dissolved in filter-sterilized phosphate buffer saline (PBS), pH 7.4. Check the mouse’s reflexes regularly (tail and toe pinch probe) to verify the depth of anesthesia. Increase the dose when appropriate, to maintain proper anesthesia but avoid overdose.
- Maintain the animal at 37.0 °C using a heating pad during surgical operation, imaging session and first hour after recovery from anesthesia.
- To protect the mouse’s eyes from drying out, apply eye lubricant.
- Administer dexamethasone (Rapidexon vet, 2 mg/kg) by subcutaneous injection to reduce inflammation and cerebral edema.
- Administer an analgesic (for instance, Ketoprophene intraperitoneally) up to 30 min prior to or immediately after the surgery. If the animal exhibits any pain symptoms, such as reluctance to move, eat or drink, or weight loss, salivation, piloerection, or abnormal respiratory sounds after surgery, repeat the injection of analgesic.
- Shave the mouse’ head with a shaving machine (see Materials and Equipment). Avoid damaging the whiskers.
- Treat the skin on the mouse’s head with 70% ethanol solution to clean the shaved area.
- Using surgical scissors (see Materials and Equipment) and forceps (see Materials and Equipment), cut the skin from the middle line between ears to the forehead.
- Gently scrape away the connective tissue attached to the skull with a blunt microsurgical blade.
- Slide skin borders sideways and pull ear bars slightly into aural orifices of the skull for head and skin fixation.
- Clean the skull with sterile PBS and treat the surgery site on the mouse’s head with 0.5% chlorhexidine digluconate, then dry the skull surface using a combination of sterile cotton swabs and compressed air.
- Infliction of the prick injury
- Position a small animal stereotaxic instrument with an animal holder (see Materials and Equipment).
- Adjust the position of the binocular microscope next to the stereotaxic instrument to focus on the surface of the animal’s skull.
- Using a binocular microscope, locate the bregma point on the skull.
- Identify the region of interest using the stereotaxic coordinates.
NOTE: Avoid those areas of interest that are directly located over superficial cortical vessels. Destruction of these can strongly affect the trauma progression. - Position the 30 G needle above the chosen region and mark the target site by scratching the skull surface.
- Drill the skull with all possible precautions to avoid unnecessary widening of the affected bone surface area. Use a high speed surgical drill (see Materials and Equipment) under the microscope. Stop drilling if liquid appears in the drilled area.
- Touch the bottom of the drilled well with the needle.
- Dip the needle smoothly into the brain (insertion rate 5-10 mm/min), to the depth of 0.5-2.0 mm according to the coordinates of the prick application site.
- Remove the needle immediately after reaching the desired depth (retraction rate 5-10 mm/min) and wipe the blood appearing after the prick with a small tampon (see Materials and equipment).
- Perform microinjection of 100 µM Sulforhodamine 101 or another compound of interest into the lesion site using a microsyringe pump (WPI) and 10 µl Hamilton syringe assemble with glass pipette.
NOTE: During preparation of the glass pipette from borosilicate glass capillary, sharpen the tip to a diameter of 10-20 µm. - Infuse 250-1,500 nl of the injection solution at the rate of 2-5 nl/sec.
NOTE: Leave the pipette after the end of infusion for at least 5 min in brain parenchyma, then remove it slowly and gently to prevent solution outflow.
- Craniotomy for chronic cranial window
- Drill the skull gently and carefully to make a circle window around the injury site. Use window diameter of 3-3.5 mm.
- Apply a drop of cortex buffer (125 mM NaCl, 5 mM KCl, 10 mM glucose, 10 mM HEPES, 2 mM CaCl2 and 2 mM MgSO4 in distilled H2O) to cover the window.
- Position a round glass coverslip (#1.5 thickness) on the cranial window.
- Remove the excess of cortex buffer around the coverslip.
- Seal the edges of the coverslip with polyacrylic glue (see Materials and Equipment).
NOTE: Ensure that the glue is not applied to the upper surface of the coverslip. If the cover glass is contaminated with glue, wait until the glass is stably glued to the skull and the glue on the glass surface gets dry, then carefully remove the contaminating glue with a microblade. - Wait for 5 min to let the glue dry up.
- Using the ear bar height screws, adjust the head position so that the metal holder can be placed.
- Apply a small amount of polyacrylic glue on the ring of the steel holder (see Materials and Equipment).
- Glue the ring of the steel holder to the glass coverslip with the metal holder handle directed backwards.
- Wait for 5 min to let the glue dry up.
- Mix dental cement (see Materials and equipment) with polyacrylic glue in a 3.5 cm Petri dish (or analogue) to achieve viscous conditions.
- Seal the borders of the cranial window with the cement + glue mixture and cover the exposed surface of the skull with the same mixture up to the skin border.
- Wait for 15 min to let the cement + glue mixture dry up and then remove ear bars.
- Perform two-photon excitation microscopic (TPEM) imaging for the region of interest and a control area as it described in Protocol 3.
- After imaging, allow the animal to recover from anesthesia on a heating pad and keep it in an individual cage under observation until full recovery. Wet food can be given to facilitate chewing and hydration.
2. Brain Injury Imaging Through the Thinned Skull
- Anaesthetizing animals and preparing the operation field
- Anesthetize the mouse and prepare it for trauma induction as described in step 1.1.
- Skull thinning and infliction of the prick injury
- Position a small animal stereotaxic instrument with the animal holder (see Materials and equipment).
- Adjust the position of a binocular microscope next to the stereotaxic instrument to focus on the animal skull surface.
- Locate the bregma point on the skull using the binocular microscope, identify the brain area to be imaged based on stereotactic coordinates and mark it by scratching.
NOTE: Skull thinning position should not be located over or nearby cranial sutures, as the skull stability is compromised in those areas. Furthermore, large cortical or meningeal vessels and meninges located below the skull sutures are likely to cause imaging artifacts. - Place the metal holder coated with glue over the area of interest on the animal's skull, apply light pressure and wait for 5 min until the metal holder is firmly glued to the skull.
- Mix dental cement (see Materials and equipment) with polyacrylic glue in a 3.5 cm Petri dish (or analogue) to achieve viscous conditions.
- Seal the borders of the metal holder with the cement + glue mixture and cover the exposed surface of the skull with the same mixture up to the skin border.
- Wait for 15 min to let the cement and glue mixture dry up.
- Rinse the thinned skull region and the surrounding parts of the metal holder several times with PBS, so that the remnants of nonpolymerized glue are washed away.
NOTE: It is crucial to ensure stable attachment of skull to the holder. This enables the preparation stability during imaging. - Using the high magnification mode of the binocular microscope, remove upper layers of the skull bone with a high-speed micro-drill to create a thinned skull area of ~0.5–1.5 mm in diameter. Use compressed air during drilling to remove the bone debris. Perform the drilling intermittently during the thinning procedure in order to avoid friction-induced overheating. Cool the drill bit using the room temperature solution and periodically apply buffer to the thinned area to absorb heat.
NOTE: To avoid damaging the cortex, do not drill over large regions (>1.5 mm) down to a thin layer (<50 μm).
NOTE: The rodent skull bone structure consists of two thin layers of compact bone separated by a thick layer of spongy bone. Tiny cavities of the spongy bone form concentric circles and canaliculi, which contain blood vessels. Use the microdrill to remove both the external compact bone layer and most of the spongy layer. Disruption of the blood vessels within the spongy bone may cause bleeding. Use hemostasis collagen sponge to stop this bleeding. - Use second-harmonic generation (SHG) imaging to examine whether the majority of the spongy bone has been removed. Be careful to avoid excessive thinning, make sure that the remaining bone is thicker than 50 µm at this stage of the preparation.
- Put a drop of warm buffer (35-37 °C) on top of the thinned region. Use a microsurgical blade or Micro Finishing Bur to further remove bone layers and form a smooth area of ~700 µm in diameter with bone thickness of ~20 µm. During this step, it is helpful to perform repetitive SHG imaging and measure regularly the bone thickness.
- Perform TPEM imaging for the region of interest and a control area.
- Adjust the head position using the ear bar height screws in such a way that thinned region is positioned strictly horizontally. Position the needle above the thinned region and make sure that there are no large vessels beneath the targeted site.
- Make a lesion by dipping the needle into the brain, to the depth of 0.5-2.0 mm from thinned skull surface and according to the coordinates of the prick application site.
- Remove the needle and suppress hemorrhage appearing after the acute brain injury with hemostatic tampon (see Materials and equipment). Wait until blood clots form and vessel pulsation at the injury site stops.
- Perform microinjection of 100 µM Sulforhodamine 101 or another compound of interest into the lesion site, as described above in section 1.2.10.
- Perform TPEM imaging to monitor the injury progression and recovery as described in Protocol 3.
- After imaging, allow the animal to regain consciousness from anesthesia on a heating pad. Do not leave the animal unattended and return it to its home cage only after full physical recovery.
3. Imaging
- Place the animal under the microscope by attaching the metal holder to the custom built frame.
- For imaging, use e.g. the FV1000MPE two-photon microscope equipped with Mai Tai DeepSee laser and XLPLN 25X 1.05 NA water immersion objective optimized for in vivo two-photon imaging.
- Identify the lesion site under the microscope using wide-field fluorescence mode. Use long pass filters to visualize brain vasculature and select the control area according to the observed pattern of blood vessels.
- To image the second harmonic generation (SHG) signal, tune the femtosecond laser to the 800 nm wavelength and collect the emitted light using the 380-410 nm bypass filter. For fluorescence imaging, use the band pass filter (515-560 nm) to collect emitted light, and the following wavelengths are used to excite the fluorescence: GFP- 860 nm, YFP- 950 nm.
- Use Fluoview software for image acquisition.
- Store coordinates of every ROI for subsequent repetitive imaging. Image the same ROIs over time, and adjust coordinates every time to maximize the image overlap.
- Analyze images with the appropriate software (e.g. ImageJ). Reconstructions presented here were done using Imaris software.
Results
We have optimized two operation procedures: 1) chronic cranial window and 2) skull thinning, for posttraumatic brain imaging in transgenic mice. Schematic view of the experimental preparations is presented in Figure 1. Traumatic prick by steel needle of 0.3 mm OD (30 G) is applied to the drilled well (Figure 1A). A successful cranial window preparation allows imaging at depths up to 650 μm below the pial surface (Figure 1B), whereas skull thinning tends to impose a limit of approximately 300 μm (Figure 1C), as demonstrated in the 3D reconstruction of Thy1-YFP-H mouse cortical pyramidal neurons.
The prick trauma results in elimination of dendrites and destruction of capillary networks in a controlled volume of the brain cortex. During the first two days, the lesion area increased and the trauma induced dendrite blebbing and formation of dendritic retraction bulbs in the perilesion areas, as observed using in vivo multiphoton microscopy (Figure 2).
We performed skull thinning to image activation and migration of microglia in CX3CR1-EGFP mice immediately after injury (Figure 3A). The SHG imaging offers a valuable tool to delineate precisely the injury site (Figure 3B). Extracellular matrix molecules that produce SHG signals are greatly enriched in brain parenchyma at the prick trauma. First, fine microglial processes are retrieved, then microglial cells migrate to the border of the injury site (Figure 3A).
To estimate potential injuries induced by thin glass pipette insertion and delivery of dye, we perform in vivo two-photon microscopy experiments with Sulforhodamine 101 microinjection in Thy1-YFP-H mice without brain trauma. Representative images shown in Figure 4 demonstrate microinjection site 3 hr after injection. The trace of pipette insertion can be seen in brain meninges visualized by SHG (Figure 4A). Astrocytes are labelled with Sulphorhodamine 101 introduced by the injection (Figure 4B). Dendrites expressing YFP under Thy1 promoter do not demonstrate any morphological signs of injury like blebbing or retraction bulbs (Figure 4C).
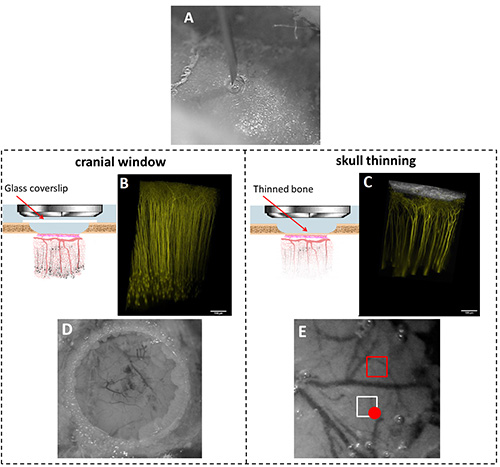
Figure 1. The method of acute brain injury in combination with cranial window or thin skull preparations combined with in vivo two-photon microscopy. A. Traumatic prick by steel needle of 0.3mm OD (30G) applied to the drilled well. The needle is briefly immersed into the brain 0.5-2 mm deep from the bottom of the well. B,C. 3D reconstruction of Thy1-YFP-H mouse cortical pyramidal neurons in yellow and schematic view of experimental preparations. The second harmonic generation (SHG) signal from thinned skull is shown in grey (C). D. Bright field view of the superficial blood vessels through the glass window immediately after the acute brain injury. E. Thinned skull before the injury application. The chosen region of interest (white frame) and the prick application site (red circle). A different area (red frame) of the thinned region should be imaged to monitor possible surgery-induced artifacts. Please click here to view a larger version of this figure.
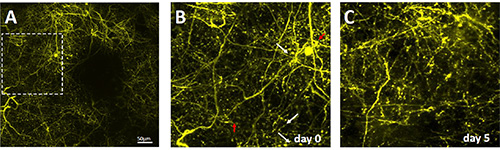
Figure 2. Example of longitudinal multiphoton imaging of brain trauma development through the thinned skull. A. Top view of the injury site surrounded by YFP-labelled dendrites of cortical neurons 20 min after trauma infliction, as imaged through the thinned skull preparation. B. Magnified view of the area outlined in panel A. C. The same area of the brain as in B, reimaged 5 days after trauma. Dendrite blebbing is shown with white arrows, dendritic retraction bulbs – with red arrows. Please click here to view a larger version of this figure.
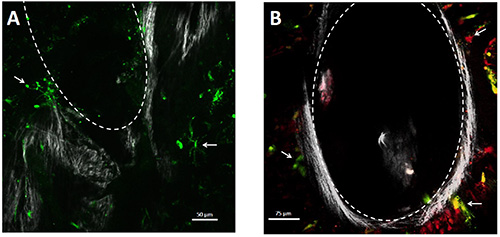
Figure 3. Examples of monitoring inflammation and glia activation during development of brain trauma using different markers suitable for in vivo multiphoton imaging e.g. fluorescent proteins, dyes, and second harmonic generation signal. The images were acquired 3 hr after the brain injury. A. GFP-expressing microglia (green) activation and migration after acute brain trauma imaged through cranial window in CX3CR1-EGFP mice; second harmonic generation (SHG) is shown in grey. B. GFP-expressing (green) and Sulforodamine 101-labeled (red) astrocytes in GFAP-EGFP mice around the injury site, which is outlined by strong second harmonic generation signal (grey) from extracellular matrix molecules. Arrows indicate examples of microglial cells (A) and astrocytes (B) after injury. The injury site border is identified with the SHG signal and depicted by dashed line. Please click here to view a larger version of this figure.
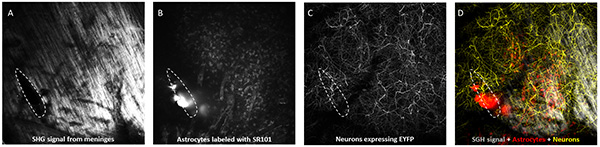
Figure 4. Examination of tissue impact made by solution injection via a glass micropipette. A. A trace (shown with dashed line) in SHG visualizing brain meninges 3 hr after injection. B. Astrocytes labelled with sulphorhodamine introduced by the injection. C. Dendrites expressing YFP under Thy1 promoter. D. Combined image of A (SHG - grey), B (astrocytes – red), C (neuronal dendrites – yellow). Please click here to view a larger version of this figure.
Discussion
Brain trauma is an abrupt, unpredictable event. Here, we describe the animal model that reproduces a spectrum of pathological changes observed in human patients after brain injury such as neurodegeneration, elimination of dendrites, brain edema, glial scar, hemorrhages in the cerebral cortex coupled with focal subarachnoid hemorrhaging and increased permeability of the blood–brain barrier. To study primary and secondary pathogenesis, as well as recovery after trauma, this injury model was combined with longitudinal in vivo visualization of fine neuronal and glial structures. Transgenic mouse lines were used that express fluorescent proteins in neurons (Thy1-YFP-H)7, astrocytes (GFAP-EGFP)8, or microglia (CX3CR1-EGFP)9. Additionally, we used second harmonic generation (SHG) imaging and astrocyte loading with Sulfarhodamine 10110.
The model described here recapitulates penetrating type of brain injury. Therefore a limitation of the present model is that it does not provide information about mechanisms of closed head injury. Recently Sword and coauthors reported multiphoton imaging results on cell behavior in pericontusional cortex6. Taking into account that closed head injury is a more frequent medical case, the methodological approach reported by the authors is highly promising to complement traditional research methods in the field of impact brain trauma11.
We used both the chronic cranial window12 and the skull thinning13 preparations to study cell behavior under posttraumatic conditions in living brain. Both methods have certain advantages and limitations. Thus, the chronic cranial window provides better resolution, deeper optical penetration into the brain tissue and convenience for multiple imaging sessions. Conversely, skull thinning is less likely to induce inflammation at the imaging site, and, perhaps more importantly, it allows repetitive applications of drugs and dyes. A few examples of pharmacological agents to be applied in this type of experiments are given in Table 1.
| Agent type | Injected agent | Areas of biology/pharmacy research |
| Anti-inflammatory | Cyclosporin A | Traumatic brain injury, secondary damage, neurodegeneration |
| Toxins | Tetrodotoxin | TBI – secondary damage, excytotoxicity |
| Bicuculline | TBI – secondary damage, chloride homeostasis | |
| Inhibitors of signaling pathways | PD98059 (MAPKK inhibitor) | signaling mechanisms of inflammation, secondary damage, posttraumatic cell death, neurodegeneration and regeneration |
| SU6656 (Src family kinase inhibitor) | ||
| Neurotrophic factors | Brain-derived neurotrophic factor, BDNF | TBI – neuronal survival after injury, neuroprotection in secondary posttraumatic brain damage |
| Glial cell line-derived neurotrophic factor, GDNF | ||
| Viruses | lentiviral vectors for protein expression | molecular mechanisms of posttraumatic neurodegeneration and regeneration, differential labelling of cell types in damaged brain for in vivo imaging |
| adenoviral vectors for protein expression | ||
| Ca2+ fluorescent indicators | Fluo-2,4 | signaling mechanisms of posttraumatic inflammation, cell death, cell migration, axonal/dendritic regeneration |
| Oregon Green BAPTA |
Table 1. Pharmacological agents and dyes for cortical injection in prick injury model.
A wide range of biochemical events that are highly important under physiological and pathological conditions can be probed with chemical inhibitors, fluorescent indicators and mutant protein introduced via viral constructs. Advantages for choosing particular time window provided by the skull thinning preparation may be highly relevant for those studies.
In the present study, we used second harmonic generation signal to delineate the injury site. Alternatively, the injury site borders could be indicated by a weakly diffusing fluorescent dye, for instance a high molecular weight dextran fluorescent conjugate (2 million Dalton).
Recently, Schaffer and colleagues14 have used a chronic preparation with reopenable cranial window for repetitive delivery of fluorescent dyes to mouse cortex. It is likely that cranial window reopening may adversely affect the brain tissue transparency. Moreover, it is difficult to predict the time course of the reopening-induced inflammation, which may affect the connective tissue regrowth.
One major advantage of the thinned skull preparation is the possibility to deliver therapeutic compounds (and other materials requiring topical injection into brain tissue) multiple times during progression of the trauma, without complicating artifacts (e.g. without cranial window reopening).
If repetitive compound delivery directly to the injury site is desired, one should consider special means to prevent skull dry-out and bacterial infection. Thus, keeping the operated head region under sterile conditions and application of antibiotics (such as enrofloxacin) is recommended. To preserve the thinned skull region from drying, fill the metal holder with 1.5% agarose and cover it with round glass coverslip. In most cases this will allow maintaining the same transparency or thinned skull over the period of up to 10 days. Some additional should be taken if multiple imaging sessions in the thinned skull preparation are planned over a prolonged period of time. Immediately before each imaging session, gently remove the newly formed connective tissue from the thinned region using a microsurgical blade. Use the TPEM imaging of SHG to verify image quality and measure bone thickness. Tissue regrowth may compromise the penetration depth and cause image blurring accompanied by an increase in the background fluorescence. Refresh the skull thinning gently with a microsurgical blade to regain high imaging quality.
In those cases that do not require direct access to the injury site, we highly recommend covering the thinned region of the skull with a glass coverslip as described in the paper on polished and reinforced thinned skull preparation by Kleinfeld and colleagues15. This could be done by using the following optional procedure. Place a small drop of agarose (1.5%) on the thinned skull region, wait until it becomes a gel, remove all unnecessary agarose, i.e. leave it only on the injury site. Agarose should protect the injury site from external effects. Dry the thinned skull region using compressed air. Drop a small amount of polyacrylic glue on a small piece of #0 coverglass and place it on the thinned skull region. The polyacrylic glue prevents bone and connective tissue regrowth, thus keeping the thinned skull under the window preserved.
A combination of these procedures allows studying acute and chronic posttraumatic processes, delivering drugs topically or systemically and directly monitoring the treatment effects. Use of dual or triple transgenic mouse lines can also be beneficial, particularly for simultaneous imaging of multiple posttraumatic processes, such as glial scar formation and neuronal branch regrowth. We expect our models of acute brain injury studied with intravital two-photon microscopy to prove fruitful for drug candidate testing.
Disclosures
The authors have nothing to disclose.
Acknowledgements
We are deeply thankful to Dr. Frank Kirchhoff for providing GFAP-EGFP and CX3CR1-EGFP mouse strains. The work was supported by grants from the Centre of International Mobility of Finland, Tekes, Finnish Graduate School of Neuroscience (FGSN) and the Academy of Finland.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 2A-sa dumb Tweezers, 115 mm | XYtronic | XY-2A-SA | |
| 30 G ½ in needle | BD | REF 304000 | |
| Animal trimmer, shaving machine | Aesculap | Isis GT420 | |
| Binocular Microscope | Zeiss | Stemi 2000 | |
| Biological Temperature Controller with stainless steel heating pad | Supertech | TMP-5b | |
| Blunt microsurgical blade | BD | REF 374769 | |
| Borosilicate tube with filament | Sutter Instruments | BF120-69-10 | For glass pipette production |
| Carprofene | Pfizer | Rimadyl vet | |
| Chlorhexidine digluconate | Sigma | C9394 | |
| Dental cement | DrguDent, Dentsply | REF 640 200 271 | |
| Dexamethasone | FaunaPharma | Rapidexon vet | |
| Disposable drills | Meisinger | HP 310 104 001 001 008 | |
| Dulbeco’s PBS 10x | Sigma | D1408 | |
| Dumont #5 forceps, 110 mm | FST | 91150-20 | |
| Ealing microelectrode puller | Ealing | 50-2013 | Vertical puller for glass pipette production |
| Eye ointment | Novartis | Viscotears | |
| Foredom drill control | Foredom | FM3545 | |
| Foredom micromotor handpiece | Foredom | MH-145 | |
| Gas anesthesia platform for mice | Stoelting | 50264 | Assembled on stereotaxic instrument |
| Hemostasis Collagen Sponge | Avitene, Ultrafoam BARD | Ref 1050050 | |
| Imaris | Bitplane | ||
| Ketamine | Intervet | Ketaminol vet | |
| Mai Tai DeepSee laser | Spectra-Physics | ||
| Metal holder | Neurotar | ||
| Microdressing forceps, 105 mm | Aesculap | BD302R | |
| Microfil | WPI | MF34G-5 | Micro syringe filling capillaries |
| Mineral oil | Sigma | M8410 | |
| Multiphoton Laser Scanning Microscope | Olympus | FV1000MPE | |
| NanoFil Syringe 10 μl | WPI | NANOFIL | Hamilton syringe |
| Nonwoven swabs 5 x 5 | Molnlycke Health Care | Mesoft | Surgical tampons |
| Polyacrylic glue | Henkel | Loctite 401 | |
| Round glass coverslip | Electron Microscopy Sciences | ||
| 1.5 thickness | |||
| Small animal stereotaxic instrument | David Kopf Instruments | 900 | |
| Stoelting mouse and neonatal rat adaptor | Stoelting | 51625 | Assembled on stereotaxic instrument. |
| Student iris scissors, straight 11.5 cm | FST | 91460-11 | |
| Sulforhodamine 101 | Molecular Probes | S-359 | |
| UMP3 microsyringe pump and Micro 4 microsyringe pump controller | WPI | UMP3-1 | Microinjector and controller |
| Xylazine | Bayer Health Care | Rompun vet |
References
- Lighthall, J. W. Controlled cortical impact: A new experimental brain injury model. J. Neurotrauma. 5 (1), 1-15 (1988).
- Lindgren, S., Rinder, L. Experimental studies in head injury. Biophysik. 2 (5), 320-329 (1965).
- Shreiber, D. I., et al. Experimental investigation of cerebral contusion: histopathological and immunohistochemical evaluation of dynamic cortical deformation. J. Neuropathol. Exp. Neurol. 58 (2), 153-164 (1999).
- Feeney, D. M., Boyeson, M. G., Linn, R. T., Murray, H. M., Dail, W. G. Responses to cortical injury: I. Methodology and local effects of contusions in the rat. Brain Res. 211 (1), 67-77 (1981).
- Bardehle, S., et al. Live imaging of astrocyte responses to acute injury reveals selective juxtavascular proliferation. Nat. Neurosci. 16 (5), 580-586 (2013).
- Sword, J., Masuda, T., Croom, D., Kirov, S. A. Evolution of neuronal and astroglial disruption in the peri-contusional cortex of mice revealed by in vivo two-photon imaging. Brain. 136 (5), 1446-1461 (2013).
- Feng, G., et al. Imaging neuronal subsets in transgenic mice expressing multiple spectral variants of GFP. Neuron. 28, 41-51 (2000).
- Nolte, C., et al. GFAP promoter-controlled EGFP-expressing transgenic mice: a tool to visualize astrocytes and astrogliosis in living brain tissue. Glia. 33 (1), 72-86 (2001).
- Jung, S., et al. Analysis of fractalkine receptor CX(3)CR1 function by targeted deletion and green fluorescent protein reporter gene insertion. Mol. Cell. Biol. 20 (11), 4106-4114 (2000).
- Nimmerjahn, A., Kirchhoff, F., Kerr, J. N. D., Helmchen, F. Sulforhodamine 101 as a specific marker of astroglia in the neocortex in vivo. Nat. Methods. 1 (1), 31-37 (2004).
- Carré, E., et al. Technical aspects of an impact acceleration traumatic brain injury rat model with potential suitability for both microdialysis and PtiO2 monitoring. J. Neurosci. Methods. 140, 23-28 (2004).
- Holtmaat, A., et al. Long-term, high-resolution imaging in the mouse neocortex through a chronic cranial window. Nat. Protoc. 4 (8), 1128-1144 (2009).
- Yang, G., Pan, F., Parkhurst, C. N., Grutzendler, J., Gan, W. B. Thinned-skull cranial window technique for long-term imaging of the cortex in live mice. Nat. Protoc. 5, 201-208 (2010).
- Cianchetti, F. A., Kim, D. H., Dimiduk, S., Nishimura, N., Schaffer, C. B. Stimulus-evoked calcium transients in somatosensory cortex are temporarily inhibited by a nearby microhemorrhage. PloS one. 8 (5), (2013).
- Shih, A. Y., Mateo, C., Drew, P. J., Tsai, P. S., Kleinfeld, D. A polished and reinforced thinned-skull window for long-term imaging of the mouse brain. J. Vis. Exp. 61, (2012).
Reprints and Permissions
