This manuscript describes methods associated with creation and repair of a ventral abdominal wall defect (hernia). This model can be used to study repair strategies such as those that use implanted materials. In this manuscript, repair of the experimental hernia with porcine small intestinal submucosa is presented as an example.
Method Article
Use of a Rat Model to Study Ventral Abdominal Hernia Repair
In This Article
Summary
Abstract
Ventral abdominal hernia is a relatively common clinical condition that sometimes requires herniorraphy (surgical repair). The repair of ventral abdominal hernia typically requires implantation of a material to serve as a mechanical bridge across the defect in the abdominal wall. Biomaterials, such as porcine small intestinal submucosa (SIS), also serve as a lattice for cell growth into the implant and can naturally incorporate into the host tissue. Development of such repair materials benefits from use of animal models in which experimental abdominal wall defects are easily created and are amenable to repair in a reproducible fashion. The method offered here describes surgical creation and repair of ventral abdominal hernia in a rat model. When SIS is used to repair an experimental ventral abdominal hernia in this model, it is rapidly incorporated into host tissue within 28 days of implantation. Histologically, incorporation of their implanted material into host tissue is characterized by a robust fibrovascular response. Future refinements and applications of the rat abdominal hernia model may likely involve diabetic and/or obese animals as a means to more closely mimic common co-morbidities of man.
Introduction
Abdominal wall hernia is a commonly encountered clinical issue which may occur as a result of congenital defect, traumatic injury, or failed closure of surgical wounds involving the abdominal wall. Repair commonly involves using an implant to reinforce the abdominal wall, with a reduced rate of recurrence noted in patients treated with an implant compared to those in whom the abdominal wall is simply closed with suture.1
Surgical hernia repair often requires mechanical bridging of the defect with an implanted material. In this regard, both synthetic and natural materials have been used for hernia repair. Many synthetic materials are typically non-absorbable and include polypropylene, polyethylene terephthalate polyester, and expanded polytetrafluoroethylene, while other synthetic implants combine one of the non-absorbable materials with an absorbable polymer such as polygalactine.1 In contrast, natural material implants are generally derived from either animal or human cadaveric sources. Natural materials used for hernia repair are typically rich in collagen and act as a scaffold for ingrowth and integration of host tissue.
The desire to develop and optimize new materials for ventral abdominal hernia repair requires an appropriate animal model for evaluation of candidate materials. Studies have been conducted in a variety of species, including sheep,2 pigs,3 rabbits,4 rats,5,6,7,8 and dogs.9 The advantage of using rats for such studies is that they offer an easily handled model available in a variety of inbred strains to allow for control of genetic variability. In addition, the smaller overall body surface area of the rat compared to the other species listed above permit evaluation of materials that may be experimental in nature and, therefore, not abundant. Further, reduced costs associated with rats versus other species allow for relatively increased ability to screen candidate materials for use in repair of ventral abdominal hernia. Considerations for materials typically include ease of handling by the surgeon, strength, ability to incorporate into host tissue, biocompatibility, and resistance to infection.
As an example, porcine small intestinal submucosa (SIS) is a natural biomaterial that has been used for a wide variety of tissue repair indications, including repair of ventral abdominal, inguinal, and diaphragmatic hernias.10,11,12 SIS is rapidly incorporated into host tissue and has been found to be generally resistant to infection and so the material has particular utility in contaminated fields.13,14 In the rat model, SIS has demonstrated ease of handling, good tensile strength as determined by the uniaxial tensile failure test, and promotion of tissue ingrowth in terms of collagen deposition and neovascularization.6,7
Accurate surgical bridging of the defect is an essential feature of productive modeling when evaluating candidate repair materials. The animal must be sufficiently anesthetized and aseptic technique strictly followed. Further, an abdominal wall defect of standard size must be carefully created and then bridged in a manner that sufficiently secures the material to the margins of the defect.8 This protocol provides a standard method to be followed for surgical creation, and repair of, a ventral abdominal hernia using SIS as an example bridging material in a rat.
Protocol
The use of animals in this protocol was approved by the University of Notre Dame Institutional Animal Care and Use Committee, followed all regulatory requirements and guidelines, and was conducted in a facility that is accredited by the Association for Assessment and Accreditation of Laboratory Animal Care (AAALAC), International.
1. Selection of Animals
- Acquire pathogen-free Sprague Dawley rats from a reputable vendor or breeding colony.
Note: Often, the facility veterinarian or manager can direct the investigator to appropriate sources. Rats of approximately 250 g body weight are suitable for this procedure. - One day prior to surgery, examine the animals to be used to ensure that they are clinically healthy. In this regard, weigh the animal and assess the body condition; note any abnormality in respiration, the presence of any open wounds or masses, and the general activity level of the animal. Note any abnormality in the surgical record and consider such observations as potential exclusion criteria.
2. Anesthesia and Preparation of Animal for Aseptic Surgery
- For analgesia, administer 1.1 - 1.2 mg/kg of sustained release buprenorphine, subcutaneously to the rat 2 h before surgery. Apply ophthalmic ointment to both eyes, and administer 2 mL of warmed sterile physiologic saline subcutaneously.
- Anesthetize the rat with an intraperitoneal dose of ketamine hydrochloride (90 mg/kg) and xylazine (10 mg/kg). Apply a small amount of ocular lubricant to each eye to prevent corneal dessication. Once the animal’s respiration is steady and there is no longer any response to a firm toe pinch, the rat has reached a level of anesthesia sufficient for surgery. An acceptable level of anesthesia can be further confirmed by the presence of deep, regular respiration, and normal color of the eye (versus pallor, which might suggest inadequate cardiovascular perfusion).
- Shave the ventral abdomen with a commercial clippers from the pubis to the sternum and from the lateral margins on the ventrum. Remove the clipped hair by applying a moist paper towel to the area.
- Scrub the shaved area with an iodophor antiseptic followed by a wipe with 70% ethanol. Apply surgical drapes so that a window for the incision can be isolated from potential contamination.
- Don a sterile surgical gown, a face mask, and a hair bonnet. Thoroughly wash and scrub hands with soap and don sterile surgical gloves.
3. Creation and Repair of the Ventral Abdominal Hernia
- Prior to surgery, sterilize surgical instruments by autoclave.
- Using a scalpel, make an approximately 3 - 4 cm vertical incision along the ventral midline down to the level of the abdominal musculature. Lift the abdominal wall gently with a forceps and create a small opening through the linea alba. To protect the underlying viscera, insert a forceps through the hole and into the abdominal cavity to serve as a protective guide as the muscle wall is incised to create an approximately 2 cm x 2 cm full thickness defect, cutting approximately 1 cm lateral from each side of the midline on both ends of the linea alba incision.
- Lay a pre-cut 2 cm x 2 cm section of mechanical bridging material, 4-layer SIS in this case (Figure 1), over the defect.
Note: Alternatively, an underlay approach can be used in which the section of material is placed into the abdominal cavity to cover the defect from the interior aspect. - Suture the four corners of the bridging material to the abdominal wall muscle using 4-0 silk or nylon in a simple interrupted suture pattern.
Note: The use of non-absorbable suture allows easy identification of the implanted material upon harvest versus absorbable suture material. - Secure each edge of the material with three additional sutures spaced equally. Examine the entire circumferential edge to ensure that significant gaps do not exist that might allow passage of viscera through the abdominal wall; and, if such gaps exist, place additional sutures to further secure the margin.
- Close the subcutaneous tissue with 4-0 absorbable suture in a simple interrupted pattern. Close the skin with surgical staples, though suture applied in a simple interrupted pattern may also be used.
- Do not leave the animal unattended until it has regained sufficient consciousness to regain sternal recumbency; and do not return an animal that has undergone surgery to the company of other animals until it has fully recovered from anesthesia. During this time, keep the animal in a warm area to prevent hypothermia.
- Examine animals daily that have undergone this procedure to ensure full recovery and normal healing. Remove skin staples with a staple remover 7 - 10 days following surgery.
4. Harvest of the Implanted Material
- Consistent with the needs of the study, euthanize, with carbon dioxide overdose administered at a chamber fill rate of 10 to 30%, the animals at a pre-determined time, often 21 - 28 days following surgery.
- Using standard necropsy tools, open the skin and abdominal wall and expose the area of the implant.
Note: If non-absorbable sutures were used to secure the implant, the material can be identified by the original sutures (Figure 2). - Observe any gross pathological observations including any adverse reactions (e.g., wound dehiscence, abscess, seroma, hematoma) and adhesion extent and tenacity to the underlying viscera.
- Remove the implant site by cutting a wide section of tissue that includes the implant. Place the sample in a fixative, such as 10% neutral buffered formalin, in preparation for processing for histological examination and characterization.
Results
By 28 days after implantation, SIS typically demonstrates good incorporation into host tissue (Figure 2). In most cases, there is residual SIS apparent, though the tissue must often be explored to identify the implanted material. Histological analyses confirmed the gross pathological observations, illustrating good tissue incorporation with primarily fibrovascular tissue and very little residual SIS noted (Figure 3). These results demonstrate the utility of the rat ventral abdominal hernia model. The rat is easily obtained and maintained, and generally recovers quickly following surgery. The tissue incorporation into the implanted biomaterial indicates biocompatibility and demonstrates the ability of the SIS to serve as a lattice for tissue ingrowth and repair. Even with substantial tissue incorporation, the site of the implant can be readily identified by the sutures used to secure the material to the abdominal wall. As a result, hernia repair materials can be evaluated in a consistent and relatively expeditious manner.

Figure 1: 2 x 2 cm Section of SIS Used for Repair of Experimental Ventral Abdominal Hernia. The SIS material is an acellular extracellular matrix derived from porcine small intestinal submucosa. Please click here to view a larger version of this figure.
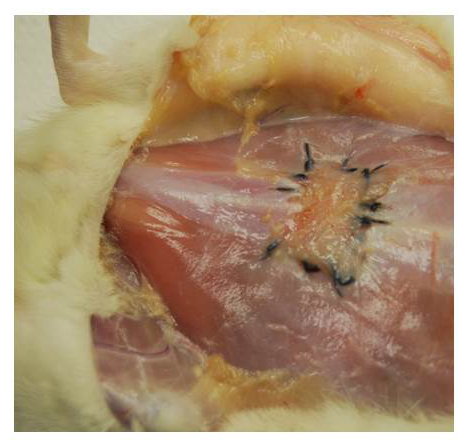
Figure 2: Incorporated SIS 28 Days After Implantation to Bridge a Ventral Abdominal Hernia in a Rat. Following euthanasia, the ventral abdominal skin was reflected to expose the implanted material that is outlined by the silk sutures used to secure the SIS. Note the ingrowth of tissue as the SIS implant has been incorporated into host tissue. Please click here to view a larger version of this figure.

Figure 3: Photomicrograph of Tissue 28 Days Following Implantation of SIS to Bridge an Experimental Ventral Abdominal Hernia. The SIS has largely been incorporated into the host tissue. The arrows show a very small strand of residual SIS in the section (H & E, 40X). Please click here to view a larger version of this figure.
Discussion
Materials for the repair of ventral abdominal hernia are of great interest, particularly those that provide an initial mechanical bridge and are then able to incorporate into host tissue. In this regard, a variety of materials have been investigated, including SIS, porcine acellular dermal matrix, and porcine pericardium.6,7 These materials represent the extracellular matrices of those tissues and act as scaffolds into which cells can migrate and proliferate, thus facilitating tissue incorporation.
Evaluation of hernia repair materials requires an animal model that is easily handled and has intact healing ability. The rat ventral hernia model allows for ease of handling in studies to assess repair materials in vivo. It has been demonstrated that this model could be used for comparative histological assessment of host response to implanted hernia repair materials.6 This is particularly essential for biomaterials, such as SIS, that undergo incorporation into the host tissue as part of the repair mechanism.
The rat ventral abdominal hernia repair model can be easily performed in a very reproducible manner. Proper aseptic technique is essential for success, as contaminated surgical fields can alter the healing response and thus complicate interpretation of experimental results.15 The protocol described here is designed to provide an individual experienced in animal surgery with a method to successfully undertake studies requiring hernia creation and repair.
The procedure described here involves an outlay approach in which the repair material is attached to the external edges of the abdominal wall defect. It is also possible to use an inlay approach in which the repair material is attached to the internal aspect of the defect. Hernia repair with mesh via laparoscopy is typically achieved with an inlay approach. The inlay method allows greater direct contact of the implant with abdominal viscera, thus somewhat increasing the possibility of adhesiogenesis between implant and viscera. Because post-surgical adhesion formation is an important clinical issue, studies that wish to closely examine adhesiogenesis may wish to use the inlay approach.
Though rats generally recover very quickly following the surgery, some possibility for post-operative complication exists. For example, some rats will remove skin sutures, even staples. If the incision wound is found to be open, the rat should either be euthanized or re-anesthetized and the skin closed. Though rare, if both the skin and abdominal wall are found to have open gaps, the animal should be euthanized. In all such cases, the attending veterinarian should be promptly informed of such animals.
The model described here has a number of advantages as indicated earlier. However, it should be recognized that modeling of ventral abdominal hernia in a quadraped, such as a rat, limits translation to man. Further, because many clinically relevant hernias are believed to be associated with co-morbidities such as diabetes, obesity, and connective tissue defects, evaluation of repair strategies in a normal animal could complicate the translational value of the model. Nonetheless, the rat model allows relatively rapid and easy evaluation of hernia repair materials.
Future refinements and applications of the rat abdominal hernia model may likely involve diabetic and/or obese animals as a means to more closely mimic common co-morbidities of man. Likewise, the evaluation of induced pluripotent stem cell methods to aid tissue repair will likely find utility in this model.
Critical steps for successful use of this model are centered on care of the animal and surgical skill. Aseptic technique must be used as a way to minimize the chance of infection. Proper anesthesia and analgesia are essential, as well as post-operative monitoring to ensure that animals are comfortable and that the surgical incision remains closed. Importantly, when securing the biomaterial to the edges of the abdominal wall defect, the surgeon must establish that all edges are secure with no openings that might allow passage of abdominal viscera into the subcutaneous space.
Disclosures
One of the authors (CJ) is employed by Cook Biotech, Inc., the manufacturer of medical grade SIS.
Acknowledgements
The authors wish to thank Valerie Schroeder for her assistance with technical aspects of this work. Work related to development of this model was supported by Cook Biotech, Inc. (West Lafayette, IN USA).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Isoflurane (Isoflo) | Henry Schine Animal Health | 17579 | gas anesthetic |
| Optixcare Eye Lubricant | Henry Schine Animal Health | OPX4240 | Ocular lubricant |
| Oster clippers | Henry Schine Animal Health | 6092 | hair clippers |
| Betadine surgical scrub | Henry Schine Animal Health | 1618 | antiseptic iodophor |
| Sterile scalpel | Henry Schine Animal Health | 329 | #10 scalpel |
| 9" x 12" disposable surgical drape | Braintree Scientific, Inc. | SP-RPS | Surgical drape |
| 4-0 nylon suture | Braintree Scientific, Inc. | SUT 812 | Suture material |
| 4-0 Absorbable Suture | Henry Schine Animal Health | 29242 | Synthetic absorbable suture |
| 9 mm Autoclips and applier | Braintree Scientific, Inc. | ACS KIT | Surgical staples for closure of skin incision |
| Torbugesic/analgesic | Henry Schein Animal Health | 12084 | Butorphanol tartarate for post-operative analgesia |
| Small intestinal submucosa (SIS) | Cook Biotech, Inc. | Implant material for bridging experimental abdominal wall defect | |
| Rats | Harlan, Inc. | Sprague Dawley | Animal for hernia modeling |
References
- Poussier, M., et al. A review of available prosthetic material for abdominal wall repair. J. Visc. Surg. 150 (1), 52-59 (2013).
- Hjort, H., Mathisen, T., Alves, A., Clermont, G., Boutrand, J. P. Three-year results from a preclinical implantation study of a long-term resorbable surgical mesh with time-dependent mechanical characteristics. Hernia. 16 (2), 191-197 (2012).
- Ko, R., Kazacos, E. A., Snyder, S., Ernst, D. M. J., Lantz, G. C. Tensile strength comparison of small intestinal submucosa body wall repair. J. Surg. Res. 135 (1), 9-17 (2006).
- Garcia-Moreno, F., et al. Comparing the host tissue response and peritoneal behavior of composite meshes used for ventral hernia repair. J. Surg. Res. 193 (1), 470-482 (2015).
- Soiderer, E. E., Lantz, G. C., Kazacos, E. A., Hodde, J. P., Wiegand, R. E. Morphologic study of three collagen materials for body wall repair. J. Surg. Res. 118 (2), 161-175 (2004).
- Liu, Z., Tang, R., Zhou, Z., Song, Z., Wang, H., Gu, Y. Comparison of two porcine-derived materials for repairing abdominal wall defect in rats. PLOS One. 6 (5), e20520(2011).
- Zhang, J., Wang, G. Y., Xiao, Y. P., Fan, L. Y., Wang, Q. The biomechanical behavior and host response to porcine-derived small intestine submucosa, pericardium and dermal matrix acellular grafts in a rat abdominal defect model. Biomaterials. 32 (29), 7086-7095 (2011).
- Ma, J., Sahoo, S., Baker, A. R., Derwin, K. A. Investigating muscle regeneration with a dermis/small intestinal submucosa scaffold in a rat full-thickness abdominal wall defect model. J.Biomed.Mater.Res.Part B. 103 (2), 355-364 (2015).
- Greca, F. H., Souza-Filho, Z. A., Giovanni, A., Rubin, M. R., Kuenzer, R. F., Reese, F. B., Araujo, L. M. The influence of porosity on the integration histology of two polypropylene meshes for the treatment of abdominal wall defects in dogs. Hernia. 12 (1), 45-49 (2008).
- Hiles, M., Record-Ritchie, R. D., Altizer, A. M. Are biologic grafts effective for hernia repair? A systematic review of the literature. Surg. Innov. 16 (1), 26-37 (2009).
- Helton, W. S., Fisichella, P. M., Berger, R., Horgan, S., Espat, N. J., Abcarian, H. Short-term outcomes with small intestinal submucosa for ventral abdominal hernia. Arch. Surg. 140 (6), 560-562 (2005).
- Franklin, M. E., Trevino, J. M., Portillo, G., Vela, I., Glass, J. L., Gonzalez, J. J. The use of porcine small intestinal submucosa as a prosthetic material for laparascopic hernia repair in infected and potentially contaminated fields: long-term follow-up. Surg. Endosc. 22 (9), 1941-1946 (2008).
- Clarke, K. M., Lantz, G. C., Salisbury, S. K., Badylak, S. F., Hiles, M. C., Voytik, S. L. Intestine submucosa and polypropylene mesh for abdominal wall repair in dogs. J. Surg. Res. 60 (1), 107-114 (1996).
- Sarikava, A., Record, R., Wu, C. C., Tullius, B., Badylak, S. F., Ladisch, M. Antimicrobial activity associated with extracellular matrices. Tissue Eng. 8 (1), 63-71 (2002).
- Serra, R., Grande, R., Butrico, L., Rossi, A., Settimio, U. F., Caroleo, B., Amato, B., Gallelli, L., de Franciscis, S. Chronic wound infections: the role of Pseudomonas aeruginosa and Staphylococcus aureus. Expert Rev. Anti. Infect. Ther. 13 (5), 605-613 (2015).
Reprints and Permissions
