We describe here a fluorometric cell-free biochemical assay for determination of HDL-lipid peroxidation. This rapid and reproducible assay can be used to determine HDL function in large scale studies and can contribute to our understanding of HDL function in human disease.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Method Article
Cell-free Biochemical Fluorometric Enzymatic Assay for High-throughput Measurement of Lipid Peroxidation in High Density Lipoprotein
In This Article
Summary
Abstract
Low high-density lipoprotein cholesterol (HDL-C) levels are one of the most powerful independent negative predictors of atherosclerotic cardiovascular disease (CVD). The structure and function of HDL rather than HDL-C may more accurately predict atherosclerosis. Several HDL protein and lipid compositional changes that impair HDL function occur in inflammatory states such as atherosclerosis. HDL function is usually determined by cell based assays such as cholesterol efflux assay but these assays have numerous drawbacks lack of standardization. Cell-free assays may give more robust measures of HDL function compared to cell-based assays. HDL oxidation impairs HDL function. HDL has a major role in lipid peroxide transport and high amount of lipid peroxides is related to abnormal HDL function. Lipid-probe interactions should be considered when interpreting the results of non-enzymatic fluorescence assays for measuring the lipid oxidative state. This motivated us to develop a cell-free biochemical enzymatic method to assess HDL lipid peroxide content (HDLox) that contributes to HDL dysfunction. This method is based on the enzyme horseradish peroxidase (HRP) and the fluorochrome Amplex Red that can quantify (without cholesterol oxidase) the lipid peroxide content per mg of HDL-C. Here a protocol is describedfor determination of HDL-lipid peroxidation using the fluorochrome reagent. Assay variability can be reduced by strict standardization of experimental conditions. Higher HDLox values are associated with reduced HDL antioxidant function. The readout of this assay is associated with readouts of validated cell-based assays, surrogate measures of cardiovascular disease, systemic inflammation, immune dysfunction, and associated cardiovascular and metabolic risk phenotypes. This technical approach is a robust method to assess HDL function in human disease where systemic inflammation, oxidative stress and oxidized lipids have a key role (such as atherosclerosis).
Introduction
Atherosclerotic cardiovascular disease (CVD) is the leading cause of death worldwide1,2. Epidemiological studies have shown that low levels of high-density lipoprotein (HDL) cholesterol are generally inversely associated with the risk for the development of atherosclerosis1,2. Although several studies support an atheroprotective role for HDL1,2, the mechanism by which HDL attenuates the initiation and progression of atherosclerosis is complex 3,4. Thus, it has been suggested that the complex structure and function of HDL rather than absolute level may more accurately predict atherosclerosis 5,6,7,8. Several HDL protein and lipid compositional changes that impair HDL function occur in inflammatory states such as atherosclerosis. These i) reduce its cholesterol efflux potential 9, ii) decrease anti-inflammatory and increase HDL-associated pro-inflammatory proteins 6,7, iii) decrease antioxidant factor levels and activity and HDLs ability to inhibit oxidation of Low Density Lipoprotein (LDLox)10 and iv) increase lipid hydroperoxide content and redox activity (HDLox)9,11. Robust assays that evaluate the pleotropic functions of HDL (such as cholesterol efflux, antioxidant function) may complement determination of HDL-HDL-C in the clinic.
HDL function is usually assessed by cell-based methods such as the cholesterol efflux assay8,12,13,14. These methods have major limitations including significant heterogeneity with regards to types of cells used, type of readout reported, lack of standardization and confounding effects of triglycerides 7,15. These drawbacks pose difficulties for large clinical studies16. Cell-free assays may give more robust measures of HDL function compared to cell-based assays. The cholesterol efflux is one of the most important functions of HDL but it can only be determined by cell-based assays. Other approaches to determine HDL function such as proteomics17,18,19,20,21,22,23,24 and cell-based monocyte chemotaxis assays of HDL function 17,22,25 have not been standardized and cannot be used in large scale human studies.
HDL has significant antioxidant atheroprotective effect5,6,7,8. The antioxidant function of HDL has been determined in the presence of LDL in previous cell free fluorometric assays 26. These biochemical fluorometric methods of HDL antioxidant function were originally developed by Mohamad Navab and Alan Fogelman and their colleagues26. Although many human studies have used these methods to determine HDL function 17,18,19,20,21,22,23,24, lipid (HDL)-lipid (LDL) and lipid-fluorochrome interactions may limit reproducibility of these cell free non-enzymatic biochemical assays of HDL function27,28.
Recent interest has focused on the functional consequences of HDL oxidation that is the result of oxidation of both lipids and proteins within HDL 27,29,30. Prior studies have shown that oxidation of HDL impairs HDL function 27,29,30. HDL has a major role in lipid peroxide transport and high amount of lipid peroxides is related to abnormal HDL function. Thus HDL lipid peroxide content can be used to determine HDL function 9,17,20,31 and given the known limitations of prior assays of HDL function7,15,27,32, we developed an alternative fluorometric method that quantifies HDL lipid peroxide content (HDLox) 32. This method is based on the enzyme horseradish peroxidase (HRP) and the fluorochrome Amplex Red that can quantify (without cholesterol oxidase) the lipid peroxide content per mg of HDL-C 32. The biochemical principle of the assay is shown in Figure 1. We have shown that this fluorescence-based approach does not have the limitations of prior HDL function assays27,28. This assay has been further refined and standardized in our laboratory so that it can reliably be used in large scale human studies even with cryopreserved plasma 32,33,34,35,36,37,38,39,40,41,42. The readout of this assay is associated with readouts of validated cell-based assays, surrogate measures of cardiovascular disease, systemic inflammation, immune dysfunction and associated cardiovascular and metabolic risk phenotypes32,33,34,35,36,37,38,39. Here, we describe this simple, yet robust method to measure HDL lipid peroxide content (HDLox). This assay can be used as a tool to answer important research questions regarding the role of HDL function in human disease where systemic inflammation, oxidative stress and oxidized lipids have a key role (such as atherosclerosis)32.
Access restricted. Please log in or start a trial to view this content.
Protocol
All experiments using human biological samples were performed with ethics approval from the University of California Los Angeles, Los Angeles and the Alfred Hospital Human Ethics committee, Melbourne.
NOTE: There are many variations of the fluorochrome HDL function Assay (see discussion)32. Below we will describe the protocol that gives the most consistent and reproducible results. An overview of the assay is shown in Figure 2.
1. Specimen Processing
- Use fresh, non-hemolyzed serum (can be collected in serum separator tubes) or citrate plasma obtained after 12-14 hours fasting. If using cryopreserved samples, include appropriate control as described in this Protocol.
2. Day 0-Preparation for the assay
- Prepare working layout of experiment with the appropriate controls, samples and replicates. Run each sample at least in triplicates. A representative 96 well layout is shown in Figure 3.
- Calculate all volumes of reagents that will be used for the assay based on number of samples and replicates.
NOTE: Include an additional 10% volume in each working stock to make sure there is enough volume for each reagent for the specific experiment. - Label all required tubes for all different steps of the assay e.g. for the separation of HDL, measurement of HDL-C (optional) and the fluorochromeassay.
3. Day 1-Preparation of controls
- Preparation of study-specific pooled control
- Create a control sample from pooled plasma or serum of all study samples. If running 20 samples in each plate in triplicate, combine 10 µL from each sample into a 200 µL pooled control. Give a separate aliquot of this pooled control to the clinical laboratory to determine the HDL-C value of this control.
NOTE: Use this pooled control to standardize the assay and account for all possible known (e.g. type of matrix serum versus plasma, freeze-thaw cycles, cryopreservation) and unknown confounders that may affect experimental variability27,28.
- Create a control sample from pooled plasma or serum of all study samples. If running 20 samples in each plate in triplicate, combine 10 µL from each sample into a 200 µL pooled control. Give a separate aliquot of this pooled control to the clinical laboratory to determine the HDL-C value of this control.
- Preparation of laboratory-specific quality control (QCs)
- Prepare a large stock of HDL in each laboratory (for example HDL isolated from 5 mL of plasma from 10 healthy donors) and cryopreserve several aliquots of this stock to minimize freeze-thaw cycles.
- Use at least 10 different replicates from this stock to determine the average value of HDLox. An acceptable range of measured HDLox values for each QC sample included in each assay is within <15% of the coefficient of variation of this average value.
- Give a separate aliquot of this pooled control to the clinical laboratory to determine the HDL-C value of this control (e.g. 40 mg/dL).
NOTE: A detailed approach how to use blood from blood banks to create these controls has previously been described 27,28,32. Use additional QCs as needed (e.g. one from a healthy donor known to have normal HDL function and one from a donor known to have largely abnormal HDL function.
- Optimization of background signal and blank values (optional)
- To minimize background, add the appropriate amount of catalase (1-4 U/mL) in the incubation medium to rapidly remove the formed H2O2 due to spontaneous air oxidation of the buffers.
NOTE: Since the values from the blank wells (no HDL) are being subtracted from the values of the HDL samples and the results are being reported relative to a pooled control (that is included in the same 96 well plate), we have found that this step does not practically affect the results. Thus, optimization of the background signal with catalase can be omitted, if needed.
- To minimize background, add the appropriate amount of catalase (1-4 U/mL) in the incubation medium to rapidly remove the formed H2O2 due to spontaneous air oxidation of the buffers.
4. Day 1-Separation of HDL Cholesterol using HDL precipitation
NOTE: Use a commercially available standardized HDL Cholesterol precipitating reagent to isolate apoB depleted serum according to the manufacturer's instructions. These reagents are widely used in colorimetric assays to determine HDL cholesterol levels.
- Use fresh (or thaw) plasma or serum sample.
- Mix equal volumes (e.g. 80 µL) of plasma and HDL Cholesterol Precipitating Reagent (20% w/v polyethylene glycol in glycine buffer at pH 10.0 (25 °C)).
- Mix well by pipetting up and down.
- Centrifuge at 1000-2000 x g for 10 min.
- Aspirate the supernatant (HDL fraction).
- Ideally use immediately the isolated HDL for the fluorochromeassay of HDL lipid peroxidation. However, if several samples are run in the same day and other steps such as measurement of HDL-cholesterol concentration are also done, then store the isolated HDL at 4 °C and use it the next day for the fluorochromeHDL function Assay.
5. Day 1-Determination of HDL-C in isolated HDL
NOTE: This is optional if the value of HDL-C from the clinical laboratory is used to normalize HDLox by HDL-C amount.
- Quantify the HDL-cholesterol from plasma, using standard colorimetric assays27. Add 50 µL of Cholesterol Reagent in each well and determine cholesterol concentration using a colorimetric plate reader and a cholesterol standard provided in each kit.
6. Day 2-Preparation of reagents
- Prepare HRP and cholesterol solutions of HRP 5 U/mL solution (Range 1-10 U/mL).
- Prepare 20 mM fluorochrome (e.g., Amplex Red) solutions: Thaw a vial of fluorochrome reagent and DMSO to room temperature. Prior to use, dissolve fluorochrome reagent (1 mg) in 200 µL of DMSO. Store stock solution frozen at ≤-20 °C, protected from light.
- Prepare positive and negative controls: Use 1X 'reaction buffer' without cholesterol and 20 mM H2O2 working solution as a negative and positive control, respectively.
7. Day 2-Fluorochrome Assay
- Add 50 µL of 1x Reaction buffer as blank (negative control).
- Optional: Add 20 mM working solution of H2O2 as positive control in each plate.
- To minimize experimental variability and ensure that addition of reagents and samples are done consistently and in a timely manner, perform all additions of samples in a separate 96 well round-bottom, clear, polystyrene or polypropylene plate (Plate 1). Then use a multichannel pipette to transfer specific volumes into 3 96-well plates (Plates 2-4: polypropylene, flat bottom, black) (that have identical layout) (Figure 2, Figure 3).
- For example, first add 160 µL of isolated HDL into each well/sample of plate 1 and then with the use of multichannel pipette transfer 50 µL of HDL-cholesterol from each well/sample into the 96-well black plates. Change tips between each row/column and use non-filtered tips for all the transfers.
- Leave samples in the wells. Do not discard. There are no wash steps between addition of reagents.
- Add 50 µL of HRP solution 5 U/mL (0.25 U) to each well.
NOTE: Use HRP before the addition of the fluorochrome reagent. - Incubate for 30 min at 37 °C. Do not discard samples after incubation (no wash steps between additions of reagents).
- Add 50 µL of fluorochromereagent for a final concentration of 300 µM. At this point, total reaction volume is 150 µL. Mix well and protect from light.
- Assess the fluorescent readout (in the dark) every minute over 120 min at 37 °C with a fluorescent plate reader (530/590 nm filters).
NOTE: Use a shorter 60-minute interval with fresh samples. We have found that 120-minute assay gives more reproducible data with the use of cryopreserved samples. - Record data using appropriate software.
8. Day 3-Data analysis
- Record fluorescence units (arbitrary units) at 120 minutes after addition of the fluorochrome Reagent for all the samples including blank wells and all controls.
- Calculate the mean value of fluorescence units (based on at least triplicates) (HDLox_sample). Do not take outliers (> 2 SDs from the average value) into consideration.
- Subtract the background fluorescence by using the following equation:
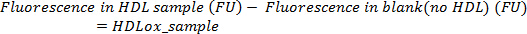
- Normalization for HDL cholesterol amount (HDL-C): Normalize the HDLox lipid peroxidation value for each sample (including the pooled control) by the HDL-C) (mg/dl). Throughout the results section, HDLox is presented as n(HDL-C) HDLox measure to reflect the adjustment for HDL-C. Use the following equation:
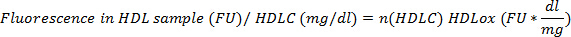
- Standardize the expression of HDLox lipid peroxidation value of each sample against the value of a pooled control. Normalize the n(HDL-C) HDLox lipid peroxidation value for each sample (adjusted for HDL-C) by the n(HDL-C) HDLox lipid peroxidation value of the pooled control. Throughout the results section, HDLox is presented as nHDLox measure to reflect the adjustment for experimental variability and HDL-C. Use the following equation:
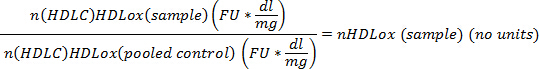
NOTE: This approach is similar to other established experimental approaches to reduce experimental variability of measurements such as international normalized ratio (INR)44,45. This approach has been validated in clinical studies32,33,34,35,36,37,38,39. - Perform quality control of experimental results using standard quality control samples. Each laboratory should establish their own quality controls (QCs). Ideally there is a QC for nHDLox from a sample with known dysfunctional HDL and a QC for nHDLox from a sample from healthy donors [e.g. use pooled sample from young adults who are established blood bank donors and have no known comorbidity and risk factors for cardiovascular disease including smoking]. The latter control standardizes results among different laboratories. The average values of these QCs are established based on at least 5 replicates (typically we use 10 replicates for this important step).
- Check whether measured QCs in each assay have values within the expected range of values. Assuming an acceptable maximum experimental variability of 15%, all the measured experimental values should fall within 15% of the known average values of established QC. Use the following equations:
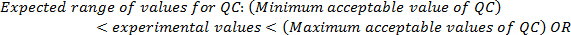
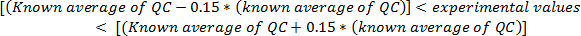
NOTE: If either of the included quality control samples (normal versus dysfunctional HDL) gives HDLox values outside expected range (established in each laboratory) then repeat the experiment.
- Check whether measured QCs in each assay have values within the expected range of values. Assuming an acceptable maximum experimental variability of 15%, all the measured experimental values should fall within 15% of the known average values of established QC. Use the following equations:
- Perform quality control of experimental results using the coefficient of variation (CV) to quantify experimental variability: Repeat all samples with CV% > 15%. Use the following equation:
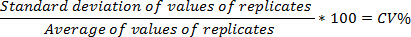
NOTE: A typical intra-assay (within the same plate) and inter-assay (among different plates) experimental variability is < 15%. 2) A typical intra-assay CV is between 1-7% and a typical interassay CV is between 3-10%.
Access restricted. Please log in or start a trial to view this content.
Results
50 µL of each HDL sample are added into each well as in step 7.3. 50 µL of HRP solution 5 U/mL (0.25 U) are then added into each well as in step 7.5. Samples are incubated for 30 min at 37 °C as in step 7.6. 50 µL of fluorochrome reagent are then added into each well as in step 7.7 (final concentration of 300 µM). The fluorescent readout (in dark) is then assessed every minute over 120 minutes at 37 °C with a fluorescent plate reader (530/590 nm filters). Representative fluorescence data ...
Access restricted. Please log in or start a trial to view this content.
Discussion
The protocol described here offers a robust tool to answer important research questions regarding the role of HDL function in atherosclerosis and human disease. The assay quantifies the HDL lipid peroxide content per mg of HDL-C using enzymatic amplification (HRP). This approach avoids known limitations of prior HDL function assays (e.g. the cholesterol efflux assay) including significant heterogeneity with regards to types of cells used, type of readout reported, lack of standardization and confounding effects of trigly...
Access restricted. Please log in or start a trial to view this content.
Disclosures
This protocol and assay are relevant to the patent PCT/US2015/018147.
Acknowledgements
The authors gratefully acknowledge the work of Dr Mohamad Navab, Alan Fogelman and Srinivasa Reddy for their key role in development of earlier iterations of this model. T.A.A. is supported by an RMIT University Vice-Chancellor's Postdoctoral Fellowship. AJ and AH are supported by NHMRC project grant 1108792. TK is supported by NIH grants NIH K08AI08272, NIH/NCATS Grant # µL1TR000124.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Experimental Reagents | |||
| HDL PEG (Polyethylene Glycol) Precipitating Reagent | Pointe Scientific | H7511 | |
| Amplex Red reagent. | Life Technologies, Grand Island, NY | A12216 | Amplex Red Cholesterol Assay Kit. • ≤–20°C • Desiccate • Protect from light |
| DMSO. | Life Technologies, Grand Island, NY | A12216 | Amplex Red Cholesterol Assay Kit. • ≤–20°C • Desiccate • Protect from light |
| Horse Radish Peroxidase (HRP) | Life Technologies, Grand Island, NY | A12216 | Amplex Red Cholesterol Assay Kit. • ≤–20°C • Desiccate • Protect from light |
| Cholesterol Esterase. | Life Technologies, Grand Island, NY | A12216 | Amplex Red Cholesterol Assay Kit. • ≤–20°C • Desiccate • Protect from light |
| Cholesterol Reference standard | Life Technologies, Grand Island, NY | A12216 | Amplex Red Cholesterol Assay Kit. • ≤–20°C • Desiccate • Protect from light |
| Resorufin fluorescense Reference standard | Life Technologies, Grand Island, NY | A12216 | Amplex Red Cholesterol Assay Kit. • ≤–20°C • Desiccate • Protect from light |
| 5x Reaction Buffer. | Life Technologies, Grand Island, NY | A12216 | Amplex Red Cholesterol Assay Kit. • ≤–20°C • Desiccate • Protect from light |
| HDL Cholesterol Automated Reagent | ThermoFisher Scientific Co., San Jose, CA, USA. | TR39601 | |
| Name | Company | Catalog Number | Comments |
| Plasticware | |||
| 96-well plates (polypropylene, flat bottom, clear). | Sigma Aldrich | M0687 | |
| 96-well plates (polypropylene, flat bottom, black). | Sigma Aldrich | M9936 | |
| 1.5 mL Eppendorf tubes | Eppendorf | 0030 125.150 | |
| ClipTip 200, sterile | ThermoFisher Scientific Co., San Jose, CA, USA. | 14-488-058 | |
| Thermo Scientific Multichannel Pipettes, 8-channel, 125 | ThermoFisher Scientific Co., San Jose, CA, USA. | 14-387--955 | |
| Name | Company | Catalog Number | Comments |
| Software | |||
| Gen5 2.01 software | Biotek, Vermont, USA | NA | |
| Name | Company | Catalog Number | Comments |
| Equipment | |||
| Gen5 Plate reader | Biotek, Vermont, USA | NA |
References
- Gordon, D. J., Rifkind, B. M. High-density lipoprotein--the clinical implications of recent studies. N Engl J Med. 321, 1311-1316 (1989).
- Rubins, H. B., et al. Gemfibrozil for the secondary prevention of coronary heart disease in men with low levels of high-density lipoprotein cholesterol. Veterans Affairs High-Density Lipoprotein Cholesterol Intervention Trial Study Group. N Engl J Med. 341, 410-418 (1999).
- Voight, B. F., et al. Plasma HDL cholesterol and risk of myocardial infarction: a mendelian randomisation study. Lancet. 380, 572-580 (2012).
- Navab, M., Reddy, S. T., Van Lenten, B. J., Fogelman, A. M. HDL and cardiovascular disease: atherogenic and atheroprotective mechanisms. Nat.Rev Cardiol. 8, 222-232 (2011).
- Navab, M., et al. The double jeopardy of HDL. Ann Med. 37, 173-178 (2005).
- Navab, M., Reddy, S. T., Van Lenten, B. J., Anantharamaiah, G. M., Fogelman, A. M. The role of dysfunctional HDL in atherosclerosis. J Lipid Res. 50, Suppl . S145-S149 (2009).
- Navab, M., Reddy, S. T., Van Lenten, B. J., Fogelman, A. M. HDL and cardiovascular disease: atherogenic and atheroprotective mechanisms. Nat Rev Cardiol. 8, 222-232 (2011).
- Patel, S., et al. Reconstituted high-density lipoprotein increases plasma high-density lipoprotein anti-inflammatory properties and cholesterol efflux capacity in patients with type 2 diabetes. J Am Coll Cardiol. 53, 962-971 (2009).
- Navab, M., et al. HDL and the inflammatory response induced by LDL-derived oxidized phospholipids. Arterioscler Thromb Vasc Biol. 21, 481-488 (2001).
- Hayek, T., Oiknine, J., Brook, J. G., Aviram, M. Role of HDL apolipoprotein E in cellular cholesterol efflux: studies in apo E knockout transgenic mice. Biochem Biophys Res Commun. 205, 1072-1078 (1994).
- Van Lenten, B. J., et al. Anti-inflammatory HDL becomes pro-inflammatory during the acute phase response. Loss of protective effect of HDL against LDL oxidation in aortic wall cell cocultures. J Clin Invest. 96, 2758-2767 (1995).
- Undurti, A., et al. Modification of high density lipoprotein by myeloperoxidase generates a pro-inflammatory particle. J Biol Chem. 284, 30825-30835 (2009).
- Van Lenten, B. J., et al. Lipoprotein inflammatory properties and serum amyloid A levels but not cholesterol levels predict lesion area in cholesterol-fed rabbits. J Lipid Res. 48, 2344-2353 (2007).
- Watson, C. E., et al. Treatment of patients with cardiovascular disease with L-4F, an apo-A1 mimetic, did not improve select biomarkers of HDL function. J Lipid Res. 52, 361-373 (2011).
- Annema, W., et al. Impaired HDL cholesterol efflux in metabolic syndrome is unrelated to glucose tolerance status: the CODAM study. Sci Rep. 6, 27367(2016).
- Movva, R., Rader, D. J. Laboratory assessment of HDL heterogeneity and function. Clin Chem. 54, 788-800 (2008).
- Charles-Schoeman, C., et al. Abnormal function of high-density lipoprotein is associated with poor disease control and an altered protein cargo in rheumatoid arthritis. Arthritis Rheum. 60, 2870-2879 (2009).
- Imaizumi, S., et al. L-4F differentially alters plasma levels of oxidized fatty acids resulting in more anti-inflammatory HDL in mice. Drug Metab Lett. 4, 139-148 (2010).
- Khera, A. V., et al. Cholesterol efflux capacity, high-density lipoprotein function, and atherosclerosis. N Engl J Med. 364, 127-135 (2011).
- Morgantini, C., et al. Anti-inflammatory and antioxidant properties of HDLs are impaired in type 2 diabetes. Diabetes. 60, 2617-2623 (2011).
- Patel, P. J., Khera, A. V., Jafri, K., Wilensky, R. L., Rader, D. J. The anti-oxidative capacity of high-density lipoprotein is reduced in acute coronary syndrome but not in stable coronary artery disease. J Am Coll Cardiol. 58, 2068-2075 (2011).
- Watanabe, J., et al. Proteomic profiling following immunoaffinity capture of high-density lipoprotein: association of acute-phase proteins and complement factors with proinflammatory high-density lipoprotein in rheumatoid arthritis. Arthritis Rheum. 64, 1828-1837 (2012).
- Watanabe, J., et al. Differential association of hemoglobin with proinflammatory high density lipoproteins in atherogenic/hyperlipidemic mice. A novel biomarker of atherosclerosis. J Biol Chem. 282, 23698-23707 (2007).
- Watanabe, J., et al. Hemoglobin and its scavenger protein haptoglobin associate with apoA-1-containing particles and influence the inflammatory properties and function of high density lipoprotein. J Biol Chem. 284, 18292-18301 (2009).
- Wang, X. S., et al. A sensitive and specific ELISA detects methionine sulfoxide-containing apolipoprotein A-I in HDL. J Lipid Res. 50, 586-594 (2009).
- Navab, M., et al. A cell-free assay for detecting HDL that is dysfunctional in preventing the formation of or inactivating oxidized phospholipids. J Lipid Res. 42, 1308-1317 (2001).
- Kelesidis, T., et al. A biochemical fluorometric method for assessing the oxidative properties of HDL. J Lipid Res. 52, 2341-2351 (2011).
- Kelesidis, T., et al. Effects of lipid-probe interactions in biochemical fluorometric methods that assess HDL redox activity. Lipids Health Dis. 11, 87(2012).
- Navab, M., et al. Mechanisms of disease: proatherogenic HDL--an evolving field. Nat Clin Pract Endocrinol Metab. 2, 504-511 (2006).
- Navab, M., et al. The oxidation hypothesis of atherogenesis: the role of oxidized phospholipids and HDL. J Lipid Res. 45, 993-1007 (2004).
- Morgantini, C., et al. HDL lipid composition is profoundly altered in patients with type 2 diabetes and atherosclerotic vascular disease. Nutr Metab Cardiovasc Dis. 24, 594-599 (2014).
- Kelesidis, T., et al. A high throughput biochemical fluorometric method for measuring lipid peroxidation in HDL. PLoS One. 9, e111716(2014).
- Kelesidis, T., Yang, O. O., Kendall, M. A., Hodis, H. N., Currier, J. S. Dysfunctional HDL and progression of atherosclerosis in HIV-1-infected and -uninfected adults. Lipids Health Dis. 12, 23(2013).
- Zanni, M. V., et al. HDL redox activity is increased in HIV-infected men in association with macrophage activation and non-calcified coronary atherosclerotic plaque. Antivir Ther. 19, 805-811 (2014).
- Roberts, C. K., Katiraie, M., Croymans, D. M., Yang, O. O., Kelesidis, T. Untrained young men have dysfunctional HDL compared with strength-trained men irrespective of body weight status. J Appl Physiol (1985). , 1043-1049 (2013).
- Davidson, W. S., et al. Weight loss surgery in adolescents corrects high-density lipoprotein subspecies and their function. Int J Obes (Lond). 41, 83-89 (2017).
- Kelesidis, T., et al. Predictors of impaired HDL function in HIV-1 infected compared to uninfected individuals. J Acquir Immune Defic Syndr. , (2017).
- Kelesidis, T., et al. Oxidized lipoproteins are associated with markers of inflammation and immune activation in HIV-1 infection. AIDS. 30, 2625-2633 (2016).
- Kelesidis, T., et al. Changes in plasma levels of oxidized lipoproteins and lipoprotein subfractions with atazanavir-, raltegravir-, darunavir-based initial antiviral therapy and associations with common carotid artery intima-media thickness: ACTG 5260s. Antivir Ther. , (2016).
- Bhattacharyya, D. K., Adak, S., Bandyopadhyay, U., Banerjee, R. K. Mechanism of inhibition of horseradish peroxidase-catalysed iodide oxidation by EDTA. Biochem J. 295 (Pt 2), 281-288 (1994).
- Rees, M. D., Pattison, D. I., Davies, M. J. Oxidation of heparan sulphate by hypochlorite: role of N-chloro derivatives and dichloramine-dependent fragmentation. Biochem J. 391, 125-134 (2005).
- Mani, K., Cheng, F., Fransson, L. A. Heparan sulfate degradation products can associate with oxidized proteins and proteasomes. J Biol Chem. 282, 21934-21944 (2007).
- Finley, P. R., Schifman, R. B., Williams, R. J., Lichti, D. A. Cholesterol in high-density lipoprotein: use of Mg2+/dextran sulfate in its enzymic measurement. Clin Chem. 24, 931-933 (1978).
- von Schenck, H., Jacobsson, M. L. Prothrombin assay standardized with an international normalization ratio (INR): goal and reality. Clin Chem. 33, 342(1987).
- de Kok, J. B., et al. Normalization of gene expression measurements in tumor tissues: comparison of 13 endogenous control genes. Lab Invest. 85, 154-159 (2005).
- Stocker, R., Keaney, J. F. Jr Role of oxidative modifications in atherosclerosis. Physiol Rev. 84, 1381-1478 (2004).
- Holzer, M., et al. Aging affects high-density lipoprotein composition and function. Biochim Biophys Acta. 1831, 1442-1448 (2013).
- Amundson, D. M., Zhou, M. Fluorometric method for the enzymatic determination of cholesterol. J Biochem Biophys Methods. 38, 43-52 (1999).
- Mishin, V., Gray, J. P., Heck, D. E., Laskin, D. L., Laskin, J. D. Application of the Amplex red/horseradish peroxidase assay to measure hydrogen peroxide generation by recombinant microsomal enzymes. Free Radic Biol Med. 48, 1485-1491 (2010).
- Lombardi, A., et al. UCP3 translocates lipid hydroperoxide and mediates lipid hydroperoxide-dependent mitochondrial uncoupling. J Biol Chem. 285, 16599-16605 (2010).
- Bhattacharya, A., et al. Denervation induces cytosolic phospholipase A2-mediated fatty acid hydroperoxide generation by muscle mitochondria. J Biol Chem. 284, 46-55 (2009).
- Havel, R. J., Eder, H. A., Bragdon, J. H. The distribution and chemical composition of µLtracentrifugally separated lipoproteins in human serum. J Clin Invest. 34, 1345-1353 (1955).
- Dyerberg, J. Comments on the quantitation of lipoproteins by agarose-gel electrophoresis. Clin Chim Acta. 61, 103-104 (1975).
- Warnick, G. R., Cheung, M. C., Albers, J. J. Comparison of current methods for high-density lipoprotein cholesterol quantitation. Clin Chem. 25, 596-604 (1979).
- Demacker, P. N., Hijmans, A. G., Vos-Janssen, H. E., van't Laar, A., Jansen, A. P. A study of the use of polyethylene glycol in estimating cholesterol in high-density lipoprotein. Clin Chem. 26, 1775-1779 (1980).
- Izzo, C., Grillo, F., Murador, E. Improved method for determination of high-density-lipoprotein cholesterol I. Isolation of high-density lipoproteins by use of polyethylene glycol 6000. Clin Chem. 27, 371-374 (1981).
- Patel, P. J., Khera, A. V., Wilensky, R. L., Rader, D. J. Anti-oxidative and cholesterol efflux capacities of high-density lipoprotein are reduced in ischaemic cardiomyopathy. Eur J Heart Fail. 15, 1215-1219 (2013).
- Roche, M., Rondeau, P., Singh, N. R., Tarnus, E., Bourdon, E. The antioxidant properties of serum albumin. FEBS Lett. 582, 1783-1787 (2008).
- Panzenbock, U., Kritharides, L., Raftery, M., Rye, K. A., Stocker, R. Oxidation of methionine residues to methionine sulfoxides does not decrease potential antiatherogenic properties of apolipoprotein A-I. J Biol Chem. 275, 19536-19544 (2000).
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
