Simple and accessible methods were developed to measure the motor aspect of cancer-related fatigue objectively and quantitatively. We describe, in detail, ways to administer the physical fatigue test using a simple handgrip device as well as methods to calculate fatigue indices.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Method Article
Measuring the Motor Aspect of Cancer-Related Fatigue using a Handheld Dynamometer
In This Article
Summary
Abstract
Cancer-related fatigue (CRF) is commonly reported by patients both during and after receiving treatment for cancer. Current CRF diagnoses rely on self-report questionnaires which are subject to report and recall biases. Objective measurements using a handheld dynamometer, or handgrip device, have been shown in recent studies to correlate significantly with subjective self-reported fatigue scores. However, variations of both the handgrip fatigue test and fatigue index calculations exist in the literature. The lack of standardized methods limits the utilization of the handgrip fatigue test in the clinical and research settings. In this study, we provide detailed methods for administering the physical fatigue test and calculating the fatigue index. These methods should supplement existing self-reported fatigue questionnaires and help clinicians assess fatigue symptom severity in an objective and quantitative manner.
Introduction
Cancer-related fatigue (CRF) is an prevalent and debilitating symptom that is reported by up to 80% of cancer patients1. The National Comprehensive Cancer Network (NCCN) defines CRF as a persistent sense of physical, emotional, and cognitive exhaustion1. The main differentiating characteristics of CRF are the disproportionality to recent activity and the inability of CRF to be relieved by rest1. As a result, CRF severely impacts patients' participation in daily activities and their health-related quality of life1.
The current assessment of CRF relies primarily on self-report questionnaires2. As a result, symptom severity which is measured using self-reports is subject to recall and reporting biases and can be influenced by the specific questionnaire and cutoff scores used to assess CRF3. As a multidimensional construct, the physical dimension of CRF has been shown to correlate with daily activity changes and a need for daytime naps4, whereas the influence of CRF on physical functioning is less explored. To this date, CRF remains an underdiagnosed and undertreated symptom with no well-defined underlying mechanism or treatment option1. To better understand this debilitating condition, there is an increasing need to measure CRF and its dimensions objectively and quantitatively.
Physical fatigue refers to an inability to maintain the required force during sustained contractile activity5. The subsequent compromised daily functioning as a result of not being able to carry out daily tasks (e.g., carrying grocery bags, lifting and holding an object) greatly affects the health-related quality of life, especially in older adults, and contributes to future injuries6,7. Various tools have been developed to quantify physical impairment including physical performance tests, such as the 6 min walk test (6MWT) and sit-to-stand test (STS), as well as wearable physical activity monitors, such as actigraphy devices and fitness trackers8,9,10. Physical performance tests such as 6MWT and STS are easy to administer and do not require special equipment10. However, the reliability and success of such tests require clinician training and logistical requirements such as a 30 m corridor10. Wearable activity monitors allow for automated data collection and longitudinal symptom monitoring11. However, these activity monitors often need to be worn for multiple days, and patient compliance can be an issue11. In addition, the large amount of data collected using activity monitors can be challenging to process, making it difficult to derive clinically meaningful information11.
The handheld dynamometer, or instrumented handgrip device with computer-assisted data acquisition, is a portable apparatus that measures grip strength. Handheld dynamometry has been used to test motor fatigue and impairment in disease conditions that typically involve the motor system including motor neurons and muscular problems12. Recent work has demonstrated an association between self-reported subjective CRF scores and motor fatigue measured using a handgrip static fatigue test13. Handgrip fatigue tests are particularly suitable for clinical use due to their reliability and time efficiency, requiring a few minutes to complete14,15. Furthermore, handgrip fatigue tests can be pre-programed, ensuring data reproducibility7. Administering the handgrip test requires minimal training on the part of the test administrator and can be easily implemented in a clinical setting given a standardized protocol. Using self-reported fatigue questionnaires in conjunction with the handgrip fatigue test should provide additional tools for clinicians to screen, monitor, and manage fatigue symptoms in cancer patients.
The lack of standardized consensus methods has limited the adoption of the handgrip fatigue test in the clinics16. In this current work, we outline three different methods to use the handheld dynamometer to quantify motor fatigue objectively. The utility of each method should be tested in each cancer population to ensure it accurately distinguishes between fatigued and non-fatigued subjects. We also outline methods to calculate the fatigue index for each handgrip fatigue test. The goal of this work is to provide a comprehensive toolkit to supplement self-reported questionnaires and to standardize CRF physical performance measurement accurately and objectively.
Access restricted. Please log in or start a trial to view this content.
Protocol
The current study (NCT00852111) was approved by the Institutional Review Board (IRB) of the National Institutes of Health (NIH). Participants enrolled in this study were 18 years of age or older, diagnosed with non-metastatic prostate cancer with or without prior prostatectomy, and scheduled to receive external beam radiation therapy at the Radiation Oncology Clinic of the NIH Clinical Center. Potential participants were excluded if they had a progressive disease that could cause significant fatigue, had psychiatric disease within the past five years, had uncorrected hypothyroidism or anemia, or had a second malignancy. Individuals who used sedatives, steroids, or non-steroidal anti-inflammatory agents were also excluded. All participants were recruited at the Magnuson Clinical Research Center at the NIH. Signed written informed consents were obtained prior to study participation.
1. Handgrip preparation and testing position
- In a quiet room, set up a chair with armrests.
- Turn on the handheld dynamometer.
- The software will prompt calibration of the dynamometer. Ensure the device is resting on a flat surface during calibration.
- Seat the subject in an upright position with their feet in full contact with the floor and hips as far back as the chair supports.
- Ensure the subject's hip and knee angles are close to 90° and shoulders are in neutral abduction/adduction and neutrally rotated. Ensure the subject's elbow is flexed at 90° and the wrist is unsupported, as recommended by the American Society of Hand Therapists handbook17.
- After calibrating the dynamometer, instruct the subject to grasp the dynamometer, with the dorsal intermediate phalanges facing forward.
- Adjust the grip position to the subject's hand size and record it7.
- Maintain the same handgrip testing position for all subsequent tests.
- Prior to each test, provide standardized scripts and ask subjects to perform a mock attempt to demonstrate understanding of the instructions.
- Inform the subjects that discomfort is normal, but the tests can be discontinued in the presence of unexpectedly severe strain/pain.
- Stop the test if severe discomfort is reported by the patient or in the event of unexpected circumstances.
- Ensure a 2 min rest period between trials to allow the muscle to recover18.
2. Maximal voluntary isometric contraction (MVIC) test
- Provide subjects with standardized instructions. For example, "in the test, you will squeeze as hard as you can for 5 s, starting with your non-dominant hand. This test will be done three times for each hand. For each test, I will count down 3, 2, 1...GO. Squeeze the device on GO as hard as you can."
- On "Go", start the program by clicking on the GO button.
- Repeat the MVIC test for a total of three times with a 30 s rest between trials.
- The average for each hand from the three trials maximum force is the MVIC19.
3. Maximum force static fatigue test
- Instruct subjects to exert full effort to achieve maximal contraction during the static fatigue test.
- On "Go", start the program by clicking on the GO button. Use standardized encouragement script such as squeeze hard repeatedly until the test ends.
- Continue the static fatigue test for 35 s, so as to provide up to 5 s to achieve Fmax (maximal handgrip strength).
- Static fatigue index (SFI)12,20,21
- Calculate SFI using the following equation:
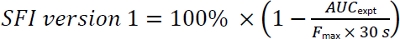
- Calculate AUCexpt by computing the experimental area under the curve from the time that Fmax was achieved (Tmax) to 30 s after Tmax.
- Calculate the hypothetical AUC (AUChypothetical) in the absence of fatigue by multiplying the Fmax by 30 s.
NOTE: Higher SFI values indicate increased divergence from the expected value, hence higher fatigue. - Calculate SFI version 2 as the ratio of the maximal force during the last 5 s (Fmax 25-30s) to the maximal force in the first 5 seconds (Fmax 0-5s) using the equation:
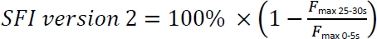
NOTE: Higher values of SFI indicate higher fatigue.
- Calculate SFI using the following equation:
4. Sub-maximum force static fatigue test
- Indicate the value of 50% of the MVIC of the participant's non-dominant hand by drawing a horizontal line on a transparency overlay of the screen.
- Draw a second line on the overlay in a different color to indicate a 10% decline of the target value.
- Ensure the participant can easily see the screen and 50% MVIC line.
- Instruct the subject to maintain a target value of 50% of MVIC for as long as possible.
- Count down. On "Go", start the program by clicking on the GO button.
- Stop the test when the strength declines by 10% of the target value for more than 5 s as indicated by the second line on the transparency.
- Calculate total work performed7 as the force-versus-time area under the curve over the period of time during which the target force (T50% MVIC) is sustained:
Total work = AUC during T50% MVIC
NOTE: Endurance can be measured as time to task completion22. Higher values of total work indicate lower fatigue.
5. Dynamic fatigue test
- Instruct subjects to perform a maximal squeeze every second for a duration of 30 s. Use a metronome to provide rhythm guidance20.
- Start the metronome which is set at 1 beep per second.
- Start the countdown. On "Go", start the test by clicking on the GO button. Ensure the countdown matches the rate of the metronome.
- Inform the participant when passing the halfway point and when 5 s are remaining.
- Stop test after the 30 s are completed.
- Dynamic Fatigue Index
- Calculate the Dynamic Fatigue Index20 using the maximal force (Fmax) of the last 5 s and the Fmax of the first 5 s.
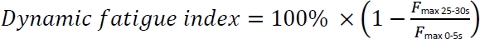
NOTE: Higher values of the dynamic fatigue index (DFI) indicate higher fatigue.
- Calculate the Dynamic Fatigue Index20 using the maximal force (Fmax) of the last 5 s and the Fmax of the first 5 s.
Access restricted. Please log in or start a trial to view this content.
Results
Representative force (kg) versus time (s) traces are shown in Figure 1. During the static fatigue test, subjects typically reach maximal strength (Fmax) within 2–3 s23. Self-reported fatigue in subjects was measured based on previous studies3. The absence of Fmax (±10% MVIC) within 3 s indicates insufficient effort23. To prevent this issue, verbal encouragement should be provided. Both subjects repo...
Access restricted. Please log in or start a trial to view this content.
Discussion
Here, we provide three different methods for measuring the physical dimension of CRF. Motor fatigue tests using handheld dynamometers are simple and easily adaptable for clinical use. Since many variations of the test exist in the literature, our goal was to provide standardized methods to administer these tests and decrease the need for extensive in-person trainings for clinicians.
Although the fatigue tests outlined in this study demonstrate good test-retest reliability7
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors have nothing to disclose.
Acknowledgements
This study is fully supported by the Division of Intramural Research of the National Institute of Nursing Research of the NIH, Bethesda, Maryland.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Quantitative Muscle Assessment application (QMA) | Aeverl Medical | QMA 4.6 | Data acquisition software. NOTE: other brands/models can be used as long as the software records force over time. |
| QMA distribution box | Aeverl Medical | DSTBX | Software distribution box which connects the handgrip to the software. |
| Baseline hand dynamometer with analog output | Aeverl Medical | BHG | Instrumented handgrip device with computer assisted data acquisition. NOTE: other brands/models can be used as long as the instrument measures force over time |
References
- Berger, A. M., et al. Cancer-Related Fatigue, Version 2.2015. Journal of the National Comprehensive Cancer Network : JNCCN. 13 (8), 1012-1039 (2015).
- Campos, M. P. O., Hassan, B. J., Riechelmann, R., Del Giglio, A. Cancer-related fatigue: a practical review. Annals of Oncology. 22 (6), 1273-1279 (2011).
- Feng, L. R., Dickinson, K., Kline, N., Saligan, L. N. Different phenotyping approaches lead to dissimilar biologic profiles in men with chronic fatigue following radiation therapy. Journal of Pain and Symptom Management. 52 (6), 832-840 (2016).
- Minton, O., Stone, P. C. A comparison of cognitive function, sleep and activity levels in disease-free breast cancer patients with or without cancer-related fatigue syndrome. BMJ Supportive & Palliative Care. 2, 231-238 (2012).
- Wan, J. J., Qin, Z., Wang, P. Y., Sun, Y., Liu, X. Muscle fatigue: general understanding and treatment. Experimental & Molecular Medicine. 49 (10), 384(2017).
- Bautmans, I., Gorus, E., Njemini, R., Mets, T. Handgrip performance in relation to self-perceived fatigue, physical functioning and circulating IL-6 in elderly persons without inflammation. BMC geriatrics. 7, 5-5 (2007).
- Gerodimos, V., Karatrantou, K., Psychou, D., Vasilopoulou, T., Zafeiridis, A. Static and Dynamic Handgrip Strength Endurance: Test-Retest Reproducibility. The Journal of Hand Surgery. 42 (3), 175-184 (2017).
- van der Werf, S. P., Prins, J. B., Vercoulen, J. H. M. M., van der Meer, J. W. M., Bleijenberg, G. Identifying physical activity patterns in chronic fatigue syndrome using actigraphic assessment. Journal of Psychosomatic Research. 49 (5), 373-379 (2000).
- Connaughton, J., Patman, S., Pardoe, C. Are there associations among physical activity, fatigue, sleep quality and pain in people with mental illness? A pilot study. Journal of Psychiatric and Mental Health Nursing. 21 (8), 738-745 (2014).
- Gurses, H. N., Zeren, M., Denizoglu Kulli, H., Durgut, E. The relationship of sit-to-stand tests with 6-minute walk test in healthy young adults. Medicine. 97 (1), 9489(2018).
- Beg, M. S., Gupta, A., Stewart, T., Rethorst, C. D. Promise of Wearable Physical Activity Monitors in Oncology Practice. Journal of Oncology Practice. 13 (2), 82-89 (2017).
- Severijns, D., Lamers, I., Kerkhofs, L., Feys, P. Hand grip fatigability in persons with multiple sclerosis according to hand dominance and disease progression. Journal of Rehabilitation Medicine. 47 (2), 154-160 (2015).
- Feng, L. R., et al. Cognitive and motor aspects of cancer-related fatigue. Cancer Medicine. 8 (13), 5840-5849 (2019).
- Bohannon, R. W. Hand-Grip Dynamometry Predicts Future Outcomes in Aging Adults. Journal of Geriatric Physical Therapy. 31 (1), 3-10 (2008).
- Reuter, S. E., Massy-Westropp, N., Evans, A. M. Reliability and validity of indices of hand-grip strength and endurance. Australian Occupational Therapy Journal. 58 (2), 82-87 (2011).
- Roberts, H. C., et al. A review of the measurement of grip strength in clinical and epidemiological studies: towards a standardised approach. Age and Ageing. 40 (4), 423-429 (2011).
- American Society of Hand Therapists. Clinical Assessment Recommendations. 2nd edn. , (1992).
- Bhuanantanondh, P., Nanta, P., Mekhora, K. Determining Sincerity of Effort Based on Grip Strength Test in Three Wrist Positions. Safety and Health at Work. 9 (1), 59-62 (2018).
- van Meeteren, J., van Rijn, R. M., Selles, R. W., Roebroeck, M. E., Stam, H. J. Grip strength parameters and functional activities in young adults with unilateral cerebral palsy compared with healthy subjects. Journal of Rehabilitation Medicine. 39 (8), 598-604 (2007).
- Meldrum, D., Cahalane, E., Conroy, R., Guthrie, R., Hardiman, O. Quantitative assessment of motor fatigue: normative values and comparison with prior-polio patients. Amyotrophic Lateral Sclerosis. 8 (3), 170-176 (2007).
- Schwid, S. R., et al. Quantitative assessment of motor fatigue and strength in MS. Neurology. 53, 743-743 (1999).
- Hunter, S. K., Critchlow, A., Shin, I. S., Enoka, R. M. Men are more fatigable than strength-matched women when performing intermittent submaximal contractions. Journal of Applied Physiology. 96 (6), 2125-2132 (2004).
- Karatrantou, K. Dynamic Handgrip Strength Endurance: A Reliable Measurement in Older Women. Journal of Geriatric Physical Therapy. 42 (3), 51-56 (2019).
- The National Isometric Muscle Strength Database. Muscular weakness assessment: Use of normal isometric strength data. Archives of Physical Medicine and Rehabilitation. 77 (12), 1251-1255 (1996).
- Desrosiers, J., Bravo, G., Hébert, R. Isometric grip endurance of healthy elderly men and women. Archives of Gerontology and Geriatrics. 24 (1), 75-85 (1997).
- White, C., Dixon, K., Samuel, D., Stokes, M. Handgrip and quadriceps muscle endurance testing in young adults. SpringerPlus. 2 (1), 451(2013).
- Trajano, G., Pinho, C., Costa, P., Oliveira, C. Static stretching increases muscle fatigue during submaximal sustained isometric contractions. Journal of Sports Medicine and Physical Fitness. 55 (1-2), 43-50 (2015).
- Liu, J. Z., et al. Human Brain Activation During Sustained and Intermittent Submaximal Fatigue Muscle Contractions: An fMRI Study. Journal of Neurophysiology. 90 (1), 300-312 (2003).
- Demura, S., Yamaji, S. Influence of grip types and intensities on force-decreasing curves and physiological responses during sustained muscle contractions. Sport Sciences for Health. 3 (1), 33-40 (2008).
- Matuszczak, Y., et al. Effects of N-acetylcysteine on glutathione oxidation and fatigue during handgrip exercise. Muscle & Nerve. 32 (5), 633-638 (2005).
- Medved, I., et al. N-acetylcysteine infusion alters blood redox status but not time to fatigue during intense exercise in humans. Journal of Applied Physiology. 94 (4), 1572-1582 (2003).
- Löscher, W. N., Cresswell, A. G., Thorstensson, A. Excitatory drive to the alpha-motoneuron pool during a fatiguing submaximal contraction in man. The Journal of Physiology. 491 (1), 271-280 (1996).
- Taylor, J. L., Allen, G. M., Butler, J. E., Gandevia, S. C. Supraspinal fatigue during intermittent maximal voluntary contractions of the human elbow flexors. Journal of Applied Physiology. 89 (1), 305-313 (2000).
- Fulco, C. S., et al. Slower fatigue and faster recovery of the adductor pollicis muscle in women matched for strength with men. Acta Physiologica Scandinavica. 167 (3), 233-239 (1999).
- Gonzales, J. U., Scheuermann, B. W. Absence of gender differences in the fatigability of the forearm muscles during intermittent isometric handgrip exercise. Journal of Sports Science & Medicine. 6 (1), 98-105 (2007).
- Liepert, J., Mingers, D., Heesen, C., Bäumer, T., Weiller, C. Motor cortex excitability and fatigue in multiple sclerosis: a transcranial magnetic stimulation study. Multiple Sclerosis Journal. 11 (3), 316-321 (2005).
- Kim, J., Yim, J. Effects of an Exercise Protocol for Improving Handgrip Strength and Walking Speed on Cognitive Function in Patients with Chronic Stroke. Medical science monitor : international medical journal of experimental and clinical research. 23, 5402-5409 (2017).
- Schnelle, J. F., et al. et al Evaluation of Two Fatigability Severity Measures in Elderly Adults. Journal of the American Geriatrics Society. 60 (8), 1527-1533 (2012).
- Enoka, R. M., Duchateau, J. Translating Fatigue to Human Performance. Medicine and science in sports and exercise. 48 (11), 2228-2238 (2016).
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
