This study describes a model of acute lung injury following visceral ischemia-reperfusion during supra-celiac aortic cross-clamping via laparotomy in rats. It enables the investigation of both the clinical and biological effects of aortic clamping as well as the impact of ischemia-reperfusion on underlying organs and remote lung injuries.
Method Article
A Model of Acute Lung Injury Following Visceral Ischemia-Reperfusion by Supra-Coeliac Aortic Cross Clamping in Rats
In This Article
Summary
Abstract
Open surgery for abdominal aortic aneurysms requires transient interruption of blood circulation, causing ischemia-reperfusion of downstream organs. Renal, mesenteric, and splanchnic arteries may be involved. No therapy has proven effective in preventing remote lung injury caused by ischemia-reperfusion after supra-coeliac aortic clamping. To study the pathophysiological pathways of acute lung injury and pharmacological treatments, an experimental model of aortic clamping has been developed in rats.
Subcutaneous analgesia with Buprenorphine (0.05 mg/kg) is administered before the procedure. General anesthesia with spontaneous ventilation is induced using halogen gas (Isoflurane 2.5%) via a mask. A xypho-pubic laparotomy is performed on a heated table (temperature monitored intrarectally). The gastro-splenic block and intestines are retracted to the right flank, and the liver is mobilized to the upper abdomen. The diaphragm and its pillars are identified to allow step-by-step release of the supra-coeliac aorta from its intradiaphragmatic passage. Dissection is performed gently to achieve circumferential control of the aorta between the diaphragm pillars. The underlying celiac trunk and superior mesenteric artery are carefully identified. A microvascular clamp may be used for aortic occlusion above the visceral arteries. Proper clamping is verified by the absence of aortic pulsatility, associated with pallor of the small intestine. The rat remains anesthetized throughout the ischemia duration. At the end of the ischemia duration, the microclamp is removed, and aortic pulsatility, as well as intestinal recoloration, are checked. The abdominal wall is closed with a suture, followed by closure of the rat's skin. At the end of the reperfusion period, the animal is anesthetized in the same manner. It is euthanized by exsanguination during blood sampling, and the lung can then be collected. Lung injury can be assessed through blood gas analysis, lung gravimetry, and histological examination. Lung samples can also be utilized for RT-PCR and Western blot analyses.
Introduction
An aortic aneurysm is a focal and permanent dilation of the aorta1. The evolution of an aneurysm tends towards rupture, associated with massive hemorrhage, which carries significant mortality2. Therefore, the focus of treatment lies in the prevention of this dramatic complication. Aortic aneurysms are most often infrarenal and can be treated with aortic endoprosthesis. An aorto-bi-iliac endograft is a covered bifurcated stent that is introduced in a minimally invasive manner through the femoral arteries using a percutaneous approach. This technique does not require aortic clamping and avoids causing visceral ischemia. It can be performed under local anesthesia. In contrast, more extensive aortic aneurysms-such as thoracoabdominal aneurysms and complex abdominal aortic aneurysms-are more challenging to treat using endovascular techniques. This is due to the involvement of the renal arteries, the superior mesenteric artery, and the celiac trunk within the aneurysmal segment (Figure 1). These major visceral arteries must be reconstructed in addition to the aorta itself. The endovascular, minimally invasive approach therefore, requires a more complex procedure involving the use of fenestrated and/or branched endografts for visceral artery reconstruction. The main limitation of these endografts is the long manufacturing time -- often several months -- making them unsuitable for emergency treatment. In such cases, conventional open surgical repair remains a feasible and reliable option.
The treatment by open repair requires laparotomy and supra-visceral clamping, i.e., temporary visceral ischemia. The complication rate is high during the treatment of these thoracoabdominal aneurysms. Mortality ranges from 5 to 15%3. Pulmonary complications occur in 60% and renal complications in 40%4. These complications, associated with a systemic inflammatory response, can progress to multi-visceral failure5. This morbi-mortality is multifactorial, involving surgical aggression, anesthesia, analgesia, hemodynamic variations, hemorrhagic shock, and ischemia-reperfusion phenomena. Surgical aggression contributes to the manifestation of complications, whether the approach includes thoracotomy, phrenotomy, lumbotomy, or laparotomy, by modifying the ventilatory mechanics, with in particular an impairment of the diaphragmatic function6.
The temporary visceral ischemia reperfusion affects downstream organs, including the digestive tract, splanchnic system, kidneys, and lower limbs7. Pulmonary complications are the most frequent adverse events following thoracoabdominal aortic surgery. Their origin is multifactorial. Supraceliac aortic clamping does not directly cause pulmonary ischemia-reperfusion. However, ischemia-reperfusion of the downstream visceral organs triggers a major systemic inflammatory response. The hypothesis of a causal link between visceral ischemia-reperfusion and the occurrence of remote injury -- particularly lung damage -- is well supported. Pulmonary endothelial dysfunction, a critical component of the alveolar-capillary membrane, appears to be central to the development of Acute Lung Injury (ALI). A massive systemic inflammatory response and the activation of neutrophils play a pivotal role in this process.
ALI is often defined based on histological criteria rather than clinical presentation. ALI refers to an acute inflammatory disorder characterized by the disruption of the pulmonary endothelial and epithelial barriers. The alveolar-capillary membrane, the functional unit of the lung, consists of three components: the microvascular endothelium, the interstitial space, and the alveolar epithelium.
A hallmark of ALI is increased permeability of this barrier, driven by neutrophil infiltration and the release of cytotoxic pro-inflammatory mediators. Alveolar epithelial damage involves both type I and type II pneumocytes. Type I cells, which cover 95% of the alveolar surface, are highly susceptible to injury and play a key role in gas exchange. Type II cells, more numerous but covering a smaller area, are essential for surfactant production, epithelial repair, and ion transport. Following injury, type II cells contribute to the restoration of alveolar integrity through their regenerative capacity and differentiation into type I cells.
Multiple cell death pathways have been implicated in epithelial injury during ALI, with type I cells being particularly vulnerable. ALI is commonly assessed by evaluating pulmonary edema, with or without measures of microvascular permeability to reflect endothelial dysfunction.
The objective of this model is to investigate the link between visceral ischemia-reperfusion and the development of remote lung injury, both at the metabolic and mechanistic levels as illustrated on Figure 2. This specific connection remains only partially understood. Our aortic clamping model represents a visceral ischemia-reperfusion scenario on a healthy aorta, without the presence of an abdominal aortic aneurysm in rat. Above the celiac trunk, there are no major branches in either humans or rats. The aorta above this level corresponds to the supra-cœliac aorta, which gives rise only to small parietal branches supplying the thoracic wall. Therefore, there is no significant difference in the vascular anatomy of the major vessels at this level between humans and rats.
The use of this model allows for extensive exploration. It will help identify early biomarkers in the development of remote tissue injury. Additionally, this model enables the study of potential inhibitors, including inhibitors of circulating mediators or inhibitors of specific remote organs injuries.
Other ischemia-reperfusion models are used to study remote injuries. Cerebral, intestinal, and renal ischemia-reperfusion models are strongly represented8,9,10. There is extensive research on pulmonary damage after intestinal ischemia-reperfusion due to transient occlusion of the superior mesenteric artery (SMA)11,12,13. Ischemia and reperfusion durations are extremely variable, ranging from minutes to several hours14,15. The rationale for the duration of ischemia is to induce sufficient aggression to trigger a significant response leading to the occurrence of remote injuries. A too short duration of ischemia may not cause a significant alteration in the studied metabolic pathway. Regarding reperfusion duration, the rationale lies in the early onset of remote injuries and the potentially transient nature of pathophysiological changes. An ideal reperfusion duration should not be too early or too late to characterize metabolic impairment adequately.
The models are mainly in rodents. Advantages of rodents include their small size, ease of maintenance, short life cycle, and abundant genetic resources16. The use of large animals such as pigs, dogs, or primates does not seem justified in the absence of additional benefits, which aligns with the ethical rules of animal experimentation regarding refinement. Furthermore, due to their anatomical, physiological, and genetic similarity to humans, rodents allow translational studies16.
One of the main limitations of SMA clamping models is that, in clinical practice, the start of the intestinal ischemia period is not identifiable. This makes extrapolation to human clinical situations more uncertain. In contrast, during complex aortic surgery, the ischemia and reperfusion periods of different organs are clearly identified. Moreover, during supra-coeliac aortic clamping, all the underlying viscera are in an ischemic period (digestive tract, liver, spleen, kidneys, pelvic organs, and lower limbs). All of these organs undergo the ischemia-reperfusion phenomenon. Conversely, models of ischemia-reperfusion focused on a specific organ (intestine, kidney, liver, etc.), models of aortic clamping and therefore of ischemia-reperfusion of multiple organs with metabolic pathophysiology are less studied. Similarly, remote injuries such as pulmonary lesions after aortic clamping are poorly studied in terms of metabolism17,18.
Existing aortic clamping models are primarily focused on clamping the abdominal aorta below the renal arteries. The limitation of this model is that it does not induce visceral ischemia-reperfusion. Therefore, it does not allow for the demonstration of a link between visceral ischemia-reperfusion and potential remote injuries18,19. Besides, there is no in vitro model allowing the study of ischemia-reperfusion through aortic clamping, that is why analysis using in vivo models remains necessary.
Therefore, this experimental model of supra-celiac aortic clamping in rats facilitates a comprehensive investigation into the pathophysiological mechanisms and pharmacological interventions targeting remote lung injuries.
Protocol
The creation of this model complies with the guidelines for animal care and experimentation, as well as French and European legislation. This model has been validated in an experimental animal study that was approved by the Regional University Ethics Committee in Normandy, Rouen, France (n°APAFIS: #18974).
1. Animal model and acclimatization
- Animal model adaptation period
NOTE: The model adheres to the principles of refinement.- House animals in non-overcrowded facilities for one week to allow adaptation before surgery.
- House the rats two per cage with ad libitum access to water and food, which will be checked daily by experienced personnel.
- Check the cleanliness of the bedding (paper strips) daily and change systematically by experienced personnel twice a week or more if needed.
- After a one-week acclimatization period, during which they will have daily contact with the experimenter and exposure to 12-h lighting cycles, procedures will take place in a separate, quiet room with the same experimenter.
- Animal model species
- Use male Wistar or Sprague Dawley rats to avoid hormonal influences, such as estradiol, on the analysis of visceral ischemia-reperfusion physiopathology from an accredited and certified breeding facility11,20.
- Determine the experimental groups and the number of animals per group in advance.
- Choose the age, 6-10-week-old rats (350 g) are recommended for use.
2. Anesthesia and analgesia
- Analgesia
- Weigh each animal on the day of the procedure.
- Administer buprenorphine (0.05 mg/kg) subcutaneously at the level of the rat's back skin 1 h before the procedure for analgesic purposes with 25-G needle and 2 mL syringe.
- Apply Lidocaine hydrochloride gel 1% to the skin of the abdomen at the level of the future skin incision. Reassess pain regularly (at least twice daily) postoperatively using a scale to assess facial expressions of pain in the rat21.
- Administer during the first 24 h, systematic subcutaneous injections of buprenorphine (0.01 to 0.05 mg/kg) every 8 h.
- Subsequently, administer buprenorphine injections (0.01 to 0.05 mg/kg) based on the facial pain scale of the National Centre for the Replacement, Refinement, and Reduction of Animals in Research, and repeated every 8 h if necessary, depending on the euthanasia time point21.
- General anesthesia
- Use halogenated gases (Isoflurane) for general anesthesia22.
- Use a ventilated chamber with isoflurane (5 %) at an airflow rate of 2 L/min for 2 min for the induction phase.
- For maintenance of anesthesia, switch the rat to a custom-fitted mask for spontaneous ventilation with isoflurane (2-2.5%) at an airflow rate of 2 L/min throughout the surgery.
- Clear the upper airways by moving the tongue out of the oral cavity to allow ventilation via the mask.
- Continuously monitor anesthesia depth during the procedure and adjust Isoflurane concentration as needed.
3. Rat placement during the procedure
- Place the rat in dorsal recumbency with the front and hind limbs immobilized using adhesive tape, while respecting the physiological joint ranges of motion of the rat.
- Place the rat on a warming pad set at 37 °C with monitoring of rectal temperature.
- Protect the eyes by applying dacryogel. Shave the abdominal fur and thoroughly disinfect the abdomen with 3 iterations of alternating iodine and alcohol scrubbing.
4. Surgical procedure
- Condition of the surgical procedure
- Perform the procedure under a microsurgical loupe to facilitate delicate maneuvers, although it is not indispensable.
- Confirm the depth of anesthesia via a toe-pinch before making the incision.
- Incision
- Following palpation of the xiphoid process at the upper border of the incision, incise the skin at the center of the abdomen, revealing the linea alba of the abdominal muscles.
- Center incision of the abdominal muscle on the linea alba to avoid bleeding from the abdominal muscles.
- Intra-abdominal exposition
- Maintain the abdominal wall on both sides with self-retaining retractors.
- Ensure the absence of anomalies (tumors), mobilize the viscera, stomach, spleen, and liver to the right side of the abdomen, and then expose the supra-celiac aorta.
- Kept all viscera inside the abdomen as much as possible by a small compress folded lengthwise and soaked in warm (37 °C) saline solution.
- Cover all viscera with a compress soaked in saline solution warmed to 37 °C, to prevent hypothermia and dehydration.
- Major intra-abdominal vessels identification
- Identify the supra-celiac aorta by its pulsations and its location between the diaphragmatic pillars.
- Control of the aorta between the diaphragmatic pillars with gentle and careful dissection using cotton-tipped applicators and dissecting forceps to release the aorta as atraumatically as possible.
- Encircle the supra-celiac aorta using a 5-0 suture with a dissecting and ligature forceps.
- Verify the origin of the celiac trunk and the underlying mesenteric artery. The duration of this surgical procedure is 10 to 15 minutes per rat.
- The underlying identification of the subrenal inferior vena cava is easy due to the transparency of the retroperitoneum.
NOTE: The supraceliac aorta is identified for cross-clamping, the downstream aorta is exposed to confirm the absence of pulsatility, and the inferior vena cava is used for injection (pre- or postconditioning) and for blood sampling at euthanasia. - Release the subrenal inferior vena cava only on its anterior surface, which allows for direct intravenous administration of any pharmacological agent.
- Intravenous injection
- For this purpose, use a 30-G needle for injection, and place a few millimeters of hemostatic compress to achieve hemostasis.
- If performing pharmacological preconditioning, administer the injection before aortic clamping. For post-conditioning treatment, administer it during or after aortic clamping.
- This protocol studied pharmacological preconditioning, so administer 5 min before aortic clamping.
- Ischemic period
- Clamp the celiac aorta with an atraumatic microvascular clamp for the entire 40-min ischemic period. Verify the effectiveness of the clamp by the disappearance of underlying aortic pulsations and the discoloration of the viscera and limbs multiple times during clamping.
- Close partially the abdomen with three simple 5-0 braided absorbable sutures to limit water and heat loss. Cover the surgical incision with a sterile compress soaked in warm saline solution for the entire duration of ischemia.
- Reperfusion period
- At the end of the ischemic period, reopen the abdomen and expose the aorta in the same manner as described earlier.
- Remove the vascular clamp, and verify the resumption of underlying aortic pulsatility and the recoloration of the viscera and limbs. The reperfusion period begins immediately upon removal of the microclamp.
- Abdomen closing
- Return the viscera to their original position, and close the abdomen with a 5-0 braided absorbable suture on the linea alba and the skin with a 5-0 monofilament absorbable suture.
- Animal awakening
- Place the rat in a left lateral decubitus position to avoid compressing the inferior vena cava by the visceral mass and the context of hypovolemia. Place the rat in an individual cage with a heat lamp to maintain temperature until awakening, approximately 10 min later.
- Second general anesthesia
- At the end of the 180-min reperfusion period, anesthetize the rat using the same gas anesthesia through a ventilated chamber with isoflurane (5%) at an airflow rate of 2 L/min for 2 min for the induction phase.
- For maintenance of anesthesia, switch the rat to a custom-fitted mask for spontaneous ventilation with isoflurane (2-2.5%) at an airflow rate of 2 L/min throughout the tissue collection period.
- Confirm the depth of anesthesia via a toe-pinch before making the incision.
5. Sampling
- Blood samples
- Collect blood samples using a 23-G needle and a 5 mL syringe by direct puncture into the inferior vena cava below the renal veins.
- Use a small portion (100 µL) of the total blood for gas and standard blood analysis on a single room temperature test card.
- Collect the remaining whole blood in a 4 mL EDTA tube, and centrifuge it at 1,000 × g for 10 min at +4 °C.
- Froze the plasma in cryotubes in liquid nitrogen and store at -80 °C until analysis.
- Tissue samples
- Tissue sampling
- Collect tissue samples (lung, intestine, kidney, liver, and heart) during euthanasia of the animal. Perform euthanasia by blood sampling leading to exsanguination after general anesthesia with isoflurane according to the same protocol as previously mentioned.
- Through the open abdomen, harvest 50 mg of each tissue: the upper pole of the left kidney, the left hepatic lobe, and the distal small intestine 1 cm before the cecum.
- Then, perform a median sternotomy quickly to identify the heart and lungs.
- Free the left lung from its ligament and remove it entirely for histological analysis. Free the right multilobe lung from its ligaments. Separate the anterior lobe for nucleic acid and protein analyses, store the rest in a cup with physiological serum at 37 °C for a few minutes to subsequently perform gravimetry.
- Extract the heart as a whole block with sections of the aorta, pulmonary artery, and both vena cavae. Sample a piece of the left ventricle for nucleic acid and protein analyses, store the remainder in a cup with physiological serum at 37 °C for a few minutes to subsequently perform gravimetry.
- Nucleic acid analysis
- For nucleic acid analysis, collect immediately a 50 g portion of tissue. Freeze it in liquid nitrogen and then store it at -80 °C until analysis.
- Extract total RNA with ready-to-use reagent for the isolation of high-quality total RNA according to the manufacturer's protocol.
- Determine RNA concentration and purity with a spectrophotometer. Measure RNA concentration using 2 µL of sample, with 2 µL of RNase-free water as a blank reference. Use the absorbance at 260 nm to determine RNA concentration.
NOTE: Acceptable RNA purity was defined as a 260/280 and 260/230 absorbance ratio ranging between 1.7 and 2.0. - Use 1 µg of each RNA sample for reverse transcription.
- Measure the mRNA levels of pro-inflammatory cytokines (IL-1beta, TNF-alpha, IL-6) and an internal reference (beta2-microglobulin), by real-time polymerase chain reaction (RT-PCR) in a rapid, plate-based, thermal block cycler with integrated real-time, online detection capabilities using ready-to-use hot start reaction mix (Primers are listed in Table 1).
- Calculate the relative mRNA level using the 2-ΔΔCT method.
- Protein analysis
- For protein analysis, place 50 mg of tissue in a 2 mL lysing tube containing fifty 2.8 mm zirconium oxide ceramic beads. This lysing tube contains 1 mL of radioimmunoprecipitation assay (RIPA) lysis buffer with a protease inhibitor tablet and a phosphatase inhibitor tablet.
- Extract protein from the samples by homogenization on the laboratory tube mill with 3 repetitions of 5-s checking, followed by a 10-s resting period.
- Centrifuge the samples at 10,000 g at +4 °C for 10 min, and store the supernatants in cryotubes at -20 °C until analysis.
- Determine protein concentrations with a Bradford-based method protein assay and keep samples at −80 °C.
- Separate an equal amount of proteins from each sample using SDS-PAGE.
- Transfer separated proteins on 0.2 µm nitrocellulose membranes.
- Incubate the membrane after blocking with 5% TBS-Tween non-fat dry milk for 1 h, with a primary antibody against the specific protein of choice. For example, to explore heparanase, use a rabbit polyclonal primary antibody against human heparanase (dilution 1:2000) and a control protein as GAPDH, use a goat monoclonal primary antibody against GAPDH (dilution 1:5000) overnight at 4 °C.
- Wash the blots three times with TBST-Tween 0.1% buffer.
- Incubate with an HRP-conjugated secondary antibody directed against the primary antibody at room temperature (RT) for 1 h in blocking solution. For example, to explore heparanase, use the goat against rabbit secondary antibody (dilution 1:5000) and to explore GAPDH, use the rabbit against goat secondary antibody (dilution 1:10000).
- Detect the immune complexes using enhanced chemiluminescence (ECL) detection system.
- Analyze the membranes using dedicated software to determine the densitometric values of the target bands, using GAPDH as the internal control. Perform densitometric analysis of the band corresponding to heparanase (50 kDa), and normalize it to the GAPDH protein band (35 kDa) to determine the relative signal intensity.
- Histological analysis
- For histological analysis, take the left unilobar lung at the hilum, then infuse through the left main bronchus with a cryopreservation solution using a 16 G catheter. Freeze it in liquid nitrogen and store it at -80 °C.
- Gravimetry analysis
- After the samples for nucleic acid and protein analysis, analyze the remaining portion of the heart and right multilobular lung by gravimetry, with desiccation in ovens at 70°C, allowing the wet/dry weight ratio to provide an estimate of tissue edema.
- Tissue sampling
Results
This protocol was found to be safe, with minimal animal losses (less than 5%) during anesthesia and surgery, and effective for the induction of acute lung injury. Anesthesia with isoflurane was safer than ketamine combined with xylazine anesthesia (loss approximately 15%), with rapid awakening and better rat recovery (data not shown). All anesthetized animals were able to undergo safe and effective aortic clamping with this method. All animals (100%) with effective aortic clamping survived the periods of ischemia and reperfusion, respectively, lasting 40 min and 3 h.
According to this protocol, the analysis of blood samples was successfully conducted. In this study involving 65 rats, the average blood volume collected was 4.5 ± 1.2 mL. It allowed for both gasometry analysis and biochemical plasma analysis by ELISA and Multiplex. The success rate of blood gas analyses was 100%. The average volume of recovered plasma was 750 µL. Blood gas analysis revealed a decrease in pH, PaO2, SpO2, and HCO3-, along with an increase in PaCO2 following supraceliac aortic clamping (Table 2)
Tissue analyses were successfully performed, enabling nucleic acid analysis (reverse transcription polymerase chain reaction/RT-PCR), protein analysis (Western Blot/WB), and histological evaluation. Pulmonary histology, described in Table 3, showed an overall increased injury score after aortic cross clamping (respectively, 9.5 ± 0.9 vs 14.6 ± 0.8, p < 0.01), with significant elevations in histological sub-scores for PNN/mm² (respectively, 2.83 ± 0.3 vs 5.0 ± 0, p < 0.001) and intravascular leukocytes (respectively, 0.33 ± 0.33 vs 2.33 ± 0.2, p < 0.01) as reported previously17.
Pulmonary inflammation markers (IL-1β and TNF-α) were also elevated after aortic cross-clamping for 40 min as described in Table 4. Additionally, pulmonary edema, as measured by gravimetric analysis, was found to be increased after aortic clamping (p < 0.001), as illustrated in Figure 3. Data are from our previous work17.
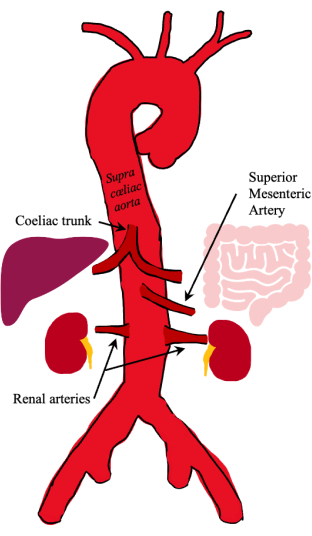
Figure 1: Simplified scheme of the Aorta, major branches, and abdominal organs. Please click here to view a larger version of this figure.
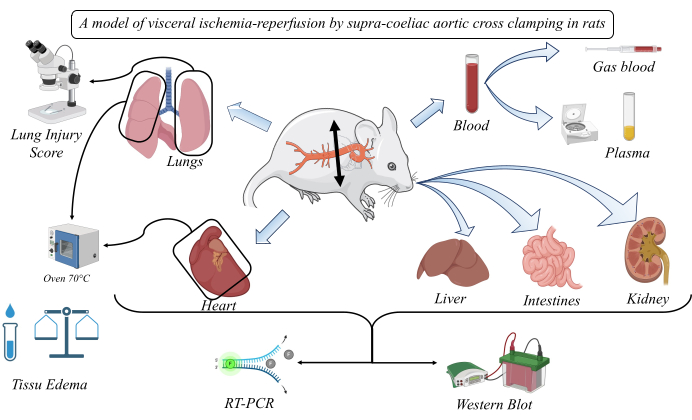
Figure 2: Schematic representation of a model of visceral ischemia-reperfusion by supra-coeliac aortic cross-clamping in rats. Schematic representation of the experimental model of 40-min supra-celiac aortic clamping followed by 3 h of reperfusion in rats. Sample collections and analyses are also synthetically represented. RT-PCR: Reverse transcription polymerase chain reaction. Please click here to view a larger version of this figure.
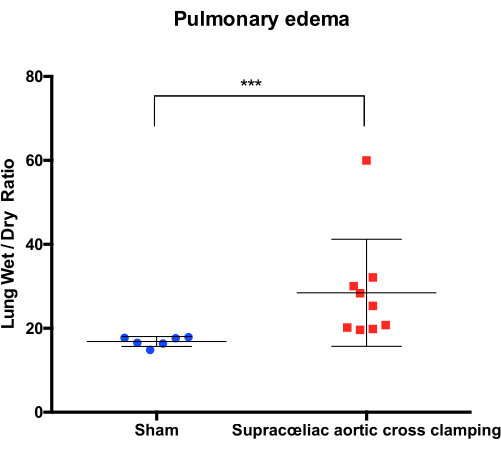
Figure 3: Pulmonary edema measured by lung wet/dry ratio. Lung edema was measured by comparing the wet/dry weight ratio of the remaining right lung. Sham: Sham-operated groups after laparotomy (blue dot; n = 6). Supra celiac aortic cross-clamping of 40 min (red square; n = 10). Data are expressed as means ± SD and compared with the Mann-Whitney test with Bonferroni correction. Data obtained from Palmier et al.17. Please click here to view a larger version of this figure.
| Gene Name | Forward (5’ -> 3’) | Reverse (3’ -> 5’) |
| IL-1β | AGATTCTTCCCCTTGAGGCC | CACTGCAGGCTTCGAGATGA |
| IL-6 | CCACTGCCTTCCCTACTTCA | TTCTGACAGTGCATCATCGC |
| TNF-α | TCTTCTCATTCCTGCTCGTGG | TGGGCCATGGAACTGATGAG |
| β-2-microglobulin | TCTCAGTTCCACCCACCTCA | GGTCTCGGTGGGTGTGAATT |
Table 1: Real-Time PCR primers.
| After Supracœliac Aortic cross clamping | Normal range | |
| pH | 7.33 ± 0.03 | 7.35–7.45 |
| PaO2 (mmHg) | 26.09 ± 3 | 80–110 |
| PaCO2 (mmHg) | 50.01 ± 3.41 | 35–45 |
| HCO3- (mmol/L) | 25.61 ± 0.67 | 20–26 |
| Lactate (mmol/L) | 2.66 ± 0.38 | 0.5–2.5 |
| Hemoglobin (g/dL) | 17.46 ± 0.7 | 13–16 |
| Hemotocrit (%) | 51.7 ± 1.94 | 40–50 |
| Creatinine (mg/dL) | 0.87 ± 0.1 | 0.2–0.5 |
Table 2: Standard blood tests and gas analysis results. Supra celiac aortic cross-clamping for 40 min followed by 3 h of reperfusion. pH: potential of hydrogen, PaO2: arterial partial pressure of oxygen, PaCO2, arterial partial pressure of carbon dioxide, HCO3- : bicarbonate. Data are expressed as mean ± SEM.
| Sham | Supracoeliac Aortic cross clamping | p | |
| Histopathologic lung injury score | 9.5 ± 0.9 | 14.6 ± 0.8 | <0.01 |
| Edema | 0.17 ± 0.17 | 0.89 ± 0.3 | NS |
| Hemorrhage | 1.33 ± 0.6 | 2.78 ± 0.2 | <0.05 |
| PNN | 2.83 ± 0.3 | 5.0 ± 0 | <0.001 |
| Alveolar septal thickening | 4.83 ± 0.2 | 3.56 ± 0.4 | NS |
| Intravascular cells | 0.33 ± 0.33 | 2.33 ± 0.2 | <0.01 |
Table 3: Histopathologic lung injury score. PNN, polynuclear neutrophil. Sham: Sham-operated groups after laparotomy (n = 6). Supra celiac aortic cross-clamping of 40 min (n = 10). Data are expressed as means ± SEM and compared with the Mann-Whitney test with Bonferroni correction. Data obtained from Palmier et al.17.
| Sham | Supracoeliac Aortic cross clamping | p | |
| TNF-alpha | 0.38 ± 0.03 | 4.61 ± 1.67 | < 0.001 |
| IL-1Beta | 0.41 ± 0.05 | 1.03 ± 0.21 | < 0.05 |
Table 4: Lung cytokines. TNF-alpha: Tumor Necrosis Factor-alpha pulmonary relative expression; IL-1Beta: Interleukin 1-Beta pulmonary relative expression. Sham: Sham-operated groups after laparotomy (n = 6). Supra celiac aortic cross-clamping of 40 min (n = 10). Data are expressed as means ± SEM and compared with a Mann-Whitney test with Bonferroni correction.
Discussion
This surgical model of aortic cross-clamping offers the advantage of allowing a comprehensive analysis, both tissue-based and plasma-based, of the acute lung injury following visceral ischemia-reperfusion. It also provides the opportunity to test pharmacological molecules with intraperitoneal, enteral, or intravenous administration in pre- or post-conditioning.
One of the critical steps remains supraceliac aortic clamping during surgery. When mastered, this step can be performed quickly. The learning curve for the technique is steep: fewer than three procedures are typically required to acquire a safe and effective surgical approach. The use of a fine curved instrument (e.g., dissecting and ligature forceps) greatly facilitates the procedure. Additionally, the use of a monofilament suture could prevent adherence to surrounding tissues and is less traumatic.
Intravenous administration into the inferior vena cava is also a procedure with significant hemorrhagic risk. The use of hemostatic compress has been a real game changer, helping to avoid technical difficulties associated with direct suturing of the inferior vena cava. The venous wall is extremely fragile, and any attempt to repair a needle-induced injury carries a high risk of enlarging the vascular lesion. Manual compression of the injury is a possible alternative to achieve hemostasis of the inferior vena cava; however, this can cause venous return collapse, potentially impacting cardiopulmonary function.
Performing this intervention under spontaneous ventilation allows the model to be conducted without complex veterinary anesthesia equipment. The anesthesia protocol using isoflurane may be a limiting factor in experimental reproducibility, as isoflurane can also interfere with the studied pathophysiological elements23. An alternative anesthesia protocol validated in this model involves induction with Xylazine 0.5 mg/kg via intraperitoneal injection, followed by a 10-min interval and subsequent intraperitoneal injection of Ketamine 20 mg/kg to minimize respiratory arrests. However, complications associated with this anesthesia method are more significant than those associated with isoflurane.
Ischemia durations can be modulated based on the physiological elements being studied. In this model, we favored an ischemia duration of 40 min to induce significant aggression of the lungs. The goal is to maximize aggression to uncover variations in this signaling pathway17. The same applies to reperfusion durations, which can be multiple, either in different groups of rats or in the same rat. Studying multiple reperfusion durations is feasible in the same rat, only for blood analyses. Small venous blood samples can be repeatedly collected from the rat's tail dorsal vein, providing the advantage of studying the rat as its control with precise kinetics of the studied elements.
A potential troubleshooting issue with the technique is the improper placement of the microvascular clamp. In some cases, the clamp may appear to be correctly positioned, yet fails to achieve complete aortic occlusion. As a result, pulsatile flow may persist in the underlying aorta, accompanied by continued perfusion of the downstream organs with lesser impaired distal perfusion, including compromised blood supply to the gastrointestinal tract and lower limbs.
Careful observation is essential to distinguish between transmitted pulsations -- caused by mechanical continuity between the microvascular clamp and adjacent tissues -- and true pulsations of the underlying abdominal aorta. The discoloration of the bowel and lower limbs must be clear and unequivocal. In case of doubt, the microvascular clamp should be repositioned to ensure it grasps only the aorta and not surrounding fatty or connective tissues. Alternatively, a second microvascular clamp can be applied proximally to the first one to ensure complete occlusion.
Among experimental models of visceral ischemia-reperfusion, several models of aortic clamping are utilized. Historically, clamping of the abdominal aorta below the renal arteries was more commonly described and used. The rationale was epidemiological, with a higher frequency of aneurysmal pathology observed below the renal arteries. However, with the development of endovascular techniques for aortic aneurysm exclusion, aortic clamping below the renal arteries, and consequently, induced ischemia-reperfusion, has significantly decreased in clinical practice28. Its experimental relevance has naturally declined as well. This is less true for extensive thoracoabdominal aortic pathologies. The interest lies in the clinical impact of supra-celiac aortic clamping. Pulmonary complications, in particular, are major and multifactorial. However, the occurrence of distant complications, especially pulmonary, is only partially understood. The underlying hypothesis of the model is the potential existence of a causal link between visceral ischemia related to surgery and the occurrence of organ failures, particularly pulmonary involvement.
Although extensively studied, pulmonary complications following intestinal ischemia-reperfusion, by selective clamping of the superior mesenteric artery, are only partially understood29,30. During mesenteric ischemia, the exact onset of the ischemic period is never precisely known. It is approximately estimated at the onset of abdominal pain. In contrast to mesenteric ischemia, during aortic surgery, the durations of ischemia and reperfusion are perfectly controlled. Aortic clamping simulation offers the definite advantage of replicating a well-defined clinical situation.
A key strength of the model described here lies in its ability to characterize ALI using a multimodal approach. While the diagnostic criteria for ALI in experimental models are not as clearly defined as those for acute respiratory distress syndrome (ARDS) in clinical settings, some recommendations have been proposed in the literature31. These suggest that ALI assessment should be based on four core features: (1) histological evidence of tissue injury, (2) alteration of the alveolar-capillary barrier, (3) an inflammatory response, and (4) evidence of physiological dysfunction.
Each of these features can be assessed using methods classified as either "very relevant" or "somewhat relevant." To establish the presence of ALI, it is recommended that at least three of the four main features be identified. In our supraceliac aortic clamping model, ALI is evaluated across all four domains. Histological evidence of tissue injury is assessed using a very relevant method. Alteration of the alveolar-capillary barrier is evaluated using a somewhat relevant measure. The inflammatory response is analyzed with multiple very relevant methods, and physiological dysfunction is assessed using a very relevant approach.
The main limitation of this model is that it represents aortic clamping on a healthy aorta. The aorta in this model lacks any pathological features, such as aneurysmal dilation or dissection. However, it is well established in the literature that the mural thrombus present within an abdominal aortic aneurysm exhibits intense biological activity32. This includes the involvement of inflammatory cytokines, immune cells, proteases, and coagulation factors. Therefore, the biological response following supraceliac aortic clamping in a healthy aorta is likely to differ significantly from that observed in an aneurysmal aorta containing mural thrombus.
Future applications of the experimental aortic clamping model will allow the investigation of additional biological markers involved in the systemic response. This model may also serve to evaluate various therapeutic strategies aimed at preventing complications following supraceliac aortic clamping.
This rat model of supra-celiac aortic clamping via laparotomy offers a reliable and reproducible platform for studying the systemic consequences of visceral ischemia-reperfusion, particularly acute lung injury. By mimicking the hemodynamic and inflammatory conditions encountered during complex aortic surgery, the model enables a mechanistic and translational approach to identifying early biomarkers and evaluating therapeutic strategies targeting remote organ damage. This model stands as a valuable tool to bridge experimental research and clinical application in the field of ischemia-reperfusion injury.
Disclosures
The authors have nothing to disclose.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 0.2 µm nitrocellulose membranes Trans-Blot Turbo Transfert Pack | Bio-Rad | 1620150 | 0.2 µm nitrocellulose membranes precut |
| 1cc Luer Slip syringe w/o Needle | Terumo | MDSS01SE | 1cc Luer Slip syringe w/o Needle |
| 2cc Luer Slip syringe w/o Needle | Becton Dinckinson | 2cc Luer Slip syringe w/o Needle | |
| 4 mL EDTA tube BD K3 13 mm x75 mm | BD Vacutainer | BD368860 | 5 mL EDTA tube BD K3 13 mm x 75 mm |
| 5-0 braided suture / Vicryl 5-0 (Ethicon) or Novosyn (B. Braun) | Ethicon - Johnson and Johnson | V7970E | Vicryl 5-0 Needle Taper Point 1/2 circle 13 mm Lenght 45 cm |
| 5-0 monofilament absorbable suture / Monocryil Poliglecaprone | Ethicon - Johnson and Johnson | Y493G | Needle 3/8 circle Lenght 18in |
| 5cc Luer Slip syringe w/o Needle | Terumo | SS-05LE1 | 5cc Luer Slip syringe w/o Needle |
| Atraumatic microvascular clamp/Disposable vessel clamps for vein | AROSurgical | TKF-1-20g | Atraumatic microvascular clamp for vein use in order to clamp the rat aorta |
| BD Microlance 3 23 G x 1 0.6 x 25 mm | BD Vacutainer | 300800 | BD Microlance 3 23 G x 1 0.6 x 25 mm |
| BD Microlance 3 25 G x 5/8 0.5 x 16 mm | BD Vacutainer | 300600 | BD Microlance 3 25 G x 5/8 0.5 x 16 mm |
| BD Microlance 3 30 G x 1/2 0.3 x 13 mm | BD Vacutainer | 304000 | BD Microlance 3 30 G x 1/2 0.3 x 13 mm |
| beta-actine Invitrogen | Carlsbad, USA | 15G5A11/E2 | |
| Bradford-based method protein assay | Biorad, Marnes-la-Coquette, France | 5000201 | |
| Buprenorphine | Buprenorphine | ||
| Centrifugator Sigma 3-30 | Sigma, Germany | 10375, 10376, 10377, 10378, 10379, 91276, 109014 | Centrifugator for eppendorf |
| cOmplete Mini | Roche | 11836153001 | protease inhibitor cocktail 25 tablets |
| Cotton swab | |||
| Dacryogel / Ocular gel Lubrithal 10 g | Dechra Veterinary products | Code ACL7376464 | Ocular gel Lubrithal 10 g |
| Disposable scalpel | Paramount | PDSS11 | Disposable scalpel blade n°11 |
| Electrocautery | DentRMed | EMB/87400 | Hemostatic pen with hight temperature |
| Enhanced ECL Detection System | Biorad, Hercules, California, USA | 1705060S | |
| Fisherbrand Bead Mill 24 | Fisher scientific | 15515799 | Used for grinding, lysis and homogenization of biological samples prior to molecular extraction |
| Gauze swabs | Raffin | .010106 | Gauze swabs |
| ImageLabTM software | Biorad | on USB drive or license | |
| Isoflurane 5% | Isoflurane 5% | ||
| Lidocaine Prilocaine gel 5% | Aguettant, Lyon, France | Lidocaine Prilocaine gel 5% | |
| LightCycler 480 Instrument | Roche, Bâle, Swiss | 5015243001 | thermal cycler |
| Lubricating Jelly Sterile K-Y 82 g | RECKITT BENCKISER | Lubricating Jelly Sterile K-Y 82 g | |
| NanoDrop 2000 | TermoScientific, Waltham, Massachusetts, USA | ND-2000 | spectrophotometer |
| Peha Pince anatomic | Hartmann | 991063 | Anatomic pliers |
| PhosSTOP | Roche | 4906837001 | phosphatase inhibitor 20 tablet |
| Plaster/Adhesive Tape | Anapore | 135320 | Surgical adhesive tape/plaster |
| Povione-iodine solution / Vétédine Solution | Vétoquinol | Antiseptic solution for external use | |
| Precellys Lysing Kit tube | Hard tissue homogenizing CK28, Bertin | CK28 | Precellys Lysing Kit tube |
| Prolène Prolypropylene suture | Ethicon - Johnson and Johnson | 7472H | Prolène 5-0 Needle Taper cut 3/8 circle 13 mm Lenght 75 cm |
| Safe-Lock tubes 1.5 mL | Eppendorf | .0030120086 | Safe-Lock tubes 1.5cc no color 1000 tubes for centrifugation |
| Safe-Lock tubes 2 mL | Eppendorf | .0030120094 | Safe-Lock tubes 2.0cc no color 1000 tubes for centrifugation |
| Safe-Lock Tubes 5 mL | Eppendorf | .0030119401 | Safe-Lock tubes 5.0cc no color 200 tubes for centrifugation |
| Saline solution NaCl 0,9% | Aguettant, Lyon, France | 600502 | Saline solution 0.9% 500 mL |
| SDS-PAGE | Sigma-Alrich | ||
| Surflash IV Catheter 16 G | Terumo | SR*FF1651 | |
| Surgicel | Ethicon - Johnson and Johnson | Hemostatic resorbable swabs | |
| Suture set n°12 | Hartmann | 4701762 | Suture sterile set with adhesine champ, cisors, Adson pliers, needle-holder |
| SYBR Green KIT Light Cycler 480 SYBR Green I Mastern | Roche | 4707516001 | SYBR Green |
| TBST-Tween 0.1% buffer | Sigma-Alrich | ||
| Test-Cards Epoc 24 cards 13 parameters | Siemens-Healthineers | ||
| Tissue TEK | Sakura Finetec | Cryopreservation solution | |
| TRIzol reagent Invitrogen | Thermo Fisher Scientific, Carlsbad, California, USA | 15596026 | TRIzol reagent |
References
- Johnston, K. W., Rutherford, R. B., Tilson, M. D., Shah, D. M., Hollier, L., Stanley, J. C. Suggested standards for reporting on arterial aneurysms. Subcommittee on Reporting Standards for Arterial Aneurysms, Ad Hoc Committee on Reporting Standards, Society for Vascular Surgery and North American Chapter, International Society for Cardiovascular Surgery. J Vasc Surg. 13 (3), discussion 245-247 452-458 (1991).
- Johansen, K., Kohler, T. R., Nicholls, S. C., Zierler, R. E., Clowes, A. W., Kazmers, A. Ruptured abdominal aortic aneurysm: the Harborview experience. J Vasc Surg. 13 (2), 245-247 (1991).
- Cambria, R. P., Clouse, W. D., Davison, J. K., Dunn, P. F., Corey, M., Dorer, D. Thoracoabdominal aneurysm repair: Results with 337 operations performed over a 15-year interval. Ann Surgery. 236 (4), 471-479 (2002).
- Feezor, R. J., et al. Genomic and proteomic determinants of outcome in patients undergoing thoracoabdominal aortic aneurysm repair. J Immunol. 172 (11), 7103-7109 (2004).
- Welborn, M. B., et al. The relationship between visceral ischemia, proinflammatory cytokines, and organ injury in patients undergoing thoracoabdominal aortic aneurysm repair. Crit Care Med. 28 (9), 3191-3197 (2000).
- Money, S. R., et al. Risk of respiratory failure after repair of thoracoabdominal aortic aneurysms. Am J Surg. 168 (2), 152-155 (1994).
- Collange, O., et al. Compartmentalization of inflammatory response following gut ischemia reperfusion. Eur J Vasc Endovasc Surg. 49 (1), 60-65 (2015).
- Shi, Y., Han, L., Zhang, X., Xie, L., Pan, P., Chen, F. Selenium alleviates cerebral ischemia/reperfusion injury by regulating oxidative stress, mitochondrial fusion and ferroptosis. Neurochem Res. 47 (10), 2992-3002 (2022).
- Wang, Q., et al. Empagliflozin protects against renal ischemia/reperfusion injury in mice. Sci Rep. 12 (1), 19323(2022).
- Wu, M. -B., Ma, B., Zhang, T. -X., Zhao, K., Cui, S. -M., He, S. -C. Propofol improves intestinal ischemia-reperfusion injury in rats through NF-κB pathway. Eur Rev Med Pharmacol Sci. 24 (11), 6463-6469 (2020).
- Breithaupt-Faloppa, A. C., et al. Acute effects of estradiol on lung inflammation due to intestinal ischemic insult in male rats. Shock. 41 (3), 208-213 (2014).
- Klausner, J. M., et al. Thromboxane A2 mediates increased pulmonary microvascular permeability following limb ischemia. Circ Res. 64 (6), 1178-1189 (1989).
- James, I. A. O., Chen, C. -L., Huang, G., Zhang, H. -Y., Velten, M., Besner, G. E. HB-EGF protects the lungs after intestinal ischemia/reperfusion injury. J Surg Res. 163 (1), 86-95 (2010).
- Kannan, K. B., et al. Hypoxia-inducible factor plays a gut-injurious role in intestinal ischemia reperfusion injury. Am J Physiol Gastrointest Liver Physiol. 300 (5), G853-G861 (2011).
- Li, Y., et al. Enteral supplementation of alanyl-glutamine attenuates the up-regulation of beta-defensin-2 protein in lung injury induced by intestinal ischemia reperfusion in rats. Int J Surg. 12 (11), 1181-1186 (2014).
- Bryda, E. C. The mighty mouse: the impact of rodents on advances in biomedical research. Mo Med. 110 (3), 207-211 (2013).
- Palmier, M., et al. A supraceliac aortic cross clamping model to explore remote lung injury and the endothelial glycocalyx. Ann Vasc Surg. 93, 18-28 (2022).
- Ak, E., Ak, K., Ustandag, U. V., Kervancioglu-Demirci, E., Emekli-Alturfan, E., Çetinel, S. Milrinone attenuates heart and lung remote injury after abdominal aortic cross-clamping. Ann Vasc Surg. 69, 391-399 (2020).
- Kurt, A., Kalkan, Y., Turut, H., Cure, M. C., Tumkaya, L., Cure, E. Topiramate reduces aortic cross-clamping-induced lung injury in male rats. Acta Medica (Hradec Kralove). 61 (4), 144-149 (2018).
- Fantozzi, E. T., et al. Estradiol mediates the long-lasting lung inflammation induced by intestinal ischemia and reperfusion. J Surg Res. 221, 1-7 (2018).
- Sotocina, S. G., et al. The Rat Grimace Scale: A partially automated method for quantifying pain in the laboratory rat via facial expressions. Mol Pain. 7, 55(2011).
- Oh, S. S., Narver, H. L. Mouse and rat anesthesia and analgesia. Curr Protoc. 4 (2), e995(2024).
- Annecke, T., et al. Sevoflurane preserves the endothelial glycocalyx against ischaemia-reperfusion injury. Brit J Anaesth. 104 (4), 414-421 (2010).
- Pararajasingam, R., Weight, S. C., Bell, P. R. F., Nicholson, M. L., Sayers, R. D. Pulmonary nitric oxide metabolism following infrarenal aortic cross-clamp-induced ischaemia-reperfusion injury. Eur J Vasc Endovasc Surg. 19 (1), 47-51 (2000).
- Nielsen, V. G., Baird, M. S., McAdams, M. L., Freeman, B. A. Desflurane increases pulmonary alveolar-capillary membrane permeability after aortic occlusion-reperfusion in rabbits: evidence of oxidant-mediated lung injury. Anesthesiology. 88 (6), 1524-1534 (1998).
- Axon, R. N., Baird, M. S., Lang, J. D., Brix, A. E., Nielsen, V. G. PentaLyte decreases lung injury after aortic occlusion-reperfusion. Am J Respir Crit Care Med. 157 (6), 1982-1990 (1998).
- Fujimura, N., et al. Neutrophil elastase inhibitor improves survival rate after ischemia reperfusion injury caused by supravisceral aortic clamping in rats. J Surg Res. 180 (1), e31-e36 (2013).
- Spanos, K., et al. Transition from open repair to endovascular aneurysm repair for rupture aortic aneurysms throughout a 16-year period of time in a single tertiary center. Ann Vasc Surg. 100, 120-127 (2024).
- Hansen, L. W., et al. Sirtuin1 activator SRT1720 protects against organ injury induced by intestinal ischemia-reperfusion. Shock. 45 (4), 359-366 (2016).
- Thais Fantozzi, E., et al. Acute lung injury induced by intestinal ischemia and reperfusion is altered in obese female mice. Pulm Pharmacol Ther. 49, 54-59 (2018).
- Matute-Bello, G., et al. An official American Thoracic Society Workshop report: Features and measurements of experimental acute lung injury in animals. Am J Respir Cell Mol Biol. 44 (5), 725-738 (2011).
- Michel, J. -B., et al. Novel aspects of the pathogenesis of aneurysms of the abdominal aorta in humans. Cardiovasc Res. 90 (1), 18-27 (2011).
Reprints and Permissions
