The sagittal adjusting screw (SAS) system has been widely used for thoracolumbar (TL) spinal trauma. Percutaneous options and specialized trauma reduction devices are also available for the SAS system. We describe a technique for reducing TL burst fractures using an SAS system and a newly introduced trauma reduction device.
Method Article
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
* These authors contributed equally
In This Article
Summary
Abstract
Thoracolumbar (TL) burst fracture is one of the most common indications for minimally invasive percutaneous pedicle screw fixation. Although the indication for surgical treatment of neurologically intact TL fractures remains under debate, studies have demonstrated that posttraumatic malalignment may lead to a deterioration in the patient's quality of life. For burst fractures with malalignment or fragments in the spinal canal, a reduction technique using ligamentotaxis is commonly used to improve long-term outcomes.
The sagittal adjusting screw (SAS) system is a monoaxial screw system with a fixed head and concave sliding saddle that allows lordotic sliding of the rod in the sagittal plane after screw insertion. SAS also has a percutaneous option and has been used for TL spine fractures. Notably, the SAS only allows motion on the sagittal plane, allowing both secure fixation and angular reduction. The SAS has certain advantages over the conventional Schanz screw system or normal mono-/multiaxial pedicle screws for TL spine fracture treatment. In addition, specialized trauma reduction devices are available for the SAS system. In this video protocol, we discuss the indication for the SAS system in TL burst fracture and describe a technique of TL burst fracture reduction and fixation using the SAS system. Additionally, we describe our recent case series with radiological evaluation, including regional kyphotic angle and percent loss of anterior vertebral body height, to evaluate the newly introduced trauma reduction device.
Introduction
Thoracolumbar (TL) burst fractures are relatively common, occurring in approximately 20% of all vertebral fractures1, and are characterized by retropulsion of the fractured middle column fragments into the spinal canal. Although the management of TL burst fractures has been extensively studied, the indication for surgical treatment remains under debate. Previous studies have reported that long-term functional outcomes may not differ substantially between operative and nonoperative treatment for neurologically intact TL burst fractures1. Nevertheless, these comparative studies were launched decades ago, making their results not applicable in this era when surgical techniques have substantially improved since then.
Recent advances in surgical techniques may have changed the surgical indications. Recently, minimally invasive approaches for TL injuries have become popular, and good results have been reported. Although their sample sizes are small, studies about the emerging novel techniques and implants support surgical treatment for neurologically intact TL fractures1.
Generally, surgical treatment of neurologically intact TL fractures aims to ensure good alignment correction, reduction of fracture fragments with ligamentotaxis, and secure fixation2,3. In patients with neurological symptoms, direct or indirect decompression of the neural structure is added to these aims. There are variations in the surgical techniques used for posterior fixation of TL burst fractures, such as surgery with and without fusion, the use of vertebroplasty, different numbers of fixation levels, and the use of additional screws on the fractured vertebrae.
Non-fusion fixation using percutaneous pedicle screws (PPSs) is commonly performed because it is less invasive and allows segmental motion after implant removal. The advantages of PPS over conventional open techniques are not limited to smaller skin incisions; PPS is associated with less paraspinal muscle damage compared to an open approach4. Moreover, a human cadaver study reported that PPS reduces the risk of medial branch nerve injury, which leads to multifidus muscle denervation5. Currently, a TL fracture is among the most common indications for minimally invasive surgery using PPSs, and a minimally invasive PPS system without fusion is reportedly associated with improved surgical outcomes in patients with TL burst fractures2,3.
Reduction techniques are also a topic of interest. Since the 1980s, the Schanz screw system has been used for TL burst fracture treatment; this system allows good angular correction, vertebral height reduction, and reduction of retropulsion fragments by ligamentotaxis. Good results have been reported with the Schanz screw system6. However, the original Schanz system appears unsuitable for percutaneous use because the connectors are too bulky and use a side-loading system.
In contrast, the designated PPS system, which was developed in the 2000s, has been widely used for various conditions7. Although it is associated with less invasiveness to back muscles, one drawback of conventional multiaxial screws (MAS), compared with the Schanz system, is that screws have less angular stability due to a mobile screw head. Monoaxial screws, which have better angular stability than MAS, are also available as PPS options. However, it is often technically demanding to align all screw heads in the same plane as rods percutaneously without any angulation of the screws to avoid excessive mechanical stress on the screws or bones. Additionally, creating lordosis after screw insertion is almost impossible when monoaxial screws are used.
To overcome these issues, the sagittal adjusting screw (SAS) system was introduced in 2013 and was first aimed to correct spinal deformity secondary to fractures. The SAS is a monoaxial screw system with a fixed head that resembles a common head-loading pedicle screw; it has a concave sliding saddle that allows lordotic sliding of the rod in the sagittal plane after screw insertion. Since then, the use of SAS has expanded among acute TL burst fractures8,9 as well as elective procedures including correction of spondylolisthesis10. The SAS only allows motion on the sagittal plane, allowing both secure fixation and angular reduction, which is usually impossible after screw insertion using conventional monoaxial screws.
One biomechanical study demonstrated that the SAS system has better force-displacement properties and fatigue test results than other head-loading PPSs, equivalent to the Schanz screw system. Trauma reduction devices can be attached to the extension towers of the SAS system and, therefore, both distraction and angulation forces can be applied at the instrumented levels using such a device9. Good results have also been reported for such trauma reduction devices used for TL fractures8.
The aim of this protocol is to describe the technique for alignment correction and fracture reduction methods using the SAS system in TL burst fractures and discuss the advantages of the SAS system. In the following protocol, PPS placement and fracture reduction using the SAS system and trauma reduction device are outlined. We also show representative cases demonstrating the results of this procedure.
Protocol
This protocol was approved by the Institutional Review Board of Showa University Hospital (No.2023-017-A) and conducted in accordance with the ethical principles outlined in the Declaration of Helsinki. The protocol follows the guidelines of our institution's human research ethics committee. As this representative case series is retrospective in nature, informed consent from each patient was waived in accordance with the institutional review board policy. Informed consent was obtained from patients presented in the figures and video of this protocol.
1. Indication of this protocol and preoperative planning
- Before the surgery, ensure the indication for the use of the SAS system and trauma reduction device. As mentioned earlier, there are controversies regarding surgical indications of TL burst fractures. Discuss the potential risks and benefits of surgery with the patient before surgery based on the best available evidence, even if it is limited.
NOTE: In case of limited evidence, we believe it is acceptable to rely on the clinician's personal experience, expert opinion, and method of treatment that is taught and practiced among practitioners in one's specific region, linguistic group, and local professional community11.- Select the following indication criteria for the posterior percutaneous short fixation procedure: skeletal maturity, absence of severe osteopenia, no evidence of PLL injury, and meeting at least one of the following criteria: thoracolumbar injury classification and severity (TLICS)12 score ≥ 4, any Arbeitsgemeinschaft Osteosynthesefragen (AO) classification13 type B1 and B2 fractures with intact PLL, local kyphotic deformity > 15°, coronal deformity > 10°, or inability to tolerate conservative treatment due to other medical/psychological/socioeconomic issues (Table 1).
- Select the following exclusion criteria: severe anterior segmental collapse and multiple consecutive fractures.
- Evaluate the patient's bone status to determine the use of the trauma reduction device.
NOTE: Avoid using the device in patients with moderate-to-severe osteoporosis for preventing iatrogenic fracture. Additionally, do not use the reduction device for patients with a ruptured posterior longitudinal ligament (PLL) because a reduction of the retropulsion fragment with ligamentotaxis is not possible.- If time allows, obtain an MRI for the diagnosis of PLL14 and other posterior ligamentous complex injury, even if the patient is neurologically intact. Use CT to evaluate the presence of "reverse cortical sign"-the posterior wall fragment rotating 180° with the cortical surface facing anteriorly and the cancellous surface facing posteriorly in the canal-indicating PLL rupture and contraindication of ligamentotaxis.15
- Ensure that the length and diameter of the SAS are measured in advance using an appropriate imaging platform, and use these images to simulate the trajectory of each screw. Draw lines anteriorly, extending from the medial borders of the bilateral pedicles. Check the location of the intersection bilaterally between the abovementioned line and the ideal pedicle screw trajectory.
- Perform surgery as early as reasonably possible.
NOTE: A study reported that the quality of TL fracture reduction with ligamentotaxis is better when performed earlier16.
2. Equipment and patient positioning
NOTE: The procedure requires intraoperative fluoroscopy (or a navigation system).
- Use an open Jackson table for the procedure. Place the patient in the prone position and extend the patient's legs slightly.
- Make efforts to achieve normal spinal alignment when placing bolsters under the patient's chest and bilateral anterior superior iliac spine before surgery to make reduction and screw insertion easier. Check the lateral fluoroscopic view, and make sure the abdomen is free of compression.
- When monitoring is used, ensure that all electrodes are securely placed. For average-risk surgeries, such as this procedure, place the recording electrodes with a belly-tendon montage in the vastus medialis, anterior tibialis, and adductor hallucis to monitor major lower extremity myotomes.
NOTE: The use of intraoperative neuromonitoring is based on each institutional protocol. In our institution, transcranial stimulation motor evoked potential is used for average-risk surgeries, including this procedure. - Use fluoroscopy to position the fractured vertebra and pedicles of the planned instrumented levels, one level above and below, as well as the fractured level at a minimum, and two levels above and/or below; if necessary, mark them on the skin. The identification of the fractured level is usually easy; however, if it is unclear or there are multiple previously fractured vertebrae, count the number of vertebrae from the sacrum or first thoracic vertebra. Record the position of the image intensifier to ensure good anteroposterior (AP) and lateral views of the spine during surgery.
NOTE: The endplates should be parallel to the image trajectory in the AP view. Keep in mind that the best angles may differ for each vertebra owing to local lordosis/kyphosis in the area. - Make sure there is enough clearance, at least 30-40 cm, between the patient's body and the image intensifier.
NOTE: Each procedural step of the SAS system, such as needle insertion using a mallet, tapping, and screw placement, requires a certain clearance.
3. Skin incisions and needle insertion
- After patient positioning, prepare the surgical site using an alcohol or iodine-based skin disinfectant. Subsequently, drape with a disposable surgical sheet set, and apply an iodophor-impregnated adhesive incision drape17.
- Similar to the standard PPS insertion7, make an incision lateral to the skin marks of the pedicles. Place the incisions 1-1.5 cm laterally to the lateral margin of the pedicles in the lumbar spine as per standard technical notes for PPS.
- Dissect the fascia longitudinally after the skin incision. Make the skin incision longer than that of a normal PPS (at least 2 cm) to prevent skin problems when using a trauma incision device. Make skin incisions relatively medial to the standard incisions in patients with a low body mass index and lateral to the standard incisions in obese patients.
NOTE: The positions should be modified based on operated levels: 0-0.5 cm lateral to the pedicles in the middle thoracic spine. Rod insertion is easier with a longitudinal incision used as the insertion site than with transverse incisions. The long midline incision, which is not "percutaneous" but still has muscles attached to the lamina, is sometimes used for upper-middle thoracic spine fractures because the pedicles are too close to make separate incisions or in cases requiring direct decompression. - Position the needle at the intersection of the facet and transverse process after skin incisions and fascia dissection. Obtain an AP image and ensure that the vertebra is not rotated.
- Gentle tapping with a mallet, insert the needle tip into the bone with fluoroscopic control. As the needle advances, ensure the tip of the needle approaches the medial margin of the pedicle on the AP image.
- Obtain a lateral image when the needle is located close to the medial margin of the pedicle. Confirm that the needle tip is located anterior to the posterior wall of the vertebra and close to the intersection point described.
- Repeat all steps bilaterally from steps 3.2 to 3.5 for as many instrumented levels as necessary. Ensure that the bilateral needles are placed in parallel, resembling a rectangle and not a trapezoid. Consider making the incision larger in case of facet degeneration and flattening caused by using a rongeur or surgical bar when placing needles; achieving a good position is difficult because of such a prominent bone.
4. Sagittal adjusting screw insertion
- Insert the guidewire through the cannulated hole of the needle after insertion. Ensure that the wire does not breach the anterior cortex.
NOTE: The anterior cortex of the vertebral body does not always overlap with the anterior margin of the vertebra on the lateral fluoroscopic view due to bone morphology. Recheck the vertebra shape on axial CT images before needle insertion. - Use a 1 mm undersized cannulated tap for tapping. Assemble the tab extenders and cap to the SAS screws, and insert the screws into the vertebrae (Figure 1). Repeat all steps from steps 4.1 to 4.2 for as many instrumented levels as necessary.
NOTE: Place all SAS screws parallel to the endplates in the sagittal plane to maximize the distraction force of the reduction device. Keep in mind that the risk of rod impingement on the facet joint, lamina, or spinous process will increase if the screw heads are located obliquely on the coronal plane. - If necessary, make modifications to the fixation at this step, such as intermediate screws (screws in the fractured vertebra) and additional screws on the two levels above/below in cases of severe deformity or impaired bone strength. Insert additional screws after fracture reduction as needed.
NOTE: When inserting screws into the fractured vertebra, ensure that the instruments do not exceed the anterior wall of the vertebra. The fractured bone offers significantly less resistance, and sharp instruments may easily deviate anteriorly due to the fracture void.
Normal multiaxial screws are usually used for intermediate screws or additional screws because rod connections may become difficult when the SAS is used for these levels. When using intermediate screws, ensure that there is no fracture in the pedicles.
5. Fracture reduction using a trauma reduction device
NOTE: This process has been described previously10.
- Set the distractor pinion of the reduction device in a neutral position. Slide the distractor rack into the distractor pinion.
- Place the inner guides on the extenders until they are fully seated. Ensure that the distractor module is placed in the posts of the extenders, and the distractor module is fully seated.
- Place the lordosis modules in a neutral position. Ensure that the distraction key is turned to distract to obtain ligamentotaxis.
- Stretch the posterior longitudinal ligament and bring the vertebral body segments back into the vertebral body from the spinal canal to restore the vertebral body height.
NOTE: Increase the incision size to seat the device if the device pinches the surrounding skin. Ensure that adequate deep application of the device is impossible in morbidly obese patients. Normal distraction/compression devices for the PPS system can still be used in these patients. - Set the lordosis indicator to zero on the lordosis module so that the lordosis indicator slides along the rack and allows an estimation of the extent of lordosis that has been applied. Each marking on the lordosis module is 2.5°. Check the real-time alignment with fluoroscopy during this maneuver.
- Squeeze the handles to restore lordosis and monitor the correction of lordosis under fluoroscopy. Verify the final correction. (Figure 2 and Figure 3).
- If deemed necessary, perform vertebroplasty using hydroxyapatite bone substitute or bone cement at this point. Place a guide needle, followed by a wire, dilator, and inserter, into the fractured vertebra via a transpedicular approach.
NOTE: It is crucial to ensure that all instruments remain within the bone during the procedure, as breaching the vertebral cortex is more likely given the compromised integrity of the fractured bone. Intermediate screw placement is also possible after vertebroplasty. If bone cement is used, prepare the screws in advance to ensure their insertion before the bone cement has fully consolidated.
- If deemed necessary, perform vertebroplasty using hydroxyapatite bone substitute or bone cement at this point. Place a guide needle, followed by a wire, dilator, and inserter, into the fractured vertebra via a transpedicular approach.
6. Rod connection
- Measure the rod lengths using a rod ruler placed on the screw heads or a measure placed on the skin. Cut the rods at least 5 mm longer than the measurements to avoid the shortage of rod length; re-confirm the length with a measure before insertion. For fractures in or below the mid-thoracic level, insert the rods through the uppermost incision. For upper thoracic fractures, insert the rods from the lowermost incisions since inserting rods in the cranial to caudal direction is often difficult due to the kyphotic shape of the thoracic spine.
NOTE: Rod bending is usually unnecessary at the thoracic or thoracolumbar junctional level. For the lumbar level, rods need to be bent, or use prebent rods to match the lumbar lordosis. - Ensure again that all the implants, rods, and screw heads are located under the fascial layer before closure to prevent compartment syndrome of back muscles.
- Apply set screws to fix the rod in an appropriate position. If the set screw application is difficult, check the depth of the screws and adjust them adequately.
NOTE: Ensure that the bilateral rods are placed parallel on the coronal plane to slide both rods appropriately during reduction.
7. Wound closure and after-treatment
- Irrigate the wounds with 500-1,000 mL of 0.5% diluted povidone-iodine solution18,19. Subsequently, apply a layered suture with size 0 antibacterial absorbable poly-filament suture for fascial layer closure and 2-0 or 3-0 antibacterial absorbable poly-filament suture for the subcutaneous layer. Close the epidermal layer using a topical skin adhesive glue or thin adhesive bandage. Ensure again that all the implants, rods, and screw heads are located under the fascial layer before closure to prevent compartment syndrome of back muscles20.
- Use a soft brace for comfort and start ambulation as soon as possible.
NOTE: Although there is no clear evidence to support the use of a brace after spine fracture surgery21, a Jewett type frame brace may be applied for patients who have certain risk factors of reduction loss, such as preexisting spinal malalignment or osteoporosis, based on the treating physician's discretion. - Use intravenous and oral acetaminophen as the first-line medication for pain management or nonsteroidal anti-inflammatory drugs (NSAIDs) to control severe pain and reduce opioid use. Discharge the patient after confirming they can ambulate safely outside the hospital.
NOTE: Try to minimize the dosage of NSAIDs as they likely inhibit bone fusion after spinal fusion surgery22, although the effect of NSAIDs on bone healing after spinal fracture is still inconclusive23. Moreover, minimize opioid use since opioids may inhibit bone healing24 and are associated with various complications and higher readmission rates25. - Perform radiological follow-up per institutional protocol. To follow this protocol, obtain AP and lateral radiographs immediately and at 1, 3, 6, and 9 months after the surgery. Additionally, obtain postoperative CT scans before implant removal, approximately 1 year after the surgery, to confirm bone union.
- For radiological assessment, use the regional kyphotic angle (RKA) and percent loss of anterior vertebral body height (%AVB) on lateral radiographs (Figure 1).
- Measure the RKA of the fractured segment as the angle between the superior endplate of the upper adjacent vertebra and the inferior endplate of the lower adjacent vertebrae26.
- Calculate the %AVB as the anterior height of the fractured vertebra divided by the mean of the anterior height of the adjacent two vertebrae using the following formula:
AVB = 100 {1- (a1 + a2)/2 ×a0}
Where the anterior vertebral body height of the fractured vertebra is marked as a0, and the anterior vertebral body heights of the upper and lower adjacent vertebrae are marked as a1 and a2, respectively27.
NOTE: We utilized %AVB because the RKA could be improved even if the fractured vertebra is not reduced, owing to the flexibility of the intervertebral disk.
- For radiological assessment, use the regional kyphotic angle (RKA) and percent loss of anterior vertebral body height (%AVB) on lateral radiographs (Figure 1).
- Remove the implant approximately 1 year after the initial surgery to restore segmental motion and prevent long-term consequences associated with the fixed region.
NOTE: Patients who had undergone implant removal had a better quality of life and less symptoms than those not undergoing implant removal28.
Results
Patient selection
The records of patients with traumatic burst fractures who underwent spine surgery between January 1, 2022, and October 31, 2023, at our university hospital were retrospectively reviewed. Patients who underwent posterior fixation with SAS devices using a trauma reduction device and met the following criteria were included in the final analysis.
Data collection and classifications
Information on age, biological sex, and fractured level was obtained from patient records. During the study period, SAS was initially used without a specialized trauma reduction device (SAS group). Subsequently, a new specialized trauma reduction device9 became available and we employed this device in all cases (SAS with new trauma device group). Consequently, analyses were conducted to stratify the results based on the use of the new trauma reduction device. Along with the AO classification13 and total TLICS12 score, load-sharing classification (LSC), a grading system of vertebral body comminution29, was also evaluated preoperatively.
Radiological outcomes and complications
All patients underwent lumbar AP and lateral radiographs preoperatively, postoperatively, and at the final follow-up. Radiograph evaluation included measurements of the RKA and %AVB, as shown in protocol step 1.1. Additionally, any intra/postoperative complications related to surgery or devices were recorded.
Results of representative case series:
A total of 15 patients met the inclusion criteria. PLL was considered intact in all cases on preoperative MRI, and no patient showed any reverse cortical sign or suspected PLL injury on intraoperative fluoroscopy. The median time between initial injury and operation was 4.5 days (range: 1-12 days). The reasons for late surgery (>7 days) were concomitant head trauma requiring surgery, unstable respiratory status due to traumatic pneumothorax, and hospital administrative reasons such as operating room availability. All 15 patients were included in the final analysis. The median age was 31.0, and 73.3% (11/15) of the patients were male (Table 2).
Five patients underwent surgery using the conventional SAS system, whereas the other 10 underwent fixation using the new SAS system. In the AO classification, most burst fracture types were categorized as Type A (compression injuries), specifically Type A3 (incomplete burst) or A4 (complete burst). Two cases were categorized as Type B (distraction injuries). The total TLICS score was 3.9, and more than half of the patients were categorized as having a TLICS score ≥ 4. The mean LSC score was 6.8 (Table 3).
The mean RKA improved on average 5.0° in the SAS with the conventional device group and 3.3° in the SAS with the new trauma device group. The %AVB improved in both groups (Table 4). Regarding RKA, since the local alignment is different by vertebral levels and a substantial proportion of lower lumbar spine fractures, such as L4 or L5, were included, only changes between pre- and postoperative values are shown in the table. The only complication reported was one case of superficial SSI requiring debridement in the new device group.
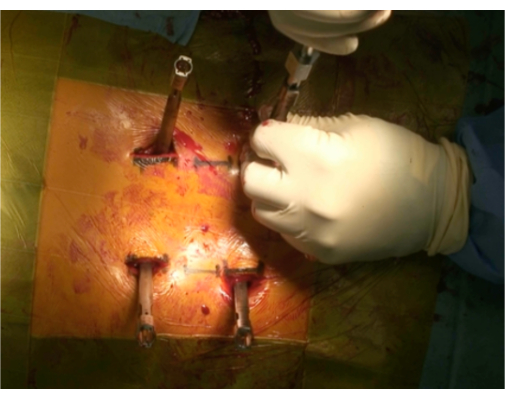
Figure 1: Incision and screw insertion. The vertical incisions are placed 1-1.5 cm lateral to the lateral margin of the pedicles in the lumbar spine as per the standard technical notes for PPS. The tab extenders and cap must be assembled using SAS screws. Abbreviations: PPS = percutaneous pedicle screw; SAS = sagittal adjusting screw. Please click here to view a larger version of this figure.
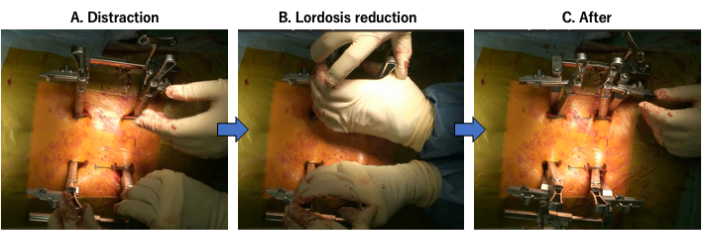
Figure 2: Fracture reduction with a trauma reduction device. (A) The lordosis indicator is set to zero on the lordosis module. (B) The handles are squeezed to restore lordosis. The correction of lordosis is monitored under fluoroscopy, and the final correction should be verified. (C) The reduction is completed. Please click here to view a larger version of this figure.
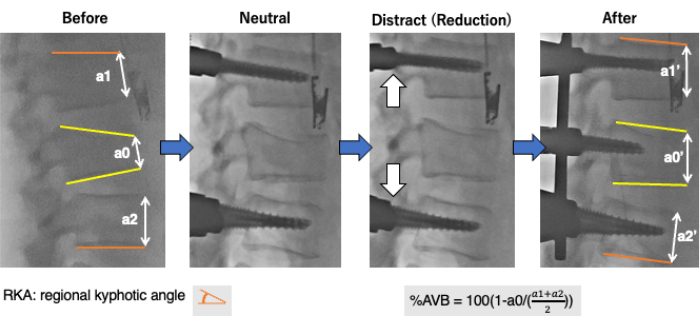
Figure 3: Fracture reduction and measurements. The image of fluoroscopy is shown. Neutral: The lordosis indicator is set to zero on the lordosis module. Reduction: The handles are squeezed to restore lordosis, and the height of the anterior wall of the fractured vertebrae is corrected. After: Insert pedicle screws to fractured vertebrae, and the fixation will be completed with the rod connection. Please click here to view a larger version of this figure.
Table 1: Contraindications for short segmental percutaneous non-fusion fixation using sagittal adjusting screw. Abbreviations: PLL = Posterior longitudinal ligament; AO: Arbeitsgemeinschaft Osteosynthesefragen. Please click here to download this Table.
Table 2: Demographic data. Abbreviation: SAS = sagittal adjusting screw. Please click here to download this Table.
Table 3: Classifications and scores. Abbreviations: AO = Arbeitsgemeinschaft Osteosynthesefragen; TLICS = thoracolumbar injury classification and severity; LSC = load-sharing classification; SAS = sagittal adjusting screw Please click here to download this Table.
Table 4: Fracture reduction parameters. Abbreviations: RKA = regional kyphotic angle; %AVB = % loss of anterior vertebral body height; SAS = sagittal adjusting screw. Please click here to download this Table.
Discussion
In this video manuscript, we describe our posterior minimally invasive fixation procedure for TL burst fractures using the SAS system and a trauma reduction device. Our representative case series showed good correction of the local kyphotic deformity and vertebral morphology. In previous studies, the potential reduction of kyphosis is 5-9% using an open approach30. Our data demonstrated results comparable to those of the open approach, even with a percutaneous approach. This is consistent with one meta-analysis of the treatment of TL burst fractures that reported a high level of evidence for the effectiveness of pedicle screw fixation without fusion and less invasive percutaneous approaches1.
As shown in Table 1, the SAS system and trauma reduction device are especially beneficial for certain types of fracture but have little additional benefit over conventional mono- or polyaxial PPS systems for other types. The SAS system and trauma reduction device can be used regardless of neurological symptoms. Patients with neurological symptoms and nerve compression often require direct decompression of nerves. Laminectomy can be done either before or after the percutaneous application of SAS, although surgical exposure is easier when it is performed before instrumentation. A study reported that the quality of TL fracture reduction with ligamentotaxis is better when performed earlier16.
For TL fracture patients with traumatic TL spinal cord injury, although the literature is scant, a meta-analysis showed significant improvement in patients undergoing decompression within 8 h of injury31. Early surgery also lowers the complication rate for TL fracture patients with neurological injury32. For patients with polytrauma, early surgery for TL fracture is generally beneficial33. However, there are substantial individual differences in polytraumatized patients. A small study suggested that AO type A injuries have less benefit on early spinal stabilization compared to type B and C injuries34. Therefore, surgical plans must be tailored to the patient's condition and institutional resources.
There are three ways to make skin incisions for minimally invasive screw placement: intermittent transverse incisions, intermittent longitudinal incisions, or long midline skin incisions with transfascial screw insertion. Rod insertion is easier with a longitudinal incision used as the insertion site than with transverse incisions. Using transverse incisions, adjusting the insertion angle is easier and especially beneficial for patients with vertebral rotation. We usually use longitudinal incisions at the rod insertion sites and transverse or intermittent longitudinal incisions elsewhere. The long midline incision, which is not "percutaneous" but still has muscles attached to the lamina, is sometimes used for upper-middle thoracic spine fractures because the pedicles are too close to make separate incisions or in cases requiring direct decompression. Studies demonstrated that muscle splitting PPS approach with midline incision showed better results in ambulation, operation time, blood loss, and postoperative analgesic consumption than conventional open approach35.
In our experience, the key step in a successful reduction is the insertion of screws parallel to the endplates. If screws are placed in diverging positions on the sagittal plane, correction of the lordosis can be difficult. In addition, because the SAS is exposed to substantial force during the reduction maneuver, reduction may cause screw loosening owing to excessive stress. Insertion of the longest screws possible is another key factor in obtaining good correction and preventing screw loosening. Studies have demonstrated that longer screws provide a more secure fixation36.
Regarding the number of fixation levels, short-segment fixation, such as one above to one below, can preserve more segmental motion and may prevent adjacent segmental disorders. However, several studies suggest that short-segment pedicle screw instrumentation is associated with a high failure rate. To date, there is no consensus on this issue37. Despite this, intermediate screws, which are pedicle screws placed in fractured vertebrae, have also become common. Intermediate screws may increase the stiffness of the implant, reduce stress on other screws, and improve clinical outcomes38,39. One clinical study demonstrated that patients with a six-screw construct and construct with intermediate screws exhibit a lower failure rate than those with a four-screw construct40. We always consider the use of intermediate screws unless there are contraindications, such as pedicle fractures. In addition, if one or more intermediate screws cannot be used for certain reasons, we often extend the fixation to one more upper level because the lower levels usually have more movement.
Another modification of this technique is vertebroplasty. For decades, various techniques have been used to fill the vertebral gap, and the grafted materials include cancellous bone, hydroxyapatite (HA) sticks, and bone cement. Finite element model studies have demonstrated that short-segment instrumentation augmented with cement vertebroplasty at the fracture level increases rigidity beyond instrumentation alone39,41. In our experience with the SAS system, a fracture void in the middle of the vertebral body in a young patient is unlikely to collapse if the outer cortices are well attached. Therefore, we do not use vertebroplasty in these patients. Moreover, we often use cement vertebroplasty with intermediate screws in older patients. In addition, HA is used to fill the gap and support the endplate in young patients with fracture voids just under the upper endplate. However, there is limited evidence regarding this method, and further studies are required.
Several complications are associated with TL fracture surgery. The following are procedure-specific complications and their related management.
Malplacement of screws may lead to nerve injury, iatrogenic fracture, implant failure, and correction loss. Follow proper procedures in each step with fluoroscopic guidance. If available, an intraoperative CT scan must be used with a navigation system42, especially for patients with a severely degenerated spine that makes identifying pedicles difficult on AP fluoroscopic view.
Great vessels or branches are endangered while inserting wires or needles during the PPS procedure43,44. Several life-threatening cases have been reported. Careful preoperative planning and real-time fluoroscopic monitoring are key for prevention.
One must be wary of unexpected vital signs such as low blood pressure; vascular surgeons must be immediately consulted when suspecting major great vessel injury. Successful intervention with prompt diagnosis with angiography and interventional radiological procedures has been reported45.
Iatrogenic intraoperative vertebral fracture and implant breakage during reduction may occur when excessive reduction force is applied to the device. Real-time fluoroscopic monitoring can help avoid excessive stress on implants or bones. In case a fracture occurs at an instrumented level, the fusion level can be extended one level above or below.
Trauma reduction devices should be used carefully or avoided in patients with osteoporosis46. Extreme care must be exercised when applying reduction force to osteoporotic bones. The diagnostic standard for low bone mineral density is dual X-ray absorptiometry (DXA); however, it is often difficult to obtain DXA scan before TL fracture surgery. In such cases, we assess Hounsfield unit value in the vertebral body on CT as a surrogate marker of DXA scan. Approximately <150 and <110 are considered diagnostic thresholds for osteopenia and osteoporosis, respectively47. In cases of severe osteoporosis, alternative surgical approaches should be considered. These may include cement kyphoplasty if the posterior vertebral wall is intact or a combined anterior-posterior surgical approach to minimize excessive stress on the posterior instrumentation.
Compartment syndrome due to inadequate placement of rods over the fascia may result in deep surgical site infection (SSI). The wound must be closed only after ensuring that all implants are placed under the fascia20. In case it occurs, the compartment must be released surgically as soon as possible.
SSI may occur after PPS fixation. The wound must be washed with povidone-Iodine solution48 before the closure and sutured tightly in each layer to prevent SSI. Although this is a minimally invasive surgical procedure, the wounds must not be too small. Skin necrosis caused by an excessively stretched wound due to too small an incision may lead to SSI. Further, a small incision may lead to entanglement of the surgical drape into the wound during PPS insertion. A study demonstrated that iodophor-impregnated adhesive incision drapes reduce postoperative SSI compared to nonimpregnated adhesive incision drapes17.
Although the obtained alignment is usually well preserved in patients with SAS fixation, secondary displacement can occur.In a systematic review49, approximately 70% of observational studies reported varying degrees of sagittal correction loss or local kyphosis deformity. The degree of deformity ranged from 0 to 64°. A study demonstrated that 15% of their patients demonstrate >20% height loss, and an age at operation > 43 years old and preoperative body height loss > 54% are risk factors for secondary vertebral height loss after surgery50.
Kyphotic deformities may also be noted after implant removal. A high degree of preoperative local kyphosis and high ratio of canal compromise on preoperative computed tomography scanning are reportedly risk factors for kyphosis recurrence after screw removal51. However, further studies are required to make strong recommendations and inform patients about the possibility of deformity recurrence during follow-up and after implant removal. Keep in mind that additional corrective surgery might be required in cases of severe secondary displacement.
Despite its usefulness, our SAS technique has a few limitations. First, this reduction technique has a certain risk for implant failure or iatrogenic fractures; thus, it is not recommended for patients with severe osteoporosis. Although only a few studies have directly evaluated the safety of fracture reduction maneuvers for TL fracture patients with osteoporosis, plenty of studies have reported the negative impact of osteoporosis on the outcomes of elective spine instrumentation surgery52. Cement-augmented pedicle screws have recently been used to treat patients with osteoporosis. A small study reported a good reduction of retropulsion fragments in osteoporotic vertebral fracture with ligamentotaxis using cement-augmented screws53. However, the amount of reduction force that can be tolerated by cement augmentation remains unclear. In addition, there is no clear cutoff value for bone strength specifically for the use of this SAS system. Another issue is that correction loss may occur during follow-up or after implant removal. A recent study showed that severe disc and endplate destruction at the time of the initial injury is associated with correction loss and the presence of low back pain after TL burst fracture surgery37. The interaction between the vertebrae, discs, and endplates has not yet been elucidated, and these issues need to be addressed in future studies.
Disclosures
I.O. receives lecture fees from Medtronic. The other authors declare that they have no conflicts of interest concerning the materials or methods used in this study or the findings specified in this paper.
Acknowledgements
We would like to thank Mr. Yudai Watanabe, a representative of Medtronic, for the implant information, Editage for editing and reviewing this manuscript in the English language, and radiology technicians and all surgical staff for helping obtain surgical images.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 3M Ioban 2 antimicrobial incise drape | 3M | MSDS_0832279_US_EN_RDS | Iodophor-impregnated adhesive incision drape |
| CDH Solera Longitude II SAS | Medtronic | SAS system | |
| CDH Solera Voyager FNS SAS | Medtronic | SAS system | |
| DERMABOND ADVANCED Topical Skin Adhesive | Ethicon Inc. | Topical skin adhesive glue or thin adhesive bandage | |
| INFINITT PACS | INFINITT Healthcare Co., Ltd. | Picture archiving and communication system | |
| Jewett brace | (Various manufacturers) | Jewett type brace | |
| Nforce Trauma | Medtronic | Trauma reduction device | |
| OEC Elite | GE healthcare | Fluoroscopy/image intensifier/c-arm | |
| Sacro-wide Dx | Alcare | 368-0208-0223/5 | Soft brace |
| Steri Strips Standard Skin Closure | 3M | MSDS_1084623_US_EN_AIS | Thin adhesive bandage. |
| Trauma Instrument Set | Medtronic | Trauma reduction device | |
| Vicryl Plus Antibacterial 0 | Ethicon Inc. | VCP587H | Antibacterial absorbable poly-filament suture |
| Vicryl Plus Antibacterial 2-0 | Ethicon Inc. | VCP453H | Antibacterial absorbable poly-filament suture |
| Vicryl Plus Antibacterial 3-0 | Ethicon Inc. | VCP398H | Antibacterial absorbable poly-filament suture |
References
- Scheer, J. K., et al. Evidence-based medicine of traumatic thoracolumbar burst fractures: A systematic review of operative management across 20 years. Global Spine J. 5 (1), 73-82 (2015).
- Ni, W. F., et al. Percutaneous pedicle screw fixation for neurologic intact thoracolumbar burst fractures. J Spinal Disord Tech. 23 (8), 530-537 (2010).
- Proietti, L., et al. Posterior percutaneous reduction and fixation of thoraco-lumbar burst fractures. Orthop Traumatol Surg Res. 100 (5), 455-460 (2014).
- Ohba, T., Ebata, S., Haro, H. Comparison of serum markers for muscle damage, surgical blood loss, postoperative recovery, and surgical site pain after extreme lateral interbody fusion with percutaneous pedicle screws or traditional open posterior lumbar interbody fusion. BMC Musculoskelet Disord. 18 (1), 415(2017).
- Regev, G. J., Lee, Y. P., Taylor, W. R., Garfin, S. R., Kim, C. W. Nerve injury to the posterior rami medial branch during the insertion of pedicle screws: Comparison of mini-open versus percutaneous pedicle screw insertion techniques. Spine (Phila Pa 1976). 34 (11), 1239-1242 (2009).
- Toyone, T., Tanaka, T., Kato, D., Kaneyama, R., Otsuka, M. The treatment of acute thoracolumbar burst fractures with transpedicular intracorporeal hydroxyapatite grafting following indirect reduction and pedicle screw fixation: A prospective study. Spine (Phila Pa 1976). 31 (7), E208-E214 (2006).
- Ishii, K., et al. The history and development of the percutaneous pedicle screw (pps) system. Medicina (Kaunas). 58 (8), 1064(2022).
- Hoffmann, M. F., Kuhlmann, K., Schildhauer, T. A., Wenning, K. E. Improvement of vertebral body fracture reduction utilizing a posterior reduction tool: A single-center experience. J Orthop Surg Res. 18 (1), 321(2023).
- Linhart, C., et al. A novel device for closed reduction and percutaneous fixation of thoracolumbar fractures. In Vivo. 36 (1), 384-390 (2022).
- Jasinski, J., Tong, D., Hanson, C., Soo, T. Sagittal adjusting screws for the correction of grade iv spondylolisthesis in a patient with ehlers-danlos syndrome: Illustrative case. J Neurosurg Case Lessons. 2 (2), Case21196(2021).
- Dandurand, C., et al. Understanding decision making as it influences treatment in thoracolumbar burst fractures without neurological deficit: Conceptual framework and methodology. Global Spine J. 14 (1_suppl), 8s-16s (2024).
- Lee, J. Y., et al. Thoracolumbar injury classification and severity score: A new paradigm for the treatment of thoracolumbar spine trauma. J Orthop Sci. 10 (6), 671-675 (2005).
- Vaccaro, A. R., et al. Aospine thoracolumbar spine injury classification system: Fracture description, neurological status, and key modifiers. Spine (Phila Pa 1976). 38 (23), 2028-2037 (2013).
- Grenier, N., et al. Normal and disrupted lumbar longitudinal ligaments: Correlative mr and anatomic study. Radiology. 171 (1), 197-205 (1989).
- Arlet, V., Orndorff, D. G., Jagannathan, J., Dumont, A. Reverse and pseudoreverse cortical sign in thoracolumbar burst fracture: Radiologic description and distinction--a propos of three cases. Eur Spine J. 18 (2), 282-287 (2009).
- Cirillo, J. I., et al. Surgical timing prevails as the main factor over morphologic characteristics in the reduction by ligamentotaxis of thoracolumbar burst fractures. BMC Surg. 23 (1), 166(2023).
- Gencer, A., Schichor, C., Tonn, J. C., Siller, S. Reducing the rate of surgical site infection using iodophor-impregnated adhesive incision draping in spine surgery compared with standard adhesive incision draping: A study in 2279 patients. J Neurosurg Spine. 40 (2), 248-254 (2024).
- Yamada, K., et al. Evidence-based care bundles for preventing surgical site infections in spinal instrumentation surgery. Spine (Phila Pa 1976). 43 (24), 1765-1773 (2018).
- Carballo Cuello, C. M., Fernández-De Thomas, R. J., De Jesus, O., De Jesús Espinosa, A., Pastrana, E. A. Prevention of surgical site infection in lumbar instrumented fusion using a sterile povidone-iodine solution. World Neurosurg. 151, e700-e706 (2021).
- Sudhir, G., Adsul, N. M., Acharya, S., Chahal, R. S. Compartment syndrome of lumbar paraspinal musculature after percutaneous pedicle screw fixation. Surg Neurol Int. 9, 190(2018).
- Nourian, S. M. A., Mozafari, S., Farzinnia, S., Saeidi, M., Bahrami, M. Evaluation of postoperative bracing on unstable traumatic lumbar fractures after pedicle screw fixation. Int J Burns Trauma. 12 (4), 168-174 (2022).
- Lindsay, S. E., Philipp, T., Ryu, W. H. A., Wright, C., Yoo, J. Nonsteroidal anti-inflammatory drugs in the acute post-operative period are associated with an increased incidence of pseudarthrosis, hardware failure, and revision surgery following single-level spinal fusion. Spine (Phila Pa 1976). 48 (15), 1057-1063 (2023).
- Piche, J. D., Muscatelli, S., Ahmady, A., Patel, R., Aleem, I. The effect of non-steroidal anti-inflammatory medications on spinal fracture healing: A systematic review. J Spine Surg. 7 (4), 516-523 (2021).
- Lambrechts, M. J., et al. The inhibitory effect of NSAIDs and opioids on spinal fusion: An animal model. Spine (Phila Pa 1976). 49 (12), 821-828 (2024).
- Ballatori, A. M., et al. Post-operative complications associated with long-term NSAID or long-term opioid use prior to lumbar spinal fusion surgery. Clin Neurol Neurosurg. 236, 108093(2024).
- Nguyen, N. Q., Phan, T. H. The radiological complications of short-segment pedicle screw fixation combined with transforaminal interbody fusion in the treatment of unstable thoracolumbar burst fracture: A retrospective case series study in Vietnam. Orthop Res Rev. 14, 91-99 (2022).
- Mumford, J., Weinstein, J. N., Spratt, K. F., Goel, V. K. Thoracolumbar burst fractures. The clinical efficacy and outcome of nonoperative management. Spine (Phila Pa 1976). 18 (8), 955-970 (1993).
- El Saman, A., Meier, S. L., Rüger, F., Hörauf, J. A., Marzi, I. Impact of implant removal on quality of life and loss of correction in the treatment of traumatic fractures of the thoracolumbar spine. Brain Spine. 4, 102845(2024).
- Mccormack, T., Karaikovic, E., Gaines, R. W. The load sharing classification of spine fractures. Spine (Phila Pa 1976). 19 (15), 1741-1744 (1994).
- Loibl, M., et al. Spinal fracture reduction with a minimal-invasive transpedicular schanz screw system: Clinical and radiological one-year follow-up. Injury. 46 (Suppl 4), S75-S82 (2015).
- Bhimani, A. D., Carr, M. T., Al-Sharshai, Z., Hickman, Z., Margetis, K. Ultra-early (≤8 hours) surgery for thoracolumbar spinal cord injuries: A systematic review and meta-analysis. N Am Spine Soc J. 16, 100285(2023).
- Ruddell, J. H., Depasse, J. M., Tang, O. Y., Daniels, A. H. Timing of surgery for thoracolumbar spine trauma: Patients with neurological injury. Clin Spine Surg. 34 (4), E229-E236 (2021).
- Bliemel, C., et al. Early or delayed stabilization in severely injured patients with spinal fractures? Current surgical objectivity according to the trauma registry of dgu: Treatment of spine injuries in polytrauma patients. J Trauma Acute Care Surg. 76 (2), 366-373 (2014).
- Kobbe, P., et al. Early spinal injury stabilization in multiple-injured patients: Do all patients benefit. J Clin Med. 9 (6), 1760(2020).
- Ulutaş, M., Seçer, M., Çelik, S. E. Minimally invasive mini open split-muscular percutaneous pedicle screw fixation of the thoracolumbar spine. Orthop Rev (Pavia). 7 (1), 5661(2015).
- Berlemann, U., Cripton, P. A., Rincon, L., Nolte, L. P., Schläpfer, F. Pull-out strength of pedicle hooks with fixation screws: Influence of screw length and angulation. Eur Spine J. 5 (1), 71-73 (1996).
- Hashimura, T., et al. Correction loss following short-segment posterior fixation for traumatic thoracolumbar burst fractures related to endplate and intervertebral disc destruction. BMC Musculoskelet Disord. 24 (1), 174(2023).
- Han, Y., Ma, J., Zhang, G., Huang, L., Kang, H. Percutaneous monoplanar screws versus hybrid fixed axial and polyaxial screws in intermediate screw fixation for traumatic thoracolumbar burst fractures: A case-control study. J Orthop Surg Res. 19 (1), 85(2024).
- Liao, J. C., Chen, W. P., Wang, H. Treatment of thoracolumbar burst fractures by short-segment pedicle screw fixation using a combination of two additional pedicle screws and vertebroplasty at the level of the fracture: A finite element analysis. BMC Musculoskelet Disord. 18 (1), 262(2017).
- Liao, J. C., Fan, K. F. Posterior short-segment fixation in thoracolumbar unstable burst fractures - transpedicular grafting or six-screw construct. Clin Neurol Neurosurg. 153, 56-63 (2017).
- Xu, G., et al. Biomechanical effects of vertebroplasty on thoracolumbar burst fracture with transpedicular fixation: A finite element model analysis. Orthop Traumatol Surg Res. 100 (4), 379-383 (2014).
- Baldwin, K. D., et al. Does intraoperative ct navigation increase the accuracy of pedicle screw placement in pediatric spinal deformity surgery? A systematic review and meta-analysis. Spine Deform. 10 (1), 19-29 (2022).
- Hsiao, M. C., Huang, S. J., Kao, T. H. Pseudoaneurysm formation of segmental artery with retroperitoneal hematoma after percutaneous transpedicular screws insertion. J Clin Neurosci. 113, 20-21 (2023).
- Yamamoto, K., et al. Retroperitoneal hematoma: A rare complication of percutaneous pedicle screw in an osteoporotic patient. Surg Neurol Int. 14, 345(2023).
- Martin, S., Lindsay, R., Baker, R. C. Simultaneous endovascular repair of a thoracic aortic injury during posterior pedicle screw removal: A case report. Ann Vasc Surg. 48, 252.e251-252.e254 (2018).
- Wood, K. B., Li, W., Lebl, D. R., Ploumis, A. Management of thoracolumbar spine fractures. Spine J. 14 (1), 145-164 (2014).
- Schreiber, J. J., Anderson, P. A., Rosas, H. G., Buchholz, A. L., Au, A. G. Hounsfield units for assessing bone mineral density and strength: A tool for osteoporosis management. J Bone Joint Surg Am. 93 (11), 1057-1063 (2011).
- Torres, K. A., et al. Irrigation techniques used in spine surgery for surgical site infection prophylaxis: A systematic review and meta-analysis. BMC Musculoskelet Disord. 23 (1), 831(2022).
- Wang, X., et al. The necessity of implant removal after fixation of thoracolumbar burst fractures-a systematic review. J Clin Med. 12 (6), 2213(2023).
- Jang, H. D., et al. Risk factor analysis for predicting vertebral body re-collapse after posterior instrumented fusion in thoracolumbar burst fracture. Spine J. 18 (2), 285-293 (2018).
- Aono, H., et al. Risk factors for a kyphosis recurrence after short-segment temporary posterior fixation for thoracolumbar burst fractures. J Clin Neurosci. 66, 138-143 (2019).
- Rometsch, E., et al. Screw-related complications after instrumentation of the osteoporotic spine: A systematic literature review with meta-analysis. Global Spine J. 10 (1), 69-88 (2020).
- Mallepally, A. R., Marathe, N., Sangondimath, G., Das, K., Chhabra, H. S. Posterior stabilization without neural decompression in osteoporotic thoracolumbar fractures with dynamic cord compression causing incomplete neurological deficits. Global Spine J. 12 (3), 464-475 (2022).
Reprints and Permissions
