This article provides a step-by-step guide to correcting presbyopia with a monocular bi-aspheric ablation profile.
Method Article
Correction of Presbyopia by Monocular Bi-Aspheric Ablation Profile
In This Article
Summary
Abstract
The study aims to evaluate visual acuity and objective visual quality before and after the monocular bi-aspheric ablation profile for correction of presbyopia surgery. This prospective self-control study included 20 cases and 38 eyes of patients who underwent monocular bi-aspheric ablation profile correction of myopia with presbyopia at the Eye Hospital of Shandong University of Traditional Chinese Medicine from January 2023 to January 2024. These patients were selected for observation, and each patient's preoperative and postoperative uncorrected distance visual acuity (UDVA), uncorrected near visual acuity (UNVA), corrected distance visual acuity (CDVA), spherical aberration (SA) (within 6 mm), horizontal and vertical coma (within 6 mm), and corneal aspheric index (Q-value) (within 6 mm) were evaluated. Statistical data analysis was performed at different time points before and after the operation. There were statistically significant differences in UDVA between dominant and non-dominant eyes before and after surgery (Z = -3.784, p < 0.001; Z = -3.817, p < 0.001). Post-operatively, 90% of the non-dominant eyes achieved UNVA of J1 and above, and 95% of the bilateral eyes achieved UNVA of J1 and above. Significant differences were found in the SA of the dominant eyes, which showed a positive increase (Z= -3.784, p < 0.001); however, compared with the dominant eye, the SA of the non-dominant eye was negatively increased, but the difference was not statistically significant (p = 0.08). There was a significant difference in the vertical coma of the dominant eye before and after the operation, but there was no significant difference in non-dominant eyes. There was no significant difference in the change of binocular horizontal coma before and after the operation. There were significant changes in the Q value of both eyes before and after the operation (Z = -3.923, p < 0.001; Z = -3.51, p < 0.001). After the monocular bi-aspheric ablation profile, the cornea of the non-dominant eye showed a prolate shape, negative SA increased, and the UDVA and UNVA improved after the operation.
Introduction
Presbyopia is an age-related reduction in amplitude of accommodation leading to loss of near vision due to the loss of function of the lens and ciliary muscle1. The global population of presbyopes is projected to exceed 2 billion by 2030, with uncorrected and undercorrected presbyopia affecting socio-economic development2. Correction of presbyopia includes lens correction, surgical approaches, and medication. Corneal surgery is one of the main forms of corneal surgery to correct presbyopia because of its less invasive nature, fewer complications, and faster recovery3.
Ruiz introduced Presby laser-assisted in situ keratomileusis (LASIK) in 1996, which ablates the cornea into a multifocal pattern and increases the negative SA to achieve simultaneous near and distance vision4,5. Depending on the proximity area, Presby LASIK can be categorized into peripheral model6 (peripheral area for near vision and central area for distance vision) and central model7(peripheral area for distance vision and central area for near vision)8,9. The monocular bi-aspheric ablation profile is a hybrid Presby LASIK that combines the advantages of multiple programs, including micro-monocular vision, bi-aspheric, and multifocal. The dominant eye is completely corrected for distance vision, the central zone of the non-dominant eye retains approximately -0.89D of refraction for near vision, the peripheral cornea is ablated for distance vision, and the range of near addition (ADD) is between +1.25D to 2.50D, and aspheric cutting is used in both the central and peripheral zones10,11.
Compared with the previous monovision LASIK, the multifocal morphology of the non-dominant eye after the monocular bi-aspheric ablation profile reduces the anisometropia between the two eyes. The negative increase of SA introduces the depth of focus, which can better improve near vision and, at the same time, improve the intermediate vision, reduce the impact on stereopsis, and improve the patient's acceptance and satisfaction11,12,13. The monocular mode will lead to complete correction of the dominant eye, which can achieve the fastest postoperative clear full vision, reduce the risk of UDVA decline, and is more suitable for patients with presbyopia who have the same requirements for UDVA and UIVA, while other algorithms are multifocal in both eyes, which need more time for adaptation after surgery and have the risk of UDVA decline14,15,16. This article describes the detailed surgical steps of excimer laser multifocal double aspheric ablation mode as a surgical guide.
Protocol
The following protocol was reviewed and approved by the Ethics Committee of the Affiliated Eye Hospital of Shandong University of Traditional Chinese Medicine (Grant No. HEC-KS-2020002KY), and was strictly adhered to the Declaration of Helsinki. All patients signed an informed consent form.
1. Patient selection
NOTE: 20 patients (38 eyes) with presbyopia treated by excimer laser monocular multifocal bi-aspheric ablation were admitted to the Department of Refractive Surgery of the Eye Hospital Affiliated with Shandong University of Traditional Chinese Medicine. Baseline and follow-up examinations were performed.
- Inclusion criteria
- Include patients between 40-55 years of age diagnosed with presbyopia in both eyes.
- Include patients with a sphere range of -1.00 D to -8.00 D and a cylinder range ≥ -4.00 D.
- Include patients with an ADD range of +1.25D to +2.50 D.
- Include patients with best corrected distance visual acuity ≥ 0.8 and best corrected near visual acuity 40 cm > J2.
- Incule patients whose monocular test tolerates anisometropia of at least 1 D.
- Include patients with the diameter of the photopic pupil of 2.5-3.5 mm and dark pupil > 4.5 mm.
- Include patients whose corneal spherical aberration at 6 mm > 0.0 µm and the root mean square value (RMS) of corneal higher-order aberration (HOA) at 6 mm < 0.5 µm.
- Exclusion criteria
- Exclude patients who have active inflammation or infection of the eyes.
- Exclude patients with abnormal corneal topography and biomechanical examination before operation. Exclude if corneal stroma thickness < 300 µm after ablation and preoperative central corneal thickness < 470 µm.
- Exclude patients with pupil offset ≥ 0.7 mm.
- Exclude patients with other eye diseases affecting vision except refractive error, history of ophthalmic surgery (including laser corneal refractive surgery), history of trauma, etc.
- Exclude patients with anxiety, depression, and other mental states and with high requirements for postoperative visual quality and vision.
2. Preoperative preparation
- Examine the patient before refractive surgery.
- Identify the dominant eye using a Hole test.
- Adjust both eyes to the best corrected visual acuity (BCVA),straighten the arms. Cross the thumbs and index fingers to form a small triangle, and look at the bow 2.5 m in front.
- Cover the left eye; if the bow is still visible, the dominant eye is the right eye. If the bow is not visible, the dominant eye is the left eye.
- Calculate and adjust ADD.
- Select experimental ADD. Calculate it by the formula, ADD =15 - age/4.
- Adjust ADD. Mesaure negative relative accommodation (NRA) and positive relative accommodation (PRA) on an experimental ADD basis. Divide the algebraic sum of NRA and PRA by two plus experimental ADD.
- Determine the final prescription. For individuals whose reading distance is greater than 40 cm, reduce +0.25 D; For patients with reading distance less than 40 cm, add +0.25 D, make several subtle adjustments and try to confirm the final prescription, so that the patient's vision is clear and comfortable.
- Identify the dominant eye using a Hole test.
- Perform other preoperative examinations.
- Include slit-lamp microscopy, comparative sensitivity function, Sirius 3D anterior segment, and corneal aberration analyzer to measure corneal topographic, corneal aberration, and pupil size in light, medium, and dark environments.
- Measure the corneal morphology by three-dimensional anterior segment analysis and assess corneal biomechanics using a corneal visual biomechanics analyzer.Finally, perform cycloplegic refraction and fundus examination.
- Plan the surgical design.
- Use the anterior segment and corneal aberration analyzer, with the Aberration Free (AF) mode selected for the dominant eye to eliminate aberrations andtarget refraction of 0.
- The non-dominant eye was selected as the monocular mode, and according to the measured pupil size, the optical zone was set to 6.2-6.7 mm, the distant target was -0.89 D, and the central 3 mm area was introduced into ADD (depending on the patient, up to-2.50 D).
- Provide preoperative medications.
- Provide preoperative medications 3 days before the operation: levofloxacin hydrochloride eye drops 3 times a day and hydroxoglycoside eye drops 4 times a day.
3. Surgical procedure
- Flush and disinfect the eye.
- Ask the patient to open his eyes and look upward. Rinse the conjunctiva sac with 0.9% normal saline.
- Disinfect the skin within 6 cm around the eyelid center with a skin disinfectant. Apply promethacaine hydrochloride eye drops for ocular surface anesthesia every 10 min, a total of 2 times.
- Place the patient supine and put the head in the right position. Lay the surgical towel, expose the surgical eye, and drop artificial tears to moisten the ocular surface. Stick a transparent dressing frame, open the eyelid fissure to fully expose the cornea, and wipe the cornea with a wet sterile sponge (Figure 1).
- Use the femtosecond laser system to create the corneal flap (Figure 2). Attach the negative pressure suction ring to the laser emission window and treatment control panel.
- Select the flap mode and start the treatment steps according to the treatment program on the treatment screen. Ask the patient to look at the green light. Use the operating microscope and operating table joystick to align accurately.
- During alignment, make the watermark just in the center of the contact lens on the negative pressure ring and let it reach about 80%-90%.
- Start the negative pressure suction until the cornea completely adheres to the contact surface of the negative pressure ring. Hear Section On for the end of negative pressure suction, and hear Ready to prepare for the next step.
- Depress the pedal to start ablation, and urge the patient to stare at the green gaze light. Corneal stromal flap parameters: thickness: 100 µm; diameter: 8.1 mm; hinge angle: 90°;intrastromal scan laser energy: 125 nJ; edge cutting scan laser energy: 125 nJ. Once the corneal flap production is completed, release the pedal, disengage the negative pressure suction, and remove the negative pressure suction ring.
- Replace the negative pressure suction head and repeat steps 3.2-3.7 to treat the other eye.
- Guide the patient to the excimer laser surgical bed and place the patient supine. Lay the surgical towel, stick a transparent dressing frame, and open the eyelid fissure to fully expose the cornea. Rinse the corneas with a balanced saline solution and accurately align them with the aid of an operating microscope.
- Separate the corneal flap using a corneal flap separator, insert a light separation from the lateral incision near the hinge, and carefully separate the flap from the corneal stroma in the opposite direction of the pedicle until the corneal flap is completely opened, exposing the stroma. Finally, use the disposable sterile medical sponge to dry surface moisture.
- Use the excimer laser to ablate the corneal stroma (Figure 3). Verify the patient's information and cut using the excimer laser according to the surgical design. Ask the patient to stare at the gaze light, keep the eyes aligned with the laser, and center the corneal apex to select the corneal apex for the stromal ablation.
- At the end of the treatment, rinse the stroma with a compound electrolyte intraocular irrigating solution. Reset the corneal flap (Figure 4), and apply 0.3% tobramycin and dexamethasone eye drops. Observe the corneal reset under a slit lamp. Repeat step 3.8-3.9 to isolate the other corneal flap and perform stromal ablation.
- Guide the patient out of the operating table, put on a sterile eye mask, and ask the patient for a review the next day after the operation.
Results
A total of 20 patients who underwent the monocular bi-aspheric ablation profile for correction of presbyopia were analyzed in this study. The preoperative age of the patients was 47 (± 3.36) years, and the preoperative spherical equivalent (SE) of the dominant and non-dominant eyes were -4.47 D (± 2.16) D and -4.34 D (±2.09 D), respectively. All surgeries were completed with no postoperative complications.
Visual acuity results
There was no significant difference in CDVA between the dominant eye and the non-dominant eye before and after surgery, but there were significant differences in UDVA between the dominant eye, the non-dominant eye, and both eyes before and after surgery(Z = -3.755, p < 0.001; Z = -3.817, p < 0.001; Z = -3.800, p < 0.001) (Table 1).
Preoperatively, 70% of the dominant eye and over 60% of the non-dominant eyes achieved a UNVA of J5 or better, with no patients reaching a near visual acuity of J1. At 6 months post-operatively, 90% of patients in the non-dominant eye achieved a UNVA of J1 or better, while 100% of the dominant eye achieved J5 or better. Additionally, 95% of patients attained a BUNVA of J1 or better (Table 1).
Corneal asphericity index
The Q values of the dominant and non-dominant eyes were positively changed after surgery, and the changes were statistically significant, and the Q values of the dominant and non-dominant eyes were statistically significant when compared with each other 6 months after surgery(Z = -3.823, p < 0.001; Z = -3.510, p < 0.001; Z = -3.474, p < 0.05) (Table 2).
NOTE: See Table 2.
High order aberration
Both binocular SA increased positively after surgery; the change in dominant eye SA was statistically significant (Z = -3.784, p < 0.001), the change in non-dominant eye SA was not statistically significant, and the difference in binocular SA compared with each other 6 months after surgery was statistically significant (Z = -3.920, p < 0.001). There was a significant difference in the vertical coma of the dominant eye before and after the operation(Z = -2.503, p < 0.05), but there was no significant difference in the horizontal coma and vertical coma of the non-dominant eye (Table 3).
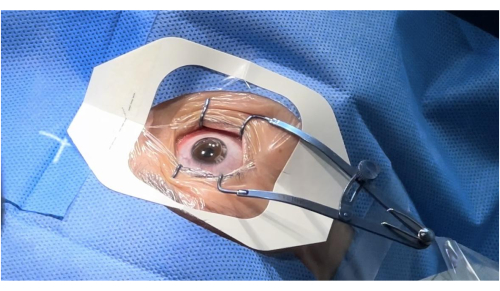
Figure 1: Patient positioning. Place the patient in the supine position, routinely flush the eyes, disinfect, spread the towel, apply the film and the lid opener to support the lid fissure, and fully expose the cornea. Please click here to view a larger version of this figure.

Figure 2: Creating the corneal flap. Use the femtosecond laser system to create the corneal flap. Please click here to view a larger version of this figure.
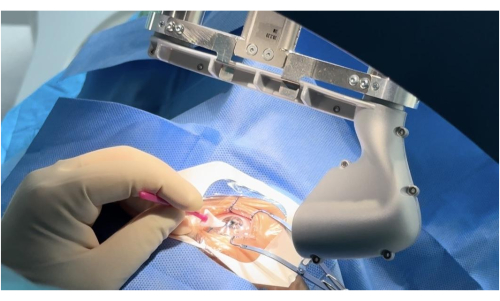
Figure 3: Corneal stromal ablation. Use the excimer laser to ablate the corneal stroma. Please click here to view a larger version of this figure.
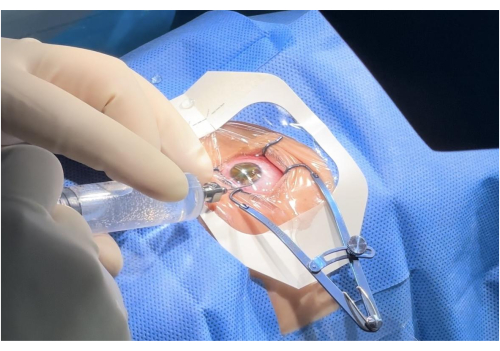
Figure 4: Flushing and resetting the corneal flap. The stroma is rinsed with a compound electrolyte intraocular irrigating solution, and the corneal flap is reset. Please click here to view a larger version of this figure.
| Eye | Pre | After | Z | p | |
| UDVA | Dom | 1.2 (0.95, 1.28) | 0 (0, 0) | -3.755 | <0.001 |
| Non | 1.1 (0.92, 1.3) | 0.2 (0.2, 0.38) | -3.817 | <0.001 | |
| OU | 1.1 (0.9, 1.2) | 0 (0, 0.1) | -3.8 | <0.001 |
Table 1: Changes in UDVA and CDVA before and after the operation.
| Eye | Pre | After | Z | p | |
| Q-value | Dom | -0.17 (-0.27, -0.12) | 0.59 (0.32, 0.96) | -3.823 | <0.001 |
| Non | -0.18 (-0.23, -0.13) | 0.46 (0.11, 0.79) | -3.51 | <0.001 |
Table 2: Changes in Q-value before and after the operation.
| Eye | Pre | After | t | p | ||
| SA | Dom | 0.24 (0.15, 0.29) | 0.5 (0.44, 0.6) | -3.784 | <0.001 | |
| Non | 0.23 (0.18, 0.32) | 0.11 (0.02, 0.32) | -1.752 | 0.08 | ||
| Horizontal | Dom | -0.11 (-0.21, -0.01) | -0.26 (-0.47, 0.03) | -1.755 | 0.079 | |
| Coma | ||||||
| Non | 0.13 (0.03, 0.17) | 0.16 (0, 0.27) | -0.959 | 0.338 | ||
| Vertical Coma | Dom | 0.15 (0.09, 0.22) | -0.03 (-0.19, 0.17) | -2.503 | 0.012 | |
| Non | -0.13 (-0.29, 0.07) | -0.14 (-0.44, 0.09) | -1.681 | 0.093 | ||
Table 3: Changes of Higher-order aberrations before and after the operation.
Discussion
Currently, there are limited effective methods for restoring ocular accommodation, making presbyopia a prominent area of research in refractive surgery. The bi-aspheric ablation profile, a widely recognized clinical modality for presbyopia correction, has shown favorable safety and efficacy with satisfactory postoperative outcomes15,16,17. However, there is a paucity of studies focusing on the monocular mode. In this study, we present a comprehensive guide to the surgical operation of the monocular bi-aspheric ablation profile and assess the postoperative visual outcomes and visual quality.
Preoperative evaluation is particularly important for patients with presbyopia, as multiple measurements are required to determine the dominant eye and the most appropriate ADD. The final choice of ADD is not only related to the measurement results, but also should pay attention to the subjective feelings of the patient, and determine the most suitable power for the patient through try-on.
Multifocal bi-aspheric ablation profile is commonly used to address various ametropia with presbyopia, leading to notable enhancements in UDVA and UNVA in both monocular and binocular eyes postoperatively10,11,12. Luger et al.18 presented one-year postoperative outcomes of bilateral bi-aspheric ablation profile for the correction of myopia or hyperopia with presbyopia, indicating that 70% of patients achieved UDVA ≥ 0.1 logMAR and 84% attained UNVA ≥ 0.1 logRAD. In another study by Luger et al.17, the hybrid mode was utilized to correct refractive errors associated with presbyopia. Both eyes underwent multifocal bi-aspheric treatment to introduce varying depths of focus while preserving different diopters. Following surgery, 90% or more of patients achieved UDVA ≥ 20/20 in both eyes, with 93% of the myopic group and 88% of the hyperopic group achieving UNVA ≥ J2 in both eyes. In contrast to these studies, our present study focused on the monocular mode, where only one eye received multifocal bi-aspheric treatment considering both distance and near vision. Notably, 95% of patients achieved postoperative binocular UDVA of 0 logMAR or better and a binocular UNVA of J1 or better. These visual acuity outcomes were comparable to those reported by Ryu et al.10. The safety profile of the procedure was underscored by the absence of any patient experiencing a loss of two or more lines of corrected distance visual acuity (CDVA) pre- or post-operatively, mirroring the findings of Chan et al.19.
The previous central Presby LASIK surgery made it difficult to achieve the alignment of the line of sight, the central pupil, and the apex of the cornea, and it was prone to vision aberrations after the operation, which affected the visual quality. The multifocal bi-aspheric ablation profile uses bi-aspheric ablation, and the cornea is multifocal after the operation. The negative spherical aberration is introduced without additional aberrations20. Fu et al.12 studied the objective visual quality of patients after monocular surgery and found that SA increased negatively after surgery, vertical and horizontal coma, trefoil aberration had no significant change, and HOA increased positively but the difference was not statistically significant. The subjects selected in this study were mainly myopic patients with presbyopia. Since the dominant eye was completely corrected for distance vision, the positive SA was significantly increased after surgery, while the non-dominant eye was subjected to multifocal bia-spheric ablation, introducing partial negative SA, which offset the positive spherical aberration produced by correcting myopia, resulting in no significant change in non-dominant ocular aberration. The study results were similar to those of Fu et al.12. Fu et al.11 also conducted another study to evaluate the subjective satisfaction of patients after the monocular profile. The study showed that patient satisfaction was 95% at three months after surgery and 100% at one year after surgery. Three months after surgery, the patient reported dry eyes, halo, and decreased night vision, but with time, these symptoms improved, and the patient gradually adapted to this binocular imbalance.
In the monocular mode, SCHWIND Custom Ablation Manager for Amaris software was used for surgical design, AMARIS 1050RS excimer laser was used for ablation of the corneal stroma, and VisuMax femtosecond laser system was used formaking of the corneal flap. Attention should be paid to the evaluation of the amount of negative SA introduced in the surgical design, so as not to affect the patient's postoperative visual quality due to excessive SA. At the same time, it should be noted that there is a reversal mode in the surgical design, and if the postoperative patient is unable to tolerate the corneal multifocal state, the reversal mode can be used to eliminate it. The size of the corneal flap needs to cover the ablation range, the ablation center selects the corneal apex, and the AMARIS 1050RS excimer laser machine is used for surgical ablation, which uses 7-dimensional eye-tracking technology to track the rotational movement of the eyeball, which greatly reduces the generation of articulated HOA.
The Q-value represents the corneal aspheric index, and under normal conditions, the cornea assumes a flat elongated elliptical shape with a central protrusion and a flat periphery, characterized by a mean Q-value of -0.23 ± 0.0821. Notably, the Q-value exhibits a positive correlation with SA when other factors, such as pupil and curvature, remain constant22. Following surgery, the cornea assumes an elevated central and flat peripheral configuration in a prolate form, leading to a concurrent negative increase in both spherical aberration and Q-value. This alteration enhances the depth of focus and effectively improves near vision22. The findings of this study demonstrated a positive increase in the Q-value in both eyes after surgery, attributable to the correction of myopia in both eyes. Specifically, the dominant eye underwent standard myopia correction, while the non-dominant eye was subjected to a double aspheric design, retaining a certain degree of refractive error alongside myopia correction. Consequently, the Q-value of the non-dominant eye was more negative than that of the dominant eye, thereby contributing to the improvement of the patient's near vision.
Although the results of the operation were good, there were still shortcomings in the research, such as the small sample size and the lack of a subjective satisfaction survey of patients. Although the results showed that the patients achieved good postoperative vision, but did not summarize and analyze the symptoms of discomfort that occurred after the operation. It is important to note that only preoperative and postoperative were selected. Based on the results of two time points in the next 6 months, it is impossible to make an accurate judgment on the changes in the patient's vision after the operation.
Monocular bi-aspheric ablation profile has emerged as a primary method for excimer laser correction of presbyopia due to its favorable outcomes in both distance and near vision post-operatively, rapid recovery time, and high patient tolerance. While it does not restore the eye's accommodative ability, it offers sufficient "pseudo-accommodation" to significantly alleviate near-vision difficulties in patients and enhance the quality of life for individuals with presbyopia.
Disclosures
All authors have nothing to disclose.
Acknowledgements
Shandong Medical and Health Science and Technology Development Plan Project (202207020806)
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 0.9% Sodium Chloride Physiological Solution | Shandong Qidu Pharmaceutical Co., Ltd. | H37020764 | |
| AMARIS 1050RS Excimer Laser System | SCHWIND eye-tech-solutions,DE | https://www.eye-tech-solutions.com/amaris1050-excimer-laser | |
| Compound Electrolyte Intraocular Irrigating Solution | Shenyang Xingqi Ophthalmic Co. | http://sinqi.com/html/SYXQ/202006/948671948671019061.html | |
| Dexamethasone Eye Drops | Alcon-Couvreur | H20150119 | |
| Dextran 70 | Chengdu Qingshan Likang Pharmaceutical Co. | 6941684920076 | |
| Glycerol Eye Drops | Chengdu Qingshan Likang Pharmaceutical Co. | 6941684920076 | |
| Hypromellose 2910 | Chengdu Qingshan Likang Pharmaceutical Co. | 6941684920076 | |
| Levofloxacin Hydrochloride Eye Drops | Shandong Bausch & Lomb Freda Pharmaceutical Co., Ltd | 6924090700180 | |
| Proparacaine hydrochloride Eye Drops | Alcon-Couvreur | H20103352 | |
| SCHWIND Cutom Ablation Manager for Amaris | Consorzio Servizi Ortopedici,Turin,IT | N/A | |
| Sirius 3D anterior segment and corneal aberration analyzer | Consorzio Servizi Ortopedici,Turin,IT | YM0020207 | |
| Skin disinfectant | Jinan Xinyongtai Shiye Co., Ltd | http://www.sdxyt.cn/zh/products_detail.asp?id=23 | |
| Sterile Irrigator for Single Use | Shandong Weigao Group Medical Polymer CO.,Ltd | https://weigaogroup.com/photo/show-114.aspx | |
| Sterile medical sponge for Single Use | Beijing Kang'an Kelin Technology Co., Ltd | SS-96A | |
| Tobramycin Eye Drops | Alcon-Couvreur | H20150119 | |
| Transparent Film Dressing Frame Style | Minnesota Mining and Manufacturing | 1624WCN | |
| VisuMax femtosecond laser system | Carl Zeiss Meditec, Inc., Dublin, CA | 20183241728 |
References
- Wolffsohn, J. S., Davies, L. N. Presbyopia: Effectiveness of correction strategies. Prog Retin Eye Res. 68, 124-143 (2019).
- Frick, K. D., Joy, S. M., Wilson, D. A., Naidoo, K. S., Holden, B. A. The global burden of potential productivity loss from uncorrected presbyopia. Ophthalmology. 122 (8), 1706-1710 (2015).
- Nanavaty, M. A., Daya, S. M. Refractive lens exchange versus phakic intraocular lenses. Curr Opin Ophthalmol. 23 (1), 54-61 (2012).
- Soler Tomás, J. R., Fuentes-Páez, G., Burillo, S. Symmetrical versus asymmetrical PresbyLASIK: Results after 18 months and patient satisfaction. Cornea. 34 (6), 651-657 (2015).
- Shetty, R., Brar, S., Sharma, M., Dadachanji, Z., Lalgudi, V. G. PresbyLASIK: A review of PresbyMAX, Supracor, and laser blended vision: Principles, planning, and outcomes. Indian J Ophthalmol. 68 (12), 2723-2731 (2020).
- Pinelli, R., Ortiz, D., Simonetto, A., Bacchi, C., Sala, E., Alió, J. L. Correction of presbyopia in hyperopia with a center-distance, paracentral-near technique using the Technolas 217z platform. J Refract Surg. 24 (5), 494-500 (2008).
- Alió, J. L., Chaubard, J. J., Caliz, A., Sala, E., Patel, S. Correction of presbyopia by technovision central multifocal LASIK (presbyLASIK). J Refract Surg. 22 (5), 453-460 (2006).
- Vargas-Fragoso, V., Alió, J. L. Corneal compensation of presbyopia: PresbyLASIK: An updated review. Eye Vis (Lond). 4, 11(2017).
- Pallikaris, I. G., Panagopoulou, S. I. PresbyLASIK approach for the correction of presbyopia. Curr Opin Ophthalmol. 26 (4), 265-272 (2015).
- Ryu, S., et al. Presbyopia correction using the monocular bi-aspheric ablation profile in myopic eyes. J Cataract Refract Surg. 49 (1), 69-75 (2023).
- Fu, D., Zhao, J., Zeng, L., Zhou, X. One year outcome and satisfaction of presbyopia correction using the PresbyMAX® monocular ablation profile. Front Med (Lausanne). 7, 589275(2020).
- Fu, D., Zhao, J., Zhou, X. T. Objective optical quality and visual outcomes after the PresbyMAX monocular ablation profile. Int J Ophthalmol. 13 (7), 1060-1065 (2020).
- Braun, E. H., Lee, J., Steinert, R. F. Monovision in LASIK. Ophthalmology. 115 (7), 1196-1202 (2008).
- Kohnen, T., Böhm, M., Herzog, M., Hemkeppler, E., Petermann, K., Lwowski, C. Near visual acuity and patient-reported outcomes in presbyopic patients after bilateral multifocal aspheric laser in situ keratomileusis excimer laser surgery. J Cataract Refract Surg. 46 (7), 944-952 (2020).
- Uthoff, D., Pölzl, M., Hepper, D., Holland, D. A new method of cornea modulation with excimer laser for simultaneous correction of presbyopia and ametropia. Graefes Arch Clin Exp Ophthalmol. 250 (11), 1649-1661 (2012).
- Baudu, P., Penin, F., Mosquera Arba, S. Uncorrected binocular performance after biaspheric ablation profile for presbyopic corneal treatment using AMARIS with the PresbyMAX module. Am J Ophthalmol. 155 (4), 636-647 (2013).
- Luger, M. H., McAlinden, C., Buckhurst, P. J., Wolffsohn, J. S., Verma, S., Arba-Mosquera, S. Presbyopic LASIK using hybrid bi-aspheric micro-monovision ablation profile for presbyopic corneal treatments. Am J Ophthalmol. 160 (3), 493-505 (2015).
- Luger, M. H., Ewering, T., Arba-Mosquera, S. One-year experience in presbyopia correction with biaspheric multifocal central presbyopia laser in situ keratomileusis. Cornea. 32 (5), 644-652 (2013).
- Chan, T. C., Kwok, P. S., Jhanji, V., Woo, V. C., Ng, A. L. Presbyopic correction using monocular bi-aspheric ablation profile (PresbyMAX) in hyperopic eyes: 1-year outcomes. J Refract Surg. 33 (1), 37-43 (2017).
- El Danasoury, A. M., Gamaly, T. O., Hantera, M. Multizone LASIK with peripheral near zone for correction of presbyopia in myopic and hyperopic eyes: 1-year results. J Refract Surg. 25 (3), 296-305 (2009).
- Yebra-Pimentel, E., González-Jéijome, J. M., Cerviño, A., Giráldez, M. J., González-Pérez, J., Parafita, M. A. Corneal asphericity in a young adult population. Clinical implications. Arch Soc Esp Oftalmol. 79 (8), 385-392 (2004).
- Calossi, A. Corneal asphericity and spherical aberration. J Refract Surg. 23 (5), 505-514 (2007).
Reprints and Permissions
