Platelet-rich plasma (PRP) is used in the treatment of equine musculoskeletal disorders. Different techniques yield PRP with varying platelet and leukocyte concentrations. This article describes a method for obtaining PRP from horse blood.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Method Article
A Simple Double Centrifugation Tube Method to Obtain Platelet-rich Plasma from Equine Blood
In This Article
Summary
Abstract
Platelet-rich plasma (PRP) is widely utilized as a routine treatment for chronic musculoskeletal conditions in horses, such as osteoarthritis, tendinopathies, and desmopathies. This effectiveness stems from the high concentration of growth factors and anti-inflammatory cytokines that are released upon activation of this orthobiologic agent, whether activated endogenously or exogenously. Despite its growing popularity, there is a notable absence of instructional videos that demonstrate the techniques for obtaining PRP in horses.
This study examines a double centrifugation tube method for obtaining PRP in horses. Whole blood from six horses was collected in sodium citrate tubes and centrifuged twice at 120 × g for 5 min and 240 × g for 5 min. The mean platelet concentration for PRP was 360.95 ± 56.31 platelets (PLT) × 103/µL, while the mean leukocyte concentration was 3.05 ± 1.53 cells × 103/µL. The platelet count in PRP was 2.41x higher than in whole blood, while the leukocyte concentration in PRP was 0.44x lower. The collection efficiency for PLT in PRP was 17%, while the collection efficiency for leukocytes in PRP was 3.1 %. The mean concentrations of transforming growth factor beta 1 and platelet-derived growth factor BB in PRP were 2601.82 (95% confidence interval (CI): 2358.88-2844.76) pg/mL and 1208.05 (95% CI: 1051.09-1365.02) pg/mL, respectively. These results indicate that PRP can be efficiently and reproducibly obtained through a simple, cost-effective method suitable for use by equine practitioners.
Introduction
Platelet-rich plasma (PRP) is an orthobiologic product commonly used to treat chronic equine musculoskeletal conditions such as tendinopathies, desmopathies, osteoarthritis, and laminitis1,2,3. It is also effective in the treatment of limb wounds and ocular surface disease4,5. The rationale for its use is based on the high concentrations of growth factors (GFs) released primarily by platelets6. Leukocytes also contribute by releasing regulatory and anti-inflammatory cytokines7. GFs such as transforming growth factor beta 1 (TGF-β1) and platelet-derived growth factor BB (PDGF-BB) exert potent anabolic, proliferative, angiogenic, and anti-inflammatory effects8. Upon exogenous or endogenous activation, PRP polymerizes into a platelet-rich gel, facilitating cell trafficking, anchoring, and differentiation6,9. In this way, the PRP serves as a complex living scaffold and not just as a container for GFs and cytokines10.
Several systems classify PRP products used in both humans and horses6,11,12. One of the simplest and most common systems categorizes these hemocomponents based on leukocyte concentration11,12. According to this classification, PRP products with low to negligible leukocyte concentrations and low to moderate platelet concentrations -- relative to the levels in the horse's whole blood -- are referred to as pure PRP (P-PRP)6,11,12. In contrast, PRP products with detectable to high leukocyte concentrations and moderate to high platelet concentrations are referred to as leukocyte- and platelet-rich plasma (L-PRP)6,11,12.
P-PRP products are typically obtained by tube-to-tube centrifugation in which whole blood is collected from horses in tubes containing anticoagulants such as sodium citrate and citrate, phosphate, and dextrose13. The blood is centrifuged twice to separate platelets from other components14. In contrast, L-PRP products are primarily prepared using semi-automated kits designed for human blood, some of which have been validated for use in horses6,15. These semi-automated kits generally require specialized centrifuges and come with a higher cost16, as well as potential concerns about aseptic handling, which can complicate their practical use in clinical settings17. Additionally, these kits may result in the undesirable concentration of excessive leukocytes or red blood cells, which could be detrimental in certain clinical situations18. For example, elevated leukocyte counts may provoke excessive inflammation, and an overabundance of red blood cells could interfere with the healing process or lead to complications such as tissue irritation or rejection15; however, a commonly used method for producing equine L-PRP involves a gravitational process that does not require specialized equipment19.
In light of these limitations, simpler and more cost-effective alternatives for PRP preparation are highly desirable. Various in vitro studies, experimental models of musculoskeletal disease, and observations in equines have shown that both P-PRP and L-PRP products have beneficial effects on treated cells and tissues1,2,20. These products promote healing, reduce inflammation, and enhance tissue regeneration6. However, the decision to use P-PRP or L-PRP to treat an equine could be influenced by technical and economic factors.
As per the authors, there are no published studies describing and fully demonstrating a widely validated step-by-step procedure for obtaining a PRP product from equine blood. This article outlines the procedures necessary to safely collect whole blood from horses and produce a PRP product suitable for both experimental and clinical use. It also includes validation of this orthobiologic by quantification of platelets and leukocytes and determination of the concentration of TGF-β1 and PDGF-BB, which are integral to its therapeutic effects. By standardizing the process and demonstrating the product's efficacy, this study seeks to provide a reliable and accessible method for equine practitioners to prepare PRP with confidence and precision.
Although the double centrifugation method for producing equine PRP was first described by Argüelles et al.14 in 2006, this is the first time the protocol has been fully presented in a video. This video is intended to serve as a practical resource for equine practitioners who face technical limitations and budgetary constraints that prevent them from using more sophisticated and expensive PRP kits for horses with musculoskeletal disorders.
Access restricted. Please log in or start a trial to view this content.
Protocol
This study was conducted in accordance with the internal protocols for the preparation and use of PRP in horses at the Veterinary Teaching Hospital of the Universidad de Caldas, Manizales, Colombia. This study did not require Internal Animal Care Committee approval as the data were obtained from lame horses treated clinically at our institution. Data from six Colombian Creole horses, three mares and three geldings, with an average age of 7.4 (± 2.6) years were used to develop this protocol. The owners of the horses were informed of the nature of the study and signed an informed consent form. All horses included in the study were clinically healthy except for the musculoskeletal problem being treated. Only animals with a basal platelet count greater than 100 × 103/mL of whole blood were included. It is important to note that horses with lower platelet concentrations may be considered thrombocytopenic14. In addition, these animals exhibited normal blood counts, liver and kidney clinical biochemistry parameters, and urine analysis values within the normal range for the equine species.
1. Horse restriction and skin disinfection
- For the safety of both the horse and the veterinarian, restrain the horse (Eqqus caballus) securely in a clinical examination chute or with a bridle (Figure 1A), depending on the behavior of the animal. Next, clip a 5 cm x 5 cm area of hair with an electric shaver in the mid-third of one side of the neck, over the jugular vein.
NOTE: Some owners prefer that the horse not be clipped. A study indicates that hair clipping at the venipuncture site is not necessary to prevent bacterial contamination of P-PRP21. Therefore, this procedure is at the discretion of the veterinarian. - Carry out a preliminary non-sterile skin preparation over the clipped area of the jugular vein for at least 10 cm using non-sterile gauze and gloves for approximately 3 min. Apply several pieces of gauze soaked in antiseptic foam in a circular pattern (Figure 1B).
- Prepare the venipuncture site aseptically using both sterile gloves and gauze soaked in disinfectant. Scrub the skin in the neck area in a circular motion for approximately 5 min. Clean the area with sterile gauze soaked in 95% ethyl alcohol.
2. Aseptic blood collection
- Place 16 4.5 mL sodium citrate tubes, previously cleaned with gauze soaked in 95% ethyl alcohol, in a clean plastic rack. Impregnate the rubber caps of the vacuum tubes with 95% ethyl alcohol, especially in the recess for the needle coupling.
NOTE: In general, eight 4.5 mL sodium citrate tubes are required to obtain 2.5 mL of PRP. The number of tubes used in a particular case will depend on the soft tissues or specific joint being treated. - Sterilely insert a butterfly needle into the disinfected jugular site (Figure 2A) and attach 4.5 mL sodium citrate tubes to the holder (Figure 2B). Gently shake the tubes and place them in a plastic rack.
NOTE: A 4.5 mL sodium citrate tube is used for automated hemograms and to prepare plasma after hard spin centrifugation. This plasma is then used as a negative control for growth factor and cytokine enrichment comparisons with PRP.
3. Platelet-rich plasma procurement
- Place the 4.5 mL sodium citrate tubes containing whole blood into a four-place swing-out rotor at an angle of 90° in a bench centrifuge. Centrifuge the tubes at 120 × g for 5 min at room temperature. After centrifugation, position the 4.5 mL tubes containing citrated blood and two additional 10 mL plain tubes in a rack and place the rack on the non-dominant hand side of the operator inside a class II laminar flow hood over a sterile, impervious drape.
NOTE: One study suggests that a Class II laminar flow hood is not essential to prevent bacterial contamination during PRP procurement21. Instead, PRP can be prepared in a clean room free of air currents and dust. In this scenario, the blood tube rack can be placed on a table covered with a sterile, impervious drape. - First centrifugation: Wearing a face mask and sterile gloves, place a 10 mL sterile luer syringe coupled with a sterile needle (21 G 5/8") at the dominant hand side in the inside of the laminar flow hood.
NOTE: From this moment onward, the dominant gloved hand always remains sterile, while the rubber caps of the sodium citrate tubes should be removed using the gloved non-dominant hand. - Insert the sterile needle in each centrifuged citrated blood tube 3 mm over the buffy coat (Figure 3A) and gently aspirate 50% of the plasma fraction, avoiding fluid turbulence and blood aspiration. Once 10 mL of plasma from four 4.5 mL tubes are aspirated, distribute it in 5-10 mL sterile plain tubes (Figure 3B).
NOTE: Remove the rubber caps of these tubes with the non-dominant hand and place them over a sterile site of the drape or hold them to avoid bacterial contamination. - Second centrifugation: close the tubes again with the rubber stoppers and place them in an equilibrated state in a four-place swing-out rotor at an angle of 90° in the bench-top centrifuge and spin these tubes at 240 × g for 5 min at room temperature.
NOTE: The choice of the relative centrifugation force (RCF or g) is based on a seminal study14 that first described this method for obtaining PRP from equine blood. Furthermore, this method has been evaluated for reproducibility by other authors22. - Place the tubes in a rack and position them on the non-dominant side inside the class II laminar flow hood, on top of the previously laid, sterile, impermeable drape.
- Use the non-dominant hand to remove the rubber caps and the sterile dominant hand to slowly aspirate the first 75% of plasma using an 18 G, 90 mm spinal needle attached to a 10 mL sterile luer syringe (Figure 3C). Discard this syringe or reserve it for other experimental or clinical uses as it contains platelet-poor plasma (PPP). Next, attach the previously used sterile spinal needle to a 5 or 10 mL sterile luer syringe to aspirate the remaining plasma (25%) from the 5-10 mL sterile plain tube. This fraction is known as P-PRP (Figure 3D).
NOTE: Under certain clinical and experimental conditions, an aliquot of 0.5-1 mL of PRP is used for automated hemograms followed by growth factor (TGF-β1 and PDGF-BB) analysis by enzyme-linked immunosorbent assay. Measurement of these mediators may be performed 3 h after activation of P-PRP with calcium salts or thrombin23 or after inducing cell damage by temperature change or the addition of nonionic detergents24. - Wrap the sterile luer syringe containing PRP in a small impermeable sterile drape with an attached sterile needle or cap to prevent bacterial contamination of the orthobiologic product (Figure 4A).
NOTE: The anatomical structure of the horse to be treated should be prepared for aseptic injection as described in section 1 of this protocol. The horse should be adequately restrained and sedated to minimize discomfort and ensure the safety of both the horse and the veterinarian. The PRP product should be handled using sterile gloves and needles and may or may not be activated based on the practitioner's preference (Figure 4B).
4. Statistical analysis
- Collect data on platelet and leukocyte counts in whole blood and PRP. Evaluate data for normality using the Kolmogorov-Smirnov test. If the data are normally distributed (P > 0.05), compare and analyze the cell data using the t-test. If platelet and leukocyte concentration data are not normally distributed (P < 0.05), compare and analyze data using a Wilcoxon test.
- Determine the platelet and leukocyte efficiency concentration in P-PRP according to the following formulas25:
Platelet collection efficiency =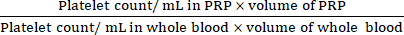 × 100
Leukocyte collection efficiency =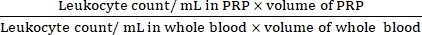 × 100
- Collect data from TGF-β1 and PDGF-BB concentrations in plasma (negative control) PRP supernatants (after 3 h of activation with calcium gluconate), and PRP lysates obtained by the addition of a nonionic detergent solution.
- Use a generalized linear mixed model to compare growth factor concentrations between, plasma, PRP supernatants, and PRP lysate. In case of significant statistical differences, apply a Tukey's post-hoc test.
- Consider p < 0.05 values statistically significant for all the tests.
Access restricted. Please log in or start a trial to view this content.
Results
The mean platelet count (platelets × 103/µL) was significantly higher in PRP than in whole blood (p < 0.001). In contrast, the mean leukocyte concentration (leukocytes × 103/µL) in PRP was significantly lower than that in whole blood (p < 0.001) (Table 1). Specifically, the platelet count in PRP was 2.41x higher than in whole blood, while the leukocyte concentration in PRP was 0.44x lower. The collection efficiency for PLT in PRP was 17%, while leukocyte collection efficiency ...
Access restricted. Please log in or start a trial to view this content.
Discussion
The use of PRP in human and veterinary medicine for the treatment of chronic musculoskeletal disorders is increasing1,8,26,27. However, a major criticism of PRP applications in experimental and clinical settings is the lack of basic data on the techniques and protocols used to prepare these hemocomponents28. In addition, there is insufficient information on the cellular ...
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors have no conflicts of interest to disclose.
Acknowledgements
We thank the Vicerrectoría de Investigaciones y Postgrados of the Universidad de Caldas, Manizales, Colombia for their financial support to publish this article.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 10 mL plain venous blood collection tubes | BD Vacutainer, Franklin Lakes, NJ, USA | Ref 366430 | This is only an example, tubes of other brands can be used. |
| 4.5 mL sodium citrate tubes (105 M/3. 2%) | BD Vacutainer, Franklin Lakes, NJ, USA | 107451 | This is only an example, tubes of other brands can be used. |
| Bench Centrifuge | Rotofix 32A, Hettich GmbH, Tuttlingen, Germany | Other bench centrifuges can be used. | |
| Butterfly needle (21 G × 0.75 in.) with 12 in. tubing and pre-attached holder | Safety-Lok Blood Collection Set, BD Vacutainer, Franklin Lakes, NJ, USA | Ref 367296 | This is only an example, butterfly needles of other brands can be used. |
| Chlorhexidine foam solution at 2.3-4% | The brand or trade names of these products may vary from country to country. | ||
| Class II laminar flow hood | Thermo Fischer Scientific, Waltham, MA, USA | Other class II laminar flow hoods can be used | |
| ELISA reader | Thermo Fischer Scientific, Waltham, MA, USA | ||
| Ethyl alcohol at 95% | The brand or trade names of these products may vary from country to country. | ||
| Human PDGF-BB DuoSet ELISA | R&D Systems, Inc, McKinley Place, MN, USA | DY220 | |
| Human TGF-beta 1 DouSet ELISA | R&D Systems, Inc, McKinley Place, MN, USA | DY240 | |
| Povidone iodine foam solution at 4-10% | The brand or trade names of these products may vary from country to country. | ||
| SPSS 25.0 software | IBM Corp, SPSS, NY, USA | ||
| Sterile luer syringes of various volumes | Discardit Syringe, BD Vacutainer, Franklin Lakes, NJ, USA | This is only an example, syringes of other brands can be used. | |
| Sterile spinal needle (18 G × 90 mm) | BD Quincke Spinel Needle, Franklin Lakes, NJ, USA | This is only an example, spinal needles of other brands can be used. |
References
- Pérez Fraile, A., González-Cubero, E., Martínez-Flórez, S., Olivera, E. R., Villar-Suárez, V. Regenerative medicine applied to musculoskeletal diseases in equines: a systematic review. Vet Sci. 10 (12), 666(2023).
- Boone, L., Peroni, J. Introduction to equine biologic and regenerative therapies. Vet Clin North Am Equine Pract. 39 (3), 419-427 (2023).
- Carmona, J. U., Gómez, W. A., López, C. Could platelet-rich plasma be a clinical treatment for horses with laminitis. J Equine Vet Sci. 61, 46-57 (2018).
- Gilger, B. C. Use of biologics and stem cells in equine ophthalmology. Vet Clin North Am Equine Pract. 39 (3), 541-552 (2023).
- Pereira, R., et al. Evaluation of three methods of platelet-rich plasma for treatment of equine distal limb skin wounds. J Equine Vet Sci. 72, 1-7 (2019).
- Camargo Garbin, L., Lopez, C., Carmona, J. U. A critical overview of the use of platelet-rich plasma in equine medicine over the last decade. Front Vet Sci. 8, 641818(2021).
- Jiménez-Aristizabal, R. F., et al. Long-term cytokine and growth factor release from equine platelet-rich fibrin clots obtained with two different centrifugation protocols. Cytokine. 97, 149-155 (2017).
- McCarrel, T. M. Equine platelet-rich plasma. Vet Clin North Am Equine Pract. 39 (3), 429-442 (2023).
- Garbin, L. C., Olver, C. S. Platelet-rich products and their application to osteoarthritis. J Equine Vet Sci. 86, 102820(2020).
- Anitua, E., et al. Advances in platelet rich plasma-derived extracellular vesicles for regenerative medicine: a systematic-narrative review. Int J Mol Sci. 24 (17), 13043(2023).
- Dohan Ehrenfest, D. M., Rasmusson, L., Albrektsson, T. Classification of platelet concentrates: from pure platelet-rich plasma (P-PRP) to leucocyte- and platelet-rich fibrin (L-PRF). Trends Biotechnol. 27 (3), 158-167 (2009).
- Dohan Ehrenfest, D. M., et al. Classification of platelet concentrates (platelet-rich plasma-PRP, platelet-rich fibrin-PRF) for topical and infiltrative use in orthopedic and sports medicine: current consensus, clinical implications and perspectives. Muscles Ligaments Tendons J. 4 (1), 3-9 (2014).
- Giraldo, C. E., Álvarez, M. E., Carmona, J. U. Effects of sodium citrate and acid citrate dextrose solutions on cell counts and growth factor release from equine pure-platelet rich plasma and pure-platelet rich gel. BMC Vet Res. 11, 60(2015).
- Argüelles, D., et al. Evaluation of single and double centrifugation tube methods for concentrating equine platelets. Res Vet Sci. 81 (2), 237-245 (2006).
- Carmona, J. U., López, C., Sandoval, J. A. Review of the currently available systems to obtain platelet related products to treat equine musculoskeletal injuries. Recent Patents on Regenerative Medicine. 3 (2), 148-159 (2013).
- Jildeh, T. R., Su, C. A., Vopat, M. L., Brown, J. R., Huard, J. A review of commercially available point-of-care devices to concentrate platelet-rich plasma. Cureus. 14 (8), e28498(2022).
- Arita, A., Tobita, M. Adverse events related to platelet-rich plasma therapy and future issues to be resolved. Regen Ther. 26, 496-501 (2024).
- Sutter, W. W., Kaneps, A. J., Bertone, A. L. Comparison of hematologic values and transforming growth factor-beta and insulin-like growth factor concentrations in platelet concentrates obtained by use of buffy coat and apheresis methods from equine blood. Am J Vet Res. 65 (7), 924-930 (2004).
- Mirza, M. H., et al. Gait changes vary among horses with naturally occurring osteoarthritis following intra-articular administration of autologous platelet-rich plasma. Front Vet Sci. 3, 29(2016).
- Peng, C., Yang, L., Labens, R., Gao, Y., Zhu, Y., Li, J. A systematic review and meta-analysis of the efficacy of platelet-rich plasma products for treatment of equine joint disease. Equine Vet J. 56 (5), 858-869 (2024).
- Alvarez, M. E., Giraldo, C. E., Carmona, J. U. Monitoring bacterial contamination in equine platelet concentrates obtained by the tube method in a clean laboratory environment under three different technical conditions. Equine Vet J. 42 (1), 63-67 (2010).
- Pereira, R. C. dF., et al. Avaliação de sete protocolos para obtenção de plasma rico em plaquetas na espécie equina. Ciência Rural. (6), (2013).
- Giraldo, C. E., Álvarez, M. E., Carmona, J. U. Influence of calcium salts and bovine thrombin on growth factor release from equine platelet-rich gel supernatants. Vet Comp Orthop Traumatol. 30 (1), 1-7 (2017).
- Carmona, J. U., López, C., Ceballos-Márquez, A. Temporal release and denature of several mediators in pure platelet-rich plasma and temperature-induced platelet lysates derived from a similar bovine platelet concentrate. Vet Med Int. 2022, 2609508(2022).
- Weibrich, G., Kleis, W. K., Hitzler, W. E., Hafner, G. Comparison of the platelet concentrate collection system with the plasma-rich-in-growth-factors kit to produce platelet-rich plasma: a technical report. Int J Oral Maxillofac Implants. 20 (1), 118-123 (2005).
- Cecerska-Heryć, E., Goszka, M., Serwin, N., et al. Applications of the regenerative capacity of platelets in modern medicine. Cytokine Growth Factor Rev. 64, 84-94 (2022).
- Bahadir, B., Sarikaya, B. Platelet-rich plasma in the management of rotator cuff tendinopathy. Jt Dis Relat Surg. 35 (2), 462-467 (2024).
- Harrison, P., Alsousou, J. Studies on platelet rich plasma - new editorial policy for "platelets". Platelets. 31 (3), 281-282 (2020).
- Chahla, J., et al. A call for standardization in platelet-rich plasma preparation protocols and composition reporting: a systematic review of the clinical orthopaedic literature. J Bone Joint Surg Am. 99 (20), 1769-1779 (2017).
- Ríos, D. L., López, C., Álvarez, M. E., Samudio, I. J., Carmona, J. U. Effects over time of two platelet gel supernatants on growth factor, cytokine and hyaluronan concentrations in normal synovial membrane explants challenged with lipopolysaccharide. BMC Musculoskelet Disord. 16, 153(2015).
- Carmona, J. U., et al. In vitro effects of platelet-rich gel supernatants on histology and chondrocyte apoptosis scores, hyaluronan release and gene expression of equine cartilage explants challenged with lipopolysaccharide. BMC Vet Res. 12 (1), 135(2016).
- Castillo-Franz, C., López, C., Carmona, J. U. Evaluation of the catabolic and anabolic gene expression effects and histology changes induced by platelet-rich gel supernatants in equine suspensory ligament explants challenged with lipopolysaccharide. MLTJ-Muscles Ligaments and Tendons. 11 (1), 1-14 (2021).
- Argüelles, D., Carmona, J. U., Climent, F., Muñoz, E., Prades, M. Autologous platelet concentrates as a treatment for musculoskeletal lesions in five horses. Vet Rec. 162 (7), 208-211 (2008).
- Carmona, J. U., Argüelles, D., Climent, F., Prades, M. Autologous platelet concentrates as a treatment of horses with osteoarthritis: a preliminary pilot clinical study. J Equine Vet Sci. 27 (4), 167-170 (2007).
- Dejnek, M., et al. Content of blood cell components, inflammatory cytokines and growth factors in autologous platelet-rich plasma obtained by various methods. World J Orthop. 13 (6), 587-602 (2022).
- Giraldo, C. E., et al. Effects of the breed, sex and age on cellular content and growth factor release from equine pure-platelet rich plasma and pure-platelet rich gel. BMC Vet Res. 9, 29(2013).
- Zimmermann, R., et al. Sample preparation technique and white cell content influence the detectable levels of growth factors in platelet concentrates. Vox Sang. 85 (4), 283-289 (2003).
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
