This protocol describes a therapeutic approach using electroacupuncture to relieve dyspnea in patients with pulmonary hypertension with chronic obstructive pulmonary disease.
Method Article
Electroacupuncture as an Adjuvant Therapy for Dyspnea in Patients with Pulmonary Hypertension Associated with Chronic Obstructive Pulmonary Disease
* These authors contributed equally
In This Article
Summary
Abstract
Pulmonary hypertension (PH) is the most prevalent cardiovascular complication of chronic obstructive pulmonary disease (COPD). Dyspnea is the most prevalent and distressing symptom in Pulmonary Hypertension Associated with COPD (PH-COPD) patients. This study elucidates the operational details of electroacupuncture therapy, encompassing instrument preparation, acupuncture point selection, procedure, precautions, and emergency handling. By assessing with the Modified Medical Research Council Dyspnea Scale (mMRC), the 6-Minute Walk Test (6MWT), the Modified Borg Scale, the UCSD Shortness of Breath Questionnaire (UCSD-SOBQ), and the oxygen partial pressure in arterial blood (PaO2), the efficacy and safety of electroacupuncture as a supplementary intervention for dyspnea in patient with PH-COPD were explored.
An exploratory randomized controlled study was conducted on 14 patients, with the electroacupuncture group receiving both conventional therapy and electroacupuncture treatment, and the control group receiving only conventional therapy. After 2 weeks, dyspnea improved in both groups, with the electroacupuncture group showing superior results. No serious adverse reactions occurred in either group. The study indicates that electroacupuncture can effectively alleviate dyspnea in PH-COPD patients, enhance their quality of life, and is simple, safe to operate, and worthy of further investigation and promotion, offering an effective adjunct therapy for PH-COPD.
Introduction
Chronic Obstructive Pulmonary Disease (COPD) is defined by persistent respiratory symptoms and airflow limitation. Due to abnormalities in the airways and/or alveoli, patients usually experience symptoms such as dyspnea, excessive sputum, and chronic cough1. As the disease progresses, pulmonary hypertension (PH) is the most prevalent cardiovascular consequence in patients with COPD2. PH arises from pulmonary vascular remodeling triggered by long-term airway inflammation and hypoxia. It will further exacerbate patients' dyspnea and lead to an increase in the load on the right ventricle, which may eventually result in right heart failure3. This greatly affects the prognosis and life quality of patients and is a major factor contributing to the reduced survival rate of patients with COPD4,5,6.
Dyspnea, as a highly prevalent and distressing symptoms for patients, not only hinders their ability to participate in daily activities but also has a profound impact on their mental health and social participation, thus increasing the socioeconomic burden6,7. Thus, investigating effective therapeutic approaches to relieve dyspnea in patients with pulmonary hypertension associated with COPD (PH-COPD) is essential for enhancing patient quality of life and reducing socioeconomic pressure.
Currently, the therapeutic approaches for PH-COPD predominantly center around the management of the primary disorder, long-term domiciliary oxygen therapy, and pulmonary rehabilitation training1. Nevertheless, these interventions frequently prove inadequate in fully alleviating symptoms or effectively curbing disease progression. They may also give rise to a multitude of adverse reactions and entail substantial treatment expenses8,9. Thus, identifying other safe and effective interventions to relieve dyspnea symptoms and enhance quality of life for PH-COPD patients is clinically imperative.
Traditional Chinese medicine (TCM) treatment is gradually gaining attention as a complementary and alternative therapy. As a traditional medical system, TCM has accumulated a wealth of experience in the treatment of chronic diseases10. Electroacupuncture is a modern modified adaptation of TCM acupuncture therapy, applying weak electrotherapeutic impulses to acupuncture needles to enhance the stimulating effect and efficacy of acupuncture. It has been widely used in pain management and neurological disorders11,12.
Studies have shown that electroacupuncture can exert its therapeutic effects through a variety of mechanisms, such as regulating the neuroendocrine system, improving microcirculation, and reducing inflammatory responses11,13,14. Especially in respiratory diseases, electroacupuncture has been used to assist in the treatment of COPD and asthma, which can improve lung function, reduce inflammatory response, and regulate immune function15,16,17,18. Despite the progress of electroacupuncture in related diseases, there is still a relative lack of research on electroacupuncture therapy for dyspnea in patients with PH-COPD, and a safe and effective standard protocol is lacking.
This study intends to evaluate the safety and efficacy of electroacupuncture integrated with conventional treatment on dyspnea associated with PH-COPD. Efficacy and safety will be evaluated by comparing the improvement of dyspnea symptoms and the changes in cardiopulmonary function index in two groups of patients. This study is expected to provide an innovative treatment modality and standardized protocol for PH-COPD patients and enrich the application of TCM acupuncture therapy in cardiopulmonary diseases.
Protocol
The clinical study protocol underwent review and approval by the Clinical Research Approval Committee of Chengdu Xinjin District Hospital of Traditional Chinese Medicine (NO. 202411). All participants were informed of the objectives and procedures of this research and consented to photographic and video recording.
1. Clinical information
- Source of cases
- Identify observed cases as hospitalized patients in the respiratory and cardiovascular departments of Chengdu Xinjin District Hospital of Traditional Chinese Medicine and the Hospital of Chengdu University of Traditional Chinese Medicine.
- Inclusion criteria
- Refer to the 2025 reported and 2022 ESC/ERS Guidelines to identify patients with a previous clinical diagnosis of PH-COPD1,3.
- Use the modified Medical Research Council (mMRC) scale to assess dyspnea symptoms, and diagnose dyspnea when the mMRC is grade 2 or above.
- Enroll participants who voluntarily join the study and obtain their written informed consent.
- Select participants aged 18-85 years old, without gender limitation.
- Exclusion criteria
- Exclude participants- with other serious heart or lung diseases.
- Rule out participants with bleeding tendency or coagulation disorders.
- Exclude participants with mental illnesses or inability to cooperate with treatment.
- Exclude pregnant or nursing women.
- Reject those with allergic reactions or fear of acupuncture/electroacupuncture treatment.
- Abscission criteria
- Withdraw participants who voluntarily exit the study for any reason.
- Remove participants experiencing adverse reactions/complications or showing deteriorating conditions during the study.
- Discontinue participants with poor compliance (failure to follow the treatment protocol) or incomplete evaluation results.
- Exclusion criteria
- Exclude participants violating inclusion criteria.
- Remove those unilaterally altering the treatment protocol during the study.
- Terminate patients who withdraw from the study for various reasons, miss visits, take prohibited drugs privately or use other treatments prohibited by the study, or do not co-operate for complete data collection.
2. Research methodology
- Study type
- Conduct a prospective, exploratory, small-sample randomized controlled study.
- Enroll patients and randomly assign them to the experimental or control group.
NOTE: In this protocol, we enrolled 14 patients, seven each in the experimental and control groups.
- Randomization method
- Use statistical software to generate random numbers.
- Fill the randomly generated numbers and group assignments into allocation cards.
- Distribute the cards to participants in the order of their clinic visits, assigning them to the experimental group or control group accordingly.
- Intervention methods
- Control group: Administer conventional medical treatment following -the 2025 reported and 2022 ESC/ERS Guidelines (Supplemental Table S1)1,3. Complete one treatment course over 2 weeks.
- Experimental group: Administer electroacupuncture in addition to conventional medical treatment. Conduct 1 treatment course over 2 weeks, with each session lasting 30 minutes and administered once daily (total of 14 sessions over 14 consecutive days).
NOTE: All practitioners must be certified as acupuncturists and have conducted clinical treatment independently for over one year. The treatment is performed according to the National Standard19,20. Acupuncturists will not be changed during the study unless necessary.
- Equipment preparation
- Make sure that the following materials are within the expiration date: sterile cotton swabs, 75% alcohol, disposable sterile acupuncture needles (size 0.25 mm x 25 mm), pulsed acupuncture therapeutic device, lead wires, and alligator clips (Figure 1).
- Doctor preparation
- Check the power switch, keep batteries on hand for the main unit that uses dry batteries, and make sure the power is sufficient.
- Check the output electrode wires and ensure that the conductivity is good, should ensure that the pulse acupuncture therapy instrument works properly.
- Wear medical masks and hats.
- Before operating with needles, wash hands with soap and water, maintain dryness, and use alcohol hand sanitizer.
- Patient preparation
- Have the patient empty their bladder.
- Assess the patient's blood pressure, heart rate, respiratory rate, and oxygen saturation.
- Ensure that the skin is not damaged or ulcerated.
- Direct the patient to adopt a supine or prone position for acupoint exposure.
- Instruct the patient to inform the practitioner immediately if discomfort arises during treatment.
- Acupuncture point selection
- Cleanse the acupuncture site with a 75% alcohol swab.
- According to the standardized acupoints in Therapeutics of Acupuncture and Moxibustion21, select Fei Shu (BL13), Zhong Fu (LU1), Tai Yuan (LU9), Ding Chuan (EX-B1), Dan Zhong (CV17), Gao Huang (BL43), and Shen Shu (BL23) (Figure 2 and Table 1).
- Acupuncture and needling techniques
- Separate the index and middle fingers of the left hand at the point of puncture.
- Hold the needle handle with the right thumb and index finger, brace the middle finger's pad against the needle body, slightly flex the middle finger to create lever support, then press vertically to insert the needle to the standard depth.
- Perform lifting-thrusting motions (3 mm depth, 60 cycles/min) combined with bidirectional rotation (≤180° angle) until achieving de qi (soreness, numbness, distension, or heaviness).
- Electroacupuncture connection and stimulation
NOTE: Based on the requirement of the current circuit, acupoint selection should be in pairs. When choosing a single acupuncture point for treatment, an indifferent electrode should be used.- Check the output knobs or buttons of the electroacupuncture instrument and adjust them to the "zero" position.
- Insert the plug end of the electrode cable into the corresponding output jack of the host, and use the crocodile clip to connect the two output terminals of the electrode cable to the handle or body of the needle, respectively. Make sure the connection is secure and conductive.
- Patients receive treatment in both supine and prone positions sequentially. Position patients in the supine position, connect bilateral LU1 and EX-LU9 and bilateral CV17. Switch to the prone position, connect bilateral BL13, EX-B1, BL43, and BL23 (Figure 3).
- Turn on the Electroacupuncture Meter power switch after securing power. Adjust the waveform and frequency knobs or buttons to select the waveform and frequency required for treatment.
- Set the parameters of the electroacupuncture device: expanding waveform at 2/100 Hz, current amplitude from 0.1 to 5 mA according to participant tolerance.
NOTE: Incrementally adjust the corresponding output controls to raise the output amplitude in gradual increments, slowly, to the extent that it is tolerated by the patient. It is preferable that the skin around the acupuncture point trembles slightly without pain. In order to prevent the patient from feeling electric shock when adjusting, the amplitude of adjustment should be small. - Start electroacupuncture stimulation for 30 minutes per session.
- Post treatment management
- After the completion of electroacupuncture treatment, first slowly adjust the intensity knob or button so that the output intensity is at the zero position.
- Turn off the power switch of the electroacupuncture instrument, and then remove the crocodile clips and electrode wires from the needle handle (needle body).
- Remove the needle when the sensation under the needle is light and smooth. If the needle sinks, then slightly push upward to lift the needle.
- Use one hand to hold a sterile dry cotton ball and lightly press the puncture site, while using the other hand to pinch the needle handle with the thumb and index finger and pull out the needle. Immediately press the needle entry point with the cotton ball after removing the needle to prevent bleeding.
- After removing the needle, closely examine the needle insertion sites for bleeding, inquire about any discomfort, and verify needle count. Advise the patient to rest in bed and avoid strenuous exercise.
- Precautions
- Before performing acupuncture, assess the patient's physical condition to prevent adverse events like needle fainting.
- Strictly implement sterilization protocols during acupuncture and instruct patients to keep the insertion site dry for 2 h to prevent infection.
- Closely observe the patient's reactions throughout the process to ensure safety.
- After the treatment, record the patient's feedback and any adverse reactions.
- Before and after each treatment, record the patient's sign changes and treatment parameters in detail.
- Treatment of abnormalities and adverse reactions
- Subcutaneous hematoma: Small ones may need no treatment. For large ones, advise cold then hot compresses until it fades.
- Fainting from needles: Turn off electroacupuncture, stop needling, remove all needles, let the patient lie down, and offer warm or sugar water if needed.
- Stagnant needles: Gently press the area or shake the needle handle in reverse. Remove the needle when the muscles relax.
- Bending needle: For slight bends, remove the needle slowly. For severe bends, adjust the angle and remove along the bent direction. If the patient changed their position, instruct them to return to the original position and relax their muscles before removing the needle.
- Fractured needle: Should a needle break with some part remaining in the body, calm the patient and prevent position changes. If the stump is exposed, remove it by hand or forceps. Should the stump be flush with the skin, squeeze the needle hole to expose and extract with forceps. For needles embedded in the body, perform surgical removal with X-ray localization.
3. Observation Indicators
- Safety indicators: Observe the occurrence of adverse reactions during the test, and record the triggers, duration, clinical manifestations, and whether there is any relief.
- Demographics and clinical characteristics: Record sex, age, height, weight, tricuspid regurgitation velocity, pulmonary artery systolic pressure, FEV1/FVC.
- Efficacy indicators: Assess mMRC, and the 6-Minute Walk Test (6MWT), the UCSD Shortness of Breath Questionnaire (UCSD-SOBQ), the Modified Borg Scale, oxygen partial pressure in arterial blood (PaO2)22,23,24.
- Safety evaluation
- Record and describe adverse reactions occurring during the study, including clinical manifestations, onset time, frequency, severity, relationship to the treatment regimen, and treatment measures.
NOTE: Mild adverse reactions should be treated symptomatically. Moderate adverse reactions should be terminated and treated. Serious adverse reactions should be immediately withdrawn from the study and given emergency treatment.
- Record and describe adverse reactions occurring during the study, including clinical manifestations, onset time, frequency, severity, relationship to the treatment regimen, and treatment measures.
4. Data analysis
- Describe continuous data by mean (standard deviation) or median (quartile), describe categorical data by frequency (percentage).
- Use paired t-tests or Wilcoxon signed-rank tests for within-group pre-post changes. Employ independent sample t-tests or Mann-Whitney U tests for between-group treatment effect comparisons.
- Consider P < 0.05 to be statistically significant.
Results
Fourteen patients were included in this research, with seven assigned to the experimental group and seven to the control group. No participants withdrew during the study, and all 14 completed the protocol. Two males and five females were enrolled in the experimental group. In the control group, there were three males and four females. Table 2 shows the results of the comparison between the control and the experimental groups for variables, including age, sex, body mass index, tricuspid regurgitation velocity, pulmonary artery systolic pressure, FEV1/FVC, and a number of pretreatment assessments (including mMRC, 6MWT, UCSD-SOBQ, the Modified Borg Scale and PaO2), all of which showed no significant intergroup differences.
Table 3 and Table 4 present pre and post treatment changes in the five assessment indicators between the two groups. The results indicated that both groups improved in 6MWT distance, UCSD-SOBQ score, mMRC score, the Modified Borg Scale score, and PaO2 after treatment, but the experimental group improved more and reached statistically significant differences compared to the control group in 6MWT, UCSD-SOBQ, the Modified Borg Scale scores, and PaO2. With respect to mMRC scores, intergroup differences were not statistically significant, although the trend of improvement was more pronounced in the experimental group. During the course of treatment, no adverse events occurred in both groups, and the patients were in good general condition without any special conditions such as needle-sickness or infection.

Figure 1: Required materials. Sterile cotton swabs, 75% alcohol, disposable sterile acupuncture needles (size 0.25 mm x 25 mm), pulsed acupuncture therapeutic device, lead wires, and alligator clips. Please click here to view a larger version of this figure.
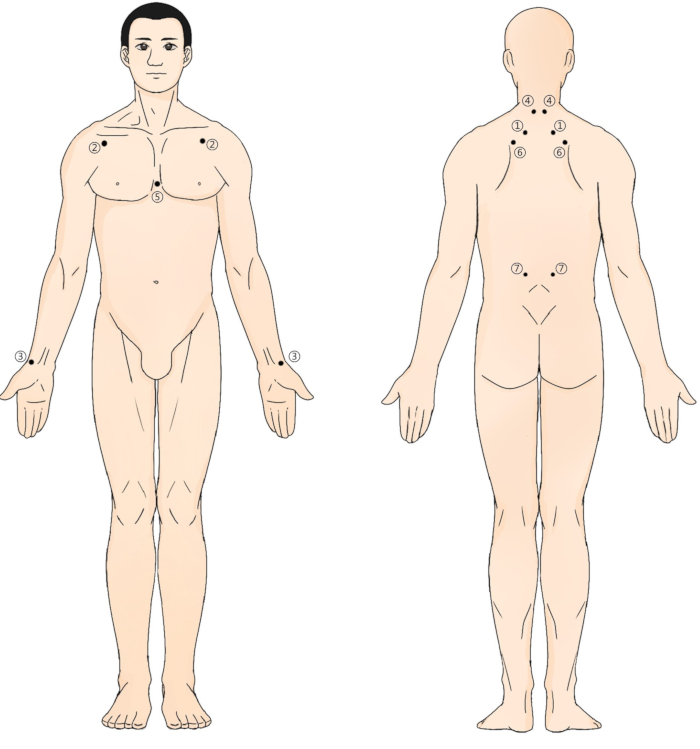
Figure 2: Acupoint selection. According to the standardized acupoints, select: (1)Fei Shu (BL13); (2)Zhong Fu (LU1); (3)Tai Yuan (LU9); (4)Ding Chuan (EX-B1); (5)Dan Zhong (CV17); (6)Gao Huang (BL43); (7)Shen Shu (BL23). Please click here to view a larger version of this figure.
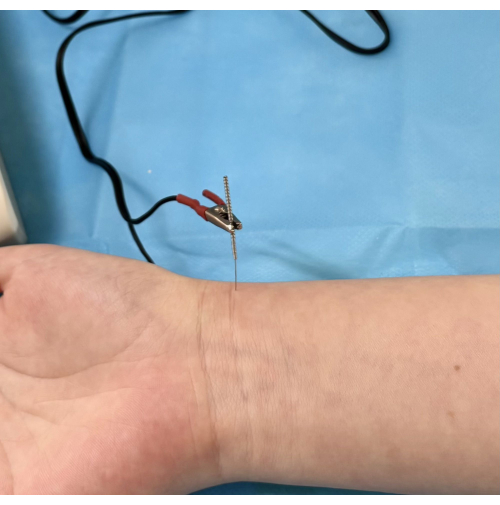
Figure 3: Electroacupuncture treatment. Please click here to view a larger version of this figure.
| Name | Number | Location | operation | remark |
| Fei shu | BL13 | below the spinous process of the 3rd thoracic vertebra, 1.5 cun lateral to it. | The general needling angle is oblique insertion at 45° towards the spine, with an insertion depth of about 0.5 - 0.8 cun (15 - 24 mm). | Vertical needle insertion may damage lung tissue, so mind the needling direction and depth. |
| Zhong fu | LU1 | upper outer part of the anterior chest wall, 1 cun below Yun men, at the level of the 1st intercostal space, and 6 cun away from the anterior midline. | Needling angles are oblique outward insertion (about 45°) or flat insertion (15°). Insertion depth is 0.5 - 0.8 cun (around 15 - 24 mm). | Vertical needle insertion may damage lung tissue, so mind the needling direction and depth. |
| Tai yuan | LU9 | radial side of the transverse crease of the palmar aspect of the wrist, at the location of the radial artery pulsation. | Vertical insertion. The needling angle is 90°, and the depth of insertion is 0.3 - 0.5 cun (about 9 - 15 mm). | As there is a radial artery here, avoid it and insert the needle slowly when needling. |
| Ding chuan | EX-B1 | on the back, below the spinous process of the 7th cervical vertebra, 0.5 cun lateral to it. | vertical insertion. The needling angle is 90°, and the depth of insertion is 0.5 - 1 cun (about 15 - 30 mm). | This acupoint mainly treats diseases like dyspnea.Vertical insertion can better exert its therapeutic effect. |
| Dan zhong | CV17 | anterior midline, at the level of the 4th intercostal space. | The needling method is mostly flat insertion at about 15°, inserting along the skin, with an insertion depth of 0.3 - 0.5 cun (9 - 15 mm). | Flat insertion can avoid damaging the tissues inside the thoracic cavity. |
| Gao huang | BL43 | on the back, below the spinous process of the 4th thoracic vertebra, 3 cun lateral to it. | The general needling angle is oblique insertion at 45° towards the spine, with an insertion depth of 0.5 - 0.8 cun (about 15 - 24 mm). 15 - 24 mm). | Despite relatively thick muscles here, mind the needling angle to avoid stabbing internal organs. |
| Shen shu | BL23 | on the waist, below the spinous process of the 2nd lumbar vertebra, 1.5 cun lateral to it. | When inserting the needle vertically, the needling angle is 90°, and the depth of insertion is 0.5 - 1 cun (about 15 - 30 mm). | Vertical insertion can stimulate relevant nerves and muscle tissues, but control the depth to prevent kidney damage. |
Table 1: Detailed information on acupoints in this study.
| Total (n=14) | Control group (n=7) | Experimental group (n=7) | Statistic | P-value | |
| Age, Mean ± SD | 74.43 ± 11.09 | 75.00 ± 10.20 | 73.86 ± 12.71 | t=0.19 | 0.856 |
| Gender, n (%) | 1 | ||||
| Male | 5 (35.71) | 3 (42.86) | 2 (28.57) | ||
| Female | 9 (64.29) | 4 (57.14) | 5 (71.43) | ||
| BMI, M (Q1, Q3) | 20.64 (19.44, 23.29) | 21.26 (19.81, 23.13) | 20.40 (18.59, 22.57) | Z=-0.50 | 0.62 |
| Tricuspid regurgitation velocity (m/s), Mean ± SD | 3.25 ± 0.15 | 3.19 ± 0.09 | 3.30 ± 0.18 | t=-1.41 | 0.184 |
| Pulmonary artery systolic pressure (mmHg), Mean ± SD | 49.71 ± 5.73 | 48.00 ± 4.90 | 51.43 ± 6.35 | t=-1.13 | 0.28 |
| FEV1/FVC (%), Mean ± SD | 52.91 ± 5.08 | 53.60 ± 5.85 | 52.21 ± 4.53 | T=0.50 | 0.629 |
| Pre-treatment 6MWT (m), Mean ± SD | 361.50 ± 15.47 | 360.00 ± 13.56 | 363.00 ± 18.14 | t=-0.35 | 0.732 |
| Pre-treatment UCSD-SOBQ, Mean ± SD | 88.50 ± 9.14 | 88.14 ± 8.53 | 88.86 ± 10.38 | t=-0.14 | 0.891 |
| Pre-treatment mMRC, M (Q1, Q3) | 3.00 (2.00, 3.00) | 3.00 (2.50, 3.00) | 3.00 (2.00, 3.00) | Z=-0.46 | 0.645 |
| Pre-treatment the Modified Borg Scale, Mean ± SD | 7.50 (7.00, 8.00) | 8.00 (7.00, 8.00) | 7.00 (7.00, 8.00) | Z=-0.35 | 0.726 |
| Pre-treatment PaO2 (mmHg), Mean ± SD | 62.07 ± 5.89 | 62.14 ± 5.52 | 62.00 ± 6.68 | t=0.04 | 0.996 |
Table 2: Baseline characteristics of patients. Abbreviations: SD = standard deviation; M = Median; Q1 = 1st Quartile; Q3 = 3rd Quartile; 6MWT = the 6-Minute Walk Test; UCSD-SOBQ = the UCSD Shortness of Breath Questionnaire; mMRC = the Modified Medical Research Council Dyspnea Scale; PaO2 = oxygen partial pressure in arterial blood.
| Group | Pre-treatment | Post-treatment | effect sizes | 95% CI | P |
| Control group | 362.00 (350.00, 371.00) | 375.00 (362.00, 384.50) | 13.00 | (11.00, 13.50) | 0.020 |
| Experimental group | 363.00 ± 18.14 | 391.00 ± 16.08 | 28.00 | (25.67, 30.33) | <0.001 |
| Control group | 88.14 ± 8.53 | 75.57 ± 9.41 | -12.57 | (-15.59, -9.56) | <0.001 |
| Experimental group | 88.86 ± 10.38 | 61.71 ± 10.59 | -27.14 | (-29.03, -25.26) | <0.001 |
| Control group | 3.00 (2.50, 3.00) | 2.00 (2.00, 2.00) | / | / | 0.072 |
| Experimental group | 3.00 (2.00, 3.00) | 2.00 (1.00, 2.00) | / | / | 0.011 |
| Control group | 8.00 (7.00, 8.00) | 5.00 (4.00, 6.00) | -2.50 | (-2.50, -2.00) | 0.019 |
| Experimental group | 7.29 ± 0.76 | 3.43 ± 0.53 | -3.86 | (-4.50, -3.22) | <0.001 |
| Control group | 62.14 ± 5.52 | 84.43 ± 2.88 | 22.29 | (19.01, 25.57) | <0.001 |
| Experimental group | 62.00 ± 6.68 | 88.71 ± 3.95 | 26.71 | (23.44, 29.99) | <0.001 |
Table 3: Comparison of efficacy indicators before and after treatment between the control group and the experimental group. Abbreviations: 6MWT: the 6-Minute Walk Test; UCSD-SOBQ = the UCSD Shortness of Breath Questionnaire; mMRC = the Modified Medical Research Council Dyspnea Scale; PaO2 = oxygen partial pressure in arterial blood.
| Control group | Experimental group | effect sizes | 95% CI | P | |
| 6MWT (m) | 372.57 ± 14.47 | 391.00 ± 16.08 | -1.21 | (-2.47, 0.06) | 0.044 |
| UCSD-SOBQ | 75.57 ± 9.41 | 61.71 ± 10.59 | 1.38 | (0.09, 2.68) | 0.024 |
| mMRC | 2.00 (2.00, 2.00) | 2.00 (1.00, 2.00) | 1.00 | (0.00, 1.00) | 0.053 |
| the Modified Borg Scale | 5.00 (4.00, 6.00) | 3.00 (3.00, 4.00) | 2.00 | (1.00, 3.00) | 0.008 |
| PaO2 (mmHg) | 84.43 ± 2.88 | 88.71 ± 3.95 | -1.24 | (-2.51, 0.03) | 0.041 |
Table 4: Comparison of efficacy indicators (post treatment) between control group and experimental group. Abbreviations: 6MWT: the 6-Minute Walk Test; UCSD-SOBQ = the UCSD Shortness of Breath Questionnaire; mMRC = the Modified Medical Research Council Dyspnea Scale; PaO2 = oxygen partial pressure in arterial blood.
Supplemental Table S1: Conventional medical treatment. Two weeks were taken as a course of treatment, and a total of 1 course of treatment was given1,3. Please click here to download this table.
Discussion
This study found that electroacupuncture therapy significantly alleviated dyspnea and improved life quality in PH-COPD patients. Results revealed that the- experimental group exhibited significantly greater improvement than the control group in 6MWT, UCSD-SOBQ, Modified Borg Scale scores, and PaO2 following intervention. This suggests that the treatment regimen received by the experimental group had a positive effect on improving the patient's ability to walk, reducing symptoms of shortness of breath, and relieving fatigue. These positive results are consistent with observations made in previous studies, suggesting that electroacupuncture may be an effective adjunctive treatment25.
Electroacupuncture may work through a variety of mechanisms, including modulating the balance of the autonomic nervous system to improve the hemodynamic status of the heart and lungs. Electroacupuncture may play a protective role in cardiovascular disease by promoting autophagy, modulating Ca2+ overload, and promoting vascular regeneration via anti-Inflammatory response, anti-oxidative stress, and anti-apoptosis26. In addition, electroacupuncture promotes local blood circulation, thereby improving tissue oxygen supply. It also reduces the production of inflammatory mediators, improves the pulmonary microenvironment, and reduces pulmonary vascular resistance, thereby reducing the symptoms of pulmonary hypertension25,27.
In this study, we used strict safety monitoring measures to ensure the safety of the electroacupuncture treatment process. Preliminary results showed that electroacupuncture therapy did not cause serious adverse events, suggesting that it has a high degree of safety as an adjunctive therapy. However, for patients with pacemakers or other implanted electronic devices, electroacupuncture needs to be used with caution as the current may interfere with the normal operation of the device. Pregnant women, patients with unstable epilepsy, and those with bleeding tendencies are also not suitable for electroacupuncture treatment28. Before administering the treatment, the doctor should take a detailed medical history and conduct a thorough evaluation to ensure that each patient can receive the treatment safely. Notably, although no severe adverse events weredocumented, some patients exhibited mild local skin redness at the acupuncture points during the initial phase of treatment. However, this condition typically resolved spontaneously within a short period without the need for specific interventions, and did not affect patients' willingness to continue the therapy.
Furthermore, all subjects demonstrated good tolerance, with no reported interruptions due to treatment discomfort. In terms of compliance, all patients adhered to the prescribed treatment regimen, indicating a high level of acceptability of this therapy among patients with PH-COPD. In addition, the specific parameters of electroacupuncture therapy (e.g., frequency, intensity, duration, etc.) need to be further optimized to ensure the best therapeutic effect and minimal side effects. Subsequent studies should further investigate the impacts of different electroacupuncture parameters on PH-COPD patients to develop a more personalized and effective treatment plan.Meanwhile, the incidence of mild side effects and their impact on patients' quality of life should be further observed in studies with a larger sample size, thereby providing more comprehensive safety data support for clinical applications.
Electroacupuncture has unique advantages over traditional drug therapy. Although drug therapy plays an irreplaceable role in controlling the pathophysiologic process of pulmonary hypertension, electroacupuncture, as an adjunctive treatment, can effectively alleviate the problem of declining quality of life caused by the disease. Electroacupuncture demonstrates superiority in rapidly relieving dyspnea through precise electrical stimulation. This distinguishes it from moxibustion, which focuses on regulating chronic fatigue with slower onset29; acupoint application, which provides delayed symptomatic relief30; and ear acupuncture, which has limited efficacy in severe cases31. As such, electroacupuncture is ideally positioned as a premier adjunct therapy for acute symptom management in PH-COPD. From a cost-effectiveness point of view, electroacupuncture therapy is less expensive and suitable for resource-limited areas. In long-term management, electroacupuncture can reduce the financial burden caused by frequent hospitalization. However, electroacupuncture is not a complete replacement for existing standard treatment protocols but rather serves as an adjunct in combination with medication, lifestyle modification, and other measures. Future studies could further explore the use of electroacupuncture in combination with medication in an integrated treatment program with a view to achieving optimal therapeutic outcomes.
This study has several limitations. First, the sample size was limited, and blinding was not implemented. Hence, a larger multicenter randomized controlled double-blind trial is needed to validate the findings of this study to further improve the scientific validity and credibility of the study. Second, in terms of mMRC scores, intergroup differences were not statistically significant, though the experimental group exhibited a more evident improvement trend. This may be related to the coarser and less sensitive grading of the mMRC scale. Therefore, in future studies, the use of a more refined and sensitive assessment tool to evaluate the treatment effect could be considered. Finally, as electroacupuncture involves complex manipulation techniques, variations between operators may also affect the treatment effect. Future studies need to focus on long-term follow-up data, validate the findings of this study on a larger scale, and incorporate more objective evaluation indicators to assess the long-lasting effects of electroacupuncture therapy and potential adverse effects. Electroacupuncture therapy, as a safe and effective adjunct, has shown good potential in improving dyspnea symptoms in patients with PH-COPD. Further scientific research should validate its long-term efficacy and safety and explore the best treatment options.
Disclosures
The authors have no conflicts of interest to disclose.
Acknowledgements
This research was supported by the Sichuan Science and Technology Program (2023ZYD0050, 2024NSFJQ0059), Special subject of scientific research of Sichuan Administration of Traditional Chinese Medicine (2023MS608, 2024zd005), 2022 "Tianfu Qingcheng Plan" Tianfu Science and Technology Leading Talents Project (Chuan Qingcheng No. 1090).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 75% alcohol | Shenzhen Baoke Medical Devices Co., Ltd. | 20182140792 | |
| alligator clips | Bozhou Rongjian Medical Supplies Co., Ltd. | 2300442G5 | |
| disposable sterile acupuncture needles | Suzhou Medical Supplies Factory Co., Ltd. | 100014261834 | |
| IBM SPSS Statistics 25.0 | IBM Corp. | / | |
| lead wires | Bozhou Rongjian Medical Supplies Co., Ltd. | 2300442G5 | |
| pulsed acupuncture therapeutic device | Bozhou Rongjian Medical Supplies Co., Ltd. | 2300442G5 | |
| Sterile cotton swabs | Chengdu Zhongxin Hygiene Materials Co., Ltd. | 20240420 | |
| The R Programming Language 4.3.2 | The R Foundation. | / |
References
- Global strategy for prevention, diagnosis and management of COPD: 2025 report. , Global Initiative for Chronic Obstructive Lung Disease (GOLD). https://goldcopd.org/2025-gold-report/ (2025).
- Morrell, N. W., et al. Pilot study of losartan for pulmonary hypertension in chronic obstructive pulmonary disease. Respir Res. 6 (1), 88(2005).
- Humbert, M., et al. ESC/ERS guidelines for the diagnosis and treatment of pulmonary hypertension. Eur Heart J. 43 (38), 3618-3731 (2022).
- Nathan, S. D., et al. Inhaled treprostinil in pulmonary hypertension associated with COPD: PERFECT study results. Eur Respir J. 63 (6), 2400172(2024).
- Andersen, K. H., et al. Prevalence, predictors, and survival in pulmonary hypertension related to end-stage chronic obstructive pulmonary disease. J Heart Lung Transplant. 31 (4), 373-380 (2012).
- Liu, K., et al. Globalm, regional, and national burden of pulmonary arterial hypertension and related heart failure from 1990 to 2021, with predictions to 2050: insights from the Global Burden of Disease Study 2021. Eur Heart J Qual Care Clin Outcomes. , (2025).
- Delcroix, M., Howard, L. Pulmonary arterial hypertension: the burden of disease and impact on quality of life. Eur Respir Rev. 24 (138), 621-629 (2015).
- Heresi, G. A., et al. Healthcare burden of pulmonary hypertension owing to lung disease and/or hypoxia. BMC Pulm Med. 17 (1), 58(2017).
- Xiong, W., Zhao, Y., Gong, S., Zhao, Q., Liu, J. Prophylactic function of excellent compliance with LTOT in the development of pulmonary hypertension due to COPD with hypoxemia. Pulm Circ. 8 (2), 2045894018765835(2018).
- Jiang, M., Zhang, C., Cao, H. X., Chan, K., Lu, A. P. The role of Chinese medicine in the treatment of chronic diseases in China. Planta Med. 77 (9), 873-881 (2011).
- Ulett, G. A., Han, S., Han, J. S. Electroacupuncture: mechanisms and clinical application. Biol Psychiatry. 44 (2), 129-138 (1998).
- Mayor, D. An exploratory review of the electroacupuncture literature: clinical applications and endorphin mechanisms. Acupunct Med. 31 (4), 409-415 (2013).
- Liu, S. B., et al. A neuroanatomical basis for electroacupuncture to drive the vagal-adrenal axis. Nat. 598 (7882), 641-645 (2021).
- Li, Y., et al. Mechanism of electroacupuncture on inflammatory pain: neural-immune-endocrine interactions. J Tradit Chin Med. 39 (5), 740-749 (2019).
- Liu, L., et al. Transcriptomic insights into different stimulation intensity of electroacupuncture in treating COPD in rat models. J Inflamm Res. 17, 2873-2887 (2024).
- Zhang, L. X., et al. Electroacupuncture attenuates pulmonary vascular remodeling in a rat model of chronic obstructive pulmonary disease via the VEGF/PI3K/AKT pathway. Acupunct Med. 40 (4), 389-400 (2022).
- Gong, R. S., Liu, X. W., Zhao, J. Electroacupuncture-induced activation of GABAergic system alleviates airway inflammation in asthma model by suppressing TLR4/MYD88/NF-κB signaling pathway. Chin Med J (Engl). 136 (4), 451-460 (2023).
- Carneiro, E. R., et al. Electroacupuncture promotes a decrease in inflammatory response associated with Th1/Th2 cytokines, nitric oxide and leukotriene B4 modulation in experimental asthma. Cytokine. 50 (3), 335-340 (2010).
- Standardized manipulations of acupuncture and moxibustion - Part 11: electroacupuncture (GB/T 21709.11-2009). , Standardization Administration of China. (2009).
- Standardized manipulations of acupuncture and moxibustion - Part 20: basic techniques of filiform needle (GB/T 21709.20-2009). , Standardization Administration of China. (2009).
- Gao, S., Ji, L. Therapeutics of acupuncture and moxibustion. , 5th ed, People's Health Press. (2021).
- Ceylan, R., Demir, R., Zeren, M., Sinan, U. Y., Kucukoglu, M. S. Sleep quality and its predictors among dyspnea, fatigue and exercise capacity in pulmonary arterial hypertension. Acta Cardiol Sin. 40 (5), 618-626 (2024).
- Bausewein, C., Farquhar, M., Booth, S., Gysels, M., Higginson, I. J. Measurement of breathlessness in advanced disease: a systematic review. Respir Med. 101 (3), 399-410 (2007).
- Agarwala, P., Salzman, S. H. Six-minute walk test: clinical role, technique, coding, and reimbursement. Chest. 157 (3), 603-611 (2020).
- Tsai, J. S., Malik, S., Tjen-a-Looi, S. C. Pulmonary hypertension: pharmacological and non-pharmacological therapies. Life-Basel. 14 (10), 1265(2024).
- Zeng, J. M., et al. Overview of mechanism of electroacupuncture pretreatment for prevention and treatment of cardiovascular and cerebrovascular diseases. CNS Neurosci Ther. 30 (10), e14920(2024).
- Pan, P., et al. Effects of electro-acupuncture on endothelium-derived endothelin-1 and endothelial nitric oxide synthase of rats with hypoxia-induced pulmonary hypertension. Exp Biol Med (Maywood). 235 (5), 642-648 (2010).
- WHO benchmarks for the practice of acupuncture. , World Health Organization. https://www.who.int/publications/i/item/978-92-4-001688-0 (2021).
- Shu, Q., et al. Acupuncture and moxibustion have different effects on fatigue by regulating the autonomic nervous system: a pilot controlled clinical trial. Sci Rep. 6, 37846(2016).
- Wang, S., Zhang, F., Tang, H., Ning, W. The efficacy and safety of acupuncture and moxibustion for breast cancer lymphedema: a systematic review and network meta-analysis. Gland Surg. 12 (2), 215-224 (2023).
- Ou, Y., et al. Acupuncture and moxibustion in patients with cancer-related insomnia: a systematic review and network meta-analysis. Front Psychiatry. 14, 1108686(2023).
Reprints and Permissions
This article has been published
Video Coming Soon