The aim of this article is to present a method for identifying and protecting the recurrent laryngeal nerve during robotic thyroidectomy through the oral vestibular approach in the absence of the laryngeal nerve monitor.
Method Article
Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
In This Article
Summary
Abstract
Thyroid cancer is a common endocrine disease, and surgery is the most important means of treating thyroid cancer. Thyroid surgery and postoperative complications have been increasing in recent years. Among them, recurrent laryngeal nerve (RLN) injury is a common complication after thyroid surgery, which is mainly manifested as paralysis of the vocal cords and respiratory difficulties, negatively affecting the quality of life of patients. In recent years, with the continuous development of the concept of minimally invasive technology, we introduced a robotic surgical system into thyroidectomy via the oral vestibular approach and used a combination of blunt and sharp detachment to explore the RLN without the aid of an RLN monitor. Identification and protection of the RLN were successfully accomplished along with thyroid lobectomy and ipsilateral central lymph node dissection. Follow-up observations were conducted 1 week, 1 month, and 6 months after surgery to assess patient recovery. Overall, using this method in robotic thyroidectomy via the oral vestibular approach helped the operator quickly explore and protect the RLN, decreasing the occurrence of postoperative complications.
Introduction
The incidence of thyroid cancer has been rising steadily, along with an increase in the number of surgeries performed1. Concurrently, postoperative complications, particularly recurrent laryngeal nerve (RLN) injury, have become more prevalent following thyroid surgery2. The incidence of RLN injury varies between 2.3% and 26%3. Current techniques for identifying and protecting the RLN during thyroidectomy include visualizing the RLN without nerve monitoring, intermittent intraoperative nerve monitoring, and continuous intraoperative nerve monitoring4. It has been clearly established that visualizing the RLN is a primary factor in maintaining nerve function and reducing the incidence of postoperative RLN paralysis5,6,7,8. Therefore, a thorough understanding of the anatomy of the RLN in the thyroid region is crucial during thyroid surgery. The course of the RLN is closely related to the inferior thyroid artery9. Although non-recurrent laryngeal nerves exist, they are rare occurrences10. Additionally, the Zuckerkandl's tubercle serves as a key anatomical landmark for identifying the RLN11,12.
With the advancements in endoscopy and minimally invasive surgery, as well as increasing patient demand for aesthetically favorable outcomes, endoscopic thyroidectomy is an effective option. This approach ensures therapeutic efficacy while minimizing postoperative pain13. Compared to traditional endoscopy, robotic systems offer an enlarged three-dimensional high-definition surgical field and a rotatable articulated mechanical wrist, allowing surgeons to perform procedures with increased flexibility14,15. Realization of minimally invasive dissection involves the anterior cervical musculature, blood vessels, nerves, parathyroid glands, and lymph nodes through three 8 mm passages for thyroid surgery16,17,18. Currently, as few hospitals are performing transoral robotic thyroidectomy in China19. The learning curve for transoral robotic thyroidectomy demonstrates a proficiency threshold at 55 cases, with operative efficiency and safety outcomes plateauing beyond this point. Case volume analysis revealed a mean requirement of 52-55 procedures to achieve technical competency. Post-proficiency (>55 cases), significant reductions occur in Complication and procedure conversion rates. There is an urgent need to rapidly explore methods to protect RLNs during operations without using a nerve monitoring device.
This study aims to introduce a technique for rapid identification and preservation of the RLN during transoral robotic thyroidectomy without intraoperative neuromonitoring (IONM). Future prospective controlled studies are warranted to validate these findings.
Protocol
This study was conducted in conformance with the Declaration of Helsinki and approved by the Clinical Research Ethics Committee of Daping Hospital, the Third Affiliated Hospital of the Army Medical University, Chongqing, China (approval number: 2024-08). All patients mentioned in the study have signed informed consent forms.
Trial registration: China Clinical Trials Registry: ChiCTR2400089023, registered August 30, 2024.
1. Patient selection
- Select patients meeting the following inclusion criteria: age range: 18-70 years; diagnostic confirmation: histopathologically confirmed papillary thyroid carcinoma (PTC) with primary tumor diameter ≤4 cm, clinically staged as cN0, cN1a, and M0; treatment history: no prior cervical surgery or radiotherapy; operational feasibility: absence of absolute surgical or anesthetic contraindications; aesthetic prioritization: explicit patient-reported demand for scarless cervical outcomes.
- Exclude patients if they meet the following criteria: absolute contraindications to general anesthesia; prior radiotherapy history involving the head, neck, or upper mediastinal regions; cervical mobility limitations due to severe degenerative cervical spine disease or postsurgical cervical extension impairment; recent submental interventions, including cosmetic procedures (e.g, hyaluronic acid fillers, implants) within 3 months preoperatively; oral health contraindications: active infections (gingivitis, abscesses), denture-related complications, or restricted oral opening (<3 cm interincisal distance) secondary to temporomandibular disorders, buccal fibrosis, or muscular contractures; substernal thyroid extension; advanced tumor features: differentiated thyroid carcinoma with primary tumor diameter >2 cm or preoperative imaging evidence of extrathyroidal extension, cN1b nodal metastasis, or distant metastases (M1).
2. Preparation of the patient before surgery
- Ensure that all patients have received standardized ultrasound and enhanced neck CT preoperatively, while those with suspected thyroid tumors have undergone fine needle aspiration cytology (FNAC).
- Forty-eight hours preoperatively, perform standardized preoperative assessments, including electronic fiberoptic laryngoscopy for vocal cord evaluation and cervical extension exercises to optimize surgical positioning.
- Have a dentist evaluate patients treated with robotic surgery for oral hygiene and routine teeth cleaning 1-2 days before surgery. Treat all patients with chlorhexidine mouthwash immediately after admission for oral preparation, and administer the antibiotic cefuroxime sodium (10 mg) intravenously 30 min before surgery to prevent incision infection.
- Airway management
- Perform nasotracheal intubation using a 6.5 mm reinforced endotracheal tube under fiberoptic bronchoscopic guidance. Confirm proper tube placement using a capnometer (end-tidal CO₂ 35-40 mmHg) and bilateral chest auscultation.
- Position the patient in 15° neck extension using a standardized shoulder roll (height: 8 cm) with a foam head stabilizer, maintaining the sniffing position for optimal surgical exposure.
NOTE: Limit nasal mucosal compression duration to <120 min using pressure-distributing tube fixation devices.
- Ocular and auditory protection
- Apply a 5 mm ribbon of sterile ophthalmic lubricant to the bilateral conjunctival sacs.
- Insert medical-grade cotton balls (20 mm diameter) into external auditory canals with Hartmann alligator forceps under direct visualization.
- Secure the eyelids in a neutral position using hypoallergenic surgical tape (6 x 125 mm).
- Surgical field isolation
- Place a sterile absorbent cotton pad (10 x 15 cm) over facial skin surfaces.
- Apply an antimicrobial incise drape (15 x 25 cm) using a tension-free technique, aligning the superior border 2 cm anterior to the hairline, extending the inferior margin to the mentolabial groove, and positioning the lateral edges at the zygomatic arches.
- Verify complete adhesion integrity through standardized tenting test: Gently elevate drape edges circumferentially to confirm uniform seal formation (Figure 1).
- Robotic system configuration
- Position the surgical platform at 90° relative to the patient's right midaxillary line with the camera arm (Arm #2) coaxial to the transoral access axis, the instrument arms (Arms #1 & #3) maintaining 30 cm instrument triangulation, and system status confirmation via Ready for Docking indicator verification.
- Complete the predocking safety protocol.
- Verify >5 cm collision-free radius for all robotic arms.
- Test the energy device connections.
- Perform a 30° endoscope white balance calibration.
- Prepare the tumescent solution using aseptic technique by sequentially combining in a sterile mixing vessel: 10 mL of 2% Lidocaine HCl: 100 mg; ≤4.5 mg/kg total dose; 10 mL of 1% Ropivacaine HCl: 50 mg; ≤3 mg/kg total dose; 0.5 mL of 1:1,000 Epinephrine: 10 calibrated drops; ≤0.5 mg total; 120 mL of 0.9% Sodium Chloride. Maintain refrigerated at 4 °C (39.2 °F) in a thermal-stable container for ≤2 h.
3. Surgical procedures
- Perform tumescent injection and access port creation (Figure 2):
- Infuse 10 mL of tumescent solution (prepared per step 2.8) at 30 kPa pressure using a 10 mL single-use syringe at the primary site: 5 mm superior to the labial frenulum (FDI tooth 41-31 region) and at secondary sites: buccal mucosa between canines (FDI 13/23) and first molars (FDI 16/26) bilaterally.
- Create an 8 ± 0.5 mm horizontal stab incision at the frenulum injection site with a #11 scalpel.
- Insert an 8 mm optical trocar at a 45° cephalad angle by using blunt separation technology.
- Robotic system docking protocol
- Confirm system self-test completion and check sterile drape integrity.
- Arm positioning
- Align Camera Arm (#2) 90° to Frankfurt horizontal plane. Maintain 18 cm working distance from the oral commissure.
- Converge Instrument Arms (#1/#3) at 30° with 25 cm separation (measured arm-to-arm at trocar base). Set instrument exchange radius: 8 cm.
- Safety engagement
- Activate a 5 cm collision buffer zone (haptic force <0.3 N). Test the emergency retract function (retraction speed: 15 cm/s).
- Inject carbon dioxide (CO2) into the surgical field.
- Maintain EtCO2 in the surgical field: 6-8 mmHg (0.798-1.066 kPa) with a flow rate of 20 L/min.
NOTE: Look for and avoid subcutaneous emphysema and gas embolism.
- Maintain EtCO2 in the surgical field: 6-8 mmHg (0.798-1.066 kPa) with a flow rate of 20 L/min.
- Dissect the subcutaneous flap.
- Load the surgical forceps into the left trocar (Arm #1). Load the referenced shears (70 W) into the right trocar (Arm #3).
- Begin dissection using the surgical forceps to assist the shears. Dissect within the following boundaries: superior: 2 cm inferior to the mandibular border; inferior: superior border of the clavicle (Deaver's line); medial: anterior jugular vein corridor; lateral: external jugular vein-great auricular nerve complex; posterior: anterior sternocleidomastoid (SCM) margin at Erb's point.
- Perform negative parathyroid imaging using mitoxantrone hydrochloride in thyroid surgery (Figure 3).
- Load the surgical forceps into the left trocar (Arm #1). Load Monopolar Curved Scissors into the right trocar (Arm #3).
- Use the Monopolar Curved Scissors to make a 4-5 cm longitudinal incision along the linea alba cervicis (midline) (Cutting mode: 15 W; Coagulation mode: 13 W). Dissect the sternohyoid muscles using blunt separation mode (Soft Coag, 20 W). Elevate the thyroid surgical capsule using the curved tip in blunt mode. Expose the mid-third of the thyroid parenchyma (target zone).
- Use a 1 mL syringe to draw mitoxantrone hydrochloride injection (5 mg/mL). Inject 0.2 mL/site of mitoxantrone hydrochloride into the thyroid parenchyma (depth: 2-3 mm). Limit the total dose to ≤ 0.6 mg.
NOTE: Strictly exclude injection of mitoxantrone hydrochloride into thyroid arterial vasculature.
- Suspend the anterior neck muscle.
- Load surgical forceps into the left trocar (Arm #1). Load the shears into the right trocar (Arm #3).
- Use surgical forceps and load the shears to separate the Sternohyoid and expose the deep cervical fascia.
- Use 4-0 absorbable sutures to suture the sternohyoid muscle and scapulohyoid muscle at a distance of 1-2 cm from the sternohyoid muscle incision margin using horizontal cricoid cartilage sutures. Elevate the muscles to form an inclined angle of 15-20° with the tracheal axis to create tension.
- Perform indocyanine green (ICG) Fluorescence Imaging (Figure 4).
- Activate the scalpel in Precision Seal mode (70 W) to divide the thyrohyoid membrane. Dissect the Cricothyroid Space and identify the carotid bifurcation level. Maintain a 2 mm margin from the external branch of the superior laryngeal nerve. Cut off the superior thyroid artery.
- Administer 2 mL of ICG (2.5 mg/mL, sterile water-diluted) via the dorsal venous plexus of the foot. Complete injection within 5 s. Inject 30-45 s pre-imaging for optimal tissue uptake.
- Localize the recurrent laryngeal nerve (RLN).
- Load the surgical forceps into the left trocar (Arm #1) and the 5 mm Maryland Bipolar Coagulator into the right trocar (Arm #3).
- Confirm the triangle of RLN Entry: medial: inner border of the parathyroid gland; lateral: thyroid gland capsule; posterior: Inferior constrictor muscle of the larynx; critical Landmark: RLN enters the larynx posterior to the cricothyroid joint.
- Use the 4-0 Absorbable Suture (prepared per step 3.5.3) to pull the anterior neck muscle outward, exposing the thyroid lobe and the tracheoesophageal groove. Identify the parathyroid gland and preserve its vascular pedicle.
- Compress bleeding site with surgical gauze for exactly 3 s. Insert the Nipple Aspirator (Figure 5) percutaneously from the contralateral side. Aspirate oozing blood continuously until field visualization is achieved.
- Apply the Maryland Bipolar Coagulator to lyse fibrofatty tissue. Advance dissection depth ≤1 mm per instrument activation, making sure to alternate coagulation and irrigation cycles. Trace the RLN along its course and continue dissection until visualizing its laryngeal entry point. Confirm anatomic position posterior to the cricothyroid joint and maintain >3 mm distance from the RLN during energy delivery.
- Dissect the thyroid lobe and central lymph nodes.
- Confirm RLN entry point at the cricothyroid joint (Figure 6). Dissect the RLN and thyroid capsule using the Maryland forceps (deactivated energy mode). Mobilize the RLN inferomedially along its course. Preserve 1-2 mm perineural tissue surrounding the RLN at all times.
- Dissect the Ligament of Berry using unipolar scissors. Start at the RLN-tracheal junction using unipolar scissors. Follow the thyroid capsule curvature, advancing at 5-7 mm/s.
- Dissect the thyrothymic ligament and anterior thyroid fascia to divide the inferior thyroid pole vessels (2 mm from the RLN). Keep the ultrasonic blade parallel to the RLN and dissect the thyroid lobe and central lymph nodes (Figure 7). Activate the ultrasonic blade in 2 s bursts with 3 s cooling intervals.
- Postoperative protocol for specimen removal and wound management
- Place all excised tissues (thyroid lobe, lymph nodes, etc.) into the sterile specimen bag and retrieve them using an 8 mm trocar. Label the bag with the patient ID, specimen type, and laterality (e.g., "Right Thyroid Lobe, Zone VI Lymph Nodes").
- Irrigate the wound with 1,000-2,000 mL of warm (37 °C) sterile saline using low-pressure pulsatile lavage (30-50 psi), clearing debris, reducing bacterial load, and ensuring no residual tissue fragments.
- Create a 2 mm stab incision 2 cm lateral to the primary wound. Secure the drain with 5-0 absorbable sutures and set continuous suction to 125 mmHg. Close the fascia with the 3-0 wound closure device and the oral mucosa with 5-0 absorbable sutures.
- Measure drain output every 6 h and remove the drain at 24 h.
4. Postoperative follow-up
- Conduct postoperative voice assessment at 1 week, 1 month, and 6 months after surgery during follow-up.
- Assess vocal cord mobility using flexible laryngoscopy only when patients experience hoarseness or voice disorders to rule out potential RLN damage.
Results
Preoperative flexible laryngoscopy was performed 48 h prior to surgery to assess bilateral vocal cord mobility, with normal findings documented in all patients. No preoperative hoarseness or dyspnea was observed on the day of surgery. All patients underwent standardized postoperative follow-up at 1 week, 1 month, and 6 months, with no evidence of vocal cord paralysis or dysphonia identified during these assessments. Demographic and clinical characteristics of the cohort are summarized in Table 1.
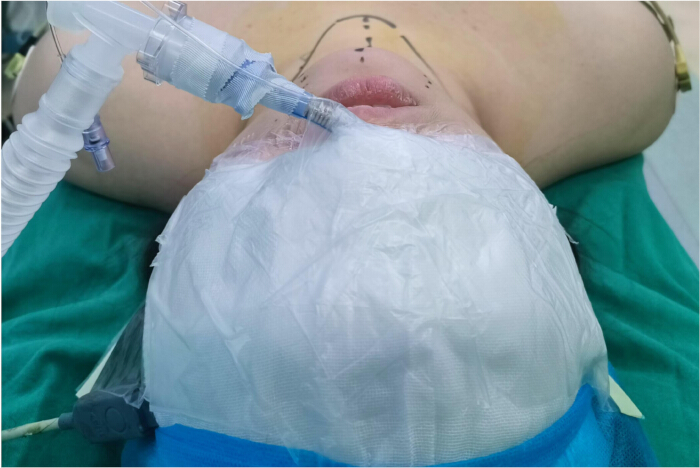
Figure 1: Placement of cotton pad. Lay a whole cotton pad flat over the face. Please click here to view a larger version of this figure.
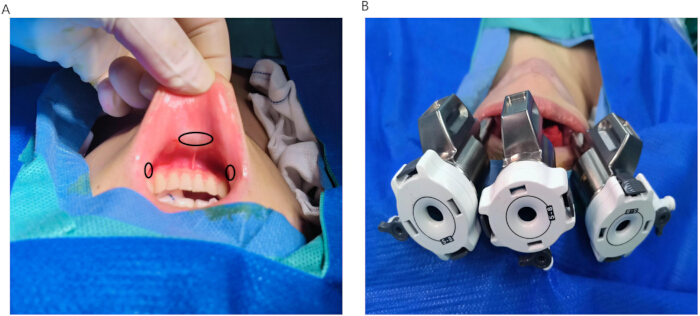
Figure 2: Trocar placement. (A) The points marked with black circles are the incision sites. (B) Trocar positions. Please click here to view a larger version of this figure.
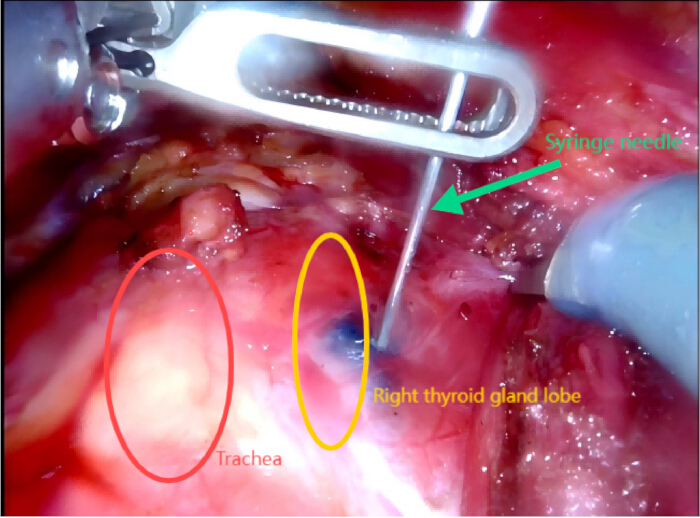
Figure 3: Injection of mitoxantrone hydrochloride tracer solution. Injection of mitoxantrone hydrochloride tracer solution enables negative imaging of the parathyroid gland. Please click here to view a larger version of this figure.
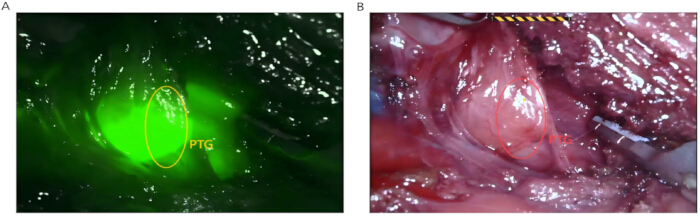
Figure 4: Localization of the parathyroid gland. Fluorescence imaging reveals the parathyroid gland (the left side shows a view under fluorescence, allowing for quick identification of the parathyroid gland's position; the right side displays the parathyroid gland under normal vision, where surrounding tissues significantly interfere). Please click here to view a larger version of this figure.
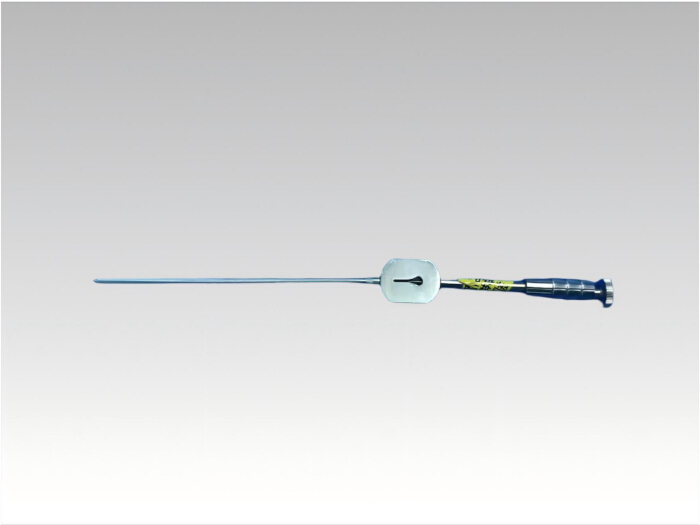
Figure 5: Nipple aspirator. A smoke extraction device. Please click here to view a larger version of this figure.
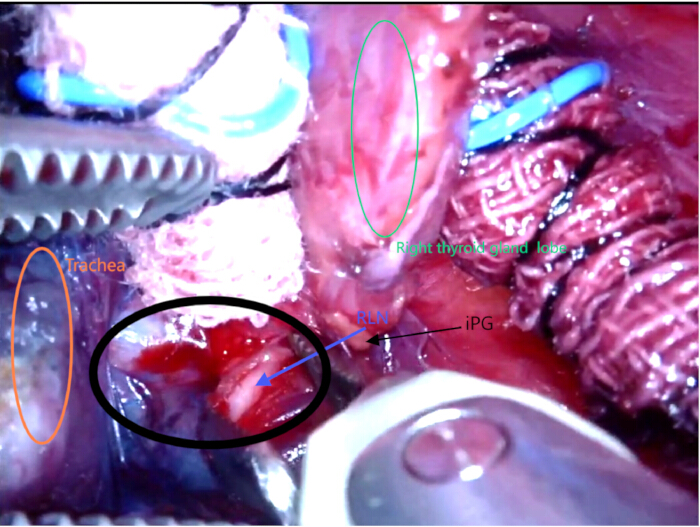
Figure 6: Identification of the recurrent laryngeal nerve at the esophagus entry. Explore the entry of the recurrent laryngeal nerve into the esophagus to locate the nerve. The black ellipse marks the "RLN triangle," the orange ellipse marks the "Trachea," and the green ellipse marks the "Right thyroid gland lobe". Please click here to view a larger version of this figure.
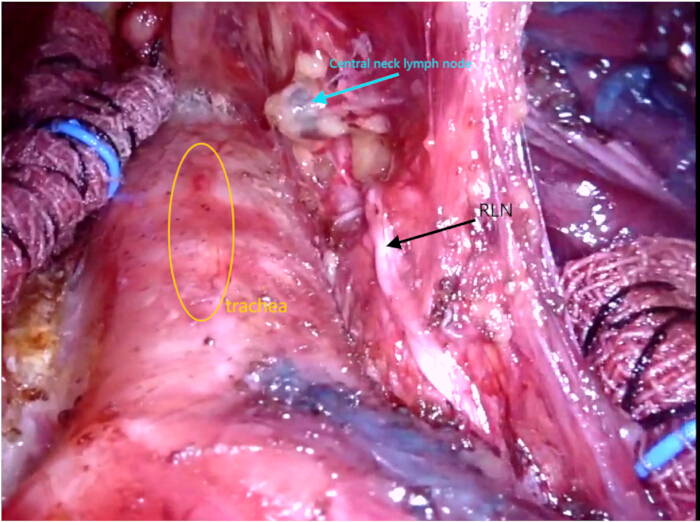
Figure 7: Tissue dissection. Use an ultrasonic scalpel to separate the tissue around the recurrent laryngeal nerve, reveal the course of the recurrent laryngeal nerve in the neck, and protect the nerve during the surgical procedure. The orange ellipse marks the "Trachea." Please click here to view a larger version of this figure.
Table 1: Clinical data of 25 patients. Please click here to download this Table.
Discussion
Recurrent laryngeal nerve (RLN) injury is the primary cause of vocal cord paralysis following thyroid surgery. Identifying the RLN remains the gold standard for preventing RLN injury during thyroidectomy. Currently, in traditional open surgery, rapid identification of the RLN primarily relies on RLN monitoring devices. However, tracheal intubation may result in improper positioning, inadequate size20,21, and displacement due to tracheal and cervical extension during the surgical procedure22,23,24. This can lead to weakened or lost laryngeal electromyography (EMG) signals, resulting in false-positive rates. In robotic thyroidectomy via the oral vestibular approach, due to the narrow operating space and tube interference with intraoperative neuromonitoring (IONM), visual localization of the RLN during surgery has become the preferred approach.
In current reports, surgeons primarily rely on anatomical landmarks such as the thyroid inferior artery and the Zuckerkandl's tubercle for visual localization of the RLN. Due to differences in visual angles and limited space compared to traditional open surgery, relying on traditional anatomical landmarks to locate the RLN is not practical in transoral robotic thyroidectomy. Therefore, after extensive exploration, our team developed a method where surgeons first identify the location of the parathyroid glands, then determine the "RLN triangle" region, enabling them to quickly locate the RLN within this area. The key procedural steps for this method are:
Dye injection procedure
Mitoxantrone Hydrochloride negative staining: Precisely injecting 5 mg/mL mitotranquine (<0.6 mL) into the thyroid capsule allows selective visualization of lymphatic structures without damaging the parathyroid glands (PTGs).
Indocyanine green (ICG) fluorescence: Intravenous injection of 2.5 mg/mL ICG, followed by near-infrared (NIR) imaging 30 s later, ensures real-time monitoring of PTG perfusion. This method not only determines the location of the parathyroid glands but also assesses the blood supply to the thyroid parathyroid glands.
The staining rate of Mitoxantrone hydrochloride for lymph nodes is 90.05%25, and the localization rate of ICG for parathyroid glands is 88.25%26. Combining the two can help surgeons quickly identify the parathyroid glands during surgery. However, when the parathyroid glands are embedded or if the PTG is occluded, ICG cannot reach the PTG via the blood vessels and highlight them for identification. In such cases, identification and localization rely on the surgeon's experience.
Anatomical landmark analysis
RLN entrance triangle identification: The triangular region formed by the medial border of the PTG, the thyroid capsule, and the laryngeal muscles serve as the primary landmark for RLN localization. Anatomical dissection is performed using a Lanzhou bipolar forceps (15 W pulse mode) to minimize thermal diffusion (radius ≤ 1.5 mm) while controlling microvascular bleeding (vessel diameter < 1 mm).
Hemostasis management: This area typically has an abundant blood supply, and bleeding or fluid leakage can contaminate the surgical field. Hemostasis can be achieved using compression or auxiliary suction methods without excessive electrocautery, thereby reducing the risk of thermal injury to the RLN.
Safety note
Intraoperative carbon dioxide (CO₂) insufflation during this procedure carries established risks of gas embolism and emphysema. Consequently, continuous hemodynamic monitoring and end-tidal CO₂ capnography were implemented to detect early signs of these complications. In this preliminary cohort (n = 25), no gas embolism or emphysema events were observed.
The learning curve for transoral robotic thyroidectomy is relatively long27, and surgeons must be proficient in the anatomical structures of the neck. According to relevant studies, the incidence of vocal cord paralysis as a complication following transoral robotic thyroidectomy with recurrent laryngeal nerve monitoring was 8.3% (5/60)19. During the follow-up period of this study, no patient developed vocal cord paralysis, and the recurrent laryngeal nerve was successfully visualized in all cases. However, in cases of anatomical variations, this method may not be applicable, and the surgeon may use a Maryland bipolar electrocautery device to slowly and bluntly dissect downward and inward along the carotid sheath until the nerve position is identified.
Three principal limitations warrant consideration:
First, the single-center, single-arm design with limited sample size (n = 25) necessitates validation through multicenter randomized controlled trials (RCTs) incorporating intraoperative neuromonitoring (IONM) of the recurrent laryngeal nerve. Second, non-standardized postoperative RLN assessment: the absence of objective laryngoscopic vocal fold evaluation and validated patient-reported outcomes (e.g., Voice Handicap Index) risks detection bias due to reliance on subjective voice assessment alone. Third, the lack of blinded assessors during postoperative evaluations may introduce observer bias in outcome determination.
In summary, using this method, during robotic thyroidectomy via the oral approach, the RLN can be identified and protected without the use of an RLN monitor, thereby reducing patients' medical expenses. With the development of artificial intelligence, machine learning algorithms capable of analyzing intraoperative videos may, in the future, identify the RLN by recognizing tissue texture and vascular patterns.
Disclosures
The authors declare that there are no conflicts of interest.
Acknowledgements
Supported by the 'Artificial Intelligence' medical research project of Daping Hospital, Army Medical University (Grant No. ZXAIYB014).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 0.9% Sodium Chloride | Generic Pharma | N/A | Sterile irrigation solution |
| 1% Ropivacaine HCl | Generic Pharma | N/A | Long-acting local anesthetic (10 mg/mL) |
| 1:1,000 Epinephrine | Generic Pharma | N/A | Injectable vasoconstrictor (1 mg/mL) |
| 2% Lidocaine HCl | Generic Pharma | N/A | Local anesthetic (20 mg/mL) |
| 3-0 V-Loc180 | COVIDIEN | 3-0, 2 Metric, 6" (15 cm) | Absorbable braided suture |
| 4-0 GL181 | COVIDIEN | N/A | Absorbable braided suture |
| 5-0 GL-885 | COVIDIEN | N/A | Absorbable braided suture |
| 5-mm Maryland Bipolar Coagulator | Olympus | MB-246 | Preloaded laparoscopic bipolar forceps (5mm) |
| 6.5-mm reinforced endotracheal tube | Smiths Medical | Portex 100-65R | Disposable surgical blade (#11) |
| 8 mm optical trocar | Ethicon | HARXX054E | Establishment of surgical space access |
| 11 scalpel | Swann-Morton | SM-11 | Disposable surgical blade (#11) |
| 30° endoscope white balance calibration | Stryker | D-Light P | Endoscopic light calibration module |
| da Vinci Xi Surgical Platform | Intuitive Surgical | IS4000 | 4th-gen robotic surgery system |
| EndoWrist Monopolar Curved Scissors | Intuitive Surgical | 470030-01 | 5 mm wristed monopolar shears (single-use) |
| Harmonic ACE+8 shears | Ethicon | HARXX054E | 5 mm ultrasonic dissector/blood vessel sealer |
| Indocyanine green | Akorn | NDC 17478-310-10 | NIR fluorescent agent (25 mg/vial) |
| Mitoxantrone Hydrochloride Injection | Generic Pharma | N/A | Antineoplastic agent (20 mg/10 mL) |
| Nipple aspirator | Stryker | 232-700-110 | Smoke evacuation system (laparoscopic) |
References
- Dralle, H. Surgical assessment of complications after thyroid gland operations. Chirurg. 86 (1), 70-77 (2015).
- Wojtczak, B., Kaliszewski, K., Sutkowski, K., Bolanowski, M., Barczyński, M. A functional assessment of anatomical variants of the recurrent laryngeal nerve during thyroidectomies using neuromonitoring. Endocrine. 59 (1), 82-89 (2018).
- Toniato, A., et al. Complications in thyroid surgery for carcinoma: one institution's surgical experience. World J Surg. 32 (4), 572-575 (2008).
- Cleere, E. F., et al. Intra-operative nerve monitoring and recurrent laryngeal nerve injury during thyroid surgery: a network meta-analysis of prospective studies. Langenbecks Arch Surg. 407 (8), 3209-3219 (2022).
- Hermann, M., Alk, G., Roka, R., Glaser, K., Freissmuth, M. Laryngeal recurrent nerve injury in surgery for benign thyroid diseases: effect of nerve dissection and impact of individual surgeon in more than 27,000 nerves at risk. Ann Surg. 235 (2), 261-268 (2002).
- Dralle, H., Sekulla, C., Lorenz, K., Brauckhoff, M., Machens, A. Intraoperative monitoring of the recurrent laryngeal nerve in thyroid surgery. World J Surg. 32 (7), 1358-1366 (2008).
- Gavilán, J., Gavilán, C. Recurrent laryngeal nerve: identification during thyroid and parathyroid surgery. Arch Otolaryngol Head Neck Surg. 112 (12), 1286-1288 (1986).
- Périé, S., et al. Value of recurrent laryngeal nerve monitoring in the operative strategy during total thyroidectomy and parathyroidectomy. Eur Ann Otorhinolaryngol Head Neck Dis. 130 (3), 131-136 (2013).
- Sturniolo, G., et al. The recurrent laryngeal nerve related to thyroid surgery. Am J Surg. 177 (6), 485-488 (1999).
- Page, C., Monet, P., Peltier, J., Bonnaire, B., Strunski, V. Non-recurrent laryngeal nerve related to thyroid surgery: report of three cases. J Laryngol Otol. 122 (7), 757-761 (2008).
- Serpell, J. W. New operative surgical concept of two fascial layers enveloping the recurrent laryngeal nerve. Ann Surg Oncol. 17 (6), 1628-1636 (2010).
- Yun, J. S., et al. The Zuckerkandl's tubercle: a useful anatomical landmark for detecting both the recurrent laryngeal nerve and the superior parathyroid during thyroid surgery. Endocr J. 55 (5), 925-930 (2008).
- Papaspyrou, G., et al. Extracervical approaches to endoscopic thyroid surgery. Surg Endosc. 25 (4), 995-1003 (2011).
- Clark, J. H., Kim, H. Y., Richmon, J. D. Transoral robotic thyroid surgery. Gland Surg. 4 (5), 429-434 (2015).
- Richmon, J. D., Pattani, K. M., Benhidjeb, T., Tufano, R. P. Transoral robotic-assisted thyroidectomy: a preclinical feasibility study in 2 cadavers. Head Neck. 33 (3), 330-333 (2011).
- Wilhelm, T., Metzig, A. Endoscopic minimally invasive thyroidectomy (eMIT): a prospective proof-of-concept study in humans. World J Surg. 35 (3), 543-551 (2011).
- Nakajo, A., et al. Trans-oral video-assisted neck surgery (TOVANS): a new transoral technique of endoscopic thyroidectomy with gasless premandible approach. Surg Endosc. 27 (4), 1105-1110 (2013).
- Anuwong, A. Transoral endoscopic thyroidectomy vestibular approach: a series of the first 60 human cases. World J Surg. 40 (3), 491-497 (2016).
- He, Q. Q., et al. Comparison of transoral vestibular robotic thyroidectomy with traditional low-collar incision thyroidectomy. J Robot Surg. 18 (1), 88(2024).
- Tsai, C. J., et al. Electromyographic endotracheal tube placement during thyroid surgery in neuromonitoring of recurrent laryngeal nerve. Kaohsiung J Med Sci. 27 (3), 96-101 (2011).
- Lu, I. C., et al. Optimal depth of NIM EMG endotracheal tube for intraoperative neuromonitoring of the recurrent laryngeal nerve during thyroidectomy. World J Surg. 32 (9), 1935-1939 (2008).
- Wu, C. W., et al. Loss of signal in recurrent nerve neuromonitoring: causes and management. Gland Surg. 4 (1), 19-26 (2015).
- Kim, H. Y., et al. Impact of positional changes in neural monitoring endotracheal tube on amplitude and latency of electromyographic response in monitored thyroid surgery: results from the porcine experiment. Head Neck. 38 (Suppl 1), E1004-E1008 (2016).
- Barber, S. R., et al. Changes in electromyographic amplitudes but not latencies occur with endotracheal tube malpositioning during intraoperative monitoring for thyroid surgery: implications for guidelines. Laryngoscope. 127 (9), 2182-2188 (2017).
- Chen, S., Hou, X., Hua, S., et al. Mitoxantrone hydrochloride injection for tracing helps to decrease parathyroid gland resection and increase lymph node yield in thyroid cancer surgery: a randomized clinical trial. Am J Cancer Res. 12 (9), 4439-4447 (2022).
- Motiee-Langroudi, M., Farahzadi, A., Shirkhoda, M., et al. Identifying and preserving parathyroid glands during thyroid surgery using indocyanine green and a review of the literature. Cancer Rep (Hoboken). 8 (6), e70226(2025).
- Kim, K. H., et al. Learning curve of transoral robotic thyroidectomy. Surg Endosc. 37 (1), 535-543 (2023).
Reprints and Permissions
