Herein, we describe a surgical method to transect the anterior cruciate ligament (ACL) as a reliable model to induce knee osteoarthritis in rodents and methodologies for harvesting knee synovial fluid, measuring knee edema, and assessing osteoarthritis severity.
Method Article
Anterior Cruciate Ligament Transection and Synovial Fluid Lavage in a Rodent Model to Study Joint Inflammation and Posttraumatic Osteoarthritis
* These authors contributed equally
In This Article
Summary
Abstract
Osteoarthritis (OA) is a joint disease characterized by chronic pain and currently has no cure. A subset of OA, posttraumatic osteoarthritis (PTOA), can occur after a joint injury. The knee is one of the most affected joints, and among knee injuries, injuries to the ACL are among the most common. Symptomatic OA, which is accompanied by changes to the joint such as cartilage degradation and osteophyte formation, can develop years after the initial injury, but early joint changes can be detected shortly after. Inflammation is considered one of the contributing factors in PTOA development, and the pro-inflammatory mediators produced in response to an injury can catalyze PTOA development. In animal models, surgically injuring structures in the knee is a widely used method of OA induction, and a common surgical technique is an ACL transection (ACLT). The purpose of this study is to describe our ACLT technique for the induction of OA, as well as methods to monitor joint inflammation and quantify OA severity. To assess inflammation post-surgery, we describe a technique for measuring knee edema as well as a technique for harvesting and analyzing knee synovial fluid. To evaluate the long-term joint changes associated with OA, we present a semi-quantitative scoring system we developed to evaluate OA severity via microCT imaging.
Introduction
The anterior cruciate ligament (ACL) is a critical structure in the knee joint, providing stability and preventing excessive forward movement of the tibia relative to the femur1. ACL injuries are among the most common knee injuries, particularly in sports that involve sudden stops, jumps, or changes in direction2. These injuries can range from partial tears to complete ruptures and often necessitate surgical intervention for optimal recovery3. However, even after surgical treatment, ACL injuries often lead to long-term joint changes, including chondral wear, osteophyte formation, and structural alterations of the subchondral bone. These changes collectively contribute to joint degeneration, commonly referred to as posttraumatic osteoarthritis (PTOA)4,5.
While the progression from initial ACL injury to symptomatic PTOA can span anywhere from as soon as 2 years to as long as 20 years following the injury, early joint changes can be detected within just a few weeks6,7,8,9. One key feature of these early changes is the elevated presence of inflammatory cytokines (e.g., interleukin (IL)-1, IL-6, tumor necrosis factor (TNF)) and markers of extracellular matrix breakdown (e.g., metalloproteinases (MMPs) and CTX-II). Synovial fluid assessments of these markers of inflammation and degradation provide crucial insights into the acute and chronic phases of joint pathology. For instance, IL-1 and IL-6 levels peak in the synovial fluid of the injured joint within the first month post-injury. Although these levels decline over time, they rarely return to the normal, baseline level, even years after treatment10,11,12. This initial pro-inflammatory response triggers a cascade of joint damage, including synovial inflammation, cartilage degradation, and biomechanical alterations, perpetuating tissue breakdown and accelerating joint degeneration13. Additionally, acute inflammation following ACL injury often results in joint effusion and knee edema, exemplified by the swelling and fluid accumulation within the joint14.
To replicate ACL injury and investigate the progression of PTOA, the surgically induced ACL transection (ACLT) model in mice is widely used15,16. This model involves cutting the ACL to simulate injury and assessing the resulting biological and mechanical consequences. The ACLT model is a valuable tool for studying the inflammatory response, cartilage degradation, and biomechanical alterations post-injury, allowing insights into the molecular and cellular mechanisms driving PTOA. Furthermore, it enables the evaluation of therapeutic strategies aimed at mitigating joint degeneration and preserving function. In humans, synovial fluid analysis is widely used to monitor inflammation and cartilage degradation over time, as obtaining synovial fluid is relatively straightforward17,18. However, in mice, collecting synovial fluid after injury models is challenging. In this manuscript, we describe our surgical technique for ACLT and a knee lavage method for synovial fluid collection to assess inflammatory and degradative markers. We also present a method for measuring knee size to quantify edema following joint injury. Additionally, we describe our microCT assessment method to grade the severity of PTOA post-ACLT. These approaches provide complementary tools for evaluating the acute and chronic effects of ACL injury in a preclinical setting.
Protocol
All animal studies were conducted in accordance with the Guidelines for the Care and Use of Laboratory Animals and were approved by the Institutional Animal Care and Use Committee of Brigham and Women’s Hospital.
1. Animal preparation
NOTE: The choice of mouse sex should align with the study's objectives, as even though ACLT reliably induces PTOA in both sexes, the severity and progression may differ.
- Anesthesia preparation: Prepare ketamine-xylazine (KX) anesthetic solution in advance.
NOTE: Inhalant anesthesia (2% isoflurane) can also be used. - Surgical controls: Use a separate age-matched, sham-operated group as the surgical control.
NOTE: The contralateral knee should not serve as a sham control, as this may raise animal welfare concerns. However, it can be used as a healthy, uninjured control to establish baseline joint conditions in paired analyses. - Animal age selection: Use 8-week-old mice to reflect the typical age at which ACL tears most commonly occur. However, any skeletally mature mouse can undergo this procedure.
2. Pre-operative care
NOTE: If the mice are transported from a different facility, allow at least 1 week for them to acclimate to their new environment before performing surgery.
- Ensure the surgery is performed in an aseptic manner, with all surfaces sterilized (e.g., using sterile drapes to cover surgical areas), and ensure the use of sterile instruments and appropriate surgical personal protective equipment (PPE).
- Induce anesthesia by administering an intraperitoneal injection of ketamine (100 mg/kg) and xylazine (10 mg/kg).
- Once anesthetized, apply eye lubricant and shave the fur over the knee to be operated on, covering the front and lateral sides from the mid-shin to the mid-thigh using small hair clippers.
NOTE: The selection of the hindlimb knee is at the researcher's discretion, based on the ease of surgery - Ensure the mouse is fully anesthetized and unresponsive to the toe pinch reflex.
- Disinfect the exposed skin by applying an antibacterial skin cleanser (e.g., betadine and 70% alcohol). Repeat disinfection 3 times.
- Administer an opioid analgesic (e.g., 0.05 mg/kg of buprenorphine) subcutaneously for pre-emptive analgesia.
NOTE: The analgesic should either be an extended-release formula to provide an analgesic effect for 72 h following surgery or should be administered regularly during this time frame to mitigate pain during recovery. - Administer an NSAID (e.g., 5 mg/kg meloxicam) as recommended unless NSAID administration interferes with the outcome of interest.
- Position the mouse on its dorsal side underneath a dissection microscope. Ensure the knee to be operated upon is facing upward and within the viewing field of the microscope.
- Cover the mouse with a sterile drape, leaving a small keyhole opening.
- Position the leg to be operated on with the knee flexed at approximately 90° with the patella facing upward. Use a surgical tape to keep the knee in a flexed position.
3. Anterior cruciate ligament transection
- Adjust the microscope to focus on the patella.
- Using forceps, pinch the skin over the patella and make a small midline longitudinal incision over the knee using a scalpel blade. Extend the incision to approximately 1 cm and retract the skin to expose the patellar tendon (Figure 1A).
- Flex the knee to about 120°. Use the non-dominant hand to maintain knee flexion and to keep the skin edges retracted, facilitating visualization of the patellar tendon (Figure 1B).
- Identify the medial border of the patellar tendon and make an incision with a No. 11 blade along this margin, extending from its midpoint to the superior pole of the patella to open the joint capsule (Figures 1C-E).
NOTE: If bleeding occurs, apply gentle pressure with a sterile cotton swab for 5-10 s to control hemostasis. - Using blunt-tip forceps, gently grasp the patellar tendon, lifting slightly upward and shifting laterally to dislocate the patella and fully expose the knee joint (Figure 1F).
- At this stage, the infrapatellar fat pad (IFP) will be visible (Figure 2A). Using blunt-tip forceps, gently shift the medial portion of the IFP to expose the ACL while preserving IFP integrity (Figure 2B).
NOTE: Complete removal of the IFP is avoided, as it plays a role in producing inflammatory markers. Since this model focuses on studying the inflammatory response following an injury that leads to PTOA, retaining the IFP is preferred. If bleeding occurs, apply gentle pressure with a sterile cotton swab for 5-10 s to control hemostasis. - While maintaining the knee at a 120° flexion, identify the ACL, which extends from the internal surface of the lateral femoral condyle to the center of the tibial plateau (Figure 2C, D).
- Using microsurgical scissors, carefully transect the ACL under microscope visualization, ensuring the surrounding cartilage, meniscus, and other ligaments remain intact (Figure 2E). The ACLT model is complete at this stage. In some cases, the remnants of the transected ACL can be visualized (Figure 2F).
- Confirm ACL transection by performing an anterior-posterior drawer test. Flex the knee to approximately 90°, stabilize the proximal tibia with fingers, and use blunt-tip forceps to gently apply a posterior force to the distal femur. Posterior translation of the distal femur confirms successful ACLT (Figure 3).
- Reposition the patella and patellar tendon to their anatomical position by lifting slightly and shifting medially (Figure 4A, B). Close the joint capsule with a single stitch using absorbable 6-0 sutures, securing the muscle surrounding the patella to the adjacent medial muscle tissue. Then, close the skin with 2-3 stitches using absorbable 6-0 sutures (Figure 4C).
- For sham surgery, perform the same procedure, but without transecting the ACL. Open the joint capsule and dislocate the patella and IFP as described. Visualize the ACL without transecting it, then replace the patella and IFP, and close the joint capsule and the skin.
4. Post-operative care
- Post-surgery, place the mouse on a heat pad and allow it to recover from anesthesia until fully conscious.
- Once the mouse is fully ambulatory, transfer it to a clean cage with fresh bedding for recovery.
- For the first 72 h post-surgery, closely monitor the mouse for signs of pain or distress, including: changes in body weight (typically no more than a 5% decrease), reduced grooming or excessive grooming around the incision site, signs of general health deterioration (such as hunched posture, facial grimacing, or abnormal respiration), and wound infection (including swelling, discharge, or wound dehiscence). If meloxicam is used, administer it every 24 h for 48 h.
- After the initial 72 h post-surgery, maintain the mouse as usual until the endpoint of interest based on the study design.
5. Evaluation of knee size (edema)
- Assess knee edema by measuring the medio-lateral width of the knee using a Vernier caliper (a digital caliper with a fine adjustment thumb wheel is recommended for precise and controlled measurements). Measure a live animal or post-mortem. Close the caliper gradually until it gently contacts the medial and lateral borders of the knee.
NOTE: While the caliper should be snug, care must be taken to avoid applying excessive pressure, as this could compress the knee and artificially reduce the measured width, leading to inaccurate results. The goal is to keep the caliper properly fitted without visibly compressing the knee. Tightening should stop once further adjustments begin to decrease the knee's size measurement (Figure 5). - Position the anesthetized or euthanized animal dorsally on a flat surface, ensuring the knee is facing upward. Flex the knee to approximately 90° and maintain this position. To keep the knee in flexion, secure the leg using surgical tape or, if performing post-euthanasia, a dissection pin. Measure the width of the knee using the caliper as described.
- Alternatively, if anesthesia is not preferred, take measurements with multiple people so that one individual can gently restrain the animal while the other obtains knee width measurements.
- To ensure reliability, measure each knee at least twice. Apply the same technique to both the injured and contralateral (uninjured) knees. Report the data as the difference between the two knees (delta knee size), not as absolute values, which reduces variability due to measurement technique and variations in individual mouse size.
6. Synovial fluid harvesting (knee joint lavage)
- Euthanize the animal using an approved method, following national licensing regulations, local guidelines, and experimental protocols. In this study, euthanasia was performed using CO2 asphyxiation followed by cervical dislocation.
- Expose the knee joint by making an anterior longitudinal incision over the knee, dissecting through the skin and underlying tissues to fully expose the patellar tendon and patella.
- Using a No. 11 blade, open the joint capsule along the medial side of the patellar ligament extending from its midpoint to the superior edge of the kneecap (Figure 6A, B).
- Displace the patella by gently moving it laterally to access the joint space, using care to ensure no damage to surrounding structures.
- Flex the knee to approximately 120° to ensure the joint cavity is well positioned for lavage to facilitate synovial fluid collection (Figure 6C).
- Prefill a tube with 100 µL of room-temperature phosphate-buffered saline (PBS).
- Using a P10 pipette, perform serial knee lavages with 2.5 µL of room-temperature PBS (Figure 6D-F) and add to the prefilled tube, for a total of 8 repetitions. The cumulative volume of knee lavage fluid should reach 120 µL.
- Centrifuge the knee lavage fluid at 4 °C for 5 min at 240 g to separate the cellular components from the supernatant.
NOTE: The cellular components can be used for cell counting, CytoSpin analysis, or flow cytometry. For flow cytometry analysis, pooling samples from multiple animals may be necessary to obtain sufficient cells for accurate analysis. - Store the supernatant at -80 °C for future analysis.
NOTE: In this study, the supernatant was used for multiplex analysis of pro-inflammatory cytokines and matrix metalloproteases (MMPs).
7. MicroCT analysis (PTOA severity in distal femur)
- Sample preparation: After collecting the synovial fluid, harvest the tibiofemoral joints by carefully dissecting the distal femur and proximal tibia, ensuring joint integrity is preserved.
NOTE: Remove excess muscle tissue surrounding the knee but take caution to preserve bone structure integrity. Preserve synovial tissue if synovitis is analyzed by histology; harvest independently if pro-inflammatory markers are evaluated via qPCR. - Fix the samples in 4% paraformaldehyde (PFA) at 4 °C for 5 days. Transfer them to 70% ethanol and store at 4 °C.
- Perform high-resolution microCT scans using the following parameters: 7-µm isotropic voxel size, 55 kVp X-ray tube voltage, 0.145 mA current, 600 ms integration time per projection.
- After scanning, export microCT data as DICOM files for further analysis.
- Load DICOM files into an image processing software for visualization, 3D reconstruction, and analysis.
- Use the 3D reconstruction tool to assess all regions of the knee, and in the sagittal view of the distal femur, identify four regions of interest (ROIs) from posterior to anterior for scoring (Figure 9)19 The posterior trough of the growth plate, the posterior aspect of the growth plate peak, anterior aspect of the growth plate peak, and anterior trough of the growth plate.
- Once an ROI is identified, select a corresponding image in the coronal view. Repeat for each ROI for a total of four images for each tibiofemoral joint.
- Save images as blinded files for unbiased analysis.
- Grade PTOA severity on coronal microCT images as previously reported19. Briefly, this semi-quantitative scoring system assesses femoral asymmetry, the presence and size of osteophytes, and femoral condyle flattening at four anatomical locations. Then, score each site on a scale of 0-6, with 6 being the most severe, for a total possible score of 24. Have at least two independent, blinded examiners score the site and average the scores for the final score.
NOTE: Two independent examiners should evaluate microCT images, and examiners must be blinded to experimental conditions to reduce bias. The final PTOA score is determined by averaging the scores from both examiners.
Results
The ACLT procedure is an effective and reproducible surgical method to induce osteoarthritis in the rodent knee. After the ACLT procedure was performed under sterile conditions, the mice showed no signs of distress or infection at the incision site and moved freely without signs of lameness in the operated limb.
Knee size was measured to monitor knee edema following ACLT (Figure 7A). To control for variation in mouse size, the width of the injured knee was normalized to the width of the contralateral knee. After ACLT, knee size increased significantly before gradually decreasing toward baseline. Synovial fluid in the knee was harvested via knee lavage at various time points following ACLT to monitor the inflammatory response post-injury (Figure 7B-F). There was an increase in leukocyte recruitment in the knee synovium, determined by manually counting cells in the synovial fluid, and this was sustained throughout the first week post-injury (Figure 7B). A multiplex assay was used to determine the levels of pro-inflammatory markers in the knee synovial fluid post-surgery. There was a significant increase in IL-1β on the first day following surgery, but the levels decreased shortly after (Figure 7C). Both IL-6 and TNF-α increased significantly on the first day after surgery and remained elevated 1-week post-surgery before returning to baseline (Figure 7D,E). Similarly to IL-1β, MMP-9 levels were elevated significantly immediately after surgery before gradually decreasing back to baseline (Figure 7F).
Osteoarthritis is associated with structural changes to bone and cartilage. Osteophyte formation is a common feature of OA, and considering morphological changes to the bone is important when assessing OA severity post-injury. A semi-quantitative scoring system was developed to evaluate OA severity based on asymmetry, the presence of osteophytes, and condyle flattening. Images of the distal femur are taken in the sagittal view at four anatomical locations and then are blindly scored by at least two examiners and averaged19. Figure 8A depicts representative images of the tibiofemoral joint of an uninjured and an injured knee at 8 weeks post-ACLT. Femoral OA severity is scored on a 6-point scale, and the score of the four ROIs is summed, resulting in a possible total score of 24. Eight weeks post-ACLT, the injured knees have severe OA compared to the contralateral knees, according to the criteria of this scoring system (Figure 8B). Cartilage damage is also a critical consideration when assessing OA. To do so, tibiofemoral joints are decalcified, embedded in paraffin, and sectioned (5 µm). The samples are then stained with Safranin-O/Fast Green, which stains the bone green and the cartilage pink (Figure 8C). Cartilage damage severity can be quantified via the osteoarthritis cartilage histopathology assessment system (OARSI)20. At 8 weeks post-ACLT, the tibiofemoral joint of the injured limbs has considerable cartilage damage compared to the contralateral knees (Figure 8D). Other histopathological methods can be used to assess cartilage damage, such as the articular cartilage structure (ACS) grading scheme, which evaluates cartilage in a similar manner using hematoxylin and eosin (HE) staining21.
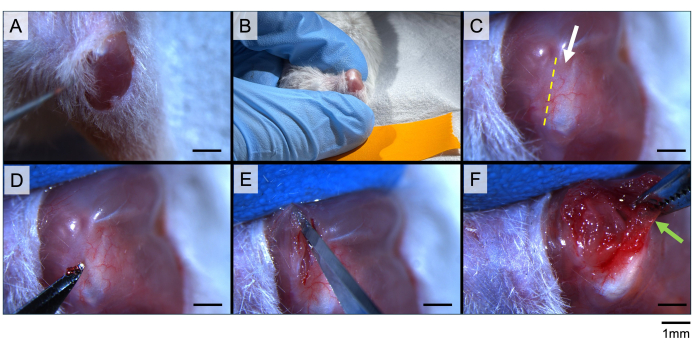
Figure 1: Anterior cruciate ligament (ACL) transection. Part 1. Exposing the knee joint. (A) A midline longitudinal incision is made over the knee. (B) The knee is flexed to approximately 120°, with the non-dominant hand maintaining flexion and retracting the skin edges. (C) The patellar tendon (white arrow) and its medial border (yellow dashed line) are identified. (D) A No. 11 blade is used to carefully incise the joint capsule, starting at its midpoint and extending to the superior pole of the patella. (E) superior pole of the patella. (F) The patellar tendon and patella (green arrow) are gently lifted and laterally displaced, allowing for complete exposure of the knee joint. Please click here to view a larger version of this figure.
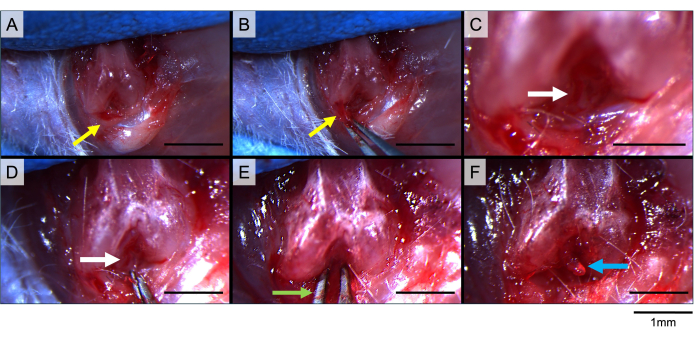
Figure 2: Anterior cruciate ligament (ACL) transection. Part 2. Identifying and transecting the ACL. (A) The infrapatellar fat pad (IFP) is identified (yellow arrow) and (B) its medial portion is gently shifted medially to expose the ACL while preserving IFP integrity (yellow arrow). (C,D) The ACL is identified (white arrow). (E) Microsurgical scissors (green arrow) are used to carefully transect the ACL. (F) In some cases, remnants of the transected ACL (blue arrow) can be visualized. Please click here to view a larger version of this figure.
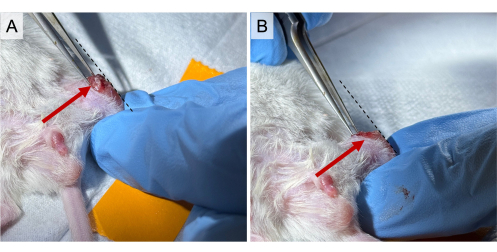
Figure 3: Anterior-posterior drawer test. The knee is flexed to approximately 90°, with the proximal tibia stabilized by the fingers, and a gentle force is applied to translate the distal femur (red arrow) posteriorly. (A) A virtual line (dashed black line) running longitudinally along the anterior surface of the tibia demonstrates the normal relationship between the tibia and the distal femur. (B) A positive anterior-posterior drawer test (successful ACL transection) is indicated when the distal femur can be translated posteriorly, causing it to move away from the anterior longitudinal line of the tibia. Please click here to view a larger version of this figure.
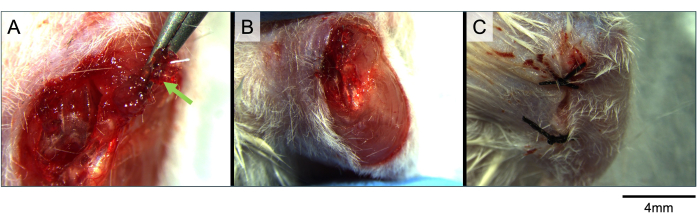
Figure 4: Anterior cruciate ligament (ACL) transection. Part 3. Closure. (A) The patella and patellar tendon (green arrow) are repositioned to their anatomical position. (B) The joint capsule and (C) the skin are closed. Please click here to view a larger version of this figure.
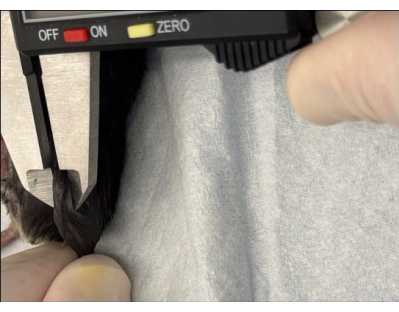
Figure 5: Knee size measurement. A Vernier caliper is used to measure the knee size by assessing the medio-lateral width. Flex the knee to approximately 120° and gradually close the caliper until it gently contacts the medial and lateral borders of the knee. For precise and controlled measurements, a digital caliper with a fine-adjustment thumb wheel is recommended. Please click here to view a larger version of this figure.
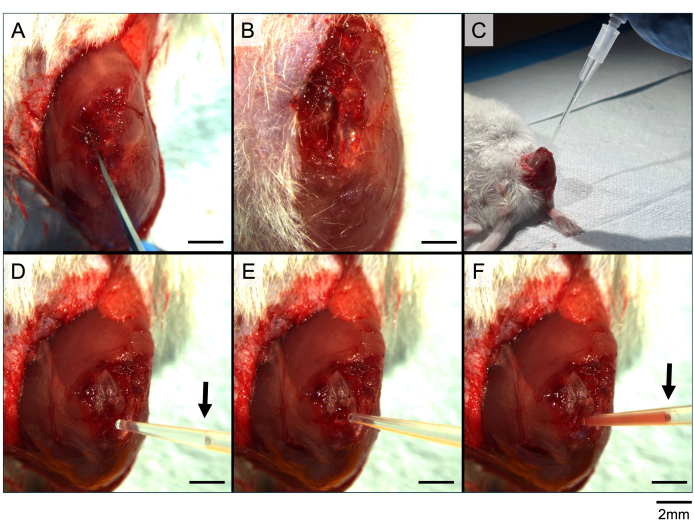
Figure 6: Synovial fluid harvesting (knee joint lavage). (A,B) The knee joint is exposed, and the joint capsule is incised along the medial side of the patellar tendon. (C) The knee is flexed to approximately 120°. (D-F) A P10 pipette is used to perform serial knee lavages with 2.5 µL of phosphate-buffered saline (black arrow) each time. Please click here to view a larger version of this figure.
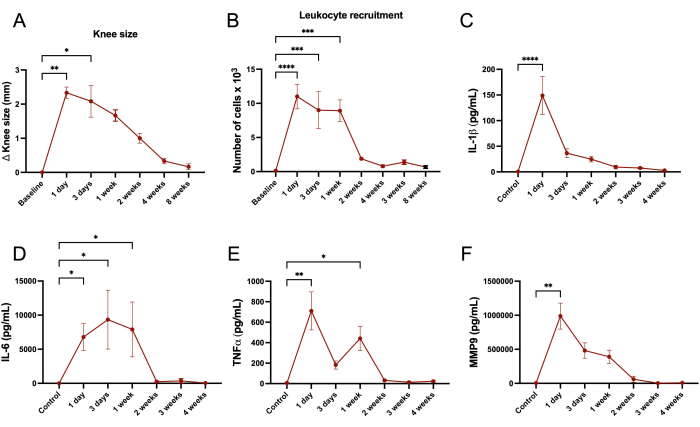
Figure 7: ACLT initiates an inflammatory reaction in the knee. (A) Digital calipers were used to measure the knees of each animal. Change in knee size was determined by the difference between the injured and the uninjured knees. (B) Leukocyte recruitment was determined by manually counting the cell population of the synovial fluid in the knee post-harvest. (C-F) Multiplex analysis was used to determine the levels of IL-1β (C), IL-6 (D), TNF-α (E), and MMP-9 (F). C57B6/J female mice were used for this study. Please click here to view a larger version of this figure.
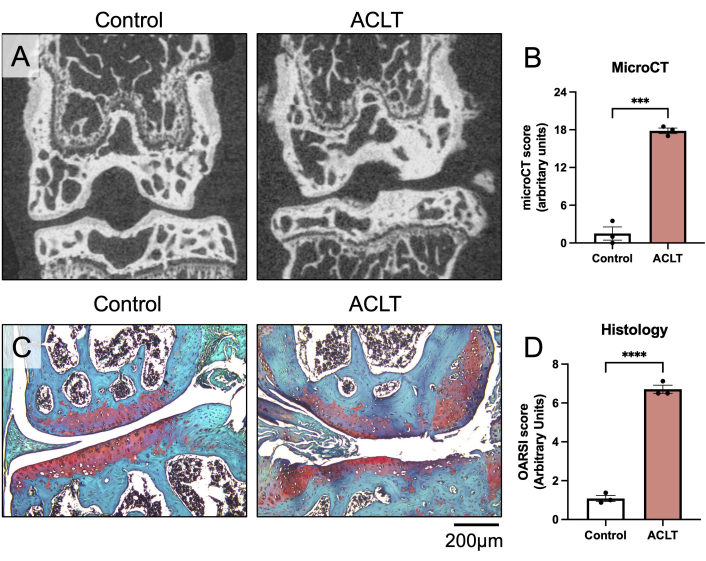
Figure 8: ACLT results in morphological changes to the bone and cartilage associated with osteoarthritis. Eight weeks after surgery, mice were euthanized, and the tibiofemoral joints of the injured and uninjured limbs were harvested. (A) MicroCT was used to scan each joint, and representative images of a control and an injured knee are shown. (B) A semi-quantitative scoring system was developed to assess microCT images for osteophyte formation and condyle flattening in order to determine osteoarthritis severity. (C) Tibiofemoral joints were embedded in paraffin, and 5 µm sections were obtained and stained with Safranin-O/Fast Green to assess cartilage post-surgery. (D) Cartilage damage post-surgery was quantified via the OARSI score. C57B6/J female mice were used for this study. Please click here to view a larger version of this figure.
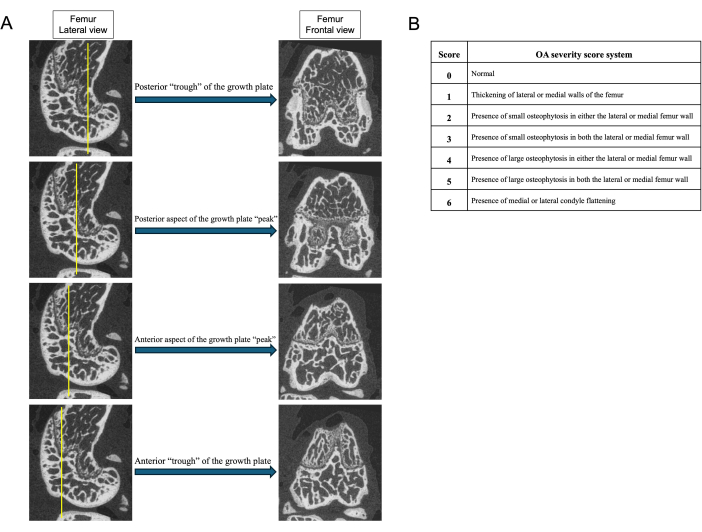
Figure 9: MicroCT evaluation. (A) MicroCT images showing the four regions of interest for scoring from posterior to anterior (i. posterior "trough" of the growth plate, ii. posterior aspect of the growth plate "peak", iii. anterior aspect of the growth plate "peak", iv. anterior "trough" of the growth plate). (B) OA severity score system. Please click here to view a larger version of this figure.
Discussion
This technique description provides a detailed surgical method for inducing ACL injuries in mice by transecting the ACL, offering a controlled model for studying PTOA. The ACLT surgical model is a widely used preclinical approach for inducing PTOA and effectively replicates key pathological features observed in human ACL injuries, including altered joint biomechanics, synovial inflammation, and cartilage degradation (Figure 7 and Figure 8)15,16,17,18,19. Additionally, the inflammatory response following ACLT is characterized by the upregulation of pro-inflammatory mediators, which accelerate extracellular matrix breakdown and cartilage damage, eventually leading to PTOA22,23,24.
Delineating the inflammatory response following ACL injury is critical for understanding osteoarthritis progression13,22. However, traditional methods for assessing inflammation, such as histology and qPCR, require tissue harvesting, a process that is often impractical in human patients. Conversely, synovial fluid analysis is a valuable tool for understanding the inflammatory response that contributes to joint degeneration. In human patients who have sustained an ACL tear, synovial fluid analysis can reveal pro-inflammatory mediators within the joint and the overall biochemical response post-injury17,25,26. Performing this analysis in murine models, however, presents significant challenges due to the small size of the mouse knee joint, which makes synovial fluid collection difficult and technically demanding. Our technique addresses this limitation by enabling synovial fluid harvesting via knee joint lavage (Figure 6). This method provides a consistent and reproducible approach to collect synovial fluid, allowing for a detailed study of inflammatory marker production over time.
Methods for evaluating PTOA severity are crucial for assessing disease progression and the effectiveness of interventions. In this regard, we developed a microCT scoring system based on common osteoarthritic findings to complement the widely used OARSI histological score (Figure 9). MicroCT imaging offers a non-invasive, high-resolution method for visualizing and quantifying structural changes in the joint, including osteophyte formation and joint deformities. Unlike traditional histological approaches, which require tissue sectioning and limit assessment to a single specific area, microCT allows for three-dimensional visualization and assessment of structural changes across multiple regions of the knee, preserving the integrity of the entire joint architecture. Our microCT scoring method focuses on key parameters, such as changes in bone morphology, osteophyte formation, and subchondral bone sclerosis, which are critical indicators of OA progression. The microCT analysis outlined above offers a method of PTOA severity quantification that is objective, reproducible, and complementary to the standard OARSI score assessment. The OARSI score focuses on damage to the cartilage and the underlying structures via histology, but does not encapsulate the entirety of the joint changes associated with PTOA. MicroCT analysis, which primarily focuses on the gross morphology of the bone, allows for a more comprehensive assessment of disease severity based on joint changes associated with PTOA in humans, such as osteophyte formation and chondral wear that are not captured by the OARSI score alone.
Although surgical models cannot entirely replicate the complex movements that cause ACL injuries in humans, they offer the benefit of controlled trauma, which can be consistently reproduced. This standardization reduces variability and potential damage to other ligaments and structures, which might occur in non-invasive models of ACL injury27. Murine models are advantageous in terms of their accessibility and feasibility, but there are many other well-established animal models of PTOA with different advantages and pitfalls. From a biomechanical standpoint, porcine models of PTOA provide the most translatability to human PTOA. Despite being quadrupedal animals, there are notable similarities in joint anatomy and knee biomechanics between pigs and humans28,29; however, the size and cost of pigs, along with their demanding husbandry, greatly limit the feasibility of porcine models. Leporine models offer a slightly larger model than a rodent, though there are also considerations to be made in terms of feasibility when working with a rabbit model30.
There are limitations to the outlined techniques. The ACLT model is well-established in translational OA/PTOA research, though it does not fully recapitulate an ACL injury and the subsequent repair and healing process in humans. The surgery is invasive, and it is important to consider the potential damage to the surrounding tissues and structures. Measuring edema via caliper also has limitations, as there is considerable subjectivity in the appropriate amount of contact and pressure to accurately capture knee width. Therefore, we suggest having multiple individuals take measurements and normalizing the knee width of the injured limb to the contralateral knee to help accommodate the natural variability. Another limitation of caliper measurements as a read-out for inflammation is that osteophytes could confound the data, a concern particularly at later times after ACLT. We suggest performing other analyses, such as microCT severity scoring, alongside the knee width measurements. The microCT analysis can be used in tandem with the OARSI score to quantify PTOA severity based on both cartilage degradation and joint morphology. A limitation to consider is the use of two-dimensional images, which cannot completely capture the entire joint, but the microCT scans can be converted into DICOM format and used for other analyses as well. For a more comprehensive analysis of the joint, the microCT score can be complemented with metrics such as osteophyte volume quantification or subchondral bone analysis.
In conclusion, the ACLT model described herein provides a reliable and reproducible approach to study the complex pathophysiology of PTOA following ACL injury. By incorporating methods to assess both the inflammatory response and structural alterations in the joint, such as synovial fluid analysis and microCT imaging, this technique description offers a comprehensive tool for investigating the mechanisms underlying ACL injury-induced OA. These methods are also invaluable for testing potential therapeutic interventions aimed at preventing or treating PTOA.
Disclosures
The authors have nothing to disclose.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 1x phosphate buffered saline (PBS) | Cytiva | SH30256.02 | |
| 4% paraformaldehyde | Fisher Scientific | AAJ19943K2 | |
| 70% Ethanol | Fisher Scientific | BP82031GAL | |
| Absorbable 6-0 sutures | Patterson Veterinary Supply | 07-893-1916 | |
| Blunt-tip forceps | Fine Science Tools | 11051-10 | |
| Cotton swabs | Fisher Scientific | 22-029-685 | |
| Dissection microscope | Leica Microsystems | M165 FC | |
| Electric razor | Braintree Scientific | CLP-9961 | |
| Ethanol wipes | Fisher Scientific | 22-246073 | |
| Ethiqa XR (Buprenorphine SR) | Covertus | 72117 | 1.3 mg/mL |
| Eye lubricant | Patterson Veterinary Supply | NC1701236 | |
| Fine scissors | Fine Science Tools | 14061-10 | |
| Heat pad | Fisher Scientific | NC1061604 | |
| Horos | Horos | horosproject.org | |
| Isoflurane | Patterson Veterinary Supply | 07-890-8115 | |
| Ketamine | Patterson Veterinary Supply | 07-890-8598 | |
| Meloxicam | Patterson Veterinary Supply | 07-893-7565 | 5 mg/mL |
| Multiplex assay | MesoScaleDiscovery | K15069M-1 | |
| Needleholder | Codman | 36-2000 | |
| No. 11 scalpel | Fine Science Tools | 10011-00 | |
| P10 pipette | Gilson | F144055M | |
| P10 pipette tips | Fisher Scientific | 02-707-439 | |
| Povidone-Iodine swabstick | Medline | MDS093901ZZ | |
| Scanco Medical µCT-35 system | Scanco | https://www.scanco.ch/systems-overview.html | 7 µm voxel size, 55 kVp, 0.145 mA, 600 ms |
| Sterile drapes | McKesson General Medical | NC2032042 | |
| Surgical face mask | Fisher Scientific | 18-048-010 | |
| Surgical gloves | Encore | 7823PF | |
| Surgical tape | Patterson Veterinary Supply | 07-888-0614 | |
| Syringes | BD | 309623 | 1 mL |
| Vannas spring scissors | World Precision Instruments | 501778 | 3 mm blades |
| Vernier capiler | Neiko | 01407A | |
| Xylazine | Patterson Veterinary Supply | 07-893-8424 |
References
- Furman, W., Marshall, J. L., Girgis, F. G. The anterior cruciate ligament: a functional analysis based on postmortem studies. J Bone Joint Surg Am. 58 (2), 179-185 (1976).
- Shimokochi, Y., Shultz, S. J. Mechanisms of noncontact anterior cruciate ligament injury. J Athl Train. 43 (4), 396-408 (2008).
- Engler, I. D., et al. Trends in anterior cruciate ligament reconstruction techniques and postoperative care among leaders in the field: a survey of the Herodicus Society. Orthop J Sports Med. 12 (10), 23259671241274770(2024).
- Amano, K., et al. Synovial fluid profile at the time of anterior cruciate ligament reconstruction and its association with cartilage matrix composition 3 years after surgery. Am J Sports Med. 46 (4), 890-899 (2018).
- Anderson, D. D., et al. Posttraumatic osteoarthritis: improved understanding and opportunities for early intervention. J Orthop Res. 29 (6), 802-809 (2011).
- MOON Group. The clinical radiographic incidence of posttraumatic osteoarthritis 10 years after anterior cruciate ligament reconstruction: data from the MOON nested cohort. Am J Sports Med. 49 (5), 1251-1261 (2021).
- Cinque, M. E., Dornan, G. J., Chahla, J., Moatshe, G., LaPrade, R. F. High rates of osteoarthritis develop after anterior cruciate ligament surgery: an analysis of 4108 patients. Am J Sports Med. 46 (8), 2011-2019 (2018).
- Nelson, F., et al. Early posttraumatic osteoarthritis-like changes in human articular cartilage following rupture of the anterior cruciate ligament. Osteoarthr Cartil. 14 (2), 114-119 (2006).
- Davidson, E. J., et al. Chondral injury associated with ACL injury: assessing progressive chondral degeneration with morphologic and quantitative MRI techniques. Sports Health. 16 (5), 722-734 (2024).
- Marks, P. H., Donaldson, M. L. C. Inflammatory cytokine profiles associated with chondral damage in the anterior cruciate ligament-deficient knee. Arthroscopy. 21 (11), 1342-1347 (2005).
- Lohmander, L. S., Atley, L. M., Pietka, T. A., Eyre, D. R. The release of crosslinked peptides from type II collagen into human synovial fluid is increased soon after joint injury and in osteoarthritis. Arthritis Rheum. 48 (11), 3130-3139 (2003).
- Palmieri-Smith, R. M., Wojtys, E. M., Potter, H. G. Early cartilage changes after anterior cruciate ligament injury: evaluation with imaging and serum biomarkers-a pilot study. Arthroscopy. 32 (7), 1309-1318 (2016).
- Leite, C. B. G., Merkely, G., Charles, J. F., Lattermann, C. From inflammation to resolution: specialized pro-resolving mediators in posttraumatic osteoarthritis. Curr Osteoporos Rep. , (2023).
- Kikuchi, N., et al. Joint effusion at 3 months after anterior cruciate ligament reconstruction is associated with reinjury. Knee Surg Sports Traumatol Arthrosc. 31 (5), 1798-1804 (2023).
- Lorenz, J., Grässel, S. Experimental osteoarthritis models in mice. Methods Mol Biol. 1194, 401-419 (2014).
- Hayami, T., et al. Characterization of articular cartilage and subchondral bone changes in the rat anterior cruciate ligament transection and meniscectomized models of osteoarthritis. Bone. 38 (2), 234-243 (2006).
- Lattermann, C., et al. Logistical challenges and design considerations for studies using acute anterior cruciate ligament injury as a potential model for early posttraumatic osteoarthritis. J Orthop Res. 35 (3), 641-650 (2017).
- Lattermann, C., et al. Biomarkers on the day of ACL reconstruction and sex predictive of knee-related quality of life at 2-year follow-up. Orthop J Sports Med. 5 (3 Suppl 3), 2325967117(2017).
- Leite, C. B. G., et al. Maresin 1-LGR6 axis mitigates inflammation and posttraumatic osteoarthritis after transection of the anterior cruciate ligament in mice. Osteoarthr Cartil. , (2025).
- Glasson, S. S., Chambers, M. G., Van Den Berg, W. B., Little, C. B. The OARSI histopathology initiative: recommendations for histological assessments of osteoarthritis in the mouse. Osteoarthr Cartil. 18 (Suppl 3), S17-S23 (2010).
- Armstrong, A. R., Carlson, C. S., Rendahl, A. K., Loeser, R. F. Optimization of histologic grading schemes in spontaneous and surgically-induced murine models of osteoarthritis. Osteoarthr Cartil. 29 (4), 536-546 (2021).
- Gilbert, S. J., et al. Inflammatory and degenerative phases resulting from anterior cruciate rupture in a non-invasive murine model of posttraumatic osteoarthritis. J Orthop Res. , (2018).
- Braza-Boïls, A., Alcaraz, M. J., Ferrándiz, M. L. Regulation of the inflammatory response by tin protoporphyrin IX in the rat anterior cruciate ligament transection model of osteoarthritis. J Orthop Res. 29 (9), 1375-1382 (2011).
- Shen, P. -C., et al. Lentiviral small hairpin RNA knockdown of macrophage inflammatory protein-1γ ameliorates experimentally induced osteoarthritis in mice. Hum Gene Ther. 24 (10), 871-882 (2013).
- Irie, K., Uchiyama, E., Iwaso, H. Intraarticular inflammatory cytokines in acute anterior cruciate ligament injured knee. Knee. 10 (1), 93-96 (2003).
- Swärd, P., Frobell, R., Englund, M., Roos, H., Struglics, A. Cartilage and bone markers and inflammatory cytokines are increased in synovial fluid in the acute phase of knee injury (hemarthrosis): a cross-sectional analysis. Osteoarthr Cartil. 20 (11), 1302-1308 (2012).
- Christiansen, B. A., et al. Non-invasive mouse models of posttraumatic osteoarthritis. Osteoarthr Cartil. 23 (10), 1627-1638 (2015).
- Proffen, B. L., McElfresh, M., Fleming, B. C., Murray, M. M. A comparative anatomical study of the human knee and six animal species. Knee. 19 (4), 493-499 (2012).
- Chu, C. R., Szczodry, M., Bruno, S. Animal models for cartilage regeneration and repair. Tissue Eng Part B Rev. 16 (1), 105-115 (2010).
- Huang, L., et al. Early changes in osteochondral tissues in a rabbit model of posttraumatic osteoarthritis. J Orthop Res. 39 (12), 2556-2567 (2021).
Reprints and Permissions
