The continuous infusion of angiotensin II (Ang II) via osmotic pumps is one of the classic methods for constructing animal models of hypertensive myocardial fibrosis. This protocol systematically optimized the process of constructing this model and elaborated the key points of osmotic pump implantation, positioning, and Ang II concentration setting.
Method Article
A Protocol for Constructing a Mouse Model of Hypertensive Myocardial Fibrosis Using Angiotensin II
* These authors contributed equally
In This Article
Summary
Abstract
The continuous infusion of Angiotensin II (Ang II) via osmotic pumps is a widely utilized approach for establishing animal models of hypertensive myocardial fibrosis. Nevertheless, this technique exhibits certain limitations in current reports, such as the instability of Ang II, inaccurate pump placement, and the lack of a standardized procedure. Current reports on the methodology for establishment remain relatively limited. This protocol has systematically optimized the establishment of Ang II osmotic pump-induced hypertensive myocardial fibrosis models in mice, including the standardized preparation of Ang II solution, calibration of dosage, precise subcutaneous implantation of osmotic pumps, and quantitative standards for model evaluation indicators. Experimental results demonstrated that Ang II osmotic pump-induced hypertensive myocardial fibrosis in mice with high survival rates. Systolic blood pressure (SBP) levels stabilized at 160 mmHg after seven days of subcutaneous implantation. The model mice had significantly reduced left ventricular ejection fractions and increased end-diastolic dimensions of the left ventricle. Compared with the sham surgery group, collagen deposition within hypertensive myocardial interstitial tissue and perivascular regions increased. This study, based on a small sample size (n = 6), preliminarily validated the feasibility of establishing a mouse model of hypertensive myocardial fibrosis using Ang II combined with an osmotic pump, and established a quantitative phenotype verification system.
Introduction
Myocardial fibrosis (MF), a major pathological outcome of hypertension, is characterized by excessive collagen fiber deposition within the damaged or compressed myocardium. It represents one of the most important forms of hypertension-mediated target organ damage and contributes to progressive cardiac dysfunction1,2. Establishing appropriate animal models is essential for advancing mechanistic research and developing novel therapeutic strategies for hypertensive myocardial fibrosis. Angiotensin II (Ang II), a central effector of the renin-angiotensin system, plays a pivotal role in hypertension pathogenesis3. Ang II-based induction has therefore become a widely used approach for establishing hypertension models in mice.
Current methods for constructing hypertension animal models primarily include surgical induction, pharmacological induction, and transgenic spontaneous models. Surgical induction typically uses techniques such as renal artery constriction, ascending aortic constriction, or aortic arch constriction to artificially increase blood flow resistance, thereby inducing elevated blood pressure4. While these methods can rapidly establish hypertension states suitable for studying stress load-related cardiac remodeling processes, they involve complex procedures with numerous postoperative complications. Pharmacological induction generally utilizes intraperitoneal injection or oral administration to elevate blood pressure in experimental animals5. While the technology is relatively straightforward, model stability remains susceptible to interference from drug dosage, administration frequency, and animal stress responses. Transgenic models such as spontaneously hypertensive rats and BPH/2J hypertensive mice, which exhibit stable hypertension phenotypes, are widely used in hereditary hypertension research. However, their singular pathogenic mechanisms limit their capacity to simulate multi-factor-induced clinical hypertension.
More recently, hypertension models based on continuous Ang II infusion via subcutaneous osmotic pumps have gained popularity. This method enables sustained release of Ang II at a constant rate, maintaining stable blood concentrations over extended periods to closely mimic pathological processes and replicate mouse hypertensive myocardial fibrosis6,7,8. Nonetheless, important limitations remain, particularly regarding the standardization of the protocol and inconsistent fibrotic outcomes, which can be influenced by factors such as pump implantation technique and animal-specific responses9. To address these gaps, this study refines the Ang II osmotic pump-based model, standardizes key steps, and provides a visualized protocol. These improvements enhance reproducibility and practical applicability, offering a valuable reference for future studies on hypertensive myocardial fibrosis.
Protocol
All experimental procedures were carried out according to the Guidelines for the Care and Use of Laboratory Animals of the National Institutes of Health, and the experimental protocols were approved by the Animal Research Committee of Southwest Medical University (approval number SWMU2020317).
1. Preparation of Ang II solution and filling of the osmotic pump
- Select 12 SPF-grade male C57BL/6J mice (see Table of Materials) weighing 20 ± 1 g by selecting 8-week-old animals for their developmental uniformity to control for age-related confounders. Divide the mice into a sham surgery group and a model group using a simple randomization method, with 6 mice in each group.
- Measure the initial body weight of the mouse and determine the dose of Ang II (see Table of Materials) as 1.46 mg/kg/d.
NOTE: According to the preliminary experiment, 1.46 mg/kg/d is the optimal dose of Ang II. This dose reliably maintains systolic blood pressure at approximately 160 mmHg, effectively inducing pathological myocardial fibrosis while ensuring animal survival throughout the 4-week study. - Add 2.45 mL of 0.9% sterile saline, pre-cooled to 4 °C, to 10 mg of Ang II lyophilized powder. Mix the solution thoroughly and keep it on ice for immediate use.
- Perform the procedure on ice by using a syringe to draw Ang II solution, then sequentially inject 200 µL (3.91 mmol/L concentration) into each of the six osmotic pump (see Table of Materials) chambers.
- Activate the osmotic pressure drive by immersing the pump in 37 °C sterile saline for 48 h.
NOTE: Fill the osmotic pumps for the sham surgery group with an equal volume of saline. As Ang II is photosensitive, the procedure must be conducted under complete light protection throughout.
2. Implantation of the osmotic pumps and construction of model 6
- Animal preparation and anesthesia
- Fast the mice for 4 h with free access to water. Then, weigh each mouse and calculate the appropriate anesthetic dose (80 mg/kg pentobarbital sodium)10.
- Anesthetize the mice via intraperitoneal injection of the calculated dose of pentobarbital sodium.
NOTE: Handling pentobarbital requires compliance with regulations, operation in a fume hood, wearing protective equipment, and labeling residual liquid for separate disposal.
- Remove the hair from the dorsal skin over the region extending from the tail base to the mid-dorsal area using a razor or depilatory cream.
- Thoroughly disinfect the shaved area three times with 70% ethanol11.
- Using a scalpel, make a 0.5 cm subcutaneous incision within the disinfected area.
- Through the incision, use forceps to bluntly separate the subcutaneous tissue towards the posterior neck, creating a pocket.
- Orient the pump body with its catheter tip pointing toward the mouse's head. Then, clamp the tip with hemostatic forceps and insert the pump subcutaneously in that direction.
- Following the pump implantation, suture the subcutaneous tissue with interrupted 6-0 absorbable sutures and close the skin incision with surgical sutures. Then, place the mouse in a preheated 37 °C thermal mat until it fully recovers from anesthesia (approximately 5-10 min).
- Continuously infuse the prepared Ang II solution at the predetermined dose (1.46 mg/kg/d) via the osmotic pumps for 28 days.
- Upon completion of the 28-day infusion period, collect all experimental data. Then, anesthetize the mice in the same manner as done for previous anesthetizations, that is following the procedures described in steps 2.1.1-2.1.2, and euthanize them by cervical dislocation.
3. Blood pressure measurement
- Equipment (see Table of Materials) preheating: Set the heating platform to 37-38 °C to ensure vasodilation in the mouse tail blood vessels.
- Gently grasp the mouse and place it in the restraint holder, ensuring the tail protrudes freely through the rear hole. Then, thoroughly clean the exposed tail with an alcohol-sopped cotton ball.
- Place an inflatable cuff at the base of the tail. Position the pulse sensor approximately 5-10 mm distal to the cuff on the mid-to-lower tail section.
- Activate the device and wait for the pulse waveform to stabilize before proceeding.
- Initiate the measurement cycle. The system will automatically inflate the cuff to a pressure exceeding 200 mmHg to occlude blood flow, then deflate slowly at 2-3 mmHg per s. The sensor detects the pulse wave reappearance as flow resumes, determining the systolic pressure.
- Measure the systolic blood pressure (SBP) at 7-day intervals after modeling, for a total of five measurements. For each mouse at every time point, record three sequential readings, allowing a 2 min rest period between consecutive measurements.
- After measurements, return the mouse to its cage with food and water. Clean the holder and tail sleeve to prevent cross-contamination.
4. Cardiac function measurement
- On day 28 of modeling, anesthetize all experimental mice with sodium pentobarbital (80 mg/kg pentobarbital sodium).
- Position the mouse in supine position on a constant-temperature platform.
- Perform transthoracic echocardiography using an ultrasound system (see Table of Materials). Connect the limbs of the mouse to electrodes on the platform to monitor electrocardiogram (ECG) signals.
- Obtain short-axis imaging at the level of the mammary muscle via M-mode ultrasound to visualize the heart and analyze cardiac function. Capture three images per mouse and average the data for subsequent analysis of left ventricular internal diastolic dimension (LVIDd), left ventricular internal diameter systolic (LVIDs), left ventricular fractional shortening (LVFS), and left ventricular ejection fraction (LVEF).
NOTE: Maintain probe contact with the chest wall without compressing the thoracic cavity; ensure M-mode sampling line perpendicular to the ventricular septum; perform continuous measurements for ≥ 3 cardiac cycles to obtain mean values.
5. Masson staining
- Cardiac sampling and fixation
- Anesthetize the mouse with sodium pentobarbital (80 mg/kg pentobarbital sodium). Then, make a longitudinal incision of approximately 1.5 cm in the thoracic cavity using scissors, ligate the major cardiac vessels, and rapidly excise the heart to avoid traction injury12.
- Immediately rinse the excised heart with pre-cooled PBS to remove blood and gently blot away excess moisture using clean filter paper. Subsequently, perform a transverse section along the papillary muscle to obtain a 3 mm-thick tissue slice.
- For fixation, immerse the heart samples in 4% paraformaldehyde for over 48 h, ensuring a minimum tissue-to-fixative volume ratio of 1:10.
- Remove the heart tissue from the 4% paraformaldehyde fixative. Then, under a fume hood, thinly slice the tissue at a thickness of 4 µm with a surgical knife and transfer the slices to a dehydration cassette13.
- Load tissue sections into dehydrator and perform the following steps: 70% ethanol, 80% ethanol, 95% ethanol for 1 h each; 100% ethanol I & II for 45 min each; xylene I & II for 30 min each.
- Embed the tissue in paraffin, and then solidify the blocks on a pre-cooled -20 °C cold plate.
- Use a paraffin microtome to obtain 4 µm-thick longitudinal sections from the paraffin-embedded tissue blocks. Then, sequentially immerse the sections in the following solutions for 5 min each to deparaffinize and rehydrate them: xylene I, xylene II, absolute ethanol, 95% ethanol, 80% ethanol, 70% ethanol, and finally distilled water.
- Immerse the tissue in the prepared Weigert's iron hematoxylin staining solution for 8 min. Then, rinse repeatedly with distilled water to remove excess staining solution. Differentiate in acidic ethanol differentiation solution for 5 s, followed by bluing in Masson's bluing solution for 5 min. Finally, rinse with distilled water14.
- Stain the sections with carmine red for 10 min, applying approximately 200-300 µL per slide to ensure complete and uniform coverage of the tissue. Then, rinse the sections in 0.2% glacial acetic acid for 1 min.
- Treat the sections with phosphomolybdic acid solution for approximately 5 min, or until the muscle fibers turn red. Then, stain the sections with a sufficient volume of aniline blue solution to cover the tissue completely (typically 200-300 µL per slide) for 5 min. Finally, rinse the sections with 0.2% glacial acetic acid solution15.
- Dehydrate the sections through a graded ethanol series. Proceed to clear the tissues with xylene using three immersions of 1-2 min each.
- Mount the sections by applying a small amount of neutral resin and covering with a coverslip.
- Microscopic (see Table of Materials) examination: Observe Masson-stained tissues at 40×, 20×, and 10× magnification. Photograph each slide to preserve representative images.
NOTE: Dispose of all waste in accordance with institutional safety protocols. Collect acidic differentiation solution and glacial acetic acid in corrosion-resistant barrels, neutralize high-concentration waste to pH 6-8, and do not mix with alkaline solutions. Store ethanol in explosion-proof barrels in a cool place, away from fire sources. Hold xylene in brown barrels, operate in a fume hood with protective equipment worn, and do not mix acids (substances) with ethanol. Place animal tissues into labeled containers, seal them, and store them under freezing conditions16. Finally, transfer all waste to qualified professional institutions for disposal; strictly prohibit mixing waste or disposing of it casually.
6. Statistical analysis
- Collect all numerical data and analyze using GraphPad Prism 9.0.
- Use the independent sample t-test to analyze the differences between groups.
- Set statistical significance as **P < 0.01 for highly significant and *P < 0.05 for significant.
Results
Twelve mice were implanted subcutaneously with osmotic pumps and survived. Model group all developed hypertension (n = 6). Seven days post-implantation, the mean SBP in the model group exceeded 160 mmHg (Figure 1A). On days 14, 21, and 28, the SBP in the model group consistently remained above 160 mmHg. In contrast, the sham surgery group maintained normal SBP levels (approximately 90-110 mmHg) throughout the experiment without significant elevation.
Twenty-eight days following the implantation of the osmotic pump, echocardiography indicated that, in comparison to the sham surgery group, the model group exhibited ventricular wall thinning, compensatory thickening of the posterior wall, and reduced anterior wall motion (Figure 1B). A significant decrease in LVEF and LVFS was observed (P < 0.01), while LVIDd and LVIDs showed significant increases (P < 0.01) (Figures 1C-F). The findings suggest that the model group of mice experienced changes in cardiac structure, evidenced by left ventricular hypertrophy and compromised cardiac function. Conversely, the sham surgery group mice retained normal ventricular dimensions (LVIDd, LVIDs), wall thickness, and cardiac function parameters (LVEF, LVFS), exhibiting no such abnormal changes.
The pathological alterations in the MF are closely linked to collagen deposition and inflammatory factor expression within the myocardial tissue17,18. Masson staining of mouse myocardium post day 28 revealed (Figure 1G) that the sham surgery group exhibited no significant blue-stained collagen fibers, while the model group showed a marked increase in network-like collagen fiber staining within the myocardial interstitium and perivascular regions. The proportion of atrial fibrotic area was significantly higher in the Ang II model group compared with the sham group (P < 0.01). These findings provide preliminary validation that the Ang II osmotic pump can induce myocardial interstitial and perivascular fibrosis, although the small sample size and potential variability should be taken into account.
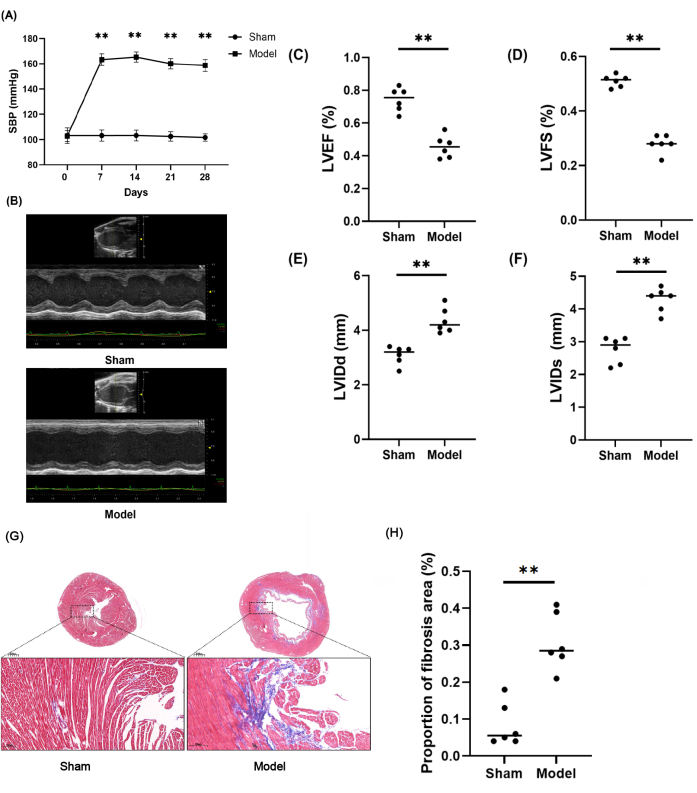
Figure 1: The comparison of Sham and Model Groups in Ang II-Induced Hypertensive MF Mouse Models. (A) Mean systolic blood pressure (SBP) measurements. (B) M-mode echocardiography images are shown. Echocardiographic measurements of cardiac functional parameters are as follows: (C) Left ventricular ejection fraction (LVEF, %); (D) Left ventricular fractional shortening (LVFS, %); (E) Left ventricular end-diastolic diameter (LVIDd, mm); (F) Left ventricular internal diameter systolic (LVIDs, mm). (G) Ventricular fibrosis was evaluated by staining fibroblasts with Masson trichrome. Scale bars: 625 µm; 1000 µm. (H) To assess ventricular fibrosis, the fibrotic area was measured and expressed as a percentage of the total area. All data are presented as mean ± SD (n=6 for each group). **P < 0.01. Please click here to view a larger version of this figure.
Discussion
This protocol optimized the key steps involved in the continuous infusion of Ang II to induce hypertensive myocardial fibrosis using an osmotic pump and detailed the critical aspects, such as the implantation positioning of the osmotic pump and the setting of Ang II concentration. The model 2004 pump was chosen for its 4-week duration, and the Ang II dose was calculated based on the nominal infusion rate, accounting for minimal inter-batch variability. The efficacy of this model was confirmed through SBP monitoring, cardiac color Doppler ultrasound, and Masson staining. In this protocol, 8-week-old male C57BL/6J mice were used to ensure uniformity in the developmental stage of the experimental subjects, thereby minimizing the confounding effects of age on the experimental outcomes19.
On the 7th day after implantation of the Ang II-loaded osmotic pump, mice in the model group exhibited a significant increase in SBP, which subsequently remained at 160 mmHg and was maintained around this level for three consecutive weeks. This dynamic response aligns with the biphasic pressor mechanism of Ang II: The acute phase (within 1 week) is primarily driven by Ang II directly activating vascular smooth muscle AT1 receptors, inducing intense vasoconstriction and rapid aldosterone release; the chronic phase (2-4 weeks) involves vascular remodeling, myocardial hypertrophy, and sympathetic nerve activation caused by sustained Ang II exposure, reflecting its neurohumoral regulatory properties20,21. These findings align with previously reported blood pressure trends in Ang II infusion models; however, our protocol led to an earlier attainment of the target hypertensive blood pressure than most similar studies, which typically require 10-14 days. This likely results from its targeted release mechanism and optimized Ang II dosage22. Compared with the dorsal approach, neck implantation mitigates the risk of pump dislodgement due to scratches by mice. The Ang II-infused model consistently maintained SBP at approximately 160 mmHg in mice, which ensured animal survival while simultaneously inducing myocardial fibrosis through a sustained, low-grade pathological stimulus, thereby more closely recapitulating the pathological process of human hypertensive myocardial fibrosis11. On day 28, the model group exhibited a significant reduction in LVEF accompanied by left ventricular dilation, a characteristic that is synergistically driven by the dual pathological effects mediated by Ang II: Ang II can directly activate the TGF-β1/Smad3 pathway, driving the pathological remodeling of cardiomyocytes; Hypertension, serving as the initial pathogenic trigger in this pathological process, amplifies the adverse outcomes by increasing cardiac afterload. As the primary pumping chamber of the heart, the left ventricle is subjected to a substantially higher systemic pressure load than the right ventricle. This markedly and persistently elevated mechanical stress further activates the TGF-β pathway in both cardiomyocytes and fibroblasts. Collectively, these two pathways promote the aberrant synthesis and deposition of collagen fibers, which disrupts the normal architecture of cardiomyocytes and the myocardial interstitium, impairs the coordination of myocardial relaxation and contraction, and ultimately culminates in adverse cardiac remodeling23,24. Masson staining of cardiac tissue revealed characteristic perivascular collagen deposition. Ang II induced hypertensive myocardial fibrosis manifested as diffuse interstitial fibrosis, characterized by thickened collagen fiber bundles predominantly deposited in interstitial regions and perivascular areas, small collagen fiber pockets (in the Endocardium) surrounding myocardial cells, and collagen fiber bundles around myocardial cell bundles (in the Epicardium). Subendocardial and subepicardial collagen deposition can hinder the transmission of force generated by myocardial cells to the left ventricular cavity, thereby adversely affecting myocardial contractility25,26. Compared to previous modeling protocols utilizing a combination of Ang II and phenylephrine (PE), the fibrosis level induced by Ang II alone in the present protocol was markedly lower. In contrast, the Ang II+PE model, due to its overactivation of the αV integrin pathway, often exhibited a substantially higher extent of fibrosis, which exceeds the range commonly observed in clinical hypertensive patients. Thus, the current approach circumvents the discrepancy between the pathological features of the model and clinical reality that is induced by combination drug administration27,28.
In summary, this protocol successfully established a hypertensive myocardial fibrosis model by continuously infusing Ang II via an osmotic pump, providing a standardized approach with broad applicability for studying the pathogenesis of hypertension-related myocardial fibrosis. It should be noted, however, that potential variability associated with tail-cuff plethysmography, the unblinded nature of assessments, and the small sample size used in this protocol may collectively introduce bias that affects study outcomes. Additionally, the findings are derived solely from male mice, which may limit their generalizability across sexes. While demonstrating robust myocardial fibrosis induction in young male C57BL/6J mice, its efficacy in aged, female, or genetically modified strains requires further validation. Additionally, this protocol shows potential for investigating hypertension-induced renal fibrosis, though its applicability to other hypertensive organ fibrotic disorders remains to be explored29,30.
Disclosures
All authors declare that this manuscript has no conflicts of interest.
Acknowledgements
This work was supported by the National Natural Science Foundation of China (82074378), the Project of Science & Technology Department of Sichuan Province (2022YFS0618), Project of Office of Science & Technology and talent work of Luzhou (2023JYJ029), 2024 Traditional Chinese Medicine Guangdong Provincial Laboratory Project (HQCML-C-2024005), Shenzhen Science and Technology Program (JCYJ20230807094603007, JCYJ20240813152440051), Shenzhen Medical Research Fund (A2403028), Sichuan Medical Association Project (Q2025014) and the Project of Southwest Medical University (2024ZKZ007, 2024ZKY073, 2023ZYYQ04). The funder had no role in the study design, data analysis, or decision to publish.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Ang II | Sigma-Aldrich Corporation | Sigma, A9525 | |
| Animal anesthesia machine | Shenzhen Reward Life Science Co., Ltd | R530 | |
| Animal ventilator | Shenzhen Reward Life Science Co., Ltd | R415 | |
| GraphPad Prism | GraphPad Software Inc. | Version 9.0 | |
| Intelligent non-invasive blood pressure monitor | Nippon Soft Dragon Co., Ltd | Softron, BP-98A | |
| Light microscope | Yijingtong Optical Technology (Shanghai) Co., Ltd | OLYMPUS, SZ61TR | |
| Masson Tricolor Staining Solution and Kit | Beijing Soleibao Technology Co., Ltd | Solarbio, G1340 | |
| Mice | Chengdu Dossy Exprimental Animals CO., Ltd | C57BL/6J | |
| Osmotic pumps | ALZA Corporation | Alzet,Model 2004 | |
| Ultrasound imaging systems | FUJIFILM VisualSonics Corporation, Canada | FUJIFILM, Vevo 3100 |
References
- Zhao, D., Liu, J., Wang, M., Zhang, X., Zhou, M. Epidemiology of cardiovascular disease in China: current features and implications. Nat Rev Cardiol. 16 (4), 203-212 (2019).
- Czubryt, M. P., Hale, T. M. Cardiac fibrosis: pathobiology and therapeutic targets. Cell Signal. 85, 110066(2021).
- Young, C. N., Davisson, R. L. Angiotensin-II, the brain, and hypertension: an update. Hypertension. 66 (5), 920-926 (2015).
- Goldblatt, H., Lynch, J., Hanzal, R. F., Summerville, W. W. Studies on experimental hypertension: I. the production of persistent elevation of systolic blood pressure by means of renal ischemia. J Exp Med. 59 (3), 347-379 (1934).
- Mezzano, S. A., Ruiz-Ortega, M., Egido, J. Angiotensin II and renal fibrosis. Hypertension. 38 (3), 635-638 (2001).
- Liu, Q., et al. Zhilong Huoxue Tongyu capsule inhibits hypertensive myocardial fibrosis via balancing TGF-β1/Smad3/Erbb4-IR/miR-29b pathway. Sci Rep. 15 (1), 25127(2025).
- Han, Y. J., Hu, W. Y., Piano, M., De Lanerolle, P. Regulation of myosin light chain kinase expression by angiotensin II in hypertension. Am J Hypertens. 21 (8), 860-865 (2008).
- Dikalova, A., et al. Nox1 overexpression potentiates angiotensin II-induced hypertension and vascular smooth muscle hypertrophy in transgenic mice. Circulation. 112 (17), 2668-2676 (2005).
- Zheng, H. Q., et al. Induction of thoracic aortic dissection: a mini-review of β-aminopropionitrile-related mouse models. J Zhejiang Univ Sci B. 21 (8), 603-610 (2020).
- Taiji, S., et al. Changes in breathing pattern during severe hypothermia and autoresuscitation from hypothermic respiratory arrest in anesthetized mice. Physiol Rep. 9 (23), e15139(2021).
- Lu, H., et al. Subcutaneous angiotensin II infusion using osmotic pumps induces aortic aneurysms in mice. J Vis Exp. (103), e53191(2015).
- Gao, E., et al. A novel and efficient model of coronary artery ligation and myocardial infarction in the mouse. Circ Res. 107 (12), 1445-1453 (2010).
- Liu, M., et al. Zhilong Huoxue Tongyu capsule inhibits rabbit model of hyperlipidemia and atherosclerosis through NF-κB/NLRP3 signaling pathway. Heliyon. 9 (11), e20026(2023).
- Foot, N. C. The Masson trichrome staining methods in routine laboratory use. Stain Technol. 8 (3), 101-110 (1933).
- Van De Vlekkert, D., Machado, E., D'azzo, A. Analysis of generalized fibrosis in mouse tissue sections with Masson's trichrome staining. Bio Protoc. 10 (10), e3629(2020).
- Bansod, H. S., Deshmukh, P. Biomedical waste management and its importance: a systematic review. Cureus. 15 (2), e34589(2023).
- Li, X., et al. Epigenetics-based therapeutics for myocardial fibrosis. Life Sci. 271, 119186(2021).
- Villalobos, E., et al. Fibroblast primary cilia are required for cardiac fibrosis. Circulation. 139 (20), 2342-2357 (2019).
- Percie Du Sert, N., et al. The ARRIVE guidelines 2.0: updated guidelines for reporting animal research. Br J Pharmacol. 177 (16), 3617-3624 (2020).
- Kawada, N., et al. A mouse model of angiotensin II slow pressor response: role of oxidative stress. J Am Soc Nephrol. 13 (12), 2860-2868 (2002).
- Tamplin, M. R., et al. Longitudinal testing of retinal blood flow in a mouse model of hypertension by laser speckle flowgraphy. Transl Vis Sci Technol. 10 (2), 16(2021).
- Lever, A. F., Lyall, F., Morton, J. J., Folkow, B. Angiotensin II, vascular structure and blood pressure. Kidney Int Suppl. 37, S51-S55 (1992).
- Kuwahara, F., et al. Hypertensive myocardial fibrosis and diastolic dysfunction: another model of inflammation. Hypertension. 43 (4), 739-745 (2004).
- Schultz, J. E. L., et al. TGF-β1 mediates the hypertrophic cardiomyocyte growth induced by angiotensin II. J Clin Invest. 109 (6), 787-796 (2002).
- Ye, S., et al. Celastrol attenuates angiotensin II-induced cardiac remodeling by targeting STAT3. Circ Res. 126 (8), 1007-1023 (2020).
- González, A., et al. Myocardial interstitial fibrosis in hypertensive heart disease: from mechanisms to clinical management. Hypertension. 81 (2), 218-228 (2024).
- Ock, S., et al. IGF-1 protects against angiotensin II-induced cardiac fibrosis by targeting αSMA. Cell Death Dis. 12 (7), 688(2021).
- Li, R., Frangogiannis, N. G. Integrins in cardiac fibrosis. J Mol Cell Cardiol. 172, 1-13 (2022).
- Wang, M. Y., et al. OTUD1 promotes hypertensive kidney fibrosis and injury by deubiquitinating CDK9 in renal epithelial cells. Acta Pharmacol Sin. 45 (4), 765-776 (2024).
- Ravanetti, F., et al. Modeling pulmonary fibrosis through bleomycin delivered by osmotic minipump: a new histomorphometric method of evaluation. Am J Physiol Lung Cell Mol Physiol. 318 (2), L376-L385 (2020).
Reprints and Permissions
This article has been published
Video Coming Soon