Systematic review and meta-analysis of randomized trials evaluating non-pharmacological behavior guidance to reduce dental anxiety and improve cooperation in autistic children. Virtual reality and sensory-adapted environments show promise, but evidence remains limited.
Research Article
Non-pharmacological Behavior Guidance Techniques on Dental Anxiety And Cooperation in Children With Autism: A Systematic Review and Meta-analysis
In This Article
Summary
Abstract
Behavior guidance is recommended as a core component of pediatric dentistry, yet the effectiveness of specific non-pharmacological techniques for autistic patients has not been systematically quantified. The researchers systematically searched PubMed, Embase, Web of Science, Cochrane Library, Scopus, APA PsycInfo, CINAHL, and AMED for randomized controlled trials of non-pharmacological behavior guidance techniques in autistic children undergoing dental procedures. Eligible studies enrolled children with a clinical diagnosis of autism spectrum disorder and compared a structured behavior guidance strategy with routine behavior management or another guidance technique, and reported anxiety and/or cooperation outcomes using validated measures. Electronic searches identified 1,242 records; after deduplication, 487 titles and abstracts were screened, 9 full texts were assessed, and 5 trials (n = 445; sample size 19–162) were included. All were conducted in specialist pediatric dental services and focused on non- or minimally invasive procedures, including examination, prophylaxis, and fluoride application. Interventions comprised a multisensory sensory-adapted dental environment, visual pedagogy, electronic media–based guidance (video modeling and video goggles), and immersive virtual reality. Owing to heterogeneity, quantitative synthesis was feasible for only two VR trials that reported Frankl Behavior Rating Scale scores. In the larger parallel-group RCT, VR improved cooperation versus conventional care (mean difference [MD] 0.55, 95% CI 0.23–0.88); the smaller crossover study showed a similar direction (MD 0.39, 95% CI −0.35 to 1.13). Pooled in a fixed-effect model, VR was associated with a moderate improvement of about half a Frankl point (pooled MD 0.52, 95% CI 0.22–0.82). Non-pharmacological behavior guidance techniques may improve clinically relevant outcomes in autistic children during routine dental care. However, pooled quantitative evidence in the present review was available only for virtual reality–related improvements in cooperation, whereas evidence for other techniques, including sensory-adapted environments, remained limited and was based primarily on narrative synthesis.
Introduction
Behavior guidance is commonly conceptualized as a structured process of communication between the dental team, the child, and the parent that aims to alleviate fear and anxiety, foster trust and positive attitudes towards oral health, and permit safe and efficient treatment under the least restrictive conditions1,2, foster trust and positive attitudes towards oral health, and permit safe and efficient treatment under the least restrictive conditions. Within this framework, non-pharmacological techniques such as communication guidance, positive pre-visit imagery, direct observation, tell–show–do, ask–tell–ask, non-verbal communication, positive reinforcement, distraction, and desensitization are recommended before recourse to more restrictive measures, including protective stabilization, sedation, or general anesthesia3,4. Emerging evidence from studies in typically developing children indicates that these strategies can lower self-reported dental anxiety, reduce behavioral distress, and attenuate physiological indices of arousal, thereby supporting an individualized approach in which combinations of sensory, cognitive, and communicative methods are tailored to each child’s needs5. However, the applicability of this evidence to children with special health-care needs remains uncertain.
Autism spectrum disorder (ASD) is a neurodevelopmental condition that is characterized by difficulties in social communication and interaction, restricted and repetitive patterns of behavior, and atypical sensory processing6,7. Given the hypersensitivity to sound, light, touch, and changes in routine8, the dental environment often becomes a major source of stress9. Meanwhile, dental visits frequently trigger marked anxiety and behavioral dysregulation that may manifest as crying, escape attempts, aggression, or self-injury, thereby substantially complicating the delivery of care10,11. In response to these challenges, behavior guidance strategies have been specifically adapted for dental care in children with autism12. For example, sensory-adapted dental environments (SADEs) in which lighting, sounds, and tactile stimuli are carefully modified, video modeling that allows the child to observe dental procedures in advance, graduated exposure and desensitization protocols that introduce dental stimuli in small steps, and visual supports such as picture schedules and social stories that clarify expectations and routines have been developed for children with autism13,14.
These approaches may offer distinct practical advantages over conventional verbal behavior guidance techniques. SADEs may be particularly useful for children whose distress is driven primarily by sensory over-responsivity15, because they reduce aversive environmental input without relying heavily on verbal comprehension or social reciprocity13,14. Visual pedagogy and social-story–based approaches may be especially helpful before the visit or across repeated preventive visits because they can improve predictability, rehearse routines, and be delivered at home with caregiver involvement. Electronic media strategies and virtual reality (VR) may provide chairside distraction and sensory shielding during short, non-invasive procedures, particularly for children who tolerate audiovisual devices and respond well to visual input16. These differences are clinically relevant because they suggest that no single technique is likely to be optimal for all autistic children, and that selection of a behavior guidance strategy should depend on the child’s sensory profile, communication abilities, treatment type, and the practical resources of the dental setting.
Although early studies suggest that these approaches can reduce observable distress, improve cooperation, and, in some cases, lower anxiety ratings during examinations, prophylaxis, and preventive procedures such as fluoride application4,17,18, most available studies have been small and heterogeneous, often using nonrandomized designs, varying outcome measures, and different combinations of techniques. which prevents quantification of the overall effects of these interventions and precludes meaningful comparison of the relative effectiveness of different behavior guidance techniques in this population. This has limited the ability to quantify their overall effects and to compare the relative effectiveness of different behavior guidance approaches in autistic children. Therefore, this systematic review aimed to evaluate randomized controlled trials of non-pharmacological behavior guidance techniques for children with autism undergoing dental procedures, with a focus on clinically relevant outcomes including anxiety-related measures, observable distress, and cooperation.
Protocol
Registration
This meta-analysis was conducted in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA)19. The protocol was prospectively registered in PROSPERO, the International Prospective Register of Systematic Reviews (registration number: CRD420261368386).
Study design
In this meta-analysis, the primary objective was to determine the effects of non-pharmacological behavior guidance techniques on dental anxiety in children with autism undergoing dental procedures. Within this framework, the population was defined as children diagnosed with autism spectrum disorder who received dental care in clinical dental settings. Interventions were defined as structured, non-pharmacological behavior guidance strategies specifically intended to facilitate dental treatment, including sensory-adapted dental environments, video modeling, graduated exposure and desensitization, communication-based techniques, and visual supports. Comparators comprised routine care. The primary Outcomes of interest were the improvement in anxiety-related measures assessed using validated scales, whereas secondary outcomes included behavioral and cooperation ratings, treatment completion, use of restrictive pharmacological or physical measures, and adverse events.
Literature search
The researchers conducted a systematic search of PubMed, Embase, Web of Science, the Cochrane Library, Scopus, APA PsycInfo, CINAHL, and AMED for English-language articles from database inception to 1 December 2025. The search strategy combined controlled vocabulary (eg, MeSH and Emtree terms) with free-text terms related to children and adolescents, dentistry and dental care, behavior guidance techniques, and anxiety. To maximize sensitivity and reduce the risk of missing potentially relevant trials that may not have been indexed consistently under autism-related terms, autism-specific terms were not used as mandatory search filters; eligibility of studies involving autistic children was instead determined during screening. The full search strategies for each database are provided in the Supplementary Material. To enhance the completeness of the evidence base, the researchers also screened the reference lists of relevant systematic reviews, all included studies, and searched ClinicalTrials.gov for registered randomized controlled trials, including completed but unpublished and ongoing trials.
Eligibility criteria
Studies were eligible for inclusion if they met all of the following criteria: (1) participants were children or adolescents with a clinical diagnosis of autism spectrum disorder receiving dental examination, prophylaxis, or treatment in a clinical dental setting; (2) the intervention consisted of a structured non-pharmacological behavior guidance technique intended to facilitate dental care, such as sensory-adapted dental environments, video modelling, video goggles, graduated exposure and desensitization, communication-based techniques, distraction, positive reinforcement, or visual supports; (3) the comparator was routine behavior management or an alternative behavior guidance strategy without the specific experimental technique under evaluation; (4) the study used a randomized controlled design, including individually randomized, split-mouth, cluster-randomized, or crossover trials; and (5) the study reported at least one clinically relevant outcome, including anxiety-related measures, observable distress, cooperation, treatment completion, or the use of restrictive pharmacological or physical measures.
Studies were excluded if they were animal or in vitro studies, case reports, case series, study protocols, reviews, letters, editorials, conference abstracts, or qualitative studies; if they did not involve autistic children or were not conducted in a dental or oral health care setting; if key outcome data were unavailable or insufficient for effect size calculation even after attempts to contact the authors; or if they were duplicate publications or full texts could not be obtained.
Data extraction
Endnote X9.1 (Clarivate Analytics) literature management software was utilized to organize the records from the literature search. For data extraction, two reviewers independently used a predesigned Excel 2016 (Microsoft Corp., Redmond, WA, USA) spreadsheet to collect information from all studies that met the inclusion criteria. Extracted data included the first author, year of publication, country, study design, setting, sample size, and characteristics of participants (age, sex, diagnostic criteria for autism spectrum disorder, severity or functional level where reported, and relevant comorbidities). Details of the dental procedures (eg, examination, prophylaxis, fluoride application, restorative or other operative treatment) were recorded, together with a description of the intervention and control conditions, including the type of behavior guidance technique, its components, timing, duration, and the personnel delivering it. Outcome-related data included the type and timing of anxiety measures, the specific scales used (eg, validated dental anxiety instruments or observational scales), behavioral or cooperation ratings, treatment completion or interruption, use of rescue sedation, general anesthesia or protective stabilization, and any reported adverse events. Where necessary, numerical data for continuous outcomes (means, standard deviations, and sample sizes) and dichotomous outcomes (number of events and total participants per group) were extracted or derived from text, tables, or figures.
To ensure consistency across trials, all non-pharmacological interventions and control conditions were classified into predefined categories of behavior guidance techniques. Two reviewers independently assigned each study arm to one or more categories, and any discrepancies were resolved through discussion, with involvement of a third reviewer when necessary.
Quality assessment
The methodological quality of the included studies was assessed using the Cochrane Risk of Bias 2.0 tool for randomized trials20. Two reviewers independently evaluated each trial, at the outcome level, across the following domains: bias arising from the randomization process, bias due to deviations from intended interventions, bias due to missing outcome data, bias in measurement of the outcome, and bias in selection of the reported result. For each domain, signaling questions were answered according to the published guidance, and a judgment of low risk of bias, some concerns, or high risk of bias was assigned. An overall risk of bias judgment for each key outcome was then derived from the domain-level assessments. Any discrepancies between the two reviewers were resolved through discussion. When consensus could not be reached, a third reviewer was consulted. The results of the quality assessment were summarized in tables and figures and were used to inform the interpretation of the findings.
Statistical analysis
For each eligible comparison and outcome, treatment effects were summarized at the study level and then, where appropriate, combined across trials. For continuous outcomes, mean differences with 95% confidence intervals were calculated when all studies used the same instrument and scale. For dichotomous outcomes, risk ratios with 95% confidence intervals were calculated. When required data were not directly reported, available numerical information from the text, tables, or figures was used, where possible, to derive the necessary study-level summary statistics. Pairwise meta-analysis was undertaken only when at least two clinically and methodologically comparable studies reported the same outcome. In practice, only two virtual reality studies reporting cooperation outcomes on the Frankl Behavior Rating Scale were considered sufficiently comparable for pooling; therefore, quantitative synthesis was restricted to this outcome, and a fixed-effect model was applied. Statistical heterogeneity was assessed using the χ2 test and quantified with the I2 statistic. Because of the small number of pooled studies, formal sensitivity analyses and publication bias assessment were not undertaken. Owing to the marked heterogeneity across the remaining interventions and outcomes, no additional meta-analyses or network meta-analyses were performed.
Pairwise meta-analysis was undertaken only when at least two clinically and methodologically comparable studies reported the same outcome. Because only two studies evaluating virtual reality reported sufficiently comparable cooperation outcomes using the Frankl Behavior Rating Scale, quantitative synthesis was limited to this outcome. Given the small number of studies available for pooling and the apparent comparability of this subset, a fixed-effect model was applied. Statistical heterogeneity was examined using the χ2 test and quantified with the I2 statistic. Owing to the marked heterogeneity in interventions, study designs, and outcome measures across the remaining trials, no additional meta-analysis or network meta-analysis was performed. For outcomes with ten or more contributing trials, small-study effects and potential publication bias were to be explored visually using funnel plots and, where appropriate, statistically using tests for funnel plot asymmetry. If sufficient trials formed a connected network of interventions for a given outcome and the assumptions of transitivity were considered reasonable, a random-effects network meta-analysis in a frequentist framework would be considered to estimate relative effects among multiple behavior guidance techniques and, if feasible, to rank interventions. All statistical analyses were performed using R (version 4.5.3), and all tools used in this review are listed in the Table of Materials.
Results
Literature search and screening process
Electronic searches of PubMed (n = 281), Scopus (n = 426), Cochrane Library (n = 25), Web of Science (n = 137), Embase (n = 306), APA PsycInfo (n = 30), CINAHL (n = 37), and AMED (n = 0) yielded 1,242 records (Figure 1). After removal of duplicates, 487 unique records remained and were screened by title and abstract. Of these, studies were excluded because the research type did not meet the inclusion criteria (n = 109), the publication language was not English (n = 1), the topic was unrelated to behavior guidance in pediatric dentistry (n = 204), or the population did not include autistic children receiving dental care (n = 165); no non-human studies were identified (n = 0). This process left 8 potentially eligible autism-related articles for full-text review (Supplementary Tables 1–2). After assessment of the full texts against the predefined inclusion and exclusion criteria, 5 randomized controlled trials were judged eligible and were included in the systematic review
Basic characteristics of the included studies
Five randomized controlled trials published between 2014 and 2024, including 445 autistic children, were eligible13,14,18,21,22 (Table 1). All were conducted in specialist pediatric or autism-oriented dental services (three in the USA, one in Saudi Arabia, and one in India). Sample sizes ranged from 19 to 162, with most participants of school age (4–18 years). Dental procedures were restricted to non-invasive or minimally invasive care, such as clinical examinations, professional prophylaxis with fluoride application, and simple preventive interventions, and none primarily evaluated restorative or surgical treatment. Most trials involved one or two planned preventive visits, with repeated visits over several months reported in a single visual pedagogy study.
The behavior guidance strategies fell into four main categories. One large crossover trial evaluated a multisensory sensory-adapted dental environment, in which visual, auditory, and tactile stimuli were modified using projected calming scenes, reduced overhead lighting, music, and a deep-pressure vest, compared with the usual clinic setting14. A four-arm pilot RCT tested electronic media–based guidance using video modeling, in-chair video goggles, or their combination versus standard preparation and behavior management18. One parallel trial examined a structured visual pedagogy program based on picture schedules and social stories21, while two trials assessed immersive virtual reality delivered via head-mounted displays presenting relaxing scenarios, compared with conventional non-pharmacological behavior management (for example, tell–show–do, distraction, and positive reinforcement)14,22. Anxiety was measured with tools such as the Venham Anxiety Scale, Venham Picture Test, and Venham Anxiety and Behavior Scale23, and cooperation with the Frankl Behavior Rating Scale or Venham Clinical Cooperation Scale. Some studies also collected parent- and dentist-reported distress and objective physiological indices such as electrodermal activity or salivary cortisol. Despite heterogeneity in design, interventions, and outcome measures, all trials focused on reducing anxiety and behavioral dysregulation in autistic children during routine dental care.
Risk of bias assessment
Overall, methodological quality was moderate (Table 2 and Figure 2). Among the five included trials, four were judged as having some concerns overall. Three of these were rated as having some concerns, mainly because of incomplete reporting of the randomization process and non-blinded outcome assessment. In contrast, one study13 was rated as low risk in the randomization process domain, although it remained at some concerns overall because blinding was not feasible, and outcome measurement may have been susceptible to bias. The final study22 was judged at overall low risk, with performance bias considered inherent to the intervention. Across all studies, missing outcome data were minimal and were judged to be at low risk. However, because behavioral and anxiety outcomes relied largely on subjective ratings without consistent masking of assessors, most trials were rated as having some concerns in the outcome measurement domain. Selective reporting was not clearly evident, although the lack of preregistered protocols in some trials contributed to isolated ratings of some concerns.
Quantitative synthesis of virtual reality on cooperation
Owing to substantial heterogeneity in intervention type, comparator, study design, outcome definition, and reporting format, only two trials evaluating virtual reality and reporting cooperation outcomes on the Frankl Behavior Rating Scale were considered sufficiently comparable for quantitative synthesis. Anxiety-related outcomes were reviewed narratively because the available measures were too heterogeneous for pooling. For the two included studies, group-specific means and standard deviations were extracted, and mean differences (VR vs control) were calculated and pooled in a fixed-effect meta-analysis. In the larger parallel-group randomized trial13 VR was associated with higher Frankl scores than conventional care (mean difference [MD] 0.55, 95% CI 0.23 to 0.88), indicating better cooperation. The smaller crossover study22 showed a similar direction of effect (MD 0.39, 95% CI −0.35 to 1.13), although with wider confidence intervals. The pooled estimate suggested that VR improved cooperation by approximately half a Frankl point compared with control (pooled MD 0.52, 95% CI 0.22 to 0.82). Statistical heterogeneity was low (χ2 = 0.15, I2 = 0%). Because only two studies were eligible for pooling, no formal sensitivity analysis or publication bias assessment was undertaken (Table 3).
Narrative synthesis of other interventions
Because the remaining interventions were highly heterogeneous in content, outcome measures, and reporting, they were synthesized narratively. Sensory-adapted dental environments were associated with lower physiological stress and behavioral distress, visual pedagogy showed benefit for selected preventive procedures, and electronic media–based approaches showed some reduction in fear and uncooperative behaviors, although between-study comparability was limited.
DATA AVAILABILITY:
The data utilized in this study were available in the supplementary material.
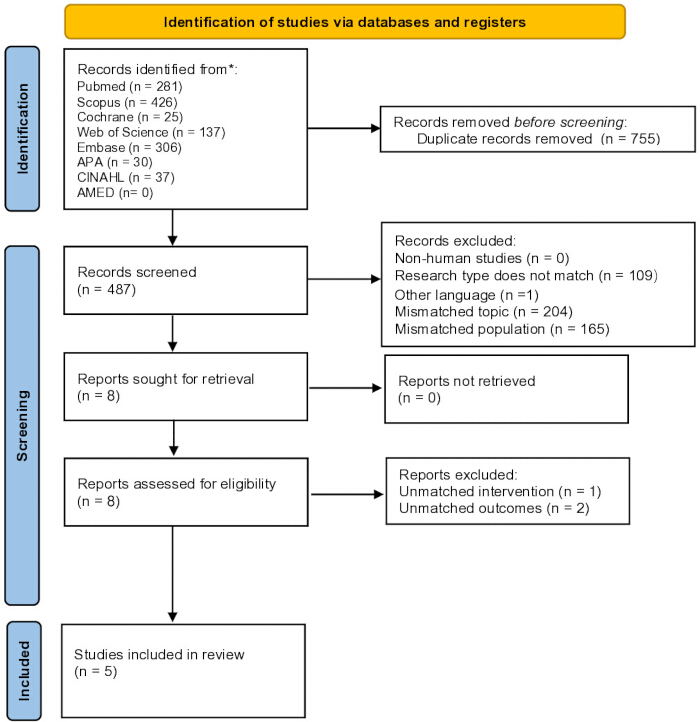
Figure 1: PRISMA flowchart for study selection. Flow diagram showing the process of study identification, screening, eligibility assessment, and final inclusion of randomized controlled trials in the systematic review and meta-analysis. Please click here to view a larger version of this figure.
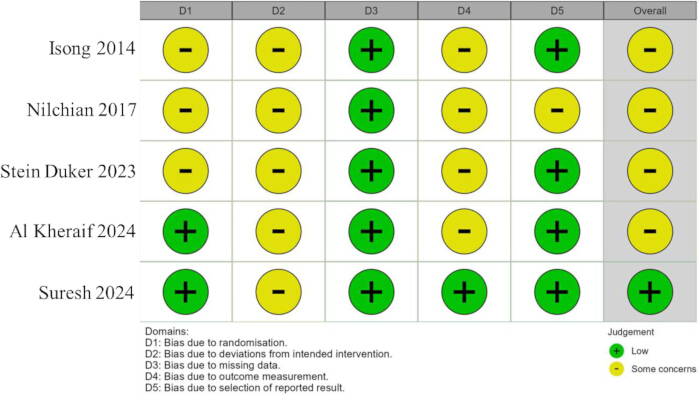
Figure 2: Risk of bias assessment for included randomized controlled trials. Summary of the methodological quality of the included randomized controlled trials based on the ROB 2 tool, covering domains including the randomization process, deviations from intended interventions, missing outcome data, measurement of the outcome, selection of the reported result, and overall risk of bias. Please click here to view a larger version of this figure.
| Study (first author, year) | Country / setting | Design | Participants (ASD only) | Dental procedure(s) | Behavior guidance intervention | Comparator(s) | Main anxiety / behavior outcomes* |
| Stein Duker 2023 (JAMA Netw Open) | USA; two hospital-based pediatric dental clinics | Randomized crossover clinical trial (SADE vs regular environment) | 162 autistic children, 6–12 y, with ≥1 previous cleaning | Two professional dental cleanings with prophylaxis and fluoride | Enhanced sensory-adapted dental environment (projected visual scenes, reduced overhead lighting, calming music, deep-pressure “hugging” vest) | Usual clinic environment with standard sensory input | Primary: physiological arousal (electrodermal activity). Secondary: video-coded behavioral distress, cooperation, proportion of cleaning steps completed, caregiver- and dentist-rated child distress and cooperation |
| Isong 2014 (Addressing Dental Fear in Children with ASD) | USA; hospital-based pediatric dental clinic | Randomized controlled pilot trial, four parallel arms | 80 children with ASD, 7–17 y | Two preventive visits (examination, prophylaxis, fluoride; radiographs as needed) | (1) Video modelling of dental procedures; (2) video goggles playing a movie during treatment; (3) combination of video modelling plus video goggles | Standard preparation and behavior guidance without electronic media | Venham Anxiety Scale and Venham Clinical Cooperation Scale (change from first to second visit); parent ratings of child anxiety and cooperation |
| Nilchian 2017 (Visual pedagogy trial) | Single-center autism / dental service | Randomized double-blind clinical trial, two parallel arms | 44 children with autism, 6–12 y | Dental check-up and preventive care in a mobile dental unit (examination, toothbrushing instruction, topical fluoride) | Visual pedagogy (structured picture-based materials and social stories explaining dental procedures and routines, used before and during visits) | Conventional verbal explanation and usual behavior guidance | Behavioral cooperation at different treatment stages (entering dental unit, examination, toothbrushing, fluoride application) rated with Frankl Behavior Rating Scale over repeated visits |
| Al Kheraif 2024 (J Clin Med; VR during examination) | Saudi Arabia; two specialized ASD centers and dental clinic | Randomized controlled trial, two parallel arms | 140 participants with ASD, 4–18 y | Chairside dental examination (mirror and probe assessment) | Virtual reality headset presenting a relaxing, immersive natural environment during the examination | Conventional dental examination with routine communication and behavior management only | Anxiety measured with Venham Anxiety and Behavior Scale; cooperation measured with Frankl Behavior Rating Scale; between-group comparisons during the examination |
| Suresh 2024 (J Autism Dev Disord; VR salivary cortisol) | India; university dental college | Randomized crossover study (two visits: conventional vs VR distraction) | 19 children with ASD, 8–15 y, needing routine non-invasive dental treatment | Two routine non-invasive dental treatments (e.g. examination, simple preventive procedures) | Virtual reality distraction during treatment (immersive VR headset) | Conventional non-pharmacological behavior management (e.g. tell–show–do, distraction, positive reinforcement) | Subjective pain (Wong–Baker Faces pain rating scale), dental anxiety (Venham Picture Test), behavior (Frankl scale); physiological stress via salivary cortisol at baseline, pre- and post-treatment |
Table 1: Characteristics of randomized trials of behavior guidance techniques for children with autism undergoing dental care. Summary of the main characteristics of the included randomized controlled trials, including country, study setting, study design, sample size, type of behavior guidance technique, comparator, and outcome measures. Please click here to download this Table.
| Study | Randomization process | Deviations from intended interventions (blinding/performance) | Missing outcome data | Measurement of outcomes | Selection of reported results | Overall risk of bias* |
| Isong 2014 | some concerns | some concerns | low | some concerns | low | some concerns overall |
| Nilchian 2017 | some concerns | some concerns | low | some concerns | some concerns | some concerns overall |
| Stein Duker 2023 | some concerns | some concerns | low | some concerns | low | some concerns overall |
| Al Kheraif 2024 | low | some concerns | low | some concerns | low | some concerns overall |
| Suresh 2024 | low | some concerns | low | low | low | overall low risk, with unavoidable performance bias |
Table 2: Risk of bias assessment for included randomized controlled trials. Detailed domain-level risk-of-bias judgments for each included randomized controlled trial, using the ROB 2 tool, together with the overall risk-of-bias assessment. Please click here to download this Table.
| Study | Design | n (VR) | Mean ± SD (VR) | n (Control) | Mean ± SD (Control) | MD (VR – Control) | 95% CI | Weight (%) |
| Al Kheraif | Parallel RCT | 70 | 3.41 ± 0.96 | 70 | 2.86 ± 1.00 | 0.55 | 0.23 to 0.88 | 84 |
| Suresh | Crossover * | 10 | 1.89 ± 0.93 | 9 | 1.50 ± 0.71 | 0.39 | -0.35 to 1.13 | 16 |
| Pooled | Fixed-effect | 0.52 | 0.22 to 0.82 | 100 |
Table 3: Effects of virtual reality on cooperation (Frankl Behavior Rating Scale) in autistic children during dental visits. Summary of the pooled effects of virtual reality–based interventions on cooperation during dental visits in autistic children, as assessed using the Frankl Behavior Rating Scale, including effect estimates and corresponding confidence intervals. Please click here to download this Table.
Discussion
In this systematic review, the researchers identified five randomized controlled trials, enrolling 445 autistic children, that evaluated non-pharmacological behavior guidance strategies during routine dental care. Interventions targeted different levels of the care pathway, from global modification of the sensory environment to chairside distraction and pre-visit preparation. Despite this heterogeneity, most trials reported some improvement in anxiety-related or behavioral outcomes. Quantitative synthesis was only possible for two VR trials that reported Frankl Behavior Rating Scale scores, and these showed that VR was associated with a moderate improvement in cooperation during dental visits, with a pooled mean difference of about half a Frankl point compared with conventional behavior management.
Meanwhile, the largest trial of an SADE in autistic children demonstrated clinically important reductions in physiological stress, reflected by lower skin conductance levels, and marked reductions in video-coded behavioral distress during prophylaxis when the lighting, auditory input, and tactile stimuli were modified, compared with a regular clinic environment15. A visual pedagogy program based on picture schedules and social stories produced incremental gains in cooperation at some treatment steps but not others, whereas electronic media–based strategies such as video modeling and video goggles showed within-group reductions in anxiety and behavioral scores but yielded less consistent between-group differences. Overall, the available evidence suggests that behavior guidance can improve the dental experience of autistic children, but effect estimates remain imprecise and methodologically constrained.
SADE represents a “context-level” intervention that seeks to reduce sensory overload by modifying multiple stimuli simultaneously15. In the recent randomized crossover trial in 162 autistic children, the adapted environment produced significantly lower electrodermal activity across the visit and large effect sizes for reductions in behavioral distress compared with the regular clinic environment. These findings extend earlier pilot work in mixed samples of autistic and typically developing children, in which SADE reduced physiological anxiety, perceived pain, and sensory discomfort during oral prophylaxis24,25. Taken together, these trials support the concept that proactively tailoring the dental environment to sensory profiles can relieve sympathetic arousal and improve tolerability of routine care in autistic children, for whom auditory, visual, and tactile hypersensitivity are common. From a clinical perspective, SADE has several attractive features26. It does not require the child to adopt a new coping skill and can be implemented even when communication is limited27. However, it demands investment in equipment and training, and some components (for example, deep-pressure vests) may not be acceptable to all children or families. In addition, the trials were conducted in highly resourced specialist settings, so the generalizability of SADE to high-volume public clinics remains uncertain. Implementation studies that adapt SADE principles to lower-cost modifications, such as dimmable lighting, simplified visual environments, and noise reduction, are warranted26.
VR is an individual-level distraction technique that combines visual and auditory immersion and can partially shield the child from noxious stimuli in the operatory16. In this review, VR was the only modality for which data permitted pairwise meta-analysis: pooling two trials showed that VR produced a moderate improvement in Frankl cooperation scores compared with standard non-pharmacological behavior management, with no evidence of statistical heterogeneity. This is consistent with the direction of effect for anxiety and physiological measures in the individual trials, although these outcomes could not be pooled. These findings align with the broader pediatric dentistry literature, in which several randomized clinical trials in neurotypical children have reported that VR distraction reduces dental anxiety, pain ratings, and salivary cortisol during prophylaxis or short invasive procedures, and in some studies, improves behavioral ratings28,29. However, studies in typically developing children have also noted variability in the magnitude of benefit and occasional null findings for behavioral scales. For autistic children, additional considerations include the child’s tolerance of head-mounted devices, potential motion sensitivity, and the need to maintain sufficient access and communication for safe care. VR should therefore be viewed as a promising but not universally applicable adjunct, best integrated into a broader behavior guidance plan rather than used in isolation.
Visual pedagogy, including picture schedules and social stories30, is widely used in educational and therapeutic settings for autistic children to improve predictability and support transitions. In the included visual pedagogy trial, both the intervention and control groups showed improved cooperation over repeated preventive visits, and visual supports conferred additional benefit primarily for fluoride application rather than for earlier steps such as entering the surgery or tolerating examination. This pattern is plausible: visual scaffolding may be most helpful once the child has accepted the basic setting and can use sequences to anticipate specific procedures31. Evidence from non-dental contexts suggests that visual schedules and social stories can reduce anxiety and problem behaviors around medical procedures and daily routines in autistic children, although effect sizes are variable and many studies lack rigorous controls. Within dentistry, the single available RCT in this review indicates that visual pedagogy is feasible and may modestly enhance cooperation, particularly when combined with repeated exposure32. Future work should clarify optimal dosing and timing (for example, home-based preparation vs chairside use) and examine whether tailoring materials to language level and cognitive ability improves outcomes21.
Large systematic reviews and meta-analyses in general pediatric populations have concluded that non-pharmacological behavioral interventions, particularly distraction techniques, can reduce dental fear and anxiety, improve cooperation, and lower physiological arousal compared with standard tell–show–do, although heterogeneity is substantial and evidence for specific named techniques (for example, VR, modeling, visual pedagogy) is mixed. These findings in autistic children broadly align with this pattern: distraction-based strategies, including VR and sensory adaptation of the environment, appear to confer benefit on anxiety-related and behavioral outcomes, but effect sizes vary, and the certainty of evidence is low to moderate. However, autistic children differ from their neurotypical peers in several relevant dimensions, including sensory over-responsivity, atypical attentional deployment, and differences in communication and social motivation. These features may amplify the benefit of interventions that reduce sensory load or enhance predictability (such as SADE and visual pedagogy), while at the same time limiting the applicability of standard techniques that rely heavily on verbal explanation or social modeling. This review underscores that behavior guidance approaches validated in typically developing children cannot be assumed to generalize directly to autistic populations without adaptation and empirical testing.
Comparative effectiveness studies that directly contrast different behavior guidance packages—for example, SADE with and without VR, or visual pedagogy with and without caregiver training—would be valuable. Mechanistic work examining how sensory adaptation, predictability, and attentional engagement interact to modulate distress in autistic children during dental procedures could help refine intervention components. Finally, economic evaluations and implementation studies in diverse service settings are needed to determine which strategies offer the greatest benefit relative to cost and complexity, and how they can be scaled beyond specialist centers.
An additional methodological consideration is that several protocol-level decisions influenced the strength and interpretability of the present review. In particular, broad inclusion of non-pharmacological behavior guidance techniques increased clinical relevance but also introduced marked heterogeneity in intervention content, delivery, and target mechanisms. Heterogeneity in outcome definitions and reporting further limited comparability across studies, especially for anxiety-, distress-, and cooperation-related measures. These challenges reduced the feasibility of quantitative synthesis beyond the subset of virtual reality studies and underscore the importance of more standardized outcome selection, reporting, and analytical planning in future systematic reviews in this field.
The review also has limitations. Only English-language publications were included, and the researchers could not formally assess publication bias, so the possibility of selective non-reporting of negative trials cannot be excluded. Given the small number of eligible studies, it was unable to conduct subgroup analyses by age, autism severity, cognitive level, or previous dental experience, all of which might plausibly modify intervention effects. In addition, although the researchers attempted a comprehensive search across multiple databases and trial registries, some relevant unpublished or ongoing work may have been missed. Finally, the available trials are few in number and often small, with three of five studies designed primarily as pilot or feasibility work. Interventions, comparators, and outcomes were highly diverse, and most studies relied on subjective behavioral scales without consistent blinding of outcome assessors, resulting in “some concerns” of bias in several risk-of-bias domains. Reporting of numeric data was sometimes incomplete, which restricted the scope for quantitative synthesis; only two VR trials contributed to the meta-analysis of Frankl scores, and network meta-analysis was not feasible. Finally, the search strategy may also have involved a trade-off between sensitivity and specificity, and the possibility of missed studies cannot be fully excluded.
In conclusion, non-pharmacological behavior guidance strategies may help improve clinically relevant outcomes in autistic children during dental care. However, pooled quantitative evidence in the present review was available only for virtual reality–related improvements in cooperation, whereas evidence for other techniques remained limited and was based primarily on narrative synthesis.
Disclosures
The authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest.
Acknowledgements
Not available.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| AMED | Ovid (Wolters Kluwer) | N/A | Allied and Complementary Medicine Database; used for systematic literature searching. |
| APA PsycInfo | American Psychological Association (via Ovid/EBSCO) | N/A | Psychology database; used for systematic literature searching. |
| Cochrane Library | Wiley | N/A | Database of systematic reviews and clinical trials; used for systematic literature searching. |
| CINAHL | EBSCO Information Services | N/A | Cumulative Index to Nursing and Allied Health Literature; used for systematic literature searching. |
| Embase | Elsevier | N/A | Biomedical and pharmacological database; used for systematic literature searching. |
| Endnote X9.1 | Clarivate | X9.1 | Literature management software; used to organize and manage references. |
| Excel 2016 | Microsoft Corporation | 2016 | Spreadsheet software; used for data extraction. |
| Frankl Behavior Rating Scale | Academic/Clinical Tool | N/A | Observational scale for assessing child cooperation in dental settings; used as a primary outcome measure. |
| PubMed | National Center for Biotechnology Information (NCBI) | N/A | Medical literature database; used for systematic literature searching. |
| R | R Foundation for Statistical Computing | 4.5.3 | Statistical computing software; used for planned meta-analysis. |
| Scopus | Elsevier | N/A | Abstract and citation database; used for systematic literature searching. |
| Venham Anxiety and Behavior Scale | Academic/Clinical Tool | N/A | Scale for measuring dental anxiety and behavior in children; used as an outcome measure in included trials. |
| Venham Anxiety Scale | Academic/Clinical Tool | N/A | Tool for assessing dental anxiety in pediatric patients; used as an outcome measure in included trials. |
| Venham Picture Test | Academic/Clinical Tool | N/A | Pictorial scale for evaluating dental fear in children; used as an outcome measure in included trials. |
| Web of Science | Clarivate | N/A | Citation database; used for systematic literature searching. |