This meta-analysis of 17 studies (1,708 patients with hepatocellular carcinoma) found pooled sensitivity, specificity, and area under the curve values of 0.87, 0.79, and 0.90, respectively, for radiomic prediction of high Ki-67 expression; substantial heterogeneity indicates a need for standardized research.
Research Article
A Meta-Analysis of Radiomics-Based Models for Preoperative Assessment of Ki-67 Status in Hepatocellular Carcinoma
* These authors contributed equally
In This Article
Summary
Abstract
This study aimed to evaluate the diagnostic value of radiomic features in predicting Ki-67 expression levels in hepatocellular carcinoma (HCC) through a meta-analysis. Electronic databases, including PubMed, Web of Science, the Cochrane Library, and Embase, were systematically searched for relevant clinical studies published through 20 August 2025. Studies using radiomic features to predict Ki-67 expression levels in patients with HCC were included. Sensitivity, specificity, and summary receiver operating characteristic curves were evaluated, and the area under the curve (AUC) was calculated. A total of 17 studies involving 1,708 patients with HCC were included. The pooled sensitivity was 0.87 (95% confidence interval [CI], 0.81–0.91), the pooled specificity was 0.79 (95% CI, 0.71–0.85), and the overall AUC was 0.90 (95% CI, 0.87–0.93). The pooled AUC values for Ki-67 cutoff values of 10% and >10% were 0.89 (95% CI, 0.86–0.92) and 0.90 (95% CI, 0.87–0.92), respectively. The AUC values for magnetic resonance imaging- and ultrasound-derived radiomic features were 0.88 (95% CI, 0.85–0.91) and 0.92 (95% CI, 0.89–0.94), respectively. The AUC for prediction models based on logistic regression was 0.89 (95% CI, 0.86–0.92). Radiomic features showed promising pooled diagnostic performance for predicting high Ki-67 expression in HCC. However, substantial heterogeneity was present among the included studies. Further standardized research is needed to validate these findings.
Introduction
Over the past decade, the incidence and prevalence of liver cancer have progressively increased, making it a significant and growing disease burden worldwide. Specifically, hepatocellular carcinoma (HCC) accounts for 90% of all primary liver cancer diagnoses and represents the fourth most common cause of cancer-related deaths globally, with 840,000 new cases reported in 20181,2. Despite recent advances in surgical techniques, local interventions, and systemic therapies, the long-term prognosis of patients with HCC remains suboptimal, with 5-year overall survival rates ranging between 13% and 36%3,4,5. This is largely attributable to its insidious onset, difficulties in early diagnosis, and high tumor biological heterogeneity. These challenges underscore a critical limitation of current diagnostic strategies: traditional histopathological assessments are invasive and unable to provide real-time, comprehensive evaluation of dynamic tumor biology. Therefore, the development of novel, noninvasive tools that can accurately quantify the intrinsic malignant potential of tumors is important for advancing personalized medicine in HCC.
Among various prognostic molecular biomarkers, Ki-67 is a well-established indicator of cellular proliferation and is closely associated with prognosis in multiple malignancies. Ki-67 reflects proliferative activity and is widely expressed in tumor cells; its high expression is strongly correlated with increased invasiveness and poor differentiation, serving as a predictor of tumor aggressiveness6. In HCC, multiple studies have confirmed that high Ki-67 expression is significantly associated with larger tumor size, vascular invasion, higher Edmondson–Steiner grade, and advanced tumor node metastasis stage. Moreover, it serves as an independent predictor of postoperative recurrence and worse overall survival7,8,9,10. As Ki-67 expression levels mirror the proliferative state of tumor cells—with elevated levels indicating greater invasiveness and more rapid disease progression—this biomarker holds considerable value in prognostic stratification, treatment decision-making, and therapeutic monitoring in HCC. However, current clinical assessment of Ki-67 relies on invasive tissue sampling. This approach not only carries procedural risks and patient discomfort but, more importantly, given the substantial spatial and temporal heterogeneity of HCC, a single biopsy may fail to represent the overall proliferative status of the tumor, potentially leading to clinical misinterpretation11. Thus, there is an urgent clinical need for a noninvasive, reproducible method that can comprehensively capture the spatial heterogeneity of Ki-67 expression.
The emergence of radiomics offers a potential approach to address this limitation. Radiomics involves the high-throughput extraction of numerous quantitative features from standard medical images, such as computed tomography (CT), magnetic resonance imaging (MRI), or positron emission tomography (PET), and the construction of predictive models using machine learning or deep learning algorithms to decode underlying tumor biology12. In HCC research, radiomics has been successfully applied in tumor grading, prediction of microvascular invasion, assessment of gene expression, and treatment response monitoring. Although several studies have attempted to develop radiomic models for predicting Ki-67 expression13,14, there remains considerable variability across studies in sample size, imaging modalities, feature extraction methods, and model performance. Therefore, a systematic meta-analysis is required to quantitatively synthesize these heterogeneous findings, establish robust pooled diagnostic estimates, and identify key sources of clinical and methodological variation, thereby providing an evidence-based foundation for future standardization and clinical translation. In practice, the clinical translation of radiomics is challenged by issues with feature reproducibility and modality-specific limitations, such as MRI’s dependence on scanning parameters and ultrasound’s dependence on the operator. Consequently, the clinical utility of these models must be critically appraised based on their methodological standardization and external validation status. The clinical applicability and robustness of these models have yet to be systematically evaluated. Therefore, this study comprehensively assesses the diagnostic performance of radiomic models in predicting Ki-67 expression status in HCC, thereby providing an evidence-based foundation for future standardization and clinical translation.
Protocol
Search strategy and information source
In accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 statement15, a systematic search was performed across PubMed, Web of Science, Cochrane Library, and Embase from database inception to 20 August 2025, without language restrictions (see Supplemental File 1). The search strategy was constructed by grouping keywords and subject headings (such as Medical Subject Headings [MeSH] in PubMed and Emtree in Embase) into three logical blocks using the Boolean operators ‘AND’ and ‘OR’. These blocks were applied to the title, abstract or topic fields in each database as follows: (1) radiomics, models and imaging: ‘radiomics’, ‘texture analysis’, ‘image features’, ‘magnetic resonance imaging’ (or ‘MRI’), ‘tomography, X-ray computed’ (or ‘CT’), ‘ultrasonography’ (or ‘ultrasound’), ‘deep learning’, ‘machine learning’, and ‘logistic’; (2) disease: ‘hepatocellular carcinoma’, ‘liver cancer’, ‘HCC’ and ‘hepatoma’; and (3) antigen: ‘Ki-67 Antigen’, ‘Ki-67’, ‘Ki67’, and ‘proliferation index’. The exact search syntax was adjusted to fit the specific rules of each database (e.g. using [Title/Abstract] and [MeSH] tags in PubMed, and ‘:ti,ab’ or ‘/exp’ tags in Embase). A manual search of the bibliographies of the retrieved studies, together with relevant review articles, was also performed to identify any additional eligible publications. The study protocol has been retrospectively registered in the INPLASY database under the registration number INPLASY202670061.
Eligibility criteria
To ensure a clinically relevant study selection, the eligibility of retrieved studies was determined using the PICOS (Population, Intervention, Comparison, Outcome, and Study design) framework.
The inclusion criteria were as follows: (1) study population consisting of patients diagnosed with HCC based on histopathological examination of resected/biopsied tissue, or according to established clinical and imaging guidelines; (2) use of radiomics, deep learning or texture features derived from medical imaging modalities (including CT, MRI or ultrasonography) to predict tumor Ki-67 expression levels; (3) histopathological evaluation of Ki-67 expression levels on tumor specimens, with a clearly defined cutoff value to classify patients into high-expression and low-expression groups; (4) availability of diagnostic outcomes in the form of a 2 × 2 contingency table enabling calculation of test performance; and (5) original, peer-reviewed clinical studies.
Studies were excluded if they (1) were conference abstracts, case reports, systematic reviews, or other non-original research; (2) contained insufficient outcome data for quantitative analysis; (3) were duplicate publications; and (4) were not available in full text.
Study screening and data extraction protocol
To execute the literature screening, all retrieved citations from the electronic databases were merged, and duplicate records were systematically identified and removed. Subsequently, two investigators independently screened the remaining literature based on the predefined inclusion and exclusion criteria. Initially, titles and abstracts were reviewed, and potentially eligible studies underwent full-text assessment. Any discrepancies between the two reviewers were resolved through discussion or by consulting a third researcher to reach a consensus.
After completing the screening process, the same two investigators independently extracted data using a standardized, predefined extraction form. The extracted information included basic study characteristics, demographic details of the study population, and diagnostic performance data, specifically, the number of true positives, false positives, true negatives, and false negatives. For studies with missing data or unresolved ambiguities, we contacted the corresponding authors via email to request the original data and excluded studies if the required data remained unavailable.
Quality assessment and risk-of-bias evaluation
The quality of the included diagnostic studies was evaluated using the Quality Assessment of Diagnostic Accuracy Studies 2 (QUADAS-2) tool, developed by Whiting et al. at the University of York16. This instrument assesses four domains: patient selection, index test, reference standard, and flow and timing. Each domain was rated for risk of bias as “high,” “low,” or “unclear.” Two investigators independently conducted the quality assessment. Any discrepancies were resolved through discussion or by consulting a third researcher to reach consensus.
Statistical analysis
Statistical analyses were conducted using Stata version 16.0 and Review Manager (RevMan) version 5.3. RevMan was used to evaluate methodological quality, assess the risk of bias, and generate the corresponding visual summaries. Diagnostic accuracy was analyzed in Stata 16.0 with the hierarchical midas module. Pooled sensitivity and specificity, together with their 95% confidence intervals (CIs), were estimated using a bivariate random-effects model. Overall diagnostic performance was summarized by constructing a hierarchical summary receiver operating characteristic (HSROC) curve and calculating the corresponding area under the curve (AUC). Between-study heterogeneity was examined with Cochran's Q test and the I2 statistic, with I2 values below 50% or Q test P values greater than 0.10 considered indicative of acceptable homogeneity. To investigate potential sources of heterogeneity, prespecified subgroup analyses were carried out according to Ki-67 cutoff values, imaging modality, and prediction model. The presence of a threshold effect was evaluated by determining the Spearman correlation between the logit-transformed sensitivity and the logit of (1 − specificity). Potential publication bias was assessed using Deeks' funnel plot asymmetry test. Unless stated otherwise, all statistical tests were two-tailed, and statistical significance was defined as P < 0.05.
Results
Characteristics of included studies
Through a systematic electronic database search, 3,923 studies were initially identified for screening. After excluding 2,032 duplicate records and 1,719 irrelevant studies, 172 articles underwent full-text review. Based on the predefined inclusion and exclusion criteria, 17 studies13,14,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31 were ultimately included in the meta-analysis (Figure 1).
The basic characteristics of the included studies are summarized in Table 1. These 17 studies comprised a total of 1,708 patients with HCC, of whom 962 had high Ki-67 expression and 746 had low expression. Various cutoff values for Ki-67 expression were applied across studies: 8 studies used 10%, whereas the remaining 9 used thresholds >10%, ranging from 14% to 50%; MRI was the most common source of radiomic features (n = 9), followed by ultrasonography (n = 5) and CT (n = 3). Ten studies used radiomic features alone for Ki-67 prediction, whereas the other 7 combined radiomic and clinical features to construct predictive models. In terms of modeling techniques, logistic regression was employed in 14 studies, and machine learning models, including support vector machine (SVM, n = 2) and Xception (n = 1), were used in 3 studies. Additionally, 5 studies were prospective in design, and 12 were retrospective.
Diagnostic value of radiomic features for predicting Ki-67 expression
A total of 17 studies evaluating the diagnostic accuracy of radiomic features in predicting Ki-67 expression levels in HCC were included. The random-effects meta-analysis showed a pooled sensitivity of 0.87 (95% CI: 0.81–0.91) and a pooled specificity of 0.79 (95% CI: 0.71–0.85) for predicting high Ki-67 expression. Significant heterogeneity was observed among studies (sensitivity: I2 = 80.81%; specificity: I2 = 86.86%), as shown in Figure 2. The Spearman correlation coefficient was −0.062 (P = 0.814), indicating no statistically significant threshold effect. The SROC analysis yielded an AUC of 0.90 (95% CI: 0.87–0.93), indicating high pooled diagnostic performance (Figure 3).
Ki-67 cutoff values and diagnostic performance
In the subgroup using a Ki-67 cutoff value of 10%, the radiomics-based diagnostic model demonstrated strong performance, with a pooled sensitivity of 0.87 (95% CI: 0.78–0.93), a specificity of 0.76 (95% CI: 0.60–0.87) and an AUC of 0.89 (95% CI: 0.86–0.92), indicating high diagnostic accuracy at this threshold (Figure 4 and Supplemental Figure S1). In the subgroup with Ki-67 cutoff values >10%, the model showed a pooled sensitivity of 0.87 (95% CI: 0.79–0.92), a specificity of 0.80 (95% CI: 0.71–0.86), and an AUC of 0.90 (95% CI: 0.87–0.92) (Figure 5 and Supplemental Figure S2).
Imaging modalities and diagnostic value
In the subgroup using MRI-derived radiomic features, the pooled sensitivity was 0.86 (95% CI: 0.77–0.92), the specificity was 0.77 (95% CI: 0.65–0.85), and the AUC was 0.88 (95% CI: 0.85–0.91), as shown in Figure 6 and Supplemental Figure S3. The subgroup based on ultrasound radiomics showed a sensitivity of 0.88 (95% CI: 0.74–0.95), a specificity of 0.81 (95% CI: 0.61–0.92), and an AUC of 0.92 (95% CI: 0.89–0.94) (Figure 7 and Supplemental Figure S4). Additionally, three studies used CT-based radiomic features20,25,30; however, due to the limited sample size, meta-analysis was not performed for this subgroup. These studies reported sensitivities ranging from 0.778 to 0.963, specificities from 0.75 to 0.877, and AUC values between 0.836 and 0.903 (Table 2).
Predictive models and diagnostic performance
In the subgroup employing logistic regression models, the pooled sensitivity was 0.86 (95% CI: 0.79–0.90), the specificity was 0.78 (95% CI: 0.68–0.85), and the AUC was 0.89 (95% CI: 0.86–0.92) (Figure 8 and Supplemental Figure S5). These estimates were similar to the overall results. Moreover, three studies used machine learning models: two employed SVM14,28, reporting AUC values of 0.94 and 0.986, sensitivities of 0.95 and 0.973, and specificities of 0.91 and 0.8397, respectively. One study used the Xception model24, with an AUC of 0.8, sensitivity of 0.76 and specificity of 0.78 (Table 2).
Risk of bias
The QUADAS-2 assessment indicated that most domains were judged to have a low risk of bias, with some high or unclear ratings in patient selection and flow and timing (Supplemental Figure S6 and Supplemental Figure S7). Deeks’ funnel plot asymmetry test showed no evidence of statistically significant publication bias (P = 0.42) (Supplemental Figure S8).
Overall, the pooled estimates indicated high diagnostic performance for radiomic prediction of Ki-67 expression, but the substantial between-study heterogeneity limits generalizability.
Data Availability
The study-level data extracted from the 17 included studies and used in this meta-analysis are provided in Supplemental File 2.
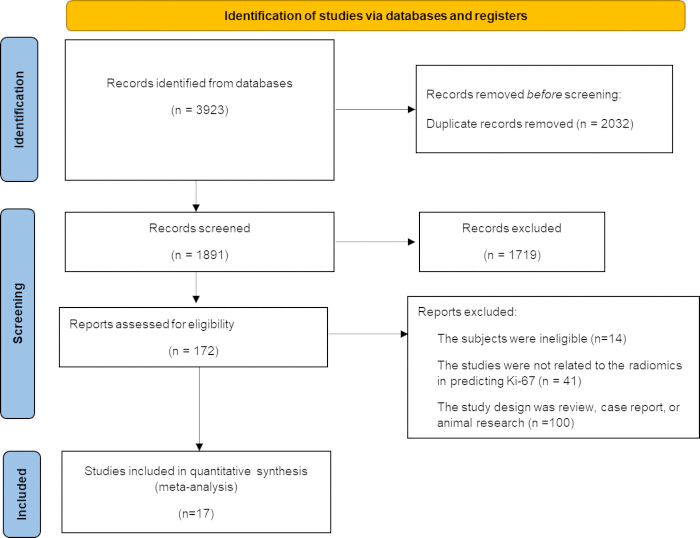
Figure 1: Flowchart of study selection. The flowchart shows the literature search, screening, eligibility assessment, and study inclusion process in accordance with PRISMA 2020. Abbreviation: PRISMA = Preferred Reporting Items for Systematic Reviews and Meta-Analyses. Please click here to view a larger version of this figure.
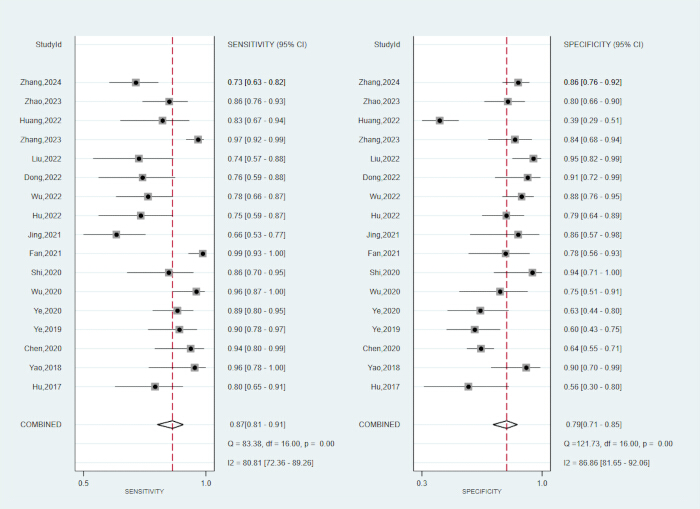
Figure 2: Sensitivity and specificity of radiomics for predicting Ki-67 expression in hepatocellular carcinoma. Paired forest plots show study-specific and pooled sensitivity and specificity estimates. Squares represent individual-study estimates, horizontal lines represent 95% CIs, and diamonds represent pooled estimates. Abbreviation: CI = confidence interval. Please click here to view a larger version of this figure.
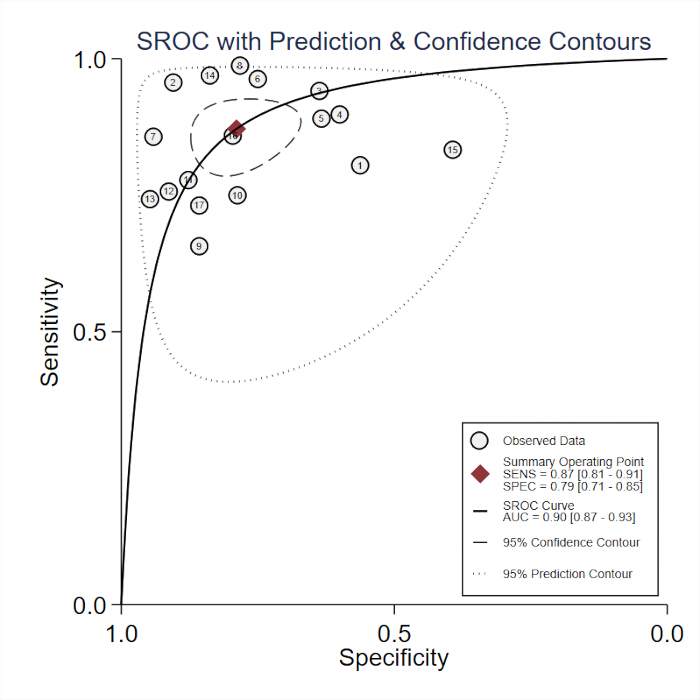
Figure 3: Overall diagnostic performance of radiomics for predicting Ki-67 expression in hepatocellular carcinoma. The SROC curve shows the summary operating point (sensitivity, 0.87; specificity, 0.79), 95% confidence contour, and 95% prediction contour; the AUC was 0.90. Abbreviations: AUC = area under the curve; SROC = summary receiver operating characteristic. Please click here to view a larger version of this figure.
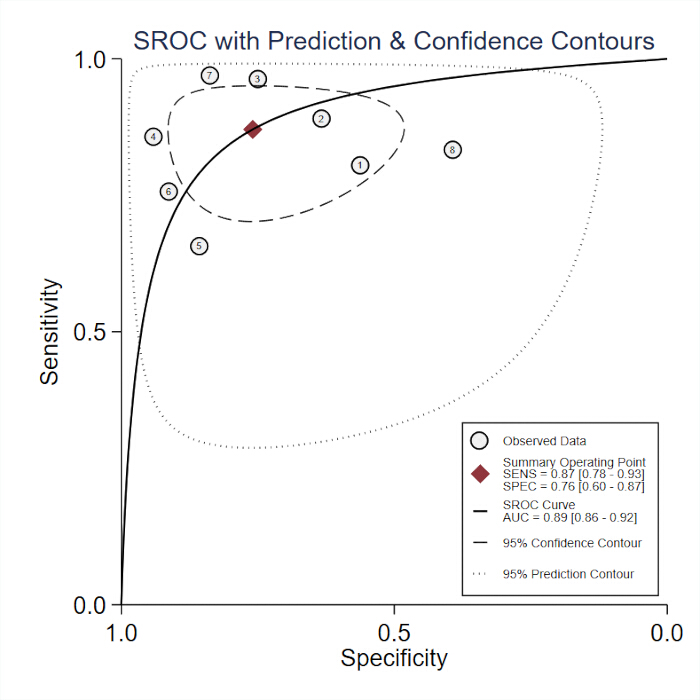
Figure 4: Diagnostic performance of the subgroup with a Ki-67 cutoff of 10%. Please click here to view a larger version of this figure.
The SROC curve shows the diagnostic performance of studies using a Ki-67 cutoff of 10%; the AUC was 0.89. Abbreviations: AUC = area under the curve; SROC = summary receiver operating characteristic.
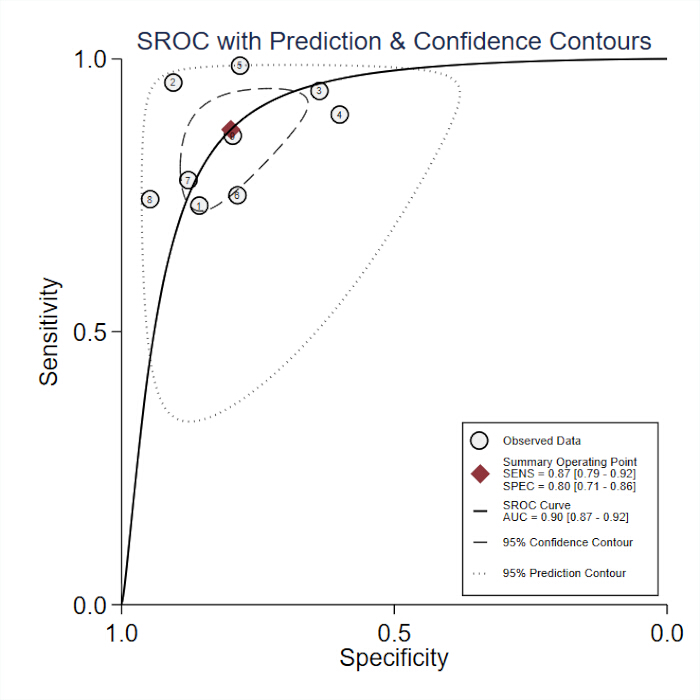
Figure 5: Diagnostic performance of the subgroup with Ki-67 cutoffs > 10%. The SROC curve shows the diagnostic performance of studies using Ki-67 cutoffs > 10%; the AUC was 0.90. Abbreviations: AUC = area under the curve; SROC = summary receiver operating characteristic. Please click here to view a larger version of this figure.
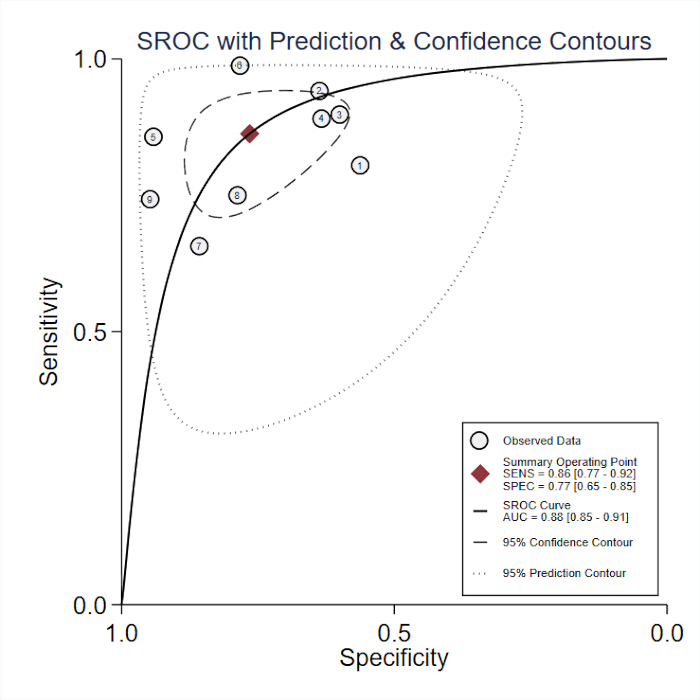
Figure 6: Diagnostic performance of MRI-based radiomic models. The SROC curve shows the pooled diagnostic performance of MRI-derived radiomic features; the AUC was 0.88. Abbreviations: AUC = area under the curve; MRI = magnetic resonance imaging; SROC = summary receiver operating characteristic. Please click here to view a larger version of this figure.
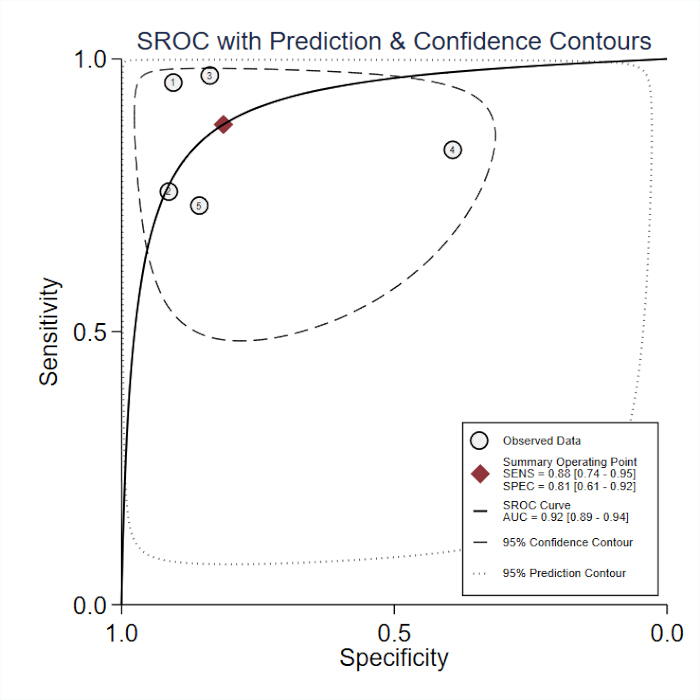
Figure 7: Diagnostic performance of ultrasound-based radiomic models. The SROC curve shows the pooled diagnostic performance of ultrasound-derived radiomic features; the AUC was 0.92. Abbreviations: AUC = area under the curve; SROC = summary receiver operating characteristic. Please click here to view a larger version of this figure.
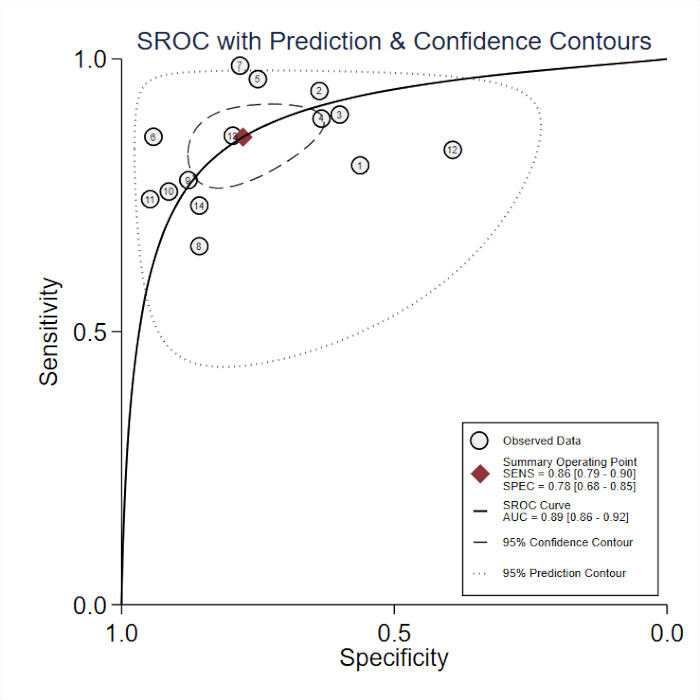
Figure 8: Diagnostic performance of logistic regression models. The SROC curve shows the pooled diagnostic performance of radiomic models constructed using logistic regression; the AUC was 0.89. Abbreviations: AUC = area under the curve; SROC = summary receiver operating characteristic. Please click here to view a larger version of this figure.
| Study | Study design | Sample size | Age | Male (%) | Imaging modality | Feature set | Prediction model | Segmentation | Validation | Ki-67 cutoff | Ki-67 high | Ki-67 low |
| Hu, 2017 | Retrospective | 57 | 54.23 ± 11.13 | 78.95 | MRI | Radiomics | Logistic regression model | Manual | No validation | 10% | 41 | 16 |
| Yao, 2018 | Retrospective | 44 | 55.5 ± 10.4 | 42.37 | Ultrasound | Radiomics | SVM | Manual | Internal validation | 25% | 23 | 21 |
| Chen, 2020 | Retrospective | 180 | 51.22 ± 10.38 | 82.8 | MRI | Radiomics | Logistic regression model | Manual | No validation | 50% | 34 | 146 |
| Ye, 2019 | Prospective | 89 | 50.72 ± 11.40 | 76.4 | MRI | Radiomics and clinical factors | Logistic regression model | Manual | Internal validation | 15% | 49 | 40 |
| Ye, 2020 | Prospective | 103 | 50.90 ± 11.93 | 77.67 | MRI | Radiomics | Logistic regression model | Manual | No validation | 10% | 73 | 30 |
| Wu, 2020 | Retrospective | 74 | 58.61 | 81.08 | CT | Radiomics | Logistic regression model | Manual | No validation | 10% | 54 | 20 |
| Shi, 2020 | Prospective | 52 | 55.7 ± 12.8 | 75. | MRI | Radiomics | Logistic regression model | Manual | No validation | 10% | 35 | 17 |
| Fan, 2021 | Retrospective | 103 | 61.0 (50.3–68.0) | 76.7 | MRI | Radiomics and clinical factors | Logistic regression model | Manual | Internal validation | 14% | 80 | 23 |
| Jing, 2021 | Retrospective | 81 | 53.52 | 76.54 | MRI | Radiomics | Logistic regression model | Manual | No validation | 10% | 67 | 14 |
| Hu, 2022 | Retrospective | 87 | 59.38 ± 11.13 | 88.51 | MRI | Radiomics | Xception | Manual | Internal validation | 20% | 40 | 47 |
| Wu, 2022 | Retrospective | 120 | 58.12 | 90. | CT | Radiomics and clinical factors | Logistic regression model | Manual | Internal validation | 20% | 63 | 57 |
| Dong, 2022 | Prospective | 60 | 59.35 ± 10.07 | 77.2 | Ultrasound | Radiomics | Logistic regression model | Manual | Internal validation | 10% | 37 | 23 |
| Liu, 2022 | Retrospective | 73 | >55 years: 71.% | 87.7 | MRI | Radiomics and clinical factors | Logistic regression model | Manual | Internal validation | 25% | 35 | 38 |
| Zhang, 2023 | Retrospective | 168 | 57.0 (49.0–64.0) | 81.5 | Ultrasound | Radiomics and clinical factors | SVM | Manual | Internal validation | 10% | 131 | 37 |
| Huang, 2022 | Prospective | 120 | 55.2 ± 11.2 | 92.5 | Ultrasound | Radiomics | Logistic regression model | Manual | No validation | 10% | 36 | 84 |
| Zhao, 2023 | Retrospective | 120 | 56.55 ± 9.53 | 87.5 | CT | Radiomics and clinical factors | Logistic regression model | Manual | Internal validation | 14% | 71 | 49 |
| Zhang, 2024 | Retrospective | 177 | 55.2 ± 11.4 | 86.4 | Ultrasound | Radiomics and clinical factors | Logistic regression model | Manual | Internal validation | 20% | 93 | 84 |
Table 1: Basic characteristics of the included studies. Characteristics of the 17 studies, including study design, sample size, imaging modality, feature set, prediction model, segmentation, validation, Ki-67 cutoff, and expression-group counts. Abbreviations: CT = computed tomography; MRI = magnetic resonance imaging; SVM = support vector machine.
| Subgroup | Reference | Sensitivity | Specificity | AUC |
| CT | 20 | 0.963 | 0.75 | 0.836 |
| CT | 25 | 0.778 | 0.877 | 0.884 (95% CI, 0.813–0.936) |
| CT | 30 | 0.86 | 0.79 | 0.903 (95% CI, 0.849–0.956) |
| Machine-learning model | 14 | 0.95 | 0.91 | 0.94 |
| Machine-learning model | 24 | 0.76 | 0.78 | 0.8 |
| Machine-learning model | 28 | 0.973 | 0.8397 | 0.986 (95% CI, 0.955–0.998) |
Table 2: Diagnostic performance of CT-based radiomic and advanced machine-learning models. Sensitivity, specificity, and AUC values reported by the individual CT-based and advanced machine-learning studies. Abbreviations: AUC = area under the curve; CI = confidence interval; CT = computed tomography.
Supplemental Figure S1: Sensitivity and specificity in the subgroup with a Ki-67 cutoff of 10%. Paired forest plots show study-specific and pooled estimates with 95% CIs. Abbreviation: CI = confidence interval. Please click here to download this file.
Supplemental Figure S2: Sensitivity and specificity in the subgroup with Ki-67 cutoffs > 10%. Paired forest plots show study-specific and pooled estimates with 95% CIs. Abbreviation: CI = confidence interval. Please click here to download this file.
Supplemental Figure S3: Sensitivity and specificity of MRI-based radiomic models. Paired forest plots show study-specific and pooled estimates with 95% CIs. Abbreviations: CI = confidence interval; MRI = magnetic resonance imaging. Please click here to download this file.
Supplemental Figure S4: Sensitivity and specificity of ultrasound-based radiomic models. Paired forest plots show study-specific and pooled estimates with 95% CIs. Abbreviation: CI = confidence interval. Please click here to download this file.
Supplemental Figure S5: Sensitivity and specificity of logistic regression models. Paired forest plots show study-specific and pooled estimates with 95% CIs. Abbreviation: CI = confidence interval. Please click here to download this file.
Supplemental Figure S6: Methodological quality graph. The graph shows the proportions of studies rated as having low, unclear, or high risk of bias and concerns regarding applicability in each QUADAS-2 domain. Abbreviation: QUADAS-2 = Quality Assessment of Diagnostic Accuracy Studies 2. Please click here to download this file.
Supplemental Figure S7: Methodological quality summary. The study-level summary shows low, unclear, or high ratings for risk of bias and concerns regarding applicability in each QUADAS-2 domain. Abbreviation: QUADAS-2 = Quality Assessment of Diagnostic Accuracy Studies 2. Please click here to download this file.
Supplemental Figure S8: Publication-bias assessment. Deeks’ funnel plot asymmetry test shows the relationship between the inverse square root of ESS and DOR; P = 0.42. Abbreviations: DOR = diagnostic odds ratio; ESS = effective sample size. Please click here to download this file.
Supplemental File 1: PRISMA 2020 checklist. The completed checklist documents reporting compliance for the systematic review and diagnostic meta-analysis. Please click here to download this file.
Supplemental File 2: Extracted data used for the diagnostic meta-analysis. The workbook contains the extracted study-level data, including patient characteristics, model details, and diagnostic performance values used for the pooled analyses. Please click here to download this file.
Discussion
This systematic meta-analysis evaluated the diagnostic performance of radiomic features for predicting Ki-67 expression in HCC. The pooled sensitivity was 0.87, the pooled specificity was 0.79, and the summary AUC was 0.90. Although estimates were broadly similar across the subgroups analyzed, substantial heterogeneity limits the generalizability of the pooled estimates. These findings suggest that radiomics may be a complement to tissue-based assessment, but its clinical utility requires further validation.
The core diagnostic value of noninvasive radiomics-based prediction of Ki-67 expression levels lies in its ability to overcome the inherent limitations of tissue biopsy, enabling visualization and quantification of the tumor's global biological characteristics. As a key indicator of cellular proliferation, Ki-67 expression often exhibits significant heterogeneity within HCC tumors and across different lesions. A biopsy sample reflects only the local status of the sampled area, carrying a risk of underestimation32. Through high-throughput extraction and analysis of texture, morphological, and intensity features from the entire tumor region, radiomics can more comprehensively capture this spatial heterogeneity and may better represent tumor proliferative status33. Furthermore, this study found that radiomics based on ultrasound modalities demonstrated a high pooled AUC of 0.92, which merits a conservative interpretation rather than being viewed as directly superior to MRI. This distinction is important because the CIs of these two modalities overlap, and the smaller number of ultrasound cohorts (n = 5) naturally broadens the prediction intervals on the SROC plot.
Rather than establishing superiority, these findings highlight the unique, modality-specific strengths of different imaging platforms. The diagnostic performance of ultrasound-derived radiomics might be related to the sensitivity of contrast-enhanced ultrasound in capturing microvascular perfusion and hemodynamics, functional information closely associated with cellular proliferative activity34. Although both ultrasound and MRI-based radiomics show promising diagnostic potential, further large-scale, head-to-head comparative studies are warranted to fully define their respective clinical positioning. Although the limited number of CT-based studies precluded meta-analysis, individual studies also showed a favorable diagnostic trend, with reported AUCs ranging from 0.836 to 0.903. This suggests the potential clinical value of radiomic features derived from different imaging sources. Contrast-enhanced CT radiomics may capture macro-level hemodynamic alterations and spatial density variations associated with microvascular remodeling and rapid tumor cell proliferation. These qualitative findings suggest that CT-derived texture features have potential utility for noninvasive Ki-67 profiling, particularly in clinical settings where multiphase CT serves as the primary imaging modality for HCC surveillance and management.
It is noteworthy that this study identified several key factors that may influence the models' diagnostic performance. First, the variation in Ki-67 expression cutoff values could be a significant source of heterogeneity. Although the model demonstrated slightly higher specificity and AUC in the subgroup with a cutoff>10%, performance between the two subgroups did not differ significantly, and the clinical importance of these differences remains uncertain. Currently, a standardized definition for Ki-67 high expression is lacking35. Future studies are needed to establish unified criteria and further validate the impact of different cutoff values on the predictive efficacy of radiomic models. Second, the choice of imaging modality significantly influences feature extraction and model construction. The multiparametric imaging capability of MRI and the dynamic enhancement characteristics of ultrasound provide complementary biological information for the models. Finally, the choice of predictive modeling algorithms also affected performance. Logistic regression models are currently mainstream due to their interpretability and stability. However, a few studies employing machine learning algorithms (e.g., SVMs) reported exceptionally high AUC values, suggesting that more complex nonlinear models may be better suited to mining the intricate mapping relationships between high-dimensional imaging features and Ki-67 expression. Nevertheless, the number of such studies is limited, and their results require further validation.
Although the summary AUC of 0.90 indicates high pooled diagnostic performance, the substantial heterogeneity in sensitivity and specificity warrants caution, as the estimates reflect averages rather than a universally reproducible clinical metric. The bivariate random-effects model accounts for between-study variance, but it does not remove clinical and technical differences among studies. Radiomics workflows are sensitive to variation in imaging protocols, reconstruction algorithms, and scanner hardware, and differences in magnetic field strength, slice thickness, and ultrasound systems may have contributed to the observed heterogeneity. Adherence to the Image Biomarker Standardization Initiative is important for improving technical reproducibility36. Standardized preprocessing, including isotropic voxel resampling and intensity normalization, together with post-extraction feature harmonization37, may improve cross-center generalizability. Future prospective studies should prioritize these methodological harmonization steps.
To bridge the gap between methodological research and clinical utility, it is essential to define the incremental value of radiomic models over conventional clinical and imaging biomarkers. Currently, established predictors such as serum alpha-fetoprotein levels and macroscopic tumor morphology, including tumor size and margin status, are standard components of clinical decision-making in HCC38. However, these conventional markers primarily reflect systemic tumor burden or macro-structural alterations. In contrast, radiomics extracts high-dimensional, subvisual digital features that quantify spatial heterogeneity at the pixel level, which is biologically linked to cellular proliferation and tissue density. Rather than replacing existing clinical diagnostic standards, the primary value of radiomics lies in its synergistic integration. Previous evidence indicated that predictive models combining radiomic signatures with conventional clinical risk factors consistently outperform clinical-only or radiomics-only models18,22. In clinical workflows, this integrated approach could serve as a noninvasive risk-stratification tool. For example, in patients with ambiguous clinical profiles, a joint clinical–radiomics model could refine the preoperative appraisal of Ki-67 expression, thereby informing further evaluation and treatment planning; prospective validation is required before such models guide clinical decisions.
Clinical translation is also constrained by overfitting in high-dimensional feature spaces, limited independent multicenter external validation, and restricted model interpretability. Most included studies used logistic regression, whereas a small number used nonlinear machine-learning or deep-learning approaches. The high AUC values reported by these exploratory cohorts suggest that advanced models warrant further study, but the limited number of studies does not establish a performance ceiling or superiority over logistic regression. Explainable artificial intelligence approaches may improve the interpretability of future models. This meta-analysis pooled radiomics-only and combined clinical–radiomics models, reflecting the current literature but introducing methodological heterogeneity. Future studies should report these approaches separately and validate them externally.
This study also has several limitations. First, the included cohorts were drawn almost exclusively from Chinese institutions, introducing potential geographic and etiological biases. Because the pathogenesis of HCC in East Asia is heavily dominated by chronic hepatitis B virus infection, whereas Western populations present a higher prevalence of hepatitis C virus, alcohol abuse, and nonalcoholic steatohepatitis, the clinical generalizability of these radiomics-based models to other global healthcare contexts remains to be fully verified. Second, the included studies were predominantly retrospective in design and mostly single-center, and although the QUADAS-2 assessment indicated an overall low risk of bias, potential selection bias and measurement bias remain possible. The interpretation criteria for Ki-67 were not fully unified across studies, and the chosen cutoff values varied considerably (from 10% to 50%). Although subgroup estimates were similar, this variability may still interfere with the comparability of the results. Additionally, differences in scanning parameters, slice thickness, and reconstruction algorithms among different imaging equipment were not standardized or corrected for. Although radiomics analysis pipelines typically include feature standardization steps, inconsistent scanning protocols remain a key challenge affecting feature reproducibility and model generalizability. Finally, the inclusion of too few studies using machine learning models limited comparative conclusions regarding the superiority of different algorithms. Future large-scale, prospective multicenter studies are needed. Based on unified imaging acquisition protocols and Ki-67 detection standards, these studies should further explore predictive models that integrate clinical–radiomics labels and employ more advanced deep learning architectures to facilitate the translation of radiomics from methodological research into a clinically useful tool.
This meta-analysis synthesizes current evidence on radiomics for predicting Ki-67 expression in HCC. Radiomic models showed high pooled diagnostic performance, but substantial between-study heterogeneity, predominantly retrospective single-center designs, and limited external validation constrain clinical interpretation. The findings support further evaluation of radiomics as a potential complement to pathological assessment; they do not establish clinical utility. Prospective, multicenter studies using standardized imaging and Ki-67 assessment are needed to evaluate generalizability and clinical application.
Disclosures
The authors have no conflicts of interest to declare.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Review Manager | Nordic Cochrane Centre | Version 5.3 | Risk-of-bias assessment and mapping |
| Stata | StataCorp | Version 16.0 | Diagnostic meta-analysis using the midas module |
References
- Philips CA, et al. Hepatocellular carcinoma in 2021: an exhaustive update. Cureus. 2021;13(11):e19274.
- Llovet JM, et al. Hepatocellular carcinoma. Nat Rev Dis Primers. 2021;7(1):6.
- Siegel RL, Miller KD, Wagle NS, Jemal A. Cancer statistics, 2023. CA Cancer J Clin. 2023;73(1):17-48.
- Feng F, Zhao Y. Hepatocellular carcinoma: prevention, diagnosis, and treatment. Med Princ Pract. 2024;33(5):414-23.
- Alawyia B, Constantinou C. Hepatocellular carcinoma: a narrative review on current knowledge and future prospects. Curr Treat Options Oncol. 2023;24(7):711-24.
- Andrés-Sánchez N, Fisher D, Krasinska L. Physiological functions and roles in cancer of the proliferation marker Ki-67. J Cell Sci. 2022;135(11):jcs258932.
- Hsu HC, et al. Expression of p53 gene in 184 unifocal hepatocellular carcinomas: association with tumor growth and invasiveness. Cancer Res. 1993;53(19):4691-4.
- Cao Y, et al. DNA topoisomerase IIα and Ki-67 are prognostic factors in patients with hepatocellular carcinoma. Oncol Lett. 2017;13(6):4109-16.
- Stroescu C, et al. Expression of p53, Bcl-2, VEGF, Ki-67, and PCNA and prognostic significance in hepatocellular carcinoma. J Gastrointestin Liver Dis. 2008;17(4):411-7.
- Jue C, et al. Vasculogenic mimicry in hepatocellular carcinoma contributes to portal vein invasion. Oncotarget. 2016;7(47):77987-97.
- Di Tommaso L, et al. Role of liver biopsy in hepatocellular carcinoma. World J Gastroenterol. 2019;25(40):6041-52.
- Gillies RJ, Kinahan PE, Hricak H. Radiomics: images are more than pictures, they are data. Radiology. 2016;278(2):563-77.
- Hu XX, et al. Whole-tumor MRI histogram analyses of hepatocellular carcinoma: correlations with Ki-67 labeling index. J Magn Reson Imaging. 2017;46(2):383-92.
- Yao Z, et al. Preoperative diagnosis and prediction of hepatocellular carcinoma: radiomics analysis based on multimodal ultrasound images. BMC Cancer. 2018;18(1):1089.
- Page MJ, et al. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ. 2021;372:n71.
- Whiting PF, et al. QUADAS-2: a revised tool for the quality assessment of diagnostic accuracy studies. Ann Intern Med. 2011;155(8):529-36.
- Chen Y, et al. Diagnostic value of Gd-EOB-DTPA-enhanced MRI for the expression of Ki-67 and microvascular density in hepatocellular carcinoma. J Magn Reson Imaging. 2020;51(6):1755-63.
- Ye Z, et al. Texture analysis on gadoxetic acid-enhanced MRI for predicting Ki-67 status in hepatocellular carcinoma: a prospective study. Chin J Cancer Res. 2019;31(5):806-17.
- Ye Z, et al. Preoperative prediction of hepatocellular carcinoma with highly aggressive characteristics using quantitative parameters derived from hepatobiliary phase MR images. Ann Transl Med. 2020;8(4):85.
- Wu H, et al. Prediction of the Ki-67 marker index in hepatocellular carcinoma based on CT radiomics features. Phys Med Biol. 2020;65(23):235048.
- Shi G, et al. Evaluation of multiple prognostic factors of hepatocellular carcinoma with intravoxel incoherent motion imaging by extracting the histogram metrics. Cancer Manag Res. 2020;12:6019-31.
- Fan Y, et al. Radiomic analysis of Gd-EOB-DTPA-enhanced MRI predicts Ki-67 expression in hepatocellular carcinoma. BMC Med Imaging. 2021;21(1):100.
- Jing M, et al. The benefit of apparent diffusion coefficient in evaluating the invasiveness of hepatocellular carcinoma. Front Oncol. 2021;11:719480.
- Hu X, et al. Added value of viscoelasticity for MRI-based prediction of Ki-67 expression of hepatocellular carcinoma using a deep learning combined radiomics (DLCR) model. Cancers (Basel). 2022;14(11):2575.
- Wu C, et al. Nomogram based on CT radiomics features combined with clinical factors to predict Ki-67 expression in hepatocellular carcinoma. Front Oncol. 2022;12:943942.
- Dong Y, et al. Prediction of histological grades and Ki-67 expression of hepatocellular carcinoma based on Sonazoid contrast-enhanced ultrasound radiomics signatures. Diagnostics (Basel). 2022;12(9):2175.
- Liu Z, et al. Nomogram development and validation to predict Ki-67 expression of hepatocellular carcinoma derived from Gd-EOB-DTPA-enhanced MRI combined with T1 mapping. Front Oncol. 2022;12:954445.
- Zhang L, et al. Noninvasive prediction of Ki-67 expression in hepatocellular carcinoma using machine learning-based ultrasomics: a multicenter study. J Ultrasound Med. 2023;42(5):1113-22.
- Huang Z, Zhou P, Li S, Li K. Prediction of the Ki-67 marker index in hepatocellular carcinoma based on dynamic contrast-enhanced ultrasonography with Sonazoid. Insights Imaging. 2022;13(1):199.
- Zhao YM, et al. Added value of CE-CT radiomics to predict high Ki-67 expression in hepatocellular carcinoma. BMC Med Imaging. 2023;23(1):138.
- Zhang D, et al. Predicting Ki-67 expression in hepatocellular carcinoma: nomogram based on clinical factors and contrast-enhanced ultrasound radiomics signatures. Abdom Radiol (NY). 2024;49(5):1419-31.
- Miller I, et al. Ki-67 is a graded rather than a binary marker of proliferation versus quiescence. Cell Rep. 2018;24(5):1105-12.e5.
- Lambin P, et al. Radiomics: the bridge between medical imaging and personalized medicine. Nat Rev Clin Oncol. 2017;14(12):749-62.
- Shia WC, et al. Effectiveness of evaluating tumor vascularization using 3D power Doppler ultrasound with high-definition flow technology in the prediction of the response to neoadjuvant chemotherapy for T2 breast cancer: a preliminary report. Phys Med Biol. 2015;60(19):7763-78.
- Luo Y, et al. Clinicopathological and prognostic significance of high Ki-67 labeling index in hepatocellular carcinoma patients: a meta-analysis. Int J Clin Exp Med. 2015;8(7):10235-47.
- Aguirre-Meneses H, et al. Radiomics and the Image Biomarker Standardisation Initiative (IBSI): a narrative review using a six-question map and implementation framework for reproducible imaging biomarkers. Cureus. 2025;17(10):e95335.
- Voitenko DA, et al. RiTex: harmonization of radiomic features based on Riemannian geometry. J Imaging. 2026;12(6):264.
- Jearth V, et al. Correlation of clinicopathological profile, prognostic factors, and survival outcomes with baseline alfa-fetoprotein levels in patients with hepatocellular carcinoma: a biomarker that is bruised but not broken. J Clin Exp Hepatol. 2022;12(3):841-52.