A preoperative CT-based radiomic model combining tumor and peritumoral features effectively predicts postoperative local recurrence from distant-metastasis progression after complete resection of T3–4 non-small cell lung cancer.
Method Article
Preoperative Computed Tomography Radiomics for Recurrence-Pattern Classification of T3–T4 Non-Small Cell Lung Cancer
In This Article
Summary
Abstract
Local recurrence after surgery remains a major clinical challenge in patients with T3 and T4 non-small cell lung cancer (NSCLC). To address the lack of a standardized preoperative imaging-based strategy for characterizing local recurrence, a computed tomography (CT)-based radiomic framework is presented to capture intratumoral and peritumoral heterogeneity and differentiate local recurrence from distant metastasis after R0 resection. The proposed protocol integrates radiomic features extracted from tumor and peritumoral regions on preoperative contrast-enhanced CT images. The application cohort comprised 103 patients with pathologically confirmed T3–T4, N0–2, M0 NSCLC who underwent surgery with R0 resection between January 2013 and December 2020. 33 developed local recurrence, and 70 developed distant metastasis. All preprocessing, feature selection, normalization, hyperparameter tuning, model fitting, and threshold determination were restricted to the training cohort. Tumor-only, peritumoral, and combined radiomic models were evaluated in a held-out validation cohort. Clinical characteristics, tumor location, preoperative laboratory parameters, and treatment information were collected. Tumor-specific and tumor-peritumoral combined radiomic representations were constructed and evaluated to characterize the behavior of the proposed framework. In the validation cohort, the peritumoral radiomic representation demonstrated improved discrimination compared with tumor-only features, while the combined tumor–peritumoral framework showed the most stable and consistent performance (AUC = 0.80). This protocol is a preliminary demonstration of a standardized CT radiomics workflow for differentiating postoperative failure patterns after R0 resection; multicenter external validation is required before clinical implementation.
Introduction
Complete surgical resection remains the standard treatment for patients with resectable non-small cell lung cancer (NSCLC), including those with locally advanced NSCLC (LA-NSCLC). Pathological margin status has immediate prognostic and therapeutic implications: R0 denotes no residual tumor, R1 denotes microscopic residual tumor, and R2 denotes macroscopic residual tumor. Incomplete resection is associated with adverse outcomes and may influence postoperative treatment1,2,3,4. Therefore, accurate characterization of local recurrence risk is a critical component of treatment planning in locally advanced NSCLC.
In current clinical practice, pathology examination is regarded as the reference standard method to determine the pathological margin. However, sampling bias exists due to the heterogeneous nature of tumors. Consequently, this method is widely recognized as imperfect, as there are small, yet significant, false-negative rates5. Furthermore, there is no guarantee that the lung tissue around the excised margin is free from malignant cells because histologic examination cannot study all aspects of the surgical margin of an excised tumor. These limitations highlight the need for complementary, noninvasive strategies capable of capturing macroscopic and spatial patterns of residual risk beyond microscopic sampling.
Radiomics enables high-throughput extraction of quantitative features from routine medical images and provides a systematic approach to characterizing tumor heterogeneity at a whole-lesion and perilesional level6. Previous radiomic studies in lung cancer have demonstrated its utility in outcome stratification across multiple treatment contexts, including surgery in early-stage NSCLC7, the stereotactic radiotherapy8, neoadjuvant therapy9, EGFR-TKI therapy10, and PD-(L)1 immunotherapy11 and systemic therapies. Peritumoral radiomics has also been used to quantify the immediate tumor–lung interface, including analyses based on 3-, 6-, and 9-mm expansions12. However, standardized workflows for comparing local recurrence with distant metastasis after R0 resection remain limited.
This protocol is intended for research datasets containing preoperative contrast-enhanced thin-section chest CT and complete pathological margin records. It is appropriate when the research objective is to compare local recurrence with distant metastasis progression after R0 resection. Therefore, a standardized workflow integrating intratumoral and 3-mm peritumoral radiomics was represented in T3–T4 NSCLC.
Protocol
The proposed CT-based radiomic protocol was designed to preoperatively differentiate local recurrence from distant metastasis in patients with T3-T4 NSCLC. The workflow consists of patient selection, CT image acquisition and preprocessing, region-of-interest segmentation, radiomic feature extraction and reduction, model construction, and performance evaluation (Figure 1A–C). The Ethics Committee of Jinling Hospital approved this retrospective study (approval number 2023DZKY-089-01) and waived the requirement for written informed consent. All software and tools used in this study are listed in the Table of Materials.
1. Patient selection and clinical data collection
- Identify consecutive patients with pathologically confirmed T3–T4 NSCLC.
NOTE: In this study, the authors have selected patients who underwent surgical resection at Jinling Hospital between January 2013 and December 2020 (Supplementary Figure 1). - Include patients who meet all of the following criteria: pathological confirmation of NSCLC; tumor staging of T3 or T4 according to the American Joint Committee on Cancer (AJCC) 8th edition; availability of preoperative contrast-enhanced chest CT acquired within 2 weeks before surgery; complete postoperative follow-up data with documented recurrence location and timing.
- Exclude patients with: R1 and R2 resection; Inadequate CT image quality due to motion artifacts or incomplete coverage; Missing or incomplete follow-up information regarding recurrence patterns.
2. Definition of labels and clinical endpoints
- Perform postoperative surveillance using serum tumor marker testing and chest CT every 3–6 months during the first 2 years and every 6 months thereafter.
- Define primary endpoints as a recurrence pattern. Have two board-certified thoracic radiologists independently review follow-up imaging while blinded to radiomic scores. Resolve disagreement by consensus.
- Use pathological confirmation or positron emission tomography/computed tomography when available.
- Distinguish any cases of second primary lung cancer using the Martini–Melamed criteria and exclude them from local-recurrence events.
- Assign patients to groups as follows:
- Local-recurrence group: patients with R0 resection who developed recurrence at a prespecified local site during follow-up.
NOTE: Local recurrence is recurrence at the bronchial stump or parenchymal resection margin, ipsilateral hilar or mediastinal lymph nodes contiguous with the original tumor or resection bed. - Count synchronous local and distant recurrence in the local-recurrence group.
- Distant metastasis group comparator group: patients with R0 resection who developed distant metastasis without local recurrence.
- Local-recurrence group: patients with R0 resection who developed recurrence at a prespecified local site during follow-up.
- Classify recurrence confined to distant organs or the contralateral thorax without any local component as distant metastasis.
3. Clinical and semantic feature collection
- Retrieve clinical variables from the electronic medical record system, including preoperative laboratory parameters, pathological findings, and treatment information.
- Collect the following variables for each patient: age, sex, smoking status, serum tumor markers, pathological stage, histological subtype, and surgical procedures.
- Independently evaluate semantic imaging features reflecting tumor location and invasion of adjacent anatomical structures using preoperative CT images.
- Assign two board-certified thoracic radiologists to independently review all cases. Resolve discrepancies in semantic feature assessment through consensus discussion.
4. CT image acquisition
- Acquire chest CT images in the transverse plane, including non-contrast, arterial, and portal venous phases, using multi-detector CT scanners.
NOTE: Contrast-enhanced chest CT examinations were performed using four multidetector CT scanners from Siemens Healthineers: SOMATOM Definition, SOMATOM Definition Flash, SOMATOM Emotion, and SOMATOM Perspective. Depending on the scanner and institutional protocol, detector configurations included 16 × 0.6 mm, 64 × 0.6 mm, or 2 × 64 × 0.6 mm. Images were acquired at 120–130 kVp using automatic tube-current modulation (approximately 62–663 mA), with a pitch of 0.5–0.8, a rotation time of 0.5 s, a field of view of approximately 300–400 mm, and a matrix of 512 × 512. The acquisition section thickness was 1.0–1.5 mm. Images used for radiomic analysis were reconstructed at a section thickness of 1.0–1.5 mm with an interval of 1.0–1.5 mm using a medium-smooth kernel (B30f or B31f). A nonionic iodinated contrast agent (300–370 mg I/mL) was administered intravenously at a dose of approximately 1.0–1.5 mL/kg, with an injection rate of 2.5–3.5 mL/s, followed by a 30–40 mL saline flush. - Set acquisition parameters and reconstruction parameters. Perform gated automatic scanning at the beginning of the arterial phase.
- Select the aortic arch as the region of interest and set the triggering threshold to 60 HU.
Use thin-slice reconstruction for all image series. - Export arterial-phase CT images in Digital Imaging and Communications in Medicine (DICOM) format for subsequent preprocessing and analysis. Detailed acquisition parameters are summarized in Supplementary Table 1.
5. Image preprocessing and anonymization
- Anonymize all CT images according to the Health Insurance Portability and Accountability Act Safe Harbor guidelines.
- Upload anonymized arterial-phase CT images to the Deepwise Multimodal Research Platform, version 3.1.3, which integrates Pyradiomics (version 3.0.1) and Scikit-learn (version 0.22)13,14.
- On the radiomics platform, select “Sample”, choose the DICOM series as input, and load the corresponding segmentation mask.
6. Tumor and peritumoral segmentation
- Perform semi-automatic segmentation13 of primary lung tumors on arterial-phase CT images.
Manually review and adjust segmentations by a radiologist with 9 years of experience in thoracic imaging to ensure anatomical accuracy. - Review the mask in axial, coronal, and sagittal planes. Manually correct the boundary to include viable tumor and exclude adjacent atelectasis, vessels, airways, pleural effusion, and chest wall unless directly invaded by tumor. Save the final mask using the study identifier.
- Automatically generate peritumoral regions by expanding the tumor boundary outward by 1 mm, 3 mm, and 5 mm in all directions, excluding non-lung structures when applicable
- Before feature extraction, CT images were resampled to an isotropic voxel spacing of 1 × 1 × 1 mm3. Image intensities were interpolated using a B-spline algorithm, whereas segmentation masks were resampled using nearest-neighbor interpolation to preserve their binary labels.
7. Radiomic feature extraction
- Extract radiomic features from tumor regions, including shape, first-order intensity, and texture features, and so on, following Image Biomarker Standardization Initiative guidelines.
- Extract the same categories of radiomic features from the peritumoral regions.
8. Dataset partitioning and r.adiomic feature reduction
- Before any preprocessing, feature reduction, or model development, randomly divide the full dataset into a training cohort and a held-out validation cohort at a ratio of 7:3 by stratified sampling according to recurrence pattern, using fixed random seed 1.
- Lock the validation cohort and do not use it for feature selection, hyperparameter tuning, or threshold determination.
NOTE: Missing and infinite values were checked within the training cohort. No missing or infinite values were identified; therefore, no imputation was performed. Assess segmentation reproducibility.- Select 20% of the cohort via stratified random sampling by recurrence pattern, using the training-set random seed 1. Confirm that the selected subset preserves the local-recurrence/distant metastasis distribution.
- Have the first reader repeat segmentation after an interval of 2 weeks, and have a second reader (a radiologist with 6 years of experience in thoracic imaging) segment the same cases independently.
- Blind both readers to clinical information, pathological findings, recurrence pattern, and model outputs.
- Calculate inter- and intra-reader single measure, absolute-agreement intraclass correlation coefficients (ICCs). Retain features only when both inter-reader and intra-reader ICCs are at least > 0.8.
- Perform pairwise correlation analysis and remove one feature from each highly correlated pair when the correlation coefficient exceeds 0.90.
- Apply L1-regularized linear models to select informative features, with the regularization parameter controlling feature sparsity.
9. Model construction and evaluation
- Using the finalized feature sets, construct the intratumoral, 3-mm peritumoral, and combined Linear SVC models within the training cohort.
- Tune model hyperparameters using stratified 10-fold cross-validation restricted to the training cohort.
NOTE: The Linear SVC models were implemented using scikit-learn version 0.22 with an L1 penalty, squared-hinge loss, dual = False, a convergence tolerance of 1 × 10⁻4, a maximum of 1,000 iterations, and intercept fitting enabled. The regularization parameter C was optimized on the training cohort using stratified 10-fold cross-validation with a random seed of 1. After hyperparameter selection, each model was refitted using the complete training cohort and applied directly to the held-out validation cohort. No resampling or class-weight adjustment was used. - Apply each locked model directly to the held-out validation cohort without refitting, feature reselection, recalibration, or threshold optimization.
- Assess model performance using the area under the receiver operating characteristic curve (AUC), sensitivity, specificity, and accuracy.
10. Statistical analysis
- Compare continuous variables using appropriate parametric or nonparametric tests based on data distribution.
- Compare categorical variables using chi-square or Fisher’s exact tests.
- Determine the classification threshold by maximizing the Youden index in the training cohort only and apply the locked threshold unchanged to the held-out validation cohort. Calculate bootstrapped confidence intervals.
- Perform all statistical analyses using SPSS (version 25), with two-sided p values < 0.05 considered statistically significant.
Results
Application cohort characteristics
Among the initially eligible patients, 12 patients with R1 resection were excluded, and no R2 resections were identified. Consequently, the final cohort comprised 103 patients who underwent R0 resection. The proposed radiomic protocol was applied to a cohort of 103 patients with surgically treated T3–T4 NSCLC (60.6 ± 8.6 years; 82.5% male), including 33 with postoperative local recurrence and 70 with distant metastasis. Among the 33 patients with local recurrence, 17 (51.5%) had pathological confirmation, whereas the remaining 16 (48.5%) were diagnosed based on serial follow-up CT findings and clinical consensus. No local recurrence was confirmed solely by PET/CT. Sixty-one patients (59.2%) had pathological T3 disease, and 42 (40.8%) had T4 disease. None of the clinical or pathological variables in Table 1 differed significantly between the local-recurrence and distant metastasis groups (all p ≥ 0.064).
Assessment of semantic imaging and treatment-related variables
Tumor lobe, central versus peripheral location, main-bronchus involvement, and large-vessel involvement did not differ significantly between the local-recurrence group and the distant metastasis group (all p ≥ 0.272; Table 2). Neoadjuvant therapy, immunotherapy, and radiotherapy distributions were similar between the two R0 progression-pattern groups (all p ≥ 0.742; Table 3). Targeted therapy was less frequent in the local-recurrence group than in the distant metastasis group (2/33 [6.1%] versus 15/70 [21.4%]; raw p = 0.0499). Because postoperative treatment may influence the recurrence pattern, this imbalance should be treated as a potential confounder rather than evidence of a causal effect.
Follow-up patterns and endpoint distribution
Among the 103 patients with a negative resection margin, 33 had local recurrence (mean progression-free survival (PFS) of 16.36 ± 14.741 months), and 70 had distant metastasis (mean PFS of 11.39 ± 11.388 months). There was no statistical difference between the local recurrence and distant metastasis groups (p = 0.131). Although no significant difference in progression-free survival was observed between the two recurrence patterns, the intended use of the present approach is to investigate whether preoperative imaging can distinguish the anatomical pattern of first disease progression after R0 resection. Such preoperative risk stratification may facilitate the appropriate application of local treatment in patients at high risk of local recurrence and potentially improve their outcomes; however, this clinical utility requires further validation in prospective studies.
Tumor and peritumor radiomic features behavior
Reproducibility was assessed in a subset of 25 patients. After ICC-based filtering, 1,820 of the 2,207 intratumoral radiomic features and 1,856 of the 2,211 3-mm peritumoral radiomic features were retained for subsequent analysis. Variance filtering removed 124 intratumoral and 120 3-mm peritumoral features. Subsequently, pairwise correlation filtering with a threshold of 0.90 removed 1,357 of the remaining intratumoral features and 1,395 of the remaining peritumoral features, leaving 339 and 341 features, respectively, for L1-regularized feature selection. The L1 procedure ultimately selected 9 intratumoral and 12 peritumoral features for model construction. Radiomic features extracted from tumor, peritumoral, and combined regions exhibited distinct predictive behaviors. In the validation cohort, the tumor, 3-mm peritumoral, and combined models achieved AUCs of 0.71 (95% CI, 0.61–0.81), 0.75 (95% CI, 0.65–0.85), and 0.80 (95% CI, 0.71–0.89), respectively (Table 4 and Figure 2A). In the peritumoral-distance sensitivity analysis, the 1-, 3-, and 5-mm models achieved apparent AUCs of 0.62, 0.75, and 0.59, respectively. Compared with the 3-mm model, the AUC difference was not statistically significant for 1 mm (ΔAUC = −0.13, p = 0.078) but was significant for 5 mm (ΔAUC = −0.16, p = 0.040) (Supplementary Table 1).
After excluding 17 patients who received targeted therapy before the first disease progression, 86 patients remained, including 31 with local recurrence and 55 with distant-only progression. The fusion model achieved an AUC of 0.80 (95% CI, 0.70–0.89), which was consistent with that in the primary analysis (AUC, 0.80; ΔAUC, −0.001; 95% CI, −0.034 to 0.033; p = 0.948). These findings suggested that the fusion model's performance was not materially affected by targeted therapy administered before disease progression.
Comparative evaluation and clinical utility of the protocol
Pairwise DeLong tests did not identify statistically significant differences between the tumor and 3-mm peritumoral models (p = 0.533), the tumor and combined models (p = 0.168), or the 3-mm peritumoral and combined models (p = 0.439). In decision curve analysis, the tumor, 3-mm peritumoral, and combined models yielded greater net benefit than both treat-all and treat-none reference strategies across threshold probabilities of 0.19–0.51, 0.18–0.56, and 0.17–0.59, respectively (Figure 2B). At a predicted-probability threshold of 0.20, the combined model achieved a sensitivity of 66.7% and a specificity of 77.1%. These ranges describe apparent utility in the selected progression cohort and are not validated treatment thresholds. As shown in Figure 3A–D, the two solid lesions in A and B were correctly classified by the model, whereas the lesions in C and D were misclassified. Both misclassified lesions contained areas of intratumoral necrosis, which may have altered the attenuation distribution and texture heterogeneity captured by the radiomic features, thereby contributing to the discordant predictions.
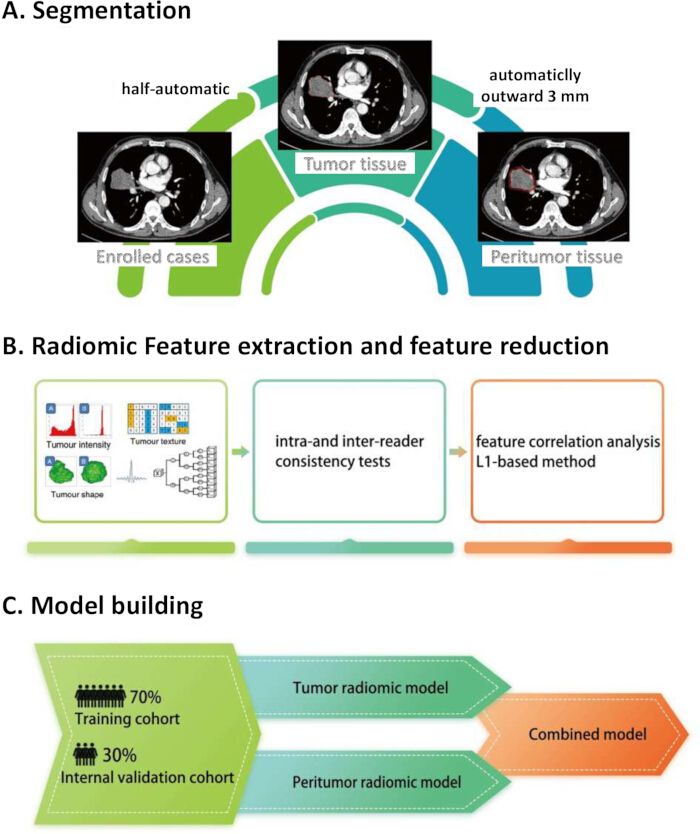
Figure 1: Workflow of tumor segmentation, radiomic feature selection, and model development. (A) The primary tumor was segmented semiautomatically. The intratumoral region of interest was defined as the tumor tissue, and the peritumoral region was generated by expanding the tumor boundary outward by 3 mm and excluding the tumor itself. (B) Intratumoral and peritumoral radiomic features were extracted, evaluated for intra- and inter-reader reproducibility, and reduced through correlation analysis and L1-regularized feature selection. (C) Eligible patients were randomly divided into a training cohort (70%) and an internal validation cohort (30%). Separate tumor and peritumoral radiomic models were constructed and integrated into a combined model. Abbreviations: CT = computed tomography; L1 = least absolute shrinkage and selection operator-based regularization. Figure 1 was created by the authors using Microsoft PowerPoint, and no copyright permissions were required. Please click here to view a larger version of this figure.
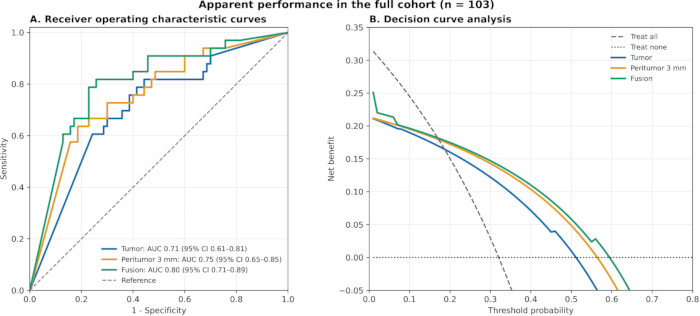
Figure 2: Receiver operating characteristic curves and decision curve analysis of the radiomic models. (A) Receiver operating characteristic curves of the tumor, 3–mm peritumoral, and combined models for differentiating local recurrence from distant metastasis in the validation cohort. The respective AUCs were 0.71 (95% CI, 0.61–0.81), 0.75 (95% CI, 0.65–0.85), and 0.80 (95% CI, 0.71–0.89); 95% CIs were estimated using 1,000 bootstrap resamples. (B) Decision curve analysis of the three models across threshold probabilities of 0.01–0.80. Treat-all and treat-none strategies are shown for reference. Abbreviations: AUC = area under the receiver operating characteristic curve; CI = confidence interval; DCA = decision curve analysis; ROC = receiver operating characteristic. Please click here to view a larger version of this figure.
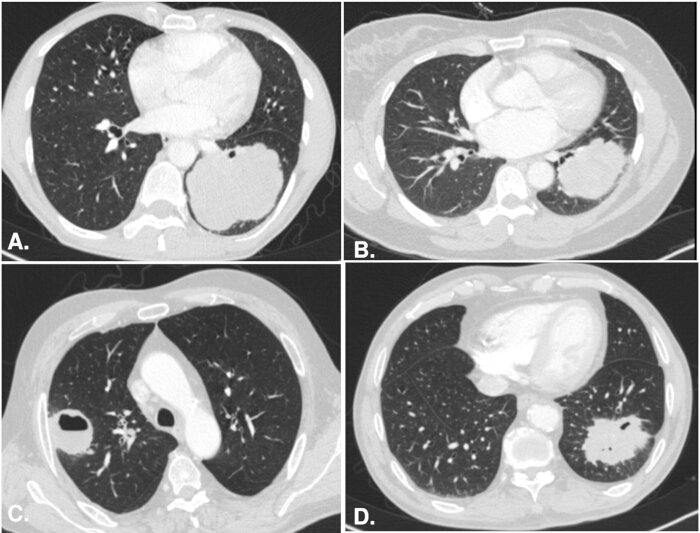
Figure 3: Representative figure of correctly and incorrectly classified cases from the combined radiomic model. (A) Correctly classified local recurrence in a 50-year-old man with left-lung squamous cell carcinoma having developed local recurrence at 4 months. (B) Correctly classified distant-only progression in a 44-year-old woman with left lower-lobe adenocarcinoma and developed osseous metastasis at 31 months without local recurrence. (C) A false-negative example in which local recurrence was classified as distant-only progression. (D) A false-positive example in which distant-only progression was classified as local recurrence. Please click here to view a larger version of this figure.
Table 1: Clinical and pathological characteristics of patients with local recurrence and distant metastasis. The analysis included 103 patients: 33 with local recurrence and 70 with distant metastasis. Data are presented as mean ± standard deviation or n (column %). Age was compared using the independent-samples Student's t-test. Categorical variables were compared using the Pearson chi-square test or Fisher's exact test when any expected cell count was <5. *Raw p < 0.05. Abbreviations: ADC = adenocarcinoma; SCC = squamous cell carcinoma; SD = standard deviation; TNM = tumor-node-metastasis. Please click here to download this Table.
Table 2: Location and involvement characteristics of patients with local recurrence and distant metastasis. The analysis included 103 patients: 33 with local recurrence and 70 with distant metastasis. Data are presented as n (column %). Categorical variables were compared using the Pearson chi-square test or Fisher's exact test when any expected cell count was <5. No data were missing. *Raw p < 0.05. Abbreviations: CT = computed tomography. Please click here to download this Table.
Table 3: Perioperative and postoperative treatment strategies among patients with local recurrence and distant metastasis. The analysis included 103 patients: 33 with local recurrence and 70 with distant metastasis. Data are presented as n (column %). Categorical variables were compared using the Pearson chi-square test or Fisher's exact test when any expected cell count was <5. No data were missing. *Raw p < 0.05. Please click here to download this Table.
Table 4: Performance of the radiomic, peritumor, and combined models for differentiating local recurrence from distant metastasis. The analysis included 103 patients: 33 with local recurrence and 70 with distant metastasis. The 95% CIs were estimated using 1,000 bootstrap resamples. Abbreviations: AUC = area under the receiver operating characteristic curve; CI = confidence interval. Please click here to download this Table.
Supplementary Figure 1: Flowchart of patient selection. Patients who underwent at least one chest CT examination between 2013 and 2020 and had pathology reports containing the terms “lung” and “cancer” were screened. After exclusions based on pathology reports and hospital information system records, 238 patients remained. A further 45 patients were excluded because of unavailable pretreatment CT images (n = 39), inflammatory carcinoma (n = 4), or CT artifacts affecting image analysis (n = 2). Finally, patients with R1 resection (n = 12), loss to follow-up (n = 43), or no progression by the end of follow-up (n = 35) were excluded, yielding 103 patients for the training and validation sets. CT, computed tomography; HIS, hospital information system; R1, microscopically margin-positive resection. Please click here to download this file.
Supplementary Table 1: Sensitivity analysis of model performance across different peritumoral expansion distances. Model discrimination was evaluated in the validation cohort using peritumoral regions of 1, 3, and 5 mm. The 3-mm peritumoral model served as the reference. ΔAUC represents the difference in AUC relative to the 3-mm model, and p values were calculated using the two-sided DeLong test. AUC, area under the receiver operating characteristic curve; CI, confidence interval. Please click here to download this file.
Discussion
This work presents a CT-based radiomic protocol to preoperatively differentiate local recurrence from distant metastasis following R0 resection in patients with T3–T4 NSCLC. Rather than focusing solely on outcome prediction, the proposed framework operationalizes local recurrence risk by integrating intratumoral and peritumoral radiomic representations derived from routine contrast-enhanced CT images. The protocol demonstrated stable performance in a representative surgical cohort, with the combined tumor–peritumoral model achieving the highest AUC. Several preoperative approaches have been investigated for estimating postoperative recurrence risk in NSCLC, including clinicoradiologic models, metabolic parameters derived from 18F-FDG PET/CT, handcrafted CT radiomics, and deep learning. PET/CT-derived metabolic tumor volume and total lesion glycolysis provide prognostic information after surgical resection but require an additional molecular-imaging examination and are affected by acquisition and reconstruction protocols15. CT-based radiomic and deep-learning models can estimate recurrence risk or disease-free survival noninvasively16, and previous studies have demonstrated the value of incorporating peritumoral information or combining imaging with clinical variables17,18. However, these previous approaches primarily focused on whether or when recurrence occurred, particularly in early-stage lung adenocarcinoma, rather than on the anatomical pattern of the first disease progression. The potential advantage of the present framework is that it uses routinely acquired preoperative contrast-enhanced CT and integrates intratumoral and immediately adjacent peritumoral information to distinguish local recurrence from distant metastasis progression after R0 resection in patients with T3–T4 NSCLC.
From a methodological perspective, the clinical motivation for this protocol arises from the intrinsic limitations of pathological margin assessment. Although histopathology remains the reference standard, it is inherently constrained by sampling bias and incomplete spatial coverage of the surgical margin. Studies have found that for stage IA NSCLC, the local recurrence rate after wedge resection is significantly higher than that after lobectomy19. This is mainly thought to be due to the missed diagnosis of residual tumor cells in the surgical margin and the high local recurrence rate caused by incomplete resection. Additionally, it is possible to observe the tumor cells in the surgical margin by reviewing the pathological sections of patients with local recurrent NSCLC20. Prior surgical series have shown that incomplete resection and occult residual disease substantially increase local recurrence risk and adversely affect long-term survival, whereas imaging can interrogate macroscopic and spatial tumor characteristics before surgery. The present protocol should therefore be viewed as a complementary research methodology for characterizing recurrence patterns rather than a substitute for pathological margin examination. This distinction avoids retrospectively labeling R0 local recurrence as evidence of a positive or intrinsically high-risk surgical margin.
A central design element of the proposed framework is the explicit incorporation of peritumoral radiomic features. The prespecified 3-mm ring samples the immediate tumor–lung interface, where imaging patterns may reflect invasion, desmoplastic reaction, edema, vascular change, or tumor–host interactions. In the sensitivity analysis, the apparent AUCs for the 1-, 3-, and 5-mm models were 0.62, 0.75, and 0.59, respectively. The 1-mm model was numerically lower than the 3-mm model, with no statistically significant difference between them, whereas the 5-mm model performed significantly worse. These findings support the prespecified 3-mm definition in this cohort but do not establish 3 mm as a universally optimal distance. Wider rings may include non-lung parenchyma or adjacent anatomical structures in T3–T4 tumors.
Postoperative treatment may alter the location and timing of recurrence and, therefore, remains a potential source of confounding. Targeted therapy was less frequent in the local-recurrence group than in the distant metastasis group (6.1% versus 21.4%; raw p = 0.0499), whereas the other treatment distributions did not differ significantly. In a sensitivity analysis excluding the 17 patients who received targeted therapy before disease progression, the fusion model maintained an AUC of 0.80 (95% CI, 0.70–0.89), which was nearly identical to that of the primary analysis (ΔAUC = −0.001; 95% CI, −0.034 to 0.033; p = 0.948). These findings suggest that the discriminatory performance of the fusion model was not materially driven by pre-progression targeted therapy.
Feature stability and reproducibility are critical considerations in radiomic methodology. In this protocol, feature extraction adhered to the Image Biomarker Standardization Initiative guidelines21. Robustness was systematically evaluated using inter- and intra-reader reproducibility testing. The most influential features in the combined model were predominantly derived from the peritumoral region, reinforcing the methodological importance of standardized peritumoral delineation. These steps collectively enhance the reliability and transferability of the proposed protocol.
Several limitations of the protocol should be acknowledged. First, the framework was developed and validated using data from a single institution, and patient selection may reflect institutional surgical practices. Second, follow-up intervals were not uniform, and loss to follow-up may have affected the characterization of recurrence. Third, while the protocol identifies radiomic features associated with margin-related recurrence risk, it does not directly elucidate the underlying pathological mechanisms. Future work should focus on multicenter validation, harmonization across imaging platforms, and integration with pathological and molecular correlates to further refine the biological interpretability of the radiomic features. In conclusion, this study introduces a standardized CT-based radiomic protocol for preoperative characterization of recurrence pattern in T3-T4 NSCLC. By explicitly integrating peritumoral radiomic information, the framework is intended as a reproducible research protocol; multicenter external validation and evaluation in an unselected postoperative cohort are required before clinical implementation or treatment decision-making.
Disclosures
The authors have no conflict of interest. No generative artificial intelligence tool was used to create or modify figures in this manuscript.
Acknowledgements
We thank LetPub (www.letpub.com.cn) for its linguistic assistance during the preparation of this manuscript. This work was supported by the Science and Technology Innovation 2030-Major Projects (2020AAA0109500).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Deepwise Multimodal Research Platform | Deepwise | version 3.1.3 | used for segmentation and radiomic feature extraction and model construction |
| Python | Python Software Foundation | https://www.python.org | version 3.9.13 |
| R | R Foundation | https://www.r-project.org | version 4.3.2 |
| Somatom Definition | Simens | none | Used for CT image acquisition |
| Somatom Definition Flash | Simens | none | Used for CT image acquisition |
| Somatom Emotion | Simens | none | Used for CT image acquisition |
| Somatom Perspective | Simens | none | Used for CT image acquisition |
References
- Ohguri T, Yahara K, Moon SD, Yamaguchi S, Imada H, et al. Postoperative radiotherapy for incompletely resected non-small cell lung cancer: clinical outcomes and prognostic value of the histological subtype. J Radiat Res. 2012;53(2):319-325.
- Hancock JG, Rosen JE, Antonicelli A, Moreno A, Kim AW, et al. Impact of adjuvant treatment for microscopic residual disease after non-small cell lung cancer surgery. Ann Thorac Surg. 2015;99(2):406-413.
- Sawabata N, Maeda H, Matsumura A, Ohta M, Okumura M; Thoracic Surgery Study Group of Osaka University. Clinical implications of the margin cytology findings and margin/tumor size ratio in patients who underwent pulmonary excision for peripheral non-small cell lung cancer. Surg Today. 2012;42(3):238-244.
- Wang EH, Corso CD, Rutter CE, Park HS, Chen AB, et al. Postoperative radiation therapy is associated with improved overall survival in incompletely resected stage II and III non-small-cell lung cancer. J Clin Oncol. 2015;33(25):2727-2734.
- Sawabata N, Funaki S, Nakagiri T, Shintani Y, Inoue M, et al. Clinical implications of the margin cytology findings and margin/tumor size ratio in patients who underwent pulmonary wedge resection for peripheral non-small cell lung cancer. J Thorac Oncol. 2012;7(11):S473.
- Gillies RJ, Kinahan PE, Hricak H. Radiomics: images are more than pictures, they are data. Radiology. 2016;278(2):563-577.
- Huang Y, Liu Z, He L, Chen X, Pan D, et al. Radiomics signature: a potential biomarker for the prediction of disease-free survival in early-stage (I or II) non-small cell lung cancer. Radiology. 2016;281(3):947-957.
- Yang H, Wang L, Shao G, Dong B, Wang F, et al. A combined predictive model based on radiomics features and clinical factors for disease progression in early-stage non-small cell lung cancer treated with stereotactic ablative radiotherapy. Front Oncol. 2022;12:967360.
- She Y, He B, Wang F, Zhong Y, Wang T, et al. Deep learning for predicting major pathological response to neoadjuvant chemoimmunotherapy in non-small cell lung cancer: a multicentre study. EBioMedicine. 2022;86:104364.
- Wang S, Yu H, Gan Y, Wu Z, Li E, et al. Mining whole-lung information by artificial intelligence for predicting EGFR genotype and targeted therapy response in lung cancer: a multicohort study. Lancet Digit Health. 2022;4(5):e309-e319.
- Sun R, Limkin EJ, Vakalopoulou M, Dercle L, Champiat S, et al. A radiomics approach to assess tumour-infiltrating CD8 cells and response to anti-PD-1 or anti-PD-L1 immunotherapy: an imaging biomarker, retrospective multicohort study. Lancet Oncol. 2018;19(9):1180-1191.
- Chen Q, Shao J, Xue T, Peng H, Li M, et al. Intratumoral and peritumoral radiomics nomograms for the preoperative prediction of lymphovascular invasion and overall survival in non-small cell lung cancer. Eur Radiol. 2023;33(2):947-958.
- Qi LL, Wang JW, Yang L, Huang Y, Zhao SJ, et al. Natural history of pathologically confirmed pulmonary subsolid nodules with deep learning-assisted nodule segmentation. Eur Radiol. 2021;31(6):3884-3897.
- Qi LL, Wu BT, Tang W, Zhou LN, Huang Y, et al. Long-term follow-up of persistent pulmonary pure ground-glass nodules with deep learning-assisted nodule segmentation. Eur Radiol. 2020;30(2):744-755.
- Kim K, Kim SJ, Kim IJ, Kim YS, Pak K, et al. Prognostic value of volumetric parameters measured by F-18 FDG PET/CT in surgically resected non-small-cell lung cancer. Nucl Med Commun. 2012;33(6):613-620.
- Kim H, Goo JM, Lee KH, Kim YT, Park CM. Preoperative CT-based deep learning model for predicting disease-free survival in patients with lung adenocarcinomas. Radiology. 2020;296(1):216-224.
- Christie JR, Daher O, Abdelrazek M, Romine PE, Malthaner RA, et al. Predicting recurrence risks in lung cancer patients using multimodal radiomics and random survival forests. J Med Imaging (Bellingham). 2022;9(6):066001.
- Lan H, Wei C, Xu F, Yang E, Lu D, et al. 2.5D peritumoural radiomics predicts postoperative recurrence in stage I lung adenocarcinoma. Front Oncol. 2024;14:1382815.
- Koike T, Koike T, Yoshiya K, Tsuchida M, Toyabe S. Risk factor analysis of locoregional recurrence after sublobar resection in patients with clinical stage IA non-small cell lung cancer. J Thorac Cardiovasc Surg. 2013;146(2):372-378.
- Sawabata N, Matsumura A, Ohota M, Maeda H, Hirano H, et al. Cytologically malignant margins of wedge resected stage I non-small cell lung cancer. Ann Thorac Surg. 2002;74(6):1953-1957.
- Zwanenburg A, Vallières M, Abdalah MA, Aerts HJWL, Andrearczyk V, et al. The Image Biomarker Standardization Initiative: standardized quantitative radiomics for high-throughput image-based phenotyping. Radiology. 2020;295(2):328-338.