This protocol describes a method to evaluate segmented versus single-segment regional citrate anticoagulation in pediatric hemodialysis, providing a standardized approach for clinical investigation.
Method Article
Effectiveness of Segmented Regional Citrate Anticoagulation in Paediatric Hemodialysis
In This Article
Summary
Abstract
This study retrospectively compared the effectiveness and safety of segmented regional citrate anticoagulation (S-RCA) and single-segment RCA (SS-RCA) in pediatric hemodialysis. Fifty-two patients were divided into S-RCA (n = 26) and SS-RCA (n = 26) groups. Treatment parameters, ionized calcium, pH, bicarbonate, coagulation in the dialyzer and venous air trap, blood urea nitrogen (BUN), creatinine (Cr), electrolytes, total calcium, coagulation function, and complications were assessed. No significant differences were found in blood flow, dialysate flow, or ultrafiltration between groups. While anticoagulation efficacy in the dialyzer was similar, venous air trap anticoagulation was significantly better with S-RCA (p = 0.030). Post-dialysis, BUN and Cr levels decreased more significantly in the S-RCA group (p < 0.001). Electrolytes, total calcium, and coagulation parameters remained stable, with no severe adverse events. It was concluded that S-RCA provides superior anticoagulation efficacy and dialysis adequacy compared to SS-RCA in pediatric hemodialysis, offering an alternative anticoagulation regimen for this population.
Introduction
Hemodialysis (HD) is the removal of metabolic wastes, harmful substances, and excess water from the blood using the principles of diffusion and convection, and is one of the most commonly used renal replacement therapies for patients with end-stage renal disease, as well as for the treatment of acute kidney injury, drug or toxic poisoning1. The effectiveness and safety of extracorporeal anticoagulation ensure safe and effective hemodialysis2. The main anticoagulation methods for hemodialysis include: heparin-free, normal heparin anticoagulation, low molecular heparin anticoagulation, citrate anticoagulation, and so on. Currently, heparin anticoagulation is most commonly used in hemodialysis, but it increases the risk of bleeding and can lead to heparin-induced thrombocytopenia (HIT)3.
Regional citrate Anticoagulation (RCA) refers to the pumping of citrate in front of the dialyser, chelating the serum ionic calcium in the extracorporeal circulation, blocking the conversion of prothrombin to thrombin, to achieve the effect of anticoagulation, and at the same time, citrate can be metabolised in the body through the tricarboxylic acid cycle to physiological metabolites, with good biocompatibility4. RCA has a good effect of extracorporeal anticoagulation, and can avoid the occurrence of bleeding complications, but also has the advantages of improving the biocompatibility of the filtration membrane, etc., does not affect the coagulation status of the patient's body, etc., in recent years in the critical bleeding tendency of the patient, heparin or other contraindications to anticoagulants in patients has been widely used5,6. Children's hemodialysis patients are mainly suffering from acute kidney injury, acute poisoning, and other critical illnesses, often combined with coagulation dysfunction. RCA can effectively reduce the risk of bleeding, and it is worth promoting the application of in children's hemodialysis5,7.
RCA has obvious advantages in the application of hemodialysis in patients with critical bleeding tendency, and most of the development so far adopts a simplified way, that is, the use of calcium-containing dialysate for citrate anticoagulation, which simplifies the operation, and does not need additional calcium supplementation, but the simplified RCA method, anticoagulation effect is often not satisfactory, and often in the Venous air trap of coagulation8,9. Traditional RCA, because the citrate root in the blood will be removed when passing through the dialyser, and at the same time the calcium ions in the calcium-containing dialysis fluid will also diffuse into the blood, increasing the calcium ion concentration in the circuit, leading to a reduction in the anticoagulation effect, and coagulation is often seen in the Venous air traps, which not only shortens the time of the patient's effective treatment, increases the cost of the treatment, but also results in a greater loss of blood10.
Based on the different infusion sites of citrate, regional citrate anticoagulation can be classified into the "single-segment" mode (SS-RCA) and the "segmented" mode (S-RCA). S-RCA has been reported in the literature to be safer and more efficacious11, but there are fewer reports of clinical studies on the S-RCA technique in paediatric hemodialysis. This study was conducted to investigate the clinical application of S-RCA in pediatric hemodialysis. By comparing it with SS-RCA, we aimed to evaluate its feasibility, efficacy, and safety in this specific population. The primary objectives were to assess its impact on circuit anticoagulation, particularly in the venous air trap, and its effect on dialysis adequacy, as measured by the clearance of small molecules such as BUN and Cr. It was hypothesized that S-RCA would provide superior anticoagulation and dialysis adequacy compared to SS-RCA, thereby offering a safe and effective alternative anticoagulation strategy for children undergoing hemodialysis.
Therefore, the primary objective of this study was to evaluate the feasibility, efficacy, and safety of S-RCA compared to SS-RCA in a pediatric hemodialysis population. It was hypothesized that S-RCA would provide superior anticoagulation, particularly in the venous circuit, and achieve better dialysis adequacy without increasing the risk of adverse events, thereby offering an optimized anticoagulation strategy for children. Figure 1 illustrates a design flow chart for the study.
Protocol
This protocol for a retrospective comparative study was approved by the Ethics Committee of Guiyang Maternal and Child Health Hospital (Guiyang Children's Hospital) (Approval No.: 2022-36). The study was conducted in accordance with the principles of the Declaration of Helsinki. Signed informed consent was obtained from the legal guardians of all pediatric participants. The reagents and the equipment used are listed in the Table of Materials.
1. Patient selection and group allocation
- Identify eligible patients
NOTE: A retrospective review of electronic medical records was conducted for all pediatric patients who underwent hemodialysis for acute kidney injury (AKI) and end-stage renal disease (ESRD) at our institution between January 2023 and February 2025.- Consider the following inclusion criteria: (1) clinical indications for hemodialysis; (2) predisposition to bleeding, but normal coagulation function; and (3) signed informed consent from a legal guardian.
- Consider the following exclusion criteria: severe hepatic failure, irreversible hypoxemia (PaO2 < 60 mmHg), hypotensive shock, severe acid-base balance disorders, hypernatremia, or the presence of coagulation abnormalities or active bleeding12,13.
- Allocate patients into study groups.
- Divide the 52 eligible patients into two groups based on the anticoagulation modality documented in their records: the Segmented Regional Citrate Anticoagulation (S-RCA) group (n = 26) and the Single-Segment Regional Citrate Anticoagulation (SS-RCA) group (n = 26).
NOTE: This protocol describes a retrospective analysis. The anticoagulation modality (S-RCA or SS-RCA) was determined by the treating physician at the time of dialysis and is not assigned prospectively by the researcher.
- Divide the 52 eligible patients into two groups based on the anticoagulation modality documented in their records: the Segmented Regional Citrate Anticoagulation (S-RCA) group (n = 26) and the Single-Segment Regional Citrate Anticoagulation (SS-RCA) group (n = 26).
2. Preparation for hemodialysis and anticoagulation setup
- Prepare the hemodialysis circuit.
- Set up the hemodialysis machine, blood tubing set, dialyzer, and venous air trap according to the manufacturer's instructions and standard clinical protocols.
- Ensure all connections are secure. For all dialysis sessions, a commercially available calcium-containing dialysate with a calcium concentration of 1.5 mmol/L was used.
- Prepare the citrate and calcium solutions.
- Use commercially available 4% trisodium citrate solution for anticoagulation. Have a calcium chloride or calcium gluconate solution ready for potential systemic calcium supplementation, though it is not routinely required with calcium-containing dialysate.
- Prime the circuit.
- Prime the extracorporeal circuit with normal saline per standard procedure to remove air and prepare for patient connection.
- Program the syringe pumps for citrate infusion. Load the citrate solution onto syringe pumps integrated with the dialysis machine.
- For the S-RCA group, program two separate syringe pumps.
- Pump 1 (Arterial End): Set the infusion rate (mL/h) to (0.5 – 1.0) × blood flow rate (mL/min). Connect this pump to the blood line immediately before the dialyzer inlet.
- Pump 2 (Venous Chamber): Set the infusion rate (mL/h) to (0.3 – 0.5) × blood flow rate (mL/min). Connect this pump to the venous air trap.
- For the SS-RCA group, program a single syringe pump.
- Set the infusion rate (mL/h) to (0.9 – 1.13) × blood flow rate (mL/min). Connect this pump to the blood line immediately before the dialyzer inlet.
NOTE: The exact multiplier within the specified ranges is determined by the clinician based on patient characteristics and institutional protocol. Blood flow rate (BFR) is prescribed based on patient size and clinical status.
- Set the infusion rate (mL/h) to (0.9 – 1.13) × blood flow rate (mL/min). Connect this pump to the blood line immediately before the dialyzer inlet.
- For the S-RCA group, program two separate syringe pumps.
3. Conducting the hemodialysis session
- Initiate the dialysis.
- Connect the patient to the primed dialysis circuit. Initiate blood pump flow gradually to the prescribed rate (typically 3–5 mL/kg/min in children). Start dialysate flow and ultrafiltration as prescribed.
- Start the citrate infusion.
- Immediately initiate the pre-programmed citrate infusion(s) according to the assigned group (Step 2.4).
- Monitor the treatment parameters.
- Continuously monitor and record the following parameters throughout the session:
- Monitor the blood flow rate (mL/min) via an ultrasonic Doppler flow meter.
- Record the dialysate flow rate (mL/min) from the dialysis machine's built-in flowmeter.
- Monitor the ultrafiltration volume (mL/kg/h) via the dialysis machine's volumetric control system.
- Record the citrate infusion rates (mL/h) from each pump via the pump's built-in flow sensor.
- Determine the transmembrane pressure (TMP) and venous pressure (VP) from the dialysis machine.
CAUTION: A sharp, sustained rise in TMP (>250 mmHg) or VP suggests a high risk of circuit clotting. Inspect the dialyzer and venous chamber promptly if this occurs.
- Continuously monitor and record the following parameters throughout the session:
4. Sample collection and point-of-care testing
- Collect blood samples at the following timepoints during a standard 4-h hemodialysis session: immediately before dialysis initiation (predialysis baseline), at 2 h of dialysis (samples from pre-filter, post-filter, and post-venous chamber lines), and immediately post-dialysis.
- At each timepoint, draw approximately 0.5 mL of blood into a pre-heparinized blood gas syringe from the specified sampling port.
- Analyze the sample immediately using a blood gas analyzer to measure: Ionized calcium (iCa2+), pH, Partial pressure of carbon dioxide (PaCO₂). Calculate the bicarbonate concentration using the Henderson-Hasselbalch equation: HCO₃⁻ = 0.03 × PaCO₂ × 10^(pH - 6.1). Record the value.
5. Assessment of circuit coagulation
- Initiate visual monitoring of the extracorporeal circuit.
- Beginning immediately after the start of dialysis and continuing throughout the 4-h session, perform regular visual inspections of the dialyzer and venous air trap.
- Visually inspect the dialyzer.
- Every 30–60 min, visually inspect the dialyzer fiber bundle against a white light background.
- Look for signs of coagulation, such as darkening of fiber color, streaky clots, or a general "frosting" appearance. Record any clotting event.
- Visually inspect the venous air trap.
- Every 30–60 min, inspect the venous air trap for clot formation on the walls or for thickening of the blood-air interface foam layer. Record any clotting event.
- Classify anticoagulation efficacy.
- At the end of the dialysis session, classify the circuit components:
- Classify the anticoagulation efficacy for the dialyzer and venous chamber at the end of each session as 'Effective' (no significant clotting, minimal fiber streaking, or a small clot in the venous chamber that did not require circuit intervention) or 'Ineffective' (clotting that led to a visible loss of >1 cm of fibers in the dialyzer, a large clot in the venous chamber requiring chamber change, or premature termination of the dialysis session due to circuit clotting).
- Calculate the effective rate as: (Number of effective cases / Total number of cases) × 100%.
- At the end of the dialysis session, classify the circuit components:
6. Collection and processing of serum samples
- At the predialysis and post-dialysis timepoints, draw 3–5 mL of venous blood into a serum separator tube. Gently invert the tube 5–8 times immediately after collection. Let the tube stand upright at room temperature for 30 min to allow complete clot formation.
- Centrifuge the sample at 1500 × g for 10 min at 4 °C. Carefully aspirate the clear supernatant serum using a pipette, avoiding the buffy coat or red blood cells. Transfer the serum to pre-labeled cryovials.
NOTE: The experiment can be paused here. Store serum aliquots at -80 °C for batch analysis.
7. Biochemical and coagulation analysis
- Analyze for dialysis adequacy markers.
- Thaw frozen serum samples on ice. Use a fully automated biochemistry analyzer to measure: Blood Urea Nitrogen (BUN), Creatinine (Cr).
- Analyze serum electrolytes and total calcium.
- Using the same or a separate serum aliquot, employ a fully automated biochemistry analyzer with ion-selective electrodes to measure: Potassium (K⁺), Sodium (Na⁺), Chloride (Cl⁻), Total Calcium (tCa2+) via a colorimetric method (e.g., arsenazo III).
- Analyze coagulation function.
- Collect plasma samples. At predialysis and post-dialysis, draw 2 mL of venous blood into a 3.2% sodium citrate anticoagulation tube. Centrifuge at 2500 × g for 15 min at 4 °C to obtain platelet-poor plasma.
- Perform coagulation assays. Use a fully automated coagulation analyzer to measure: Activated Partial Thromboplastin Time (APTT), Prothrombin Time (PT), Thrombin Time (TT).
8. Monitoring and recording complications
- Monitor for clinical symptoms.
- Throughout the dialysis session and in the immediate recovery period, ask the patient and observe for symptoms.
- Record the occurrence of: Numbness of lips/mouth or extremities, Muscle cramps, Nausea or vomiting.
- Monitor hemodynamics.
- Measure and record blood pressure every 15–30 min. Document episodes of hypotension, defined as a drop in systolic blood pressure >20 mmHg from baseline or an absolute value <90 mmHg.
- Assess for citrate accumulation.
- Using the measured post-dialysis tCa2+ (from Step 7.2) and iCa2+ (from Step 4.2) values, calculate the tCa2+ / iCa2+ ratio. A ratio > 2.5 suggests possible citrate accumulation14.
9. Data management and statistical analysis
- Organize the data.
- Compile all recorded and measured data into a structured electronic database. Ensure patient identifiers are removed or coded for confidentiality.
- Perform statistical analysis.
- Use statistical software (e.g., SPSS 26.0) for analysis. Test for normality. Perform normality tests (e.g., Shapiro-Wilk) on all continuous data. Compare continuous variables.
- Express normally distributed data as mean ± standard deviation (x̄ ± s). Use independent samples t-tests to compare parameters (e.g., iCa2+, BUN, Cr) between the S-RCA and SS-RCA groups at different timepoints. Use paired t-tests for within-group comparisons (pre vs. post-dialysis). Compare categorical variables.
- Express count data (e.g., anticoagulation efficacy, complication rates) as number (percentage). Use the Chi-squared (χ2) test to compare these variables between the two groups. Set significance level. Consider a P-value of < 0.05 as statistically significant for all tests.
Results
A total of 52 pediatric patients meeting the inclusion criteria were enrolled and divided into the S-RCA (n=26) and SS-RCA (n=26) groups. Baseline demographic and clinical characteristics were comparable between groups (P>0.05), as shown in Table 1.
As shown in Table 2, the total citrate dose was significantly higher in the S-RCA group than in the SS-RCA group (P<0.001), reflecting the additional venous chamber infusion in the S-RCA protocol. Arterial-end citrate infusion rates, blood flow rate, dialysate flow rate, and ultrafiltration volume were similar between groups (P>0.05), confirming that extracorporeal circuit parameters were well matched.
At 2 h of dialysis, iCa2+ concentrations measured pre-filter were significantly lower than pre-dialysis values in both groups, confirming effective regional anticoagulation within the extracorporeal circuit. In the S-RCA group, the pre-filter iCa²⁺ was 0.43 ± 0.14 mmol/L, and in the SS-RCA group, it was 0.39 ± 0.15 mmol/L, both markedly reduced compared to baseline pre-dialysis levels (1.13 ± 0.21 mmol/L and 1.12 ± 0.22 mmol/L, respectively). Furthermore, the post-venous chamber iCa²⁺ concentration was significantly lower in the S-RCA group than in the SS- RCA group (0.85 ± 0.11 vs. 1.03 ± 0.14 mmol/L, P < 0.001), indicating superior maintenance of anticoagulation in the venous segment with the segmented infusion strategy. Systemic iCa²⁺ remained stable from pre- to post-dialysis in both groups (P>0.05), indicating no procedure‑induced hypocalcemia.
The S-RCA group showed slightly higher pH values pre-filter and post-venous chamber at 2 hours (P=0.027 and P=0.017, respectively), though post-filter pH and systemic pH changes were comparable. Bicarbonate (HCO₃⁻) levels were similar between groups at all time points (P>0.05), and both groups demonstrated stable acid-base balance throughout dialysis. See Table 3. Anticoagulation efficacy in the dialyzer was comparable between the S-RCA (92.31%) and SS-RCA (84.62%) groups (P=0.664). However, anticoagulation in the venous air trap was significantly more effective in the S-RCA group (100.00% vs. 76.92%, P=0.030), as detailed in Table 4.
Predialysis blood urea nitrogen (BUN) and creatinine (Cr) levels were similar between groups. Post-dialysis, both BUN and Cr decreased significantly more in the S-RCA group than in the SS-RCA group (P<0.001 for both), indicating superior small-molecule clearance (Table 5).
Post-dialysis serum potassium, sodium, chloride, and total calcium levels were comparable between groups (P>0.05). Both groups showed expected increases in HCO₃⁻ after dialysis, with no significant intergroup differences (Table 6).
Activated partial thromboplastin time (APTT), prothrombin time (PT), and thrombin time (TT) were similar between groups both before and after dialysis (P>0.05), indicating no differential effect on systemic coagulation (Table 7).
No severe adverse events occurred in either group. The S-RCA group showed a trend toward lower incidences of hypocalcemia-related symptoms (lip/limb numbness, muscle cramps), nausea/vomiting, hypotension, and citrate accumulation, though these differences did not reach statistical significance (P>0.05, Table 8).
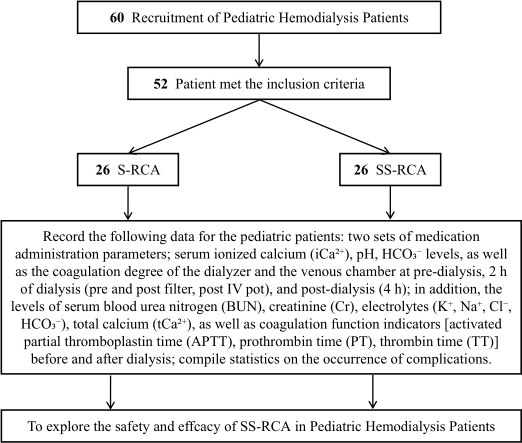
Figure 1: Design flow chart. Please click here to view a larger version of this figure.
Table 1: Comparison of general information. BMI: Body Mass Index; S-RCA: Segmented SS-RCA; SS-RCA: Single-Segment SS-RCA. The same below. Please click here to download this Table.
Table 2: Comparison of treatment parameter indicators. Please click here to download this Table.
Table 3: Comparison of iCa2+, PH, and HCO3-levels. Please click here to download this Table.
Table 4: Comparison of the degree of coagulation in dialysers and Venous air traps. Please click here to download this Table.
Table 5: Comparison of BUN and Cr levels before and after dialysis treatment. Please click here to download this Table.
Table 6: Comparison of serum electrolytes, tCa2+ in vivo before and after dialysis. Please click here to download this Table.
Table 7: Comparison of coagulation function (APTT, PT, TT) before and after dialysis. Please click here to download this Table.
Table 8: Comparison of indicators of complications. Please click here to download this Table.
Discussion
The management of anticoagulation in paediatric hemodialysis has always been a major challenge in clinical practice. Due to the slender vasculature, small blood volume, and significant differences in metabolic characteristics between paediatric patients and adults, traditional systemic anticoagulation (e.g., heparin) is prone to hemorrhagic or thrombotic complications, with a higher risk, especially in children with a bleeding tendency, during the perioperative period, or with low body weight15,16. Citrate anticoagulation inhibits thrombin activity through local chelation of calcium ions, which theoretically enables selective anticoagulation in the extracorporeal circulation and reduces the risk of systemic hemorrhage17, but because the dialysis fluid is a calcium-containing dialysate, the blood undergoes ion exchange through the filter. The ionic calcium in the blood that has been chelated is corrected, thus affecting coagulation, and the speed of blood flow in children is low, so the risk of coagulation occurring during a single section of drug administration is higher than in adults. Physiological specialties of children (e.g., the presence of citrate) can lead to bleeding or thrombotic complications. Specificities of children's physiology (e.g., limited ability to metabolise citrate, easily disturbed acid-base balance) lead to technical complexities in its application18. S-RCA can optimise the balance between anticoagulation efficacy and safety by dynamically modulating citrate infusion and calcium supplementation19,20. Exploring the efficacy of S-RCA in paediatric hemodialysis is important to improve outcomes, reduce complications, and promote individualised anticoagulation in children. This study found that neither S-RCA nor SS-RCA caused significant electrolyte disturbances, acid-base imbalances, or coagulation dysfunction in pediatric hemodialysis. Moreover, no serious adverse reactions related to citrate accumulation were observed. These results demonstrate that both anticoagulation methods are equally safe and effective in the pediatric population.
Optimisation of citrate anticoagulation parameters is a key component to ensure the safety and effectiveness of hemodialysis. In recent years, with the promotion of the concept of precision medicine, S-RCA has demonstrated potential advantages in clinical applications due to its unique delivery method 21. Conventional SS-RCA uses a fixed-rate infusion of citrate, which may lead to insufficient local anticoagulation or an increased risk of metabolic complications2. Several studies have shown a non-linear relationship between citrate dose and anticoagulant effect, which may increase the risk of metabolic alkalosis and hypocalcaemia when the dose exceeds the threshold22. Meanwhile, changes in hemodynamic parameters during dialysis affect drug metabolism kinetics, suggesting the need for more refined dosing regimens23,24. This study found that the total citrate dose was significantly higher in the S-RCA group than in the SS-RCA group (P<0.001). Notably, there was no significant difference (P>0.05) between the two groups in basal treatment parameters (blood flow rate, dialysate rate, ultrafiltration volume), ruling out the influence of these factors on the study's results.The S-RCA group used a differentiated pump speed setup: the arterial end of the pump speed was 68.42 ± 15.22 mL/h, and the Venous air trapentiometric end was reduced to to be 50.23 ± 10.05 mL/h. From a procedural standpoint, it is critical to ensure that the citrate infusion rate at the arterial end is precisely calibrated relative to the blood flow rate (BFR), typically maintained within a range of 0.5–1.0 times the BFR (mL/min), to achieve adequate pre-filter anticoagulation without inducing systemic hypocalcemia. Clinicians should verify that the citrate pump is correctly connected to the pre-dialyzer line and that there are no occlusions or kinks that could disrupt flow. Additionally, the venous chamber infusion line should be inspected regularly for proper placement and patency. In cases where clotting is observed in the venous chamber despite correct infusion rates, troubleshooting should include checking for mechanical obstructions, confirming that the venous chamber is not overloaded with foam or clots, and considering a temporary increase in the venous citrate infusion rate within the recommended range (0.3–0.5 × BFR). If citrate accumulation is suspected, indicated by a rising total calcium-to-ionized calcium ratio >2.5, clinicians should promptly reduce or pause the citrate infusion, increase dialysate flow if possible, and consider temporary calcium supplementation. These practical considerations are essential for the safe and effective implementation of S-RCA, particularly in pediatric patients who are more susceptible to metabolic fluctuations.
The dose difference in the S-RCA group reflects its unique mechanism of action2,25: (1) a higher dose at the arterial end ensured initial anticoagulation, which matched the high coagulation risk characteristics of the filter segment; (2) a lower dose at the Venous air trapentiometric segment maintained the basic anticoagulation requirements while reducing the metabolic burden; and (3) dynamically adjusted dosing may be more in line with the pharmacokinetic characteristics of citrate, optimising the time of drug exposure. This mode of administration ensures anticoagulant efficacy while potentially reducing the risk of metabolic complications by reducing the citrate load in the venous segment. In addition, the pH of the S-RCA group was slightly higher than that of the SS-RCA group before the 2-h dialysis filter and after the intraVenous air trap (P=0.027 and P=0.017, respectively), but the difference in HCO₃- concentration between the two groups was not statistically significant (both P>0.05). Before and after treatment, there were no significant changes in Ca2⁺, pH, and HCO₃- levels in either group, suggesting that both the two multistage SS-RCA groups and the SS-RCA group were able to maintain the stability of the overall electrolyte and acid-base balances. The slight difference in pH may be related to the alkali load generated during citrate metabolism, but the stability of the HCO₃- concentration suggests that both methods were effective at buffering metabolic changes and maintaining acid-base homeostasis26.
The choice of anticoagulation modality for hemodialysis is directly related to the safety and efficacy of the treatment. RCA has become an important clinical anticoagulation option due to its excellent local anticoagulation effect and low risk of bleeding27. Compared with SS-RCA, S-RCA dynamically adjusts the citrate infusion rate. Several studies have shown that conventional hemodialysis patients suffer from inadequate anticoagulation, which often leads to dialyser coagulation and venous air-trap thrombosis, seriously affecting dialysis adequacy1,28. The results of this study showed that the S-RCA group was significantly better than the SS-RCA group in terms of venous air-trap anticoagulation efficiency, with a statistically significant difference. This finding is partially consistent with those reported by Ting et al., who observed that S-RCA reduced the risk of coagulation in the venous circuit by approximately 40%29. The significant anticoagulation effectiveness of S-RCA may stem from its unique mechanism of action: Since the dialysate contains calcium, as blood flows through the dialyzer and undergoes ion exchange with the calcium-containing dialysate, the chelated ionized calcium is corrected, thereby affecting coagulation. Furthermore, when blood passes through the dialyzer, citrate is cleared, which further compromises the anticoagulant effect. Therefore, S-RCA achieves anticoagulation by re-chelating calcium ions in the segment before the venous chamber following citrate infusion. Notably, children have lower blood flow rates and are inherently more prone to coagulation risks compared to adults. Therefore, the risk of coagulation with single-segment administration is higher in children than in adults.
A critical safety concern is the metabolic handling of the increased citrate load in the S-RCA group. The total calcium-to-ionized calcium ratio (tCa/iCa) is a reliable surrogate marker of citrate accumulation, with a ratio >2.5 indicating potential toxicity. In this study, no patient in either group exhibited a tCa/iCa ratio exceeding this threshold, and the clinically observed incidence of citrate accumulation, while not statistically different, was lower in the S-RCA group. This seemingly paradoxical finding, a higher dose but lower accumulation risk, can be explained by the segmented infusion strategy. In S-RCA, a portion of the total citrate dose is infused directly into the venous chamber. This fraction bypasses the dialyzer, where the majority of citrate removal occurs, and enters the systemic circulation, where it is metabolized. The stable post-dialysis bicarbonate levels and the absence of an elevated tCa/iCa ratio indicate that the pediatric patients in our cohort, who were carefully screened to exclude those with severe hepatic failure, possessed sufficient metabolic capacity (primarily hepatic, but also renal and muscular) to clear this load effectively. These findings suggest that S-RCA, by distributing the citrate load, may place less acute demand on the dialyzer's clearance capacity and more evenly distribute the metabolic task across the patient's endogenous pathways. However, vigilant monitoring of the tCa/iCa ratio remains paramount, particularly in children with suspected or unknown liver impairment.
We propose that the superior anticoagulation efficacy observed in the venous chamber with S-RCA likely prevents silent or overt circuit clotting, thereby preserving dialyzer surface area and ensuring the delivery of a full, uninterrupted dialysis session. This maximizes the time available for solute removal, thereby enhancing the clearance of small molecules. Interestingly, while BUN and Cr clearance differed significantly, post-dialysis serum potassium (K⁺) levels were comparable between the two groups. This discrepancy may be explained by differences in solute removal kinetics. Potassium removal is highly dependent on the rapid establishment of a transmembrane concentration gradient, which can occur effectively even in suboptimal circuit conditions. In contrast, the clearance of larger molecules, such as BUN and Cr, is more time-dependent and more susceptible to interruptions in dialysis efficacy caused by minor clotting events. Therefore, the benefit of a perfectly patent circuit provided by S-RCA may be more pronounced for solutes whose clearance is critically dependent on sustained, uninterrupted dialysis time.
In recent years, the treatment of end-stage renal disease in children has faced important challenges, particularly the optimisation of the anticoagulation modality for hemodialysis30. SS-RCA has become an important choice for hemodialysis in children due to its unique anticoagulation mechanism and lower risk of bleeding31. However, traditional SS-RCA still has problems with unstable anticoagulation and limited dialysis efficiency in clinical applications32. By comparing the levels of BUN and Cr before and after dialysis in this study, it is found that the decline in these levels was significantly greater in the S-RCA group than in the SS-RCA group (P<0.001). The findings of this experimental study suggest that S-RCA, by optimizing anticoagulant distribution during dialysis, may more effectively prevent localized coagulation and thereby prolong effective dialysis time. Sha et al. found that BUN clearance was increased by 18.5% (P<0.01) and Cr clearance was improved by 21.3% (P<0.001) with S-RCA compared with single-segment33 , further supporting the conclusions of our study. Future large-sample studies are needed to further validate the applicability of this mechanism in children.
Electrolyte balance is a key factor in maintaining the stability of the internal environment of hemodialysis patients, and dynamic changes in electrolytes such as potassium, sodium, chloride, calcium, and bicarbonate not only reflect the adequacy of dialysis but also directly impact the cardiovascular stability of patients34. The metabolism of RCA, an important anticoagulant for hemodialysis, may have complex effects on electrolyte balance35. Paul et al. reported that the metabolism of citric acid may cause metabolic alkalosis, while the formation of a calcium citrate complex may temporarily reduce ionic calcium concentration, which may induce complications related to hypocalcaemia. alkalosis36, while the formation of calcium citrate complex temporarily reduces ionic calcium concentration and may induce hypocalcaemia-related complications37. Electrolyte disturbances are an important cause of arrhythmias and muscle spasms in long-term dialysis patients38. The present study showed that both patient groups showed significant reductions in blood potassium (P<0.05) and increases in HCO₃- (P<0.05) after dialysis. It is worth noting that although there was no statistical difference between the S-RCA and SS-RCA groups in terms of potassium, sodium, chloride, and total calcium (P>0.05), the S-RCA group showed a trend toward more stable potassium control and HCO₃- elevation. S-RCA may maintain a more stable electrolyte balance through the following mechanisms: (1) phased regulated citrate infusion reduced the magnitude of electrolyte fluctuations and avoided abrupt changes that could result from single-staging17; (2) more precise calcium chelation reduced the risk of secondary electrolyte disturbances39; (3) optimised citrate metabolism mitigated the dramatic fluctuations in HCO₃-. Particularly for potassium control, S-RCA may have reduced the risk of post-dialysis hypokalaemia by maintaining a more stable transmembrane gradient40.
Coagulation Haematological function monitoring is an important part of assessing the effectiveness of anticoagulation in hemodialysis patients, in which APTT, PT, and TT are commonly used indicators reflecting the exogenous and endogenous coagulation pathways41. Xiao et al. found that fluctuations in the post-dialysis APTT, PT, and TT were within the normal reference interval, whether in the S-RCA or SS-RCA, and the difference between groups was not statistically significant (P>0.05)6. S-RCA and SS-RCA are two common anticoagulation modalities, and this study compared their effects on coagulation function in dialysis patients. The results showed that there was no significant difference in APTT, PT, and TT values between the two groups of patients before and after dialysis (P>0.05), suggesting that both anticoagulation modalities have similar effects on coagulation function. This result may be related to the equivalence of the two strategies in terms of citrate metabolism and calcium antagonism. Citrate inhibited the coagulation process by chelating calcium ions, whereas S-RCA and SS-RCA may have reached a similar balance in local anticoagulation concentration and metabolic clearance efficiency, which did not lead to significant differences in coagulation indices. In addition, the body's compensatory mechanisms during dialysis (e.g., the liver's ability to metabolise citrate) may further buffer the potential differences between the two methods.
The prevention and control of RCA-related complications has always been a key concern in the field of hemodialysis. Previous studies have shown that traditional RCA techniques may cause a variety of adverse reactions, among which the incidence of hypocalcaemia-related symptoms (e.g. numbness of lips and mouth, numbness of limbs) can be up to 15%–20%, The incidence rates are positively correlated with the dose and infusion rate of citrate, and these complications not only affect the patient's comfort, but also endanger the safety of the treatment in serious cases18,42. It is particularly noteworthy that children are more prone to related adverse effects due to their underdeveloped metabolic system and weaker ability to clear citrate5. But the results of this study showed that the S-RCA group showed a trend of superiority over the SS-RCA group in a number of complication indicators. In terms of symptoms related to hypocalcaemia, the S-RCA group had lower rates of numbness of lips and mouth, numbness of limbs and muscle cramps, which were not statistically significant (P>0.05). This may be related to the small sample size, and further investigation using larger sample-sized, high-quality studies is warranted.
This pilot study showed that both anticoagulation modalities are equally safe and effective in paediatric hemodialysis applications, with better dialysis adequacy in the S-RCA group. In the standard operating procedures for blood purification regarding citrate dosage, recommended doses for S-RCA in adults are provided. However, based on the findings of this study, for segmental citrate dosing, the pump speed before the filter (mL/h) = (0.5–1.0) × blood flow rate (mL/min), and the pump speed at the venous chamber (mL/h) = (0.3–0.5) × blood flow rate (mL/min). From a clinical implementation perspective, it is vital to establish a standardized monitoring protocol. This should include point-of-care testing of ionized calcium at predialysis, 2 h into the session (pre-filter, post-filter, and post-venous chamber), and post-dialysis to guide any necessary adjustments. For troubleshooting, if post-filter ionized calcium exceeds 0.40 mmol/L, indicating insufficient anticoagulation, the pre-filter citrate infusion rate should be increased incrementally. Conversely, if the patient shows signs of hypocalcemia (e.g., perioral numbness) or a rising total calcium/iCa2⁺ ratio, the infusion should be reduced and intravenous calcium administered. These detailed procedural steps and troubleshooting guidelines are critical to translating the efficacy observed in this study into routine clinical practice, particularly in the pediatric population, where precision is paramount.
Based on the findings of this study, S-RCA is particularly suitable for the following pediatric hemodialysis populations: Children with a significant bleeding tendency or active bleeding disorders, such as those in the perioperative period, with HIT, or with coagulation dysfunction; Patients requiring prolonged dialysis sessions who are at increased risk of venous chamber clotting, such as low-weight children or those with limited blood flow rates; Those with high demands for dialysis adequacy, where maximal removal of small-molecule toxins is essential. Clinically, S-RCA should be implemented in settings with access to real-time blood gas monitoring and supported by experienced nursing staff to ensure both safety and efficacy.
Disclosures
The authors declare that they have no financial conflicts of interest.
Acknowledgements
Science and Technology Fund Project of the Health Commission of Guizhou Province (gzwkj2023—185).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Blood Gas Analyzer | Werfen | GEM Premier 5000 | Used for measuring iCa2+, pH, PaCO2, and calculating HCO3-. |
| Ultrasonic Doppler Blood Flow Meter | Transonic Systems Inc. | HD02 | On-line monitoring of blood flow rate during dialysis. |
| Fully Automated Biochemistry Analyzer | Roche Diagnostics | Cobas 8000 | Used for measuring BUN, Cr, electrolytes (K+, Na+, Cl-), tCa2+, and albumin. |
| Fully Automated Coagulation Analyzer | Sysmex Corporation | CS-5100 | Used for measuring APTT, PT, and TT. |
| Dialysis Machine (built-in syringe pump with flow sensor) | Gambro | AK 96 | Built-in flow sensor with accuracy ±0.5 mL/h for citrate infusion; volumetric ultrafiltration control system for monitoring ultrafiltration volume. |
| Sodium Citrate Anticoagulation Tubes | BD Vacutainer | 363083 | 2.7 mL tubes (3.2% sodium citrate) for coagulation tests. |
| Blood Pressure Monitor | GE Healthcare | Carescape V100 | Non-invasive blood pressure monitoring during dialysis. |
| Dialyzer | Fresenius Medical Care | FX Paed | Low-volume, high-efficiency dialyzer designed for pediatric use. |
| Venous Air Trap / Chamber | Fresenius Medical Care | Integral venous chamber | Part of the extracorporeal circuit, regularly checked for coagulation. |
| Calcium-containing Dialysate | Fresenius Medical Care | GranuPac | Standard bicarbonate dialysate with calcium concentration of 1.25 or 1.5 mmol/L. |
| Citrate Solution | Baxter | 4% trisodium citrate (46.7 mmol/L) | Used for regional citrate anticoagulation in SS-RCA and S-RCA modes. |
| Syringe Pump for Citrate Infusion | B. Braun | Perfusor Space | Programmable syringe pump used for precise citrate infusion at arterial and venous sites. |
| Continuous Venous Pressure Monitor | Gambro | AK 96 | Monitors venous pressure (VP) to assess circuit patency and coagulation risk. |
| Transmembrane Pressure Monitor | Gambro | AK 96 | Monitors TMP to detect dialyzer clotting. |
| Statistical Software | IBM | SPSS 26.0 | Used for data analysis and statistical comparisons. |
References
- Daugirdas, J. T., et al. KDOQI clinical practice guideline for hemodialysis adequacy: 2015 update. Am J Kidney Dis. 66 (5), 884-930 (2015).
- Yanna, F., et al. An individualized regional citrate anticoagulation protocol for hemodialysis: A real-world retrospective study. Int Urol Nephrol. 56 (1), 295-302 (2023).
- KDIGO Group. KDIGO clinical practice guideline for acute kidney injury. Kidney Int Suppl. 2, 1(2012).
- Francesca Di, M., et al. Sustained low-efficiency dialysis (SLED) with regional citrate anticoagulation (RCA) and new dialysis equipment: A prospective study with serum citrate measurements and electrolyte monitoring. J Nephrol. 38 (2), 473-480 (2025).
- Dan, P., Zili, C., Jie, H., Wei, D., Xinping, Z. Comparison of regional citrate anticoagulation and nafamostat mesylate anticoagulation during plasma exchange for children at high bleeding risk: A retrospective study. Ital J Pediatr. 51 (1), 114(2025).
- Xiaoyan, T., et al. Application of regional citrate anticoagulation in patients at high risk of bleeding during intermittent hemodialysis: A prospective multicenter randomized controlled trial. J Zhejiang Univ Sci B. 23 (11), 931-942 (2022).
- Aakash Chandran, C., Ankit, M., Karthi, N. Anticoagulation strategies for pediatric continuous renal replacement therapy. J Pediatr Crit Care. 11 (5), 218-226 (2024).
- Xiao, B., Qi, Z., Feng, Z., Feng, D. A mathematical estimation for quantified calcium supplementation during intermittent hemodialysis using regional citrate anticoagulation. Artif Organs. 46 (6), 1122-1131 (2022).
- Alexandra, C., et al. Calcium-free dialysate hemodialysis: A simplified approach. J Pers Med. 14 (6), 660(2024).
- Stanislas, F., et al. A randomized crossover trial of regional anticoagulation modalities for intermittent haemodialysis. Nephrol Dial Transplant. 40 (3), 537-543 (2024).
- Yu, C., Fang, F., Hong, G., Lu, Z., Jian, L. Study on the application of a segmented sodium citrate solution anticoagulation strategy in critically ill patients receiving CRRT: A prospective randomized controlled study. Trials. 25 (1), 542(2024).
- Giovana Seno Di, M., et al. Monocytes as targets for immunomodulation by regional citrate anticoagulation. Int J Mol Sci. 25 (5), 2900(2024).
- Garan, A. R., et al. Predictors of survival for patients with acute decompensated heart failure requiring extracorporeal membrane oxygenation therapy. ASAIO J. 65 (8), 781-787 (2019).
- Gabutti, L., Marone, C., Colucci, G., Duchini, F., Schönholzer, C. Citrate anticoagulation in continuous venovenous hemodiafiltration: A metabolic challenge. Intensive Care Med. 28, 1419-1425 (2002).
- Theodore, E. W. Immunologic effects of heparin associated with hemodialysis: Focus on heparin-induced thrombocytopenia. Semin Nephrol. 43 (6), 151479(2023).
- David, K. B., et al. Anticoagulation practices associated with bleeding and thrombosis in pediatric extracorporeal membrane oxygenation: A multi-center secondary analysis. Perfusion. 38 (2), 363-372 (2022).
- Thomas, D., Muriel, G., Piet Ter, W., Mario, C., Björn, M. Regional citrate anticoagulation: A tale of more than two stories. Semin Nephrol. 43 (6), 151481(2023).
- Yasemin Ezgi, K., et al. Evaluation of the efficacy and associated complications of regional citrate anticoagulation in neonates: Experience from a fourth level neonatal intensive care unit. Eur J Pediatr. 182 (11), 4897-4908 (2023).
- Federico, N., et al. Safety of citrate anticoagulation in CKRT: Monocentric experience of a dynamic protocol of calcium monitoring. J Clin Med. 12 (16), 5201(2023).
- Lenar, Y., et al. Regional citrate anticoagulation non-shock protocol with pre-calculated flow settings for patients with at least 6 l/hour liver citrate clearance. BMC Nephrol. 22 (1), 244(2021).
- Yi, Z., et al. Development and validation of a risk prediction model for citrate accumulation in patients undergoing continuous renal replacement therapy with regional citrate anticoagulation. Blood Purif. 54 (4-5), 250-263 (2025).
- Dmytro, K., et al. Intensive monitoring of post filter ionized calcium concentrations during CVVHD with regional citrate anticoagulation: a retrospective study. J Crit Care. 58, 1-5 (2020).
- Peerapat, T., et al. Citrate pharmacokinetics in critically ill liver failure patients receiving CRRT. Sci Rep. 12 (1), 1815(2022).
- Ren, J. Advances in combination therapy for gastric cancer: Integrating targeted agents and immunotherapy. Adv Clin Pharmacol Ther. 1 (1), 1-15 (2024).
- Thierry, P., Bernard, B. Can regional anticoagulation with calcium-free dialysate be extended to maintenance hemodialysis. Artif Organs. 48 (7), 704-712 (2024).
- David, P. S. Regulation of renal citrate metabolism by bicarbonate ion and pH: Observations in tissue slices and mitochondria. J Clin Invest. 46 (2), 225-238 (1967).
- Detlef, K. M., Timo, B., Thomas, D. Regional citrate anticoagulation for continuous renal replacement therapy. Curr Opin Crit Care. 24 (6), 450-454 (2018).
- Emanuele, B., et al. Regional citrate anticoagulation and systemic anticoagulation during pediatric continuous renal replacement therapy: A systematic literature review. J Clin Med. 11 (11), 3121(2022).
- Ting, L., et al. Modified regional citrate anticoagulation is optimal for hemodialysis in patients at high risk of bleeding: A prospective randomized study of three anticoagulation strategies. BMC Nephrol. 20, 472(2019).
- Laimin, L., Meirong, F., Qinkai, C., Jing, C. A simplified protocol for individualized regional citrate anticoagulation for hemodialysis. Medicine. 100 (8), e24639(2021).
- Desheng, Z., Jie, H., Zhenghui, X., Xiong, Z., Xinping, Z. Citrate and low-dose heparin combined anticoagulation in pediatric continuous renal replacement therapy. Sci Rep. 14 (1), 13504(2024).
- Franck, P., et al. Sustained low-efficiency dialysis with regional citrate anticoagulation for patients with liver impairment in intensive care unit: A single-center experience. Ther Apher Dial. 25 (2), 211-217 (2020).
- Shasha, C., et al. Comparison of citrate anticoagulation strategies in hemodialysis patients at high risk of bleeding: A multicenter prospective observational cohort study. Ren Fail. 48 (1), 2624876(2020).
- Heba Abd El, G., Mamdouh El, N., Amir, O., Basma Bader, E., Fatima Taha, M. Comparison between calcium and non-calcium-based phosphate binders concerning acid-base status and electrolytes in hemodialysis patients in Alhyat Hospital. Medicine Updates. 17 (17), 55-65 (2024).
- Simon, W., Friederike, C., Johannes, S. Impact of continuous veno-venous hemodialysis with regional citrate anticoagulation on non-nutritional calorie balance in patients on the ICU-the Nutri-Day study. Nutrients. 15 (1), 63(2022).
- Paul, K., et al. Low bicarbonate replacement fluid normalizes metabolic alkalosis during continuous veno-venous hemofiltration with regional citrate anticoagulation. Ann Intensive Care. 11 (1), 62(2021).
- Undefined, U., et al. Calcium profile of chronic kidney disease patients undergoing hemodialysis. J Noncommun Dis Prev Control. 2 (1), 28-34 (2024).
- John, C. E., et al. Arrhythmia in chronic hemodialysis as a function of predialysis electrolytes and interdialytic interval. Hemodial Int. 27 (1), 45-54 (2022).
- Warnar, C., Faber, E., Katinakis, P. A., Schermer, T., Spronk, P. E. Electrolyte monitoring during regional citrate anticoagulation in continuous renal replacement therapy. J Clin Monit Comput. 36 (3), 871-877 (2021).
- Nuria, G. F., et al. Comparative effect on bone remodeling and inflammation biomarkers of citrate dialysate and bicarbonate dialysate in HDF-OL patients. Nephrol Dial Transplant. 39, 0854-1235 (2024).
- Dunois, C. Laboratory monitoring of direct oral anticoagulants (DOACs). Biomedicines. 9 (5), 445(2021).
- Wang, M. M., Mark, M., Yu, W. Y., Yao, Q. Adverse events with regional citrate anticoagulation versus heparin anticoagulation during continuous renal replacement therapy: A systematic review and trial sequential analysis. J Clin Nephrol. 20, 144(2023).