The diagnosis rate of breast cancer is relatively low. The fourfold table method was used to analyze the diagnostic value of miR-362-3p combined with Doppler ultrasound for breast cancer. The combination of Doppler ultrasound and miR-362-3p effectively enhanced the diagnostic efficacy, providing a promising method for breast cancer diagnosis.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
The Diagnostic Efficacy of Plasma miR-362-3p Combined with Doppler Ultrasound in the Diagnosis of Breast Cancer
* These authors contributed equally
In This Article
Summary
Abstract
Breast cancer is the second most common malignant tumor in the world, seriously threatening the lives of women and imposing a huge economic burden. This study aims to explore the value of miR-362-3p combined with Doppler ultrasound in the diagnosis of breast cancer. A total of 182 breast cancer patients and 147 patients with benign breast disease were included in this study. The plasma miR-362-3p levels of the patients were measured using Real-time fluorescence quantitative polymerase chain reaction (RT-qPCR). The chi-square test was used to analyze the differences in the parameters of Doppler ultrasound between the two groups of patients. The receiver operator characteristic (ROC) curve was used to evaluate the diagnostic effectiveness of miR-362-3p, Resistance Index (RI), and Pulsatility Index (PI). The diagnostic efficiency of Doppler ultrasound combined with plasma miR-362-3p in breast cancer was analyzed through the fourfold table method. The miR-362-3p levels were markedly decreased in breast cancer patients. There were significant differences in two-dimensional ultrasound parameters. miR-362-3p, RI, and PI have diagnostic value for breast cancer. The combined diagnostic value of the three factors was higher. Ultrasound combined with miR-362-3p significantly improved the sensitivity, accuracy, and negative predictive value in breast cancer diagnosis. Doppler ultrasound combined with miR-362-3p could enhance the diagnostic efficiency of breast cancer, which may provide a non-invasive and potential auxiliary diagnostic tool for breast cancer.
Introduction
According to the statistics of the International Agency for Research on Cancer, the incidence rate of breast cancer exceeded that of lung cancer in 20201. Breast cancer is a malignant tumor that commonly occurs and is a leading cause of cancer-related death in women globally1. Timely diagnosis of breast cancer is beneficial to the prognosis of patients. Tissue biopsy is the gold standard for diagnosing breast cancer. However, this is a type of invasive diagnosis, and it does not apply to patients with early-stage breast cancer2.
Doppler ultrasound is a commonly used imaging technique for breast cancer screening and auxiliary diagnosis3. Doppler ultrasound can accurately assess the size of nodules, blood flow signals, and the status of lymph node metastasis4. Breast Doppler ultrasound, due to its advantages such as no ionizing radiation, safety, and non-invasiveness, as well as the ability for repeatable examinations, has become one of the most widely used imaging techniques in breast cancer screening and diagnosis5. However, Doppler ultrasound is prone to being interfered with by the tissue background when detecting breast cancers with low density or small volume, resulting in a significant decline in diagnostic sensitivity and making it difficult to meet the clinical needs for early diagnosis6. Therefore, it is necessary to develop plasma biomarkers that can overcome the limitations of Doppler ultrasound technology. If the combination of the two methods can enhance the sensitivity of diagnosis for breast cancer, it will have significant clinical value and practical significance.
MicroRNAs (miRNAs) are a class of non-coding RNA molecules with a length of approximately 20 to 24 nucleotides7,8. One of the characteristics of miRNAs is a high degree of conservation during the evolutionary process. miRNAs have a wide tissue distribution, which is not only specifically expressed in various human tissue cells, but also can stably exist in multiple body fluids such as blood and saliva9. These distribution characteristics provide advantages for the development of non-invasive diagnostic markers. Functionally, miRNAs degrade mRNA by complementary binding to the 3' Untranslated Regions (UTR)10,11, participating in a series of key pathological and physiological processes such as cellular inflammatory responses, oxidative stress, apoptosis, and proliferation and differentiation12. A large number of studies have confirmed that the abnormal changes in miRNA expression profiles were closely related to the occurrence and development of breast cancer13,14. The dysregulation of miRNA expression can promote the malignant transformation of breast epithelial cells by regulating the expression networks of oncogenes or tumor suppressor genes. miR-362-3p is a typical factor that inhibits tumor progression. Multiple reports found that miR-362-3p inhibited the progression of breast cancer15,16,17. Assiri et al. reported that low expression of miR-362-3p was closely associated with poor prognosis and shorter overall survival in breast cancer patients15. Mechanistically, miR-362-3p exerted anti-tumor effect in breast cancer by targeting DEAD-box helicase 5 (DDX5) to promote cancer cells proliferation, invasion and migration16. In addition, the team led by Kang also found that miR-362-3p was significantly downregulated in breast cancer tissues, and targeted regulation of miR-362-3p expression may serve as a novel potential therapeutic strategy for breast cancer management17. However, there has been no report on whether miR-362-3p can serve as an early diagnostic marker for breast cancer.
This study measured the expression level of miR-362-3p in the plasma and simultaneously analyzed the core image parameters of Doppler ultrasound in breast cancer patients. The study thoroughly explored the combined application value of plasma miR-362-3p expression levels and Doppler ultrasound image parameters, and clearly demonstrated the effectiveness of this combined diagnostic approach in the screening of breast cancer and in the differential diagnosis between benign and malignant breast diseases.
Access restricted. Please log in or start a trial to view this content.
Protocol
This study was performed in line with the principles of the Declaration of Helsinki. Approval was granted by the Ethics Committee of Affiliated Hospital of Shandong Second Medical University, School of Clinical Medicine, Shandong Second Medical University (approval number: wyfy-2023-ky-124). Informed consent was obtained from all subjects involved in the study. The reagents and the equipment used are listed in the Table of Materials.
1. Experimental subjects
Sample size calculation was performed using G*Power 3.1 software based on an independent sample t-test. A medium effect size (Cohen’s d = 0.5, widely used in clinical observational studies), two-tailed test, α = 0.05, and power (1 − β) = 0.95 were set. The calculation indicated that at least 105 participants were required per group. Finally, 182 breast cancer patients and 147 patients with benign breast lesions were enrolled, and the actual sample size of both groups far exceeded the minimum required sample size, ensuring sufficient statistical power to support the study conclusions and controlling the risk of type II error within an acceptable range. All participants were strictly and consecutively enrolled according to unified inclusion and exclusion criteria.
From 2023 to 2024, all patients were enrolled at the Affiliated Hospital of Shandong Second Medical University, School of Clinical Medicine, Shandong Second Medical University. Benign lesions: Non-malignant lesions were confirmed by pathology. Breast cancer: malignant tumors were confirmed by pathology. Venous blood samples were collected from all participants after overnight fasting. The venous blood samples were anticoagulated and centrifuged to separate the plasma, complying strictly with the standard procedures, and then transferred to −80 °C for long-term storage, which was subsequently used for miRNA extraction. All plasma samples were strictly limited to no more than two freeze-thaw cycles before RNA extraction to prevent miRNA degradation. All patients were fully informed about the study protocol and voluntarily provided written informed consent before enrollment.
Inclusion criteria for breast cancer patients: (1) Patients with pathologically confirmed primary breast cancer. (2) No surgical treatment before enrollment. (3) Not received radiotherapy or chemotherapy treatment before sample collection.
Inclusion criteria for benign breast disease patients: (1) Pathologically confirmed benign breast lesions. (2) Without any other systemic malignant tumors or precancerous lesions. (3) Non-pregnant and non-lactating. (4) No severe acute infection or chronic inflammatory disease.
Exclusion criteria for breast cancer and benign breast lesion patients: (1) Severe breast infection or acute critical illness. (2) Severe liver or kidney dysfunction, or autoimmune disease. (3) Patients who received hormone therapy within 6 months.
2. Doppler ultrasound examination
Patient's bilateral breasts were thoroughly examined in four quadrants using Doppler ultrasound. Two-dimensional ultrasound scanning was used to record the lesion features, including boundaries, shape, internal echo, posterior echo waves, and aspect ratio of the lesion. Color Doppler flow imaging was applied to assess the blood flow parameters of the lesion, including resistance index (RI), pulsatility index (PI), and maximum blood flow velocity (Vmax). Blood flow signals were graded according to a previously reported classification system18: Grade 0: No blood flow signal; Grade I: minimal blood flow signal; Grade II: The length of the blood flow signal exceeds half of the lesion diameter; Grade III: Abundant blood flow signal.
3. Positive definition for ultrasound diagnosis of breast cancer
These included (1) Ambiguous boundaries; (2) Irregular shape; (3) Uneven internal echo; (4) Weakened rear echo; (5) Aspect ratio >1; (6) RI > 0.70; (7) PI > 1.50; (8) Maximum blood flow rate (Vmax)> 18.00 cm/s; (9) Blood flow signal ≥ grade II. Any lesion that meets any of the above suspicious criteria is classified as ultrasound positive, while those without suspicious features are classified as ultrasound negative.
4. Real-time fluorescence quantitative polymerase chain reaction (RT-qPCR)
Plasma miRNAs were extracted using a specialized miRNA extraction kit. The successfully extracted RNA samples were used to synthesize cDNA using specialized miRNA reverse transcription kits. Reverse transcription reaction conditions for miR-362-3p: The total volume of this reaction was 20 µL. The PCR reaction procedure was as follows: (1) The mixture was incubated at 37 °C for 15 min, (2) The reverse transcription reaction was carried out for 50 min at 42 °C, (3) The enzyme was inactivated for 5 min at 95 °C. The product was stored at 4 °C. The qPCR reaction conditions: The total volume of the reaction system was 20 µL.The amplification conditions were performed as follows: (1) The cDNA was pre-denatured, and the DNA polymerase was activated at 95 °C for 2 min. (2) The DNA strands anneal and extend for 30 s at 60 °C. The above two steps were carried out for a total of 40 cycles. The gene relative expression was calculated by the formula 2-(ΔΔCt). The miR-362-3p relative expression was calibrated by U6. To justify the use of U6 as an endogenous control, the stability of U6 was evaluated using the BestKeeper algorithm in the plasma cohort. The coefficient of variation (CV) of U6 Ct values across all samples was less than 2%, indicating high expression stability. Therefore, U6 was validated and selected as the reference gene for normalization of miR‑362‑3p expression in the present study. The downstream sequence of the primers was provided by the kit. The primer sequences were as follows:
miR-362-3p: GCCGAGAACACACCTATTCA.
U6: CTCGCTTCGGCAGCACATATACT.
5. Receiver Operating Characteristic (ROC) curve
The Youden index was used to determine the optimal cut-off value for miR-362-3p in diagnosing breast cancer by calculating the sensitivity and specificity values of the ROC curve. The combined diagnostic model was constructed using binary logistic regression in SPSS, with miR-362-3p, RI, and PI entered as independent variables. Variables were included by the Enter method to generate the predicted probability value of the combined diagnosis for each subject. The formula for the prediction probability (PRE): 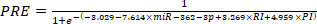 . ROC curves were plotted based on the PRE. The Delong test was used to compare the differences in Area Under Curve (AUC) values between different ROC curves.
6. Definition of outcome parameters
The primary outcome parameter was the overall diagnostic efficacy of the combined model of plasma miR-362-3p and Doppler ultrasound for breast cancer, with pathological diagnosis as the gold standard. The secondary outcome parameters included the diagnostic performance of Doppler ultrasound alone and plasma miR-362-3p alone.
7. Data statistics
The expression levels of miR-362-3p and the ROC curves of the two groups of patients were analyzed using statistical and graphing software. The t-test was used to compare the differences in continuous variables between the two groups. The chi-square test and the fourfold table method were analyzed using SPSS 26.0. The chi-square test was used to evaluate the statistical differences of categorical variables; the two-index combination (miR-362-3p + doppler ultrasound) was regarded as the primary analysis, representing a routine qualitative diagnostic conclusion in clinical practice; if there were any suspicious features derived from the Breast Imaging Reporting and Data System (BI-RADS) classification, the lesion was defined as positive; the fourfold table method was used to calculate the specificity, positive predictive value, negative predictive value, and accuracy of the combined diagnosis of Doppler ultrasound and miR-362-3p. The diagnostic results between Doppler ultrasound and miR-362-3p included true positive (a), false positive (b), false negative (c), and true negative (d). Calculation formula: Sensitivity = a / (a + c); Specificity = d / (d + b); Positive Predictive Value = a / (a + b); Negative Predictive Value = d / (d + c); Accuracy = (a + d) / (a + b + c + d). The three diagnostic methods (miR-362-3p, ultrasound, and combined diagnosis) were performed using the Pearson χ2 test for R×C contingency tables. P < 0.05 was considered statistically significant.
Access restricted. Please log in or start a trial to view this content.
Results
The level of miR-362-3p was significantly decreased in breast cancer patients
The clinical baseline information and clinical pathological characteristics of 182 breast cancer patients and 147 patients with benign breast lesions were compared. The detailed data were summarized in Table 1. The RT-qPCR was used to measure the levels of plasma miR-362-3p in two groups of patients. The results showed that the circulating miR-362-3p expression in breast cancer patie...
Access restricted. Please log in or start a trial to view this content.
Discussion
Breast cancer is one of the most common types of malignant tumors, becoming a major public health issue threatening human health19,20. The high incidence and mortality rates not only cause severe psychological trauma to the families of the patients but also bring about a huge burden on society and the economy. Most breast cancer patients have already experienced local invasion or distant metastasis at the time of diagnosis21,
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| BD Vacutainer K2EDTA Blood Collection Tube (purple cap) | USA | 367861 | For venous blood collection and plasma preparation for miRNA analysis. |
| CFX96 Touch Real-Time PCR Detection System | Bio-Rad Laboratories | 1855195 | 96-well 6-channel fluorescence quantitative PCR instrument, using optical fiber conduction and cold CCD imaging, with synchronous fluorescence collection in each well without delay.The dynamic range reaches 10 orders of magnitude, and it is compatible with both conventional qPCR and high-resolution melting curve (HRM) analysis.The software supports RDML format export, is compatible with both research and clinical testing, and is commonly used in experiments such as gene expression quantification, SNP typing, and methylation analysis. |
| Kirgen 0.1 mL PCR Tubes (or 8-Strip PCR Tubes), Sterile | Shanghai, China | KG0811 | Used for preparing and performing qPCR reactions. |
| Kirgen 1.5 mL Microcentrifuge Tubes, Sterile | Kirgen Biotech Co., Ltd. | KG2911 | Used for sample storage, reagent preparation, and centrifugation during miRNA extraction and reverse transcription. |
| miRcute miRNA Isolation Kit (Spin Column) | Beijing, China | DP501 | For the isolation and purification of total RNA including miRNA from human plasma samples, using spin column-based technology. |
| miRcute Plus miRNA First-Strand cDNA Kit | Beijing, China | KR211 | For the reverse transcription of purified miRNA into first-strand cDNA via the poly(A) tailing method. |
| miRcute Plus miRNA qPCR Kit (SYBR Green) | Beijing, China | FP411 | For quantitative real-time PCR detection of miRNA using SYBR Green I-based chemistry. |
| Roche LightCycler 480 Multiwell Plate 96, White | Mannheim, Germany | 4729692001 | Used for quantitative real-time PCR assays on the Roche LightCycler 480 instrument. |
| Siemens Acuson 14L5 / 14L5 SP Linear Array Probe | Siemens Healthineers | 10041226 | High-frequency linear array probe, with a frequency range of 5–14 MHz, specially designed for the examination of superficial organs such as the breast and thyroid. It features high resolution and excellent tissue contrast, and supports elastography and automatic breast volume scanning. |
| Siemens Acuson S2000/S3000/S1000 Ultrasound System | Siemens Healthineers | / | The color Doppler ultrasound diagnostic system supports real-time 3D/4D imaging and elasticity imaging functions, and is widely used in multiple departments such as abdomen, cardiovascular, gynecology and obstetrics, and breast. |
| Veriti 96-Well Thermal Cycler | Thermo Fisher Scientific | 4375786 | 96-channel gradient PCR instrument, Supports gradient temperature optimization; has high temperature control accuracy; used for cDNA synthesis and conventional PCR amplification. |