This double-blind, placebo-controlled trial evaluated 12 weeks of Weishen Decoction monotherapy in 72 older adults with osteoporosis and kidney-yang deficiency. Outcomes included traditional Chinese medicine syndrome response, low back pain, bone mineral density, bone turnover markers, and safety. Findings provide preliminary support for further larger, longer-term confirmatory clinical trials.
Research Article
Safety and Efficacy of Weishen Decoction in Elderly Patients with Osteoporosis and Kidney-Yang Deficiency: A Randomized Trial
In This Article
Summary
Abstract
This study described the protocol and evaluated the safety and preliminary efficacy of Weishen Decoction monotherapy. This randomized, double-blind, placebo-controlled trial enrolled 72 eligible patients (aged 60–80 years) who were assigned 1:1 to receive either Weishen Decoction granules or placebo for 12 weeks. No background conventional osteoporosis medications (including calcium or vitamin D) were permitted. The primary outcome was the total effective rate based on the traditional Chinese medicine TCM syndrome score reduction (≥30% reduction using the back pain visual analog scale (VAS), bone mineral density (BMD) at lumbar spine and femoral neck, and serum bone metabolism markers (procollagen type I N‑terminal propeptide (PINP), C‑terminal telopeptide of type I collagen (β-CTX), osteocalcin (OC)). Safety was assessed via laboratory tests and adverse event monitoring. All 72 patients completed the trial. The protocol-defined primary outcome showed a higher total effective rate with Weishen Decoction compared with placebo (66.7% vs. 41.7%; P < 0.05). Exploratory BMD findings suggested a between-group difference in femoral neck BMD change (P < 0.05), whereas lumbar spine BMD changes did not differ significantly. Given the 12‑week treatment duration, these BMD results are preliminary and hypothesis‑generating. No serious adverse events occurred in either group. These trial results demonstrate that a 12‑week course of Weishen Decoction monotherapy is feasible and safe in this population. The observed improvements in TCM symptoms and pain, along with suggestive changes in femoral neck BMD, warrant further long‑term confirmatory trials.
Introduction
Osteoporosis is a systemic skeletal disease characterized by reduced bone mass, deterioration of bone microarchitecture, and increased bone fragility. Osteoporotic fractures substantially increase disability and mortality among older adults1,2,3. With the intensification of global population aging, osteoporosis has become a serious public health issue4. In China, the prevalence of osteoporosis in individuals aged 60 years or older is as high as 32%, creating a substantial and increasing clinical and socioeconomic burden.
Currently, the main treatment strategies for senile osteoporosis (SOP) in modern medicine include calcium and vitamin D supplementation, use of anti-resorptive drugs (such as bisphosphonates, RANKL-targeting monoclonal antibodies), and anabolic agents5,6. While these therapies can effectively increase bone mineral density (BMD) and reduce fracture risk, they still face numerous challenges in long-term use. For example, bisphosphonates may lead to osteonecrosis of the jaw or atypical femoral fractures7, while agents such as teriparatide and denosumab are limited by high cost and potential rapid bone loss after discontinuation8. Therefore, exploring safer, more economical, and more suitable alternatives or complementary therapies for long-term management holds significant clinical importance.
Traditional medicine often categorizes osteoporosis under the scope of "bone wilting" (Gu Wei) or "bone withering" (Gu Ku). The Su Wen · Wei Lun states: "The kidney governs the bones and marrow... When kidney qi is hot, the lumbar spine cannot be raised, the bones wither, and the marrow diminishes, leading to bone wilting," establishing kidney deficiency as the core pathogenesis9. The kidney stores essence, governs the bones, and generates marrow. The warming and propelling functions of the primordial yang within the kidney are fundamental to robust bones and balanced metabolism. Kidney-yang deficiency leads to insufficient essence and blood, malnourishment of the marrow, and bones that are insufficiently nourished and weakened, becoming fragile. Clinical manifestations often include cold pain in the lumbar spine, soreness and weakness, aversion to cold, and cold limbs10. Therefore, warming and tonifying kidney-yang has become an important principle in TCM for preventing and treating kidney-yang-deficient osteoporosis11.
Weishen Decoction (also known as Weishen Pill) originates from Liu Wansu's Suwen Bingji Qiyi Bao Ming Ji from the Jin Dynasty, originally indicated for "impairment of the liver and kidney affecting the spleen, poor digestion of food, and low back pain preventing rising11." The formula uses Eucommia bark (Du Zhong) and Psoralea fruit (Bu Gu Zhi) as the sovereign herbs to warm the kidney, strengthen yang, and fortify tendons and bones; Dodder seed (Tu Si Zi), Fenugreek (Hu Lu Ba), and Cyathula root (Chuan Niu Xi) as minister herbs to tonify the liver and kidney and dispel wind-dampness; assisted by Saposhnikovia root (Fang Feng), Dioscoreae hypoglaucae rhizoma (Bi Xie), Tribulus fruit (Bai Ji Li), and Cinnamon bark (Rou Gui) to dispel wind-dampness, benefit the lower jiao, pacify the liver and subdue yang, and warm and unblock the channels. Together, these herbs are traditionally considered to synergistically warm and tonify kidney-yang and replenish essence to strengthen bones. Preliminary animal experiments have shown that Weishen Decoction may improve bone metabolism and promote bone formation by modulating signaling pathways, including TGF-β/Smad2 and MAPK12. However, in clinical practice, this formula is most often used in combination with Western medicine. There is a lack of high-quality, rigorously designed clinical research evidence to support its efficacy and safety as a monotherapy for kidney-yang deficient senile osteoporosis.
To clarify the positioning of Weishen Decoction monotherapy, this paper compares it with mainstream clinical interventions. Conventional pharmacotherapy mainly includes bisphosphonates, denosumab, and teriparatide, which may be used with or without calcium and vitamin D supplements. These regimens can effectively reduce fracture risk and deliver reliable long-term efficacy, yet they have notable drawbacks. They may cause severe adverse reactions such as osteonecrosis of the jaw and atypical femoral fractures, and are associated with high costs and poor tolerability in some elderly patients. In addition, rapid bone loss commonly occurs after discontinuation of denosumab. Although calcium and vitamin D supplementation alone are safe and affordable, it exerts a limited effect on fracture prevention among elderly individuals with adequate vitamin D status5,6. It is merely an adjunctive therapy rather than a disease-modifying treatment.
Another common approach is combined therapy with Chinese herbal formulas and conventional pharmacotherapy, which helps relieve clinical symptoms and reduce the dosage of Western drugs. Nevertheless, such add-on designs are confounded by background treatments, making it impossible to identify the independent therapeutic effect of herbal medicines. Furthermore, most relevant studies lack rigorous blinding, placebo control, and standardized criteria for TCM syndrome differentiation. For this reason, the true efficacy of kidney-tonifying herbal formulas, including Weishen Decoction, when used alone, remains unclear. There is therefore an urgent clinical need to verify whether standardized Chinese herbal formulas can serve as effective monotherapies, offering an alternative for patients who prefer pure TCM treatment or have contraindications to conventional Western medications.
This study adopts a placebo-controlled monotherapy design without calcium and vitamin D supplementation for the following reasons. First, it enables an unbiased assessment of the standalone efficacy of Weishen Decoction while eliminating confounding factors from background treatments. Second, no high-quality clinical trials have yet to confirm the independent effects of Weishen Decoction in this patient population, and a placebo-controlled design can yield the most rigorous evidence. Third, given the 12-week intervention period and close monitoring throughout the trial, withholding calcium and vitamin D was considered ethically acceptable under the study’s eligibility criteria and monitoring procedures. This design aims to address a key clinical question: Can monotherapy with Weishen Decoction improve clinical symptoms, pain severity, bone metabolism, and bone mineral density in elderly patients with senile osteoporosis of kidney-yang-deficiency pattern?
This study intends to fill the research gap. To our knowledge, this is the first clinical trial to evaluate the efficacy and safety of Weishen Decoction, used alone (without conventional anti-osteoporosis medications), in senile osteoporosis with a kidney-yang-deficiency pattern. The findings will provide preliminary evidence to support the precise clinical application of this formula and inform the design of subsequent confirmatory clinical trials.
Protocol
This study was performed in line with the principles of the Declaration of Helsinki. The study was approved by the Ethics Committee of Xuzhou Central Hospital (approval no. XZXY-LK-20230320-037). The trial was registered in the National Medical Research Registration System (No.: MR-32-23-014328).
Trial design
This was a prospective, single‑center, randomized, double‑blind, placebo‑controlled clinical trial designed to evaluate the clinical efficacy and safety of Weishen Decoction monotherapy in kidney-yang-deficient senile osteoporosis.
Recruitment and enrollment
Participants were recruited from the outpatient clinic of the Department of Orthopedics and TCM at Xuzhou Central Hospital between April 2023 and September 2024. A research coordinator screened electronic medical records daily for patients aged 60–80 years with diagnostic codes for osteoporosis (M80–M81) and presenting symptoms of back pain, soreness, and weakness in the waist and knees. Potentially eligible patients were then contacted by telephone using a standardized script that explained the study's purpose, the 12-week, double-blind, placebo‑controlled design, the absence of background calcium or vitamin D supplementation, and the availability of rescue treatment if needed. Patients who remained interested were scheduled for a screening visit. At screening, written informed consent was obtained from all participants before any study‑specific procedures. A screening log was maintained to record all contacted patients, reasons for exclusion, and those who declined participation. After consent, a fasting blood sample was drawn to measure serum 25‑hydroxyvitamin D₃ (a concentration≥20 ng/mL was required for inclusion), calcium, phosphorus, and bone turnover markers (PINP, β‑CTX, OC) using an automated biochemical analyzer. A dual‑energy X‑ray absorptiometry (DXA) device was used to measure bone mineral density at the lumbar spine (L1–L4) and left femoral neck. TCM syndrome differentiation was performed independently by two attending TCM physicians using a standardized case report form (CRF); any disagreement was resolved by discussion with a third senior TCM physician. All inclusion and exclusion criteria were checked against a preprinted checklist. Eligible participants were then scheduled for a baseline assessment within 7 days before randomization.
Sample size calculation
The sample size was calculated based on the primary outcome—the total effective rate (dichotomous outcome). According to two previously published meta‑analyses of TCM interventions for primary osteoporosis13,14, the reported total effective rates (based on TCM syndrome score reduction) for kidney‑tonifying herbal formulas ranged from approximately 60% to 75% in treatment groups and from 35% to 50% in placebo or control groups. Based on these estimates, effective rates of 66% for the Weishen Decoction group and 40% for the placebo group were assumed. Using a two‑sided α = 0.05 and β = 0.20 (power = 80%), sample size estimation for comparing two independent proportions was performed with dedicated sample size calculation software. The following parameters were entered: p1 = 0.66, p2 = 0.40, α = 0.05, power = 0.80, allocation ratio N2/N1 = 1. The calculation indicated that 33 patients per group were needed. Considering an approximate 10% dropout rate, a total sample size of 72 patients was ultimately determined, with 36 patients in each group. The software output and analysis settings were saved as a PDF and stored in the trial master file.
Randomization and blinding
A stratified block randomization method was employed. Stratification factors were age group (60–70 years vs. 71–80 years) and sex (male vs. female). A fixed block size of 4 was used. An independent statistician not involved in participant recruitment, treatment, or efficacy evaluation used randomization software to generate the allocation sequence. The following procedure was followed: (1) a new blank dataset was created with 72 rows; (2) stratification variables (age group and sex) and a sequential participant ID (1–72) were entered; (3) within each stratum, a uniform random number between 0 and 1 was generated; (4) participants were sorted by stratum and by the random number; (5) within each block of size 4, the first two were assigned to Weishen Decoction (code A) and the next two to placebo (code B); (6) the final allocation table was printed. The random sequence was printed and sealed in sequentially numbered opaque envelopes. These envelopes were stored in a locked cabinet in the hospital's central pharmacy, accessible only to the dispensing pharmacist, who was not involved in any other trial procedures. After enrollment and baseline assessment, the research coordinator assigned the next available participant ID (in ascending order) and retrieved the corresponding envelope from the pharmacy. The envelope was opened by the pharmacist only after the participant had completed all baseline assessments and eligibility had been confirmed. The pharmacist then prepared the study medication according to the allocation code and recorded the assignment on a secure allocation log (kept in a separate locked file). The study drugs (Weishen Decoction granules and the matching placebo) were identical in appearance, odor, packaging, and weight (each sachet weighed approximately 12.05 g). The pharmacy prepared a 4‑week supply of study medication for each participant according to the randomization envelope. For each participant, a set of labeled containers (one per 4‑week interval) was filled with the allocated sachets. Each container label included the participant ID, container number (e.g., W1, W2, W3 for weeks 1–4, 5–8, 9–12), and the instruction “Take one sachet twice daily after meals.” A separate dispensing log recorded participant ID, container number, number of sachets dispensed (28 per container), date of dispensing, and the dispensing pharmacist's initials. The log was signed and dated by both the pharmacist and a second independent pharmacy technician who verified the count. Participants, clinical investigators (responsible for enrollment, treatment, and follow‑up), efficacy evaluators, and data statisticians were all blinded to group assignments, which remained concealed until database lock and completion of the prespecified analyses. No unplanned unblinding events occurred during the study.
Diagnostic criteria
Western medical diagnosis of osteoporosis was based on the Guidelines for the Diagnosis and Treatment of Primary Osteoporosis (2022)15. Dual‑energy X‑ray absorptiometry was used to measure bone mineral density at the lumbar spine (L1–L4) or femoral neck, and a T‑score ≤−2.5 was used to confirm the diagnosis16. TCM diagnostic criteria for the kidney‑yang-deficiency pattern followed the Expert Consensus on TCM for Prevention and Treatment of Primary Osteoporosis (2020)16. The main symptoms were cold pain in the back and waist, and soreness and weakness of the waist and knees. Secondary symptoms included aversion to cold and a preference for warmth (aggravated by cold), as well as frequent urination or nocturia. Tongue and pulse findings included a pale, swollen tongue with a white, slippery coating and a deep, thready or slow pulse. Diagnosis required all main symptoms plus at least one secondary symptom, combined with the tongue and pulse presentation. Each symptom was quantified to calculate a total TCM syndrome score. According to the Expert Consensus on TCM for Prevention and Treatment of Primary Osteoporosis (2020)17, primary symptoms (cold pain in the back and waist, soreness and weakness of the waist and knees) were scored on a a four-level scale scored as 0, 2, 4, or 6 (0 = none, 2 = mild, 4 = moderate, 6 = severe), with the severity of cold pain in the back and waist anchored to VAS scores (mild: 1–3; moderate: 4–6; severe: 7–10). Secondary symptoms (limited lumbar activity, aversion to cold and preference for warmth, frequent urination or nocturia) were scored on a 0–1–2–3 scale (0 = none, 1 = mild, 2 = moderate, 3 = severe). All evaluators were trained on these criteria and pilot‑tested on 10 patients before the study to ensure inter‑rater consistency (intraclass correlation coefficient ≥0.85).
Inclusion, exclusion, and withdrawal criteria
Inclusion criteria were: age 60–80 years; meeting the above Western medical diagnostic and TCM kidney‑yang-deficiency pattern criteria; no use of drugs affecting bone metabolism (e.g., bisphosphonates, teriparatide, denosumab) within 3 months prior to enrollment; stable vital signs, clear consciousness, ability to cooperate with scale assessments and follow‑up; and voluntary participation with signed informed consent. Exclusion criteria were: secondary osteoporosis (e.g., hyperparathyroidism, Cushing’s syndrome, long‑term glucocorticoid use); comorbid severe primary diseases of the ardiac, hepatic, renal, or hematologic disease, or malignant tumors; a history of hypersensitivity or known allergy to any ingredient of the study drug; comorbid lumbar compression fractures, severe spinal deformities, or a history of joint replacement affecting BMD measurement affecting the accuracy of BMD measurement; a cognitive or psychiatric condition that precluded informed consent or completion of study procedures; and concurrent participation in another clinical study. Discontinuation and withdrawal criteria were: occurrence of serious adverse events deemed by the investigator to preclude continuation; poor participant compliance (medication adherence rate <80% or loss to follow‑up); withdrawal of consent; and occurrence of clinical events that required standard treatment and urgent intervention during the study.
Treatment methods
This study did not include conventional pharmacotherapy (background treatment: calcium and vitamin D). Participants received either Weishen Decoction or a matching placebo to assess its independent efficacy. The Weishen Decoction group received oral Weishen Decoction granules (prepared by a Chinese pharmaceutical company; Batch No.: 20240217). The granules were manufactured using a standardized water extraction and spray‑drying process. The daily crude herb equivalent (total 111 g) yielded approximately 20.5 g of extract after spray‑drying. After adding dextrin (15% w/w), the total daily granule weight was approximately 24.1 g, divided equally between two sachets (each containing approximately 12.05 g of granules, equivalent to 55.5 g of crude herb and 10.25 g of dry extract per sachet). Participants dissolved one sachet in 150–200 mL of warm water and consumed it after breakfast and again after dinner. The control group received oral matching placebo granules identical in appearance, color, odor, and taste (Batch No.: 20240211; made from dextrin, caramel, and food coloring, without pharmacological activity), packaged identically and with the same dosing regimen. The treatment course for both groups was 12 weeks. Throughout the 12‑week treatment period, patients were monitored at weeks 4, 8, and 12. Any participant who developed a new fragility fracture, significant worsening of back pain limiting mobility, or a clinically meaningful decline in functional status was to be withdrawn from the trial and referred for standard care osteoporosis management. No such withdrawals occurred.
Adherence monitoring
Medication adherence was assessed using a combined method of sachet count and patient diary. A 4-week twice-daily supply should ordinarily contain 56 sachets. Participants were instructed to return all sachets, used and unused, at each follow‑up visit (weeks 4, 8, and 12). At each visit, study staff counted the returned sachets and recorded the count on a standardized adherence log.
The adherence rate for each interval was calculated as:
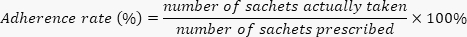
where "number of sachets actually taken" was derived from (sachets dispensed at previous visit) − (sachets returned at current visit).
Each participant also received a paper diary to record the date and time of each sachet intake. Diaries were reviewed and signed by the study coordinator at each follow‑up visit. Discrepancies between diary entries and sachet counts were reconciled through participant interviews; if unresolved, the more conservative estimate was used. An adherence rate of ≥80% over the entire 12-week period was considered acceptable. Participants with adherence <80% at week 4 or week 8 received additional counseling; if adherence remained <80% at the subsequent visit, they were considered non‑adherent and withdrawn from the per‑protocol analysis (but were still followed for safety and included in the intention‑to‑treat analysis). After a missed dose, participants were instructed not to double the next dose but to resume the regular schedule.
Observation measures and evaluation methods
The primary outcome was the total effective rate, defined as the reduction in TCM syndrome score. TCM syndrome scores were assessed before treatment and after 12 weeks of treatment. Using the Nimodipine method ([(baseline score − post-treatment score) / baseline score] × 100%), “markedly effective” was defined as a syndrome score reduction rate ≥70%, “effective” as 30% ≤ reduction rate <70%, and “ineffective” as reduction rate <30%. The total effective rate was calculated as (number of participants classified as markedly effective or effective) / total number of cases × 100%. Key secondary outcomes were the change in total TCM syndrome score (continuous variable) and the change in low back pain intensity measured by the Visual analog scale (VAS, 0–10 scale)17. Exploratory secondary outcomes included changes in bone mineral density (BMD) at the lumbar spine and femoral neck, changes in serum bone metabolism markers (PINP, β‑CTX, OC, Ca, P, 25(OH)D₃, bone-specific alkaline phosphatase (BALP)), and safety indices. BMD was measured using a DXA device by the same certified technician, blinded to group assignment, at baseline (within 7 days before randomization) and at the post‑treatment follow‑up visit (within 12 weeks after treatment completion)4,19. Fasting venous blood was drawn before treatment and after 12 weeks for measurement of bone metabolism markers using an automated electrochemiluminescence immunoanalyzer. Safety was assessed through continuous adverse event (AE) monitoring; scheduled laboratory tests (complete blood count, urinalysis, liver and kidney function tests, electrocardiography (ECG)) at baseline and at week 12; and physical examinations at each visit (weeks 4, 8, and 12). All AEs were collected via spontaneous reporting and active inquiry at each visit. Severity was graded using the
Common Terminology Criteria for Adverse Events (CTCAE).
Clinical safety instructions and stopping rules
An independent Data and Safety Monitoring Board(DSMB) consisting of a clinical pharmacologist, a geriatrician, and a biostatistician convened every 6 weeks to review all safety data. The following safety rules were predefined. Any serious adverse event (SAE)—defined as death, a life-threatening event, initial or prolonged hospitalization, persistent or substantial disability, or a congenital anomaly, or prolongation of existing hospitalization, persistent or significant disability, or congenital anomaly—was to be reported to the ethics committee within 24 hours and to the DSMB within 48 hours. Unblinding of the affected participant could be performed by the principal investigator only if knowledge of the treatment assignment was deemed essential for patient management. The unblinding procedure was managed by the central pharmacy, which maintained the allocation code in a sealed envelope. If an SAE was judged as possibly, probably, or related to the study drug, the DSMB would recommend discontinuation of the affected participant and, if multiple similar SAEs occurred, suspension of the entire trial. For non‑serious AEs, treatment could be continued at the investigator’s discretion; if an AE caused persistent discomfort or became moderate to severe (grade 2 or higher) and did not resolve within 7 days, the investigator could withdraw the participant from the study. The trial would be stopped early if (i) two or more SAEs were related to the study drug; (ii) a previously unrecognized serious toxicity emerged; or (iii) the DSMB recommended stopping due to futility or harm.
Data handling and statistical methods
All case report forms (CRF) were completed by trained study coordinators and independently entered twice into an electronic database by two independent data entry clerks. The two entries were compared using the software’s built‑in validation module; discrepancies were resolved by referring to the original source documents. A data query log was maintained. After the last participant completed the week‑12 visit and all queries were resolved, the principal investigator and the data manager locked the database. The locked database was exported to statistical analysis software for analysis. The syntax file containing all data transformations, variable labeling, and analysis commands (including the χ2 test for the primary outcome, independent t‑tests for change scores, and ANCOVA sensitivity analyses) was saved and archived with the trial master file. Statistical analysis was conducted on both the Full Analysis Set and the Per‑Protocol Set; because no patients withdrew and no major protocol deviations occurred, the two sets were identical. For the primary outcome (total effective rate), the χ2 test was used. For continuous secondary outcomes, change scores (post‑treatment minus baseline) were compared between groups using independent‑sample t‑tests (for normally distributed changes) or Mann‑Whitney U tests (for non‑normally distributed changes). As a sensitivity analysis, analysis of covariance (ANCOVA) was performed to adjust for baseline values, yielding consistent results. All statistical tests were two‑sided, with P < 0.05 considered statistically significant. No interim analysis was planned or performed.
Results
Participant flow, blinding validation, and follow-up completeness
Randomization and allocation
72 patients were randomized (36 to Weishen Decoction, 36 to placebo). All 72 received the assigned intervention; no protocol deviations occurred.
Blinding integrity
Blinding was not formally assessed (e.g., using the James Blinding Index). However, no unplanned unblinding events were reported. The placebo and active granules were identical in appearance, taste, and packaging, and no group-specific adverse events indicative of allocation were observed (mild AEs were similar between groups: 8.3% vs. 5.6%). No unplanned unblinding events were reported.
Follow-up and withdrawals:
All 72 patients (100%) completed the 12‑week treatment, all follow-up visits (weeks 4, 8, and 12), and the post-treatment BMD assessment. No patient withdrew, was lost to follow-up, or met discontinuation criteria. The post‑treatment BMD assessment was performed at a mean (SD) of 6.5 (3.2) days (Weishen Decoction) and 6.8 (3.5) days (placebo) after the last dose.
A CONSORT flow diagram is summarized in Figure 1.
Baseline data analysis
The Full Analysis Set (FAS) and Per‑Protocol Set (PPS) were identical, and all analyses are reported for this single set of 72 patients. There were no statistically significant differences between the two groups in terms of sex distribution, age, weight, and other general characteristics (P > 0.05), indicating comparability (Table 1).
Adherence
Medication adherence was assessed at weeks 4, 8, and 12 using sachet counts and patient diaries. In the Weishen Decoction group, the mean adherence rates were 97.1% ± 2.3% at week 4, 96.4% ± 2.9% at week 8, and 95.8% ± 2.9% at week 12. In the placebo group, the mean adherence rates were 96.8% ± 2.5% at week 4, 96.1% ± 2.7% at week 8, and 95.5% ± 3.0% at week 12. No significant between-group differences were observed at any time point (all P > 0.05). All 72 patients maintained adherence rates ≥80% throughout the 12‑week treatment period, and no patient was withdrawn due to nonadherence.
TCM syndrome scores and efficacy
Baseline TCM syndrome scores were comparable between the two groups (all P > 0.05). After 12 weeks of treatment, the change scores for core kidney-yang deficiency symptoms (cold pain in the back and waist, soreness and weakness, and aversion to cold) were significantly greater in the Weishen Decoction group compared with the placebo group (all P < 0.05; Table 2). For symptoms of limited activity and frequent urination, the change scores did not differ significantly between groups (P > 0.05). The reduction in total TCM syndrome score (change score) was significantly larger in the Weishen Decoction group than in the placebo group (mean change: −4.8 ± 1.5 vs. −1.6 ± 1.8; between-group difference: −2.9 (Weishen Decoction minus placebo), 95% CI: −4.1 to −1.7; P < 0.001) (Table 2).
The total effective rate based on TCM syndrome score reduction was significantly higher in the Weishen Decoction group than in the control group (66.7% vs. 41.7%; rate difference, 25.0%, 95% CI: 3.9%–46.1%; P = 0.027) (Table 3).
Pain score: Low back pain (VAS)
The change in VAS pain score from baseline to week 12 was significantly greater in the Weishen Decoction group than in the placebo group (mean change: −1.3 ± 1.1 vs. −0.5 ± 1.0; between-group difference: −0.8, 95% CI: −1.5 to −0.1; P = 0.024) (Table 4). Exploratory within-group analyses showed a significant decrease in the Weishen Decoction group (P = 0.001) but not in the placebo group (P = 0.176).
Changes in bone mineral density (BMD)
The change in femoral neck T-score from baseline to week 12 was significantly greater in the Weishen Decoction group than in the placebo group (mean change: +0.3 ± 0.4 vs. +0.1 ± 0.5; between-group difference: +0.2, 95% CI: +0.03 to +0.57; P = 0.032). Similarly, the change in femoral neck BMD was significantly greater in the Weishen Decoction group (mean change: +0.1 ± 0.03 vs. 0.0 ± 0.04; between-group difference: +0.1, 95% CI: +0.04 to +0.16; P = 0.001). For lumbar spine BMD and T-score, no significant between-group differences were observed in change scores (all P > 0.05) (Table 5). Within-group comparisons (descriptive) showed significant improvements in femoral neck parameters only in the Weishen Decoction group.
Timing of post-treatment BMD assessments
Per protocol, post-treatment BMD assessments were allowed within 28 days of completion of the 12‑week treatment. The actual mean (SD) time from the last dose to BMD measurement was 6.5 (3.2) days (range: 2–14 days) in the Weishen Decoction group and 6.8 (3.5) days (range: 2–15 days) in the placebo group. No patient required the full 28‑day window. The between‑group difference was not significant (P = 0.71). Thus, all post‑treatment BMD measurements were obtained within a narrow, balanced time window.
Bone metabolism markers
The change scores for serum β-CTX, PINP, and OC were significantly greater in the Weishen Decoction group compared with the placebo group (β-CTX: mean change −127.7 ± 50.2 vs. −47.9 ± 68.1, P = 0.002; PINP: −12.1 ± 9.5 vs. −6.3 ± 10.2, P = 0.004; OC: −3.0 ± 3.5 vs. −1.5 ± 3.8, P = 0.013). No significant between-group differences were observed for changes in Ca, P, 25(OH)D₃, or BALP (all P > 0.05) (Table 6).
Safety outcomes
Adverse events were assessed at each scheduled visit (weeks 4, 8, and 12) and via continuous spontaneous reporting. During the 12‑week treatment period, no serious adverse events were reported in either group. Mild adverse events occurred in 3 patients (8.3%) in the Weishen Decoction group (mild gastrointestinal discomfort, n = 2; mild dizziness, n = 1) and in 2 patients (5.6%) in the control group (mild gastrointestinal discomfort, n = 1; mild dry mouth, n = 1). All AEs resolved without medical intervention, and no participant discontinued treatment because of an AE. Laboratory safety indices (AST, ALT, serum creatinine, BUN) showed no clinically significant changes from baseline to week 12 in either group. Between-group comparisons of change scores revealed no statistically significant differences (all P > 0.05; Table 7). No stopping criteria were met during the trial. All safety decisions and their rationales were documented in DSMB meeting minutes.
DATA AVAILABILITY:
The de-identified individual participant data (including baseline characteristics, primary and secondary outcome measures, and adverse event records) that underlie the results reported in this article, as well as the study protocol, statistical analysis plan, and annotated CRF templates, have been deposited in a public repository. All raw data are publicly available on Zenodo under the DOI:10.5281/zenodo. 20527390 (or the permanent identifier provided upon final deposition). The repository contains the complete dataset in CSV format, a data dictionary, and the analysis syntax files. No login or special permission is required to access the data.
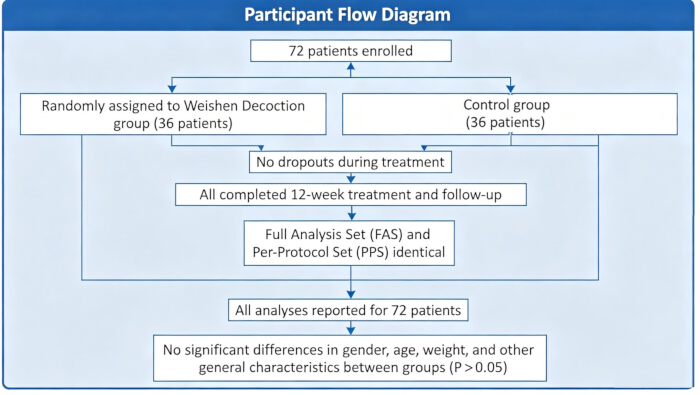
Figure 1: Participant flow diagram. A total of 72 elderly patients with kidney‑yang deficient senile osteoporosis were enrolled and randomly assigned in a 1:1 ratio to receive either Weishen Decoction granules (n = 36) or a matching placebo (n = 36) for 12 weeks. All 72 patients (100%) completed the 12‑week treatment period and all scheduled follow‑up visits (weeks 4, 8, and 12, as well as the post‑treatment bone mineral density assessment). No patient withdrew from the study, was lost to follow‑up, or was excluded from the analysis. Therefore, the Full Analysis Set (FAS) and Per‑Protocol Set (PPS) were identical, comprising all 72 randomized participants. Baseline characteristics were well balanced between the two groups, with no statistically significant differences in sex, age, weight, or other general characteristics (all P > 0.05). All analyses reported in this study are based on this full cohort of 72 patients. Please click here to view a larger version of this figure.
| Characteristic | Weishen Decoction Group (n = 36) | Control Group (n = 36) | P value |
| Sex (Male/Female) | 15 / 21 | 13 / 23 | 0.516 |
| Age (years) | 68.2 ± 7.5 | 67.5 ± 7.8 | 0.699 |
| Weight (kg) | 62.8 ± 8.9 | 61.9 ± 9.1 | 0.672 |
| Lumbar spine BMD (g/cm²) | 0.8 ± 0.2 | 0.8 ± 0.2 | 0.876 |
| Lumbar spine T-score | −2.4 ± 1.4 | −2.4 ± 1.5 | 0.923 |
| Femoral neck BMD (g/cm²) | 0.6 ± 0.2 | 0.6 ± 0.2 | 0.912 |
| Femoral neck T-score | −2.7 ± 1.0 | −2.7 ± 1.2 | 0.885 |
| VAS pain score | 4.1 ± 1.6 | 4.0 ± 1.6 | 0.854 |
| β-CTX (ng/mL) | 620.5 ± 25.3 | 658.2 ± 278.1 | 0.432 |
| PINP (ng/mL) | 48.9 ± 16.5 | 49.8 ± 18.9 | 0.827 |
| OC (ng/mL) | 16.9 ± 4.8 | 17.1 ± 5.8 | 0.875 |
| 25(OH)D₃ (ng/mL) | 17.8 ± 8.5 | 18.9 ± 8.8 | 0.593 |
| Calcium (mmol/L) | 2.3 ± 0.1 | 2.3 ± 0.1 | 0.762 |
| Phosphorus (mmol/L) | 1.1 ± 0.2 | 1.1 ± 0.2 | 0.935 |
Table 1: Baseline Characteristics. Data are presented as mean ± standard deviation or number (%), as appropriate. P values are from an independent t-test for continuous variables or a χ2 test for sex. β‑CTX: C‑terminal telopeptide of type I collagen; PINP: procollagen type I N‑terminal propeptide; OC: osteocalcin; 25(OH)D₃: 25‑hydroxyvitamin D₃; BMD: bone mineral density; VAS: visual analog scale.
| Item | Group | Baseline | Week 12 | Within-group P | Change Score (Week 12 – Baseline) | Between-Group Difference in Change Scores (95% CI) | P value |
| Low back cold pain | Weishen | 3.3 ± 1.4 | 2.2 ± 1.5 | 0.008 | −1.1 ± 0.9 | −0.7 (−1.3 to −0.1) | 0.038 |
| Control | 3.2 ± 1.5 | 2.9 ± 1.6 | 0.089 | −0.3 ± 0.8 | |||
| Soreness/weakness | Weishen | 3.4 ± 1.6 | 1.9 ± 1.5 | 0.002 | −1.5 ± 0.9 | −0.8 (-1.4 to -0.2) | 0.038 |
| Control | 3.4 ± 1.5 | 2.7 ± 1.7 | 0.074 | −0.7 ± 1.0 | |||
| Limited mobility | Weishen | 2.6 ± 1.9 | 2.1 ± 1.4 | 0.152 | −0.5 ± 1.2 | −0.2 (-0.9 to 0.5) | 0.574 |
| Control | 2.3 ± 1.7 | 2.3 ± 1.6 | 0.856 | 0.0 ± 1.1 | |||
| Fear of cold | Weishen | 2.5 ± 1.9 | 1.7 ± 1.5 | 0.031 | −0.8 ± 1.1 | −0.6 (-1.3 to 0.1) | 0.077 |
| Control | 2.4 ± 1.9 | 2.4 ± 1.8 | 0.924 | 0.0 ± 1.0 | |||
| Frequent urination | Weishen | 2.4 ± 1.7 | 1.9 ± 1.5 | 0.063 | −0.5 ± 1.1 | −0.3 (-1.0 to 0.4) | 0.383 |
| Control | 2.6 ± 1.6 | 2.2 ± 1.4 | 0.121 | −0.4 ± 1.0 | |||
| Total score | Weishen | 14.2 ± 3.4 | 9.4 ± 3.3 | <0.001 | −4.8 ± 1.5 | −2.9 (−4.1 to −1.7) | <0.001 |
| Control | 13.9 ± 3.8 | 12.3 ± 4.2 | 0.068 | −1.6 ± 1.8 |
Table 2: Comparison of traditional Chinese medicine Syndrome Scores. Between-group comparison of the change from baseline (Between-group differences in changes from baseline were assessed using an independent-samples t-test). Data are presented as mean ± SD. P < 0.05 indicates statistically significant results.
| Indicator | Weishen Decoction Group (n = 36) | Control Group (n = 36) | Statistical Value |
| Sample size | 36 | 36 | -- |
| Markedly effective, n (%) | 5 (13.9%) | 4 (11.1%) | -- |
| Effective, n (%) | 19 (52.8%) | 11 (30.6%) | -- |
| Ineffective, n (%) | 12 (33.3%) | 21 (58.3%) | -- |
| Total effective rate, n (%) | 24 (66.7%) | 15 (41.7%) | Rate difference: 25.0% (95% CI: 3.9%–46.1%) |
| χ² value | -- | -- | 4 |
| P value | -- | -- | 0.046 |
Table 3: Comparison of total effective rate [n (%)]. Efficacy analysis was based on the dichotomized total effective rate (effective = markedly effective + effective; ineffective = ineffective). χ2 test with continuity correction (χ2 = 4.0, df = 1) was used to compare the total effective rate between groups. The rate difference (Weishen Decoction minus placebo group) and its 95% confidence interval (CI) were calculated using the normal approximation method. P < 0.05 indicates statistically significant results.
| Group | Sample Size | Baseline | Week 12 | Change Score (Week 12 – Baseline) | Within group P value |
| Weishen Decoction | 36 | 4.1 ± 1.6 | 2.8 ± 1.6 | −1.3 ± 1.1 | 0.001 |
| Control | 36 | 4.0 ± 1.6 | 3.5 ± 1.5 | −0.5 ± 1.0 | 0.176 |
| Between-Group Difference in Change Scores (95% CI) | −0.8 (−1.5 to −0.1) | ||||
| Between group P value | 0.024 |
Table 4: Comparison of VAS Pain Scores. Between-group comparison of the change from baseline (Between-group differences in changes from baseline were assessed using an independent-samples t-test). Data are presented as mean ± SD. P < 0.05 indicates statistically significant results.
| Site | Group | Baseline | Post-treatment | Change Score (Post – Baseline) | Between-Group Difference in Change Scores (95% CI) | Within-Group P value | Between-Group P value |
| Lumbar spine | |||||||
| T-score | Weishen | −2.4 ± 1.4 | −2.3 ± 1.4 | +0.1 ± 0.5 | =+0.1 (−0.3 to +0.5) | 0.846 | 0.784 |
| Control | −2.4 ± 1.5 | −2.4 ± 1.6 | 0.0 ± 0.5 | 0.784 | |||
| BMD (g/cm²) | Weishen | 0.8 ± 0.2 | 0.8 ± 0.1 | 0.0 ± 0.1 | =0.0 (−0.1 to +0.1) | 0.423 | 0.657 |
| Control | 0.8 ± 0.2 | 0.9 ± 0.1 | +0.1 ± 0.1 | 0.657 | |||
| Femoral neck | |||||||
| T-score | Weishen | −2.7 ± 1.0 | −2.4 ± 1.1 | +0.3 ± 0.4 | =+0.3 (+0.03 to +0.57) | 0.012 | 0.032 |
| Control | −2.7 ± 1.2 | −2.6 ± 1.3 | +0.1 ± 0.5 | 0.847 | |||
| BMD (g/cm²) | Weishen | 0.6 ± 0.2 | 0.7 ± 0.1 | +0.1 ± 0.03 | +0.1 (+0.04 to +0.16) | 0.006 | 0.001 |
| Control | 0.6 ± 0.2 | 0.6 ± 0.3 | 0.0 ± 0.04 | 0.759 |
Table 5: Bone Mineral Density (BMD) Results. Between-group comparison of the change from baseline (Between-group differences in changes from baseline were assessed using an independent-samples t-test). Data are presented as mean ± SD. P < 0.05 indicates statistically significant results.
| Marker | Group | Baseline | Week 12 | Change Score (Week 12 – Baseline) | Between-Group Difference in Change Scores (95% CI) | Within-Group P value | Between-Group P value |
| Ca (mmol/L) | Weishen | 2.3 ± 0.1 | 2.4 ± 0.1 | +0.1 ± 0.1 | +0.1 (−0.1 to +0.3) | 0.759 | 0.812 |
| Control | 2.3 ± 0.1 | 2.3 ± 0.1 | 0.0 ± 0.1 | 0.947 | |||
| P (mmol/L) | Weishen | 1.1 ± 0.2 | 1.1 ± 0.3 | 0.0 ± 0.2 | 0.0 (−0.1 to +0.1) | 0.543 | 0.698 |
| Control | 1.1 ± 0.2 | 1.1 ± 0.2 | 0.0 ± 0.2 | 0.985 | |||
| 25(OH)D₃ (ng/mL) | Weishen | 17.8 ± 8.5 | 20.1 ± 10.3 | +2.3 ± 5.6 | −0.7 (−5.8 to +4.4) | 0.074 | 0.764 |
| Control | 18.9 ± 8.8 | 20.5 ± 10.6 | +1.6 ± 5.9 | 0.157 | |||
| β-CTX (ng/mL) | Weishen | 620.5 ± 25.3 | 492.8 ± 96.5 | −127.7 ± 50.2 | −84.5 (−139.2 to -29.8) | 0.002 | 0.002 |
| Control | 658.2 ± 278.1 | 610.3 ± 281.4 | −47.9 ± 68.1 | 0.015 | |||
| PINP (ng/mL) | Weishen | 48.9 ± 16.5 | 36.8 ± 18.7 | −12.1 ± 9.5 | −8.3 (−14.0 to -2.6) | 0.001 | 0.004 |
| Control | 49.8 ± 18.9 | 43.5 ± 19.3 | −6.3 ± 10.2 | 0.217 | |||
| BALP (ng/L) | Weishen | 16.5 ± 4.3 | 15.1 ± 4.7 | −1.4 ± 2.8 | −0.6 (−2.5 to +1.3) | 0.127 | 0.592 |
| Control | 16.7 ± 3.4 | 15.5 ± 4.8 | −1.2 ± 3.1 | 0.239 | |||
| OC (ng/mL) | Weishen | 16.9 ± 4.8 | 13.9 ± 4.9 | −3.0 ± 3.5 | −2.3 (−4.1 to -0.5) | 0.018 | 0.013 |
| Control | 17.1 ± 5.8 | 15.6 ± 5.2 | −1.5 ± 3.8 | 0.092 |
Table 6: Comparison of Bone Metabolism Markers. β-CTX: C-terminal telopeptide of type I collagen; PINP: procollagen type I N-terminal propeptide; BALP: bone-specific alkaline phosphatase; OC: osteocalcin. Within-group P value: paired t-test comparing after treatment vs. before treatment. Between-group comparison of the change from baseline (Between-group differences in changes from baseline were assessed using an independent-samples t-test). Data are presented as mean ± SD. P < 0.05 indicates statistically significant results.
| Indicator | Group | Baseline | Post-treatment | Change Score (Post – Baseline) | Between-Group Difference in Change Scores (95% CI) | Within-Group P value | Between-Group P value |
| AST (U/L) | Weishen | 32.1 ± 3.4 | 32.8 ± 4.9 | +0.7 ± 4.2 | =+0.1 (−2.4 to +2.6) | 0.412 | 0.298 |
| Control | 30.9 ± 4.9 | 31.5 ± 5.8 | +0.6 ± 5.1 | 0.523 | |||
| ALT (U/L) | Weishen | 36.2 ± 6.5 | 36.8 ± 5.2 | +0.6 ± 5.8 | =+1.2 (−1.4 to +3.8) | 0.567 | 0.672 |
| Control | 36.9 ± 5.4 | 36.3 ± 5.3 | −0.6 ± 4.9 | 0.498 | |||
| Cr (μmol/L) | Weishen | 67.8 ± 8.9 | 68.9 ± 9.8 | +1.1 ± 7.5 | =−0.2 (−4.1 to +3.7) | 0.389 | 0.512 |
| Control | 66.2 ± 9.1 | 67.5 ± 9.3 | +1.3 ± 8.1 | 0.431 | |||
| BUN (mmol/L) | Weishen | 5.5 ± 0.7 | 5.8 ± 0.9 | +0.3 ± 0.8 | =+0.2 (−0.3 to +0.7) | 0.215 | 0.637 |
| Control | 5.6 ± 0.3 | 5.7 ± 1.0 | +0.1 ± 0.9 | 0.584 |
Table 7: Comparison of Safety Indicators. AST: Aspartate aminotransferase; ALT: Alanine aminotransferase; Cr: Creatinine; BUN: Blood urea nitrogen. Within-group P value: paired t-test comparing after treatment vs. before treatment. Between-group comparison of the change from baseline (Between-group differences in changes from baseline were assessed using an independent-samples t-test). Data are presented as mean ± SD. P < 0.05 indicates statistically significant results.
Discussion
This study, through a rigorously designed randomized, double-blind, placebo-controlled trial, evaluated the clinical efficacy and safety of the traditional Chinese herbal formula Weishen Decoction, administered alone (without any conventional pharmacotherapy), in treating kidney-yang-deficient senile osteoporosis. The results indicate that after 12 weeks of intervention, compared to placebo, Weishen Decoction significantly improved patients' core clinical symptoms of kidney-yang deficiency and alleviated low back pain. Additionally, the Weishen Decoction group showed suggestive improvements in femoral neck bone mineral density and favorable changes in bone turnover markers (β-CTX, PINP, OC), although these findings should be interpreted as preliminary and hypothesis‑generating given the short 12‑week treatment period, the exploratory nature of these endpoints, and the relatively modest magnitude of between‑group differences as presented. No serious adverse events were observed, although the sample size and follow-up period limit safety conclusions.
The results of this study show that Weishen Decoction significantly improved typical kidney-yang deficiency symptoms, including cold pain in the back and waist, soreness and weakness, and aversion to cold. The total effective rate for TCM syndromes was 66.7%, significantly higher than that of the control group. This confirms the practical value of the TCM theories of "treatment based on syndrome differentiation" and "treating different diseases with the same method"20. The fundamental pathogenesis of kidney-yang deficient senile osteoporosis lies in kidney-yang deficiency, leading to a lack of warming and propelling functions. Weishen Decoction uses Eucommia bark and Psoralea fruit as sovereign herbs to greatly tonify the gate of life fire and strengthen tendons and bones; Cinnamon bark and Fenugreek warm the kidney and assist yang; Dodder seed mildly tonifies the liver and kidney, assisted by Cyathula root, Saposhnikovia root, and others, to unblock collaterals and dispel impediment. The whole formula closely focuses on the core of "warming and tonifying kidney-yang," enabling kidney-yang to be replenished and tendons and bones to be nourished, thereby naturally eliminating signs of deficiency-cold. This led to significant efficacy at the clinical symptom level, reflecting TCM's unique advantage in improving patients' quality of life.
Previous pharmacological studies have reported that active components of Eucommia bark and Psoralea fruit have been reported to promote osteoblast proliferation and inhibit osteoclast activity via regulation of the RANKL/OPG system and other pathways21,22,23. Recent studies have further highlighted the involvement of Wnt signaling and BMP-2‑mediated pathways in osteoporosis, which may intersect with the mechanisms of Weishen Decoction and warrant future investigation24,25. However, the present clinical study did not measure any pathway-specific biomarkers (e.g., RANKL, OPG, TGF-β, MAPK, Wnt, BMP-2), and therefore, no direct mechanistic conclusion can be drawn from our data. The observed "dual decrease" in both formation and resorption markers suggests, as a hypothesis to be tested in future studies, that Weishen Decoction might shift a pathological high-turnover state toward a more balanced profile, but this interpretation remains speculative and requires confirmation in dedicated mechanistic studies. It is also noteworthy that the improvement in lumbar spine BMD was not significant. One speculative explanation is that the common presence of lumbar degenerative changes (e.g., osteophytes, facet joint hypertrophy) and abdominal aortic calcification in elderly patients may interfere with DXA measurement accuracy, particularly at the lumbar spine. However, we did not collect baseline imaging data (such as lateral spine radiographs or CT scans) to quantify the extent of degenerative changes, so this interpretation remains hypothetical. Alternatively, the lack of significant change in lumbar spine BMD could be due to the short 12‑week treatment duration, as lumbar spine BMD may respond more slowly to treatment in elderly patients, or to true site‑specific differences in the pharmacological action of Weishen Decoction. Future research could incorporate methods such as quantitative CT (QCT) or vertebral fracture assessment (VFA), which can exclude the influence of osteophytes, to determine whether Weishen Decoction has a differential effect on lumbar versus femoral neck BMD.
Within the limitations of this single‑center, 12‑week, 72‑patient trial, the findings suggest that Weishen Decoction monotherapy may offer a potential alternative for a specific subset of patients with kidney‑yang deficient senile osteoporosis: those who are unable to tolerate or unwilling to use conventional anti‑osteoporosis drugs (e.g., bisphosphonates, denosumab), or who have contraindications to these agents. However, given the short treatment duration and the exploratory nature of the BMD and bone marker endpoints, this should not be interpreted as a general recommendation for Weishen Decoction as a routine monotherapy. The results are hypothesis‑generating, and any clinical application would require shared decision‑making, considering the preliminary evidence, patient preferences, and the lack of long‑term fracture data. Larger, longer‑term, multicenter trials are needed before definitive claims about clinical utility can be made. Critical to successful protocol execution were the pre-randomization standardization of TCM syndrome differentiation (two independent physicians, pilot-tested with ICC ≥0.85), centralized, pharmacy-controlled allocation concealment using sequentially numbered opaque envelopes, and adherence monitoring that combined sachet counts with patient diaries (achieving >95% adherence). For troubleshooting, if recruitment is hindered by patient expectations of background calcium/vitamin D, we suggest a standardized telephone script emphasizing the short 12‑week duration and rescue availability; if herbal taste threatens blinding, a placebo can be matched with dextrin, caramel, and food coloring, with consideration of encapsulation or flavor masking; for elderly patients living alone, blister packaging and pre‑visit telephone reminders improve compliance. Compared with existing approaches, our monotherapy‑without‑background design provides unbiased proof‑of‑concept for the intrinsic effect of Weishen Decoction, unlike most add‑on TCM osteoporosis trials; however, it is explanatory rather than pragmatic, and the 12‑week BMD findings are hypothesis‑generating only—researchers aiming for fracture or BMD endpoints should extend treatment to ≥6 months or replace BMD with bone turnover markers as the primary outcome.
This study has several limitations. First, the sample size was relatively small (72 patients), and the intervention period was only 12 weeks. For a chronic disease like osteoporosis, the short treatment duration is particularly problematic for interpreting bone mineral density changes, which typically require longer follow-up to detect clinically meaningful progression or treatment response. Therefore, the observed BMD changes should be regarded as exploratory and hypothesis-generating rather than definitive evidence of efficacy. Second, the study used a placebo-only comparator without any foundational therapy (e.g., calcium and vitamin D), which, while allowing an unbiased evaluation of Weishen Decoction's standalone effect, does not reflect real-world clinical practice where such foundational supplements are routinely recommended. Consequently, the results may not be directly generalizable to settings where patients receive standard background therapy. Third, the trial was not powered or designed for subgroup analyses. Any exploratory comparisons based on age subgroups, sex, or baseline characteristics should be interpreted as hypothesis-generating only; no formal statistical inferences can be drawn from such post hoc examinations. Fourth, the average age of the study population was around 67 years; its applicability to very elderly patients (> 80 years) or frail elderly patients with multiple comorbidities requires further study. Finally, the single-center design limits generalizability, and the lack of long-term fracture outcome data means the clinical relevance of the observed changes in BMD and bone markers remains uncertain. Future multicenter, larger-sample, long-term studies with fracture endpoints and standardized background therapy are needed to confirm its efficacy and define the role of Weishen Decoction in clinical practice. Future studies should also include animal experiments and cellular assays to clarify the molecular mechanisms underlying the observed effects of Weishen Decoction on bone metabolism, including the potential involvement of the RANKL/OPG and TGF‑β/Smad2 pathways.
In conclusion, within the limitations of this single‑center, 12‑week, placebo‑controlled trial involving 72 elderly patients with kidney-yang-deficient senile osteoporosis, Weishen Decoction monotherapy showed preliminary evidence of improving TCM symptoms, reducing low back pain, and affecting femoral neck BMD and bone metabolism markers, with a favorable safety profile. These findings are hypothesis‑generating rather than definitive. They provide initial support for further investigation of Weishen Decoction as a potential treatment option for this specific population, but do not yet establish its value within a comprehensive treatment system. Larger, longer‑term, multicenter randomized trials with fracture endpoints and standard background supplementation or therapy are required before any clinical recommendations can be made.
Disclosures
Competing interests: The authors have no relevant financial or non-financial interests to disclose.
Acknowledgements
Funding: This research received no external funding.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Study interventions | |||
| Weishen Decoction granules | Beijing Kangrentang Pharmaceutical Co., Ltd., Beijing, China | Batch 20240217 | Weishen Decoction granules |
| Placebo granules | Beijing Kangrentang Pharmaceutical Co., Ltd., Beijing, China | Batch 20240211 | placebo simulant granules |
| Bone and metabolism measurements | |||
| Discovery Wi | Hologic, Inc., Marlborough, MA, USA | N/A | dual-energy X-ray absorptiometry (DXA) device |
| Cobas e 601 module | Roche Diagnostics, Mannheim, Germany | N/A | automated electrochemiluminescence immunoanalyzer |
| Cobas c 701 module | Roche Diagnostics, Mannheim, Germany | N/A | automated biochemical analyzer |
| Safety and routine laboratory tests | |||
| XN-9000 | Sysmex Corporation, Kobe, Japan | N/A | automated hematology analyzer |
| Clinitek Atlas | Siemens Healthineers, Erlangen, Germany | N/A | automated urinalysis system |
| AU5800 | Beckman Coulter, Brea, CA, USA | N/A | automated chemistry analyzer |
| CardioFax V6.0 | Nihon Kohden, Tokyo, Japan | N/A | electrocardiograph |
| Quality control | |||
| (not specified) | (not specified) | N/A | high-performance liquid chromatography (HPLC) system |
| Software for trial management and analysis | |||
| PASS 15.0 | NCSS, LLC, Kaysville, UT, USA | N/A | sample size calculation software |
| SPSS 22.0 | IBM Corp., Armonk, NY, USA | N/A | randomization software |
| EpiData 3.1 | The EpiData Association, Odense, Denmark | N/A | electronic database software |
| SPSS 22.0 | IBM Corp., Armonk, NY, USA | N/A | statistical analysis software |
| Supplies and consumables | |||
| (not specified) | (not specified) | N/A | sachets (packaging) |
| (not applicable) | (not applicable) | N/A | patient diary |
References
- Vilaca T, Eastell R, Schini M. Osteoporosis in men. Lancet Diabetes Endocrinol. 2022;10(4):273–83.
- Cotts KG, Cifu AS. Treatment of osteoporosis. JAMA. 2018;319(10):1040–1.
- Hoong CWS, Saul D, Khosla S, Sfeir JG. Advances in the management of osteoporosis. BMJ. 2025;390. doi:10.1136/bmj-2024-081250.
- Johnston CB, Dagar M. Osteoporosis in older adults. Med Clin North Am. 2020;104(5):873–84.
- Kaufman JM. Management of osteoporosis in older men. Aging Clin Exp Res. 2021;33(6):1439–52.
- Chen YJ, et al. Osteoporosis treatment: current drugs and future developments. Front Pharmacol. 2024;15:1456796. doi:10.3389/fphar.2024.1456796.
- Ensrud KE. Bisphosphonates for postmenopausal osteoporosis. JAMA. 2021;325(1):96.
- Chai SJ, et al. The efficacy and safety of denosumab, risedronate, alendronate and teriparatide to treat male osteoporosis: a systematic review and Bayesian network meta-analysis. Front Endocrinol (Lausanne). 2025;16:1579101. doi:10.3389/fendo.2025.1579101.
- Unschuld PU, Tessenow H, Zheng J. Huang Di Nei Jing Su Wen: An Annotated Translation of Huang Di’s Inner Classic—Basic Questions. University of California Press; Berkeley, CA; 2011.
- Ding X, et al. The nexus between traditional Chinese medicine and immunoporosis: implications in the treatment and management of osteoporosis. Phytother Res. 2025;39(4):1826–46.
- Shu B, Shi Q, Wang YJ. Shen (kidney)-tonifying principle for primary osteoporosis: to treat both the disease and the Chinese medicine syndrome. Chin J Integr Med. 2015;21(9):656–61.
- Zhang P, et al. Research on the bone-protective effect of Weishen Decoction by regulating the TGF-β/Smad2 and MAPK pathways in osteoporosis. Chinese Journal of Osteoporosis. 2025;31:806–11.
- Ma X, Ma Y, Guo Y. Meta-analysis of the efficacy of tonifying the kidney, strengthening the spleen and activating the blood in treating postmenopausal osteoporosis. Chinese Journal of Osteoporosis. 2022;(4):527–35.
- Wang B, et al. Meta-analysis of tonifying the kidney, strengthening the spleen and activating the blood in treating primary osteoporosis in middle-aged and older adults. Chinese Journal of Osteoporosis. 2021;27:7–13.
- Zhang Z. Guidelines for the diagnosis and treatment of primary osteoporosis (2022). Chinese Journal of Osteoporosis and Bone Mineral Research. 2022;15:573–611.
- Yang J, Zeng Y, Yu W. Criteria for osteoporosis diagnosis: a systematic review and meta-analysis of osteoporosis diagnostic studies with DXA and QCT. EClinicalMedicine. 2025;83:103244. doi:10.1016/j.eclinm.2025.103244.
- Ge J, et al. Expert consensus on traditional Chinese medicine for the prevention and treatment of primary osteoporosis. Chinese Journal of Osteoporosis. 2020;26:7–15.
- Chiu LYL, et al. The evaluation of smartphone versions of the visual analogue scale and numeric rating scale as postoperative pain assessment tools: a prospective randomized trial. Can J Anaesth. 2019;66(6):706–15.
- Bischoff-Ferrari HA, et al. Effect of vitamin D on falls: a meta-analysis. JAMA. 2004;291(16):1999–2006.
- Zhai X, et al. Treating different diseases with the same method—a traditional Chinese medicine concept analyzed for its biological basis. Front Pharmacol. 2020;11:946. doi:10.3389/fphar.2020.00946.
- Zhang T, et al. Psoralen accelerates bone fracture healing by activating both osteoclasts and osteoblasts. FASEB J. 2019;33(4):5399–410.
- Kim SC, et al. Polysaccharides from Psoralea corylifolia seeds suppress osteoclastogenesis and alleviate osteoporosis. Int J Biol Macromol. 2025;315(Pt 2):144423. doi:10.1016/j.ijbiomac.2025.144423.
- Ma X, et al. Effects of Eucommia ulmoides leaf extracts and Caltrate on osteoblast proliferation and differentiation. Bioact Carbohydr Diet Fibre. 2024;32:100448. doi:10.1016/j.bcdf.2024.100448.
- Liu H, et al. Synthetic biology-based bacterial extracellular vesicles displaying BMP-2 and CXCR4 to ameliorate osteoporosis. J Extracell Vesicles. 2024;13(4). doi:10.1002/jev2.12429.
- Huang Y, et al. The role of Wnt signalling in osteoporosis: a bibliometric analysis. Biomater Transl. 2025;6(3):345–58.