Serum myosin heavy-chain-associated RNA transcript (MHRT) levels were elevated in patients with coronary artery disease (CAD) but decreased after high-intensity interval training (HIIT). HIIT improved cardiopulmonary function and quality of life, while MHRT showed potential as a biomarker for monitoring HIIT response and treatment efficacy in CAD.
Research Article
Myosin Heavy-Chain-Associated RNA Transcript for Cardiopulmonary Recovery Prediction in High-Intensity Interval Training for Coronary Artery Disease
In This Article
Summary
Abstract
This study highlights the expression characteristics of MHRT in CAD and analyzes its predictive potential regarding HIIT intervention on cardiopulmonary function and quality of life in CAD patients. A total of 88 CAD patients were enrolled, and non-CAD volunteers were randomly recruited as the study sample. Serum levels of MHRT were assessed by qRT-PCR. The association between MHRT levels and the Gensini score was assessed using Pearson's correlation analysis. The predictive value of MHRT in CAD was evaluated using ROC curves and logistic regression. Serum MHRT expression was elevated in CAD and correlated positively with the Gensini score. Cardiopulmonary function indicators and quality-of-life scores increased after the HIIT intervention in the HIIT group. Furthermore, serum MHRT decreased after the HIIT intervention, and levels were lower in the clinically effective group than in the ineffective group. HIIT significantly improved cardiopulmonary function and quality of life in CAD patients, accompanied by a marked reduction in serum MHRT levels. This suggests that MHRT may serve as a potential biomarker for monitoring HIIT efficacy.
Introduction
Coronary artery disease (CAD) is a general term for cardiovascular diseases characterized by myocardial ischemia, hypoxia, or necrosis caused by the narrowing or blockage of the coronary arteries1,2. Clinically, coronary heart disease is the most common form of CAD, involving complex interactions between genetic susceptibility and modifiable lifestyle factors, many of which are not entirely preventable3. Consequently, current therapeutic approaches primarily focus on disease management rather than complete cure. The accelerating demographic aging in China has contributed to a rising prevalence of cardiovascular disorders, particularly CAD, posing escalating threats to patient mortality and overall public health security4. Exercise-based rehabilitation is a crucial component of post-operative management for CAD patients, demonstrating significant potential to enhance cardiopulmonary functional recovery5. High-intensity interval training (HIIT) is a training method that combines high-intensity exercise and short rest6. In past clinical practice, HIIT was considered useful for exercise and recovery in patients with cardiovascular disease7,8. Consequently, this investigation was designed to evaluate the therapeutic potential of HIIT to enhance post-operative recovery outcomes in CAD patients.
Long non-coding RNAs (lncRNAs) can mediate gene expression regulation, although they have no capacity for direct protein coding9. The significant variations in lncRNAs in different diseases and their stable structures make them valuable for reliable applications in disease prediction and treatment. In the context of CAD, lncRNAs ANRIL, PVT1, and UCA1 have been reported to intervene in the development of the disease10,11,12. LncRNA MHRT (myosin heavy chain-associated RNA transcript) is mostly present in myocardial tissue13. A study showed that MHRT was prominently expressed in the heart14. There is also evidence that MHRT can promote the activity of cardiomyocytes and reduce apoptosis, and overexpression of MHRT may be a diagnostic marker for acute myocardial infarction15. More critically, MHRT was implicated as a critical modulator in both diagnostic stratification and prognostic evaluation of coronary artery disease16. Therefore, it is hypothesized that MHRT is also expressed in CAD and may contribute to disease progression.
This study quantitatively analyzed serum MHRT levels in CAD patients, primarily evaluating the regulatory effect of HIIT intervention on MHRT levels and its association with physical rehabilitation. Additionally, it elucidated the effects of HIIT on cardiopulmonary function and quality of life in CAD patients, while investigating the clinical value of MHRT as a potential biomarker to assess HIIT rehabilitation efficacy.
Protocol
A total of 88 patients with CAD admitted to Wuhan Xinzhou District People′s Hospital from March 2023 to May 2024 were selected (CAD group), and 88 volunteers who underwent coronary angiography and were judged to be free of CAD were also recruited (non-CAD group). Inclusion criteria: Adherence to the criteria described in the Guidelines for the diagnosis and Treatment of CAD17. No other blood system diseases or immune system diseases. Normal cognitive function without a history of psychiatric disorders. No history of cardiovascular disease. Exclusion criteria: Comorbidity with oncological diseases or other chronic diseases. Comorbidity with severe infectious diseases. Severe heart failure. Withdrawal from follow-up midway. The experimental protocol received ethical approval from the Wuhan Xinzhou District People′s Hospital Institutional Review Board (No. 2023A03), and written informed consent was obtained from all study participants prior to enrollment. All the materials used in this study are listed in the Table of Materials.
Nursing intervention and efficacy grouping
Patients with CAD who underwent percutaneous coronary intervention (PCI) were recruited, and using a random-number table, patients were randomly assigned in a 1:1 ratio to either the HIIT group (n = 44) or the usual care group (non-HIIT, n = 44). To ensure concealment of assignments, the randomization sequence was generated by an independent investigator and placed in sequentially numbered, opaque envelopes. Blinding of subjects and intervention implementors was not possible due to the nature of the exercise intervention, but outcome assessment and data analysis personnel were always blinded. Patients in the non-HIIT group received moderate-intensity exercise training for 1 week after surgery at 60% to 80% of maximal heart rate, as determined by wristband monitoring, for 28 min per session. The training frequency was three times per week, and the patients were free to choose their preferred exercise methods, such as jogging and aerobic exercise. Furthermore, patients in the HIIT group underwent HIIT one week after surgery while receiving postoperative care. Briefly, train at 85% to 95% of maximum heart rate for 4 min, followed by 40% of maximum heart rate for 3 min. A total of 4 groups were performed, which took 28 min at a frequency of 3 times/week18. The patients were examined before training and monitored throughout the one-month training period. The endpoint was defined as an inability to complete the training program due to worsening disease or poor adherence. Calculated the change in 6MWT distance before and after intervention in CAD patients within the HIIT group. Using the median as the cutoff, patients with values above this threshold were defined as the effective group, and the remainder as the ineffective group.
Collection of clinical indicators
Venous blood was collected from participants before, during, and after the HIIT intervention, centrifuged for 15 min (2500 × g), and separated to obtain the upper serum layer, which was stored at -80 °C for examination. The biochemical indices were tested by an automatic blood analyzer. The degree of coronary artery disease in patients was assessed using the Gensini score, with higher scores indicating more severe coronary artery disease19. A pulmonary function instrument and a cardiovascular ultrasound system were selected to monitor cardiopulmonary function. Patients' quality of life is measured according to the World Health Organization Quality of Life Instrument-BREF (WHOQOL-BREF), which includes social relationships, environment, physical health, and psychological health20. Scores on each domain range from 0 to 30, with higher scores indicating better quality of life.
qRT-PCR
RNA in serum samples was extracted. The cDNA samples were prepared using the reverse transcription Kit. PCR mixtures were prepared using the SYBR Premix Ex Taq Kit, and quantitative reactions were performed on Real-Time PCR system. MHRT expression was normalized by GAPDH and calculated by the 2-ΔΔCt method.
Statistical methods
SPSS 26 and GraphPad Prism 9 were used to analyze and process all data. The Shapiro-Wilk test was used to assess the normality of the data distribution. Measurement information was expressed as mean ± standard deviation, count information was expressed as n/%, and comparisons between groups were made by t-test or chi-square test. For multiple comparisons, error was controlled with the use of the Bonferroni correction. The predictive value of MHRT was evaluated using the ROC method. Risk factors for CAD were assessed using Pearson's correlation and logistic regression. p < 0.05 was considered statistically significant.
Results
Assessment of clinical features
The baseline characteristics of the enrolled subjects are shown in Table 1. In the CAD group, hsCRP was elevated (p < 0.001), except for a decrease in HDL-C levels (p = 0.003), compared with the non-CAD group. LDL-C, TC, and TG levels, as well as general indicators (p > 0.05), were not statistically different between the two groups.
MHRT expression was upregulated in CAD
Serum MHRT was markedly elevated in CAD patients compared with healthy individuals (p < 0.001; Figure 1A). This suggests that increased MHRT levels may herald the onset of CAD. Furthermore, the positive correlation between the Gensini score and MHRT expression in CAD patients was assessed using Pearson's correlation (r = 0.735, p < 0.001; Figure 1B), confirming that MHRT overexpression was associated with CAD lesions. Based on whether HIIT was performed, the recruited CAD patients were randomly assigned to the HIIT group (n = 44) and the non-HIIT group (n = 44). After the HIIT intervention, the 6MWT was significantly increased in the HIIT group, and the scores for social relationships, environment, physical health, and psychological health were all elevated (p < 0.01; Table 2). This suggests the clinical effectiveness of the HIIT intervention. Given the significant improvement in the HIIT group, MHRT levels were further quantified.
MHRT was associated with cardiopulmonary function
Before HIIT intervention, there was no statistically significant difference in serum MHRT expression between the non-HIIT group and the HIIT group (p = 0.070, Figure 2A). After 2 weeks and 1 month of intervention, the MHRT level of the HIIT group was significantly lower than that of the non-HIIT group (p = 0.040, p = 0.036, Figure 2B–C). Moreover, MHRT levels were negatively correlated with SV (r = -0.647, p < 0.001; Figure 3A), LVEF (r = -0.631, p < 0.001; Figure 3B), and 6MWT (r = -0.741, p < 0.001; Figure 3C) levels in CAD patients after HIIT intervention. This result indicates that improvements in cardiopulmonary function and quality of life in CAD patients are closely associated with reduced serum MHRT levels.
Predictive value of MHRT for CAD and HIIT efficacy
ROC results indicate that MHRT demonstrated a sensitivity of 84.09% and a specificity of 92.05% in distinguishing between CAD and non-CAD groups (AUC = 0.914, p < 0.001, Figure 4A). In the effective and ineffective groups, MHRT levels decreased during recovery (p < 0.001; Figure 4B). In addition, the AUC of MHRT in distinguishing the effective group from the ineffective group was 0.813 (sensitivity = 66.67%, specificity = 86.96%, p < 0.001; Figure 4C), supporting MHRT's efficacy as a measure. Binary logistic regression analyses were performed to show that changes in the levels of MHRT (Table 3, OR = 0.070, 95% CI 0.014–0.347, p = 0.001), social relationships (OR = 0.145, 95% CI 0.032–0.659, p = 0.012), environment (OR = 0.177, 95% CI 0.040–0.775, p = 0.022), physical health (OR = 0.147, 95% CI 0.039–0.558, p = 0.005), and psychological health (OR = 0.204, 95% CI 0.046–0.902, p = 0.036) were all strongly associated with the HIIT intervention, and may confer protective effects against CAD.
DATA AVAILABILITY:
The data that support the findings of this study are available in Supplementary Table 1 of this article.
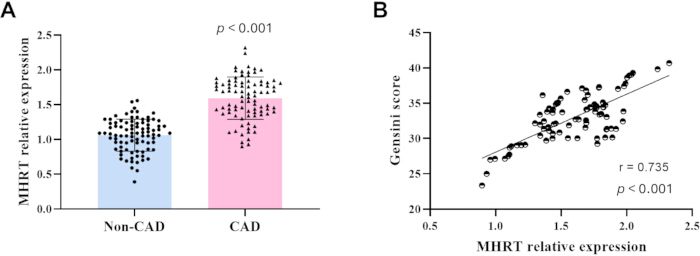
Figure 1: Quantitative detection of serum MHRT in CAD. (A) MHRT is upregulated in CAD patients compared with non-CAD subjects (p < 0.001). (B) MHRT expression was consistent with the trend of the Gensini score (r = 0.735, p < 0.001). Please click here to view a larger version of this figure.
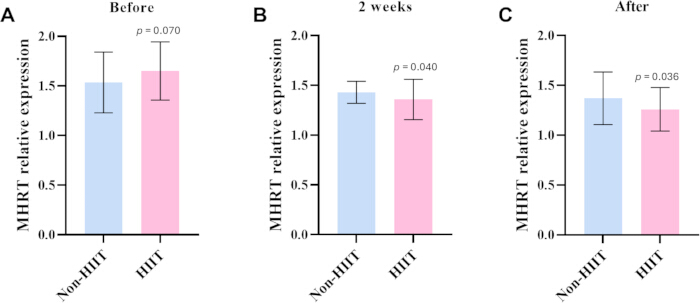
Figure 2: Changes in serum MHRT levels before and after HIIT intervention. (A) Before HIIT, serum MHRT levels did not differ significantly between the two groups (p = 0.070). (B) Serum MHRT levels decreased after 2 weeks of HIIT (p = 0.040). (C) One month after HIIT, MHRT was significantly downregulated in the HIIT group (p = 0.036). Please click here to view a larger version of this figure.
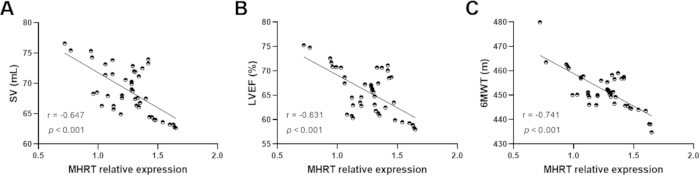
Figure 3: Correlation between MHRT and cardiopulmonary function in CAD patients. After HIIT intervention, MHRT was negatively correlated with (A) SV (r = -0.647, p < 0.001), (B) LVEF (r = -0.631, p < 0.001), and (C) 6MWT (r = -0.741, p < 0.001). Please click here to view a larger version of this figure.
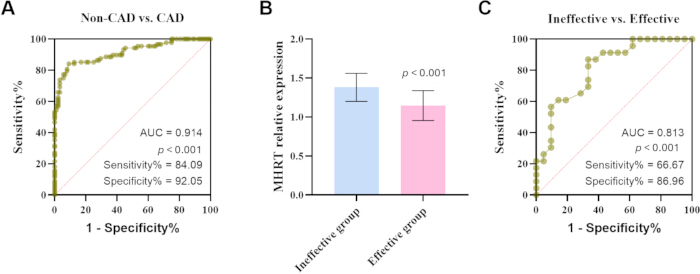
Figure 4: Biological potential of MHRT in CAD. (A) The predictive potential of MHRT in diagnosing CAD patients. (B) MHRT level in the effective group was lower than that in the ineffective group after HIIT intervention (p < 0.001). (C) The potential of MHRT for monitoring HIIT efficacy. Please click here to view a larger version of this figure.
| Parameters | Non-CAD (n = 88) | CAD (n = 88) | p value |
| Age, year | 56.22 ± 6.30 | 57.41 ± 5.47 | 0.191 |
| BMI, kg/m2 | 23.27 ± 1.36 | 23.35 ± 2.00 | 0.759 |
| Gender (n, %) | 0.65 | ||
| Female | 49 (55.68) | 52 (59.09) | |
| Male | 39 (44.32) | 36 (40.91) | |
| Course of disease, year | / | 3.98 ± 1.21 | / |
| HDL-C, mmol/L | 1.32 ± 0.41 | 1.16 ± 0.29 | 0.003 |
| LDL-C, mmol/L | 2.61 ± 1.07 | 2.88 ± 0.98 | 0.082 |
| TC, mmol/L | 4.16 ± 0.86 | 4.41 ± 1.31 | 0.148 |
| TG, mmol/L | 1.30 ± 0.52 | 1.42 ± 0.34 | 0.077 |
| hsCRP, mmol/L | 0.81 ± 0.29 | 1.84 ± 0.31 | <0.001 |
| Gensini score | / | 32.94 ± 3.40 | / |
| FVC, L | / | 3.17 ± 0.49 | / |
| PEF, L/S | / | 5.45 ± 1.19 | / |
| SV, mL | / | 63.58 ± 7.25 | / |
| LVEF, % | / | 61.91 ± 4.94 | / |
| VO2max, mL/kg·min | / | 14.38 ± 2.53 | / |
| 6MWT, m | / | 365.75 ± 10.95 | / |
| Social relationships | / | 8.32 ± 2.35 | / |
| Environment | / | 18.47 ± 3.24 | / |
| Physical health | / | 18.07 ± 1.84 | / |
| Psychological health | / | 15.11 ± 1.16 | / |
Table 1: Baseline characteristics of the enrolled subjects. Demographic, clinical, and baseline laboratory characteristics of the enrolled participants are presented and compared between the study groups. Abbreviations: CAD = coronary artery disease; BMI = body mass index; HDL-C = high density of lipoprotein cholesterol; LDL-C = low density of lipoprotein cholesterol; TC = total cholesterol; TG = triglyceride; hsCRP = high sensitivity C-reactive protein; FVC = forced vital capacity; PEF = peak expiratory flow; SV = stroke volume; LVEF = left ventricular ejection fraction; VO2max = maximum oxygen uptake; 6MWT = 6-minute walk test.
| Parameters | Non-HIIT (n = 44) | HIIT (n = 44) | p value |
| Cardiopulmonary function | |||
| FVC, L | 3.45 ± 0.42 | 3.63 ± 0.54 | 0.073 |
| PEF, L/S | 6.12 ± 0.99 | 6.22 ± 0.88 | 0.624 |
| SV, mL | 66.76 ± 4.79 | 68.76 ± 3.90 | 0.034 |
| LVEF, % | 63.69 ± 4.41 | 65.64 ± 4.64 | 0.047 |
| VO2max, mL/kg·min | 15.54 ± 2.70 | 16.19 ± 2.41 | 0.232 |
| 6MWT, m | 408.72 ± 8.60 | 451.93 ± 7.86 | <0.001 |
| Quality of life | |||
| Social relationships | 11.34 ± 1.42 | 14.19 ± 1.50 | <0.001 |
| Environment | 21.62 ± 2.55 | 25.35 ± 2.81 | <0.001 |
| Physical health | 22.24 ± 2.01 | 26.11 ± 1.96 | <0.001 |
| Psychological health | 21.90 ± 1.87 | 23.04 ± 1.58 | 0.004 |
Table 2: Comparison of cardiopulmonary function and quality of life in CAD patients by HIIT.
Cardiopulmonary function parameters and quality-of-life scores are compared between coronary artery disease (CAD) patients who underwent high-intensity interval training (HIIT) and the control group after the intervention. Abbreviations: CAD = coronary artery disease; HIIT = high-intensity interval training; FVC = forced vital capacity; PEF = peak expiratory flow; SV = stroke volume; LVEF = left ventricular ejection fraction; VO2max = maximum oxygen uptake; 6MWT = 6-minute walk test.
| Parameters | OR value | 95% CI | p value |
| LncRNA MHRT | 0.07 | (0.014, 0.347) | 0.001 |
| FVC | 0.41 | (0.106, 1.585) | 0.196 |
| PEF | 2.347 | (0.519, 10.607) | 0.268 |
| SV | 1.873 | (0.470, 7.463) | 0.374 |
| LVEF | 1.808 | (0.404, 8.092) | 0.439 |
| VO2max | 0.649 | (0.162, 2.604) | 0.542 |
| 6MWT | 0.334 | (0.066, 1.705) | 0.188 |
| Social relationships | 0.145 | (0.032, 0.659) | 0.012 |
| Environment | 0.177 | (0.040, 0.775) | 0.022 |
| Physical health | 0.147 | (0.039, 0.558) | 0.005 |
| Psychological health | 0.204 | (0.046, 0.902) | 0.036 |
Table 3: Logistic regression analysis of factors associated with HIIT efficacy in patients with coronary artery disease (CAD). Binary logistic regression analysis was performed to evaluate the association between changes in serum MHRT levels, cardiopulmonary function parameters, quality-of-life domains, and the clinical efficacy of high-intensity interval training (HIIT) in patients with coronary artery disease (CAD). Results are presented as odds ratios (ORs) with 95% confidence intervals (CIs). Abbreviations: CAD = coronary artery disease; FVC = forced vital capacity; PEF = peak expiratory flow; SV = stroke volume; LVEF = left ventricular ejection fraction; VO2max = maximum oxygen uptake; 6MWT = 6-minute walk test.
Supplementary Table 1: Raw data. All the raw data used in this study are present in this table.Please click here to download this file.
Discussion
Coronary heart disease (CAD), a prevalent cardiovascular disorder characterized by impaired myocardial perfusion, has witnessed a significant rise in prevalence attributed to modern lifestyle alterations21. This condition is associated with unfavorable clinical outcomes, substantially compromising both quality of life and long-term survival. Exercise rehabilitation training is a rehabilitation method of clinical concern at present, and some studies have claimed that patients with CAD can effectively improve cardiopulmonary function and delay the development of the disease after moderate exercise training22. HIIT is gradually being used in the rehabilitation of patients with CAD due to its efficient enhancement of cardiopulmonary function and improvement of metabolism23. This study examined the modulation of MHRT level and the rehabilitation effect in CAD patients after applying HIIT.
The regulatory functions of lncRNAs in human pathologies have been widely investigated. For instance, MHRT, a well-characterized lncRNA, has been demonstrated to play significant roles in various heart diseases through its upregulation24,25. MHRT was quantified to confirm its robust expression in the serum of CAD patients. Relatedly, MHRT was upregulated in acute myocardial infarction and may be a diagnostic marker for patients15. Lang et al also demonstrated increased MHRT in mouse models of MI26. Meanwhile, MHRT levels were strongly correlated with deterioration in CAD patients. The downregulation of MHRT levels observed after HIIT intervention suggests that HIIT may regulate MHRT levels and that MHRT may be a potential biomarker for monitoring disease changes.
The main pathological change of CAD is coronary artery obstruction or stenosis, which leads to different degrees of myocardial ischemia and hypoxia in patients and affects the cardiac reserve function27. The findings suggest that both routine care and HIIT interventions affect recovery of cardiopulmonary function, with HIIT interventions more significantly increasing lung capacity, enhancing cardiac pumping capacity, and improving patients' activation capacity. This may be because HIIT intervention upregulated the heart's ejection fraction, improved the heart's systolic and diastolic function, and repaired cardiopulmonary coordination28. Katsunori and colleagues similarly noted HIIT's ability to improve cardiopulmonary health, consistent with the present findings29. Based on the repair of the organism, the quality of life of CAD patients has also been improved. In this study, the HIIT group had better social relationships, environment, physical health, and mental health during the recovery period than the non-HIIT group, indicating that the HIIT intervention could alleviate anxiety, increase social activities, and improve the overall health of the patients, which is consistent with the report of a group30. It has been suggested that HIIT helps to strengthen vascular endothelial function and coronary artery structural function, which has a positive effect on the prognosis and recovery of patients31. Moreover, ROC curves and logistic regression analyses revealed MHRT's independent predictive value for assessing HIIT efficacy, suggesting that MHRT may be a potential biomarker for cardiopulmonary rehabilitation in CAD patients.
However, this single-center study with a limited sample size and a short intervention period limits generalizability. Furthermore, the lack of in vitro and in vivo experiments precludes the exploration of MHRT regulatory mechanisms and tissue-specific expression. Future studies are needed not only to explore the long-term effects of HIIT interventions but also to confirm the pathological mechanism of MHRT in CAD, using larger sample sizes and more systematic experimental designs. In summary, HIIT represents a promising therapeutic intervention for CAD patients, which improves cardiopulmonary function and quality of life. These clinical recoveries were significantly associated with reduced serum MHRT levels, suggesting MHRT's potential as a biomarker for CAD and as a predictor of HIIT efficacy, facilitating dynamic monitoring of rehabilitation efficacy and individualized exercise prescription in clinical practice.
Disclosures
The authors have no relevant financial or non-financial interests to disclose.
Acknowledgements
Not applicable.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| ABI 7500 Real-Time PCR system | Applied Biosystems, USA | 4368814 | qRT-PCR |
| Automatic blood analyzer | Hitachi 7180, Japan | 7180 | Biochemical indexes |
| Cardiovascular ultrasound system | PHILIP, Netherlands | CX50 | Cardiac function |
| Centrifuge | Thermo Scientific, USA | 75002446 | Sample processing |
| GraphPad Prism 9 | GraphPad software | 9.0 | Data analysis |
| Pulmonary function instrument | CONTEC, China | SP10 | Cardiopulmonary function |
| QuantiTect Reverse Transcription Kit | Qiagen, USA | 205311 | cDNA synthesis |
| Refrigerator | Haier, Qingdao, China | DW-86L828J | Sample preservation |
| SPSS 26 | SPSS software | 26.0 | Data analysis |
| SYBR Premix Ex Taq Kit | Takara, China | RR420A | PCR mixture |
| TRIzol reagent | Invitrogen, USA | 15596026 | RNA extraction |
References
- Liu C, Liu J, Zhang Y, Wang X, Guan Y. Immune-related potential biomarkers and therapeutic targets in coronary artery disease. Front Cardiovasc Med. 2022;9:1055422.
- Huang R, et al. Association of tumor necrosis factor-α gene polymorphisms and coronary artery disease susceptibility: a systematic review and meta-analysis. BMC Med Genet. 2020;21(1):29.
- Wu L, et al. Homocysteine and Lp-PLA2 levels: diagnostic value in coronary heart disease. Medicine (Baltimore). 2023;102(46):e35982.
- Ma T, Bai YP. The hydromechanics in arteriogenesis. Aging Med (Milton). 2020;3(3):169-177.
- López-Hernández A, et al. Differential response to preoperative exercise training in patients candidates to cardiac valve replacement. BMC Anesthesiol. 2024;24(1):280.
- Park HY, Jung WS, Kim J, Hwang H, Lim K. Changes in the paradigm of traditional exercise in obesity therapy and application of a new exercise modality: a narrative review. Iran J Public Health. 2019;48(8):1395-1404.
- Qin Y, Kumar Bundhun P, Yuan ZL, Chen MH. The effect of high-intensity interval training on exercise capacity in post-myocardial infarction patients: a systematic review and meta-analysis. Eur J Prev Cardiol. 2022;29(3):475-484.
- Tan S, Lin C, Li H, Peng F. Bioinformatics analysis of high-intensity intermittent exercise for prevention of myocardial infarction. Cell Mol Biol (Noisy-le-grand). 2024;70(7):92-99.
- Chen X, et al. Screening of plasma exosomal lncRNAs to identify potential biomarkers for obstructive sleep apnea. Ann Transl Med. 2022;10(17):936.
- Liu ZF, et al. Expression of lncRNA-ANRIL in patients with coronary heart disease before and after treatment and its short-term prognosis predictive value. Eur Rev Med Pharmacol Sci. 2020;24(1):376-384.
- Liu H, et al. LncRNA PVT1 inhibits endothelial cells apoptosis in coronary heart disease through regulating MAPK1 expression via miR-532-3p. Acta Cardiol. 2024;79(3):295-303.
- Li J, Chen Z, Wang X, Song H. LncRNA UCA1, miR-26a, and miR-195 in coronary heart disease patients: correlation with stenosis degree, cholesterol levels, inflammatory cytokines, and cell adhesion molecules. J Clin Lab Anal. 2022;36(1):e24070.
- Guo F, et al. LncRNA H19 drives proliferation of cardiac fibroblasts and collagen production via suppression of the miR-29a-3p/miR-29b-3p-VEGFA/TGF-β axis. Mol Cells. 2022;45(3):122-133.
- Ismail N, Abdullah NA, Abdul Murad NA, Jamal R, Sulaiman SA. Long non-coding RNAs (lncRNAs) in cardiovascular disease complications of type 2 diabetes. Diagnostics (Basel). 2021;11(1):145.
- Zhang J, Gao C, Meng M, Tang H. Long noncoding RNA MHRT protects cardiomyocytes against H2O2-induced apoptosis. Biomol Ther (Seoul). 2016;24(1):19-24.
- Wu X, et al. Role of lncRNAs in the pathogenesis of coronary artery disease. Rev Cardiovasc Med. 2023;24(4):96.
- Dietz R, Rauch B. Guidelines for diagnosis and treatment of chronic coronary heart disease. Z Kardiol. 2003;92(6):501-521.
- Hajj-Boutros G, et al. Potential mechanisms involved in regulating muscle protein turnover after acute exercise: a brief review. Front Physiol. 2022;13:1106425.
- Xue X, et al. Effect of hypercholesterolemia alone or combined with hypertension on the degree of coronary artery stenosis in patients with coronary heart disease angina pectoris: a medical records-based retrospective study protocol. Medicine (Baltimore). 2020;99(38):e22225.
- Gumuchian ST, Boyle A, Hazel LH, Ellenbogen MA. Fear of depression recurrence among individuals with remitted depression: a qualitative interview study. BMC Psychiatry. 2024;24(1):152.
- Ren L, Li Z, Wu J, Duan L, Gao J. Knowledge, attitudes, and practices among elderly CHD patients towards self-perceived health abilities. J Multidiscip Healthc. 2024;17:1999-2011.
- Li ZH, Fu T. Application value of exercise therapy in the prevention and treatment of coronary heart disease. Zhongguo Yi Xue Ke Xue Yuan Xue Bao. 2024;46(3):393-401.
- Ferrari F, Martins VM. High-intensity interval training versus continuous exercise: is there a difference regarding the magnitude of blood pressure reduction? Arq Bras Cardiol. 2020;115(1):15-16.
- Zhang G, Dou L, Chen Y. Association of long-chain non-coding RNA MHRT gene single nucleotide polymorphism with risk and prognosis of chronic heart failure. Medicine (Baltimore). 2020;99(29):e19703.
- Kontaraki JE, et al. The long non-coding RNAs MHRT, FENDRR and CARMEN, their expression levels in peripheral blood mononuclear cells in patients with essential hypertension and their relation to heart hypertrophy. Clin Exp Pharmacol Physiol. 2018;45(11):1213-1217.
- Lang M, et al. LncRNA MHRT promotes cardiac fibrosis via miR-3185 pathway following myocardial infarction. Int Heart J. 2021;62(4):891-899.
- Huang X, Chu Y, Ren H, Pang X. Antioxidation function of EGCG by activating Nrf2/HO-1 pathway in mice with coronary heart disease. Contrast Media Mol Imaging. 2022;2022:8639139.
- Liu H, Liu F, Ji H, Dai Z, Han W. A bibliometric analysis of high-intensity interval training in cardiac rehabilitation. Int J Environ Res Public Health. 2022;19(21):13745.
- Tsuji K, Tsuchiya Y, Ueda H, Ochi E. Home-based high-intensity interval training improves cardiorespiratory fitness: a systematic review and meta-analysis. BMC Sports Sci Med Rehabil. 2023;15(1):166.
- Jiang L, et al. Effect of high-intensity intermittent rehabilitation training on physical function, gut microbiome, and metabolite after percutaneous coronary intervention in patients with coronary heart disease. Front Cardiovasc Med. 2024;11:1508456.
- Chen S, et al. Effects of exercise training in hypoxia versus normoxia on fat reduction in overweight and/or obese adults: a systematic review and meta-analysis of randomized clinical trials. Front Physiol. 2022;13:940749.