Sorafenib plus gemcitabine shows preliminary evidence of additive inhibition of HepG2 cell proliferation, and shows correlative changes in p-ERK and VEGF expression, and suppresses liver tumor growth in NOD/SCID mice.
Research Article
Evaluating Combined Sorafenib and Gemcitabine Treatment in HepG2 Cells and a NOD/SCID Mouse Xenograft Model: A Pilot Study
* These authors contributed equally
In This Article
Summary
Abstract
Liver cancer remains a leading cause of cancer-related mortality due to drug resistance and limited treatment options. There is an urgent need to explore therapeutic strategies to improve outcomes. This pilot study presents a protocol for assessing the potential effects and underlying mechanisms of the combination of sorafenib and gemcitabine in liver cancer. The liver cancer cell line HepG2 was used, and a non-obese diabetic/severe combined immunodeficient (NOD/SCID) mouse xenograft model was established. Key procedural steps are demonstrated including: (1) HepG2 cell culture and drug treatment; (2) MTT assay setup, incubation, and absorbance reading; (3) protein extraction, SDS-PAGE, transfer, and immunoblotting for ERK and p-ERK; (4) subcutaneous xenograft establishment in NOD/SCID mice; (5) tumor measurement and volume calculation; and (6) VEGF immunohistochemistry on tumor sections. Critical steps, troubleshooting tips, and equipment specifications are provided. The combination of sorafenib (3 µmol/L) and gemcitabine (10 µmol/L) achieved an inhibition rate of 71.23% ± 6.76% at 72 h, with a q-value of 1.35, suggesting a synergistic effect at this specific dose pair under the conditions tested. Compared with the control group, the combination treatment was associated with reduced p-ERK expression, decreased tumor volume, and qualitatively lower VEGF immunostaining. These data show a correlative association between reduced p-ERK expression and the observed anti-proliferative effect, without establishing causality. In HepG2 cells and a NOD/SCID mouse xenograft model, the combination of sorafenib and gemcitabine shows preliminary evidence of anti-proliferative potential and is associated with reduced VEGF expression; however, this finding does not constitute direct evidence of anti-angiogenic activity, as microvessel density or functional vascular analyses were not performed. This reproducible protocol provides a useful framework for evaluating drug combinations in HCC models and can be adapted for other targeted therapy-chemotherapy regimens, though further mechanistic and dose-validation studies are required before any clinical implications can be drawn.
Introduction
Liver cancer is one of the most common and deadliest cancers, and it is also one of the fastest-growing malignant tumors1,2. Although the incidence of liver cancer has been decreasing, the overall burden of liver cancer has continued to increase. The global epidemiological data in 2022 revealed that the age-standardized incidence rate of liver cancer in the Global Cancer Observatory (GLOBOCAN) 2022 online database was 15.0 per 100,000 population, while the age-standardized mortality rate of liver cancer was 26.7 per 100,000 population, making it the second leading cause of cancer mortality3. At present, due to the lack of effective treatment of liver cancer, coupled with its insidious onset, most patients die within one year after diagnosis. Sorafenib is the first multi-target kinase inhibitor approved for clinical use, targeting receptor tyrosine kinases such as epidermal growth factor receptor (EGFR), platelet-derived growth factor receptor (PDGFR), and serine/threonine kinases4,5. Sorafenib, an oral multikinase inhibitor, exerts anti-proliferative and anti-angiogenic effects in liver cancer by targeting multiple growth factor pathways. Historically, sorafenib was the first FDA-approved first-line systemic therapy for patients with advanced or unresectable liver cancer6. However, the current first-line treatment landscape for advanced hepatocellular carcinoma (HCC) has expanded significantly. Recommended options now include the immune checkpoint inhibitor combination atezolizumab plus bevacizumab, lenvatinib, and the dual immunotherapy combination durvalumab plus tremelimumab, among others. Despite these advances, sorafenib remains an important first-line option, particularly in regions where immunotherapy combinations are not readily available or contraindicated. Given its widespread use in liver cancer, drug-related adverse events have been a concern7. In the FDA Adverse Event Reporting System (FAERS) database analysis from 2006 to 2023, the adverse events of sorafenib mainly involved the digestive system, skin, and subcutaneous tissues, as well as non-specific physical discomfort such as infection and injury7. While some patients with advanced liver cancer may benefit from treatment with sorafenib, most patients eventually develop resistance or treatment failure, leading to a poor prognosis8,9,10. Despite its use, sorafenib benefits only about 30% of HCC patients; moreover, responders often develop resistance within 6 months11. The molecular pathways involved in sorafenib resistance include extracellular signal-regulated kinase (ERK)/phosphorylated ERK (p-ERK), protein kinase B (Akt), phosphoinositide 3-kinase (PI3K)/AKT/mammalian target of rapamycin (mTOR), hypoxia-inducible factor 1α (HIF-1α)/HIF-2α, and autophagy-related pathways, with ERK/p-ERK being specifically highlighted and selected in this research11. Gemcitabine is a cytidine analog that enters the body to produce difluorocytidine diphosphate and difluorocytidine triphosphate, which have different inhibitory effects on DNA synthesis12. In hepatobiliary malignancies, gemcitabine has been evaluated as a component of combination chemotherapy. However, gemcitabine has also been clinically reported to exhibit greater drug resistance, limiting the effectiveness of gemcitabine12,13. Therefore, determining the optimal drug regimen effectively and efficiently is extremely challenging. Recent studies have shown that gemcitabine combined with sorafenib may have enhanced therapeutic efficacy based on a novel tumor stemness biomarker prediction14. However, to our knowledge, no study has examined this combination specifically in liver cancer using HepG2 cells and a non-obese diabetic/severe combined immunodeficient (NOD/SCID) mouse xenograft model of hepatocellular carcinoma. Therefore, experimental evidence directly validating the additive effects of sorafenib and gemcitabine in liver cancer remains lacking.
The procedures described in this manuscript are widely used but rarely presented in a detailed, visual, step-by-step format suitable for replication by early-career researchers. We hypothesized that the combination of sorafenib and gemcitabine would additively inhibit liver cancer cell proliferation and tumor growth, and that this effect would be associated with downregulation of the ERK/p-ERK pathway and reduced vascular endothelial growth factor (VEGF)-mediated angiogenesis. This study aims to preliminarily explore the inhibitory effect of sorafenib combined with gemcitabine on the proliferation of the HepG2 liver cancer cell line in vitro and in vivo and its mechanism (Supplementary Figure 1). The novelty of this study lies in three aspects: (1) it is the first to test the sorafenib-gemcitabine combination specifically in liver cancer using the widely used HepG2 cell line and a corresponding NOD/SCID mouse model; (2) it investigates the understudied ERK/p-ERK pathway as a potential mechanism; and (3) it provides direct experimental evidence—rather than computational predictions—for the additive effect of this combination in liver cancer. These features distinguish this work from prior combination therapy reports conducted in other tumor types or using different experimental models, particularly in the context of sorafenib-based regimens.
Protocol
Ethical approval was provided by the Zhejiang University-Laboratory Animal Welfare and Ethics Review (Approval No. ZJU20250049).
Animals and grouping
A total of 40 female NOD/SCID mice, 4–5 weeks old, weighing 18–20 g, were purchased from a licensed commercial supplier (License No. SCXK (Shanghai) 2013-0006) and housed in specific pathogen-free (SPF)-grade animal rooms. All animal protocols followed standard guidelines. During the experiment, animals were allowed to eat and drink freely, housed in groups (5 mice/cage) in a well-controlled SPF room, with the room temperature maintained at 22 ± 2 °C, 50%–60% humidity, and a light/dark cycle of 12/12 h. The animals were provided food and water ad libitum, and their body weight was monitored every 2 weeks. When mice showed persistent pain, cachexia, tumor ulcers, the tumor size reached a maximum dimension of 2 cm, or other irreversible health problems, euthanasia was carried out by intraperitoneal injection of 0.45% pentobarbital sodium at ≥150 mg/kg body weight followed by confirmation of cessation of breathing and heartbeat, loss of corneal reflex, or application of a secondary physical method if necessary in accordance with the humane termination criteria approved by the Animal Ethics Committee. Sample size (n = 10 per group) was determined based on a power analysis assuming an effect size of 1.2 (derived from pilot experiments), α = 0.05, and β = 0.20 (80% power), plus 20% attrition allowance. Tumor implantation procedures were performed before treatment allocation (see below for xenograft establishment).
The mice were randomly divided into 4 groups using the random number table method after tumor implantation and confirmation of tumor take: control group, sorafenib group, gemcitabine group, and sorafenib combined with gemcitabine group, with 10 mice (5 mice/cage) in each group, to construct the NOD/SCID mouse transplant tumor model. Because tumor tissues during the modeling process may cause poor general condition or even death in NOD/SCID mice, and considering that statistical analysis generally requires an effective sample size, at least 10 mice were included in each group. Random grouping was carried out by independent technicians and the cages were labeled; blinding was not implemented during drug administration or tumor measurement, which is a significant limitation. The remaining tissue sampling, biochemical, and pathological evaluations were all conducted by blinded laboratory personnel. The data were also analyzed blindly by statisticians who had access only to encoded files until the statistics were completed and the data were unblinded. All animals were included in the final analysis. The intraperitoneal route was selected for both drugs to ensure systemic absorption and consistent bioavailability; once-daily dosing was based on previous pharmacokinetic studies showing sustained plasma concentrations with this regimen. The vehicle control group was intraperitoneally injected with 0.2 mL of sterile normal saline. In the sorafenib group, 0.2 mL of 40 mg/kg sorafenib was intraperitoneally injected. In the gemcitabine group, 0.2 mL of 100 mg/kg gemcitabine was intraperitoneally injected. Combination treatment group: 0.2 mL each of 40 mg/kg sorafenib and 100 mg/kg gemcitabine was administered intraperitoneally. Each group was administered once a day for 20 consecutive days. All animals were included in the final analysis, and no mice were excluded from the study. No mortality was observed in any group during the 20-day treatment period. The schedule and doses were selected based on published studies in hepatobiliary cancer models. It should be noted that daily intraperitoneal administration of gemcitabine may cause toxicity. The length and width of the transplanted tumors were measured daily, and the volume of the transplanted tumors was calculated. After 20 days, the animals were euthanized by cervical dislocation under deep anesthesia, and the transplanted tumor tissues were fixed in formalin. Body weight was measured every 2 days throughout the study. Mice were monitored daily for clinical signs of toxicity, including piloerection, hunched posture, reduced mobility, diarrhea, and lethargy. However, serum biochemistry (e.g., alanine aminotransferase, aspartate aminotransferase, and creatinine) and histopathological examination of major organs were not performed. Therefore, subclinical toxicity cannot be excluded.
Drugs and reagents
Sorafenib was dissolved in 10% dimethyl sulfoxide (DMSO) and stored at -20 °C. Before use, the solution was thawed and diluted to a final DMSO concentration of less than 0.5%, which had no effect on cell growth. Gemcitabine was obtained from a commercial source. Radioimmunoprecipitation assay (RIPA) lysis buffer, thiazolyl blue, primary antibodies against glyceraldehyde-3-phosphate dehydrogenase (GAPDH), ERK, p-ERK, and VEGF, secondary antibodies, Dulbecco's Modified Eagle Medium (DMEM) high-glucose medium, fetal bovine serum, and the HepG2 cell line were obtained from commercial sources.
Sorafenib and gemcitabine are cytotoxic agents. All drug preparation and handling procedures should be performed in a designated biosafety cabinet while wearing appropriate personal protective equipment (laboratory coat, nitrile gloves, and safety goggles). DMSO, methanol, xylene, and other organic solvents used in this protocol are hazardous and should be handled in a fume hood to avoid inhalation or skin contact. Material safety data sheets (MSDS) for all reagents should be reviewed prior to use.
Cell Culture
The HepG2 cell line was revived and inoculated into cell culture bottles, containing 10 mL of DMEM high-glucose medium (supplemented with 10% fetal bovine serum, 100 U/mL penicillin-streptomycin, and 4 mmol/L glutamine). The cells were incubated at 37 °C in a humidified incubator containing 5% CO₂. The culture medium was replaced every 2 days, and cells were passaged every 4 days to maintain logarithmic growth. The HepG2 cell line was obtained from a commercial source; however, independent cell-line authentication (e.g., short tandem repeat profiling) and mycoplasma testing were not performed in this study.
MTT method for detecting the proliferation inhibition rate
The 3-(4,5-dimethylthiazol-2-yl)-2,5-diphenyltetrazolium bromide (MTT) method was used to determine the proliferation inhibition rate of sorafenib and gemcitabine on the HepG2 cell line. Cells in the logarithmic growth phase were digested using 0.25% trypsin for 2 min, and the digestion was terminated by adding an equal volume of complete medium. After centrifugation at 1000 × g for 10 min, the cells were resuspended in complete medium. The cell density was adjusted to 1 × 10⁵ cells/mL, and 200 µL of the cell suspension was seeded into each well of a 96-well plate. This seeding density was selected based on preliminary optimization experiments in which cell densities ranging from 5 × 10³ to 5 × 10⁴ cells/well were tested. The density of 2 × 10⁴ cells/well resulted in linear absorbance increase over 96 h and maintained confluence below 80% at the endpoint, as confirmed by visual inspection under an inverted microscope. To ensure that MTT measurements remained within the linear range, pilot experiments were performed at each time point with vehicle-treated control wells. Medium was replaced every 48 h to prevent nutrient depletion and accumulation of metabolic byproducts. Confluence was monitored daily using an inverted microscope. At 96 h, control wells reached approximately 75%–80% confluence, and no overt signs of nutrient depletion were observed. After cell attachment, the medium was discarded, and the drug-containing medium was added. A drug-free medium was added to the untreated control group (vehicle control for in vivo experiments). The experiment was divided into an untreated control group, a sorafenib group, a gemcitabine group, and a combination treatment group. The doses of sorafenib were 1.5 µmol/L, 3 µmol/L, 4.5 µmol/L, and 6 µmol/L, and the doses of gemcitabine were 5 µmol/L, 10 µmol/L, 15 µmol/L, and 20 µmol/L. The doses of sorafenib combined with gemcitabine were 1.5 µmol/L + 5 µmol/L, 3 µmol/L + 10 µmol/L, 4.5 µmol/L + 15 µmol/L, and 6 µmol/L + 20 µmol/L. Cells in each group were cultured for 24 h, 48 h, 72 h, and 96 h. After the culture, 20 µL of 5 mg/mL MTT was added to each well, and the cells were incubated in a cell incubator for 4 h. The supernatant was carefully discarded, and then 150 µL of DMSO was added to each well, and the plate was shaken for 10 min to completely dissolve the formazan, and the optical density (OD) value of each well was measured at 490 nm using a multifunctional microplate reader. The experiment was repeated three times, and each group had five replicate wells. Data were presented as mean ± SD of the three biological replicates. The cell growth inhibition rate (%) =(1 - OD experimental group /OD untreated group)× 100%. The interaction between the two drugs was judged by the q-value, which was calculated by the formula: q = EAB / (EA + EB - EA × EB). Here, EA and EB are the inhibition rates of drugs A and B when used alone, and EAB is the inhibition rate when the two drugs are used together. When q is greater than 1.15, it indicates a synergistic effect between the two drugs; 0.85–1.15 indicates an additive effect; and q less than 0.85 indicates an antagonistic effect. The q-value method is a simple screening tool and does not substitute for more rigorous synergy analyses. Only a few fixed-ratio dose pairs were tested, which limits the robustness of the synergy claim. Therefore, the term "synergy" in this study refers to q > 1.15 at specific dose pairs and time points, not to a validated additive interaction across the full dose-response matrix.
Western blot analysis of ERK and p-ERK protein expression
Cell culture and experimental grouping were performed as described above. For the detection of ERK and p-ERK by Western Blotting, the dose of sorafenib was 3 µmol/L; the dose of gemcitabine was 10 µmol/L; and the combined dose was 3 µmol/L + 10 µmol/L. After 72 h of treatment, cells were lysed with RIPA lysis buffer, and total protein was extracted from each experimental group. The protein concentration was determined by the bicinchoninic acid (BCA) method. Equal amounts of protein (30 µg per lane) were loaded and separated by 10% sodium dodecyl sulfate-polyacrylamide gel electrophoresis (SDS-PAGE) at 120 V for 90 min. Proteins were transferred to polyvinylidene difluoride (PVDF) membranes (0.45 µm pore size) at 300 mA for 90 min at 4 °C. After blocking with 5% non-fat milk in Tris-buffered saline with 0.1% Tween-20 (TBST) for 1 h at room temperature, membranes were incubated with primary antibodies overnight at 4 °C with gentle shaking. After three washes with TBST (10 min each), membranes were incubated with secondary antibodies for 1 h at room temperature. Protein bands were visualized using enhanced chemiluminescence (ECL) substrate and imaged using a digital gel imaging system. Exposure times were optimized for each antibody to avoid saturation. Densitometric quantification was performed using ImageJ software using the gel analysis tool. All target protein band intensities were normalized to GAPDH as a loading control, and p-ERK expression was further normalized to total ERK expression. No additional blocking steps beyond 5% non-fat milk were performed. Quantification results were presented as fold change relative to the control group, which was set to 1.0. Each experiment was repeated three times independently. Representative immunoblots are shown.
Immunohistochemical detection of VEGF expression in HepG2 xenograft tumors in NOD/SCID mice
For xenograft establishment: HepG2 cells in the logarithmic growth phase were harvested by trypsinization, washed twice with sterile phosphate-buffered saline (PBS), and resuspended in serum-free DMEM. A total of 2 × 10⁶ cells in 0.2 mL of serum-free DMEM (without Matrigel) were injected subcutaneously into the right axillary region (a rich blood supply area) of each NOD/SCID mouse using a 1 mL syringe to establish a HepG2 subcutaneous xenograft model in NOD/SCID mice. Tumor take was monitored every 2 days. The size of the tumor was measured every two days, and when the tumor diameter reached 0.3–0.5 cm (approximately 7–10 days post-injection, defined as the treatment initiation point), mice were randomly divided into 4 groups for the experiment. The length (L) and width (W) of the subcutaneous xenograft were measured every day using digital calipers, and the tumor volume (V) was calculated according to the formula: V = (L × W2) / 2. All measurements were performed by an investigator blinded to group allocation. After 20 days, the animals were euthanized by cervical dislocation under deep anesthesia, and the xenograft tissue was fixed in 10% neutral buffered formalin for 24 h at room temperature, then paraffin-embedded. Tissue sections (5 µm thick) were cut using a rotary microtome and mounted on poly-L-lysine-coated glass slides. For immunohistochemistry, sections were deparaffinized in xylene (three changes, 5 min each) and rehydrated through a graded ethanol series (100%, 95%, 70%, 50%; 3 min each). Antigen retrieval was performed by heating sections in 10 mM sodium citrate buffer in a microwave for 15 min, followed by cooling at room temperature for 20 min. Endogenous peroxidase activity was blocked with 3% hydrogen peroxide in methanol for 10 min at room temperature. Non-specific binding was blocked with 5% normal goat serum in PBS for 1 h at room temperature. Sections were then incubated with primary anti-VEGF antibody (dilution 1 : 200) overnight at 4 °C in a humidified chamber. After washing with PBS (three times, 5 min each), sections were incubated with horseradish peroxidase (HRP)-conjugated goat anti-rabbit secondary antibody (1 : 500) for 1 h at room temperature. Signal was detected using 3,3′-diaminobenzidine (DAB) substrate. Sections were counterstained with hematoxylin for 30 s, dehydrated, cleared, and mounted with coverslips using permanent mounting medium. Imaging was performed using a fluorescence inverted microscope with brightfield settings at ×100 magnification. Representative images are shown for qualitative illustration.
All contaminated tips, tubes, and cell culture waste were collected as biohazardous waste and autoclaved prior to disposal. Chemical waste, including drug-containing solutions, DMSO, xylene, and methanol, was collected in segregated, labeled waste containers and disposed of in accordance with local institutional regulations for hazardous chemical waste.
Statistical analysis
SPSS 19.0 software was used for statistical analysis. Experimental data were expressed as mean ± SD from three independent biological replicates for in vitro experiments, and as mean ± standard deviation (SD) from n = 10 mice per group for in vivo experiments. For comparisons between two groups, two-tailed unpaired t-tests were used. For comparisons among multiple groups, one-way analysis of variance (ANOVA) followed by Tukey's post hoc test was used. p < 0.05, p < 0.01, and p < 0.001 were reported.
Results
The inhibitory effect of sorafenib and gemcitabine on HepG2 cell proliferation
Sorafenib and gemcitabine dose-dependently inhibited HepG2 cell proliferation, as shown in Table 1. The combination therapy showed significantly higher inhibition rates at all time points compared to monotherapy. MTT measures metabolic activity, which correlates with cell number but does not directly measure proliferation or cytotoxicity. Therefore, the term "inhibition of proliferation" should be interpreted as a reduction in MTT conversion. Notably, the combination of sorafenib at 3 µmol/L and gemcitabine at 10 µmol/L achieved the most pronounced inhibitory effect, highlighting its potential as an effective treatment regimen against liver cancer. Further investigation demonstrated an additive effect of sorafenib and gemcitabine on HepG2 cells. Table 2 presents the q-values, which indicate potential synergistic interactions between the two drugs. Notably, the combination at 3 µmol/L sorafenib plus 10 µmol/L gemcitabine showed q-values above 1.15 at multiple time points, suggesting an association between reduced p-ERK expression and the observed anti-proliferative effect, although causality is not demonstrated by these data. These findings indicate that further investigation in additional liver cancer models is warranted before conclusions regarding therapeutic potential can be drawn. The synergy was not observed across all dose pairs; rather, it was limited to one specific concentration combination.
Figure 1 illustrates that the inhibitory rate of cell proliferation in the sorafenib group and the combination treatment group reached a peak at 72 h. The combination therapy, particularly at the 3 µmol/L sorafenib and 10 µmol/L gemcitabine dosage, resulted in a markedly higher inhibition rate compared to single-agent treatments.
The effect of sorafenib and gemcitabine on ERK and p-ERK expression
Figure 2A shows no significant change in ERK protein expression across all groups. However, p-ERK expression was significantly decreased in the sorafenib group and combination treatment group, with the greatest decrease observed in the combination group. These data demonstrate an association between reduced p-ERK levels and the combination treatment, but do not establish that reduced p-ERK directly mediates the anti-proliferative effect. Densitometric quantification, normalization of p-ERK to total ERK and GAPDH, biological replicate information, and statistical comparisons were not performed. Therefore, the presented immunoblots are representative and qualitative only.
The effect of sorafenib and gemcitabine on the volume of subcutaneous xenografts in transplanted liver cancer in NOD/SCID mice
There was no significant difference in the volume of subcutaneous xenografts among the groups before treatment (p = 0.367). After treatment, the tumor volume was significantly reduced compared to the control group, and the combination treatment group was significantly smaller than those in the sorafenib and gemcitabine groups (p < 0.001), as shown in Figure 2B. These results should be interpreted with caution because no toxicity or pharmacokinetic data were collected to confirm that the observed differences are not confounded by drug-related morbidity or differences in systemic exposure.
The effect of sorafenib and gemcitabine on VEGF expression in transplanted liver cancer in NOD/SCID mice
Figure 2C depicts the immunohistochemical analysis of VEGF expression in tumor tissues. The sorafenib and combination groups exhibited reduced brown-yellow immunostaining and weaker VEGF expression by qualitative immunohistochemistry. This finding is suggestive of reduced angiogenic potential but does not directly demonstrate angiogenesis, as no endothelial cell markers or microvessel density analyses were performed. The gemcitabine and control groups showed qualitatively stronger VEGF expression. These qualitative VEGF findings are correlative and hypothesis-generating only. Without quantitative analysis or direct vascular markers, no conclusion about angiogenesis or synergy in angiogenesis can be drawn.
DATA AVAILABILITY
The raw data generated and analyzed during this study are included in the supplementary materials (Supplementary File 1).
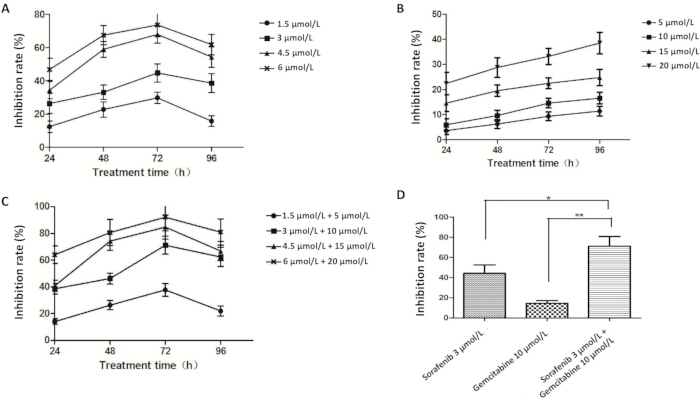
Figure 1: Effects of different interventions on the proliferation inhibition rate of HepG2 cells. (A) Inhibition rate (%) of sorafenib at different time points on HepG2 cells. (B) Inhibition rate (%) of gemcitabine at different time points on HepG2 cells. (C) Inhibition rate (%) of sorafenib combined with gemcitabine on HepG2 cells. (D) Inhibition rate (%) of sorafenib (3 µmol/L) and gemcitabine (10 µmol/L) alone, and in combination after 72 h of treatment on HepG2 cells. *p < 0.05, **p < 0.01 vs. control group. All inhibition rate data were obtained using the MTT assay as described in the protocol. Please click here to view a larger version of this figure.
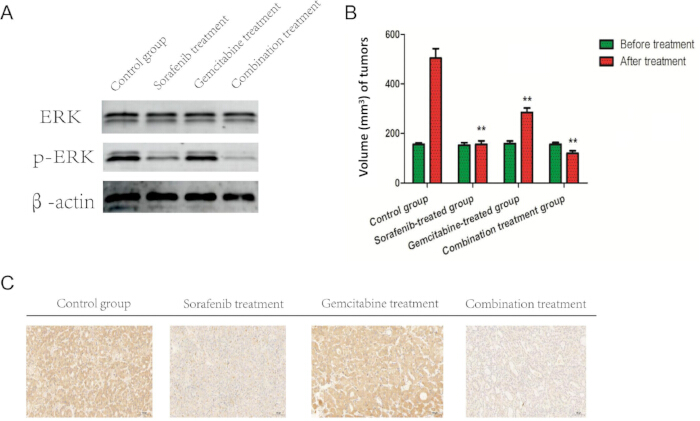
Figure 2: ERK/p-ERK expression, tumor volume, and VEGF expression in treated groups. (A) Expression of ERK and p-ERK in HepG2 cells with different treatments; (B) Volume (mm3) of tumors in four groups before and after treatment (n = 10 per group). **p < 0.01 vs. control group after treatment. Statistical comparisons were performed using one-way ANOVA on endpoint volumes. (C) Representative immunohistochemistry images (scale bar = 100 µm) of VEGF expression in tumor tissues from each group (n = 10 per group). These images are shown for qualitative illustration. Please click here to view a larger version of this figure.
| Group(μmol/L) | Treatment time(h) | ||||
| 24 | 48 | 72 | 96 | ||
| Sorafenib | 1.5 | 12.41 ± 3.37 | 22.74 ± 4.57 | 29.76 ± 3.48 | 15.77 ± 3.18 |
| 3 | 26.37 ± 6.14 | 33.10 ± 4.39 | 44.71 ± 5.49 | 38.63 ± 5.68 | |
| 4.5 | 34.42 ± 5.26 | 58.91 ± 4.67 | 67.85 ± 5.20 | 54.26 ± 6.07 | |
| 6 | 46.88 ± 6.61 | 67.48 ± 5.70 | 73.57 ± 7.07 | 61.73 ± 6.10 | |
| Gemcitabine | 5 | 3.56 ± 1.41 | 6.17 ± 1.73 | 9.31 ± 1.76 | 11.35 ± 1.95 |
| 10 | 5.89 ± 2.47 | 9.62 ± 2.15 | 14.57 ± 1.94 | 16.58 ± 2.31 | |
| 15 | 14.57 ± 3.38 | 19.53 ± 2.27 | 22.43 ± 2.13 | 24.75 ± 3.25 | |
| 20 | 22.36 ± 4.46 | 28.76 ± 3.92 | 33.18 ± 3.19 | 38.49 ± 4.28 | |
| Sorafenib +Gemcitabine | 1.5 + 5 | 14.13 ± 2.16 | 26.41 ± 3.43 | 37.75 ± 4.75 | 22.04 ± 2.84 |
| 3 + 10 | 38.69 ± 3.94 | 46.26 ± 4.06 | 71.23 ± 6.76 | 62.47 ± 7.20 | |
| 4.5 + 15 | 40.89 ± 4.21 | 74.30 ± 6.98 | 84.82 ± 9.17 | 66.89 ± 7.16 | |
| 6 + 20 | 64.05 ± 6.54 | 80.67 ± 9.79 | 92.22 ± 10.24 | 81.05 ± 9.87 | |
Table 1: Inhibition rate (%) of sorafenib and gemcitabine on HepG2 cells. Data are presented as mean ± SD from three independent experiments.
| Group(μmol/L) | Treatment time(h) | ||||
| 24 | 48 | 72 | 96 | ||
| Sorafenib+Gemcitabine | 1.5 + 5 | 0.91 | 0.96 | 1.04 | 0.87 |
| 3 + 10 | 1.26 | 1.17 | 1.35 | 1.28 | |
| 4.5 + 15 | 0.93 | 1.11 | 1.13 | 1.02 | |
| 6 + 20 | 1.09 | 1.05 | 1.12 | 1.06 | |
Table 2: q-value of the synergistic effect of sorafenib and gemcitabine on HepG2 cells. q > 1.15 indicates synergy; 0.85–1.15 indicates additivity; q < 0.85 indicates antagonism. Data are derived from three independent experiments.
Supplementary Figure 1: The study was conducted in two main phases: in vitro experiments using the HepG2 cell line and in vivo experiments using a NOD/SCID mouse xenograft model. In vitro, HepG2 cells were treated with sorafenib, gemcitabine, or their combination at various concentrations. Cell proliferation was assessed using the MTT assay, and the expression of ERK and p-ERK was analyzed by Western blotting. In vivo, a xenograft model was established by subcutaneous injection of HepG2 cells into NOD/SCID mice. Mice were divided into four treatment groups and received daily intraperitoneal injections. Tumor volume was measured throughout the treatment period. After euthanasia, tumor tissues were harvested and subjected to immunohistochemical staining for VEGF. All data were statistically analyzed using SPSS 19.0 software.Please click here to download this file.
Supplementary File 1: Raw data.rar.Please click here to download this file.
Discussion
Liver cancer has a high mortality rate due to its insidious onset, rapid progression, and few effective treatments3,15. Advanced liver cancer often exhibits chemotherapy and radiation resistance, and current options, including surgical resection and liver transplantation, remain insufficient15,16 The combination of two or more chemotherapy drugs with different mechanisms of action has been well developed and was believed to greatly increase the efficiency, which may be an alternative strategy to treat it15,16. Targeted drugs for liver cancer research include monoclonal antibodies (anti-VEGF and anti-EGFR), tyrosine kinase inhibitors, and mTOR inhibitors, and a key challenge is the optimal integration of existing drugs to achieve overall survival and quality of life improvements17. If a combination of efficient and low-toxic drugs were explored, it may help overcome the current limitations in liver cancer treatment. A recent cell model exhibiting chemoresistance to gemcitabine suggested that it may be re-sensitized to gemcitabine/sorafenib (EGFR inhibitors)14. This finding is of great interest to us because it is an unexplored scientific topic. A fractional factorial design identified the optimal three-drug combination of gemcitabine (1.4 mmol/L), sorafenib (0.03 mmol/L), and S-1 (0.185 mmol/L), which significantly inhibits cholangiocarcinoma (CCA) proliferation and tumor growth by suppressing the AKT/mTOR pathway and inducing apoptosis18. Awasthi and colleagues showed that sorafenib inhibited the phosphorylation of mitogen-activated protein kinase (MEK), ERK1/2, 70 kDa ribosomal protein S6 kinase (p70S6K) and 4E-binding protein 1 (4EBP-1) in pancreatic ductal adenocarcinoma (PDAC) cells, as well as cell proliferation; when combined with gemcitabine, it exhibited additive anti-proliferative and pro-apoptotic effects in various cells, thereby significantly prolonging the survival period of tumor-bearing animals19. The combined treatment with gemcitabine and sorafenib inhibits the epithelial-mesenchymal transition process, additionally suppressing the proliferation, migration, and invasion of non-small cell lung cancer (NSCLC) cells, and inducing cell cycle arrest and apoptosis20. However, to the best of our knowledge, this study is the first to test this combination specifically in a HepG2-based in vitro and subcutaneous xenograft model of hepatocellular carcinoma.
This study aimed to fill this gap by investigating the effects of the combination of sorafenib, a multi-target kinase inhibitor, and gemcitabine, a cytidine analog, on liver cancer both in vitro and in vivo. In this study, sorafenib and gemcitabine alone both had inhibitory effects on the proliferation of HepG2 cells, and the inhibitory effect of the combination of the two drugs is significantly stronger than that of a single drug, showing an additive effect. However, MTT alone cannot distinguish between cytostatic (growth arrest) and cytotoxic (cell death) effects, nor does it provide direct evidence of anti-proliferative mechanisms. Among them, the q-value of the sorafenib 3 µmol/L + gemcitabine 10 µmol/L combination group was greater than 1.15 at each time point, showing a synergistic effect. Sorafenib and gemcitabine alone or in combination did not significantly change the expression of ERK in HepG2 cells, but sorafenib alone and in combination significantly inhibited the expression of p-ERK. The combination of the two drugs additively inhibited the phosphorylation of ERK in HepG2 cells. These data indicate an association between reduced p-ERK and the anti-proliferative effect of the combination, although causality has not been established. The synergy was not a general property of the combination across all tested conditions, but was observed only at one specific concentration ratio. The immunohistochemical results from the NOD/SCID mouse liver cancer xenograft model showed that the combination of sorafenib and gemcitabine could significantly decrease the expression of VEGF and reduce the tumor volume. However, because no toxicity or body weight data were systematically collected, we cannot exclude the possibility that reduced tumor volume is partly attributable to drug-induced morbidity rather than specific anti-tumor effects. The combination of sorafenib and gemcitabine was also associated with reduced VEGF expression in tumor tissues, as shown by immunohistochemistry. This observation suggests a potential anti-angiogenic effect, but direct evidence of reduced vascularization (e.g., microvessel density analysis) is lacking. Therefore, the contribution of VEGF downregulation to the observed anti-proliferative effect remains correlative. This synergistic effect suggests that the combination therapy may overcome the limitations of single-agent treatments, which often result in drug resistance and treatment failure. The identification of an optimal combination dose of sorafenib and gemcitabine is a crucial step towards the clinical application of this treatment regimen.
The molecular mechanisms underlying the additive effect of sorafenib and gemcitabine may be associated with the inhibition of the ERK pathway, as suggested by the significant decrease in p-ERK expression in the combination treatment group. The ERK pathway is known to play a critical role in cell proliferation, survival, and angiogenesis, making it a key target for cancer therapy. The results suggest that the combination treatment may disrupt the ERK pathway more effectively than single-agent treatments, which correlates with a greater reduction in p-ERK expression compared to monotherapy. In vivo studies in a NOD/SCID mouse model further support the potential therapeutic benefits of the combination treatment. We observed a significant reduction in tumor volume and decreased VEGF expression in the combination treatment group. VEGF is a key driver of angiogenesis in HCC, and its inhibition is associated with reduced tumor growth and metastasis. The downregulation of VEGF in response to the combination treatment is consistent with the hypothesis that this regimen may modulate angiogenic processes; however, direct evidence of anti-angiogenic activity was not assessed in this study. The observed association between reduced p-ERK expression and the anti-proliferative effect of the combination is suggestive but does not establish a causal mechanism. Because the Western blot analysis was performed only at a time point after prolonged drug exposure, it cannot capture early, dynamic changes in ERK phosphorylation. Moreover, the lack of densitometric quantification, replicate-level statistics, and normalization to total ERK and loading controls limits interpretability. Thus, while reduced p-ERK correlates with the combination treatment, whether ERK pathway inhibition directly mediates the additive effect remains unsubstantiated by the current data. This mechanistic insight is consistent with emerging strategies that target parallel or compensatory pathways to overcome resistance in HCC.
While this study provides valuable insights into the potential additive effects of sorafenib and gemcitabine on liver cancer, several limitations of this study should be acknowledged. Firstly, the sample size in this study is relatively small, which may limit the generalizability of the findings. A larger cohort study would be necessary to confirm the efficacy and safety of the combination treatment across a more diverse patient population. Secondly, this study utilized the HepG2 cell line, which is a well-established model for liver cancer research but may not fully capture the heterogeneity of liver cancer found in patients. Different liver cancer subtypes and genetic backgrounds could potentially respond differently to the combination treatment. Therefore, the findings reported here may not be generalizable to all liver cancer types, and validation using additional cell lines (e.g., Huh7 [human hepatocellular carcinoma cell line] and PLC/PRF/5 [human hepatocellular carcinoma cell line, also known as Alexander cells], or patient-derived xenografts) is necessary before broader conclusions can be drawn. Thirdly, the in vivo experiments were conducted using a NOD/SCID mouse model, which lacks an immune system, thereby not fully representing the complex tumor-immune microenvironment in human liver cancer. Future studies should incorporate immune-competent mouse models or humanized systems to better understand the immunological aspects of the treatment. Fourth, this study did not assess the toxicity or safety profile of the sorafenib–gemcitabine combination. No data on body weight changes, organ toxicity (e.g., liver, kidney function tests), or adverse events in the NOD/SCID mice were collected. Therefore, no conclusions regarding the safety or tolerability of this combination can be drawn from the current data. Fifth, the anti-angiogenic claim is preliminary and should not be overinterpreted. While VEGF expression was reduced qualitatively, we did not perform any quantitative immunohistochemistry (IHC) analysis (e.g., H-score, percentage positive area, staining intensity, or blinded digital image analysis across multiple fields per tumor). Moreover, we did not assess microvessel density using endothelial markers such as Cluster of Differentiation 31 (CD31) or endomucin, nor did we perform functional vascular assays. Therefore, the current VEGF data do not directly demonstrate reduced angiogenesis; they only show a correlative reduction in VEGF protein levels. Sixth, the statistical analysis has several limitations. Tumor volume was measured repeatedly in the same mice over 20 days, but we used only one-way ANOVA on endpoint volumes rather than a repeated-measures ANOVA or mixed-effects model that accounts for temporal correlation. Normality and homogeneity of variance were not formally tested. Moreover, while this study identified an association between reduced p-ERK expression and the additive anti-proliferative effect of sorafenib and gemcitabine, causality cannot be inferred from these data. The Western blot analysis has several additional limitations: (i) only a single, late time point (72 h) was examined, whereas ERK phosphorylation is an early and transient signaling event; (ii) representative blots are shown without densitometric quantification or statistical analysis across independent biological replicates; (iii) p-ERK was not normalized to total ERK, nor was total ERK consistently normalized to a loading control in a quantitative manner. Consequently, these data are primarily qualitative and hypothesis-generating. Definitive mechanistic validation would require rescue experiments (e.g., constitutive activation of ERK via mutant MEK or use of ERK activators) to test whether restoring p-ERK levels diminishes the anti-proliferative effect of the combination. A major limitation is the lack of deep molecular validation. We did not examine p-VEGFR, p-AKT, or apoptotic markers. The ERK pathway data are qualitative and do not establish causality. Further studies specifically designed to elucidate the underlying mechanism are required before any mechanistic conclusions can be drawn. Similarly, siRNA-mediated knockdown of ERK or pharmacological inhibitors targeting upstream regulators (e.g., MEK inhibitors) could help establish whether the observed effect is indeed ERK-dependent. These validation experiments were beyond the scope of this initial study but represent a critical direction for future research. Other key pathways involved in tumor proliferation and survival, such as PI3K/AKT or related downstream factors, are not explored and may also contribute to the observed effects. The findings regarding VEGF expression in this study are preliminary and hypothesis-generating. The reduced VEGF immunostaining provides an important clue for potential modulation of angiogenic pathways, but it is not conclusive evidence of an anti-angiogenic mechanism. We explicitly caution readers that VEGF IHC alone, especially without quantification or corroborating vascular markers, cannot establish an anti-angiogenic mechanism. The lack of analysis of endothelial cell markers and vascular function is one of the main limitations of this study. Thus, a more comprehensive analysis of the signaling pathways involved, including the potential role of other kinases and angiogenic factors, is needed to fully understand the mode of action of the combination treatment.
The procedures described herein have been optimized for HepG2 cells and NOD/SCID mice. Reproducibility may vary with different cell lines or mouse strains. Key factors affecting reproducibility include: (1) cell passage number (use below passage 20); (2) MTT incubation time (standardize to exactly 4 h); (3) antibody lot numbers (record for each experiment); and (4) caliper operator training (use the same blinded operator throughout). We recommend that users perform positive control experiments (e.g., sorafenib alone at 6 µmol/L) to validate their setup before testing combinations.
This study showed through Western blotting that the combination therapy of sorafenib and gemcitabine significantly reduced the expression of p-ERK in HepG2 cells, suggesting modulation of the ERK signaling pathway; however, these data are qualitative and do not establish a causal relationship. p-ERK is widely used as a functional marker of ERK pathway activation, and its downregulation is commonly interpreted as an indicator of reduced pathway activity(11). Although we did not further detect the transcriptional changes of downstream target genes (such as c-Fos, c-Myc) by RT-PCR, the observed reduction in p-ERK provides correlative support for the involvement of the ERK pathway, rather than direct mechanistic evidence. Future studies can further reveal the regulatory details of the ERK downstream network through transcriptome analysis or targeted qPCR, thereby improving the understanding of the mechanism of the combined treatment. Additionally, this study focused on the short-term effects of the combination treatment. Long-term studies are necessary to assess the durability of the response, potential resistance development, and delayed toxicities associated with the treatment. Lastly, this research did not explore the potential of combining sorafenib and gemcitabine with other emerging strategies, such as immunotherapy or other targeted therapies, which could potentially enhance the treatment effects. Future research should investigate multi-drug combinations to develop more effective treatment regimens for liver cancer. In summary, while this study suggests a promising additive effect of sorafenib and gemcitabine in liver cancer, these findings must be interpreted within the context of the study's limitations. Further research is needed to validate these results and to translate these insights into improved clinical outcomes and potential side effects in patients with liver cancer.
In conclusion, this study provides preliminary evidence that the combination of sorafenib and gemcitabine exhibits anti-proliferative activity and is associated with reduced VEGF expression in HepG2 cells and a NOD/SCID mouse xenograft model. However, the VEGF data are qualitative and do not directly demonstrate anti-angiogenic effects; therefore, any claim of anti-angiogenic activity remains unsubstantiated at this stage. Although the data show an association between reduced p-ERK expression and the anti-proliferative effect of the combination, causal mechanisms remain to be established. Given the Western blot limitations noted here, the mechanistic role of the ERK pathway in this combination remains speculative at this stage. The combination of sorafenib and gemcitabine warrants further investigation, including pathway rescue experiments and testing in additional liver cancer models, to determine whether ERK pathway inhibition is indeed a key mediator of the observed synergy. The clinical relevance of sorafenib plus gemcitabine would need to be evaluated against the modern standards in future preclinical and clinical studies, particularly in the context of sorafenib-resistant tumors or in settings where sorafenib remains a clinical option.
Disclosures
The authors have nothing to disclose.
Acknowledgements
The authors have no acknowledgments.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Digital gel imaging system | Bio-Rad Laboratories, Inc., USA | 1708280 | |
| DMEM high-glucose medium | HyClone, USA | SH30243.01 | |
| ERK rabbit monoclonal antibody | Santa Cruz, USA | sc-94 | |
| Fetal bovine serum | Zhejiang Tianhang Biotechnology Co., Ltd., China | 11011-8611/11011-8615 | |
| Fluorescence inverted microscope | Olympus, Japan | IX73 | |
| GAPDH rabbit polyclonal antibody | Santa Cruz, USA | sc-25778 | |
| Gemcitabine | Eli Lilly and Company | 95058-81-4 | |
| Goat anti-rabbit second antibody | Shanghai Shenggong Biological Engineering Co., Ltd., China | D111018 | |
| ImageJ software | National Institutes of Health, Bethesda, MD, USA | Version 1.8.0_112 | |
| Microplate reader | Thermo Fisher Scientific Inc., USA | MK3 | |
| p-ERK rabbit monoclonal antibody | Santa Cruz, USA | 9106 | |
| Refrigerated centrifuge | Changsha Xiangyi Centrifuge Co., Ltd. | DL-5M | |
| RIPA lysis buffer | Biyuntian Biological Technology Research Institute, China | P0013B | |
| Rotary microtome | Leica, Germany | CM3050 | |
| Sorafenib | Bayer Company, Germany | 284461-73-0 | |
| Thiazolyl Blue (MTT) | Sigma, USA | M5655 | |
| Three-gas incubator | Thermo Fisher Scientific Inc., USA | 51026402 | |
| VEGF rabbit monoclonal antibody | BioLegend, USA | B199116 |
References
- Fujii T, Kuzuya T, Kondo N, Funasaka K, Ohno E, Hirooka Y, et al. Altered intestinal Streptococcus anginosus and 5α-reductase gene levels in patients with hepatocellular carcinoma and elevated Bacteroides stercoris in atezolizumab/bevacizumab non-responders. J Med Microbiol. 2024;73(9):001878.
- Gay MD, Drda JC, Chen W, Huang Y, Yassin AA, Duka T, et al. Implicating the cholecystokinin B receptor in liver stem cell oncogenesis. Am J Physiol Gastrointest Liver Physiol. 2024;326(3):G291-g309.
- Diao X, Guo C, Jin Y, Li B, Gao X, Du X, et al. Cancer situation in China: an analysis based on the global epidemiological data released in 2024. Cancer Commun (Lond). 2025;45(2):178-97.
- Yokota S, Yonezawa T, Momoi Y, Maeda S. Sorafenib inhibits tumor cell growth and angiogenesis in canine transitional cell carcinoma. J Vet Med Sci. 2022;84(5):666-74.
- Nassar-Reis JP, Umeta PF, Stefano JT, Longatto-Filho A, Carrilho FJ, Alves VAF, et al. P53 and VEGF are promising biomarkers for sorafenib efficacy in an experimental model of NASH-related HCC. J Mol Histol. 2023;54(5):473-88.
- Taha AM, Aboulwafa MM, Zedan H, Helmy OM. Ramucirumab combination with sorafenib enhances the inhibitory effect of sorafenib on HepG2 cancer cells. Sci Rep. 2022;12(1):17889.
- Ning L, Tian Y, Chen D, Han J, Xie G, Sun J. Sorafenib safety evaluation: Real-world analysis of adverse events from the FAERS database. Heliyon. 2024;10(18):e37348.
- Vij P, Hussain MS, Satapathy SK, Cobos E, Tripathi MK. The emerging role of long noncoding RNAs in sorafenib resistance within hepatocellular carcinoma. Cancers (Basel). 2024;16(23):3904.
- Lu X, Chen Z, Mi W, Zheng J, Liu Y. MARK1 suppress malignant progression of hepatocellular carcinoma and improves sorafenib resistance through negatively regulating POTEE. Open Med (Wars). 2024;19(1):20241060.
- Lee HJ, Lee JS, So H, Yoon JK, Choi JY, Lee HW, et al. Comparison between nivolumab and regorafenib as second-line systemic therapies after sorafenib failure in patients with hepatocellular carcinoma. Yonsei Med J. 2024;65(7):371-9.
- Tang W, Chen Z, Zhang W, Cheng Y, Zhang B, Wu F, et al. The mechanisms of sorafenib resistance in hepatocellular carcinoma: theoretical basis and therapeutic aspects. Signal Transduct Target Ther. 2020;5(1):87.
- Lin Q, Guan S, Peng M, Yu H. A mesoporous silica-based nano-drug co-delivery system with gemcitabine for targeted therapy of pancreatic cancer. J Coll Physicians Surg Pak. 2024;34(12):1456-63.
- Tang J, Liu Z, Xie G, Wang C, Jiang Y. POU4F1 enhances lung cancer gemcitabine resistance by regulating METTL3-dependent TWF1 mRNA N6 adenosine methylation. 3 Biotech. 2025;15(1):7.
- Cheng J, Zhu T, Liu S, Zhou J, Wang X, Liu G. Prediction of synergistic gemcitabine-based combination treatment through a novel tumor stemness biomarker NANOG in pancreatic cancer. RSC Med Chem. 2024;15(11):3853-61.
- Man S, Luo C, Yan M, Zhao G, Ma L, Gao W. Treatment for liver cancer: From sorafenib to natural products. Eur J Med Chem. 2021;224:113690.
- Llovet JM, Pinyol R, Kelley RK, El-Khoueiry A, Reeves HL, Wang XW, et al. Molecular pathogenesis and systemic therapies for hepatocellular carcinoma. Nat Cancer. 2022;3(4):386-401.
- Bronte F, Bronte G, Cusenza S, Fiorentino E, Rolfo C, Cicero G, et al. Targeted therapies in hepatocellular carcinoma. Curr Med Chem. 2014;21(8):966-74.
- Li H, Zhang Z, Zhou Z, Ding X, Zhou G. Optimal combination of gemcitabine, sorafenib, and S-1 shows increased efficacy in treating cholangiocarcinoma in vitro and in vivo. Anticancer Drugs. 2016;27(7):600-8.
- Awasthi N, Zhang C, Hinz S, Schwarz MA, Schwarz RE. Enhancing sorafenib-mediated sensitization to gemcitabine in experimental pancreatic cancer through EMAP II. J Exp Clin Cancer Res. 2013;32(1):12.
- Jiang S, Wang R, Zhang X, Wu F, Li S, Yuan Y. Combination treatment of gemcitabine and sorafenib exerts a synergistic inhibitory effect on non-small cell lung cancer in vitro and in vivo via the epithelial-to-mesenchymal transition process. Oncol Lett. 2020;20(1):346-56.