This randomized trial evaluates a smartphone measurement application as an adjunct for body-smartphone measurement application before percutaneous vertebroplasty. The approach shortened localization and correction times and reduced the number of fluoroscopic images acquired during localization, without a statistically significant difference in initial localization accuracy or 3-month pain and disability outcomes.
Research Article
Smartphone Measurement Application for Percutaneous Vertebroplasty in Osteoporotic Vertebral Compression Fractures: A Randomized Trial
In This Article
Summary
Abstract
Accurate vertebral-level localization before percutaneous vertebroplasty (PVP) commonly requires fluoroscopic confirmation, and repeated imaging may prolong the localization workflow. This single-center randomized controlled trial evaluated a smartphone measurement application for transmitting distance data obtained from imaging to the patient's back to assess its clinical efficacy. A smartphone with a rear-facing LiDAR sensor was used as the measurement instrument. The LiDAR’s principal function is to acquire high-precision three-dimensional point-cloud data of terrain, object surfaces, and the surrounding environment, thereby enabling accurate determination of object outlines and structures, measurement of distances, and detection of dynamic changes in ground objects. From October 2025 to March 2026, 43 patients with acute thoracolumbar osteoporotic vertebral compression fractures were allocated using a random-number table to smartphone measurement application (n = 21) or conventional anatomical localization with C-arm verification (n = 22). Outcomes included localization time (T0), the number of fluoroscopic images acquired during T0, initial localization accuracy, additional time required to correct a localization deviation (T1), and Visual Analog Scale (VAS) and Oswestry Disability Index (ODI) scores before surgery and at 3 months. Key findings: Compared with conventional localization, the smartphone measurement application resulted in a shorter T0, fewer fluoroscopic images during T0, and a shorter T1 (all P < 0.05). Initial localization accuracy was numerically higher in the smartphone measurement application group, but the between-group difference was not statistically significant (P > 0.05). VAS and ODI scores improved within both groups, with no significant between-group differences at 3 months (P > 0.05). The smartphone measurement application for smartphone measurement application improved localization efficiency without a detectable difference in initial accuracy or short-term clinical outcomes. Because radiation dose was not directly quantified, fewer fluoroscopic images should not be interpreted as proof of a proportional dose reduction.
Introduction
Osteoporotic vertebral compression fractures (OVCFs) are common in older adults and can cause pain, impaired mobility, reduced quality of life, spinal deformity, and, in severe cases, neurological impairment1,2. Percutaneous vertebroplasty (PVP) is widely used in selected patients with painful OVCFs because it can provide rapid pain relief with limited tissue trauma3,4. Accurate identification of the fractured vertebral level is essential before needle placement, particularly in the thoracolumbar region, where an inaccurate skin mark may lead to repeated fluoroscopic checks, interruption of the operative workflow, or wrong-level procedures5,6.
Conventional localization combines palpation of anatomical landmarks, manual distance estimation, and C-arm fluoroscopic confirmation7. A standard surgical ruler is simple, inexpensive, available as either a reusable sterilizable device or a single-use sterile device, and independent of software, battery power, and ambient lighting. Nevertheless, reusable rulers require cleaning and sterilization after each use, resulting in reprocessing costs. Ruler markings may also become worn over time, and dedicated stainless-steel surgical rulers may not be routinely available in every operating room. Ruler-based measurement further requires manual alignment between anatomical landmarks and measurement over a curved body surface. C-arm fluoroscopy provides direct vertebral confirmation but contributes to ionizing radiation exposure and requires repeated equipment positioning and experienced operation8. Advanced three-dimensional navigation and intraoperative computed tomography (CT) provide more sophisticated spatial guidance but require specialized equipment, additional setup, and substantial cost9.
Smartphones are widely available and portable, and a smartphone measurement application may allow an imaging-derived distance to be transferred to the body surface without preparing a dedicated measuring instrument10. Continuous on-screen distance display and device-orientation feedback may reduce dependence on subjective distance estimation and help standardize this transfer11. The intended advantage is therefore operational convenience and workflow standardization rather than established superiority over a sterile ruler or advanced navigation. However, this potential advantage is device-dependent because light detection and ranging (LiDAR)-equipped smartphones and devices using camera-based optical estimation or other depth-sensing technologies rely on different hardware and algorithms12,13. Device model, software version, calibration, operator training, patient body habitus, lighting, and device orientation may therefore affect reproducibility.
The present study evaluated a protocol in which the vertical distance from the posterior superior iliac spine to the spinous process at the fractured vertebral level was measured on preoperative imaging and transferred to the patient’s back using a smartphone measurement application. The method was compared with conventional anatomical localization followed by C-arm confirmation. The hypothesis was that the smartphone measurement application would shorten localization and correction times and reduce the number of fluoroscopic images acquired during localization without compromising initial localization accuracy or short-term clinical outcomes.
Protocol
The study was approved by the Ethics Committee of the Second Hospital of Lanzhou University (Approval no. 2025A-1064) and was conducted in accordance with institutional requirements for research involving human participants. All participants, or their legally authorized representatives, provided written informed consent for research participation, follow-up data collection, and publication of de-identified clinical images. The tools used for this protocol are listed in the Table of Materials.
1. Study design, setting, and participants
This single-center randomized controlled trial enrolled patients treated at the Second Hospital of Lanzhou University from October 2025 to March 2026. Eligible patients were randomly allocated to the smartphone measurement application group (n = 21) or the conventional localization group (n = 22). All procedures in both groups were performed by the same senior spine surgeon to reduce between-operator procedural variability.
Patients were eligible for inclusion if they had an acute thoracolumbar osteoporotic vertebral compression fracture involving T10–L2 that was confirmed by clinical examination, radiography, and preoperative imaging; a symptom duration of < 3 months; low-back pain corresponding to the fractured level; a Visual Analog Scale score > 4; an inadequate response to conservative treatment; a bone mineral density T-score of ≤−2.5 measured by dual-energy X-ray absorptiometry (DXA), consistent with osteoporosis; an absolute or relative indication for percutaneous vertebroplasty (PVP); and written informed consent provided by the patient or a legally authorized representative.
Patients were excluded if they had a pathological fracture caused by malignancy, multiple myeloma, infection, or another defined cause; disruption of the posterior vertebral wall; pedicle fracture; retropulsion into the spinal canal with spinal cord or nerve-root compression; burst fracture; vertebral collapse > 75%; severe cardiopulmonary, neurological, hepatic, renal, or coagulation disorders; previous spinal surgery at the same or an adjacent level; severe cognitive or psychiatric impairment preventing completion of perioperative assessment or follow-up; allergy to a contrast agent used during surgery; or pregnancy or lactation.
2. Randomization and allocation
A random sequence was generated from a random-number table by a clinician from another department who was not involved in the study. Eligible patients were allocated in a 1:1 ratio to either the smartphone measurement application group or the conventional localization group. Allocation concealment was maintained using sealed, opaque, consecutively numbered envelopes. Each envelope containing the group assignment was opened by the circulating nurse in the operating room only after written informed consent had been obtained. Because the localization procedures were visibly different, the operating surgeon could not be blinded to group assignment.
3. Smartphone measurement application calibration and operator training
A single depth-sensing smartphone and a single operating system version were used for each patient in the smartphone measurement application group. Calibration of the smartphone measurement application was required before each clinical measurement.
The calibration procedure was performed as follows. First, a standard 20 cm physical ruler was used as the reference distance. Second, calibration was performed indoors under stable lighting and room-temperature conditions to reduce environmental variability. Third, a single well-trained operator placed the smartphone at the ruler origin and moved it to the 20 cm mark, and the value reported by the measurement application was recorded. This sequence was repeated at least twice before each clinical measurement to ensure repeatability.
Measurements were accepted only when the discrepancy between the application reading and the physical ruler was < 5 mm. Representative repeated calibration measurements are shown in Figure 1.
Screen brightness and autofocus settings were maintained throughout all calibration and clinical sessions to minimize variation caused by ambient illumination. Standardized training covered application use, scanning-plane selection, maintenance of device orientation, distance transfer, and endpoint marking.
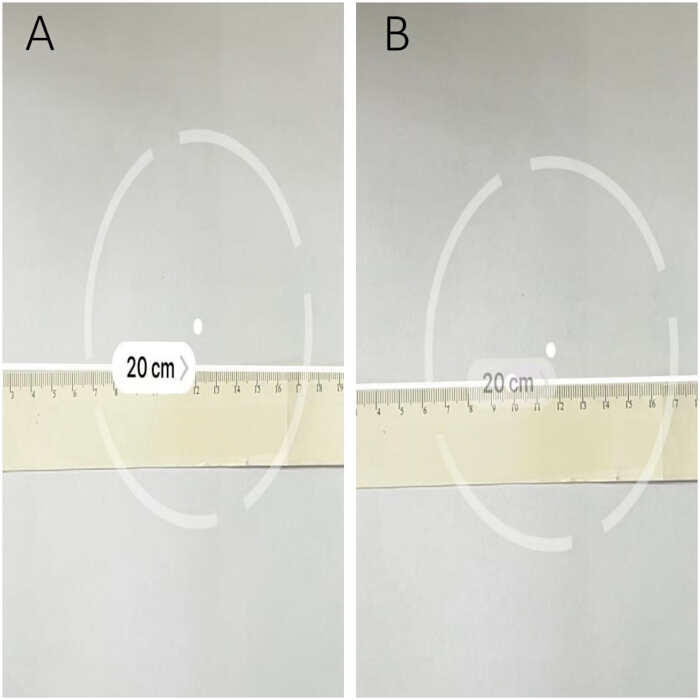
Figure 1: Preoperative calibration of the smartphone measurement application. (A, B) Two repeated measurements of a 20 cm physical ruler were performed under stable indoor conditions. Both displayed measurements were 20 cm. Clinical use required a discrepancy of < 5 mm. Please click here to view a larger version of this figure.
4. Preoperative imaging measurement
Preoperative sagittal computed tomography (CT) reconstructions were reviewed using a medical imaging archiving and communication system. The midsagittal image showing the full length of the sacrum was identified first. The image series was then advanced laterally until the sacrum narrowed and the posterior ilium appeared (Figure 2).
The posterior superior iliac spine was identified where the posterior ilium intersected or separated from the sacrum. The vertical distance from the posterior superior iliac spine to the spinous process at the fractured vertebral level was then measured. In the representative case shown in Figure 3, the displayed distance was 190.43 mm.
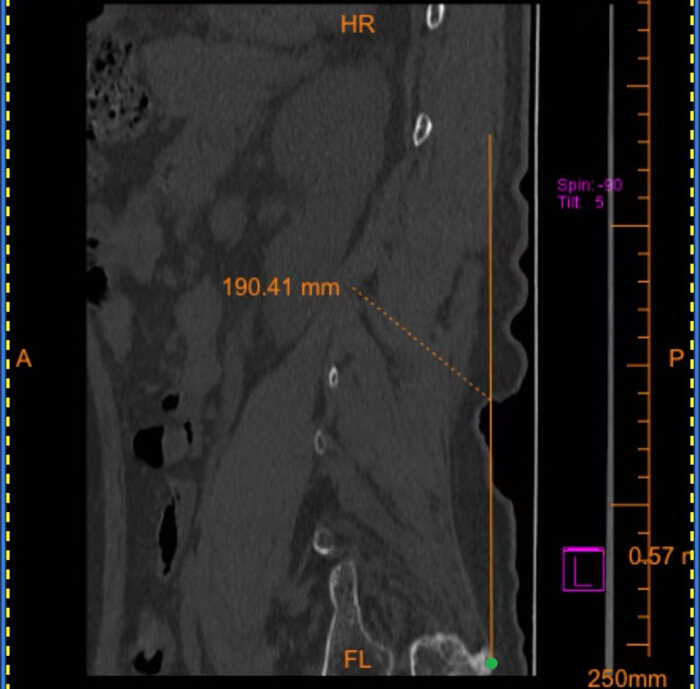
Figure 2: Preoperative sagittal computed tomography reconstruction used to identify the fractured thoracolumbar vertebral level and define the measurement plane. The green dots indicate the posterior superior iliac spine. Patient identifiers and institutional metadata have been removed. Please click here to view a larger version of this figure.
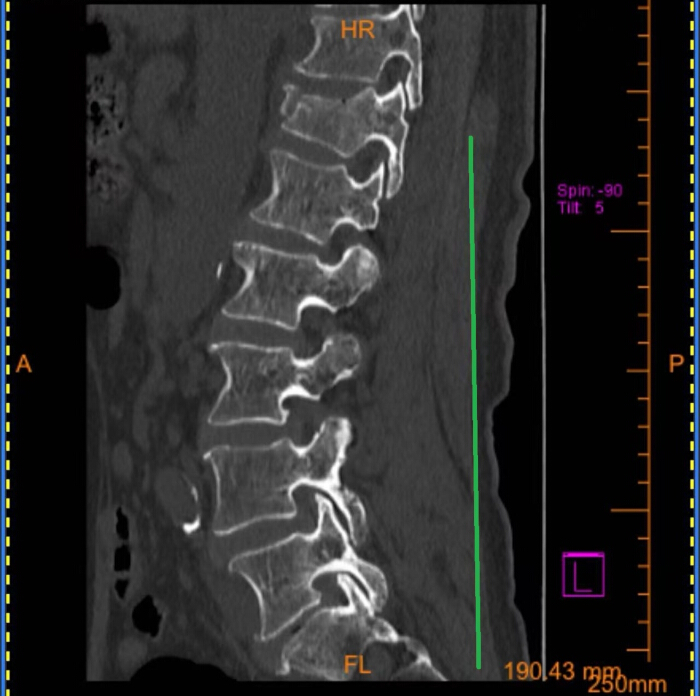
Figure 3: Preoperative sagittal computed tomography reconstruction showing measurement of the vertical distance from the posterior superior iliac spine reference level to the fractured vertebral level. The displayed distance was 190.43 mm. The green line represents the distance measured on the preoperative picture archiving and communication system from the posterior superior iliac spine to the spinous process at the fractured level. Patient identifiers and institutional metadata have been removed. Please click here to view a larger version of this figure.
5. Smartphone measurement application for body-surface localization
Before localization, the smartphone case and camera lens were cleaned with alcohol wipes. The patient was placed prone in a neutral position on the spinal operating table. The posterior superior iliac spine nearest the surgeon was palpated and marked (Figure 4).
The smartphone screen was positioned facing the surgeon, the measurement origin was placed at the marked posterior superior iliac spine, and the smartphone's long axis was maintained parallel to the patient’s back. The smartphone was moved slowly toward the head in the coronal plane while large horizontal fluctuations were avoided (Figure 5).
When the displayed distance corresponded to the preoperative imaging measurement, the endpoint was marked on the skin. Using this endpoint as a landmark, the presumed spinous process at the level of fracture was identified. A syringe needle was placed adjacent to the spinous process as a radiopaque marker (Figure 6).
Lateral fluoroscopy was then performed to verify the vertebral level before PVP (Figure 7). The smartphone served only as an auxiliary localization tool and did not replace fluoroscopic confirmation.
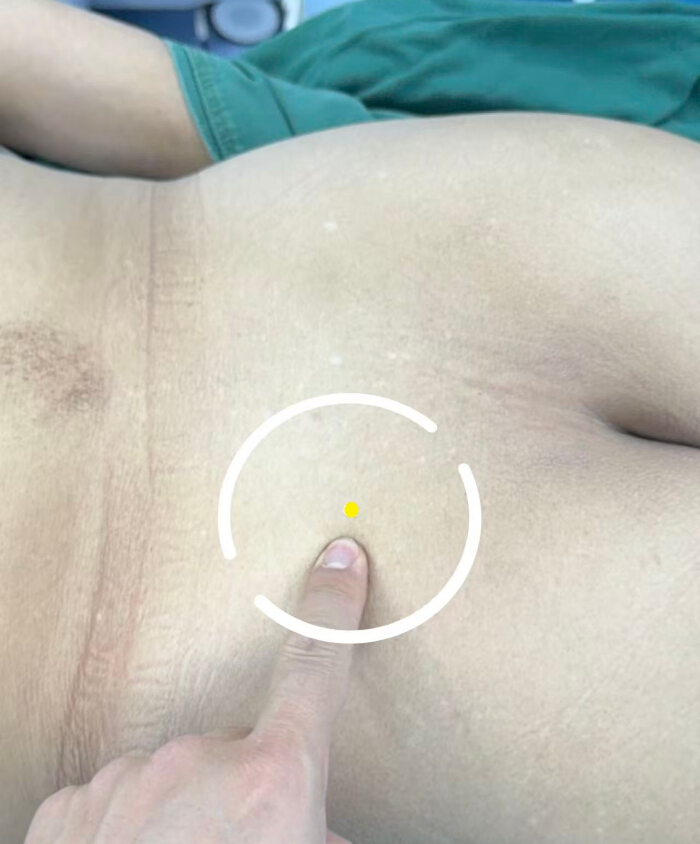
Figure 4: Intraoperative marking of the posterior superior iliac spine. The yellow marker indicates the palpated landmark. The left side of the image is oriented toward the patient’s head, and the right side is oriented toward the patient’s feet. Please click here to view a larger version of this figure.
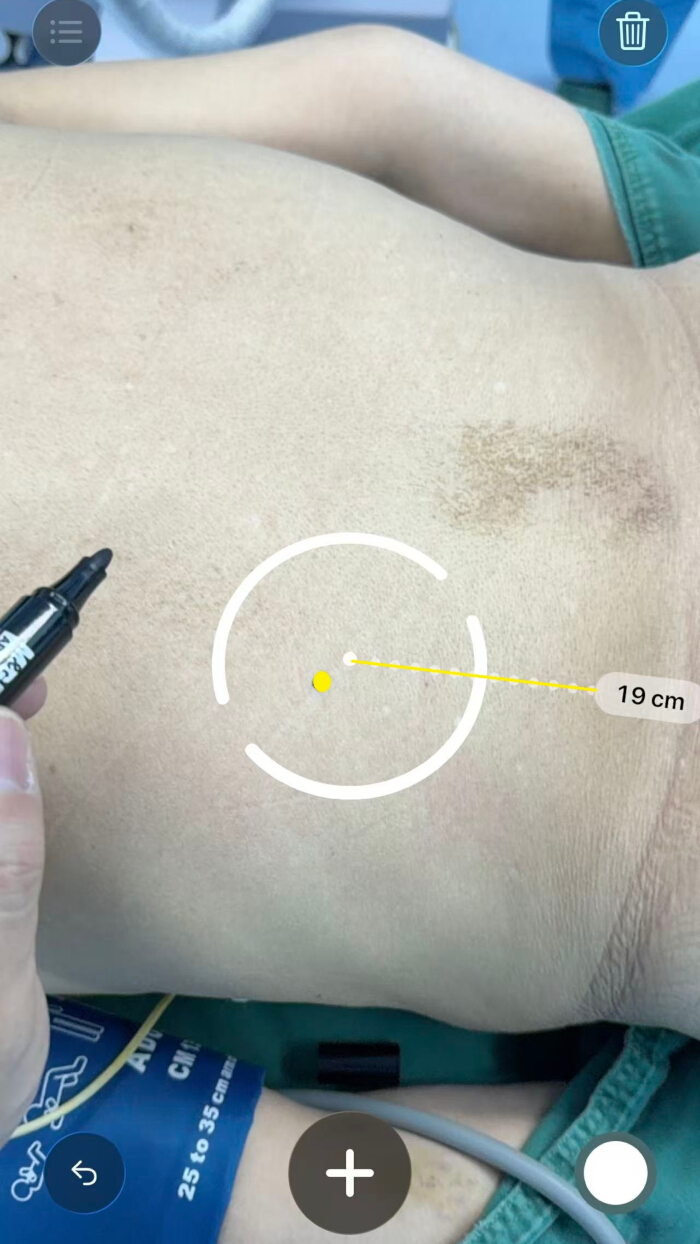
Figure 5: Transfer of the preoperative distance to the patient’s back using the smartphone measurement application. The application displays a transfer distance of 19 cm, and the yellow dots indicate the endpoint of the transfer. The left side of the image is oriented toward the patient’s head, and the right side is oriented toward the patient’s feet. Please click here to view a larger version of this figure.
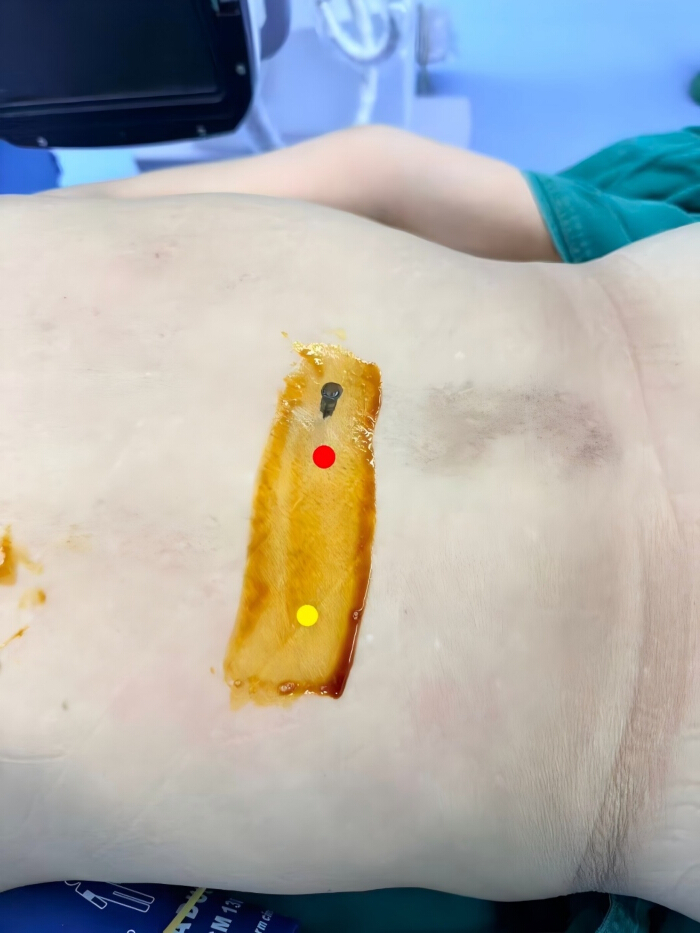
Figure 6: Placement of a radiopaque marker adjacent to the presumed T12 spinous process. The red marker denotes the presumed fractured segment, and the yellow marker denotes the reference point corresponding to the transferred endpoint. A 10 mL syringe needle was placed adjacent to the fractured segment for fluoroscopic verification. Please click here to view a larger version of this figure.
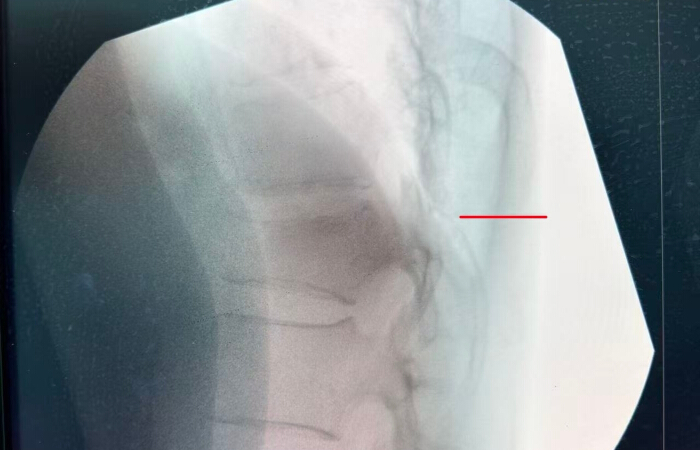
Figure 7: Anonymized lateral C-arm fluoroscopic confirmation of the marked T12 level. The red line indicates the position of the radiopaque marker, represented by a 10 mL syringe needle. Institutional names, patient identifiers, dates, and procedural metadata have been removed. Please click here to view a larger version of this figure.
6. Conventional localization
In the conventional localization group, the same surgeon estimated the target vertebral level using the posterior superior iliac spine, palpable spinous processes, interspinous spaces, and clinical experience. The estimated site was marked on the skin and checked using lateral fluoroscopy.
When the mark did not correspond to the intended vertebral level, the mark was adjusted and fluoroscopy was repeated until the correct level was confirmed.
7. Outcomes and time recording
T0, defined as localization time, was measured from the start of intraoperative localization, when the surgeon began marking the skin, until completion of anteroposterior and lateral fluoroscopy confirming the fractured vertebral level.
In the smartphone measurement application group, T0 included palpation of the posterior superior iliac spine and initiation of the smartphone measurement application. In the conventional localization group, T0 began with freehand marking based on anatomical landmarks.
T1, defined as correction time, represented the additional time required for remarking and repeated fluoroscopic verification when the initial skin marker did not overlie the fractured vertebral body. T1 was recorded as 0 when the initial localization was accurate.
T0, T1, and the number of fluoroscopic images were recorded prospectively by a circulating operating room nurse who was not involved in the surgical procedure. A standard stopwatch and data-collection sheet were used.
Clinical outcomes included Visual Analog Scale (VAS) and Oswestry Disability Index (ODI) scores obtained before surgery and at 3 months. The number of fluoroscopic images was recorded only during the localization phase. Only the number of fluoroscopic images obtained to locate the fractured vertebral level was recorded; fluoroscopy time and actual radiation dose were not collected.
8. Statistical analysis
Statistical analyses were performed using statistical analysis software. Approximately normally distributed continuous variables were summarized as mean ± standard deviation, and non-normally distributed variables were summarized as median and interquartile range.
Between-group continuous variables were compared using independent-samples t-tests or Mann–Whitney U tests, as appropriate. Categorical variables were reported as n (%) and compared using the chi-square test or Fisher’s exact test when expected cell counts were small. All tests were two-sided, and P < 0.05 was considered statistically significant.
Results
Participant characteristics
Forty-three patients were included, with 21 assigned to the smartphone measurement application group and 22 assigned to the conventional localization group. In the smartphone measurement application and conventional localization groups, respectively, mean age was 72.24 ± 5.12 years (smartphone group n = 21) and 73.00 ± 5.35 years (conventional group n = 22), the male-to-female distribution was 10:11 and 11:11, body mass index (BMI) was 23.41 ± 2.33 kg/m2 (smartphone group n = 21) and 23.54 ± 2.14 kg/m2 (conventional group n = 22), and bone mineral density T-score was −2.80 ± 0.16 (smartphone group n = 21) and −2.77 ± 0.14 (conventional group n = 22). No significant between-group differences were observed for these baseline variables (all P > 0.05; Table 1).
| Characteristic | smartphone measurement application group (n = 21) | Conventional group (n = 22) | Statistic | P value |
| Age (years) | 72.24 ± 5.12 | 73.00 ± 5.35 | t = −0.48 | 0.64 |
| Sex, male/female, n (%) | 10 (47.62%)/11 (52.38%) | 11 (50.00%)/11 (50.00%) | χ² = 0.02 | 0.88 |
| BMI (kg/m²) | 23.41 ± 2.33 | 23.54 ± 2.14 | t = −0.18 | 0.86 |
| Bone mineral density T-score | −2.80 ± 0.16 | −2.77 ± 0.14 | Z=0.41 | 0.68 |
| Data are presented as mean ± standard deviation (SD) for normally distributed continuous variables, as median (interquartile range) for non-normally distributed continuous variables, and n (%) for sex. All analyses included 21 participants in the smartphone measurement application group and 22 participants in the conventional localization group; there were no missing data. The normality of distributions was assessed using the Shapiro–Wilk test. Two-sided independent-samples t-tests were used for age and BMI; the Mann–Whitney U test was used for bone mineral density T-score; Pearson’s chi-square test was used for sex. BMI, body mass index; P, two-sided probability value. | ||||
Table 1: Baseline characteristics of the smartphone measurement application and conventional localization groups. Data are presented as mean ± standard deviation (SD) for normally distributed continuous variables, as median (interquartile range) for non-normally distributed continuous variables, and n (%) for sex. All analyses included 21 participants in the smartphone measurement application group and 22 participants in the conventional localization group; there were no missing data. The normality of distributions was assessed using the Shapiro–Wilk test. Two-sided independent-samples t-tests were used for age and BMI; the Mann–Whitney U test was used for bone mineral density T-score; Pearson’s chi-square test was used for sex. BMI, body mass index; P, two-sided probability value.
Intraoperative observational indicators
Compared with the conventional localization group, the smartphone measurement application group had a shorter T0 (1.52 ± 0.60 (smartphone group n = 21) min vs. 3.77 ± 1.11 min (conventional group n = 22)), P < 0.001; fewer fluoroscopic images acquired during T0 (2.33 ± 0.58 (smartphone group n = 21) vs. 3.18 ± 1.05 (conventional group n = 22)), P < 0.001; and a shorter T1 (0.14 ± 0.36 min (smartphone group n = 21) vs. 0.77 ± 0.97 min (conventional group n = 22)), P=0.02. Initial localization accuracy was 20/21 (95.24%) in the smartphone measurement application group (n = 21) and 18/22 (81.82%) in the conventional localization group (n = 22), P = 0.34. Significant between-group differences were observed for T0, fluoroscopic image count, and T1, but not for initial localization accuracy (Table 2). These findings indicate greater localization efficiency with the smartphone measurement application but do not demonstrate superior initial accuracy or a quantified reduction in radiation dose.
| Outcome | smartphone measurement application group (n = 21) | Conventional group (n = 22) | Statistic | P value |
| T0 (min) | 1.52 ± 0.60 | 3.77 ± 1.11 | Z = −5.14 | < 0.001 |
| Fluoroscopic images acquired during T0, (n) | 2.33 ± 0.58 | 3.18 ± 1.05 | Z = −2.55 | < 0.001 |
| Initial localization accuracy, n/N (%) | 20/21 (95.24%) | 18/22 (81.82%) | Fisher OR=4.44 | 0.34 |
| T1 (min) | 0.14 ± 0.36 | 0.77 ± 0.97 | Z = −1.97 | 0.02 |
| Data are presented as median (interquartile range) for non-normally distributed continuous variables and n/N (%) for initial localization accuracy. All analyses included 21 participants in the smartphone measurement application group and 22 participants in the conventional localization group; there were no missing data. T0 was the time from the start of skin marking to completion of fluoroscopic confirmation of the fractured vertebral level. Fluoroscopic image count was the number of images acquired during T0. T1 was the additional time required for remarking and repeated fluoroscopic verification after an inaccurate initial mark and was recorded as 0 when the initial localization was accurate. The normality of distributions was assessed using the Shapiro–Wilk test. Two-sided Mann–Whitney U tests were used for T0, fluoroscopic image count, and T1. Initial localization accuracy was compared using a two-sided Fisher’s exact test because an expected cell count was <5. P, two-sided probability value. | ||||
Table 2: Intraoperative observational indicators in the smartphone measurement application and conventional localization groups. Data are presented as median (interquartile range) for non-normally distributed continuous variables and n/N (%) for initial localization accuracy. All analyses included 21 participants in the smartphone measurement application group and 22 participants in the conventional localization group; there were no missing data. T0 was the time from the start of skin marking to completion of fluoroscopic confirmation of the fractured vertebral level. Fluoroscopic image count was the number of images acquired during T0. T1 was the additional time required for remarking and repeated fluoroscopic verification after an inaccurate initial mark and was recorded as 0 when the initial localization was accurate. The normality of distributions was assessed using the Shapiro–Wilk test. Two-sided Mann–Whitney U tests were used for T0, fluoroscopic image count, and T1. Initial localization accuracy was compared using a two-sided Fisher’s exact test because an expected cell count was <5. P, two-sided probability value.
Pain and disability outcomes
In the smartphone measurement application group (n = 21), Oswestry Disability Index (ODI) scores decreased from 46.10 ± 3.02 before surgery to 19.05 ± 2.96 at 3 months after surgery. In the conventional localization group (n = 22), ODI scores decreased from 45.27 ± 3.12 to 18.23 ± 3.04. Visual Analog Scale (VAS) scores decreased from 6.62 ± 0.86 to 2.62 ± 0.67 in the smartphone measurement application group (n = 21) and from 6.41 ± 0.85 to 2.68 ± 0.72 in the conventional localization group (n = 22). No significant between-group differences were observed at either time point in Table 3 (ODI preoperative, P=0.38; ODI at 3 months, P= 0.37; VAS preoperative, P=0.43; VAS at 3 months, P=0.77).
| Outcome and time point | smartphone measurement application group (n = 21) | Conventional group (n = 22) | Statistic | P value |
| ODI, preoperative | 46.10 ± 3.02 | 45.27 ± 3.12 | t = 0.88 | 0.38 |
| ODI, at 3 months | 19.05 ± 2.96 | 18.23 ± 3.04 | t= 0.90 | 0.37 |
| VAS, preoperative | 6.62 ± 0.86 | 6.41 ± 0.85 | t= 0.80 | 0.43 |
| VAS, at 3 months | 2.62 ± 0.67 | 2.68 ± 0.72 | t= -0.30 | 0.77 |
| Data are presented as mean ± standard deviation (SD). All analyses included 21 participants in the smartphone measurement application group and 22 participants in the conventional localization group; there were no missing data. Preoperative scores were recorded before percutaneous vertebroplasty, and follow-up scores were recorded 3 months after surgery. P values are from two-sided independent-samples t-tests comparing the groups at each time point; formal paired within-group comparisons are not reported in this table. ODI, Oswestry Disability Index; VAS, Visual Analog Scale; P, two-sided probability value. | ||||
Table 3: Between-group comparisons of Visual Analog Scale and Oswestry Disability Index scores before surgery and at 3 months. Data are presented as mean ± standard deviation (SD). All analyses included 21 participants in the smartphone measurement application group and 22 participants in the conventional localization group; there were no missing data. Preoperative scores were recorded before percutaneous vertebroplasty, and follow-up scores were recorded 3 months after surgery. P values are from two-sided independent-samples t-tests comparing the groups at each time point; formal paired within-group comparisons are not reported in this table. ODI, Oswestry Disability Index; VAS, Visual Analog Scale; P, two-sided probability value.
DATA AVAILABILITY:
The de-identified participant-level dataset underlying Tables 1–3 is publicly available in Zenodo: https://doi.org/10.5281/zenodo.21827327. The record contains one row per participant and excludes direct identifiers, dates of birth, medical record numbers, contact details, and identifiable imaging.
Discussion
This randomized study evaluated a smartphone-based measurement application for transferring a preoperatively measured vertebral-level distance to the body surface prior to percutaneous vertebroplasty (PVP). Use of the smartphone measurement application shortened localization time, reduced the number of fluoroscopic images acquired during localization, and reduced the additional time required to correct localization deviations. Initial localization accuracy was numerically higher in the smartphone measurement application group but did not differ significantly between groups. Visual Analog Scale (VAS) and Oswestry Disability Index (ODI) outcomes were also similar between groups at 3 months. The principal finding was therefore improved efficiency in the localization workflow rather than demonstrated superiority in accuracy or clinical efficacy.
Conventional localization relies on palpable anatomical landmarks, spatial judgment, and fluoroscopic verification14. In practice, C-arm positioning and repeated image acquisition can interrupt the operative workflow and expose patients and staff to additional ionizing radiation15. The smartphone measurement application converts a distance measured in image space into a body-surface reference and provides a continuous distance display during transfer. This approach may reduce subjective distance estimation and the need for repeated corrections. Nevertheless, the method remains dependent on correct landmark identification and requires fluoroscopic confirmation before needle placement.
The present study did not directly compare localization using the smartphone measurement application with localization using a standard sterile surgical ruler. A standard sterile surgical ruler offers advantages including simplicity, low cost, sterility, and independence from software, battery power, and ambient lighting. The potential technical advantages of the smartphone measurement application include real-time digital measurement with automatic distance calculation, reduced reliance on manual alignment, and reduced potential for visual estimation errors. Reusable rulers also require cleaning and disinfection after each use, which may increase reprocessing requirements. Their markings may deteriorate over time, and dedicated stainless-steel surgical rulers may not be available in every operating room. The smartphone measurement application may therefore reduce the need to prepare, clean, or disinfect a dedicated measuring instrument for each case. However, the current findings do not establish technical or clinical superiority over a standard surgical ruler. A direct comparison between smartphone-assisted measurement and conventional anatomical localization is warranted.
The lower number of fluoroscopic images acquired during localization is relevant to workflow efficiency and is directionally consistent with the as low as reasonably achievable (ALARA) principle14. However, fluoroscopic image count is only a proxy for radiation exposure. Dose per exposure varies according to patient body habitus, beam geometry, equipment settings, collimation, magnification, and acquisition mode15. Because no direct dosimetric endpoint was reported, the findings should be described as fewer fluoroscopic images during localization rather than a quantified reduction in radiation dose. Future studies should record fluoroscopy time, dose-area product, reference air kerma, and, when feasible, staff dosimetry during both the localization phase and the complete procedure.
Generalizability is influenced by device characteristics, operator technique, and environmental conditions. Rear-facing LiDAR sensors became commercially available selectively, whereas other smartphones rely on camera-based augmented-reality algorithms, time-of-flight sensors, structured-light systems, or other depth-sensing technologies to estimate distance. Differences in sensing hardware and software algorithms may therefore affect measurement accuracy and limit cross-device applicability.
Operator consistency is another important consideration. A single-device, single-operator workflow was used to reduce procedural heterogeneity. Nevertheless, measurements remain sensitive to device orientation, scanning speed, and consistency in identifying bony landmarks. These factors may introduce variability when different operators perform the procedure. Ambient lighting and patient posture may also affect measurement performance. Reproducible use therefore requires reporting the exact device model and software version, applying standardized calibration procedures, and ensuring adequate operator training. Larger multicenter trials should prespecify the devices and operators used and establish standardized calibration protocols.
Patient morphology may further affect landmark palpability and transfer of a measured distance over the body surface16,17. Atik and Gul assessed sarcopenia using psoas muscle measurements in patients with osteoporotic vertebral compression fractures, illustrating the body-composition heterogeneity present in this population18. The present study did not measure psoas muscle area or diagnose sarcopenia; therefore, direct comparison according to sarcopenia status was not possible. Future studies should evaluate whether body mass index, soft-tissue thickness, psoas muscle area, spinal deformity, or sarcopenia affects localization error or the benefit of smartphone measurement applications.
Several procedural precautions are important. The device should be maintained in a stable coronal orientation, and large lateral deviations should be corrected before measurement continues. Ambient glare and abrupt lighting changes should be minimized, and consistent focus and display settings should be maintained. The posterior superior iliac spine and the target spinous process level must be accurately identified because the application cannot compensate for an incorrect anatomical reference point. In patients with obesity, skin folds, or indistinct surface landmarks, palpation and imaging information should be interpreted together. Key landmarks should be marked temporarily and reconfirmed before fluoroscopy to reduce errors caused by patient movement19. The localization workflow must not compromise aseptic technique. The smartphone serves as an auxiliary prelocalization device and should not enter the sterile field unless it is covered and handled in accordance with institutional infection-control procedures. For multilevel or anatomically complex fractures, each target level should be verified fluoroscopically20.
This study has several limitations. First, the single-center design and small sample size limit precision and generalizability, particularly for patients with severe deformity or other anatomical variation. Second, the method depends on palpable bony landmarks and may be affected by obesity, soft-tissue thickness, skin folds, or movement between imaging measurement and operative positioning. Third, no direct comparison was performed with a sterile ruler, three-dimensional navigation, or intraoperative computed tomography navigation. Fourth, a single experienced surgeon and one smartphone workflow were used, and interoperator reproducibility, the learning curve, and performance across different device models were not assessed. Fifth, the sample was insufficient for robust analysis of single-level versus multilevel OVCF. Sixth, radiation assessment was limited to the number of fluoroscopic images acquired during localization, and fluoroscopy time and actual radiation dose were not collected. Larger multicenter trials should include multiple devices and operators, direct dosimetry, standardized calibration, prespecified morphology-related subgroup analyses, and an appropriate ruler-based comparator.
Conclusion
The smartphone measurement application shortened localization and correction times and reduced the number of fluoroscopic images acquired during the localization phase of PVP, without a statistically significant difference in initial localization accuracy or 3-month pain and disability outcomes. The method may serve as a low-cost workflow adjunct when device-specific calibration, anatomical assessment, aseptic precautions, and fluoroscopic confirmation are retained. These findings do not establish superiority over advanced navigation and do not directly demonstrate a reduction in radiation dose. Larger multicenter studies using multiple devices and operators, direct dosimetry, and appropriate comparators are warranted.
Disclosures
The authors declare no conflicts of interest.
Author Contributions:
Jing Wang contributed to the study design, calibrated the smartphone measurement application, conducted clinical measurements, participated in patient enrollment and surgical procedures, curated and analyzed clinical data, visualized the results, and drafted the manuscript. The study was conceptualized and overseen by Jin Zhang, who verified the imaging measurements and surgical procedures and provided substantial intellectual input during manuscript revision.
Acknowledgements
This work was supported by the Gansu Provincial Scientific Research Project on Traditional Chinese Medicine (GZKZ-2025-49) and the Cuiying Scientific and Technological Innovation Program of The Second Hospital & Clinical Medical School, Lanzhou University (CY2025-LC-A02).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Alcohol | Lanzhou Meierkang Biotechnology Co., Ltd. | 2024-0006 | Used with gauze for cleaning |
| Depth-sensing smartphone | Apple Inc., Cupertino, CA, USA | A2412 | iPhone 12 Pro Max |
| Fluoroscopy system | Shanghai Siemens Medical Devices Co., Ltd. | Cios Select S3 | C-arm fluoroscopy system |
| Gauze | Henan Hongran Medical Devices Co., Ltd. | 20190025 | Used with alcohol for cleaning |
| Medical imaging archiving and communication system | Beijing Sichuang Guanyu Technology Development Co., Ltd. | Not applicable | Picture archiving and communication system, version 3.1 |
| Physical ruler | Shenzhen Pumen Technology Co., Ltd. | 9350B | Standard 20 cm ruler, Lifowave 9350B |
| Radiopaque marker | Shanghai Kangdelai Enterprise Development Group Co., Ltd. | 0.7 × 32 TWLB | 10 mL syringe needle |
| Smartphone measurement application | Apple Inc., Cupertino, CA, USA | Not applicable | Built-in distance-measurement application |
| Smartphone operating system | Apple Inc., Cupertino, CA, USA | Not applicable | iOS 18.1 |
| Statistical analysis software | IBM Corp., Armonk, NY, USA | 5725-A54 | IBM SPSS Statistics for Windows, version 25.0 |
| Timing device | Apple Inc., Cupertino, CA, USA | Not applicable | Built-in smartphone stopwatch application |
References
- Liang JW et al. Enhancing precision in percutaneous vertebroplasty: a study on patient-specific 3D-printed guides for osteoporotic vertebral compression fractures. Front Surg. 2026;13:1800908. doi:10.3389/fsurg.2026.1800908.
- Li G et al. Clinical outcomes of percutaneous vertebroplasty using robot-assisted cross-puncture technique for osteoporotic vertebral compression fractures. J Robot Surg. 2026;20(1):674. doi:10.1007/s11701-026-03587-z.
- Ma C, Chen Z, Fang Q, Shu Y. Comparative efficacy of percutaneous vertebroplasty combined with minimally invasive pedicle screw fixation versus percutaneous vertebroplasty alone in the treatment of elderly osteoporotic vertebral compression fractures. Libyan J Med. 2026;21(1):2670006.
- Song Z et al. Percutaneous vertebroplasty and percutaneous kyphoplasty for osteoporotic vertebral compression fractures: medium- and long-term evaluation of clinical outcomes and affecting factors. BMC Musculoskelet Disord. 2026. doi:10.1186/s12891-026-10050-5.
- Yusufu A, Yasin P, Haibier A, Ma Y. The impact of bone cement distribution in unilateral PVP on therapeutic outcomes of vertebral compression fracture repair. Orthop Res Rev. 2026;18:567335.
- Zhou T et al. Efficacy of acupuncture in the treatment of residual pain after osteoporotic vertebral compression fractures percutaneous vertebroplasty among older adults: a study protocol for a randomized controlled clinical trial. J Pain Res. 2026;19:598264.
- Warimezgane O et al. Occupational radiation exposure in spine surgery: organ-specific OSL phantom dosimetry and workload-based risk assessment. J Radiol Prot. 2026;46(3). doi:10.1088/1361-6498/ae8551.
- Kim DH, Hur JW, Hong JT. Radiation exposure in minimally invasive cervical spine surgery: a systematic review. Medicina (Kaunas). 2026;62(5):977.
- Kitahara T et al. Real-time phase-dependent occupational radiation exposure analysis in full-endoscopic spine surgery. Sci Rep. 2026. doi:10.1038/s41598-026-58052-6.
- Nakaso S, Ueda H, Ono S, Ogawa R. Volumetric assessment of a soft-tissue tumor using smartphone light detection and ranging and neural radiance fields: a single case. Plast Reconstr Surg Glob Open. 2026;14(5):e7712.
- Moj K, Arseniy I, Żak K, Malicki D, Oszkinis G. 3D measurement of chronic wounds in routine care: a review with practical guidance for smartphone photogrammetry. Ann Biomed Eng. 2026. doi:10.1007/s10439-026-04172-z.
- Song B et al. Smartphone-based LiDAR application for easy and accurate wound size measurement. J Clin Med. 2023;12(18):6042.
- Papadakis K, Mileva-Popova RD, Yanev KK, Peychinov D, Bogdanov TG. Rapid low-cost production of a patient-specific thumb orthosis using smartphone light detection and ranging scanning and three-dimensional printing. Cureus. 2026;18(4):e106955.
- Cool J et al. Radiation reduction in computer-assisted spinal deformity surgery using 3D and 2D pediatric-specific low-dose fluoroscopy protocols. N Am Spine Soc J. 2026;26:100889.
- Türkmen A et al. The effect of a mobile application-based music intervention on pain levels and analgesic consumption following surgery: a randomized controlled trial. Rev Assoc Med Bras (1992). 2026;72(4):e20251930.
- Xu X et al. Spatial posture perception method combined with ball-tip technique improves pedicle screw placement in adult degenerative scoliosis: a dual-center retrospective cohort study. BMC Surg. 2026;26(1):491.
- Lamé G et al. A qualitative human factors investigation of the impact of intraoperative CT-based navigation on interprofessional work in the operating room. Surg Open Sci. 2026;33:37–43.
- Atik I, Gul E. Evaluation of sarcopenia by psoas muscle measurements in osteoporotic patients with vertebral compression fracture. J Coll Physicians Surg Pak. 2024;34(6):713–716.
- Maizels M et al. Utilization of an ultrasonography-computed tomography fusion system in the lumbar spine. Int J Spine Surg. 2026;20(3):420–425.
- Garg S, Aranha RSM, Sam F. Localization of the motor entry point of the adductor pollicis muscle using surface landmarks for safe and effective botulinum toxin injection administration. Ann Anat. 2026;267:152881.
Reprints and Permissions
This article has been published
Video Coming Soon