This retrospective clinical study compares fiber post-and-core crowns and all-ceramic onlays for restoring posterior teeth after root canal treatment and demonstrates that all-ceramic onlays provide improved periodontal health, masticatory function, and oral health-related quality of life.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
Clinical Efficacy and Long-term Observation of Fiber Post-and-Core Crown versus Onlay Restoration for Posterior Teeth with Post-endodontic Defects
In This Article
Summary
Abstract
This retrospective study aimed to compare the clinical efficacy and long-term outcomes of fiber post-and-core crown restoration and all-ceramic onlay restoration for posterior teeth with defects following root canal treatment. A total of 100 patients treated between January 2020 and December 2022 were allocated to two groups (n = 50 each): a fiber post-and-core crown group and an all-ceramic onlay group. Restoration integrity, tooth integrity, marginal adaptation, interproximal contacts, periodontal parameters (periodontal pocket depth, gingival index, and plaque index), masticatory function (bite force and chewing efficiency), and oral health-related quality of life (OHIP-14 scores) were evaluated before treatment and at 3 months and 2 years after restoration. No significant differences were observed between the groups in restoration integrity, tooth integrity, marginal adaptation, or interproximal contacts at either follow-up. However, the all-ceramic onlay group demonstrated significantly lower periodontal pocket depth, gingival index, and plaque index at both follow-up time points. Bite force and chewing efficiency were significantly greater in the onlay group, and OHIP-14 scores indicated better oral health-related quality of life. At the 2-year follow-up, two restoration failures occurred in the fiber post-and-core crown group, whereas no failures were observed in the all-ceramic onlay group. These findings suggest that all-ceramic onlay restorations provide superior clinical outcomes for posterior teeth after root canal treatment, particularly with respect to periodontal health, masticatory function, and patient-reported quality of life, and may represent a promising alternative to conventional fiber post-and-core crown restorations.
Introduction
Root canal treatment is a common procedure for managing pulpitis and apical periodontitis. Its primary objectives are to eliminate inflammation, prevent the spread of infection, and preserve the function and appearance of the affected tooth by removing infected pulp tissue, disinfecting the root canal system, and sealing it with an appropriate filling material1. Advances in endodontic techniques have improved treatment outcomes, enabling teeth with pulpitis, apical periodontitis, and extensive structural defects to be preserved for extended periods following successful root canal treatment2. Posterior teeth, including premolars and molars, play a critical role in mastication by grinding food into smaller particles, thereby facilitating digestion and absorption3. However, after root canal treatment, these teeth exhibit reduced structural strength due to extensive removal of carious and infected dentin, as well as the loss of pulpal vitality, thereby increasing their susceptibility to fracture4. Consequently, restoration after root canal treatment should be planned with consideration of the remaining tooth structure, the magnitude and direction of occlusal forces, and the most appropriate restorative approach to optimize clinical outcomes.
Successful restoration of tooth defects depends on adherence to both biological and mechanical principles; failure to do so may compromise restoration longevity and damage the supporting tooth structure and surrounding tissues5. Selection of an appropriate restorative method requires comprehensive evaluation of multiple factors, including restoration of masticatory function, long-term durability, periodontal and gingival health, esthetic outcome, mechanical stability, and individual patient needs6. Because the remaining tooth structure is often limited after root canal treatment, post-and-core restorations have traditionally been used to improve retention and resistance, thereby providing support for subsequent full-coverage crowns7. Fiber post-and-core crowns have gained widespread clinical acceptance because of their favorable biocompatibility and mechanical properties, including an elastic modulus similar to that of dentin, which enhances biomechanical compatibility with the restored tooth8. Nevertheless, although post-and-core restorations improve crown retention, they require additional removal of radicular dentin during post-space preparation. This secondary invasive procedure increases the risk of root perforation and fracture and conflicts with the principle that preservation of tooth structure contributes to greater fracture resistance9.
To minimize tooth preparation and maximize preservation of the remaining tooth structure, minimally invasive restorative concepts and stepwise treatment strategies have received increasing attention in recent years. Clinicians are increasingly selecting restorative approaches based on the condition of the remaining tooth structure while evaluating the clinical performance of different techniques. Advances in dental materials and adhesive technologies have expanded the use of indirect adhesive restorations consistent with minimally invasive principles. An inlay is an indirect restoration fabricated outside the oral cavity and adhesively bonded into a prepared tooth to restore its morphology and function10. Similar to a full crown, the restoration is fabricated after tooth preparation and subsequently cemented using adhesive techniques11. When sufficient remaining tooth structure provides adequate fracture resistance, compressive strength, and retention form, inlay restoration may be considered. However, conventional inlays restore only the defect itself and provide limited protection for the remaining tooth structure12. An onlay is a modified form of indirect restoration in which part of the restoration is bonded within the tooth while the remaining portion covers one or more cusps. This design is particularly suitable for posterior teeth with cusp involvement because it redistributes oblique occlusal forces toward more favorable vertical loading, thereby reducing mechanical stress on the restoration13. Compared with conventional full-coverage restorations, onlays require less tooth preparation, preserve cervical tooth structure, reduce stress concentration in the cervical region, and lower the risk of cervical fracture. They are therefore appropriate for restoring large posterior defects, fractured cusps, cracked teeth, and teeth requiring occlusal reconstruction while simultaneously restoring anatomical form, occlusion, and proximal contact relationships14.
In current clinical practice, post-and-core crowns and onlays are the two most frequently used options for restoring posterior teeth with extensive structural defects. However, clear clinical criteria for selecting between these restorative approaches remain lacking, and treatment decisions often rely on clinician experience, introducing substantial subjectivity. To date, few clinical studies have directly compared all-ceramic onlays with fiber post-and-core crowns for restoring posterior teeth after root canal treatment, and most of the available evidence derives from laboratory investigations. In recent years, the biomimetic concept has received increasing attention because it emphasizes maximal preservation of tooth structure and avoidance of invasive procedures such as post-space preparation. Consequently, postless restorative strategies based on adhesive bonding and the ferrule effect have emerged as promising alternatives to traditional intraradicular retention methods. However, comparative clinical evidence evaluating these approaches remains limited. Therefore, it was hypothesized that all-ceramic onlay restoration would provide superior clinical outcomes compared with fiber post-and-core crown restoration by improving periodontal health, enhancing masticatory function, and achieving better oral health-related quality of life at 3 months and 2 years after restoration. To test this hypothesis, this study compared the clinical efficacy of all-ceramic onlays and fiber post-and-core crowns for restoring posterior teeth with defects after root canal treatment by evaluating restoration outcomes, recovery of masticatory function, periodontal health, and oral health-related quality of life. The findings are intended to provide clinical evidence to support restorative decision-making for posterior teeth following root canal treatment.
Access restricted. Please log in or start a trial to view this content.
Protocol
This retrospective study was conducted in accordance with the Declaration of Helsinki. The study protocol was approved by the Ethics Committee of WuYi County Stomatological Hospital (Approval No. 2025-1) on February 25, 2025. Patients treated between January 2020 and December 2022 were enrolled. Written informed consent was obtained from all participants for study participation and publication of de-identified clinical images. The research tools used in this experiment are listed in the Table of Materials. The study workflow is illustrated in Figure 1.

Figure 1: Study workflow. Flowchart illustrating patient enrollment, group allocation, restorative procedures, and follow-up evaluations performed at 3 months and 2 years after restoration. Please click here to view a larger version of this figure.
1. Study design
This retrospective study enrolled patients treated between January 2020 and December 2022 who met the predefined eligibility criteria.
- Inclusion criteria
Patients were eligible for inclusion if they met all of the following criteria: posterior tooth defects confirmed by dental radiographs, with root canal treatment completed more than 1 week previously; radiographs demonstrating adequate root canal filling, no significant periapical radiolucency, no alveolar bone resorption, and healthy periodontal tissues; absence of percussion pain or tooth mobility; sufficient remaining tooth structure to support either all-ceramic onlay or fiber post-and-core crown restoration; normal posterior occlusion without parafunctional habits such as bruxism or clenching; no acute or severe systemic disease that would contraindicate treatment; and normal cognitive function with the ability to cooperate throughout treatment. - Exclusion criteria
Patients were excluded if they presented with uncontrolled residual pulpitis, apical periodontitis, temporomandibular joint disorder syndrome, poor oral hygiene, active periodontitis, absence of an opposing tooth, presence of a removable prosthesis as the opposing dentition, abnormal occlusal habits, pregnancy or lactation, anatomical abnormalities such as malformed teeth, or temporomandibular joint disease.
2. Fiber post-and-core crown restoration treatment
The fiber post-and-core crown restoration procedure was performed according to a standardized protocol. Tooth shade was determined within 5 s under natural light using a shade guide to minimize visual fatigue. Based on the working length established during root canal treatment and the root diameter observed on dental radiographs, the post space was sequentially prepared with P-drills and then shaped with a fiber post-shaping drill. The post diameter was maintained at approximately one-quarter to one-third of the root diameter. The post length was planned to be at least equal to the clinical crown length, with the intrabony portion extending beyond one-half of the root length within the alveolar bone while preserving a minimum 5 mm apical seal. The root canal walls were confirmed to be smooth before post placement.
A glass fiber post of appropriate length and diameter was selected and tried in to confirm an accurate fit. The post was immersed in 75% alcohol, shaken, and air-dried. The root canal was irrigated with saline, ultrasonically cleaned, disinfected with 75% alcohol, and dried. A self-etch adhesive was applied to both the root canal walls and the post surface, then light-cured for 15 s. Dual-cure resin cement was injected from the base of the post space, the post was inserted, and the assembly was light-cured for 40 s. A resin core was subsequently built up using core resin and light-cured.
Tooth preparation was performed according to the requirements for an all-ceramic crown, including a uniform 1.0 mm occlusal reduction, elimination of undercuts on all surfaces, and a chamfer finish line at the cervical margin. Impressions were obtained using a two-step addition silicone technique. Following gingival displacement with retraction cords, a heavy-body impression was made, followed by a light-body wash impression using the double-cord technique. A temporary crown was fabricated and cemented to protect the prepared tooth and maintain the prepared space until definitive restoration.
The tooth shade was reconfirmed, and a super-hard plaster model was prepared. The occlusal relationship was recorded using bite registration silicone and submitted to the dental laboratory for fabrication of a zirconia full crown. During the clinical try-in, proximal contacts and marginal adaptation were evaluated using articulating paper (40 µm and 200 µm) and adjusted as necessary.
For final bonding, the intaglio surface of the crown and the prepared tooth were cleaned and dried. Dual-cure resin cement was mixed and applied to the internal surface of the restoration. The crown was fully seated, and excess cement was tack-cured for 1–2 s before removal. Final light curing was then performed from multiple directions for 20 s per surface. Iodine glycerin was applied to the gingival sulcus, and patients were instructed to avoid chewing hard foods on the treated side for 24 h (Figure 2).
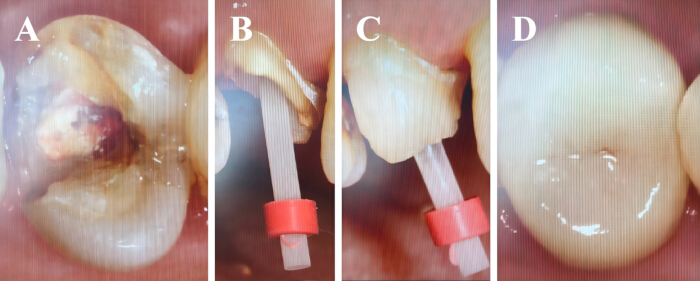
Figure 2: Representative clinical images of posterior tooth restoration with a fiber post-and-core crown. (A) Clinical appearance of the tooth 1 week after root canal treatment, before restoration. (B) Placement of the fiber post within the prepared root canal. (C) Bonding and core build-up following fiber post placement. (D) Immediate postoperative appearance after placement of the definitive crown. Please click here to view a larger version of this figure.
3. All-ceramic onlay restoration
The all-ceramic onlay restoration procedure was performed according to a standardized protocol. Tooth shade was determined within 5 s under natural light using the same shade guide described for the fiber post-and-core crown group. Discolored, softened, and structurally weakened cusp tissue was removed. A P-drill was used to remove 1–2 mm of gutta-percha from the root canal orifice, after which the canal was irrigated with saline, dried, disinfected with 75% alcohol, and treated with a self-etch adhesive. The canal orifice was sealed with flowable resin and light-cured for 40 s. The cavity was prepared with a flat pulpal floor, straight axial walls, and no undercuts. Occlusal reduction consisted of 1.5 mm on functional cusps and 1.0 mm on non-functional cusps while maintaining a remaining tooth thickness greater than 3 mm. The cavity walls were flared at approximately 6°, with rounded internal line angles, a convergence angle of 2°–6°, and a 90° shoulder finish line.
Impressions were obtained using the same two-step addition silicone technique described for the fiber post-and-core crown group. A temporary onlay was fabricated and placed to protect the prepared tooth. The occlusal relationship was recorded using bite registration silicone, and the working model was submitted to the dental laboratory for fabrication of a lithium disilicate ceramic onlay. During the clinical try-in, marginal adaptation was evaluated using a periodontal probe, interproximal contacts were assessed using dental floss, and the shape and shade of the restoration were confirmed with the patient.
For final bonding, the intaglio surface of the onlay was etched with 9.5% hydrofluoric acid for 40 s, rinsed thoroughly, neutralized with sodium bicarbonate, ultrasonically cleaned in 95% alcohol for 5 min, and dried. A silane coupling agent followed by an adhesive was applied to the restoration surface. The prepared tooth was isolated, etched with 35% phosphoric acid for 30 s, rinsed, and dried. Adhesive was applied and light-cured for 15 s. The onlay was bonded using dual-cure resin cement, excess cement was removed, and the restoration was light-cured for 40 s. Occlusion was adjusted as required, and the restoration was polished (Figure 3).
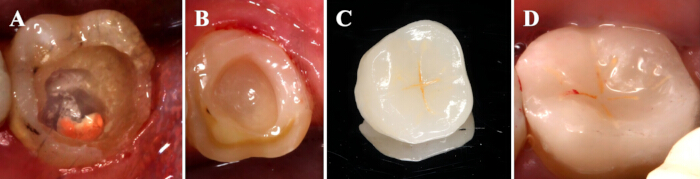
Figure 3: Representative clinical images of posterior tooth restoration with an all-ceramic onlay. (A) Clinical appearance of the tooth 1 week after root canal treatment, before restoration. (B) Tooth preparation for the all-ceramic onlay. (C) Lithium disilicate ceramic onlay before placement. (D) Immediate postoperative appearance after onlay try-in and definitive bonding. Please click here to view a larger version of this figure.
4. Operator standardization and calibration
To minimize operator-related variability, all restorative procedures were performed by three prosthodontists who followed standardized clinical protocols. Before patient enrollment, all operators completed a 2-week calibration program using typodont models. A detailed operative manual was provided, and weekly review sessions were conducted to reinforce adherence to the standardized procedures. Intraoperative checklists were used to ensure consistency during critical procedural steps. All completed restorations were subsequently reviewed by a senior prosthodontist for quality assurance. In addition, quarterly inter-operator calibration sessions were conducted to review representative cases and standardize clinical decision-making. These measures were implemented to ensure procedural consistency throughout the study.
5. Clinical evaluation
Clinical outcomes were evaluated at 3 months and 2 years after restoration by two dentists with more than 15 years of clinical experience who were not involved in the treatment procedures. Both examiners were blinded to group allocation. Before the formal evaluations, the examiners completed three calibration sessions using 20 representative cases to standardize the interpretation of all evaluation indices. Inter-examiner agreement was excellent, with Cohen's κ values ranging from 0.82 to 0.91 and intraclass correlation coefficients (ICC) ranging from 0.88 to 0.94.
6. Outcome measures
- Restoration integrity
Restoration integrity was classified as follows: Grade A, the restoration was intact without defects; Grade B, the restoration exhibited minor damage that did not affect function; and Grade C, the restoration was fractured or detached. - Tooth integrity
Tooth integrity was classified as follows: Grade A, the tooth hard tissue was intact without defects; Grade B, minor defects or cracks were present in the tooth hard tissue; and Grade C, significant hard-tissue defects were present that could potentially affect tooth function. - Marginal adaptation
Marginal adaptation was classified as follows: Grade A, no detectable gap was present between the tooth and the restoration margin, and the periodontal probe did not catch; Grade B, a slight marginal gap was present, with slight probe catch; and Grade C, a significant marginal gap allowed insertion of the periodontal probe. - Interproximal contacts
Interproximal contacts were classified as follows: Grade A, dental floss passed through the contact area with resistance; Grade B, dental floss passed with slight resistance and mild food impaction was present; and Grade C, dental floss passed without resistance, accompanied by severe food impaction. - Periodontal pocket depth
Periodontal pocket depth was measured using a periodontal probe that was cleaned and disinfected before each examination. The probe was held using a modified pen grasp, and a standardized probing force of 20–25 g was applied. The probe was inserted to the base of the periodontal pocket, and the probing depth was recorded in millimeters. Greater probing depths indicated poorer periodontal outcomes. - Gingival index
The Gingival Index was used to evaluate the severity of gingival inflammation according to gingival color, consistency, and bleeding tendency. Examinations were performed under standardized conditions using a blunt-ended periodontal probe at six sites per tooth (mesiobuccal, midbuccal, distobuccal, mesiolingual, midlingual, and distolingual). The highest score recorded for each tooth was used for analysis. Scores ranged from 0 to 3, where 0 indicated normal gingiva with no bleeding on probing; 1 indicated mild erythema and edema without bleeding on probing; 2 indicated moderate redness, edema, a shiny appearance, and bleeding on probing; and 3 indicated severe redness, swelling, spontaneous bleeding, or ulceration. Higher scores indicated poorer periodontal health. - Plaque index
The Plaque Index was used to evaluate the thickness and amount of plaque accumulation at the gingival margin of the index teeth. Examinations were performed by visual inspection combined with gentle probing of the tooth surface. Each tooth was scored from 0 to 3 according to the following criteria: 0, no plaque at the gingival margin; 1, a thin plaque film adherent to the gingival margin that was not visible to the naked eye but detectable by probing; 2, moderate plaque accumulation visible at the gingival margin or on adjacent tooth surfaces; and 3, abundant soft deposits filling the gingival sulcus and covering the gingival margin and adjacent tooth surfaces. Higher scores indicated poorer oral hygiene and greater plaque accumulation. - Chewing function
Chewing function was assessed by measuring bite force and masticatory efficiency. Bite force was measured using a bite force tester. Masticatory efficiency was determined using the sieving and weighing method and expressed as the percentage of food comminuted within a standardized chewing period. Participants were instructed to chew 5 g of peanuts for 20 s before expectorating all chewed material into a collection container. The oral cavity was then rinsed to recover any remaining food particles. The collected material was passed through a 2.0 mm sieve, and the residue retained on the sieve was dried and weighed. Masticatory efficiency was calculated as:
(total weight - residual weight)/total weight × 100%. - Oral health-related quality of life
Oral health-related quality of life was evaluated using the Chinese version of the Oral Health Impact Profile-14 (OHIP-14), a validated instrument widely used to assess the psychosocial impact of oral conditions on daily life. The questionnaire comprises 14 items across seven domains: functional limitation, physical pain, psychological discomfort, physical disability, psychological disability, social disability, and handicap. Each item is scored on a 5-point Likert scale ranging from 0 ("never") to 4 ("very often"), yielding a total score of 0–56, with higher scores indicating poorer oral health-related quality of life. The Chinese version of the OHIP-14 has demonstrated good reliability and validity (Cronbach's α = 0.93)15, supporting its use for evaluating oral health outcomes in Chinese populations.
7. Statistical analysis
Statistical analyses were performed using SPSS software. Normally distributed continuous variables were expressed as mean ± standard deviation and compared using the independent-samples t-test. Non-normally distributed continuous variables were expressed as median (Q1, Q3) [M (Q1, Q3)] and compared using the Mann-Whitney U test. Categorical variables were expressed as numbers (percentages) and compared using the χ2 test, continuity-corrected χ2 test, or Fisher's exact test, as appropriate. Ordinal variables were compared using the Mann-Whitney U test. All statistical tests were two-sided, and P < 0.05 was considered statistically significant.
Access restricted. Please log in or start a trial to view this content.
Results
A total of 100 eligible posterior teeth were included, with 50 teeth in the fiber post-and-core crown group and 50 in the onlay restoration group. All patients completed clinical follow-ups at 3 months and 2 years postoperatively.
Baseline characteristics
No statistically significant differences were observed in baseline demographic or clinical characteristics between the two groups (all P > 0.05; gender, P = 0.841; age, P = 0.462; education level, P = 0.687; body ma...
Access restricted. Please log in or start a trial to view this content.
Discussion
Dental caries is the leading cause of tooth defects, particularly in posterior teeth, and affects not only tooth morphology but also masticatory function, dentofacial esthetics, and patients' quality of life16. With advances in oral healthcare and increasing public awareness, both patients and clinicians have placed greater emphasis on preserving natural teeth whenever possible. Complete root canal treatment is essential for retaining teeth affected by pulpal and periapical disease because it ...
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors declare that they have no competing financial interests.
Acknowledgements
The authors thank all participants for their involvement in this study. This research received no external funding.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 35% phosphoric acid etchant | Bisco, USA | E-59110P | Etching of enamel/dentin before bonding |
| 9.6% hydrofluoric acid | Pulpdent, USA | PEG-3 | Etching of ceramic restoration surface |
| Addition silicone impression material kit | President Dental, Switzerland | PRD.01.PGUMP01 | Heavy-body and light-body for final impression |
| Alginate impression material | Kerr, USA | 27477DX-2 | Preliminary impression for study model |
| Bausch occlusion paper | Bausch, Germany | BK-288-3 | Occlusal adjustment and contact marking |
| Bite force tester | West China Medical, China | YHL001 | Measurement of maximum bite force |
| Core resin (for post-and-core build-up) | 3M, USA | 56864-4 | Resin core build-up over fiber post |
| Dental floss | Johnson & Johnson | 1993.0107.205 | Checking interproximal contacts |
| Dual-cure resin cement (part of Multilink N kit) | Ivoclar Vivadent, Liechtenstein | V30339-8 | Bonding of crowns and onlays |
| Fiber post drill (for post space preparation) | 3M ESPE (RelyX), USA | 56864-4 | Part of the core resin kit; used for post space drilling |
| Flowable resin | Dentsply Sirona (SDR), USA | 61C130-5 | Cavity sealing and base placement |
| Full-zirconia crown (prefabricated) | Vita Zahnfabrik, Germany | 20182170377 | Crown restoration for post-and-core group |
| Gingival retraction cord | Pascal International (KnitTrax), USA | 07-585-7 | Gingival displacement for impression |
| Glass fiber post | 3M (RelyX Fiber Post), USA | 306831603-8 | Post-and-core restoration |
| Hard plaster / Super-hard plaster | Heraeus Kulzer, Germany | OCTA-SUPERROCK | Pouring of study models and working casts |
| Hiluster Plus polishing cup | Kerr Rotary, Switzerland | 278925 | Final polishing of restorations |
| Iodine glycerol | Xinlong, China | 4011244-10 | Gingival soothing after retraction and bonding |
| IPS e.max press onlay (lithium disilicate) | Ivoclar Vivadent, Liechtenstein | U01738 | Onlay restoration fabricated in lab |
| Light-curing lamp | 3M, USA | 76973 | Light curing of adhesive resins (wavelength: 440-480 nm) |
| Multilink N bonding kit | Ivoclar Vivadent, Liechtenstein | V30339-8 | Self-adhesive resin cement for definitive bonding |
| Occlubrush polishing brush | Kerr, USA | 2520 | Polishing of restorations and margins |
| Occlusal registration silicone | President Dental, Switzerland | PRD.01.PGUML01-1 | Bite registration and occlusal record transfer |
| Periodontal probe | Hu-Friedy, USA | PCPUNC15 | Measurement of periodontal pocket depth |
| Saline (0.9% sodium chloride) | Baxter, USA | 2F7124 | Irrigation and rinsing of root canal and operative field |
| Self-etch adhesive | 3M, USA | 41925 | Bonding agent for post and crown |
| Silane coupling agent (Monobond N) | Ivoclar Vivadent, Liechtenstein | Monobond N | Surface pretreatment of ceramic for adhesive bonding |
| Sodium bicarbonate | Sigma-Aldrich, USA | V900182 | Neutralization of hydrofluoric acid after etching |
| SPSS software | IBM, USA | Version 26.0 ; RRID: SCR_002865 | Statistical analysis of clinical data |
| Ultrasonic device | E.M.S. Electro Medical Systems S.A. (Switzerland) | PIEZON® 150 | Cleaning of instruments and ultrasonic activation of root canal irrigants |
| Vita 3D-master shade guide | Vita, Germany | B360 | Shade matching before restoration fabrication |
References
- Gulabivala K, Ng YL. Factors that affect the outcomes of root canal treatment and retreatment-a reframing of the principles. Int Endod J. 2023;56 Suppl 2:82-115.
- Brochado Martins JF, et al. Outcome of selective root canal retreatment-a retrospective study. Int Endod J. 2023;56(3):345-55.
- Plotino G, et al. Present status and future directions: Surgical extrusion, intentional replantation and tooth autotransplantation. Int Endod J. 2022;55(S3):827-42.
- Versiani M, Martins J, Ordinola-Zapata R. Anatomical complexities affecting root canal preparation: A narrative review. Aust Dent J. 2023;68(S1):S5-S23.
- Chen S, et al. Biomechanical perspectives on dentine cracks and fractures: Implications in their clinical management. J Dent. 2023;130:104424.
- Tian X, et al. CBCT imaging and root canal treatment for taurodontism in mandibular second molar - a case report and literature review. J Radiol Case Rep. 2023;17(11):1-7.
- Martins MD, et al. Is a fiber post better than a metal post for the restoration of endodontically treated teeth? A systematic review and meta-analysis. J Dent. 2021;112:103750.
- Jurema ALB, et al. Effect of intraradicular fiber post on the fracture resistance of endodontically treated and restored anterior teeth: A systematic review and meta-analysis. J Prosthet Dent. 2022;128(1):13-24.
- Guo X, Chen Z, Gao M, Ma X. Synchronous fabrication of custom one-piece glass fiber post-and-core and zirconia crown by a fully digital workflow. Oper Dent. 2023;48(2):130-6.
- Naik VB, Jain AK, Rao RD, Naik BD. Comparative evaluation of clinical performance of ceramic and resin inlays, onlays, and overlays: A systematic review and meta analysis. J Conserv Dent. 2022;25(4):347-55.
- Dioguardi M, et al. The influence of indirect bonded restorations on clinical prognosis of endodontically treated teeth: A systematic review and meta-analysis. Dent Mater. 2022;38(8):e203-e219.
- Kassis C, et al. Effect of inlays, onlays and endocrown cavity design preparation on fracture resistance and fracture mode of endodontically treated teeth: An in vitro study. J Prosthodont. 2021;30(7):625-31.
- Althaqafi KA. Performance of direct and indirect onlay restorations for structurally compromised teeth. J Prosthet Dent. 2025;133(6):1513-19.
- Yurdagüven GY, Çiftçioğlu E, Kazokoğlu FŞ, Kayahan MB. 5-year clinical performance of ceramic onlay and overlay restorations luted with light-cured composite resin. J Dent. 2024;149:105258.
- Wong MC, Lo EC, Mcmillan AS. Validation of a Chinese version of the Oral Health Impact Profile (OHIP). Community Dent Oral Epidemiol. 2002;30(6):423-30.
- Sabharwal A, Stellrecht E, Scannapieco FA. Associations between dental caries and systemic diseases: A scoping review. BMC Oral Health. 2021;21(1):472.
- Corbella S, Walter C, Tsesis I. Effectiveness of root resection techniques compared with root canal retreatment or apical surgery for the treatment of apical periodontitis and tooth survival: A systematic review. Int Endod J. 2023;56(S3):487-98.
- Schmalz G, Hickel R, Price RB, Platt JA. Bioactivity of dental restorative materials: FDI policy statement. Int Dent J. 2023;73(1):21-7.
- Schlichting LH, et al. Ultrathin CAD-CAM glass-ceramic and composite resin occlusal veneers for the treatment of severe dental erosion: An up to 3-year randomized clinical trial. J Prosthet Dent. 2022;128(2):158.e1-158.e12.
- Sulaiman TA, Suliman AA, Abdulmajeed AA, Zhang Y. Zirconia restoration types, properties, tooth preparation design, and bonding. A narrative review. J Esthet Restor Dent. 2024;36(1):78-84.
- Malament KA, et al. 10.9-year survival of pressed acid etched monolithic e.max lithium disilicate glass-ceramic partial coverage restorations: Performance and outcomes as a function of tooth position, age, sex, and the type of partial coverage restoration (inlay or onlay). J Prosthet Dent. 2021;126(4):523-32.
- Weimann D, Fleck C, Razi H. Marginal integrity in minimally invasive molar resin composite restorations: Impact of polymerization shrinkage. J Mech Behav Biomed Mater. 2024;155:106554.
- Tsukahara R, et al. Fracture strength of flared root canals reinforced using different post and core materials. J Prosthodont. 2023;32(7):639-45.
- Fráter M, et al. Fatigue failure of anterior teeth without ferrule restored with individualized fiber-reinforced post-core foundations. J Mech Behav Biomed Mater. 2021;118:104440.
- Yazdi HK, Sohrabi N, Mostofi SN. Effect of direct composite and indirect ceramic onlay restorations on fracture resistance of endodontically treated maxillary premolars. Front Dent. 2020;17:1-8.
- Lin J, Lin Z, Zheng Z. Effect of different restorative crown design and materials on stress distribution in endodontically treated molars: A finite element analysis study. BMC Oral Health. 2020;20(1):226.
- Tavares MJ, et al. Effect of different design and surface treatment on the load-to-failure of ceramic repaired with composite. Acta Odontol Latinoam. 2024;37(1):88-95.
- Krug R, et al. Long-term performance of ceramic in/-onlays vs. cast gold partial crowns – a retrospective clinical study. Clin Oral Investig. 2024;28(5):298.
- Chirca O, et al. Adhesive-ceramic interface behavior in dental restorations. FEM study and SEM investigation. Materials (Basel). 2021;14(17):5048.
- Kanamori Y, et al. Influence of resin-coating techniques on the marginal adaptation and the bond strengths of CAD/CAM-fabricated hybrid ceramic inlays. Dent Mater J. 2024;43(3):407-14.
- Griffis E, et al. Tooth-cusp preservation with lithium disilicate onlay restorations: A fatigue resistance study. J Esthet Restor Dent. 2022;34(3):512-18.
- Vargas-Corral FG, et al. Clinical comparison of marginal fit of ceramic inlays between digital and conventional impressions. J Adv Prosthodont. 2024;16(1):57-65.
- Yli-Urpo T, Lassila L, Vallittu P, Närhi T. Co-influence of restoration bonding and inlay cavity design on fracture load of restored tooth. Eur J Prosthodont Restor Dent. 2023;32.
- Wang B, et al. Onlays/partial crowns versus full crowns in restoring posterior teeth: A systematic review and meta-analysis. Head Face Med. 2022;18(1):36.
- Al-Meshal SK, et al. Remaining tooth structure and prognosis of restored endodontically treated teeth: A systematic review. Cureus. 2025;17(10):e94406.
- Chen S, Lu M, Zhu Z, Chen W. Clinical performance of two onlay designs for molars after root canal treatment. J Oral Sci. 2023;65(3):171-5.
- Golrezaei M, Mahgoli HA, Yaghoobi N, Niakan S. The effect of modified framework design on the fracture resistance of IPS e.max Press crown after thermocycling and cyclic loading. J Contemp Dent Pract. 2024;25(1):79-84.
- Stevens CD, Couso-Queiruga E, Blen D, Renné WG. Differences in Volumetric Tooth Loss for Monolithic Ceramic Crowns, Occlusal Overlays, and Partial-Coverage Onlays. Int J Prosthodont. 2024;37(2):181-9.
Access restricted. Please log in or start a trial to view this content.