This study evaluates ARHGAP22 expression in clear cell renal cell carcinoma and its associations with prognosis, clinicopathological features, the tumor immune microenvironment, and computationally predicted drug sensitivity.
Research Article
ARHGAP22 as a Potential Prognostic Biomarker in Clear Cell Renal Cell Carcinoma: Insights into Tumor Immunity and Co-Expression Networks
* These authors contributed equally
In This Article
Summary
Abstract
Clear cell renal cell carcinoma (ccRCC) is the most common subtype of kidney cancer and is characterized by substantial clinical heterogeneity, highlighting the need for reliable prognostic biomarkers. This study evaluated the expression pattern, prognostic relevance, and immune-related associations of ARHGAP22 in ccRCC using transcriptomic and clinical data from The Cancer Genome Atlas Kidney Renal Clear Cell Carcinoma (TCGA-KIRC) cohort, together with external validation data and protein-expression information from the Human Protein Atlas (HPA). ARHGAP22 expression was compared between tumor and adjacent normal tissues, and its associations with overall survival, clinicopathological characteristics, tumor microenvironment scores, and estimated immune-cell fractions were assessed. Co-expression and functional-enrichment analyses were also performed to characterize potential biological associations. ARHGAP22 was significantly upregulated in ccRCC tissues at the transcriptomic level, with corresponding differences observed in immunohistochemical images. High ARHGAP22 expression was associated with shorter overall survival, advanced clinicopathological features, and higher ImmuneScore, StromalScore, and ESTIMATEScore values. CIBERSORT-based analysis showed that the high-expression group had higher estimated fractions of M2 macrophages and regulatory T cells and lower estimated fractions of naïve B cells, resting mast cells, and activated dendritic cells after false discovery rate correction. Functional-enrichment analyses linked ARHGAP22-associated genes to immune-related processes, cell migration, and chemokine- and cytokine-mediated signaling pathways. These findings suggest that ARHGAP22 may represent a potential prognostic and immune-related biomarker in ccRCC, although further independent clinical and experimental validation is required.
Introduction
Clear cell renal cell carcinoma (ccRCC) is the most common histological subtype of renal cell carcinoma, accounting for approximately 70%–80% of cases and contributing substantially to renal cancer–related mortality1˒2. The incidence of renal cell carcinoma has increased overall in recent years, with marked epidemiological variation across regions. Established risk factors include smoking, obesity, hypertension, and chronic kidney disease3˒4. Clear cell renal cell carcinoma is characterized by pronounced aggressiveness and molecular heterogeneity. A subset of patients presents with metastatic disease at diagnosis, and postoperative recurrence and progression remain common2˒5. At the molecular level, von Hippel–Lindau (VHL) inactivation and sustained activation of hypoxia-inducible factor (HIF) signaling are recognized as key events in ccRCC pathogenesis and are accompanied by widespread genomic and epigenetic alterations6˒7. Although targeted therapies and immunotherapies have improved outcomes in advanced disease, treatment responses remain highly heterogeneous, underscoring the need for reliable prognostic and immune-related biomarkers8,9,10.
Rho guanosine triphosphatases (Rho GTPases) are molecular switches that regulate cytoskeletal remodeling, cell polarity, adhesion, migration, and invasion and have multifaceted roles in tumorigenesis and cancer progression11˒12. In addition to regulating tumor-cell proliferation, apoptosis, and motility, Rho GTPase signaling contributes to angiogenesis, inflammatory responses, and remodeling of the tumor immune microenvironment13,14,15. The biological significance of Rho GTPase signaling in ccRCC has received increasing attention. Rac signaling has been reported to promote ccRCC growth and angiogenic switching, whereas VHL/HIF-driven ccRCC may depend on the Rho GTPase/Rho-associated coiled-coil-containing protein kinase (ROCK) pathway16˒17. Rho GTPase–related gene signatures have also been associated with poor prognosis, immunosuppressive status, and differential responses to immunotherapy in ccRCC, suggesting that this pathway may represent an important molecular link between tumor progression and tumor immunity18˒19.
ARHGAP22 belongs to the Rho GTPase-activating protein (RhoGAP) family and the FilGAP-related subfamily and primarily functions as a Rac-specific RhoGAP involved in antagonistic regulation of the RhoA–Rac1 axis20˒21. The protein contains a pleckstrin homology (PH) domain and a RhoGAP domain and can regulate Rac activity through endosomal localization and transport to the plasma membrane, thereby influencing lamellipodia formation, cell spreading, and migration20˒22˒23. Previous studies have associated ARHGAP22 with cytoskeletal dynamics, tumor-cell motility, the tumor immune microenvironment, and potential biomarker roles in several malignancies20,23,24,25. However, the expression pattern, prognostic significance, immune associations, and potential therapeutic relevance of ARHGAP22 in ccRCC remain insufficiently characterized. The present study therefore evaluated whether ARHGAP22 expression is associated with clinicopathological progression, patient prognosis, immune infiltration, computationally predicted drug sensitivity, and co-expression networks in ccRCC, with the aim of assessing its potential value as a prognostic and immune-related biomarker.
Protocol
This study used publicly available, de-identified data from TCGA, HPA, and other open-access databases and did not involve new human participant recruitment, animal experiments, or identifiable private information. Therefore, additional institutional ethics approval and informed consent were not required. Detailed information on the tools used in the protocol is provided in the Table of Materials.
1. Public datasets and bioinformatics analysis
Publicly available datasets were used, and no direct research involving human participants or animals was conducted. Transcriptomic and clinical data were obtained from The Cancer Genome Atlas Kidney Renal Clear Cell Carcinoma (TCGA-KIRC) project, and protein-expression data were retrieved from the Human Protein Atlas. This computational approach enabled efficient screening of large-scale transcriptomic and clinical datasets, supported the preliminary identification of candidate biomarkers, and provided a basis for subsequent experimental validation. All computational analyses were performed using statistical software.
2. Data acquisition and sample selection
The Genomic Data Commons Data Portal was accessed, and the TCGA-KIRC project was selected. Transcriptome-profiling data and corresponding clinical information for clear cell renal cell carcinoma (ccRCC) were downloaded. Transcripts per million (TPM)-normalized messenger RNA expression data were used for subsequent transcriptomic analyses. ARHGAP22 expression values were extracted from the TCGA-KIRC transcriptomic matrix and matched with the corresponding clinical records using TCGA sample barcodes. Primary tumor tissues and adjacent normal kidney tissues with available ARHGAP22 expression data and clinical annotations were included. Samples with missing ARHGAP22 expression values, incomplete key clinical or survival information, duplicated records, or survival times of less than 30 days were excluded. After filtering, 533 tumor samples and 72 adjacent normal tissue samples were retained for downstream analyses.
3. Pan-cancer expression analysis
Pan-cancer expression analysis of ARHGAP22 was performed using the Gene_DE module of TIMER2.0 (http://timer.cistrome.org/; accessed April 12, 2026). TCGA RNA-sequencing data were used to compare ARHGAP22 expression between tumor tissues and corresponding normal tissues across multiple cancer types. Expression values were presented as log2(TPM), and differential expression was evaluated using the Wilcoxon rank-sum test implemented in TIMER2.0. A two-sided P value of less than 0.05 was considered statistically significant.
4. External GEO validation
External validation was performed using the Gene Expression Omnibus dataset GSE167573 through the BEST online platform (https://rookieutopia.hiplot.com.cn/app_direct/BEST/; accessed July 9, 2026). ARHGAP22 expression in ccRCC and normal kidney tissues was compared using the normalized expression data provided by the platform and assessed using an unpaired Student’s t-test. For survival analysis, patients were divided into high- and low-expression groups using the platform’s optimal cutoff method, and overall survival was evaluated using Kaplan–Meier analysis with the log-rank test. A two-sided P value of less than 0.05 was considered statistically significant.
5. ARHGAP22 expression analysis
TPM-normalized ARHGAP22 messenger RNA expression data were extracted from the TCGA-KIRC cohort and transformed as log2(TPM + 1) before statistical analysis. Differential ARHGAP22 expression between primary tumor tissues and adjacent normal kidney tissues was evaluated. The Wilcoxon rank-sum test was used for unpaired comparisons between tumor and normal tissues. For paired analysis, matched tumor-normal pairs were identified using TCGA patient barcodes, and the Wilcoxon signed-rank test was applied to compare ARHGAP22 expression between adjacent normal tissues and the corresponding tumor tissues. A two-sided P value of less than 0.05 was considered statistically significant.
6. Survival and receiver operating characteristic analysis
Survival and time-dependent receiver operating characteristic (ROC) analyses were performed using TCGA-KIRC tumor samples with available clinical follow-up data. Overall survival time was converted from days to years. Patients were divided into high- and low-ARHGAP22 expression groups using the median ARHGAP22 expression value, and the same cutoff was applied consistently across all analyses involving expression-based grouping. Kaplan–Meier curves were generated using the survival package, and the survminer package. Differences between groups were assessed using the log-rank test. Cox proportional hazards regression was used to estimate hazard ratios and 95% confidence intervals. Time-dependent ROC curves were generated using the timeROC package. Areas under the curve at 1, 3, and 5 years were calculated using the Aalen weighting method. A two-sided P value of less than 0.05 was considered statistically significant.
7. Clinicopathological association analysis
The association between ARHGAP22 expression and clinicopathological characteristics was analyzed using TCGA-KIRC tumor samples. Normal samples were excluded. Age was categorized as 65 years or younger and older than 65 years. Samples with unknown or missing annotations were excluded from the corresponding analysis. The Wilcoxon rank-sum test was used for comparisons between two groups, and the Kruskal–Wallis test was used for comparisons involving three or more groups. Violin plots were generated using the ggpubr package ; ggplot2, and scales. For heatmap visualization, patients were classified into high- and low-ARHGAP22 expression groups using the median cutoff. Associations between expression groups and clinicopathological variables were assessed using chi-square tests. Heatmaps were generated using ComplexHeatmap, after preprocessing with limma. A two-sided P value of less than 0.05 was considered statistically significant.
8. Nomogram construction
A prognostic nomogram was constructed by integrating ARHGAP22 expression with available clinicopathological characteristics in a Cox proportional hazards regression model. The model was used to estimate 1-, 3-, and 5-year overall survival in the TCGA-KIRC cohort. Individual patient risk scores were calculated using the fitted Cox model. Calibration curves for 1-, 3-, and 5-year overall survival were generated using the Kaplan–Meier method with 1,000 bootstrap resampling iterations. Agreement between nomogram-predicted survival probabilities and observed survival outcomes was evaluated. Cox regression was performed using the survival package. Nomogram visualization and calibration analyses were conducted using regplot and rms. A two-sided P value of less than 0.05 was considered statistically significant.
9. Co-expression analysis
Transcriptomic data from TCGA-KIRC tumor samples were used to evaluate co-expression relationships between ARHGAP22 and all other genes by Pearson correlation analysis. Genes with an absolute Pearson correlation coefficient greater than 0.6 and a P value of less than 0.001 were defined as significantly co-expressed genes. Significantly co-expressed genes were ranked according to the absolute value of the correlation coefficient. The highest-ranking genes were selected to construct a correlation matrix, and a chord diagram was generated to visualize the ARHGAP22-associated co-expression network.
10. Differentially expressed gene and functional-enrichment analyses
Differential expression analysis between the high- and low-ARHGAP22 expression groups was performed using the Wilcoxon rank-sum test with false discovery rate (FDR) correction. Genes with an absolute log2 fold change greater than 1 and an FDR of less than 0.05 were defined as significantly differentially expressed genes. The results were visualized using a volcano plot and heatmap. Gene Ontology and Kyoto Encyclopedia of Genes and Genomes enrichment analyses were performed using clusterProfiler. Gene symbols were converted to Entrez identifiers using org.Hs.eg.db. Gene Ontology terms and Kyoto Encyclopedia of Genes and Genomes pathways with both a nominal P value of less than 0.05 and an FDR-adjusted P value of less than 0.05 were considered significantly enriched. Gene Set Enrichment Analysis was performed using Kyoto Encyclopedia of Genes and Genomes gene sets from the Molecular Signatures Database file c2.cp.kegg.v7.4.symbols.gmt. Genes were ranked by log2 fold change, and gene sets with a nominal P-value < 0.05 were considered significantly enriched.
11. Immune infiltration and immune-checkpoint analysis
Immune-infiltration and immune-checkpoint analyses were performed using TCGA-KIRC tumor samples. StromalScore, ImmuneScore, and ESTIMATEScore values were calculated using the estimate package. Immune-cell fractions were estimated using the CIBERSORT R script, with 1,000 permutations and quantile normalization. Samples with a CIBERSORT deconvolution P value of less than 0.05 were retained. Patients were divided into ARHGAP22-high and ARHGAP22-low groups according to the median ARHGAP22 expression level. Differences in ESTIMATE scores and immune-cell fractions between the two groups were assessed using the Wilcoxon rank-sum test. Correlations between ARHGAP22 expression and immune-checkpoint genes were evaluated using Pearson correlation analysis. P values from multiple immune-cell comparisons and immune-checkpoint correlation tests were adjusted using the Benjamini–Hochberg FDR method, and an FDR of less than 0.05 was considered statistically significant. FDR-significant immune-checkpoint genes were visualized using correlation heatmaps generated with corrplot. Data preprocessing and visualization were performed primarily using limma; ggpubr; and corrplot.
12. Drug-sensitivity prediction
TCGA-KIRC tumor transcriptomic data were used after normal tissue samples had been excluded. Computationally predicted half-maximal inhibitory concentration values were calculated using the oncoPredict package and the Genomics of Drug Sensitivity in Cancer 2-based reference dataset. Patients were divided into ARHGAP22-high and ARHGAP22-low groups using the median ARHGAP22 expression value. Predicted half-maximal inhibitory concentration values were compared between groups using the Wilcoxon rank-sum test. P values from multiple drug comparisons were adjusted using the Benjamini–Hochberg method, and an FDR of less than 0.05 was considered statistically significant. The results were interpreted as computationally predicted drug-sensitivity estimates rather than experimentally validated or clinically observed drug responses.
13. Human protein atlas validation
The Human Protein Atlas database was accessed, and ARHGAP22 was searched. The Tissue section was reviewed to assess ARHGAP22 protein expression in normal kidney tissue. The Pathology section was opened, clear cell renal cell carcinoma was selected, and ARHGAP22 protein expression in tumor tissue was reviewed. Representative immunohistochemical images of normal kidney tissue and ccRCC tissue were retrieved and selected for inclusion in the manuscript to compare ARHGAP22 protein expression between normal and tumor tissues.
Results
Pan-cancer expression profiling of ARHGAP22
Pan-cancer transcriptional profiling showed marked heterogeneity in ARHGAP22 expression across tumor types and corresponding normal tissues (Figure 1). An overall trend toward increased ARHGAP22 expression was observed in several solid tumors. ARHGAP22 expression was significantly higher in tumor tissues than in corresponding normal tissues in breast invasive carcinoma, cholangiocarcinoma, head and neck squamous cell carcinoma, kidney chromophobe, kidney renal clear cell carcinoma, kidney renal papillary cell carcinoma, and liver hepatocellular carcinoma. These findings indicated that ARHGAP22 was differentially expressed across multiple cancer types and may have relevance as a tumor-associated biomarker.
Expression pattern and prognostic value of ARHGAP22 in clear cell renal cell carcinoma
The expression pattern and clinical relevance of ARHGAP22 in clear cell renal cell carcinoma (ccRCC) were evaluated using transcriptomic data, survival analyses, an independent validation dataset, and immunohistochemical images. ARHGAP22 expression was significantly higher in ccRCC tissues than in normal kidney tissues in both unpaired and paired The Cancer Genome Atlas Kidney Renal Clear Cell Carcinoma (TCGA-KIRC) samples (Figure 1B, C). Kaplan–Meier analysis showed that patients with high ARHGAP22 expression had significantly shorter overall survival (OS) than patients with low expression (P = 0.013; Figure 1D). Time-dependent receiver operating characteristic analysis yielded areas under the curve of 0.641, 0.637, and 0.641 for 1-, 3-, and 5-year OS, respectively, indicating modest prognostic performance (Figure 1E). The findings were further evaluated using the independent GSE167573 dataset. ARHGAP22 expression was significantly higher in ccRCC tissues than in normal kidney tissues (Figure 1F), and high ARHGAP22 expression was associated with shorter OS (Figure 1G). Immunohistochemical images obtained from the Human Protein Atlas showed stronger ARHGAP22 protein staining in ccRCC tissue than in normal kidney tissue, providing additional protein-level support for the transcriptomic findings (Figure 1H, I).
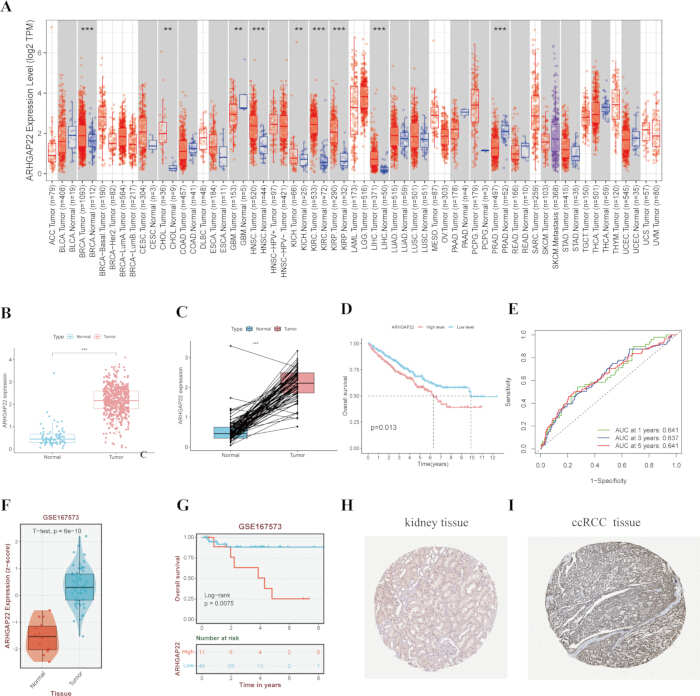
Figure 1: Pan-cancer expression, expression pattern, and prognostic value of ARHGAP22 in clear cell renal cell carcinoma. (A) Pan-cancer expression profile of ARHGAP22 across multiple tumor types and corresponding normal tissues. (B) ARHGAP22 expression in unpaired clear cell renal cell carcinoma (ccRCC) and normal kidney tissues. (C) ARHGAP22 expression in matched ccRCC and adjacent normal kidney tissues. (D) Kaplan–Meier overall survival curves comparing patients with high and low ARHGAP22 expression. (E) Time-dependent receiver operating characteristic curves evaluating the prognostic performance of ARHGAP22 for 1-, 3-, and 5-year overall survival. (F) Validation of ARHGAP22 expression in the GSE167573 dataset. (G) Kaplan–Meier overall survival analysis in the GSE167573 dataset. (H, I) Immunohistochemical images from the Human Protein Atlas showing ARHGAP22 protein expression in normal kidney tissue (H) and ccRCC tissue (I). *P < 0.05; **P < 0.01; ***P < 0.001. Abbreviations: ccRCC, clear cell renal cell carcinoma; OS, overall survival; ROC, receiver operating characteristic; DEG, differentially expressed gene; GO, Gene Ontology; KEGG, Kyoto Encyclopedia of Genes and Genomes; GSEA, Gene Set Enrichment Analysis; FDR, false discovery rate; IC50, half-maximal inhibitory concentration. Please click here to view a larger version of this figure.
Association of ARHGAP22 with clinicopathological features
The association between ARHGAP22 expression and clinicopathological characteristics was evaluated to determine whether expression varied with disease severity. ARHGAP22 expression was significantly higher in patients with advanced T, M, and N classifications, including patients with metastatic disease (Figure 2A–C). Expression also increased with advancing histological grade and clinical stage (Figure 2D, E). Heatmap analysis further showed significant associations between high ARHGAP22 expression and higher histological grade, advanced clinical stage, and unfavorable tumor-node-metastasis classification (Figure 2F). These results indicated that elevated ARHGAP22 expression was associated with more aggressive clinicopathological features in ccRCC.
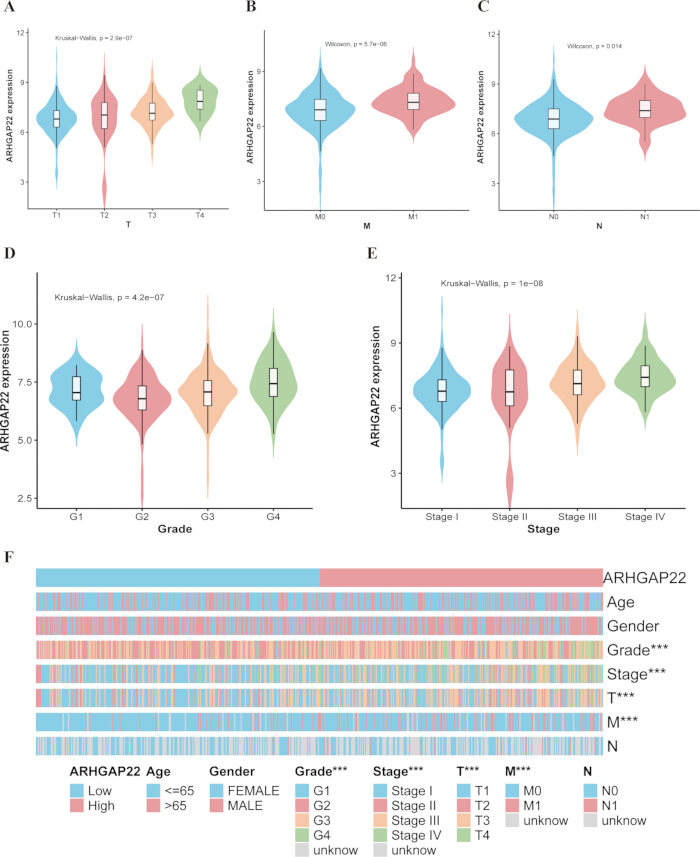
Figure 2: Association between ARHGAP22 expression and clinicopathological features in clear cell renal cell carcinoma. (A–C) ARHGAP22 expression according to T, M, and N classification, respectively. (D) ARHGAP22 expression according to histological grade. (E) ARHGAP22 expression according to clinical stage. (F) Heatmap showing associations between ARHGAP22 expression and clinicopathological characteristics. *P < 0.05; **P < 0.01; ***P < 0.001. Please click here to view a larger version of this figure.
Clinicopathological features and overall survival
Kaplan–Meier analysis showed significant differences in OS across clinicopathological subgroups (Figure 3). Patients with higher histological grades, G3–G4, had significantly shorter OS than patients with lower grades, G1–G2 (P < 0.0001; Figure 3A). Patients with stage III–IV disease also had significantly shorter OS than patients with stage I–II disease (P < 0.0001; Figure 3B). Overall survival differed significantly across T-classification subgroups, with advanced T classifications associated with less favorable outcomes (P < 0.0001; Figure 3C). Patients with lymph node metastasis (N1) or distant metastasis (M1) also had significantly shorter OS than those without lymph node or distant metastasis (both P < 0.0001; Figure 3D, E). These findings confirmed that histological grade, clinical stage, and tumor-node-metastasis classification were associated with survival in ccRCC.
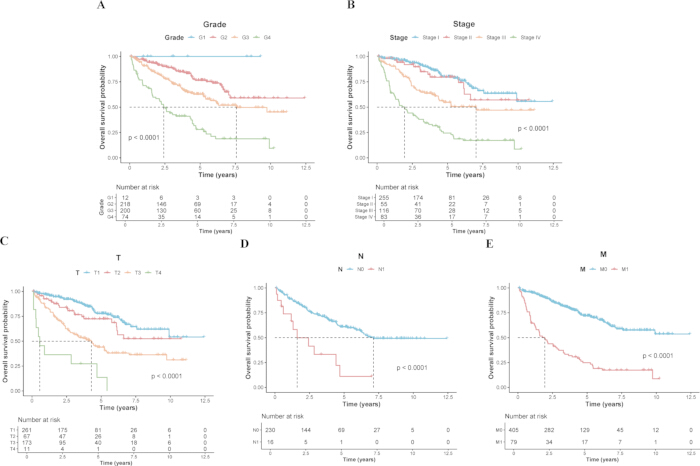
Figure 3: Overall survival according to clinicopathological features in clear cell renal cell carcinoma. (A–E) Kaplan–Meier overall survival curves according to histological grade, clinical stage, T classification, N classification, and M classification, respectively. Please click here to view a larger version of this figure.
Prognostic nomogram for clear cell renal cell carcinoma
A prognostic nomogram integrating ARHGAP22 expression with available clinicopathological characteristics was constructed to estimate 1-, 3-, and 5-year OS in patients with ccRCC (Figure 4A). Calibration analysis showed agreement between the nomogram-predicted and observed survival probabilities at all three time points. The calibration curves were positioned close to the ideal reference line, indicating satisfactory calibration performance (Figure 4B). The clinical model had a concordance index of 0.779 (95% confidence interval, 0.729–0.828), whereas addition of ARHGAP22 yielded a concordance index of 0.781 (95% confidence interval, 0.735–0.827), indicating minimal incremental prognostic improvement.
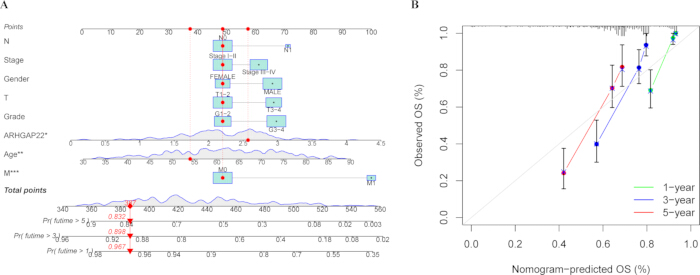
Figure 4: ARHGAP22-based prognostic nomogram and calibration analysis in clear cell renal cell carcinoma. (A) Nomogram for estimating 1-, 3-, and 5-year overall survival. (B) Calibration curves comparing nomogram-predicted and observed 1-, 3-, and 5-year overall survival. Please click here to view a larger version of this figure.
Molecular network analysis of ARHGAP22
Correlation analysis was performed to characterize the molecular network associated with ARHGAP22 expression. The correlation network showed associations between ARHGAP22 and multiple genes in ccRCC (Figure 5A). ARHGAP22 expression was significantly positively correlated with GMIP, TRPM2, CARD9, FMNL1, STAC3, and MYO9B. Significant negative correlations were observed with BSND, HEPACAM2, ATP6V1G3, TMEM38A, and FOXI1 (Figure 5B–L). These findings indicated that ARHGAP22 expression was associated with a complex co-expression network in ccRCC.
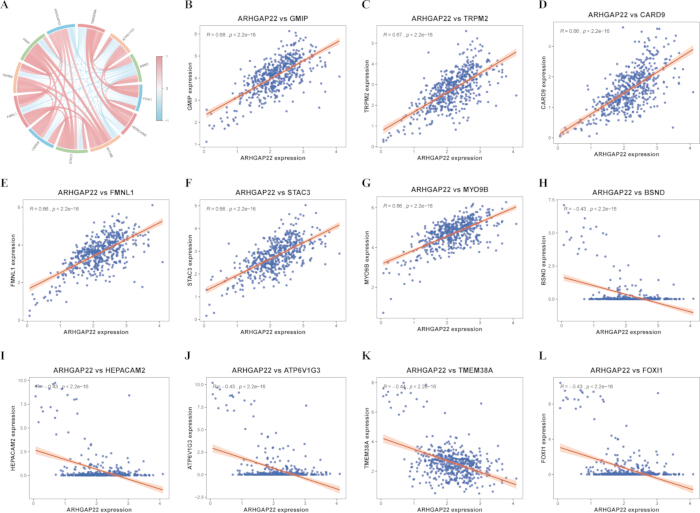
Figure 5: ARHGAP22-associated molecular features in clear cell renal cell carcinoma. (A) Correlation network showing associations between ARHGAP22 and related genes. (B–G) Positive correlations between ARHGAP22 and GMIP, TRPM2, CARD9, FMNL1, STAC3, and MYO9B, respectively. (H–L) Negative correlations between ARHGAP22 and BSND, HEPACAM2, ATP6V1G3, TMEM38A, and FOXI1, respectively. Please click here to view a larger version of this figure.
ARHGAP22-associated differentially expressed genes
Clear cell renal cell carcinoma samples were divided into high- and low-ARHGAP22 expression groups using the median expression value, and differential expression analysis was performed. A total of 334 genes were upregulated, and 38 genes were downregulated in the high-expression group (Figure 6A). Heatmap analysis revealed distinct expression patterns between the high- and low-ARHGAP22 groups, indicating that the identified differentially expressed genes separated the two groups (Figure 6B).
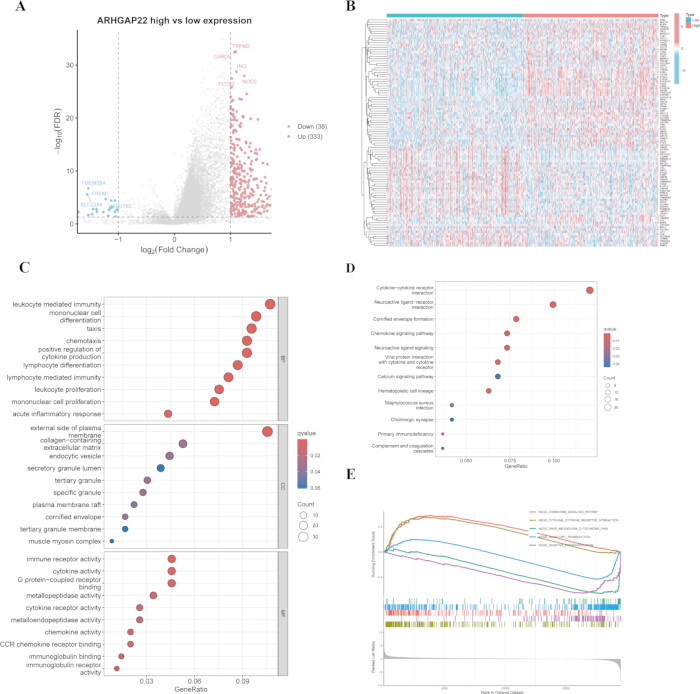
Figure 6: ARHGAP22-associated differentially expressed genes and functional enrichment. (A) Volcano plot of differentially expressed genes between the high- and low-ARHGAP22 expression groups. (B) Heatmap of differentially expressed genes. (C) Gene Ontology enrichment analysis. (D) Kyoto Encyclopedia of Genes and Genomes pathway enrichment analysis. (E) Gene Set Enrichment Analysis showing pathways enriched in the high-ARHGAP22 expression group. Please click here to view a larger version of this figure.
Functional enrichment of ARHGAP22-associated differentially expressed genes
Functional-enrichment analysis was performed to characterize the biological processes associated with the differentially expressed genes. Gene Ontology analysis showed enrichment in immune-related biological processes, including leukocyte-mediated immunity, chemotaxis, cytokine production, and lymphocyte differentiation and proliferation. At the cellular-component level, enrichment was observed in the extracellular matrix, secretory granules, and plasma membrane-associated structures. At the molecular function level, enrichment was observed for cytokine activity, chemokine receptor binding, and metallopeptidase-related activities (Figure 6C). Kyoto Encyclopedia of Genes and Genomes analysis showed significant enrichment in cytokine–cytokine receptor interaction, chemokine signaling, calcium signaling, and infection- and immunity-related pathways (Figure 6D). Gene Set Enrichment Analysis further identified multiple immune-related pathways enriched in the high-ARHGAP22 expression group (Figure 6E).
ARHGAP22 and the immune microenvironment in clear cell renal cell carcinoma
CIBERSORT-based analysis of estimated immune-cell fractions showed significant differences between the ARHGAP22-high and ARHGAP22-low groups (Figure 7A). After false discovery rate correction, the ARHGAP22-high group had higher estimated fractions of M2 macrophages and regulatory T cells and lower estimated fractions of naïve B cells, resting mast cells, and activated dendritic cells. Correlation analysis showed that ARHGAP22 expression was positively associated with M2 macrophages and regulatory T cells and negatively associated with naïve B cells, resting mast cells, and activated dendritic cells (Figure 7B). These CIBERSORT-derived estimates indicated that elevated ARHGAP22 expression was associated with an immunosuppressive profile in ccRCC.
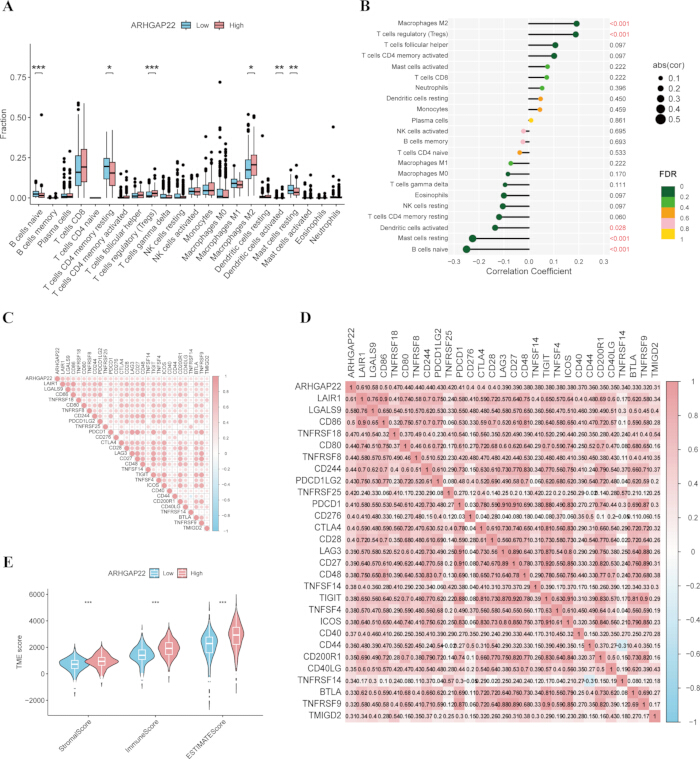
Figure 7: Association between ARHGAP22 expression and immune microenvironment features in clear cell renal cell carcinoma. (A) Differences in CIBERSORT-estimated immune-cell fractions between the ARHGAP22-high and ARHGAP22-low groups. (B) Correlations between ARHGAP22 expression and CIBERSORT-estimated immune-cell fractions. (C) Correlation heatmap showing associations between ARHGAP22 expression and immune-checkpoint genes. (D) Correlation matrix of ARHGAP22 and immune-checkpoint molecules. (E) Differences in StromalScore, ImmuneScore, and ESTIMATEScore between the ARHGAP22-high and ARHGAP22-low groups, calculated using the ESTIMATE algorithm. *P < 0.05; **P < 0.01; ***P < 0.001. Please click here to view a larger version of this figure.
ARHGAP22, immune checkpoints, and tumor microenvironment components
High ARHGAP22 expression was positively associated with several immune-checkpoint genes, including PDCD1LG2, CTLA4, LAG3, TIGIT, and ICOS (Figure 7C, D), suggesting a potential association with immune-evasion-related features. ESTIMATE analysis also showed that StromalScore, ImmuneScore, and ESTIMATEScore values were significantly higher in the ARHGAP22-high expression group (Figure 7E), reflecting increased stromal and immune components within the tumor microenvironment. These findings indicated that ARHGAP22 expression was associated with CIBERSORT-estimated immune-cell fractions, immune-checkpoint expression, and an immunosuppressive tumor microenvironment profile in ccRCC.
ARHGAP22 and computationally predicted targeted-drug sensitivity
The association between ARHGAP22 expression and computationally predicted targeted-drug sensitivity was evaluated by comparing predicted half-maximal inhibitory concentration values between the high- and low-expression groups (Figure 8A–I). The low-expression group had significantly lower predicted half-maximal inhibitory concentration values for axitinib, sorafenib, savolitinib, foretinib, cediranib, alpelisib, buparlisib, afuresertib, and ipatasertib. Lower predicted half-maximal inhibitory concentration values indicated greater computationally predicted sensitivity. These findings suggested an association between lower ARHGAP22 expression and greater predicted sensitivity to the evaluated targeted agents. The results represented computational predictions and did not constitute experimentally or clinically validated drug responses.
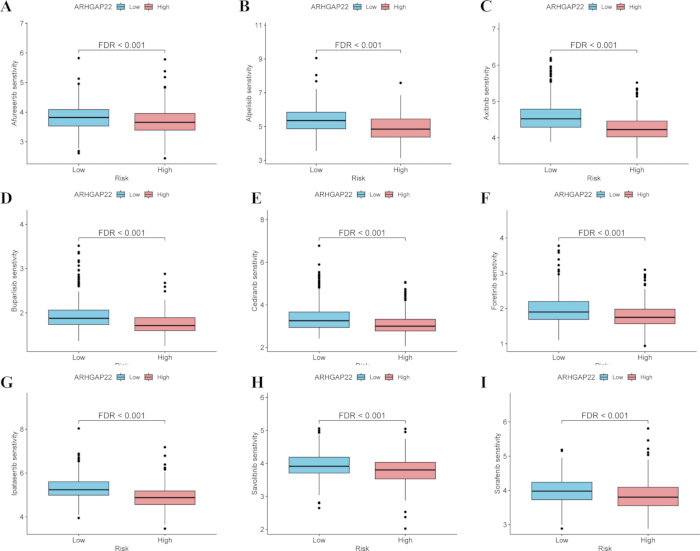
Figure 8: Association between ARHGAP22 expression and computationally predicted targeted-drug sensitivity in clear cell renal cell carcinoma. (A–I) Comparison of computationally predicted half-maximal inhibitory concentration values for axitinib, sorafenib, savolitinib, foretinib, cediranib, alpelisib, buparlisib, afuresertib, and ipatasertib, respectively, between the high- and low-ARHGAP22 expression groups. Lower predicted half-maximal inhibitory concentration values indicate greater predicted drug sensitivity. Please click here to view a larger version of this figure.
DATA AVAILABILITY:
The transcriptomic and clinical data analyzed in this study were obtained from the publicly available The Cancer Genome Atlas Kidney Renal Clear Cell Carcinoma (TCGA-KIRC) project (https://portal.gdc.cancer.gov/). External expression and survival validation data were obtained from the Gene Expression Omnibus dataset GSE167573. Protein-expression data were retrieved from the Human Protein Atlas (https://www.proteinatlas.org/). Pan-cancer expression data were analyzed using TIMER2.0, and external validation was performed through the BEST platform. Drug-sensitivity reference data were obtained from the Genomics of Drug Sensitivity in Cancer 2 dataset, and gene sets used for enrichment analysis were obtained from the Molecular Signatures Database. The original datasets are publicly accessible through the corresponding repositories and platforms. The R scripts used for data processing, statistical analysis, and visualization are provided as Supplementary File 1. Processed results are provided as Supplementary Table 1, containing the complete differential expression analysis results; Supplementary Table 2, containing the Gene Ontology enrichment results; and Supplementary Table 3, containing the Kyoto Encyclopedia of Genes and Genomes pathway enrichment results.
Supplementary Table 1: Complete differential expression analysis results. This file contains the complete list of differentially expressed genes identified between the high- and low-ARHGAP22 expression groups, including gene identifiers, group expression values, log2 fold changes, P values, false discovery rate-adjusted P values, and regulation direction. Please click here to download this file.
Supplementary Table 2: Gene Ontology enrichment analysis results. This file contains the complete Gene Ontology enrichment results for ARHGAP22-associated differentially expressed genes, including biological process, cellular component, and molecular function categories, together with enrichment statistics, P values, adjusted P values, gene counts, and associated gene identifiers. Please click here to download this file.
Supplementary Table 3: Kyoto Encyclopedia of Genes and Genomes pathway enrichment analysis results. This file contains the complete Kyoto Encyclopedia of Genes and Genomes pathway enrichment results for ARHGAP22-associated differentially expressed genes, including pathway identifiers and names, enrichment statistics, P values, adjusted P values, q values, gene counts, and associated gene identifiers. Please click here to download this file.
Supplementary File 1: R scripts for data processing, statistical analysis, and visualization. This file contains the R scripts used for data preprocessing, expression analysis, survival analysis, clinicopathological association analysis, co-expression analysis, differential expression analysis, functional enrichment analysis, immune infiltration analysis, drug sensitivity prediction, and figure generation. Please click here to download this file.
Discussion
Renal cell carcinoma (RCC) is one of the most common malignancies of the urinary system, and clear cell renal cell carcinoma (ccRCC) is the predominant histological subtype and a major contributor to RCC-related mortality. The incidence of RCC has increased overall in recent years, with notable geographic variation. Established risk factors include smoking, obesity, hypertension, and chronic kidney disease3˒4. Despite advances in diagnosis and treatment, ccRCC remains clinically heterogeneous; some patients present with advanced or metastatic disease, and postoperative recurrence and distant metastasis remain common2˒5˒26. The identification of molecular biomarkers associated with tumor behavior and prognosis, therefore, remains an important objective in ccRCC research. The present analysis showed that ARHGAP22 was upregulated in ccRCC and was associated with poorer overall survival, adverse clinicopathological features, immune-related transcriptomic changes, an immunosuppressive tumor microenvironment profile, and differences in computationally predicted sensitivity to targeted agents. These findings support the potential value of ARHGAP22 as a candidate prognostic and immune-related biomarker, although clinical utility and causality have not been established.
ARHGAP22 encodes a Rho GTPase-activating protein involved in cytoskeletal regulation and cell motility. The protein contains a pleckstrin homology domain, a RhoGAP domain, and a C-terminal coiled-coil region and can interact with 14-3-3 proteins, suggesting a role in growth factor-regulated cell migration22. As a FilGAP-related protein, ARHGAP22 participates in antagonistic regulation of the RhoA–Rac1 axis and in the control of cell-migration modes21˒27. ARHGAP22 is primarily localized to endosomes and can be transported to membrane ruffles or the plasma membrane, where it inhibits Rac-dependent lamellipodia formation and cell spreading; its subcellular localization is closely related to RacGAP activity20˒23. Tumor-related associations have also been reported. In ccRCC, ARHGAP22 has been identified as a candidate molecule in bromodomain-containing protein 4 inhibition-related transcriptional analyses and has been associated with poorer overall survival28. Members of the ARHGAP family have also been linked to tumor-promoting immune infiltration and disease progression in bladder cancer25, altered expression and exon variation in acute myeloid leukemia24, and differential response to bevacizumab in metastatic colorectal cancer29.
The present findings were consistent with these observations. ARHGAP22 expression increased with advancing T, N, and M classification, histological grade, and clinical stage, and higher expression was associated with shorter overall survival. Rac signaling has previously been shown to promote ccRCC growth and angiogenic switching16, whereas the Rho GTPase/Rho-associated coiled-coil-containing protein kinase pathway has been associated with malignant behavior in ccRCC17. The observed upregulation of ARHGAP22 may therefore reflect molecular changes associated with aggressive tumor phenotypes. Co-expression and differential expression analyses further showed that ARHGAP22 was associated with a broad transcriptional network. Positive correlations were observed with genes including FMNL1, CARD9, and TRPM2, whereas negative correlations were observed with genes including BSND and FOXI1. Gene Ontology, Kyoto Encyclopedia of Genes and Genomes, and Gene Set Enrichment Analysis results showed enrichment in leukocyte-mediated immunity, chemotaxis, cytokine production, lymphocyte differentiation and proliferation, cytokine–receptor interactions, and chemokine signaling. Chemokine networks contribute to immune-cell recruitment, tumor growth, and metastasis in RCC30, while immune-related pathway enrichment has been associated with poor prognosis and an altered tumor microenvironment in ccRCC31. Clear cell renal cell carcinoma also exhibits distinct immune transcriptional signatures associated with clinical outcome and immune microenvironment complexity32. Similar relationships between aberrant gene expression, immune-pathway enrichment, poor prognosis, and complex co-expression patterns have been reported in other malignancies33.
ARHGAP22 expression was also associated with differences in the tumor immune microenvironment. The high-expression group showed higher estimated fractions of regulatory T cells and M2 macrophages and lower estimated fractions of naïve B cells, resting mast cells, and activated dendritic cells after false discovery rate correction. Positive associations were also observed between ARHGAP22 expression and several immune-checkpoint molecules, together with higher ImmuneScore, StromalScore, and ESTIMATEScore values. Clear cell renal cell carcinoma is characterized by substantial immune infiltration, but this feature does not necessarily indicate an effective antitumor response34. Dysfunctional immune-cell states and immunosuppressive features may limit the effectiveness of immune-checkpoint blockade35. Regulatory T cells and M2 macrophages have been associated with immunosuppression, tumor progression, and poor prognosis in RCC36˒37, whereas increased immune-checkpoint expression may reflect immune-evasion-related processes38. The present results therefore suggest that high ARHGAP22 expression is associated not simply with greater immune infiltration, but with an immune profile containing features commonly linked to immunosuppression. This interpretation remains inferential because the immune-cell estimates were derived from bulk RNA-sequencing data and a single computational deconvolution method.
Differences in computationally predicted drug sensitivity were also observed between the ARHGAP22 expression groups. High-risk molecular features have previously been associated with altered immune infiltration, immune-pathway enrichment, and differential drug response39. Immune-related gene signatures in ccRCC have also been reported to stratify survival and predict differential responses to immunotherapy and targeted therapy40˒41. In the present analysis, the low-ARHGAP22 expression group had lower predicted half-maximal inhibitory concentration values for several targeted agents. These findings indicate an association between ARHGAP22 expression and computationally predicted drug sensitivity but do not demonstrate actual treatment response or clinical benefit. Several methodological choices supported analytical consistency, including sample-quality filtering, use of a uniform median-based expression cutoff, confidence filtering of CIBERSORT results, and false discovery rate correction for multiple comparisons. Nevertheless, predicted drug sensitivity should be interpreted as exploratory, and independent validation using experimentally measured or clinically observed drug-response data is required.
Several limitations should be considered. Although GSE167573 provided external validation of ARHGAP22 expression and its associations with survival, validation in larger, multicenter clinical cohorts remains necessary. The analyses were based largely on retrospective public datasets and bulk RNA-sequencing data; consequently, the cellular source of ARHGAP22 expression could not be distinguished among tumor cells, stromal cells, and infiltrating immune cells. Single-cell RNA sequencing, multiplex immunofluorescence, or spatial transcriptomics would help address this limitation. Immune-cell infiltration, immune-checkpoint expression, and drug sensitivity were inferred computationally and may not directly represent biological function or clinical treatment response. No independent immune-deconvolution method, institutional immunohistochemical cohort, or experimental perturbation analysis was included. In addition, the observed associations do not establish causal relationships among ARHGAP22 expression, co-expressed genes, immune-cell infiltration, and drug response. Mechanistic experiments, prospective clinical validation, and model-performance comparisons will therefore be required before clinical translation. Overall, the workflow provides a reproducible framework for evaluating candidate biomarkers using public molecular datasets, but the biological and clinical relevance of ARHGAP22 requires further independent confirmation.
Disclosures
The authors declare no conflicts of interest.
Acknowledgements
Publicly available data from The Cancer Genome Atlas (TCGA) were used in this study. The TCGA Research Network is acknowledged for generating and providing these resources.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| circlize R package | Version 0.4.16 | CRAN | Used for circos plots and chord diagrams. |
| clusterProfiler R package | Version 4.12.0 | Bioconductor | Used for GO, KEGG and GSEA enrichment analyses. |
| ComplexHeatmap R package | Version 2.20.0 | Bioconductor | Used for complex heatmap visualization and clinical annotation heatmaps. |
| e1071 R package | Version 1.7.16 | CRAN | Used for support vector regression in CIBERSORT-related analysis. |
| enrichplot R package | Version 1.24.0 | Bioconductor | Used for visualization of functional enrichment results. |
| estimate R package | Version 1.0.13 | R package/source package | Used to calculate stromal, immune and ESTIMATE scores. |
| ggExtra R package | Version 0.10.1 | CRAN | Used for scatter plots with marginal density distributions. |
| ggplot2 R package | Version 3.5.1 | CRAN | Used for general data visualization. |
| ggpubr R package | Version 0.6.0 | CRAN | Used for boxplots, violin plots and statistical comparisons. |
| ggrepel R package | Version 0.9.5 | CRAN | Used for non-overlapping text labels in volcano plots. |
| limma R package | Version 3.60.4 | Bioconductor | Used for expression data preprocessing and differential expression-related analysis. |
| oncoPredict R package | Version 1.2 | CRAN | Used to predict drug sensitivity based on transcriptomic data. |
| org.Hs.eg.db R package | Version 3.19.1 | Bioconductor | Used for gene annotation and conversion between gene symbols and Entrez IDs. |
| pheatmap R package | Version 1.0.12 | CRAN | Used for heatmap visualization. |
| preprocessCore R package | Version 1.68.0 | Bioconductor | Used for quantile normalization in CIBERSORT-related analysis. |
| R software | Version 4.4.0 | R Foundation for Statistical Computing | Used for statistical analysis and visualization. |
| RColorBrewer R package | Version 1.1.3 | CRAN | Used for color palette generation in visualization. |
| regplot R package | Version 1.1 | CRAN | Used for nomogram visualization. |
| reshape2 R package | Version 1.4.4 | CRAN | Used for data reshaping before visualization. |
| rms R package | Version 6.8.1 | CRAN | Used for prognostic model construction, calibration analysis and nomogram-related analysis. |
| scales R package | Version 1.4.0 | CRAN | Used for scale adjustment and color transparency settings. |
| survival R package | Version 3.5.8 | CRAN | Used for Cox regression and Kaplan-Meier survival analysis. |
| survminer R package | Version 0.4.9 | CRAN | Used for visualization of Kaplan-Meier survival curves. |
| timeROC R package | Version 0.4 | CRAN | Used for time-dependent ROC curve analysis. |
References
- Winter TD et al. Using Mendelian randomization to investigate etiologic heterogeneity across renal cell carcinoma subtypes. Int J Epidemiol. 2025;54(6):dyaf177. https://doi.org/10.1093/ije/dyaf177
- Hsieh JJ et al. Renal cell carcinoma. Nat Rev Dis Primers. 2017;3:17009. https://doi.org/10.1038/nrdp.2017.9
- Capitanio U et al. Epidemiology of renal cell carcinoma. Eur Urol. 2019;75(1):74-84.
- Siegel RL, Miller KD, Fuchs HE, Jemal A. Cancer statistics, 2022. CA Cancer J Clin. 2022;72(1):7-33.
- Wiechno P et al. Contemporary treatment of metastatic renal cell carcinoma. Med Oncol. 2018;35(12):156. https://doi.org/10.1007/s12032-018-1217-1
- Chen W et al. Targeting renal cell carcinoma with a HIF-2 antagonist. Nature. 2016;539(7627):112-117.
- Rydzanicz M, Wrzesiński T, Bluyssen HA, Wesoły J. Genomics and epigenomics of clear cell renal cell carcinoma: recent developments and potential applications. Cancer Lett. 2013;341(2):111-126.
- Barata PC, Rini BI. Treatment of renal cell carcinoma: current status and future directions. CA Cancer J Clin. 2017;67(6):507-524.
- Chowdhury N, Drake CG. Kidney cancer: an overview of current therapeutic approaches. Urol Clin North Am. 2020;47(4):419-431.
- Gulati S, Vaishampayan U. Current state of systemic therapies for advanced renal cell carcinoma. Curr Oncol Rep. 2020;22(3):26. https://doi.org/10.1007/s11912-020-0892-1
- Haga RB, Ridley AJ. Rho GTPases: regulation and roles in cancer cell biology. Small GTPases. 2016;7(4):207-221.
- Sahai E, Marshall CJ. RHO-GTPases and cancer. Nat Rev Cancer. 2002;2(2):133-142.
- Bustelo XR. RHO GTPases in cancer: known facts, open questions, and therapeutic challenges. Biochem Soc Trans. 2018;46(3):741-760.
- Crosas-Molist E et al. Rho GTPase signaling in cancer progression and dissemination. Physiol Rev. 2022;102(1):455-510.
- Li H, Peyrollier K, Kilic G, Brakebusch C. Rho GTPases and cancer. BioFactors. 2014;40(2):226-235.
- Goka ET, Chaturvedi P, Lopez DTM, Lippman ME. Rac signaling drives clear cell renal carcinoma tumor growth by priming the tumor microenvironment for an angiogenic switch. Mol Cancer Ther. 2020;19(7):1462-1473.
- Thompson JM, Landman J, Razorenova OV. Targeting the RhoGTPase/ROCK pathway for the treatment of VHL/HIF pathway-driven cancers. Small GTPases. 2020;11(1):32-38.
- Feng J et al. RhoJ promotes the progression of clear cell renal cell carcinoma via .the TNF-α/NF-κB axis. Transl Androl Urol. 2025;14(7):1849-1864.
- Guo K et al. Activation of RHO-GTPase gene pattern correlates with adverse clinical outcome and immune microenvironment in clear cell renal cell carcinoma. Clin Exp Med. 2025;25(1):67. https://doi.org/10.1007/s10238-025-01593-3
- Mori M, Saito K, Ohta Y. ARHGAP22 localizes at endosomes and regulates actin cytoskeleton. PLoS One. 2014;9(6):e100271. https://doi.org/10.1371/journal.pone.0100271
- Nakamura F. FilGAP and its close relatives: a mediator of Rho-Rac antagonism that regulates cell morphology and migration. Biochem J. 2013;453(1):17-25.
- Hu SH et al. The weak complex between RhoGAP protein ARHGAP22 and signal regulatory protein 14-3-3 has 1:2 stoichiometry and a single peptide binding mode. PLoS One. 2012;7(8):e41731. https://doi.org/10.1371/journal.pone.0041731
- Mori M et al. Endosomal localization of RacGAP protein ARHGAP22 regulates its GAP activity in human melanoma cells. Anticancer Res. 2022;42(12):5763-5771.
- El-Masry OS, Alamri AM, Alzahrani F, Alsamman K. ADAMTS14, ARHGAP22, and EPDR1 as potential novel targets in acute myeloid leukaemia. Heliyon. 2022;8(3):e09065. https://doi.org/10.1016/j.heliyon.2022.e09065
- Yang C et al. Transcriptomic analysis identified ARHGAP family as a novel biomarker associated with tumor-promoting immune infiltration and nanomechanical characteristics in bladder cancer. Front Cell Dev Biol. 2021;9:657219. https://doi.org/10.3389/fcell.2021.657219
- Schiavoni V et al. Recent advances in the management of clear cell renal cell carcinoma: novel biomarkers and targeted therapies. Cancers (Basel). 2023;15(12):3207. https://doi.org/10.3390/cancers15123207
- Sanz-Moreno V et al. Rac activation and inactivation control plasticity of tumor cell movement. Cell. 2008;135(3):510-523.
- Sakaguchi T et al. Bromodomain protein BRD4 inhibitor JQ1 regulates potential prognostic molecules in advanced renal cell carcinoma. Oncotarget. 2018;9(33):23003-23017.
- Stránská J et al. Copy number variation and clinical response to chemotherapy and bevacizumab in Czech patients with metastatic colorectal cancer. Klin Onkol. 2024;37(4):277-285.
- Parihar JS, Tunuguntla HS. Role of chemokines in renal cell carcinoma. Rev Urol. 2014;16(3):118-121.
- Chen Z, Wu R, Ma J, Zheng J. C chemokines are prognostic biomarkers correlated with diverse immune cell infiltrations in clear cell renal cell carcinoma. Transl Cancer Res. 2022;11(8):2501-2522.
- Şenbabaoğlu Y et al. Tumor immune microenvironment characterization in clear cell renal cell carcinoma identifies prognostic and immunotherapeutically relevant messenger RNA signatures. Genome Biol. 2016;17(1):231. https://doi.org/10.1186/s13059-016-1092-z
- Song DM et al. LIG1 is a novel marker for bladder cancer prognosis: evidence based on experimental studies, machine learning, and single-cell sequencing. Front Immunol. 2024;15:1419126. https://doi.org/10.3389/fimmu.2024.1419126
- Vuong L, Kotecha RR, Voss MH, Hakimi AA. Tumor microenvironment dynamics in clear-cell renal cell carcinoma. Cancer Discov. 2019;9(10):1349-1357.
- Burgers FH et al. Immunological features of clear-cell renal-cell carcinoma and resistance to immune checkpoint inhibitors. Nat Rev Nephrol. 2025;21(10):687-701.
- Davidsson S et al. Infiltration of M2 macrophages and regulatory T cells plays a role in recurrence of renal cell carcinoma. Eur Urol Open Sci. 2020;20:62-71.
- Zhang X et al. Tumor-associated M2 macrophages in the immune microenvironment influence the progression of renal clear cell carcinoma by regulating M2 macrophage-associated genes. Front Oncol. 2023;13:1157861. https://doi.org/10.3389/fonc.2023.1157861
- Tronik-Le Roux D et al. Comprehensive landscape of immune checkpoints uncovered in clear cell renal cell carcinoma reveals new and emerging therapeutic targets. Cancer Immunol Immunother. 2020;69(7):1237-1252.
- Hong J et al. A zinc metabolism-related gene signature for predicting prognosis and characteristics of breast cancer. Front Immunol. 2023;14:1276280. https://doi.org/10.3389/fimmu.2023.1276280
- Xu W et al. Prognostic immunophenotyping clusters of clear cell renal cell carcinoma defined by the unique tumor immune microenvironment. Front Cell Dev Biol. 2021;9:785410. https://doi.org/10.3389/fcell.2021.785410
- Gu J et al. A novel immune-related gene signature for predicting immunotherapy outcomes and survival in clear cell renal cell carcinoma. Sci Rep. 2023;13(1):18922. https://doi.org/10.1038/s41598-023-45966-8