This protocol describes a rat skin excisional wound model in rats incorporating a moist chamber. The system enables the evaluation of topical liquid formulations, cell suspensions, biomaterials, and other wound therapeutics.
Method Article
A Rat Excisional Wound Model for Investigating Therapeutics in Critical-Size Skin Wounds
In This Article
Summary
Abstract
Skin wounds represent a major global healthcare challenge, creating substantial morbidity and economic burden. Reliable and clinically relevant animal models are essential for investigating mechanisms of tissue repair and evaluating emerging therapeutic strategies. However, conventional rodent excisional wound models are limited by rapid wound contraction due to the panniculus carnosus, which differs significantly from human wound healing. The latter predominantly occurs through granulation tissue formation and re-epithelialization. This study describes a rat excisional wound model designed to limit wound contraction while providing a protected environment for testing sensitive therapeutic interventions. Full-thickness 10-mm dorsal excisional wounds were created in Sprague Dawley rats and stabilized using a nitrile butadiene rubber (NBR) O-ring secured with interrupted sutures. To maintain a moist wound environment, an Eakin cohesive seal and transparent adhesive film were applied to form a chamber suitable for topical administration of cells, biomaterials, or pharmaceutical compounds. Additional protective layers consisting of a foam dressing, adhesive tape, a tubular bandage, and a double-shoulder fixation system were used to prevent the animals from removing the dressing. Wound healing was monitored over 14 days by digital planimetry and histological assessment using hematoxylin and eosin staining. The procedure required approximately 30 min per animal and yielded consistent wound-healing outcomes. The NBR O-ring was used as a splint to limit wound contraction. Healing occurred primarily through granulation tissue formation and re-epithelialization. Dressings remained intact for up to seven days without evidence of infection. Histological analysis demonstrated active tissue repair characterized by epidermal regeneration and inflammatory cell infiltration. This model provides a platform for preclinical evaluation of wound therapeutics and advanced regenerative treatments.
Introduction
Skin wounds, including difficult-to-heal wounds, affect more than 40 million patients worldwide and impose a substantial burden on healthcare systems, with annual costs of $22 billion by 2024. In Europe alone, 4 million patients suffer from difficult-to-heal wounds annually, occupying up to half of available acute admissions1. Despite advances in surgical technique, intra-operative practice, and availability of advanced wound dressings, some wounds are refractory, while complications will ultimately develop. Therefore, it is essential to develop new therapeutic approaches that require an experimental animal model of skin wounds to test a wide range of topical materials.
Among experimental skin wound animal models, skin excision is the most applicable technique to create a wound healing model2. Such a model can help investigate hemorrhage, inflammatory reactions, granulation, re-epithelialization, angiogenesis, and tissue remodelling3. Excisional wounds are created mainly on the dorsum of the animal by surgical removal of a defined skin area. The wound should be of critical size to avoid spontaneous healing. This critical-size excisional wound provides direct access for investigating the topical application of different chemicals, cells, or biomaterials and their involvement in the healing process4,5.
Rodents and human skin share similarities in the cellular and molecular phases of wound healing, including hemostasis, inflammation, proliferation, and remodelling. Rats and mice are the most widely used species in wound models due to their availability, small size, relative ease of genetic manipulation, and ease of handling. Rats provide several practical advantages over mice, including a larger body size and thicker skin, which is composed of more layers of keratinocytes than that of mice. Wounds in mice typically heal within 7 days, whereas in rats, the healing process can be evaluated over approximately 12–14 days6.
A major challenge associated with the use of rodents with loose skin is wound contraction3. Rodents’ skin has a panniculus carnosus layer, which contracts following injury to reduce the exposed area. In contrast, human wounds have a limited capacity to contract and depend on granulation and re-epithelialization for repair7. One approach to overcome the limitations of animal models is to perform physical fixation or splinting of the skin surrounding the wound area8. Titanium wound chambers were among the devices successfully developed to prevent wound contraction9, but had drawbacks including high animal stress due to chamber weight, complex surgical placement, potential for device dislodgement, potential for infection, and high cost. The concept of the splinted wound model was introduced by Galiano et al.10 in 2004 by suturing a rigid silicone ring around the wound edge. This approach markedly reduces wound contraction11, but has several drawbacks and limitations, primarily centred on the potential for soft tissue damage, a high rate of splint displacement, and inconsistent wound healing. Splints (such as rigid silicone rings) can cause excessive pressure on the surrounding skin, leading to ischemia, irritation, and necrosis, especially if applied incorrectly. Silicone splints are frequently mutilated, broken, or dislodged due to animal movement or grooming 8,11. Uneven sutures often create uneven tension around the wound, leading to inconsistent healing. In the model presented here, a Nitrile Butadiene Rubber (NBR) O-ring is sutured onto the edge of the skin wound by placing 8-12 simple interrupted polyamide sutures evenly around the ring. This approach is expected to minimize the aforementioned risks and sufficiently limit wound contraction, allowing the wound to heal through granulation tissue formation and re-epithelialization, similar to the human wound-healing process. This healing mechanism would facilitate the translation of findings from animal models into clinical applications.
The moist wound healing theory was introduced by George D. Winter in 1962 as a concept for wound care product design12. Based on this theory, various wound dressings have been developed over the past decades, such as gauzes, transparent films, foams, and hydrogels13. On the other hand, a moldable hydrocolloid ostomy barrier ring seal was designed and developed in 1974 to prevent and protect against leaks. They can be easily shaped and molded to match the wound border, particularly in stoma care applications. In this model, a cohesive seal is applied to the outside of the wound, and together with sterile, transparent films, it creates a moist chamber that mimics the clinical situation of patients with skin wounds undergoing treatment, promoting wound epithelialization and protecting topical agents (e.g., cells, biomaterials, compounds) from leakage.
Wound dressing is vital for protecting the wound bed from physical trauma and microbial infection. Wound dressing in rats has always been challenging due to their low tolerance for it. Rats frequently remove or destroy dressings by biting and tearing them almost as soon as they recover from anaesthesia. It makes the retention of topical agents such as cells and pharmaceuticals very difficult, and the protection of wounds from external pathogens and contaminants is impossible. This is another challenge to address in the rodent model, especially in studies that require a sterile environment, such as biologics testing, cell-based therapy, and advanced therapeutic medicinal products. In the model presented here, a foam dressing and sticky tape were used to cover the moist chamber. The elasticated tubular bandage, fixation bandage, and micropore surgical tape were then used to apply a double shoulder crossed dressing to prevent rats from removing or damaging the bandages.
The reported model here combines several elements from different protocols and has been developed over several years. The aim was to establish a model of an excisional wound in rats using a moist chamber that is well tolerated by the animal and to facilitate the testing of sensitive topical materials, especially in liquid form.
Protocol
All animal procedures presented below were approved by Linköping Ethical Committee (Dnr 5163-2023), Sweden. The reagents and the equipment used are listed in the Table of Materials.
1. Experimental animals
- Use adult male Sprague Dawley rats aged 8–14 weeks.
- Before the experiment, acclimate the rats for at least 1 week in a 12-h light/dark cycle with a standard diet.
2. Pre-surgical preparation
- Anesthetize the animal using 1.5%–2.5% isoflurane (4.5% for induction) mixed with 1.0–1.5 L/min oxygen. Place the animal in a prone position on a heating pad to keep it warm. Apply ophthalmic lubricant to protect the eyes and administer 0.05 mg/kg Buprenorphine bodyweight diluted in saline subcutaneously on the animal’s back for post-operative pain relief.
NOTE: It is important to have a thin layer of disposable underlay isolation between the animal and the pad.
CAUTION: Isoflurane is a central nervous system depressant and a respiratory irritant. Use a calibrated vaporizer with an active waste gas scavenging system to prevent vapor exposure. - Shave the dorsum area with an electric clipper from the neck base down approximately 10 cm. Thoroughly clean the shaved area twice with chlorhexidine and 70% ethanol, then cover the animal with a fenestrated surgical drape that exposes only the cleaned area.
3. Creation of an excisional wound
- Use suitable sterilized surgical instruments, such as scissors and forceps.
- Draw a 10 mm diameter circle using a template with a surgical permanent marker, approximately 4 cm caudal to the base of the neck.
- Grasp the center of the marked skin with forceps and excise the marked skin tissue with scissors. The depth of the wound should go down to the superficial fascia. This can be identified by releasing the full thickness of the skin and visualizing the semi-transparent fascia that covers the muscle.
- Apply an NBR O-ring to the edge of the skin wound and secure it in position by suturing 8-12 stitches. The aim of the ring fixation is to prevent skin contraction. Ensure that the primary sutures are at the 12 O’clock position, followed by 6 O’clock, 3 O’clock, and then 9 O’clock position. In the case of 8 sutures, stitch each suture in the middle of the space between each two of the primary sutures (Figure 1A).
- Apply cohesive seal outside of the NBR O-ring, using its adhesive properties, to build a moist chamber together with sterile transparent and adhesive film (Figure 1B). At this stage, the wound is splinted with the NBR O-ring, and the application chamber side walls are formed by both the skin edge and the cohesive seal; the floor is formed by the raw wound surface, while the roof is formed by the transparent film.
- Cover the wound with one layer of the film, and afterwards administer the treatment solution (cell solution or compound solution) through the film to the wound surface. The chamber of the described size would easily accommodate 100 µL.
- Cover the injection site with another layer of the film to prevent leakage of the treatment (Figure 1C).
- Cover the film with a soft silicone bandage to protect the film (Figure 1D).
- Apply adhesive tapes (Figure 1E), then elasticated tubular bandage, in a double-shoulder configuration around the rat with fixation bandage and micropore surgical tapes (Figure 1F–H).
- Trim the rats’ claws to prevent the dressing from being ripped off by the rats.
- Administer carprofen (5 mg/kg body weight), diluted in saline, subcutaneously to the animal before disconnecting it from anesthesia.
4. Post-operative procedures
- Keep the animal on the heating pad, covered with a blanket, until awake from anaesthesia. Place animals in separate cages or in a single cage with a divider to prevent the animals from biting each other and removing the dressing.
- Administer carprofen, 5 mg/kg bodyweight diluted in saline, subcutaneously the following morning to manage post-operative pain. The rats must be monitored daily for post-operative pain or weight loss, and an additional dose of analgesia could be administered if necessary.
5. Wound measurements and dressing changes
- Examine each animal daily in the first week after wound surgery. The dressing should be inspected and corrected if the animals have difficulty moving or show discomfort.
- Change dressing on day 7 while the animal is under anaesthesia as described in step 2.1.
- Gently remove the dressing cover from the skin. Photographs of the wound are taken with a ruler for scale. The images were analysed using Fiji/ImageJ software in order to evaluate the wound surface area.
- Perform measurements or other procedures as needed by the investigator.
- Apply a clean dressing as in step 3.8–3.11 and allow the animal to recover as described in step 4.1.
6. Wound collection and euthanization
- Apply anaesthesia as mentioned in point 2.1 on day 14, or otherwise according to the specific experimental plan. Remove the dressing and take photos of the wound sites.
- Remove the dressing and take photos of the wound sites.
- Collect wound skin tissue. Using a scalpel, excise the skin around the wound, including some healthy tissue.
- Place the excision in a 2 mL tube and snap-freeze in liquid nitrogen for later molecular analysis, or store in 4% buffered formaldehyde at room temperature for histology. Alternatively, cut the excision into two pieces to perform both assays.
- After removing wound tissue, euthanize the animal by CO2 inhalation or an alternative method according to the ethical approval.
CAUTION: CO2 causes pain, distress, and rapid acidification of mucous membranes prior to unconsciousness. Using a regulated flow meter to displace chamber air.
7. Histochemical staining: Wound fixation, embedding, and sectioning
- Fix the wound tissue biopsies in 4% formaldehyde solution for 3 h at room temperature, then keep them at 4 °C overnight.
CAUTION: Formaldehyde is toxic, a potent sensitizer, and a known human carcinogen. Handle the solution in a chemical fume hood while wearing personal protective equipment. - Wash the biopsies twice with PBS for 30 min each.
- Change the PBS with ethanol (70%) and store at 4 °C.
- Keep the biopsies for a maximum of 24–48 h before processing to avoid antigen loss, or for 1–2 weeks for simple histological characterisation.
- Wash the biopsies thoroughly with running tap water to remove residual formaldehyde.
- Dehydrate the tissue in ethanol baths in the following order: 70% ethanol for 20 min; 2 changes of 95% ethanol for 20 min each; 2 changes of 100% ethanol for 20 min each.
- Keep the biopsies at 65 °C in the paraffin bath.
- Dispense the melted paraffin into the designated mold, placing the biopsies at the centre, and allow it to cool and solidify. The biopsies should be oriented perpendicular to the mold surface to allow visualization of all skin layers upon sectioning.
- Section the paraffin-embedded tissue block at 5 μm thickness with a microtome and float in a 39 °C water bath containing deionized water.
- Transfer the sections onto the slides and dry them, allowing the tissue to adhere to the slide surface. The slides can be stored at 4 °C for later use or processed immediately for histochemical staining.
8. Hematoxylin and Eosin (HE) staining
- Dewax slides on hot plates at 60 °C for 30 min, then in 3 changes of xylene (or any substitute) for 5 min each, followed by 1 change of PBS for 2 min.
CAUTION: Xylene is toxic and highly flammable. Handle the solution in a fume hood, applying the standard personal protective measures. - Perform rehydration in 100% ethanol, 96% ethanol, then dH2O for 5 min each.
- Apply the hematoxylin stain for 5 min, then wash in running tap water for 5 min.
- Differentiate with 0.3% acid alcohol (0.3% hydrochloric acid in 70% ethanol) for a few dips, then wash with running tap water for 5 min.
- Stain in Eosin Y (0.2%) for 30 s, then wash in running tap water for 5 min.
- Dehydrate in 96% ethanol for 1 min, 100% ethanol for 1 min.
- Apply a few drops of mounting medium, then place the coverslip.
- Observe the slides under a light microscope and capture digital photographs.
Results
The rat excisional wound model surgery took approximately 30 min per animal when performed efficiently. The different steps of model creation, O-ring fixation, and dressing are shown in Figure 1.
Figure 2 shows the wound-healing progress on days 7 and 14. The wound radius was measured in mm, and the surface area was calculated with the formula (area = πr2) where r = 5 mm on day 0. Wound closure progression was represented as a percentage of the non-covered area to the induced wound area on day 14. Using Fiji/ImageJ software, a digital image of the wound area was analysed, with the scale calibrated to 10 mm using a ruler included in the image (Figure 2D). Once the wound area had been outlined and measured, the area was presented in mm2. The remaining wound area on day 14 (29.4% ± 10.1%; n = 7) is presented in Figure 3.
HE staining of the skin wound on day 14 is presented in Figure 4. The sections showed that biopsies followed the natural healing of skin wounds, from the periphery to the centre. Wound healing remained incomplete, with the centre devoid of the normal classical multilamellar arrangement with a thin epidermal layer. The dermis showed abundant inflammatory cell infiltration, which is important for the process of physiological healing. Overall, the model was well tolerated by the animals, with hindrance of skin contraction and incomplete but physiological healing.
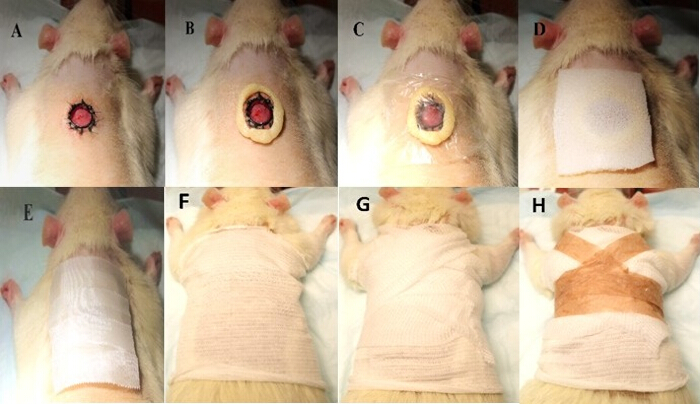
Figure 1: Excisional wound creation and dressing procedure. (A) Excisional wound created on the dorsal surface of the rat, with an O-ring sutured around the wound margin. (B) Moldable hydrocolloid barrier ring applied around the O-ring. (C) Two layers of transparent adhesive film dressing applied over the hydrocolloid barrier ring. (D) Foam dressing placed over the transparent adhesive film dressing. (E) Elastic adhesive tape applied to secure the dressing. (F–H) A tubular retention bandage applied around the rat, followed by a fixation bandage and surgical tape arranged in a double-shoulder configuration to secure the dressing. Please click here to view a larger version of this figure.
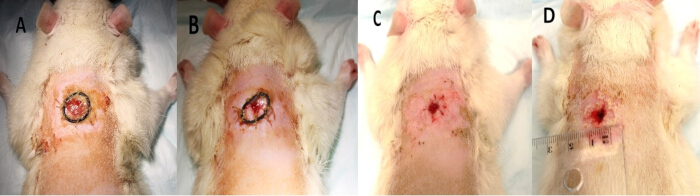
Figure 2: Representative images of wound healing. (A) Representative wound image obtained on day 7. (B–D) Representative wound images obtained on day 14, showing the wound with the O-ring in place (B) and after removal of the O-ring (C,D). Please click here to view a larger version of this figure.
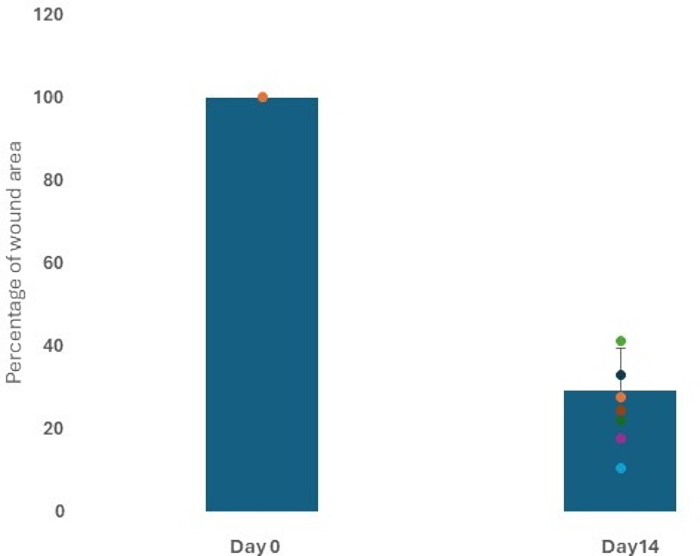
Figure 3: Quantification of wound area at day 14. Percentage of the remaining wound area at day 14, demonstrating wound size reduction. Data are presented as the mean ± standard deviation (SD) (n = 7). Please click here to view a larger version of this figure.
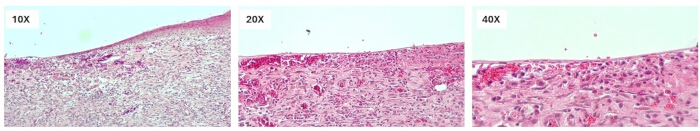
Figure 4: Histological evaluation of wound healing at day 14. Representative hematoxylin and eosin (HE)-stained sections of wound tissue at 10×, 20×, and 40× magnification. The wound center exhibited incomplete re-epithelialization, whereas the wound margins showed physiological epidermal healing. The dermis contained abundant inflammatory cells consistent with the normal wound healing response. Please click here to view a larger version of this figure.
Discussion
Difficult-to-heal skin wounds are wounds that do not progress through the normal stages of healing within the expected timeframe and can be a consequence of surgical procedures, trauma, and allergic reactions, in addition to being secondary to many other health issues, including vascular insufficiency, diabetes, and obesity14. Despite the availability of several management modalities, many patients fail to heal properly. The investigation of new treatment avenues, such as cell-based therapies, chemicals, plant extracts, and newly discovered compounds, is crucial for identifying novel management strategies. The model can be applied to a wide range of wound-healing studies. The establishment of a standardized protocol for testing medications, cells, and biological treatments may facilitate preclinical wound-healing research. The excisional wound model and the protocol described here address the main limitations of the rat skin wound model in research: i.e., skin contraction and wound dressing.
Titanium splints are commonly used to reduce wound contraction in murine excisional wound models; their application is not without limitations. The rigidity of the splint alters the mechanical environment of the wound and surrounding tissue, which may affect cellular responses, inflammation, and matrix remodelling. As a result, healing occurs under conditions that differ from those in untreated rodent skin. While limiting contraction improves comparability with human wound closure, the mechanical constraints imposed by the splint may also introduce artifacts that influence the healing process and should be considered when interpreting experimental findings15.
For this purpose, NBR O-rings were used in the model to limit skin contraction and were fixed to the original wound edge. The rings were well tolerated by the animals and fixed in position for the 14 days of the experiment. Although appreciable wound contraction was not qualitatively observed in any animal, tattooing of the wound edge or other quantitative methods would strengthen the assessment of wound contraction in future studies. Thus, tattooing can be considered an optional step in this protocol.
The application of dressings protected wounds from contamination and infection while maintaining treatment at the wound site, which is crucial for skin wound-healing models. However, it is not uncommon for some animals to remove different types of dressings. Rats frequently groom and manipulate the wound area, which can lead to dressing displacement or complete removal despite the use of adhesive films or secondary fixation methods. Loss of dressing coverage can alter the wound environment, affect treatment delivery, and increase variability between animals16. In the model presented here, the dressing remained intact for up to 7 days, without being removed or damaged by the animals. There was no sign of skin wound infection in any of the experimental animals. It is advisable to replace the dressings weekly because the fit becomes tighter as animals grow and gain weight. Care should be taken to balance secure fixation with animal mobility, while ensuring the dressing is not too loose and can be taken off by the animals.
The protocol is flexible and customizable. While we recommend isoflurane inhalation for its rapid recovery and high safety, investigators may alternatively use injectable anaesthesia, such as ketamine/xylazine, if an isoflurane vaporizer is unavailable. Although only male rats were used in this study, the protocol is equally applicable to female rats.
We recommend analgesic administration of buprenorphine in conjunction with carprofen, which enhances pain relief. Buprenorphine alone may also provide adequate post-operative analgesia due to its relatively long duration of action. This drug has minimal effect on immune function, compared to other opioids, which provides an advantage for wound healing in accordance with the inflammatory process17. Nonsteroidal anti-inflammatory drugs, which suppress inflammation and reduce pain, should be avoided when investigating inflammation. Although one wound was created per animal in this study, the investigators could create additional wounds using the same protocol, in accordance with their ethical approval and experimental design. Animal welfare considerations and the principles of the 3Rs should be carefully considered. Investigators must comply with the 3Rs principles (replacement, reduction, and refinement) and respect animal welfare when using animal models. Surgical procedures must align with guidelines and strictly follow the approved animal protocol. In this study, wound healing was assessed by wound area measurements and histological evaluation, with re-epithelialization representing one component of the healing response. The presence of the sutures in relation to the ring fixation may interfere with the local healing. The number of sutures must be consistent across the animals. The evaluation of the wound area should include all the raw areas, including the suturing sites18. This model can be developed to include various underlying conditions associated with skin wounds, such as ischemia, diabetes, and aging. The principal limitations of this study were the absence of a non-splinted control group, the lack of quantitative assessment of wound contraction, and the limited quantitative biological outcome measures beyond wound area assessment and descriptive histology. Various technical challenges and troubleshooting were evident during the development of this model. Proper fitting of the protective vest/dressing is essential for animal welfare and successful wound healing. A loose dressing may be removed by the animal after anaesthesia recovery, whereas an overly tight dressing can restrict movement, impair circulation, or affect respiration. The dressing should allow sufficient space for one finger (or a little finger for smaller rats) between the dressing and the skin. Animals should be monitored daily, and the dressing should be adjusted if signs of discomfort, impaired mobility, or abnormal posture are observed. Post-operative pain management may vary between individual animals due to differences in analgesic sensitivity. Animals should be regularly assessed for pain-related signs, including hunching, reduced activity, decreased appetite, and weight loss. Additional analgesia should be provided when necessary according to institutional guidelines. Consistent fixation of the ring is critical to prevent wound contraction. The 8–12 simple interrupted sutures should be evenly spaced around the ring to distribute tension uniformly and prevent lifting or deformation. Each suture should be secured with a surgeon’s knot to minimize loosening during recovery. Finally, we recommend using rats of the same strain, age, body weight, and sex within a given study to minimize variation. Also, the same experienced researcher can perform all the surgical procedures. To avoid bias, we recommend using double blinding for histological and molecular analyses.
Disclosures
The authors have nothing to disclose.
Acknowledgements
The authors would like to acknowledge the Region Östergötland for funding this research. The authors thank Mr. Anders Delleskog at CBR, Linköping University, for suggestions, support, and assistance in establishing the animal model. The authors also thank Dr. Maria Ntzouni at the Core Facility, Linköping University, for support and guidance in skin tissue embedding, sectioning, and HE staining. Special thanks to Sallam Abdallah at the R&D unit for skin and cultured cells, Linköping University, for skin sample preparation and HE staining.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Buprenorphine | Salfarm Scandinavia | 451790 | Conc. 0.3 mg/mL |
| Carprofen | Zoetis Animal Health | 191380 | Rimadyl 50 mg/mL |
| Eakin seal | Swemed | 2076152 | Thickness 3 mm |
| Embedding station | Leica Biosystems | EG1150 H&C | |
| Eosin | Histolab | 1650 | 0.2% colour solution |
| Ethanol absolute | Solveco | 1015 | Analytical grade |
| Fixation bandage | Swemed | 2048934 | 4cm x 4m PA/viscose |
| Formaldehyde | Histolab | 2176 | 4% in PBS, pH 7.2-7.4 |
| Hair cutter | Swevet | F95000 | Cutting length: 0.5 mm |
| Hemotoxylin | Histolab | 1800 | Harris HTX |
| Histolab-Clear | Histolab | 14250 | Xylene substitute |
| Isoflurane | VM Pharma | 448210 | Attane vet 1000 mg/g |
| Lekotape | Swemed | 2056774 | |
| Mepilex | Swemed | 2059125 | 7.5x8.5cm |
| Mepore film | Swemed | 2057753 | 6x7cm with frame |
| Micropore surgical tape | Swemed | 2063856 | 1.2cm x 9.1m |
| Microtome | Thermo Fisher Scientific | 387861 | Microm HM355S |
| Mounting medium | Histolab | 00840-05 | Pertex |
| O Ring | Ruilogod | B0B1TRQBRT | 11mm inner D 1mm W |
| Suture (ethilon 4-0) | Scandivet | 21274-A | Non-absorb polyamide |
| Tissue dehydration | Leica Biosystems | Leica TP1020 | |
| Tubifast 2-way stretch | Swemed | 2069292 | 7.5cm x 10m PES/PA |
References
- Europe advanced wound care market size & share 2025-2034: market size by product, by application, by end use, regional forecast. Global Market Insights. Available from: https://www.gminsights.com/industry-analysis/europe-advanced-wound-care-market.
- Nauta AC, Gurtner GC, Longaker MT. Adult stem cells in small animal wound healing models. In: Gourdie RG, Myers TA, editors. Wound Regeneration and Repair Methods and Protocols. New York (NY): Humana Press; 2013. p. 81-98.
- Masson-Meyers DS, et al. Experimental models and methods for cutaneous wound healing assessment. Int J Exp Pathol. 2020;101(1-2):21-37.
- Wong VW, et al. Surgical approaches to create murine models of human wound healing. J Biomed Biotechnol. 2011;2011:969618.
- Shahin H, et al. MicroRNA-155 mediates multiple gene regulations pertinent to the role of human adipose-derived mesenchymal stem cells in skin regeneration. Front Bioeng Biotechnol. 2024;12:1328504.
- Ojeh N, et al. The Wound Reporting in Animal and Human Preclinical Studies (WRAHPS) guidelines. Wound Repair Regen. 2024;33(1):e13232.
- Flynn K, et al. Chronic wound healing models. ACS Pharmacol Transl Sci. 2023;6(5):783-801.
- Davidson JM, Yu F, Opalenik SR. Splinting strategies to overcome confounding wound contraction in experimental animal models. Adv Wound Care (New Rochelle). 2013;2(4):142-148.
- Nuutila K, et al. Titanium wound chambers for wound healing research. Wound Repair Regen. 2016;24(6):1097-1102.
- Galiano RD, Michaels J, Dobryansky M, Levine JP, Gurtner GC. Quantitative and reproducible murine model of excisional wound healing. Wound Repair Regen. 2004;12(4):485-492.
- Miller AW, Anderson AR, Suarez-Arnedo A, Segura T. Wound healing splinting devices for faster access and use. JID Innov. 2024;5(2):100332.
- Winter GD. Formation of the scab and the rate of epithelialization of superficial wounds in the skin of young domestic pig. Nature. 1962;193:293-294.
- Laurano R, Boffito M, Ciardelli G, Chiono V. Wound dressing products: a translational investigation from the bench to the market. Eng Regen. 2022;3(2):182-200.
- Rhea L, Dunnwald M. Murine excisional wound healing model and histological morphometric wound analysis. J Vis Exp. 2020;(162):61616.
- Davidson JM, Yu F, Opalenik SR. Splinting strategies to overcome confounding wound contraction in experimental animal models. Adv Wound Care (New Rochelle). 2013;2(4):142-148.
- Bae SH, Bae YC, Nam SB, Choi SJ. A skin fixation method for decreasing the influence of wound contraction on wound healing in a rat model. Arch Plast Surg. 2012;39(5):457-462.
- DeMarco GJ, Nunamaker EA. A review of the effects of pain and analgesia on immune system function and inflammation: relevance for preclinical studies. Comp Med. 2019;69(6):520-534.
- Jorgensen LB, Sorensen JA, Jemec GBE, Yderstraede KB. Methods to assess area and volume of wounds: a systematic review. Int Wound J. 2016;13(4):540-553.