miR-488-3p may serve as a novel non-invasive diagnostic marker for RA. miR-488-3p modulates the biological function of synoviocytes via ROCK1. It exhibited a significant negative correlation with disease severity in RA patients.
Research Article
Serum Expression of Mir-488-3p Serves as a Non-Invasive Diagnostic Biomarker in Patients with Rheumatoid Arthritis
In This Article
Summary
Abstract
The diagnosis of rheumatoid arthritis (RA) remains challenging because of the limitations of existing biomarkers. The purpose of the study was to investigate the potential of miR-488-3p in serum as a biomarker for RA and to reveal its potential mechanism of action. The study included 135 RA patients, 130 osteoarthritis (OA) patients, and 125 healthy controls. miR-488-3p expression levels were examined by RT-qPCR. The mechanism of action was analyzed by functional tests (CCK-8, flow cytometry, ELISA) and target validation experiments (luciferase reporter gene, RIP). Serum miR-488-3p expression levels were significantly lower in RA patients than in osteoarthritis (OA) patients and healthy controls (p < 0.001). ROC curve analysis showed that miR-488-3p had a high diagnostic accuracy in distinguishing RA from healthy controls and OA patients. miR-488-3p negatively correlated with erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP), rheumatoid factor (RF), and DAS28 scores. Functional validation revealed that overexpression of miR-488-3p inhibited the proliferation and inflammatory response of synoviocytes while inducing apoptosis. Mechanistic studies showed that miR-488-3p could directly target Rho-associated coiled-coil containing protein kinase 1 (ROCK1), which mediates its protective effects. Serum miR-488-3p holds promise as a novel non-invasive diagnostic marker for RA and protects synoviocyte from injury.
Introduction
Rheumatoid arthritis (RA) is a common autoimmune disease characterized by synovial inflammation, joint erosion, and destruction1,2. The global prevalence of RA is about 0.5%–1%3, which seriously affects patients' quality of life and ability to work. The disease has an insidious onset, and early symptoms are often atypical and easily misdiagnosed or missed4. As the disease progresses, it can lead to joint deformity, loss of function, and even increase the risk of complications such as cardiovascular disease5 placing a substantial burden on patients, their families, and healthcare systems..
At present, a combination of clinical symptoms, signs, laboratory tests, and imaging evaluation is required for the diagnosis of RA6. Commonly used laboratory indicators include the erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP), which are non-specific markers of systemic inflammation, as well as rheumatoid factor (RF) and anti-cyclic citrullinated peptide (anti-CCP) antibodies, which are important serological biomarkers for RA7,8. However, these traditional biomarkers have limitations: RF can be positive in some healthy people and patients with other autoimmune diseases (false-positive rate of about 5%); anti-CCP, although highly specific (>95%), has limited sensitivity in the early stages of the disease (about 60–70%)4,9, and some patients with RA remain seronegative10. Therefore, it is important to find more sensitive and specific biomarkers for early diagnosis, disease monitoring, and prognosis assessment of RA11.
MicroRNAs (miRNAs) are a group of endogenous non-coding regulatory RNA molecules approximately 22–25 bases in length12,13. It has been found that miRNAs act as key regulator in the development of a variety of diseases, and their aberrant expression is closely related with disease pathogenesis13,14,15, making miRNAs promising biomarkers for disease diagnosis and therapeutic monitoring. In the past few years, the role of miRNAs in RA has received increasing attention16. Studies have shown that multiple miRNAs are associated with dysregulated expression (e.g., miR-146a, miR-155, etc.) in serum, synovial tissues, and peripheral blood mononuclear cells (PBMCs) of RA patients17,18,19. These miRNAs contribute to RA pathogenesis by regulating inflammatory cytokine production, promoting synovial cell proliferation and invasion, and influencing osteoclast differentiation20. Among them, miR-488 is mapped to the human chromosome 1q25.2 region21, and previous studies have confirmed its neuroprotective effects: it plays a regulatory role in the progression of gliomas22 and neuroblastomas23, and notably, miR-488-3p promotes apoptosis of osteoarthritic chondrocytes in osteoarthritis (OA)24. Although OA and RA are different joint diseases, they share common mechanisms in the pathological processes of synovial inflammation and cartilage destruction25. We hypothesized that miR-488-3p may play a role in RA by regulating similar target pathways. However, the specific role and potential mechanisms of miR-488-3p in RA have not been elucidated.
The study investigated the changes in serum miR-488-3p expression levels in RA patients and its relationship with disease activity and clinical indicators, aiming to evaluate its potential value as a non-invasive diagnostic marker for RA. This study provides a novel insight into the early screening and prediction of disease progression in RA, thereby improving the prognosis of patients with RA.
Protocol
The study was approved by the Ethics Committee of Hefei BOE Hospital (Approval no. 2021–1), and written informed consent was obtained from all participants prior to enrollment.
Patients and specimens
This study recruited 135 patients with RA (diagnosed according to the 2010 ACR/EULAR classification criteria) from the Department of Rheumatology and Immunology of Hefei BOE Hospital, 130 patients with OA from the Department of Orthopedics (diagnosed according to the 2018 Chinese Medical Association OA diagnostic criteria), and 125 age- and sex-matched healthy controls from the same hospital's medical examination center. Participants were aged 30–80 years. Healthy controls were confirmed to be free of autoimmune diseases, joint disorders, and acute infections by a comprehensive history review, physical examination, and laboratory tests. Participants were excluded if they had comorbid autoimmune diseases, a history of infection or trauma within the previous 3 months, malignancy, or were pregnant or lactating.
Sampling and preparation
Fasting venous blood was collected from all study subjects. After coagulation at room temperature for 30 min, serum samples were isolated by centrifugation at 1500 × g for 15 min. Serum was stored at -80°C until further analysis.
Detection of clinical and serological markers
To comprehensively evaluate disease status and inflammatory activity, clinical and serological biomarkers were measured using standardized clinical laboratory methods. ESR was measured using the Westergren method to assess nonspecific systemic inflammation. CRP was quantified using an immunoturbidimetric assay (normal reference value: <10 mg/L) to evaluate the acute-phase inflammatory response. RF was measured using an enzyme-linked immunosorbent assay (ELISA) with a normal reference value of ≤20 IU/mL. Anti-CCP antibodies were measured using a second-generation ELISA to provide serological evidence for the diagnosis of RA.
Cell lines and culture
Human fibroblast-like synoviocytes affected by RA (HFLS-RA) cells were grown in Dulbecco's Modified Medium (DMEM) supplemented with 10% fetal bovine serum (FBS) and 1% penicillin-streptomycin. The cells were maintained in an incubator at 37 °C with 5% CO₂, and cells between the third and sixth passages were used for all experiments.
RNA extraction and quantitative real-time RT-PCR
Total RNA was extracted from serum samples using an RNA extraction reagent. Reverse transcription was performed using a miRNA first-strand synthesis kit for miRNAs and a reverse transcription kit for messenger RNA (mRNA) target genes according to the manufacturer's instructions. Quantitative real-time-polymerase chain reaction (RT-qPCR) was performed using a real-time PCR system with a SYBR Green-based PCR master mix. The thermocycle program was set to 95 °C pre-denaturation for 30 s; followed by 40 cycles of amplification (95 °C denaturation for 5 s and 60 °C annealing/extension for 30 s). Each sample was analyzed in triplicate. U6 small nuclear RNA (U6 snRNA) and glyceraldehyde-3-phosphate dehydrogenase (GAPDH) served as endogenous reference genes for miRNA and mRNA normalization, respectively. Primer sequences have been summarized in Supplementary Table 1. The relative expression levels of miR-488-3p and its target genes were calculated using the 2−ΔΔCt method. The changes in mRNA levels of target genes after overexpression or inhibition of miR-488-3p were also analyzed to verify their regulatory relationships.
Cell transfection
HFLS-RA cells were seeded into 6-well plates at a density of 5 × 10⁵ cells/well. The cells were transfected using a liposome-based transfection reagent following the manufacturer’s instructions. The transfection groups included single transfection and co-transfection groups. The single transfection groups were: 1) control—untransfected cells; 2) mimic negative control (NC)—cells transfected with negative control of miR-488-3p mimic; 3) miR-488-3p mimic—cells transfected with miR-488-3p mimic; 4) inhibitor NC—cells transfected with negative control of miR-488-3p inhibitor; 5) miR-488-3p inhibitor—cells transfected with miR-488-3p inhibitor. Co-transfection groups were: 1) miR-488-3p mimic + overexpression-NC (oe-NC) —cells co-transfected with miR-488-3p mimic and negative control of ROCK1 overexpression vectors; 2) miR-488-3p mimic + oe-ROCK1—cells co-transfected with miR-488-3p mimic and ROCK1 overexpression vectors. All transfection sequences have been summarized in Supplmentary Table 1. The overexpression vector of ROCK1 was established by cloning the coding sequence (CDS) region into pcDNA 3.1 plasmid. Transfected cells were available for the following experiments after 48 h of cell transfection.
Cell function assay
Cell proliferation assay (Cell Counting Kit-8 [CCK-8]): Transfected HFLS-RA cells were inoculated into 96-well plates at 5 × 10³ cells/well, with three replicate wells per group. At 0, 24, 48, and 72 h after transfection, 10 µL of CCK-8 solution was added to each well, followed by incubation at 37 °C for 2 h. The absorbance was measured at 450 nm (detection wavelength) and 630 nm (reference wavelength) using a microplate reader. The relative proliferation rate was calculated using 0 h as the baseline.
Apoptosis detection (flow cytometry): Apoptosis was assessed by analyzing with Annexin V-fluorescein isothiocyanate (FITC)/propidium iodide (PI) apoptosis assay. Cells were transfected with the appropriate plasmids and then collected after trypsinization. Apoptosis rate was determined by flow cytometry.
Inflammatory factor assay (Enzyme-Linked Immunosorbent Assay [ELISA]): HFLS-RA cells were seeded into 24-well plates and transfected with the indicated miR-488-3p mimic, miR-488-3p inhibitor, or their corresponding negative controls for 48 h. The concentrations of interleukin-6 (IL-6), tumor necrosis factor-α (TNF-α), and interleukin-1β (IL-1β) in the cell culture supernatants were quantified using ELISA kits.
Target validation
Target prediction: ROCK1 was predicted to be a downstream target of miR-488-3p using the TargetScan database26. The predicted binding sites between miR-488-3p and the ROCK1 3′-untranslated region (3′UTR) were also identified.
Dual-Luciferase Reporter Gene Assay: The wild type or mutant 3′UTR of ROCK1 was cloned into the pGL3 plasmid. The predicted binding and mutant sites are shown in Figure 4. HEK- 293T cells were co-transfected with miR-488-3p mimic or inhibitor with constructed vectors27. Luciferase activity was measured 48 h after transfection with miR-488-3p mimic or inhibitor.
RNA Immunoprecipitation (RIP): HFLS-RA cells were incubated with an anti-Argonaute 2 (Ago2) antibody (RRID: AB_2882071, 1:200 dilution) or an immunoglobulin G (IgG) control antibody (RRID: AB_2819160, 1:5000 dilution), followed by RNA extraction and quantitative PCR (qPCR) for ROCK1 mRNA enrichment according as described above.
Statistical analysis
The study was statistically analyzed using SPSS 23.0 (RRID: SCR_002865) and GraphPad Prism 9.0 (RRID: SCR_002798). Measurement data were expressed as mean ± standard deviation (SD). All experiments were performed with three biological replicates, and each biological replicate was analyzed in triplicate. Raw data have been attached in the supplementary material. Data was evaluated using a normal probability (P-P) plot before parametric statistical tests. The independent samples t-test was used to compare continuous baseline variables (e.g., age, body mass index [BMI], etc.) and the chi-square test was used for categorical variables (e.g., gender, etc.). Gene expression levels were compared using an independent-samples t-test. Changes in cell proliferation at different time points were analyzed using repeated-measures analysis of variance (ANOVA), whereas one-way ANOVA was used to compare apoptosis rates determined by flow cytometry. Correlation analysis was performed using Spearman (for variables not meeting normal distribution) and Pearson (for variables meeting normal distribution). Diagnostic performance was evaluated using receiver operating characteristic (ROC) curve analysis. The optimal cutoff value, sensitivity, and specificity were determined using the maximum Youden index. All statistical tests were two-sided, and p < 0.05 was considered statistically significant.
Results
Basic characteristics of study participants
This study included 125 healthy controls, 130 patients with OA, and 135 patients with RA for systematic analysis (Table 1). There were no significant differences in the baseline characteristics of the three groups in terms of age (p = 0.191), sex ratio (p = 0.203), and BMI (p = 0.562), which ensured the comparability of the study population. In terms of disease characteristics, ESR (82.63 ± 40.32 vs. 18.39 ± 6.38 mm/h, p < 0.001) and CRP levels (56.33 ± 38.07 vs. 10.54 ± 4.98 mg/L, p < 0.001) in the RA group were significantly higher than those in the OA group, reflecting the level of systemic inflammation. Meanwhile, RF, a serological marker associated with RA, was positive in 70.37% (95/135), with a significantly higher serum concentration (144.13 ± 81.05 vs. 5.10 ± 1.37 IU/mL, p < 0.001); and the anti-CCP positivity rate in RA patients was 56.30% (76/135), with a DAS28 score of 4.12 ± 1.36.
Expression characteristics and diagnostic value of miR-488-3p in RA patients
Serum expression levels of miR-488-3p were significantly downregulated in RA patients compared to OA patients and healthy controls (p < 0.0001, Figure 1A). ROC curve analysis showed that miR-488-3p had high diagnostic accuracy in distinguishing RA from OA and healthy controls: in distinguishing RA from healthy controls, it had an AUC value of 0.931 (95% CI: 0.896–0.967), a sensitivity of 96.15% (95% CI: 91.31%–98.35%) and a specificity of 80.95% (95% CI: 73.22%–86.85%, p < 0.001, Figure 1B); and when distinguishing RA from OA patients, the AUC value was 0.800 (95% CI: 0.747–0.854), with a sensitivity of 85.93% (95% CI: 79.06%–90.80%) and a specificity of 66.15% (95% CI: 57.66%–73.72%, p < 0.001, Figure 1C). Multivariable logistic regression analysis identified miR-488-3p as an independent factor associated with the risk of RA (OR = 0.166, 95% CI: 0.097–0.284; Table 2).
Correlation analysis of miR-488-3p with clinical indicators of RA
Serum miR-488-3p expression levels were significantly negatively correlated with key clinical indicators of RA, including ESR, CRP, RF, and DAS28 (all p < 0.001; Table 3). Specifically, miR-488-3p was negatively correlated with ESR (r = −0.718), CRP (r = −0.726), RF (r = −0.805), and DAS28 score (r = −0.836) (Table 3).
Overexpression of miR-488-3p inhibits cell proliferation and inflammatory responses and induces apoptosis in HFLS-RA cells
To investigate the effect of miR-488-3p on HFLS-RA function, we modulated its expression by transfection with mimics and inhibitors. The RT-qPCR analysis confirmed that the expression level of miR-488-3p was significantly higher in the miR-488-3p mimic group compared with the control group (p = 0.0001), while the expression level of miR-488-3p inhibitor group was significantly lower (p = 0.0003, Figure 2A). The CCK-8 assay showed that overexpression of miR-488-3p inhibited cell proliferation, which was significantly lower than that in the control group at 24 h, 48 h, and 72 h (p = 0.0208, p < 0.0001, p = 0.0036), and inhibition of miR-488-3p expression significantly increased cell proliferation (Figure 2B). Flow cytometry showed that overexpression of miR-488-3p significantly promoted apoptosis (p = 0.0033, Figure 2C).
We then performed an ELISA to investigate the effect of miR-488-3p expression upregulation on inflammatory cytokine levels. The results showed that when miR-488-3p was overexpressed, the levels of inflammatory cytokines (IL-6, TNF-α, and IL-1β) were significantly decreased (p < 0.0001, Figure 3A-C), while inhibition of miR-488-3p expression produced the opposite effect. These significant regulatory effects were verified in all three independent biological replicate experiments and negative controls showed no significant changes (p > 0.05).
MiR-488-3p regulates ROCK1 expression of ROCK1 molecules
To elucidate the molecular mechanisms underlying the role of miR-488-3p in RA disease progression, we explored the downstream targets of miR-488-3p. Bioinformatics analyses showed that miR-488-3p was predicted to bind to the 3'UTR region of ROCK1 (Figure 4A). Dual luciferase reporter assay confirmed that luciferase activity was significantly reduced when wild-type ROCK1 3'UTR was co-transfected with miR-488-3p mimics (p < 0.0001), and luciferase activity was significantly upregulated when miR-488-3p expression was inhibited (p < 0.0001); whereas there was no significant change in this regulatory effect after mutation of the binding site (Figure 4B). RIP experiments further verified this regulatory relationship, showing that the expression level of ROCK1 mRNA was significantly elevated in Ago2 antibody-enriched complexes compared to IgG controls (p < 0.0001, Figure 4C).
In addition, in clinical samples, ROCK1 showed an expression pattern opposite to that of miR-488-3p, where significant upregulation of ROCK1 was observed relative to both OA patients and healthy controls (Figure 4D). In HFLS-RA cells, RT-qPCR revealed that overexpression of miR-488-3p resulted in a significant decrease in ROCK1 expression (p = 0.0093), while inhibition of miR-488-3p significantly increased ROCK1 expression (p = 0.0003, Figure 4E).
ROCK1 mediates the regulatory effects of miR-488-3p on HFLS-RA cells
In HFLS-RA cells, the suppression of ROCK1 expression by miR-488-3p overexpression was reversed by the transfection with the ROCK1 overexpression vectors (Figure 5A). Similarly, the inhibitory effect of miR-488-3p overexpression on cell proliferation was attenuated by ROCK1 overexpression (Figure 5B). Furthermore, ROCK1 overexpression also reversed the enhanced apoptosis induced by miR-488-3p (Figure 5C) and restored inflammatory cytokine levels that had been suppressed by miR-488-3p overexpression (Figure 5D).
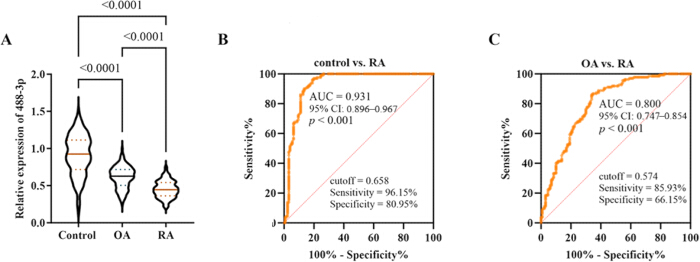
Figure 1. Expression levels and diagnostic performance of miR-488-3p in patients with rheumatoid arthritis (RA), osteoarthritis (OA), and healthy controls. (A) Comparison of relative expression levels of miR-488-3p in RA patients, OA patients, and healthy controls. (B) Receiver operating characteristic (ROC) curve analysis of miR-488-3p for distinguishing RA from healthy controls. (C) ROC curve analysis of miR-488-3p for distinguishing RA from OA patients. AUC, area under the curve; CI, confidence interval. Please click here to view a larger version of this figure.
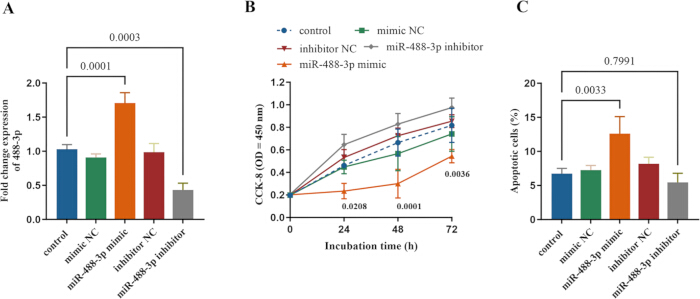
Figure 2. Functional effects of miR-488-3p in HFLS-RA cells. (A) Relative expression of miR-488-3p in transfected HFLS-RA cells determined by quantitative reverse transcription polymerase chain reaction (RT-qPCR). (B) Effects of miR-488-3p overexpression and inhibition on cell proliferation. (C) Effects of miR-488-3p overexpression and inhibition on apoptosis. Data are presented as the mean ± SD. All measurements were performed using three biological replicates, each with three technical replicates. p < 0.05 indicates a statistically significant difference between the indicated groups. Please click here to view a larger version of this figure.
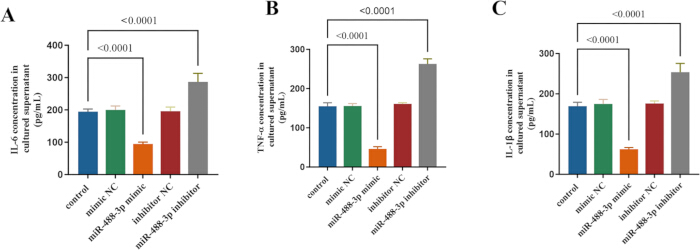
Figure 3. Effect of miR-488-3p on inflammatory cytokine secretion. (A) Interleukin-6 (IL-6). (B) Tumor necrosis factor-α (TNF-α). (C) Interleukin-1β (IL-1β). Cytokine concentrations were measured by enzyme-linked immunosorbent assay (ELISA). Data are presented as the mean ± SD. All measurements were performed using three biological replicates, each with three technical replicates. Please click here to view a larger version of this figure.
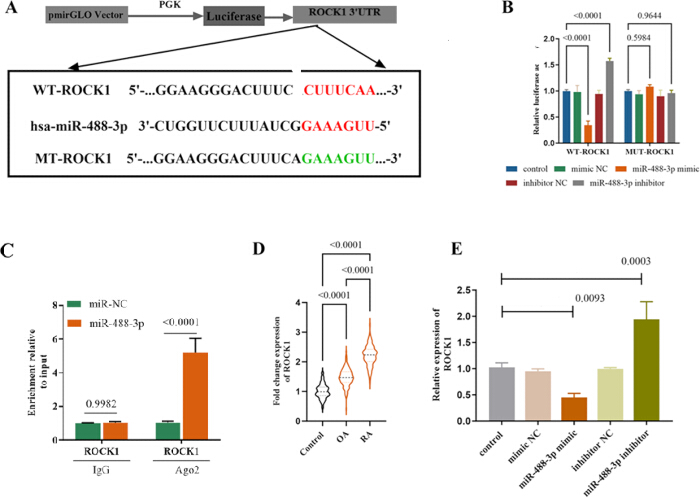
Figure 4. Validation of the molecular mechanism underlying miR-488-3p targeted regulation of ROCK1. (A) Predicted binding site of miR-488-3p within the 3′-untranslated region (3′UTR) of ROCK1. (B) Dual luciferase reporter assay demonstrating the interaction between miR-488-3p and the wild-type or mutant ROCK1 3′UTR. (C) RNA immunoprecipitation (RIP) assay showing ROCK1 messenger RNA (mRNA) enrichment in Argonaute 2 (Ago2) antibody-enriched complexes. (D) Relative ROCK1 expression levels in patients with RA, patients with OA, and healthy controls. (E) Relative ROCK1 expression in transfected HFLS-RA cells determined by quantitative reverse transcription polymerase chain reaction (RT-qPCR). Data are presented as the mean ± SD. All measurements were performed using three biological replicates, each with three technical replicates. Please click here to view a larger version of this figure.
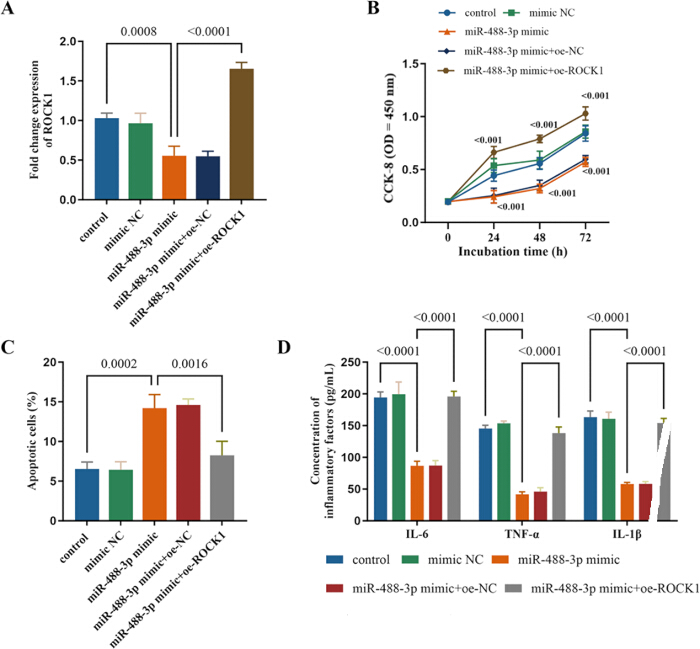
Figure 5. Involvement of ROCK1 in the regulation of HFLS-RA cells by miR-488-3p. (A) Regulation of ROCK1 expression in HFLS-RA cells following cell transfection. (B) Effects of ROCK1 overexpression on cell proliferation under miR-488-3p overexpression. (C) Effects of ROCK1 overexpression on apoptosis under miR-488-3p overexpression. (D) Effects of ROCK1 overexpression on inflammatory cytokine production under miR-488-3p overexpression. Data are presented as the mean ± SD. All measurements were performed using three biological replicates, each with three technical replicates. Please click here to view a larger version of this figure.
| Variable | Control (n = 125) | OA (n = 130) | RA (n = 135) | p-value |
| Age (years) | 55.10 ± 9.30 | 57.21 ± 10.27 | 55.22 ± 11.61 | 0.191 |
| Sex (male/female) | 74/51 | 63/67 | 69/66 | 0.203 |
| BMI (kg/m2) | 22.79 ± 1.73 | 22.98 ± 1.98 | 23.04 ± 2.05 | 0.562 |
| Disease duration (years) | - | 7.96 ± 4.00 | 8.03 ± 3.83 | 0.882 |
| Anti-CCP positive (n/%) | - | - | 76 (56.30) | - |
| ESR (mm/h) | 18.39 ± 6.38 | 82.63 ± 40.32 | <0.001 | |
| CRP (mg/L) | 10.54 ± 4.98 | 56.33 ± 38.07 | <0.001 | |
| RF positive | - | - | 95 (70.37) | |
| RF (IU/mL) | - | 5.10 ± 1.37 | 144.13 ± 81.05 | <0.001 |
| DAS28 | - | - | 4.12 ± 1.36 | - |
Table 1: Baseline characteristics of study participants. The three study groups were comparable with respect to demographic characteristics. RA patients exhibited elevated inflammatory markers and RF levels.
| Variable | OR | 95%CI | p-value |
| Age (years) | 1.411 | 0.822–2.422 | 0.211 |
| Sex (male/female) | 1.209 | 0.707–2.067 | 0.489 |
| BMI (kg/m2) | 1.336 | 0.778–2.295 | 0.293 |
| Disease duration (years) | 1.13 | 0.663–1.929 | 0.653 |
| MiR-483-3p | 0.166 | 0.097–0.284 | <0.001 |
Table 2: Multivariable logistic regression‑derived independent factors associated with progression of osteoarthritis to rheumatoid arthritis. MiR-488-3p was identified to be associated with the risk of RA development in OA patients.
| Items | MiR-488-3p (Rheumatoid arthritis) | p-value |
| Correlation(r) | ||
| ESR (mm/h) | -0.718 | <0.001 |
| CRP (mg/L) | -0.726 | <0.001 |
| RF (IU/mL) | -0.805 | <0.001 |
| DAS28 | -0.836 | <0.001 |
Table 3: Correlations between miR-488-3p and clinicopathological features of RA patients. miR-488-3p was significantly negatively correlated with ESR, CRP, RF, and DAS28 score in patients with RA.
Supplementary Table 1. Sequence information of cell transfection and PCR assay. Primer sequences and transfection reagents used in the study are summarized.Please click here to download this file.
Discussion
As emphasized by Smolen et al1 in the latest guidelines for the diagnosis and treatment of RA, the development of novel biomarkers has significant clinical value. In this study, we confirmed that serum miR-488-3p was significantly downregulated in patients with RA and showed promising diagnostic performance, with relatively satisfactory sensitivity and specificity. Early diagnosis of RA has always been a clinical difficulty, and existing biomarkers are not sufficiently sensitive for the diagnosis of RA, while the significant diagnostic potential of miR-488-3p may fill this gap, especially for the identification of seronegative RA patients. Compared with healthy individuals, RA patients exhibited more pronounced systemic inflammation. While OA patients predominantly have a local degenerative joint disorder, low-grade systemic inflammation is frequently observed. Hence, the discriminating efficiency of miR-488-3p is much higher when compared with healthy individuals than that in comparison with OA patients. The diagnostic performance of miR-488-3p was not directly compared with that of established clinical biomarkers. The patients included in this study were diagnosed according to the current clinical gold standard for RA, which incorporates established biomarkers such as anti-CCP antibodies, RF, ESR, and CRP. Significant differences in these markers were observed between patients with OA and RA (Table 1). Therefore, this cohort was not suitable for directly comparing the diagnostic performance of miR-488-3p with these established biomarkers. Such comparisons require an independent validation cohort.
In addition, miR-488-3p expression levels were found to be significantly negatively correlated with various clinical indicators of RA, including systemic inflammatory markers (ESR, CRP)28, and autoantibodies (RF)6. Of particular clinical significance, miR-488-3p showed a strong negative correlation with the Disease Activity Score (DAS28). DAS28 is a composite index reflecting disease activity based on joint swelling, tenderness, inflammation, and patients’ clinical status. Therefore, these findings suggest that miR-488-3p may serve as a potential biomarker for disease activity in RA. It also supports its regulatory role in RA pathogenesis and may influence disease progression by inhibiting inflammatory signaling pathways or autoimmune responses29.
In functional experiments, we found that miR-488-3p suppressed the proliferation and promoted apoptosis of HFLS-RA cells from RA patients and significantly reduced the production of inflammatory cytokines (IL-6, TNF-α, and IL-1β). HFLS-RA cells play a key role in the pathologic process of RA30, and its aberrant proliferation and invasive growth can lead to synovial hyperplasia and joint destruction, whereas the overproduction of inflammatory factors further exacerbates local and systemic inflammatory responses31. Therefore, the regulation of HFLS-RA function by miR-488-3p may directly inhibit synovial invasion and bone erosion in RA, providing a theoretical basis for the development of novel targeted therapeutic strategies. Previous studies have shown that other miRNAs such as miR-155 can affect RA progression by regulating synoviocyte function19, which further supports our findings.
Mechanistic studies demonstrated that miR-488-3p can directly target ROCK1 and inhibit its expression by binding to its 3'UTR. ROCK1 is a key effector molecule of the Rho/ROCK signaling pathway, which is involved in cytoskeletal reorganization, inflammatory response, and fibrosis32. Previous studies showed that ROCK1 is highly expressed in RA synoviocytes and promotes their migration and invasion33. As expected, overexpression of ROCK1 significantly reversed the effects of miR-488-3p on HFLS-RA cells, indicating its involvement in the regulatory role of miR-488-3p in RA progression.
However, there is still much work to be done in future research. The expression of miR-488-3p in the clinical samples was evaluated using RT-qPCR with U6 as internal reference. Previous studies have reported conflicting findings on the stability of U6, especially in circulating samples, such as serum. Although preliminary experiments have been conducted in the present study to ensure the stability of U6, the potential volatility of U6 is still a limitation, thereby increasing the risk of misdiagnosis. Further validation using more stable internal reference genes is warranted. On the other hand, the clinical evaluation of miR-488-3p was based on a single-center cohort without external validation. The sample size was relatively small, limited to the hospital scale. Moreover, there was a lack of longitudinal follow-up assessing the prognostic value of miR-488-3p. These limitations should be addressed in future studies. Moreover, some studies show that in vivo delivery of miRNAs remains a major challenge for clinical translation34. Future studies could validate the therapeutic potential of miR-488-3p in vivo by constructing conditional knockout mice or using targeted delivery systems such as nanocarriers35.
In conclusion, this study revealed the potential value of miR-488-3p in the diagnosis and potential therapeutic targeting of RA. MiR-488-3p demonstrated high diagnostic performance and inhibited the proliferation and inflammatory responses of HFLS-RA cells while promoting apoptosis. This suggests that it may represent a promising target for the development of novel therapeutic strategies for RA. Future research should focus on 1) validating the diagnostic stability of miR-488-3p in large multicenter cohorts, 2) exploring its synergistic effects with existing therapeutic agents, such as JAK inhibitors or biologics28, and 3) optimizing the miRNA delivery systems to improve their clinical translational feasibility36.
DATA AVAILABILITY:
The raw data supporting the findings of this study are available in the supplementary materials submitted with this manuscript.
Disclosures
The authors declare no conflicts of interest.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Annexin V-FITC Apoptosis Detection Kit | BD Bioscience | 556547 | cell apoptosis |
| anti-Ago2 antibody | Proteintech | 66720-1-Ig | RNA Immunoprecipitation |
| CCK-8 solution | Dojindo | CK04 | cell proliferation |
| Dulbecco's Modified Eagle Medium (DMEM) | Thermo Fisher | 121000146 | cell culture |
| Fetal bovine serum | Thermo Fisher | 10437028 | cell culture |
| Flow cytometer | BD Bioscience | FACSCalibur | cell apoptosis |
| Human anti-CCP antibody ELISA Kit | Cusabio | CSB-E09077h | anti-CCP detection |
| Human RF-IgA ELISA Kit | Feien Biotechnology | EH4270 | RF detection |
| Human rheumatoid arthritis fibroblast-like synoviocytes (HFLS-RA) | Cell Applications | HFLS-RA-200 | in vitro validatio for the function of miR-488-3p |
| IgG control antibody | Abcam | ab205718 | RNA Immunoprecipitation |
| Interleukin-1β (IL-1β)ELISA Kit | R&D Systems | DY201-05 | cellular IL-1β concentration |
| Interleukin-6 (IL-6) ELISA Kit | R&D Systems | D6050B | cellular IL-6 concentration |
| Liposome Transfection Reagent 3000 | Ingenuity Life Technologies | L3000015 | cell transfection |
| Microplate reader | BioTek | ELx808 | ELISA assay |
| Mir-XTM miRNA First-Strand Synthesis Kit | Nihonbao Bioengineering Co., Ltd. | 638313 | reverse transcription |
| Opti-MEM medium | Ingenuity Life Technologies, Inc | 31985070 | cell transfection |
| pcDNA 3.1 | Invitrogen | V790-20 | overexpression of ROCK1 |
| Penicillin-streptomycin | Thermo Fisher | 15140122 | cell culture |
| Phadia 250 Laboratory System | Thermo Fisher | Phadia 250 | blood analysis |
| PrimeScriptTM Reverse Transcription Kit | Nihonbao Bioengineering Co., Ltd. | RR037A | reverse transcription |
| Propidium iodide (PI)/ ribonuclease (RNase) | BD Bioscience | 550825 | cell apoptosis |
| QuantStudio 5 system | Applied Biosystems, Inc. | A28138 | PCR assay |
| RNAiso Plus reagent | Nihonbao Bioengineering Co., Ltd. | 9108 | RNA isolation |
| SYBR Green Premix Ex Taq | Nippon Poh Bio-Engineering Co., Ltd. | RR420A | PCR amplification |
| TargetScan database | TargetScan | N/A | binding sites prediction, (https://www.targetscan.org/) |
| Tina-quant C-Reactive Protein IV | Roche Diagnostics | 7876033190 | CRP detection |
| Tumor necrosis factor-α (TNF-α) ELISA Kit | R&D Systems | DY210-05 | cellular TNF-α concentration |
References
- Smolen JS, et al. Rheumatoid arthritis. Nat Rev Dis Primers. 2018;4:18001.
- Kook HY, et al. Serum miR-214 as a novel biomarker for ankylosing spondylitis. Int J Rheum Dis. 2019;22(7):1196-201.
- Alamanos Y, Voulgari PV, Drosos AA. Incidence and prevalence of rheumatoid arthritis, based on the 1987 American College of Rheumatology criteria: a systematic review. Semin Arthritis Rheum. 2006;36(3):182-8.
- van der Linden MPM, et al. Long-term impact of delay in assessment of patients with early arthritis. Arthritis Rheum. 2010;62(12):3537-46.
- Anderson J, et al. Rheumatoid arthritis disease activity measures: American College of Rheumatology recommendations for use in clinical practice. Arthritis Care Res (Hoboken). 2012;64(5):640-7.
- Aletaha D, et al. 2010 rheumatoid arthritis classification criteria: an American College of Rheumatology/European League Against Rheumatism collaborative initiative. Arthritis Rheum. 2010;62(9):2569-81.
- Yang J, et al. MicroRNA-488: a miRNA with diverse roles and clinical applications in cancer and other human diseases. Biomed Pharmacother. 2023;165:115115.
- Molendijk M, Hazes JMW, Lubberts E. From patients with arthralgia, pre-RA and recently diagnosed RA: what is the current status of understanding RA pathogenesis? RMD Open. 2018;4(1):e000256.
- van Venrooij WJ, van Beers JJBC, Pruijn GJM. Anti-CCP antibodies: the past, the present and the future. Nat Rev Rheumatol. 2011;7(7):391-8.
- Szodoray P, et al. Anti-citrullinated protein/peptide autoantibodies in association with genetic and environmental factors as indicators of disease outcome in rheumatoid arthritis. Autoimmun Rev. 2010;9(3):140-3.
- Filer A, et al. Utility of ultrasound joint counts in the prediction of rheumatoid arthritis in patients with very early synovitis. Ann Rheum Dis. 2011;70(3):500-7.
- Zuo C, Fan P, Yang Y, Hu C. MiR-488-3p facilitates wound healing through CYP1B1-mediated Wnt/β-catenin signaling pathway by targeting MeCP2. J Diabetes Investig. 2024;15(2):145-58.
- Mendell JT, Olson EN. MicroRNAs in stress signaling and human disease. Cell. 2012;148(6):1172-87.
- Cai Z, Poulos RC, Liu J, Zhong Q. Machine learning for multi-omics data integration in cancer. iScience. 2022;25(2):103798.
- Fabian MR, Sonenberg N. The mechanics of miRNA-mediated gene silencing: a look under the hood of miRISC. Nat Struct Mol Biol. 2012;19(6):586-93.
- Duroux-Richard I, et al. Circulating miRNA-125b is a potential biomarker predicting response to rituximab in rheumatoid arthritis. Mediators Inflamm. 2014;2014:342524.
- Zakeri Z, et al. MicroRNA and exosome: key players in rheumatoid arthritis. J Cell Biochem. 2019;120(7):10930-44.
- Pauley KM, et al. Upregulated miR-146a expression in peripheral blood mononuclear cells from rheumatoid arthritis patients. Arthritis Res Ther. 2008;10(4):R101.
- Kurowska-Stolarska M, et al. MicroRNA-155 as a proinflammatory regulator in clinical and experimental arthritis. Proc Natl Acad Sci U S A. 2011;108(27):11193-8.
- Pers YM, et al. miR-155 contributes to the immunoregulatory function of human mesenchymal stem cells. Front Immunol. 2021;12:624024.
- Fu Q, et al. miR-488-3p alleviates neuropathic pain by regulating target gene ROCK1. Acta Neurobiol Exp (Wars). 2023;83(3):271-9.
- Xue W, et al. PVT1 regulates the malignant behaviors of human glioma cells by targeting miR-190a-5p and miR-488-3p. Biochim Biophys Acta Mol Basis Dis. 2018;1864(5 Pt A):1783-94.
- Muiños-Gimeno M, et al. Human microRNAs miR-22, miR-138-2, miR-148a, and miR-488 are associated with panic disorder and regulate several anxiety candidate genes and related pathways. Biol Psychiatry. 2011;69(6):526-33.
- Le TD, Zhang J, Liu L, Li J. Computational methods for identifying miRNA sponge interactions. Brief Bioinform. 2017;18(4):577-90.
- Scanzello CR, Goldring SR. The role of synovitis in osteoarthritis pathogenesis. Bone. 2012;51(2):249-57.
- McGeary SE, et al. The biochemical basis of microRNA targeting efficacy. Science. 2019;366(6472):eaav1741.
- Liu X, et al. Impaired AGO2/miR-185-3p/NRP1 axis promotes colorectal cancer metastasis. Cell Death Dis. 2021;12(4):390.
- Smolen JS, Aletaha D, McInnes IB. Rheumatoid arthritis. Lancet. 2016;388(10055):2023-38.
- O'Connell RM, Rao DS, Baltimore D. microRNA regulation of inflammatory responses. Annu Rev Immunol. 2012;30:295-312.
- Bottini N, Firestein GS. Duality of fibroblast-like synoviocytes in RA: passive responders and imprinted aggressors. Nat Rev Rheumatol. 2013;9(1):24-33.
- Firestein GS, McInnes IB. Immunopathogenesis of rheumatoid arthritis. Immunity. 2017;46(2):183-96.
- Amano M, Nakayama M, Kaibuchi K. Rho-kinase/ROCK: a key regulator of the cytoskeleton and cell polarity. Cytoskeleton (Hoboken). 2010;67(9):545-54.
- Peng H, et al. ROCK1 induces endothelial-to-mesenchymal transition in glomeruli to aggravate albuminuria in diabetic nephropathy. Sci Rep. 2016;6:20304.
- van der Meel R, et al. Smart cancer nanomedicine. Nat Nanotechnol. 2019;14(11):1007-17.
- Yin H, et al. Non-viral vectors for gene-based therapy. Nat Rev Genet. 2014;15(8):541-55.
- Setten RL, Rossi JJ, Han SP. The current state and future directions of RNAi-based therapeutics. Nat Rev Drug Discov. 2019;18(6):421-46.